Pathophysiology
Foundations: The Cell, ABGs & Genetics
No organ fails on its own. Something goes wrong first in the cell, in the fluids around it, or in the genes that built it. This chapter is the floor the rest of the book stands on. You will see how cells cope and how they die. You will see how water and electrolytes stay in balance. You will see how the body guards its pH. And you will see how traits and disorders run in families.
By the end of this chapter you can
- Tell reversible cell injury from irreversible, and name the five cellular adaptations.
- Compare apoptosis with necrosis, and spot the main necrosis types.
- Explain how fluid moves between compartments, plus the four ways edema forms.
- Predict what sodium, potassium, and calcium imbalances do.
- Read a basic ABG. Is it respiratory or metabolic? Is it compensating?
- Use inheritance patterns and a Punnett square to predict risk. Know trisomy 21 and the sex-chromosome disorders.
Section 1Cells: injury, adaptation & death
Every cell in your body is a tiny, hard-working machine. Like any machine, it needs fuel and it needs to dump waste. Two supplies matter most: oxygen and glucose. Cells burn glucose with oxygen inside the mitochondria. That makes ATP, the energy cash that runs every pump, every repair, and every heartbeat. Take the oxygen away and the whole factory starts to fail. That is why the most common cause of cell injury is a lack of oxygen.
When the fuel runs out: hypoxia and ischemia
Hypoxia means too little oxygen reaches the tissue. Ischemia is a worse version of the same problem. Blood flow itself is blocked. So the cell loses oxygen, loses glucose, and cannot wash its waste away. Without ATP the sodium-potassium pump quits. Sodium and water rush in, and the cell swells. That swelling is cellular edema, the first change you can see. Bring oxygen back fast and the cell recovers. That stage is reversible injury. If the insult drags on, mitochondria rupture. Calcium floods in. Enzymes start to digest the cell from the inside. Now the damage is irreversible.
Free radicals and oxidative damage
Injury also comes from unstable molecules called free radicals (reactive oxygen species). Each one carries an unpaired electron. It grabs electrons from whatever is nearby. That damages membranes, proteins, and DNA. This harm is called oxidative stress. It lies under radiation injury, reperfusion damage, and aging. The body fights back with antioxidants and enzymes. When radicals outrun those defenses, the cell is harmed.
Five ways cells adapt
Cells try to adjust to long-term stress before they give up. There are five classic adaptations:
- Atrophy - shrinking. A leg in a cast for weeks loses muscle bulk from disuse.
- Hypertrophy - cells get bigger. The heart wall thickens against high blood pressure. A weightlifter's muscles enlarge.
- Hyperplasia - more cells. The uterus grows a thicker lining each cycle under hormones. The liver regrows after damage.
- Metaplasia - one mature cell type is swapped for a tougher one. In a smoker's airway, delicate ciliated cells turn into flat squamous cells. In the lower esophagus, reflux pushes the change the other way. There the squamous lining is replaced by columnar cells (Barrett esophagus).
- Dysplasia - cells look disordered and abnormal. This is not a normal adaptation. It signals trouble, and it can be a precancerous change, as on an abnormal Pap smear.
Two ways cells die
When adaptation fails, cells die in one of two very different ways. Apoptosis is programmed, tidy cell death. The cell shrinks, packs itself into neat bundles, and is cleared quietly. Nothing spills. It is normal and useful. It carves out fingers in the womb and clears worn-out cells. Necrosis is messy, unplanned death from injury. The cell bursts, spills its enzymes, and provokes inflammation in the tissue around it.
| Feature | Apoptosis | Necrosis |
|---|---|---|
| Trigger | Programmed, a normal body process | Injury, usually ischemia or a toxin |
| Energy | Needs ATP | ATP is used up |
| Membrane | Stays whole | Bursts and spills its contents |
| Inflammation | None | Yes, often strong |
Necrosis comes in patterns worth knowing:
- Coagulative - firm tissue that keeps its outline. This is the classic look after an ischemic infarct in the heart or kidney.
- Liquefactive - tissue melts into liquid. Think of the brain after a stroke, and of bacterial abscesses.
- Caseous - a crumbly center that looks like soft cheese. It is the hallmark of tuberculosis.
Signs of chronic stress inside the cell
Cells under long strain often show accumulations. These are substances that pile up because the cell cannot use them or ship them out. Fat builds up in liver cells, which is called steatosis. So does brown lipofuscin, the wear-and-tear pigment of aging. Cells and dead tissue may also show calcification, which means calcium salts get laid down. When that happens in damaged or dead tissue while the blood calcium is normal, it is dystrophic calcification. When a high blood calcium drives deposits into otherwise normal tissue, it is metastatic. Both are quiet fingerprints of an injury the body has fought for a long time.
The five adaptations are hard to keep straight in words alone. Use the interactive figure below. It puts atrophy, hypertrophy, hyperplasia, metaplasia, and dysplasia side by side.
- Cells need a steady supply of oxygen and glucose to make ATP. Hypoxia and ischemia are the top causes of injury. Ischemia is worse, since it also cuts off glucose and waste removal.
- Injury is reversible at first, with cell swelling from failed pumps. Once mitochondria rupture and calcium floods in, it turns irreversible. Free radicals add oxidative damage.
- The five adaptations are atrophy (shrink), hypertrophy (bigger cells), hyperplasia (more cells), metaplasia (swapped cell type), and dysplasia (disordered, often precancerous).
- Apoptosis is tidy, programmed, and causes no inflammation. Necrosis is messy and sparks inflammation. Its patterns are coagulative (infarct), liquefactive (brain or abscess), and caseous (TB).
- Long cell stress leaves footprints: odd accumulations such as fat and lipofuscin, plus calcification.
Section 2Fluid balance & edema
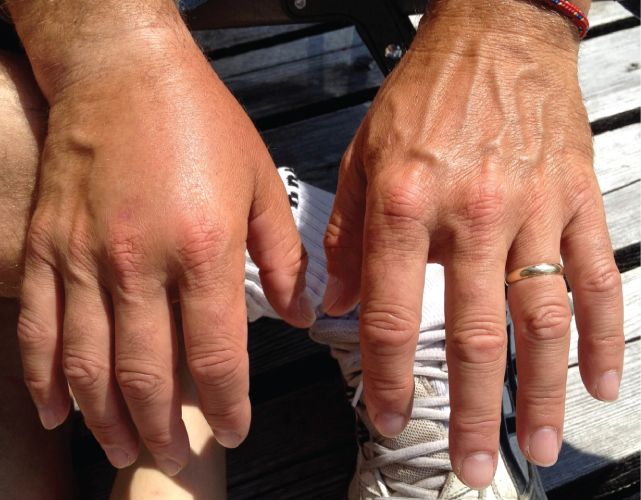
Your body is mostly water. Where that water sits matters as much as how much you have. In a healthy adult, water makes up about 60% of body weight. A handy memory trick is the 60-40-20 rule. About 60% of body weight is total water. About 40% sits inside cells. About 20% sits outside them.
The fluid compartments
Picture two big rooms. The intracellular fluid (ICF) compartment is all the water inside your cells. It holds the most, roughly two-thirds of body water. The extracellular fluid (ECF) compartment is everything outside the cells, the other one-third. The ECF splits again into two parts. Interstitial fluid bathes the spaces between cells. Intravascular fluid is the plasma inside your blood vessels. Fluid shifts between these spaces all day long. Keeping that balance is what keeps cells alive and blood pressure steady.
Osmosis and tonicity
Water follows solute. Osmosis is water moving across a semipermeable membrane. It moves from where solute is low toward where solute is high. It chases the particles it cannot easily follow. Tonicity tells you how a solution changes cell volume. It is one of the most important ideas behind choosing IV fluids.
| Solution | What it does to the cell | Why |
|---|---|---|
| Isotonic (e.g., 0.9% normal saline) | No net change. The cell stays the same. | The solute matches the cell, so water does not shift. |
| Hypotonic (e.g., 0.45% saline) | Cell swells and may burst (lyse). | The outside is more dilute, so water rushes into the cell. |
| Hypertonic (e.g., 3% saline) | Cell shrinks (crenates). | The outside is more concentrated, so water is pulled out. |
Starling forces: the tug-of-war at the capillary
At every capillary, two pressures fight. One pushes fluid out and one pulls it back. We call them the Starling forces. Hydrostatic pressure is the outward push of fluid on the vessel wall. It is basically the pressure of pumped blood, and it drives fluid out into the tissue. Oncotic pressure is the inward pull. It is also called colloid osmotic pressure, and albumin creates most of it. Albumin is a large protein that stays in the blood and draws water back in. Normally fluid leaves at the arterial end and is reabsorbed at the venous end. The lymph system mops up the small amount left over. When that balance tips, fluid piles up in the tissue. That is edema.
The four mechanisms of edema
Edema is not one problem. It is any break in that Starling balance or in the drainage system. Four mechanisms cause it:
- Increased hydrostatic pressure. Too much outward push forces fluid into tissue. This is classic in heart failure, where blood backs up. It also comes from venous obstruction such as a DVT. Holding on to sodium and water belongs here too, since the extra volume is how the pressure rises. Aldosterone or kidney failure often drives that. You see dependent swelling in the ankles and feet.
- Decreased plasma oncotic pressure. Low albumin means a weak inward pull, so fluid stays out. Look for it in cirrhosis, nephrotic syndrome, and severe malnutrition.
- Lymphatic obstruction. Lymph channels normally drain the leftover fluid. If they are blocked, protein-rich fluid backs up as lymphedema. It often follows lymph node removal or radiation in cancer care.
- Leaky capillaries. Inflammation, burns, or sepsis widen the gaps in the capillary wall. Fluid and even protein escape straight into the tissue, so the swelling is local and warm in inflammation, and body-wide in sepsis.
Third spacing
Third spacing is fluid that leaves the vessels and the tissue spaces and gets trapped. It sits where it does no useful work. That can be the belly (ascites), the pleural cavity, or the bowel wall after surgery or in sepsis. This matters because the fluid is lost to the circulation. The patient can look puffy and swollen and still be intravascularly dry. Look for a low blood pressure, a rising heart rate, and poor urine output. You may be giving fluids to someone who appears fluid-overloaded. So judge perfusion, not just how the patient looks. Try the interactive figure below to move fluid between the compartments.
- Total body water is about 60% of weight. Roughly 40% is inside cells and 20% is outside them, as interstitial plus intravascular fluid. That is the 60-40-20 rule.
- Tonicity predicts cell volume. Hypotonic fluid swells cells, hypertonic fluid shrinks them, and isotonic fluid leaves them unchanged.
- Starling forces weigh the outward hydrostatic push against the inward oncotic pull from albumin. Tip that balance and you get edema.
- Edema has four mechanisms: high hydrostatic pressure, low oncotic pressure from low albumin, leaky capillaries, or blocked lymph drainage. Holding on to sodium and water is not a fifth mechanism. It is how hydrostatic pressure rises.
- Third spacing traps fluid where it cannot circulate. So a patient can look swollen yet be short on blood volume. Judge by perfusion and vital signs.
Section 3The electrolytes that matter most
Electrolytes are the tiny charged particles dissolved in your body's water. They make nerves fire, muscles squeeze, and the heart beat on rhythm. Because they carry a charge, small shifts change how excitable your cells are. The body works hard to hold them in a narrow range. When it cannot, the nervous system and the heart usually complain first. Let's walk through the big three, plus a quiet helper.
Sodium: the master of water balance
Sodium is the main electrolyte outside your cells. Normal is roughly 135 to 145 mEq/L. Where sodium goes, water follows. That single rule explains almost every symptom. Sodium sets where water sits, so sodium problems are really water problems. The brain feels them the most, because it is packed inside a rigid skull.
In hyponatremia the sodium is low, so the blood outside the cells is dilute. Water moves into cells by osmosis and they swell. In brain cells that means cerebral edema. So patients get headache, confusion, and lethargy. If the drop is severe or fast, they can seize. In hypernatremia the outside is too salty. Water is pulled out of cells and they shrink. The brain literally dries out. You see thirst, restlessness, irritability, and altered mental status. Notice the pattern. Sodium imbalances are neurologic, because they move water in and out of neurons.
Potassium: the heart's electrolyte
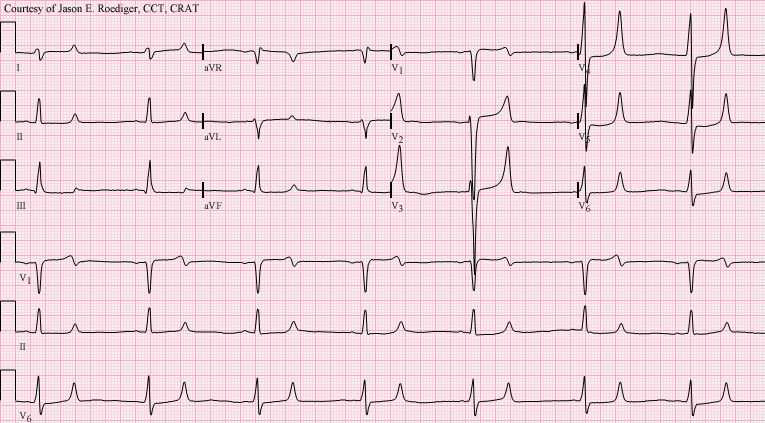
Potassium is the major electrolyte inside cells. Normal is about 3.5 to 5.0 mEq/L. It sets the electrical resting membrane potential. That is what lets heart muscle depolarize and repolarize on cue. This is why potassium is often called the most dangerous electrolyte. Too little and too much can both stop the heart. The danger shows up on the ECG.
In hypokalemia, heart cells turn sluggish to repolarize. That gives flattened T waves, ST depression, and U waves. Patients also get muscle weakness and risk lethal arrhythmias. In hyperkalemia, cells depolarize too easily at first. That gives the classic peaked (tall, tented) T waves. Then the QRS widens. Last comes a sine-wave pattern that can slide into ventricular fibrillation or asystole. Both extremes cause arrhythmias, so potassium sits at the top of the emergency list.
| Feature | Hypokalemia | Hyperkalemia |
|---|---|---|
| Level | < 3.5 mEq/L | > 5.0 mEq/L |
| ECG | Flat T waves, U waves, ST depression | Peaked T waves, wide QRS |
| Muscle | Weakness, cramps, ileus | Weakness, then paralysis |
| Main danger | Fatal arrhythmia | Fatal arrhythmia or arrest |
Calcium: nerves, muscles, and PTH
Calcium steadies nerve and muscle membranes. Total normal is roughly 8.5 to 10.5 mg/dL, so a total below 8.5 mg/dL is hypocalcemia. Parathyroid hormone (PTH) guards it. PTH raises calcium in three ways. It pulls calcium out of bone, saves it in the kidney, and turns on vitamin D. Here the rule flips. Low calcium makes cells more excitable.
In hypocalcemia, membranes turn twitchy and fire too easily. That causes tetany, muscle cramps, and tingling. Two signs help you catch it. Trousseau sign is carpal spasm when a blood-pressure cuff is inflated. Chvostek sign is a facial twitch when you tap the cheek over the facial nerve. In hypercalcemia, membranes are over-stabilized, so things slow down. The old line is "stones, bones, groans, and psychiatric moans". That means kidney stones, bone pain, constipation with belly pain, and lethargy or confusion. Too much PTH or a cancer is often the cause.
Magnesium: the quiet partner
Magnesium tends to travel with potassium and calcium. Normal is about 1.5 to 2.5 mEq/L. Low magnesium makes potassium hard to replace. It also worsens a low calcium. So you often cannot fix a stubborn hypokalemia until you correct the magnesium first. Think of it as the electrolyte that keeps the other two honest.
Which imbalances are true emergencies? The ones that threaten the heart or brain fastest. Severe hyperkalemia and hypokalemia can cause lethal arrhythmias within minutes. Symptomatic hyponatremia with seizures means the brain is swelling. Severe hypocalcemia can cause laryngospasm. Use the interactive figure below to see how each imbalance shifts.
- Sodium controls water, so its imbalances are neurologic. Low sodium swells brain cells, with edema and seizures. High sodium shrinks them, with thirst and confusion. Correct both slowly.
- Potassium is the most dangerous electrolyte, since both hypo- and hyperkalemia cause lethal arrhythmias. Watch the ECG for flat T waves and U waves when low, peaked T waves and a wide QRS when high.
- Calcium reverses the rule. Low calcium raises excitability and causes tetany, with positive Trousseau and Chvostek signs. PTH is the main regulator.
- Magnesium tracks with potassium and calcium. A low magnesium often blocks a successful potassium replacement.
- True emergencies are the ones hitting the heart or brain fastest: severe hyperkalemia, severe hypokalemia, and symptomatic hyponatremia.
Section 4Acid-base balance & the ABG
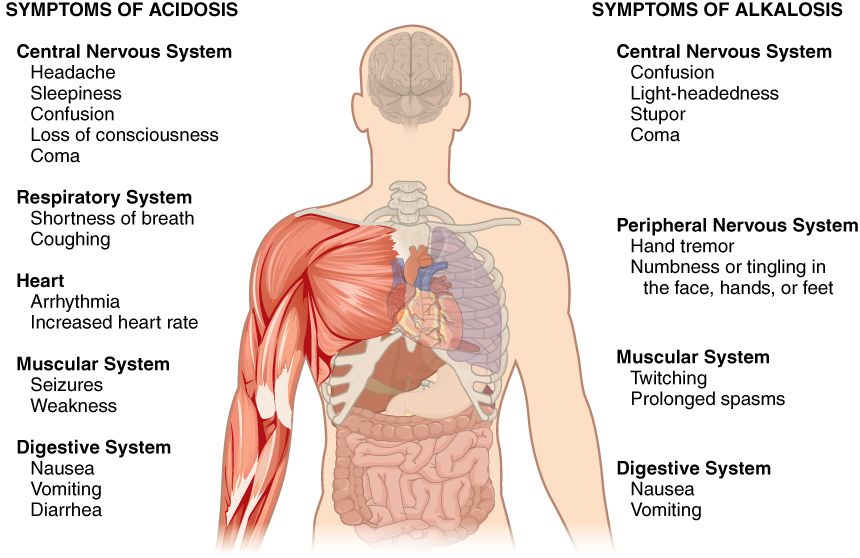
Your blood is fussy about one thing above almost all others. That thing is its pH. Every enzyme, every heartbeat, and every nerve signal depends on a narrow window of 7.35 to 7.45. That sits just barely on the alkaline (basic) side of neutral. Your body guards it closely. Slip below 7.35 and we call it acidosis. Drift above 7.45 and it is alkalosis. Go much past 6.8 or 7.8 in either direction and cells simply stop working. So the body runs two teams whose whole job is defending that pH.
Two defenders: the lungs (fast) and the kidneys (slow)
Picture pH as a seesaw between an acid and a base. The acid side is carbon dioxide (CO2), a waste gas that dissolves into carbonic acid. The base side is bicarbonate (HCO3), the buffer that soaks up extra acid. The lungs control the CO2 side, and they are fast. Breathe harder and you blow off CO2 within minutes, so there is less acid. Breathe slower and CO2 builds up. The kidneys control the bicarbonate side, and they are slow. They take hours to days to hold onto or dump HCO3. Fast lungs, slow kidneys. Remember that and half of ABGs make sense.
The four primary disorders
Every simple acid-base problem is a story about one of those two chemicals going wrong. If the trouble starts with CO2, it is a breathing problem, so it is respiratory. If it starts with HCO3, it is a metabolic or kidney problem, so it is metabolic.
| Disorder | Primary change | Classic cause |
|---|---|---|
| Respiratory acidosis | CO2 high, so acid is kept in | COPD, hypoventilation (slow breathing), opioid overdose |
| Respiratory alkalosis | CO2 low, blown off | Hyperventilation (fast breathing), anxiety, early sepsis |
| Metabolic acidosis | HCO3 low, too much acid | DKA, shock with lactic acid, diarrhea |
| Metabolic alkalosis | HCO3 high | Vomiting, NG suction, diuretics |
Reading an ABG in three steps
You do not need to memorize a chart. Just walk down three numbers in order. The standard normals are pH 7.35-7.45, PaCO2 35-45 mmHg, and HCO3 22-26 mEq/L.
- Look at the pH first. Below 7.35 is acidosis. Above 7.45 is alkalosis. This tells you which way the body has actually gone.
- Look at the CO2 (normal 35-45 mmHg). Above 45 is acidic. Below 35 is alkalotic, because CO2 is an acid. Now compare its direction with the pH. If the two moved opposite ways, the lungs are the culprit. It is respiratory.
- Look at the HCO3 (normal 22-26 mEq/L). Below 22 is acidic. Above 26 is alkalotic. Compare its direction with the pH. If the two moved the same way, the kidneys and metabolism are the culprit. It is metabolic.
Those two checks have a name. It is ROME, for Respiratory Opposite, Metabolic Equal. Use one rule only, so the answer never flips on you. Here is an example. The pH is 7.28, which is low, and the CO2 is 60 mmHg, which is high. The two numbers went opposite ways, so the lungs are to blame. This is respiratory acidosis. You often see that in a COPD patient who is retaining CO2. Now flip it. If the pH is 7.28 and the HCO3 is 14 mEq/L, both numbers fell together. Equal directions point to the metabolic side, as in DKA.
Compensation: the other team pitches in
Here is the elegant part. When one system fails, the other one tries to drag the pH back toward normal. If the lungs cause an acidosis, the kidneys slowly retain bicarbonate to buffer it. If the kidneys or metabolism cause an acidosis, the lungs speed up to blow off CO2. Those deep, sighing Kussmaul respirations in DKA are exactly that rescue in action. The compensating system pushes its own number the same way as the primary problem. So a compensated respiratory acidosis shows a high CO2, which is the problem, plus a high HCO3, which is the kidney rescue.
Watch the pH to judge how far compensation has gone. If the pH is back inside 7.35-7.45, it is fully compensated. If the pH is still abnormal but the second value has clearly shifted to help, it is partially compensated. If only the primary system is off and the other has not budged, it is uncompensated. Remember, compensation nudges pH toward normal but rarely overshoots it. The body does not overcorrect past neutral.
Tie it to real patients and it sticks. The vomiting patient loses stomach acid and swings alkalotic, which is metabolic alkalosis. The panicking patient hyperventilates and blows off CO2, which is respiratory alkalosis. The septic or bleeding patient in shock pours out lactic acid, which is metabolic acidosis. The sedated patient after surgery barely breathes and retains CO2, which is respiratory acidosis. Use the step-by-step ABG interpreter below to practice walking those three numbers yourself.
- Normal blood pH is 7.35-7.45. Below that is acidosis and above it is alkalosis. The lungs defend pH fast with CO2, the kidneys slowly with bicarbonate.
- CO2 problems are respiratory. HCO3 problems are metabolic. High CO2 or low HCO3 means acidosis. Low CO2 or high HCO3 means alkalosis.
- Read an ABG in order: pH, then CO2, then HCO3, and use ROME: Respiratory Opposite, Metabolic Equal. A CO2 moving opposite the pH is respiratory. An HCO3 moving with the pH is metabolic.
- Compensation is the opposite system shifting to pull pH back toward normal. The kidneys retain HCO3 in a respiratory acidosis. The lungs blow off CO2 in DKA. It rarely overshoots normal.
- Classic causes: DKA and shock give metabolic acidosis. COPD and hypoventilation give respiratory acidosis. Vomiting gives metabolic alkalosis. Hyperventilation gives respiratory alkalosis.
Section 5Genes & inheritance
Every cell in your body carries a full instruction manual written in DNA. Think of DNA as a long string of just four chemical letters: A, T, C, and G. A gene is one meaningful sentence in that manual. Each gene tells the cell how to build one protein. Proteins do almost everything. They form structures, carry oxygen, speed up reactions as enzymes, and open and close channels. The flow is simple to remember. DNA is copied (transcribed) into mRNA. Then the mRNA is read (translated) into a protein. When the recipe is spelled correctly, the protein works.
What a mutation actually does
A mutation is a spelling change in a gene. Sometimes it is harmless. Other times it swaps one letter and changes one amino acid. Then the protein folds wrong or stops working. In sickle cell disease, a single letter change turns normal hemoglobin into a sticky version. That warps red cells into a sickle shape. So the whole chain matters. A tiny DNA typo can leave a missing or broken protein, and a broken protein shows up as disease. This is why genetic conditions look so much alike inside one family. Everyone inherits the same misspelled recipe.
Autosomal dominant vs autosomal recessive
You inherit two copies of most genes, one from each parent. These genes live on the autosomes, chromosomes 1 through 22. Whether a condition appears depends on how many broken copies it takes.
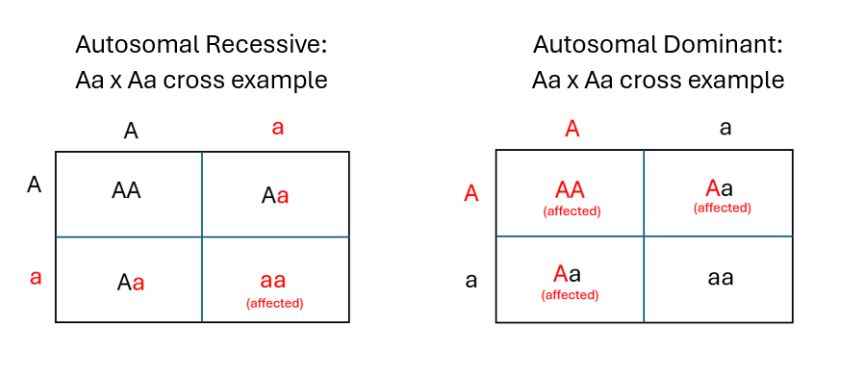
In autosomal dominant inheritance, one faulty copy is enough to show the trait. So it usually appears in every generation, and it affects males and females equally. Huntington disease is the classic example. In autosomal recessive inheritance, you need two faulty copies to be affected. People with just one copy are healthy carriers. They carry the gene silently and can pass it on. Cystic fibrosis and sickle cell disease follow this pattern. That is why they often seem to skip generations, then appear when two carriers have a child.
| Feature | Autosomal dominant | Autosomal recessive |
|---|---|---|
| Copies needed to show | One | Two |
| Family pattern | Usually every generation | Often skips generations |
| Carriers | Rare idea here, since one copy shows | Yes. One copy is a silent carrier. |
| Examples | Huntington disease | Cystic fibrosis, sickle cell |
X-linked recessive: why males are hit harder
Some genes sit on the X chromosome. Females are XX and males are XY. In X-linked recessive conditions like hemophilia, the faulty gene is on the X. A female has a backup X. One healthy copy usually covers for the broken one, so she is typically a carrier. A male has only one X and no second copy to cover for it. So a single faulty gene shows. That is why X-linked recessive disorders affect males far more often. A carrier mother has a 50 percent chance of passing the affected X to each son.
Predicting the odds with a Punnett square
A Punnett square is a simple grid. It lays out each parent's possible gene copies and shows the chance of each combination in their children. Use capital letters for dominant and lowercase for recessive. Take two carriers of a recessive condition, both Aa. The grid gives four boxes: AA, Aa, Aa, and aa. So there is about a 25 percent chance of an affected child (aa). There is a 50 percent chance of a carrier and a 25 percent chance of neither. Each pregnancy is its own independent roll. The odds reset every time. You can explore the patterns and squares in the interactive figure below.
Penetrance and expressivity
Penetrance is whether a gene shows at all. It is the share of people with the gene who actually develop the trait. Expressivity is how strongly it shows. The same gene can look mild in one person and severe in another.
- DNA holds the recipe. A gene builds a protein. A mutation is a spelling change that can break that protein and cause disease.
- Autosomal dominant needs one copy and appears every generation, as in Huntington disease. Autosomal recessive needs two copies and has healthy carriers, as in cystic fibrosis and sickle cell.
- X-linked recessive conditions such as hemophilia mostly affect males, because they have only one X and no backup copy.
- A Punnett square predicts the odds for children. Two recessive carriers have about a 25 percent chance of an affected child in each pregnancy.
- Penetrance is whether the gene shows. Expressivity is how strongly it shows.
Section 6Chromosomal & congenital disorders
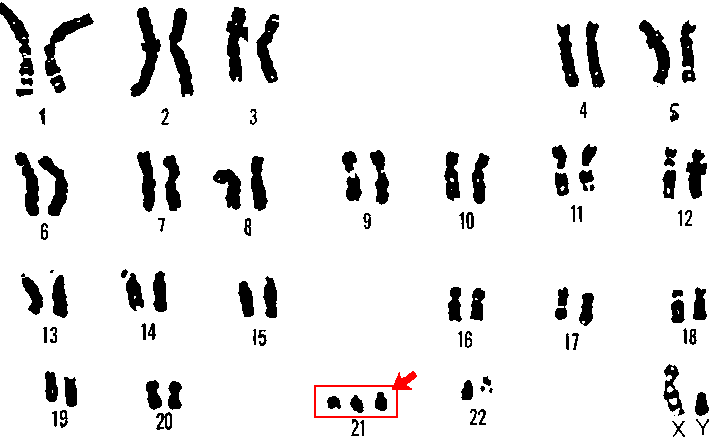
Every cell in your body normally carries 46 chromosomes in 23 pairs. That is 22 pairs of autosomes plus one pair of sex chromosomes, XX in females and XY in males. You inherit exactly half from each parent. This tidy sorting happens during meiosis, the special cell division that makes eggs and sperm. When meiosis works, each gamete ends up with exactly 23 chromosomes. Fertilization then restores the full set of 46. Chromosomal disorders happen when that sorting goes wrong. They also happen when an outside exposure damages a developing embryo. Use the interactive figure below to see how one extra chromosome reshapes the picture.
Nondisjunction: chromosomes that refuse to separate
The most common mistake is nondisjunction. A pair of chromosomes fails to pull apart during meiosis. One gamete ends up with an extra copy, and the other is left short. If that gamete joins in fertilization, the embryo carries the wrong count. We call that state aneuploidy. Three copies of a chromosome instead of two is a trisomy. Having only one copy is a monosomy. Chromosomes are packed with genes. So even one extra or missing chromosome throws off the dose of hundreds of proteins. That is why these disorders affect so many body systems at once. Nondisjunction becomes more likely with advancing maternal age. That is why the risk of trisomies climbs after about age 35.
Trisomy 21 and its cousins
Trisomy 21 (Down syndrome) is the most common surviving autosomal trisomy. It means three copies of chromosome 21. Classic features usually include intellectual disability and a flat facial profile with upslanting palpebral fissures, the slant of the eyelid openings. A single palmar (simian) crease is common, along with hypotonia, which means low muscle tone. That extra genetic material affects many systems. Congenital heart defects are common, often an atrioventricular septal defect. There is also a higher risk of leukemia and of early Alzheimer-type changes. Two rarer and far more severe trisomies are worth knowing. They are trisomy 18 (Edwards syndrome) and trisomy 13 (Patau syndrome). Both usually cause profound impairment and many organ malformations. Most affected infants do not survive past infancy.
When the sex chromosomes are off
Nondisjunction can also hit the sex chromosomes. Turner syndrome (45,X) is a monosomy. It is a female with only one X. It usually shows up as short stature, a webbed neck, and ovarian dysgenesis. That means the ovaries do not work, so there is infertility and no puberty without hormone therapy. Coarctation of the aorta, a narrowed aorta, is also common. Klinefelter syndrome (47,XXY) is a male with an extra X. It often appears around puberty with tall stature, small firm testes, and gynecomastia, which is breast tissue growth. Testosterone is reduced, which leads to infertility. Notice the pattern. An extra sex chromosome tends to be tolerated better than an extra autosome. That is largely because the body naturally silences extra X chromosomes.
| Feature | Turner (45,X) | Klinefelter (47,XXY) |
|---|---|---|
| Karyotype | One X, with a sex chromosome missing | Two X plus one Y |
| Phenotype | Female | Male |
| Stature | Short | Tall |
| Classic clue | Webbed neck, coarctation | Small testes, gynecomastia |
| Fertility | Usually infertile, from ovarian dysgenesis | Usually infertile, from low testosterone |
Teratogens: when the environment is the culprit
Not every congenital disorder is genetic. A teratogen is any agent that disrupts normal fetal development. It can be a drug, an infection, a chemical, or radiation. Timing matters enormously. The embryonic period runs roughly from week 3 to week 8. Organs are first forming then, so it is the window of greatest risk. An exposure during it can cause major structural defects. Later exposure tends to affect growth and function instead. One key cluster to memorize is the TORCH infections. TORCH stands for Toxoplasmosis, Other (including syphilis), Rubella, Cytomegalovirus, and Herpes simplex. These infections in the mother can cross the placenta. They cause malformations, growth restriction, hearing loss, and neurologic damage. Alcohol is one of the most preventable teratogens. Exposure before birth can produce fetal alcohol spectrum disorder, with characteristic facial features, growth deficits, and lifelong problems with thinking and learning. There is no known safe amount.
Multifactorial disorders
Finally, many common conditions are multifactorial. Neural tube defects, cleft lip and palate, and congenital heart disease are examples. They arise from several genes plus environmental influences, not from one single cause.
- Nondisjunction means chromosomes fail to separate in meiosis. It causes trisomies, with an extra copy, and monosomies, with a copy missing.
- Trisomy 21 (Down syndrome) is the most common autosomal trisomy. Trisomy 18 (Edwards) and trisomy 13 (Patau) are rarer and usually fatal in infancy.
- Sex-chromosome disorders include Turner (45,X), a short and infertile female, and Klinefelter (47,XXY), a tall and infertile male.
- Teratogens include the TORCH infections and alcohol. They do the most structural harm during the embryonic period, weeks 3 to 8.
- Multifactorial disorders arise from genetic and environmental causes together.
The chapter in one breath
- Cellular adaptation is the cell's survival plan under stress. It runs in five modes: atrophy (shrink), hypertrophy (enlarge), hyperplasia (multiply), metaplasia (swap to a tougher cell type), and dysplasia (disordered growth that can come before cancer).
- When stress outpaces adaptation you get reversible injury, which is cell swelling from failing Na+/K+ pumps. If hypoxia and ATP loss keep going, it tips into irreversible injury and cell death.
- Apoptosis is tidy, programmed, energy-using single-cell suicide with no inflammation. Necrosis is messy, accidental death. Cells rupture, spill their contents, and trigger inflammation.
- Body water splits into intracellular fluid, about two-thirds, and extracellular fluid. Edema happens when fluid leaks into tissue from high hydrostatic pressure, low albumin and so a weak oncotic pull, leaky capillaries, or blocked lymphatics.
- The must-know electrolytes are sodium (water balance and nerve firing), potassium (the cardiac rhythm ion, dangerous high or low), calcium (bones, clotting, muscle contraction), and magnesium (the quiet cofactor that steadies nerves and heart).
- Acid-base balance is a tug-of-war between the lungs, which are fast and blow off CO2, and the kidneys, which are slow and adjust HCO3-. Together they hold arterial pH in the tight 7.35-7.45 window.
- Read an ABG by checking pH first, acid or alkaline. Then use ROME, for Respiratory Opposite and Metabolic Equal: a CO2 that moved opposite the pH is respiratory, and an HCO3 that moved with the pH is metabolic. Then decide whether the other system is compensating to nudge pH back toward normal.
- Inheritance patterns follow the pedigree: autosomal dominant (one copy shows, every generation), autosomal recessive (needs two copies, carriers hidden), and X-linked recessive (hits males hardest, as in hemophilia).
- Chromosomal disorders come from wrong chromosome numbers, classically trisomy 21 (Down syndrome) from nondisjunction. Many congenital defects such as neural tube defects arise from gene-environment hits during development, for example low folate.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Apoptosis
- Apoptosis is orderly, programmed cell death. The cell shrinks and packages itself neatly for removal without spilling its contents, so no inflammation follows.
- Atrophy
- Atrophy is a drop in the size of cells, and so of the whole tissue or organ. It follows disuse, loss of nerve supply, aging, or reduced blood supply, as when a casted limb shrinks.
- Autosomal recessive
- Autosomal recessive describes an inheritance pattern that needs two copies of a mutated gene, one from each parent, on a non-sex chromosome. Unaffected carriers with one copy can pass it on silently.
- Compensation (acid-base)
- Compensation is the body's attempt to restore normal blood pH using the system that is not primarily broken. The lungs adjust CO₂ for a metabolic problem, and the kidneys adjust bicarbonate for a respiratory problem.
- Dysplasia
- Dysplasia is disordered growth in which cells vary in size, shape, and arrangement. It is not cancer, but it is often a warning change that can come before it.
- Edema
- Edema is a buildup of extra fluid in the interstitial space, the tissue between cells. It shows as visible swelling, and it sometimes pits when you press on it.
- Hyperplasia
- Hyperplasia is a rise in the number of cells in a tissue, driven by more cell division. An example is the endometrium thickening under hormonal stimulation.
- Hypertrophy
- Hypertrophy is a rise in the size of single cells, with no new cells added, which enlarges the organ. An example is heart muscle thickening against high blood pressure.
- Hyponatremia
- Hyponatremia is a blood sodium level below normal, usually under about 135 mEq/L. It often means too much water for the amount of sodium, and it can cause confusion or seizures.
- Hypoxia
- Hypoxia is too little oxygen reaching the tissues. It starves cells of the fuel they need to make energy.
- Ischemia
- Ischemia is reduced blood flow to a tissue. It limits delivery of both oxygen and nutrients while letting wastes build up, and it is a common cause of hypoxia.
- Metaplasia
- Metaplasia is the reversible swap of one mature cell type for another, tougher one under stress. Airway cells changing under long-term cigarette smoke is one example. The swap withstands the stress but loses the original tissue's special job, and it can come before dysplasia.
- Necrosis
- Necrosis is disorderly, unplanned cell death from injury. Cells swell and burst, spill their contents, and trigger inflammation.
- Nondisjunction
- Nondisjunction is the failure of chromosomes to separate properly during cell division. It leaves a cell with an extra or missing chromosome, as in trisomy 21 (Down syndrome).
- Oncotic pressure
- Oncotic pressure is the inward pull that plasma proteins, mainly albumin, exert to keep fluid inside blood vessels. When it drops, fluid leaks out and edema forms.
- Tonicity
- Tonicity is how a solution's solute concentration moves water in or out of a cell. The cell swells in a hypotonic solution, shrinks in a hypertonic one, and stays unchanged in an isotonic one.
DrillFlashcards for this unit
These are the Week 1 cards. It is the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
Immunity, Inflammation & Hypersensitivity
Your immune system is a standing army. You never notice it until it wins too slowly, fights too hard, or turns on your own side. This chapter follows the whole arc. You will meet the invaders. You will see how the innate and adaptive defenses answer them. You will learn what inflammation costs. Then you will see what happens when immunity misfires as allergy, autoimmunity, or immunodeficiency.
By the end of this chapter you can
- Name the main groups of pathogens and how each one causes disease.
- Compare innate with adaptive immunity, and humoral with cell-mediated defense.
- Match each of the five antibody classes to the job it is known for.
- Explain the cardinal signs of inflammation by what causes each one.
- Tell the four hypersensitivity types apart, with a classic example of each.
- Describe how autoimmunity and immunodeficiency (including HIV/AIDS) start.
Section 1The invaders: types of pathogens
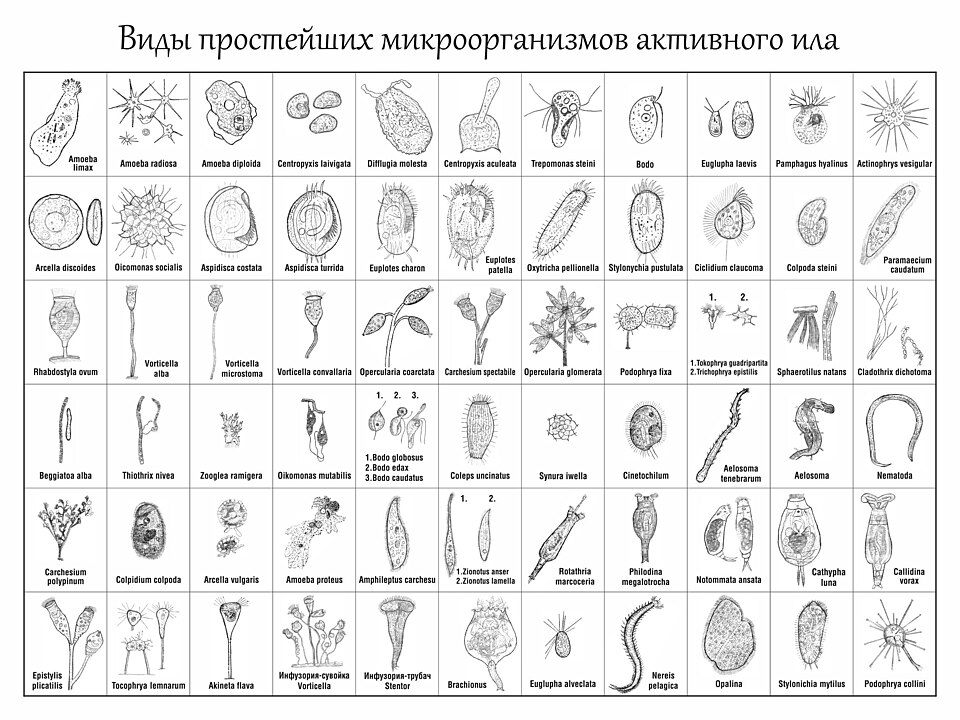
Right now, as you read this, trillions of microbes live on you and in you. That is completely normal. These resident microbes are your normal flora (also called your microbiota). They live on your skin, in your mouth, and most of all in your gut. They earn their keep. They crowd out troublemakers, help digest food, and even make some vitamins, like vitamin K. Most of the time, you and your flora help each other. A pathogen is different. It is any organism that can cause disease. It may invade tissue, release toxins, or set off an immune response that harms you. Some organisms are opportunistic. They are harmless in their usual spot. They turn dangerous when they reach a place they do not belong. Gut bacteria that slip into the blood after surgery are one example. So your first question is what kind of invader this is. The type of organism decides the treatment.
Bacteria: tiny, but they play dirty
Bacteria are single cells with their own tools for living and copying themselves. That is why many can grow on their own, outside our cells. We sort them two ways. First by shape, as round cocci or rod-shaped bacilli. Second, and more useful, by the Gram stain. Gram-positive bacteria have a thick peptidoglycan cell wall and no outer membrane. That thick wall traps and holds the purple stain. Gram-negative bacteria have a thin wall hidden under an extra outer membrane. They lose the purple and pick up a pink counterstain instead. That difference is more than a color. Gram-negative bacteria carry endotoxin (lipopolysaccharide, LPS) in that outer membrane. When the bacteria die and break apart, LPS pours out. It can drive high fever, dangerously low blood pressure, and septic shock. Bacteria harm us in two broad ways. One is invasion, where they spread into tissue and destroy it. The other is releasing toxins. Exotoxins are proteins that some bacteria send out to damage cells at a distance. The toxins behind tetanus and C. difficile colitis work this way. Endotoxin is different. It is part of the gram-negative wall itself.
Viruses: hijackers that cannot live alone
Viruses are not really cells. A virus is genetic material, either DNA or RNA, wrapped in a protein coat. Viruses are obligate intracellular parasites. That means a virus must get inside one of your living cells to do anything at all. It attaches to a host cell, enters, and releases its genes inside. Then it takes over the cell's own ribosomes and enzymes. The cell becomes a factory that turns out new virus copies, and it is often destroyed in the process. Viruses hide inside your cells and borrow your machinery. So antibiotics do nothing against them, and treatment is harder to aim without harming the host.
Fungi, parasites, and a word on prions
Fungi are more complex cells. They include yeasts, such as Candida, and molds. Fungi often turn harmful when the immune system is weak, or when antibiotics wipe out normal flora. Protozoa are single-celled parasites. One example is the Plasmodium that causes malaria. Helminths are the parasitic worms, and they are made of many cells. Prions are the strange outliers. They are misfolded proteins with no DNA or RNA at all. A prion makes other proteins misfold too, which leads to fatal brain disease.
Matching the treatment to the invader
Here is the payoff. Naming the class of organism guides the whole plan. Antibiotics attack features that only bacteria have, such as the cell wall. That is why they are useless against viruses. Giving them anyway breeds antibiotic resistance. It can also set off a C. difficile infection by killing the flora that protect you.
| Pathogen | Key trait | Treatment class |
|---|---|---|
| Bacteria | Own cells; toxins & invasion | Antibiotics |
| Viruses | Take over host cells | Antivirals |
| Fungi | Yeasts & molds | Antifungals |
| Parasites | Protozoa & worms | Antiparasitics |
Look at the main classes of pathogens in the figure below. It lines these families up side by side.
- Normal flora usually protect us. A pathogen is any organism that causes disease, and opportunists turn harmful in the wrong place or when defenses drop.
- Bacteria harm us by invasion and by toxins. Gram-negative endotoxin (LPS) can drive fever and septic shock, and the Gram stain guides the first drug choice.
- Viruses are obligate intracellular parasites that take over host cells to copy themselves. That is why antibiotics do not work on them.
- Fungi, protozoa, and helminths each need their own drug class. Prions are misfolded proteins with no nucleic acid.
- Match the drug to the organism: antibiotic, antiviral, or antifungal. Misusing antibiotics breeds resistance and can cause C. difficile.
Section 2The body’s defenses
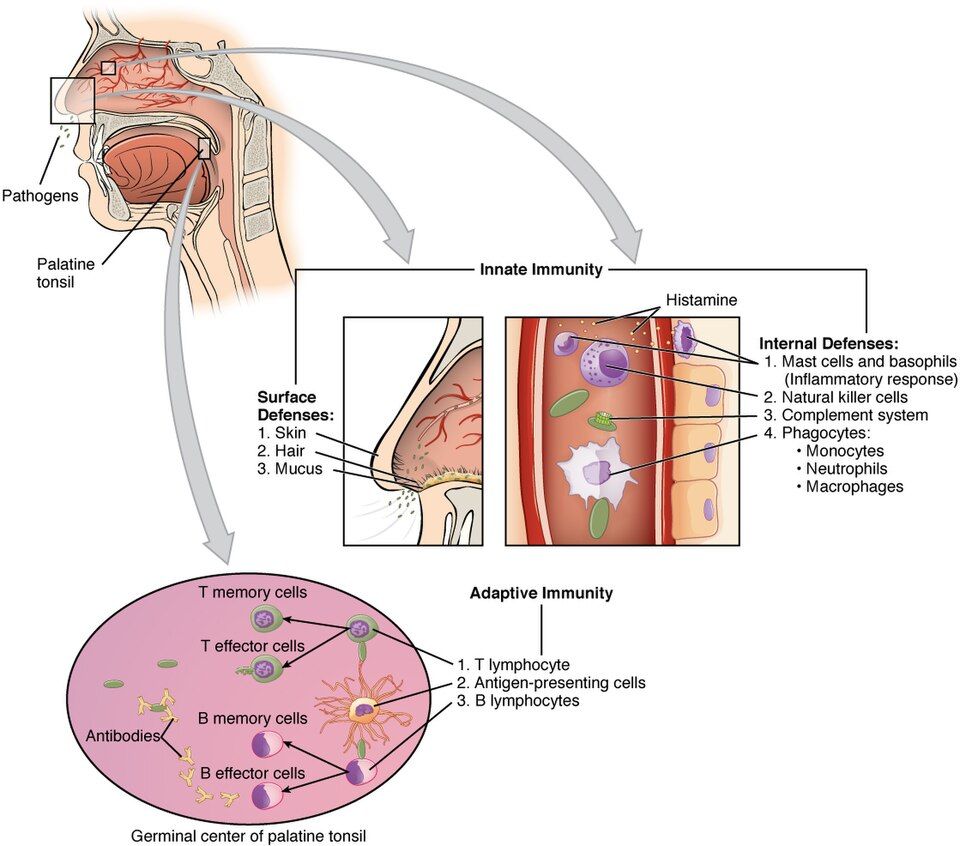
Every second of every day, your body fights off bacteria, viruses, and other invaders. You never notice. It does this with two teams that work together. One is a fast, general-purpose crew called innate immunity. The other is slower but far more exact, and it is called adaptive immunity. How these two teams work is the base for everything else in this chapter.
Innate immunity: fast, but nonspecific
Innate immunity is the defense you are born with. It acts within minutes to hours. But it does not care exactly who the invader is. It treats most threats the same way. Think of the locks, alarms, and guards in a building.
- Physical and chemical barriers come first. Unbroken skin is a wall that invaders cannot cross easily. Mucous membranes line the airways and gut and trap microbes, so cilia and secretions can sweep them out. Stomach acid and lysozyme in tears add a chemical defense. This is why any break in the skin, like an IV site or a pressure injury, is a real infection risk.
- Phagocytes are cells that eat invaders. Neutrophils get there first and fast. They lead the early response and are the main cell in pus. Macrophages arrive a bit later, swallow debris, and clean up. This eating process is called phagocytosis.
- Complement is a chain of plasma proteins. It punches holes in microbes, tags them for phagocytes (opsonization), and turns up inflammation.
- Natural killer (NK) cells destroy your own cells once they turn dangerous. They go after virus-infected cells and some tumor cells.
- Fever is a whole-body innate response. Chemical messengers called pyrogens reset the hypothalamus to a higher temperature. That slows microbial growth and speeds up immune cells. So a fever feels bad, but it is often a sign your defenses are working.
Adaptive immunity: specific, with memory
Adaptive immunity takes longer to start. A first exposure may take days. But it is specific, which means it aims at one invader. It also remembers. It has two branches.
- Humoral immunity is run by B cells. Once activated, B cells become plasma cells. Those cells pump antibodies (immunoglobulins) into the blood and body fluids. Antibodies shut down toxins, clump microbes together, and flag them to be destroyed. This branch is best against invaders outside your cells, such as bacteria in the bloodstream.
- Cell-mediated immunity is run by T cells. It handles threats inside cells, such as viruses, and it handles abnormal cells.
The T-cell coordinators and killers
Two kinds of T cells are worth knowing by name. Helper T cells (CD4) are the coordinators. They release cytokines that switch on B cells, cytotoxic T cells, and macrophages. HIV attacks CD4 cells. So a falling CD4 count leaves the whole system without a leader, and that is why HIV does so much damage. Cytotoxic T cells (CD8) are the killers. They destroy virus-infected and cancerous cells directly.
Active vs passive immunity
Immunity can be earned or borrowed. In active immunity your own body makes the response and builds memory. You can get there by getting sick, or by vaccination, which is a safe preview of the invader. Active immunity is slow to build but lasts a long time. In passive immunity you receive ready-made antibodies from someone else. Protection starts right away, but it is temporary, because you never made memory cells. Antibodies crossing the placenta to the fetus are one example. Antibodies in breast milk are another.
| Feature | Active immunity | Passive immunity |
|---|---|---|
| Source | Your own immune response | Borrowed antibodies |
| Onset | Slow (days to weeks) | Right away |
| Duration | Lasts a long time (memory) | Short (no memory) |
| Examples | Infection, vaccines | Placenta, breast milk, antibody shots |
Primary vs secondary response
The primary response is your body's first meeting with an invader. It is slow. Building up antibodies often takes a week or more, which is why you can feel sick that first time. But the immune system files away memory cells. On a repeat exposure, the secondary (memory) response is faster and stronger. It makes far more antibodies, far more quickly, so you may never feel sick at all. This is exactly why vaccines and booster doses work. They build memory safely, so the real invader meets a fast secondary response. Look at the figure below to see how the innate and adaptive teams fit together.
- Innate immunity is fast but nonspecific. It includes barriers, neutrophils and macrophages, complement, NK cells, and fever. Adaptive immunity is slower but specific, and it remembers.
- Adaptive immunity has two branches. Humoral means B cells make antibodies, best against threats outside cells. Cell-mediated means T cells, best against threats inside cells.
- Helper T cells (CD4) coordinate the response. Cytotoxic T cells (CD8) kill infected and abnormal cells.
- Active immunity comes from infection or a vaccine. You make it yourself and it lasts. Passive immunity comes from the placenta, breast milk, or antibody shots. It is borrowed, immediate, and temporary.
- The secondary (memory) response is faster and stronger than the primary response. That is the whole basis for vaccines and boosters.
Section 3Antibodies (immunoglobulins)
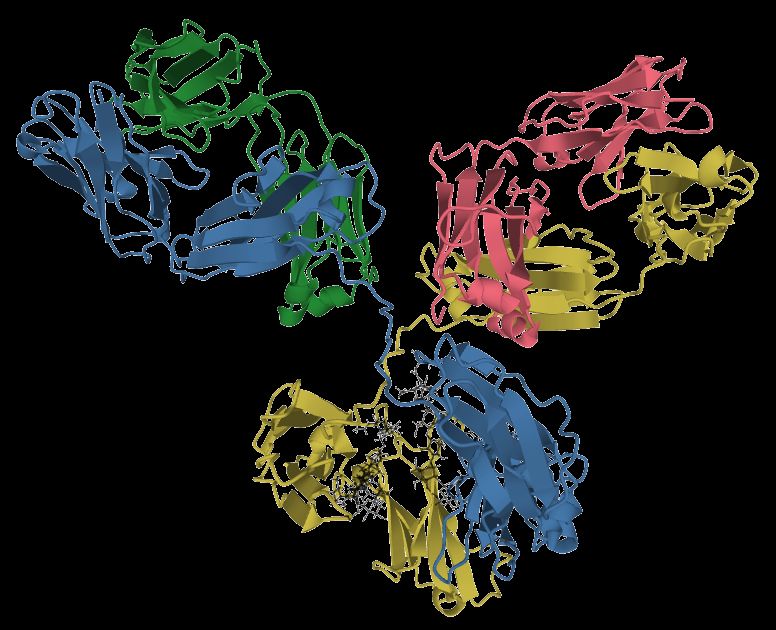
Your immune system faces a huge problem. How do you spot millions of different germs when each one looks a little different? The answer is antibodies, also called immunoglobulins (Ig). Picture a tiny Y-shaped protein tag that your body builds to match one target. The tips of the Y are the variable region. They are shaped to lock onto one antigen, which is a molecular fingerprint on a microbe. The stem of the Y is the constant region. It is the handle that the rest of the immune system grabs.
Antibodies are made by plasma cells. These are mature B lymphocytes that their antigen has switched on. Once an antibody is released, it does three main jobs. First, it tags the invader so phagocytes know to eat it. That tagging is called opsonization. Second, it can neutralize a threat. It coats a virus or a toxin so the threat can no longer attach to your cells. Third, it can activate complement. Complement is a chain of blood proteins that punches holes in bacterial membranes and turns up inflammation. In short: tag, neutralize, and activate.
The five classes and their signature jobs
All antibodies share that Y shape. But the constant-region handle comes in five flavors. Each flavor sends the antibody to a different job and a different place in the body.
- IgG is the most abundant antibody in blood. It is the workhorse of the secondary (memory) response. It is the only class that crosses the placenta. It is very good at opsonization, at neutralizing, and at activating complement.
- IgM is the first to appear in a new infection, and it is the largest antibody. It travels as a pentamer, which means five Y units joined together. Those ten binding arms make it a strong early complement activator.
- IgA guards the mucosal surfaces, the wet linings of the gut, lungs, and airways. It is concentrated in secretions like saliva, tears, and breast milk. That gives a nursing newborn ready-made protection.
- IgE drives allergy and type I hypersensitivity, and it defends against parasites. It binds to mast cells and basophils. When an antigen links those IgE molecules together, the cells release histamine.
- IgD mostly sits on the surface of naive B cells as part of the B-cell receptor. It helps those cells get switched on.
Reading antibody levels: recent versus past infection
IgM and IgG appear on different timelines. So a lab panel can tell you when an exposure happened. When you meet an antigen for the first time, IgM rises first, usually within days. It then fades over a few weeks. IgG rises later and stays high for months to years, which gives lasting immunity. Clinicians use this pattern all the time.
| Feature | IgM elevated | IgG elevated |
|---|---|---|
| What it suggests | Recent or current infection | Past infection or immunity |
| Timing | Shows up first, fades in weeks | Shows up later, stays for years |
| Response type | Primary response | Secondary / memory response |
| Classic example | Acute hepatitis or rubella | An old vaccine or an old exposure |
So IgM positive with IgG negative usually points to a fresh infection. IgG positive with IgM negative usually means the person was infected or vaccinated in the past and is now immune.
Why placenta-crossing IgG protects a newborn
A newborn's immune system is still learning. It cannot make strong antibody responses yet. Because IgG crosses the placenta during pregnancy, the mother loans her baby a whole library of antibodies. This passive immunity shields the infant for roughly the first few months of life, while the baby's own B cells grow up. IgA in breast milk adds a second layer right at the gut lining. The trade-off is that borrowed protection does not last. That is exactly why the infant vaccine schedule starts before it wears off.
The figure below lets you look at the five classes side by side.
- Antibodies (immunoglobulins) are Y-shaped proteins from plasma cells. They tag, neutralize, and activate complement against one specific antigen.
- There are five classes. The hook is GAMED: IgG (most abundant, crosses the placenta), IgA (mucosa and breast milk), IgM (first and largest, a pentamer), IgE (allergy and parasites), IgD (B-cell receptor).
- IgM rises first and fades, so it points to a recent infection. IgG rises later and stays, so it points to past infection or immunity.
- The mother's IgG crosses the placenta. It gives the newborn temporary passive immunity for the first months of life.
Section 4Inflammation & healing
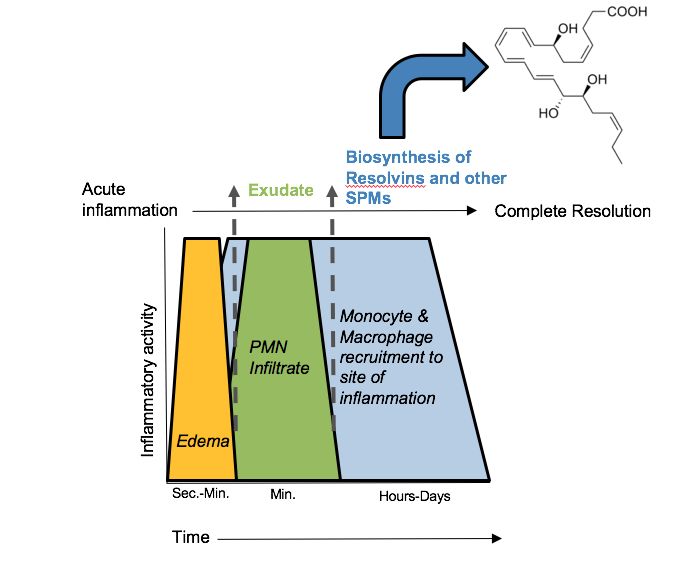
Think of inflammation as your body's first-responder team. It is not the same thing as infection. Infection means microbes have invaded. Inflammation is the response, and it fires for many triggers. Bacteria, a splinter, a burn, a sprain, or dying tissue will all set it off. In healthy tissue, capillaries run quietly and white blood cells patrol the blood. The moment cells are injured, that calm is broken on purpose. The goal is to contain the threat, clear the debris, and set up repair. To understand the response, you need a handful of chemical mediators and what they do to blood vessels.
The five cardinal signs and why each happens
Injured cells and nearby mast cells release histamine. They also release prostaglandins, bradykinin, and cytokines. These mediators cause two changes in blood vessels, and those two changes explain every classic sign.
- Redness (rubor) and heat (calor) come from vasodilation. The arterioles widen, so more warm blood floods the area.
- Swelling (tumor) comes from increased capillary permeability. The vessel walls loosen and let protein-rich fluid leak into the tissue. That fluid is edema.
- Pain (dolor) comes from bradykinin and prostaglandins firing nerve endings. Pressure from the swelling adds to it.
- Loss of function (functio laesa) is the sum of pain and swelling. A swollen, aching joint simply will not move well.
Meanwhile, neutrophils are the first white cells on the scene. They squeeze out of the vessels, a step called diapedesis. Then they begin phagocytosis of pathogens and debris. Monocytes follow them out and mature into macrophages, which take over the cleanup. So the order is neutrophils first, then monocytes and macrophages.
Acute versus chronic inflammation
Acute inflammation is fast and it stops on its own. It runs for hours to a few days, and ideally it ends in full healing. Chronic inflammation drags on for weeks, months, or years. Usually the trigger never clears, as in a lasting infection, an autoimmune disease, or ongoing irritation. The cast of cells changes too. Neutrophils give way to macrophages and lymphocytes. The cost to the tissue is real. Chronic inflammation drives fibrosis, which is scarring, plus tissue destruction and sometimes granulomas. The organ slowly loses working cells and gains stiff scar that does no work.
Exudates and the systemic response
The fluid that leaks out is called exudate. Serous exudate is thin and watery, like the fluid in a blister. Purulent exudate is thick pus, full of dead neutrophils and microbes, and it points to infection. Inflammation is not only local. Cytokines such as IL-1 and IL-6 travel to the brain and liver and cause systemic signs. These include fever, which is a raised set-point in the hypothalamus, and leukocytosis, which is a high white blood cell count. Acute-phase reactants rise as well. A climbing CRP is a true acute-phase protein. A rising ESR is an indirect marker driven by fibrinogen. Both are lab clues that inflammation is active somewhere in the body.
Healing: resolution versus repair
Two endings are possible. Resolution is the best case. The injury was mild and the cells can grow back, so the tissue returns to normal. Repair with scar (fibrosis) happens when the damage is wide, or when those cells cannot grow back. Fibroblasts lay down collagen and granulation tissue fills the gap. The scar holds, but it does not fully work.
| Feature | Primary intention | Secondary intention |
|---|---|---|
| Wound edges | Clean, lined up (sutured) | Wide and gaping, cannot be closed |
| Tissue loss | Very little | A lot |
| Healing time | Fast | Slower |
| Scar | Small | Larger, more granulation tissue |
| Infection risk | Lower | Higher |
Why anti-inflammatory drugs work
NSAIDs such as ibuprofen and aspirin block the COX enzymes that make prostaglandins. So they dull pain, fever, and swelling but leave much of the immune response in place. Corticosteroids such as prednisone act much further upstream. They shut down the genes for many mediators at once. They are far stronger, but they also suppress immunity more. That is why they raise infection risk and slow healing. Use the figure below to trigger the acute inflammatory response and watch the cardinal signs appear.
- All five cardinal signs (redness, heat, swelling, pain, loss of function) trace back to vasodilation and increased capillary permeability from histamine and prostaglandins.
- Acute inflammation is short and usually heals. Chronic inflammation lasts, and it costs tissue through fibrosis and destruction.
- Systemic signs of inflammation include fever, leukocytosis, and a high CRP/ESR. Purulent exudate suggests infection.
- Healing ends in resolution, which is back to normal, or repair with scar. Clean wounds heal by primary intention, gaping wounds by secondary.
- NSAIDs block prostaglandins through COX. Corticosteroids shut down many mediators at once and can mask the signs of infection.
Section 5When immunity overreacts: hypersensitivity
Your immune system is built to protect you. Sometimes it protects too hard. Hypersensitivity means the immune response is too big or aimed at the wrong target. The defense itself becomes the cause of tissue damage. To see how, recall how normal immunity works. Your body makes antibodies (immunoglobulins) that tag foreign invaders. It also makes special T cells that spot threats directly. Normally these tools attack germs and leave your own cells alone. In hypersensitivity, that aim breaks down. The immune system may react to something harmless, such as pollen, a food, or a medication. It may target your own cells. Or it may leave inflammatory debris behind that damages healthy tissue.
Clinicians sort these overreactions into four classic types. A simple memory device keeps them straight: ACID. That stands for Anaphylactic, Cytotoxic, Immune-complex, and Delayed. Antibodies drive the first three. Only the fourth one works without them.
Type I - Immediate (IgE-mediated): allergy and anaphylaxis
This is the classic allergy. On the first exposure, the body makes IgE antibodies against a harmless allergen. It parks that IgE on the surface of mast cells and basophils. This quiet step is called sensitization. On the next exposure, the allergen bridges those IgE molecules together. The mast cells then degranulate, dumping histamine and other mediators within minutes. Histamine causes vasodilation, which brings redness, warmth, and low blood pressure. It causes increased capillary permeability, which brings swelling and hives. It also causes bronchoconstriction, which brings wheezing. A local reaction is hay fever or hives. A whole-body reaction is anaphylaxis, where airway swelling and vasodilatory shock can kill quickly. This is why epinephrine is the first-line rescue drug. It reverses bronchoconstriction and vasodilation fast.
Type II - Cytotoxic (antibody against cells)
Here antibodies, usually IgG or IgM, bind right onto antigens on the surface of certain cells. That marks those cells for destruction by complement and phagocytes. The classic example is a mismatched blood transfusion. Give type A blood to a type B patient, and the patient's ready-made antibodies attack the donor red cells. The result is rapid hemolysis, with fever, flank pain, and dark urine. Another example is hemolytic disease of the newborn. An Rh-negative mother makes anti-Rh antibodies. Those antibodies cross the placenta and destroy the red cells of an Rh-positive baby.
Type III - Immune-complex mediated
In Type III, antibody and antigen clump into immune complexes. These clumps circulate, then settle in tissues such as joints, skin, kidney glomeruli, and blood vessel walls. Once lodged, they switch on complement and set off inflammation right where they landed. This is the mechanism behind systemic lupus erythematosus (SLE). It also causes serum sickness, a reaction to foreign proteins such as certain antivenoms. Here is the key difference from Type II. The antibody is not aimed at a fixed cell. It is floating debris that inflames wherever it lands.
Type IV - Delayed (T-cell mediated)
Type IV is the odd one out, because there is no antibody at all. Instead, sensitized T lymphocytes recognize the antigen and call in macrophages. This cell-driven process takes time, so the reaction peaks at 48 to 72 hours. That is exactly why you read a TB skin test (PPD) at 48 to 72 hours. The firm raised induration is delayed T-cell inflammation. Other examples are contact dermatitis, from poison ivy or nickel, and transplant (graft) rejection.
| Type | Mediator | Timing | Classic example |
|---|---|---|---|
| I - Anaphylactic | IgE, mast cells, histamine | Seconds to minutes | Anaphylaxis, hay fever |
| II - Cytotoxic | IgG/IgM against the cell surface | Minutes to hours | Transfusion reaction, HDN |
| III - Immune-complex | Antibody-antigen clumps in the blood | Hours | SLE, serum sickness |
| IV - Delayed | T cells (no antibody) | 48-72 hours | TB skin test, poison ivy |
Use the figure below to compare the four types side by side.
- ACID puts the four types in order: Anaphylactic (I), Cytotoxic (II), Immune-complex (III), Delayed (IV).
- Types I, II, and III are antibody-driven. Type IV is T-cell driven, with no antibody.
- Type I needs sensitization first. The severe reaction hits on re-exposure, and epinephrine is the rescue drug for anaphylaxis.
- Type II targets certain cells, as in a transfusion reaction or hemolytic disease of the newborn. Type III drops floating clumps that inflame tissue, as in SLE and serum sickness.
- Type IV is delayed 48 to 72 hours. That is the reason a TB skin test is read days later.
Section 6Autoimmunity & immunodeficiency
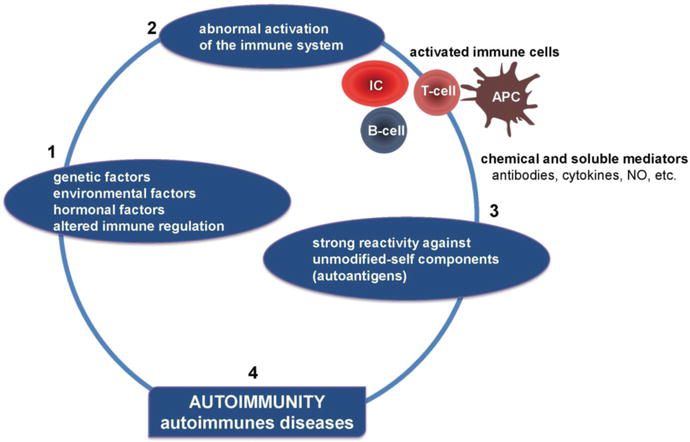
Your immune system has an almost impossible job. It must attack anything foreign, such as bacteria, viruses, and cancer cells. At the same time it must leave you completely alone. The skill of telling "self" from "non-self" is called self-tolerance, and it is built while the immune system develops. As lymphocytes mature, any that react strongly against your own tissue are normally deleted or switched off. That filtering is called central and peripheral tolerance. When it breaks down, the immune system turns its weapons inward. This section covers what happens when tolerance fails, which is autoimmunity. It also covers the flip side, when the immune system is too weak to defend at all, which is immunodeficiency.
When self-tolerance breaks down: autoimmunity
In autoimmune disease, the immune system loses self-tolerance. It starts making autoantibodies and self-reactive T cells that treat normal tissue like an invader. The result is chronic inflammation and tissue destruction wherever the immune system aims. The trigger is usually a mix of two things. One is genetic susceptibility, often certain HLA types. The other is an environmental push, such as an infection, hormones, or drugs. Here is a helpful way to learn these diseases. Ask one question: what tissue is being attacked? Use the figure below to watch tolerance break down step by step.
| Disease | Target attacked | Classic result |
|---|---|---|
| SLE (lupus) | Many tissues at once: skin, joints, kidneys, blood | Butterfly rash, joint pain, lupus nephritis; ANA usually positive |
| Rheumatoid arthritis | Synovial joints (the joint lining) | Matching joints on both sides are warm and swollen; morning stiffness |
| Multiple sclerosis | Myelin around CNS nerves | Nerve signals slow down: weakness, vision changes, numbness |
| Type 1 diabetes | Beta cells of the pancreas | No insulin is made, so blood glucose runs high |
| Hashimoto thyroiditis | Thyroid (destroys it) | Hypothyroidism: tired, cold, gaining weight |
| Graves disease | Thyroid (over-stimulates it) | Hyperthyroidism: heat intolerance, weight loss, exophthalmos |
Notice that Hashimoto and Graves hit the same organ with opposite results. In Hashimoto, autoantibodies and T cells slowly destroy thyroid tissue, so hormone output falls. In Graves, the autoantibody copies TSH and switches the gland on all the time. That floods the body with thyroid hormone. Same target, opposite mechanism. It is a favorite exam contrast.
The opposite problem: immunodeficiency
Sometimes the danger is not an overactive immune system. It is an underactive one. In immunodeficiency, part of the immune defense is missing or weak, so ordinary germs turn dangerous. There are two broad types.
- Primary (congenital) means the person is born with a genetic defect in immune development. These are usually rare. They often show up in infancy with repeated, severe, or unusual infections.
- Acquired (secondary) means the immune system grew normally but was damaged later. Causes include infection such as HIV, chemotherapy, long-term steroids or other immunosuppressants, poor nutrition, and aging. These are far more common.
HIV/AIDS and the CD4 count
The key example of acquired immunodeficiency is HIV (human immunodeficiency virus). HIV infects and destroys CD4+ T-helper cells. Those are the "quarterback" cells that coordinate almost the entire immune response. As the virus copies itself, the CD4 count drops steadily. A normal CD4 count is usually about 500 to 1,500 cells/mm³. The diagnosis becomes AIDS when the count falls below roughly 200 cells/mm³, or when an AIDS-defining opportunistic infection appears. At that point the body can no longer fight off opportunistic infections. These are organisms like Pneumocystis pneumonia that a healthy immune system would handle easily. So the CD4 count is basically a scoreboard of how much immune defense is left.
When inflammation goes body-wide: SIRS and sepsis
Inflammation is usually local and protective. But an infection can spill the inflammatory response into the whole bloodstream. Then the reaction loses its controls and turns dangerous. SIRS (systemic inflammatory response syndrome) is the older name for that body-wide inflammatory storm. It is scored on an abnormal temperature, a fast heart rate, fast breathing, and an abnormal white-cell count. That ladder is useful for spotting a sick patient, but it is not the current definition. The definition that counts is Sepsis-3. Under Sepsis-3, sepsis is infection plus new organ dysfunction, not infection alone. Septic shock is sepsis that still needs vasopressor drugs to hold a mean arterial pressure of 65 mmHg, with a blood lactate above 2 mmol/L. The middle term severe sepsis was retired in 2016, so you will see it only in older writing. In all of it, the same mediators meant to fight germs now cause widespread vasodilation and leaky vessels. Blood pressure drops and organs are starved of oxygen. It is a sobering reminder that too much immune activity can kill as surely as too little.
Why immunosuppressed patients are so fragile
The cause may be HIV, chemotherapy, anti-rejection drugs after a transplant, or steroids. Either way, an immunosuppressed patient has fewer or weaker defenders. Germs that a healthy person would shrug off can cause overwhelming infection. The usual warning signs may also be muted. A patient with a low white-cell count, called neutropenia, may not run a fever or form pus. So the infection hides until it is advanced. That is why care focuses on strict hand hygiene and neutropenic precautions. It is also why even a low-grade fever is treated as a possible emergency.
- Autoimmunity is a loss of self-tolerance, so the immune system attacks the body's own tissue. Learn each disease by asking what tissue is targeted: SLE hits many systems, RA hits joints, MS hits myelin, T1DM hits beta cells, and Hashimoto and Graves hit the thyroid.
- Hashimoto destroys the thyroid, so hormone levels fall. Graves over-stimulates it, so they rise. Same organ, opposite effect.
- Immunodeficiency is either primary, meaning born with it, or acquired. HIV is the key acquired example. It destroys CD4+ helper cells, and a CD4 count below about 200 cells/mm³ defines AIDS.
- Use Sepsis-3. Sepsis is infection plus new organ dysfunction. Septic shock is sepsis needing vasopressors to hold a MAP of 65 mmHg with a lactate above 2 mmol/L. SIRS is the older framing, and severe sepsis was retired in 2016.
- Immunosuppressed patients catch infections easily, and their signs may be blunted, with little fever or pus. So any fever is treated urgently.
The chapter in one breath
- Pathogens differ in structure and in treatment. Bacteria have a cell wall and answer to antibiotics. Viruses need a host cell and answer to antivirals. Fungi, protozoa and parasites, and misfolded-protein prions each call for a different defense and a different drug.
- Innate immunity is the fast, nonspecific first responder you are born with, built from skin, phagocytes, complement, and fever. Adaptive immunity is slower but specific, and it remembers the invader through B cells that make antibodies and T cells.
- The five immunoglobulin classes split the work. IgG is the most abundant and crosses the placenta. IgM is the first responder and the biggest. IgA guards mucous membranes and rides in breast milk. IgE drives allergy and fights parasites. IgD is the B-cell surface receptor.
- Inflammation is the alarm at the tissue level, with five cardinal signs: redness (rubor), heat (calor), swelling (tumor), pain (dolor), and loss of function. All of them come from vasodilation and increased capillary permeability driven by histamine and other mediators.
- The four hypersensitivity reactions run in order. I is immediate and IgE-mediated, as in anaphylaxis. II is cytotoxic, where antibody attacks cells, as in transfusion reactions. III is immune-complex deposition, as in lupus. IV is delayed and T-cell-mediated, as in the TB skin test and contact dermatitis.
- Autoimmunity is a loss of self-tolerance, where the immune system attacks the body's own tissue. It causes diseases such as rheumatoid arthritis, systemic lupus erythematosus, and type 1 diabetes.
- Immunodeficiency is a weak or missing defense. It can be primary, meaning congenital, or secondary, meaning acquired from chemo, steroids, or poor nutrition. Either way the patient is open to opportunistic infection.
- HIV is a retrovirus that destroys CD4+ helper T cells and cripples adaptive immunity. Once the CD4 count falls below 200 cells/mm³, or an opportunistic infection appears, the illness has become AIDS.
ReferenceWords worth knowing
Here is a quick reference for the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Anaphylaxis
- A severe, fast, whole-body type I hypersensitivity reaction. A flood of histamine causes vasodilation all over the body, bronchoconstriction, and dangerously low blood pressure. It can kill within minutes if it is not treated.
- Antibody
- A Y-shaped protein, also called an immunoglobulin, made by plasma cells. It binds one specific antigen to tag it for destruction, to neutralize it, or to call in other immune defenses.
- Antibody titer
- A lab measure of how much of one antibody is in the blood. It is used to check immunity from a vaccine or past infection, or to follow an active immune response.
- Antigen
- Any molecule, usually a protein or sugar on a germ or foreign cell, that the immune system reads as "not self." The body answers by making antibodies or by switching on T cells.
- Adaptive immunity
- The slower, learned arm of defense. It aims at one specific antigen and builds memory, so the next meeting with that same invader is met faster and harder.
- Autoimmunity
- A breakdown of self-tolerance. The immune system mistakes the body's own healthy tissue for a threat and attacks it, as in lupus or rheumatoid arthritis.
- Cell-mediated immunity
- The arm of adaptive immunity run by T lymphocytes rather than antibodies. It kills virus-infected and cancerous cells directly, and it coordinates other immune responses.
- Complement
- A chain of blood proteins. Once triggered, it punches holes in microbe membranes, coats germs so they will be eaten, and turns up inflammation.
- Cytokine
- A small signaling protein, such as an interleukin or an interferon. Immune cells release cytokines to talk to each other, call in help, and set the strength and type of the response.
- Exudate
- The protein-rich fluid, cells, and debris that leak from blood vessels into inflamed tissue. It ranges from watery (serous) to full of pus (purulent), depending on the cause.
- Humoral immunity
- The arm of adaptive immunity run by B lymphocytes and the antibodies they release. Those antibodies travel in body fluids to neutralize pathogens and toxins.
- Immunodeficiency
- A weak or missing part of the immune system. It may be inherited or acquired, as in HIV or chemotherapy, and it leaves a person open to frequent or unusual infections.
- Inflammation
- The body's protective response to injury or infection. Blood vessels widen and immune cells rush in, which produces the classic redness, heat, swelling, and pain.
- Innate immunity
- The fast, nonspecific first line of defense you have from birth. It includes skin barriers, phagocytes, and inflammation, and it attacks any invader with no prior exposure needed.
- Pathogen
- Any disease-causing microbe, such as a bacterium, virus, fungus, or parasite, that can invade the body and set off an immune response.
- Phagocyte
- A cell-eating white blood cell, such as a neutrophil or a macrophage. It swallows and digests germs, dead cells, and debris to clear an infection.
DrillFlashcards for this unit
These are the Week 2 cards, the same deck as the hub, pulled in here so you can review as soon as you finish reading. Tap a card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
Oncology: How Cancer Works
Cancer is not one disease. It is a process. One cell stops obeying the body’s rules and starts dividing on its own. This chapter follows that process from the first mutation to a spreading tumor. You will see how a normal cell turns malignant. You will learn how we tell a harmless lump from a dangerous one, how cancer travels, what sets it off, and how it is graded, staged, and treated.
By the end of this chapter you can
- Explain how a normal cell becomes cancer. Mutated oncogenes and tumor-suppressor genes drive it.
- Compare benign and malignant tumors. Use the -oma, carcinoma, and sarcoma names.
- Describe how cancer invades. Name the routes and common sites of metastasis.
- Name the major carcinogens. Say what p53 and BRCA do.
- Tell grading from staging (TNM). Spot tumor lysis syndrome.
Section 1From a normal cell to cancer
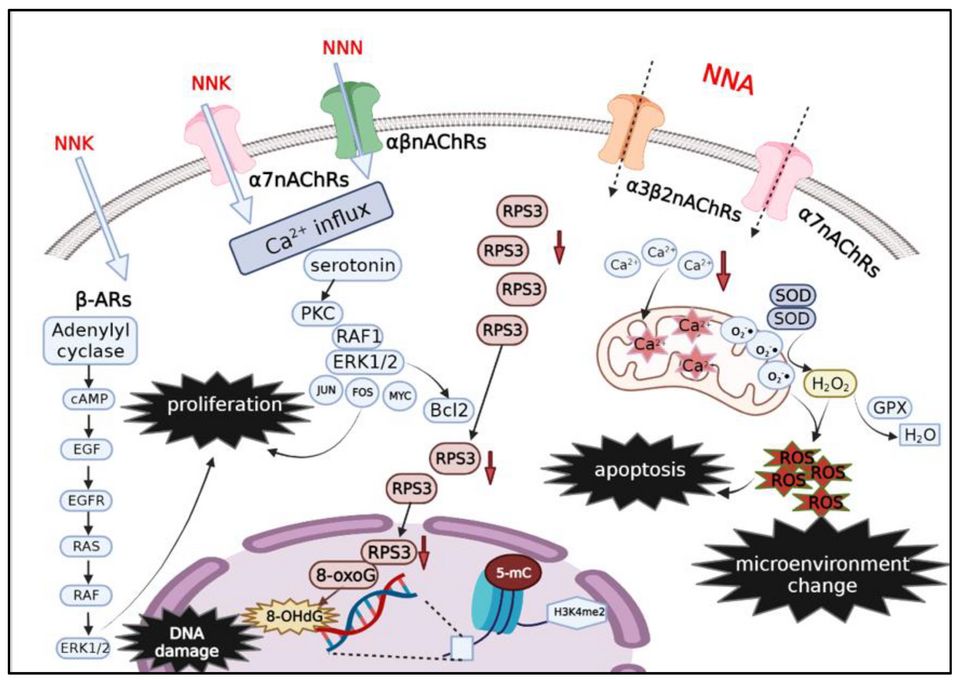
Every cell in your body lives by a simple rule: divide only when you are told to, and stop when the job is done. A healthy cell reads chemical signals from its neighbors. It copies its DNA with care. It checks that copy for errors. Then it either keeps going or quietly retires. Genes control that balance between growing and stopping. When those control genes get damaged, the balance tips. A normal cell can then turn, slowly, into a cancer cell. Cancer is not an invader from outside. It is one of your own cells that has lost its instructions.
The accelerator and the brakes
Think of cell division like driving a car. Two sets of genes keep it under control. Proto-oncogenes are the accelerator. They normally tell the cell when it is time to grow and divide. Tumor-suppressor genes are the brakes. They slow division, fix damaged DNA, or order a broken cell to self-destruct. In a normal cell these two work together. So growth happens only when it should.
Mutations break this system in two different ways. When a proto-oncogene mutates, it becomes an oncogene. That is a stuck accelerator. It screams "grow!" even with no signal. This is a gain of function. Usually only one copy of the gene needs to change. When a tumor-suppressor gene mutates, the brakes fail. This is a loss of function. Here, both copies must usually be knocked out before protection is lost. The famous tumor suppressor p53 is often called the "guardian of the genome." It normally halts a damaged cell and triggers apoptosis, the cell’s self-destruct program. When p53 fails, damaged cells survive and keep dividing.
The multistep journey: how tissue changes over time
Cancer does not appear overnight. Tissue drifts through stages we can recognize as mutations pile up:
- Hyperplasia: too many cells, but they still look normal and stay in order.
- Dysplasia: cells start to look abnormal, with odd shapes, odd sizes, and messy arrangement. This is pre-cancerous, but it can still reverse.
- Carcinoma in situ: cells look fully cancerous, but they stay above the basement membrane. Nothing has spread yet, so cure rates are high.
- Invasive cancer: cells break through the basement membrane into nearby tissue. They can then travel to distant sites (metastasis).
What makes a cancer cell dangerous: the hallmarks
Researchers describe cancer through a set of shared "hallmark" behaviors. Put simply, cancer cells learn to do these things:
- Divide without permission: the stuck accelerator and failed brakes problem. They multiply even when the body signals stop.
- Evade apoptosis: normal cells with broken DNA are told to die. That ordered death is programmed cell death. Cancer cells silence the signal, often by disabling p53. Damaged cells then refuse to die.
- Grow their own blood supply: a process called angiogenesis. Once a tumor grows past roughly 1 to 2 mm, it starves for oxygen. So it releases signals that pull in new blood vessels to feed it. Later those vessels give cancer cells a highway to spread.
Tumor is not the same as cancer
These two get mixed up all the time. A tumor (or neoplasm) is simply a lump. It is an abnormal mass of cells. Cancer means the tumor is malignant: it invades and can spread. A benign tumor, like a lipoma, is a lump that stays put.
| Feature | Benign tumor | Malignant tumor (cancer) |
|---|---|---|
| Growth | Usually slow | Often fast |
| Border | Clear edge, often inside a capsule | Ragged edge, grows into nearby tissue |
| Cell appearance | Looks like normal tissue (well-differentiated) | Odd and disordered (poorly differentiated) |
| Spread (metastasis) | No | Yes, through blood or lymph |
| Danger | Usually harmless unless it presses on something | Deadly if not treated |
Explore the figure below. Watch a cell move from normal, through adaptation, into dysplasia. It is the same stepwise drift described here.
- Proto-oncogenes are the accelerator. Tumor-suppressor genes are the brakes. Cancer needs a stuck accelerator (an oncogene, one hit) and failed brakes (a tumor suppressor, usually two hits).
- Cancer builds in steps: hyperplasia to dysplasia to carcinoma in situ to invasive cancer, as mutations pile up over time.
- Hallmark behaviors: uncontrolled division, evading apoptosis (often by disabling p53), and angiogenesis, which means growing its own blood supply.
- A tumor is any lump. Only a malignant tumor is cancer. What defines it is the power to invade and metastasize.
- Invasion means breaking through the basement membrane. That is the line between contained disease and spreading disease.
Section 2Benign vs malignant
Your body makes new cells all the time. Skin, gut lining, and blood cells are always being replaced. Normally this runs under tight control. Cells divide only when signaled. They mature into a specific job. Then they stop dividing once the tissue is repaired. This maturing process is called differentiation. A well-differentiated cell looks and acts like the tissue it came from. A neoplasm (literally "new growth") is a lump of cells that has escaped normal growth controls. It keeps dividing when it should not. The big clinical question is always the same. Is this growth benign or malignant?
Benign growths: slow, walled-off, and well-behaved
A benign tumor grows slowly and stays put. Because it grows slowly, the tissue around it often has time to build a fibrous capsule. The mass is then encapsulated, so a surgeon can usually shell it out cleanly. Its cells are well-differentiated. That means they still look much like the normal tissue of origin, and they often still do that tissue’s job. Benign tumors do not invade nearby structures. They also do not metastasize, which means spread to distant sites. Under the microscope the cells look orderly. The nuclei are normal in size, and few cells are dividing (a low mitotic rate).
Malignant growths: fast, invasive, and mobile
Malignant tumors (true cancer) behave the opposite way. They grow fast, so they rarely build a tidy capsule. Instead they send out finger-like projections that invade and destroy nearby tissue. That is why the cut surface can look crab-like, which is where the word "cancer" comes from. Their cells are poorly differentiated or undifferentiated. They no longer look like the parent tissue or act like it. Most important, malignant cells can break away. They travel through blood or lymph and seed new tumors elsewhere. That spread is metastasis. It is the feature that makes cancer so dangerous and so hard to cure.
| Feature | Benign | Malignant |
|---|---|---|
| Growth rate | Slow | Fast, often uneven |
| Border | Inside a capsule, clear edge | Invades, edge is unclear |
| Differentiation | Well-differentiated | Poorly differentiated to anaplastic |
| Metastasis | Never | Common |
| Comes back after removal | Rare | Common |
How tumors are named
Naming follows a pattern worth memorizing. The ending -oma usually means a benign tumor, named for the tissue it came from. A lipoma is a benign fat tumor. An adenoma is a benign gland tumor. A leiomyoma is a benign smooth-muscle tumor, which is a uterine "fibroid." Malignant tumors get one of two labels, based on the tissue they came from: carcinomas from epithelial tissue, sarcomas from connective (mesenchymal) tissue. A carcinoma starts in epithelial tissue, which lines skin, glands, and organs. It is by far the most common group, and it includes adenocarcinoma of the colon or breast. A sarcoma starts in connective tissue such as bone (osteosarcoma), cartilage, muscle, or fat. A few dangerous "-oma" names break the rule. Melanoma and lymphoma are malignant, despite the friendly ending.
Differentiation and anaplasia
Pathologists describe cancers by how far the cells have drifted from normal. Grading measures differentiation. A well-differentiated (low-grade) cancer still looks like its tissue of origin. It usually behaves less aggressively. Anaplasia is the far opposite. The cells are so primitive and disordered that they barely look like any tissue. Anaplastic cells show pleomorphism, which means they vary in size and shape. They have large dark nuclei with a high nucleus-to-cytoplasm ratio. They also show many mitoses, some of them abnormal. In general, the less differentiated the cell, the more aggressive the tumor and the worse the outlook.
When "benign" still hurts you
Benign does not always mean harmless. A tumor that would be minor elsewhere can be deadly because of where it sits. A benign meningioma in the skull has nowhere to expand. As it grows it raises intracranial pressure and presses on brain tissue. That brings headaches, seizures, or lost nerve function. A benign adenoma can also make hormones. One example is insulin from a pancreatic tumor, which drives dangerous hypoglycemia, or low blood sugar. A benign mass can also block a hollow organ or press on a vital vessel. Location, hormone release, and pressure drive the risk, not just the label.
Try the dial below. One lump slides from calm to wild, and the growth rate, the capsule, the edge and the cells all move together.
- Benign tumors are slow, encapsulated, well-differentiated, and they stay put. Malignant tumors are fast, invasive, poorly differentiated, and they metastasize.
- Metastasis is the defining danger of malignancy. It is the main reason cancer is hard to cure.
- Naming: -oma usually means benign, carcinoma means malignant epithelial, sarcoma means malignant connective tissue. Watch the exceptions, melanoma and lymphoma.
- Differentiation drives grade. Anaplasia, with primitive, pleomorphic, fast-dividing cells, signals the most aggressive tumors.
- A benign tumor can still be deadly, because of its location, its hormone release, or the pressure it makes. The classic case is a meningioma raising intracranial pressure.
Section 3How cancer grows and spreads
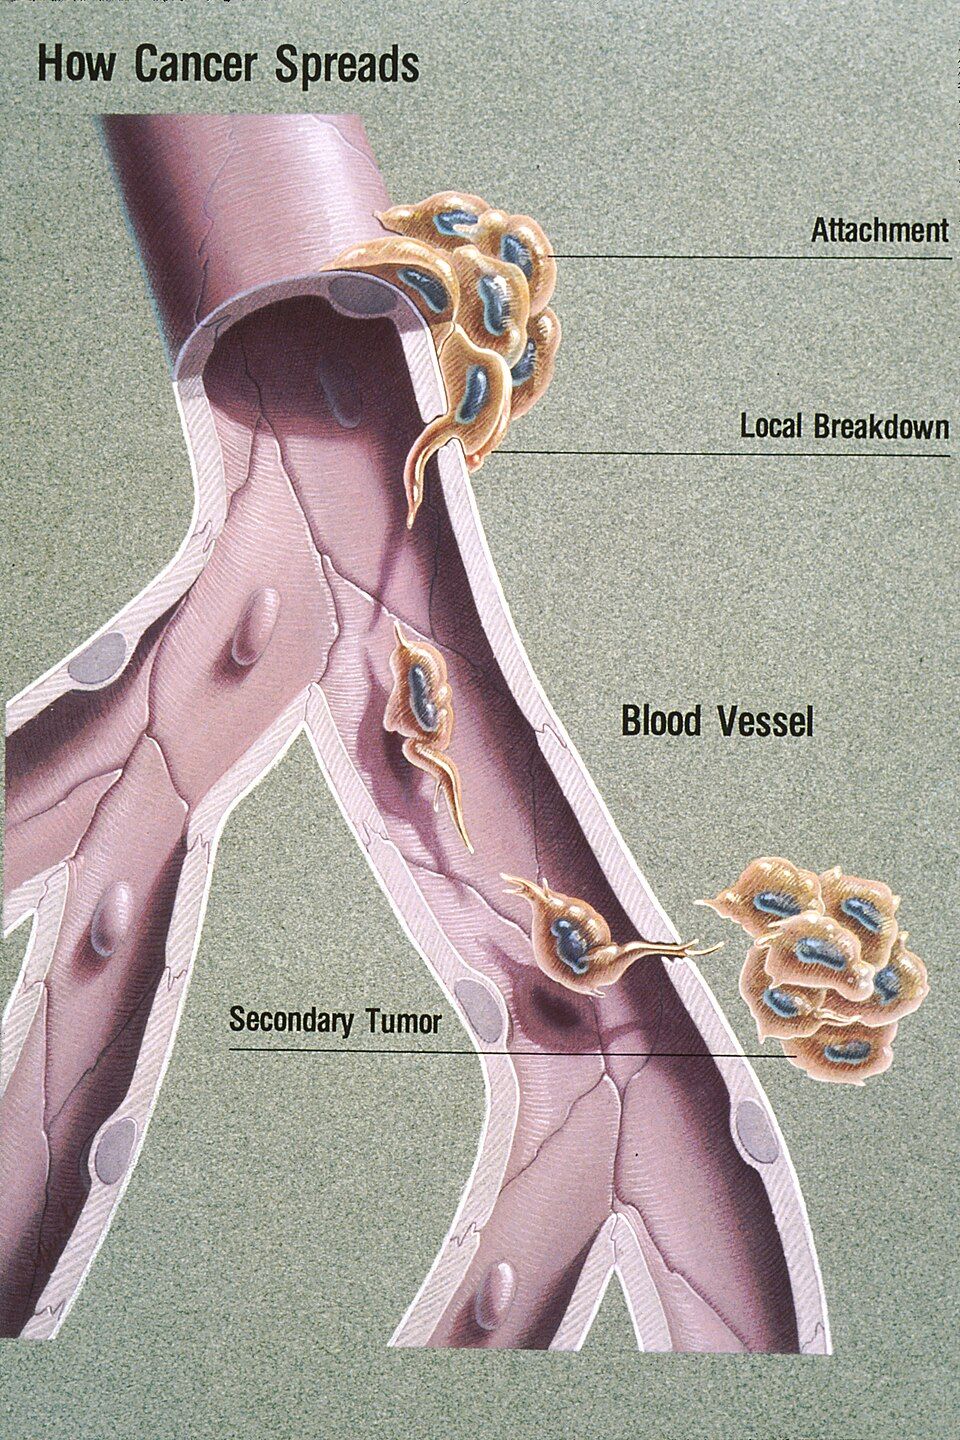
Normally your tissues are beautifully organized. Cells stay in their own neighborhood. A thin, tough sheet called the basement membrane holds them in place. It separates the surface layer (epithelium) from the deeper connective tissue below. Cells also respect their neighbors. They stop dividing when they touch, which is called contact inhibition. They anchor down where they belong. And they call for new blood vessels only when the body truly needs them. Cancer is what happens when a cell breaks every one of these rules at once. So how cancer grows and travels is really the story of a cell that has forgotten how to stay put. Explore it below as we walk through each step.
Local invasion: breaking through the basement membrane
A tumor usually starts as a well-behaved lump. It stays on its own side of the basement membrane. As long as it has not crossed that barrier, we call it carcinoma in situ, which means "in place." This stage is often curable, because nothing has gone anywhere yet. The dangerous turning point is local invasion. Cancer cells release enzymes called matrix metalloproteinases (MMPs). These enzymes digest the basement membrane and the extracellular matrix around it. Once that fence dissolves, the cells lose their normal stickiness. They turn down E-cadherin, the "glue" protein, and crawl into the deeper tissue. This is the moment a cancer becomes invasive. It is also why pathologists care so much whether the basement membrane is intact.
Metastasis: how cancer travels to distant sites
Metastasis is the spread of cancer from the first (primary) tumor to a distant site. It is the single biggest reason cancer becomes life-threatening. There are three main routes.
- Lymphatic spread: cells enter lymph vessels and travel to nearby lymph nodes first. This is the classic route for carcinomas, the epithelial cancers such as breast and colon. It is why lymph nodes are examined. It is also why we biopsy the sentinel lymph node, the first node that drains a tumor, to see whether spread has begun.
- Hematogenous spread: cells invade blood vessels and ride the bloodstream to far-off organs. This is the favored route for sarcomas, the connective-tissue cancers. It explains tumors that show up in distant organs.
- Seeding of body cavities: cells shed off the tumor surface and scatter across a cavity lining. Peritoneal seeding in ovarian cancer is the classic case. This can cause malignant ascites, a fluid buildup in the belly, or fluid around the lungs (pleural effusions).
| Feature | Lymphatic spread | Hematogenous spread |
|---|---|---|
| Typical cancer type | Carcinomas (epithelial) | Sarcomas (connective tissue) |
| First stop | Nearby (regional) lymph nodes | Distant organs |
| Clinical clue | Large, firm nodes | Masses in lung, liver, bone, brain |
| Checked by | Sentinel node biopsy | CT or PET imaging, bone scan |
Where cancer tends to land
Metastases are not random. Cells often lodge in the first capillary bed they reach. Certain organs also make good "soil" for tumor cells to settle in. That idea is called the seed-and-soil hypothesis. The four most common landing sites are lung, liver, bone, and brain. The lung and liver catch a large share of traveling cells, because they work as filters with dense capillary networks. The liver receives portal blood, and the lungs filter all the blood coming back from the veins. Bone metastases are common in breast and prostate cancer. They often cause deep pain, pathologic fractures, and high calcium levels (hypercalcemia). Brain metastases can raise intracranial pressure. That brings headaches, seizures, or new nerve problems.
Angiogenesis: the tumor builds its own supply lines
A clump of cancer cells can only grow to about 1 to 2 mm on its own. After that the cells in the center start to starve. They sit too far from any blood vessel to get oxygen and nutrients by diffusion. To keep growing, the tumor pulls off a striking trick called angiogenesis. It releases chemical signals, above all vascular endothelial growth factor (VEGF). Those signals coax nearby blood vessels to sprout new branches straight into the tumor. This "angiogenic switch" gives the tumor its own supply line for more growth. Sadly, it also gives escaping cells an on-ramp into the bloodstream for metastasis. These new vessels are usually leaky and poorly built. That adds to swelling and makes drug delivery hard to predict. Because VEGF is so central, several cancer drugs block it to try to starve the tumor. Bevacizumab is one of these anti-angiogenic agents.
Now pick a starting cancer and a route out of it. The road decides which organs can light up, and the funnel shows how few traveling cells ever take hold.
- Cancer turns invasive when it uses enzymes (MMPs) to break through the basement membrane. Before that, carcinoma in situ is often curable.
- Metastasis spreads by three routes: lymphatic (typical of carcinomas), hematogenous through the bloodstream (typical of sarcomas), and seeding of body cavities.
- The most common landing sites are lung, liver, bone, and brain. New bone pain in a cancer patient is a red flag for metastasis.
- Angiogenesis, driven by VEGF, lets a tumor recruit its own blood supply and grow past 1 to 2 mm. It also opens a route for cells to escape and spread.
Section 4What causes cancer
Every day your body makes billions of new cells. Old cells wear out, get injured, or reach the end of their life. So a healthy cell divides to make a fresh copy of itself. Normally this process is tightly controlled. Before a cell divides, it copies all of its DNA. Then it pauses at built-in checkpoints to proofread that copy. If the DNA looks damaged, the cell either repairs it or kills itself on purpose. That tidy self-destruct program is called apoptosis. Cancer begins when this careful system breaks down. The cell then divides on its own schedule, ignores the stop signals, and refuses to die.
So the real question is simple. What damages the DNA and the control genes badly enough to let a cell go rogue? Usually it is a slow buildup of mutations, which are permanent changes in the DNA sequence. They hit the specific genes that run the cell cycle.
Carcinogens: the things that damage DNA
A carcinogen is any agent that causes cancer. Most do it by damaging DNA directly. Others push cells to divide so fast that copy errors pile up. They fall into a few broad groups:
- Chemical: the classic example is tobacco smoke, which carries dozens of DNA-damaging compounds. Others include asbestos, benzene, and certain dyes. Many act right where they touch the body, such as asbestos in the lungs and dyes in the bladder. But some, like benzene, are absorbed and cause blood cancers such as leukemia.
- Radiation: ultraviolet (UV) light from the sun damages skin-cell DNA. It drives melanoma and other skin cancers. Ionizing radiation, such as X-rays and radon, does the same thing inside the body.
- Viral and microbial: some infections insert their own genes, and some cause lasting irritation. Know these: HPV (cervical and oropharyngeal cancers), EBV (some lymphomas), hepatitis B and C (liver cancer), HHV-8 (Kaposi sarcoma), and the bacterium H. pylori (stomach cancer). Herpes simplex is not on the list.
Oncogenes and tumor-suppressor genes
Two families of genes normally keep cell division in check, and cancer usually damages both. Think of driving a car. You need a working gas pedal and working brakes.
Proto-oncogenes are the gas pedal. They tell a cell when it is time to grow and divide. When a proto-oncogene mutates and gets stuck in the "on" position, it becomes an oncogene. That oncogene floors the accelerator and drives nonstop division.
Tumor-suppressor genes are the brakes. They slow division, run the DNA proofreading checkpoints, and trigger apoptosis when a cell is too damaged. The most famous one is p53, nicknamed the guardian of the genome. It halts the cell cycle so repair can happen, and it orders apoptosis when repair fails. When p53 is knocked out, damaged cells sail through the checkpoints and pick up even more mutations. The BRCA1 and BRCA2 genes are tumor suppressors too. They help repair broken DNA. So when they fail, breast and ovarian tissue lose a key safety net.
| Feature | Oncogene | Tumor-suppressor gene |
|---|---|---|
| Normal job | Pushes cell growth (gas pedal) | Holds growth back, repairs DNA, triggers apoptosis (brakes) |
| Effect of mutation | Gain of function, stuck ON | Loss of function, brakes fail |
| Copies needed to cause trouble | Usually one mutated copy is enough | Usually both copies must be lost |
| Examples | Mutated RAS, HER2 | p53, BRCA1/2, RB |
Inherited vs acquired mutations, and why some cancers run in families
Most cancers come from acquired (somatic) mutations. This is damage that builds up in one person’s cells over a lifetime. It comes from carcinogens, random copying errors, and aging. These changes are not passed to children. That is why most cancers are sporadic.
A smaller group involves inherited (germline) mutations. These sit in every cell from birth, because they came from a parent’s egg or sperm. Say someone inherits one broken copy of a tumor-suppressor gene like BRCA1. They only need to lose the second copy for that safety net to fail. They are already halfway there. That head start is why these cancers show up earlier in life. They also often appear in both breasts, or in several family members. This is the mechanism behind family patterns, and the basis for genetic counseling.
Chronic inflammation and failed immune surveillance
Two background factors quietly raise the odds. First, chronic inflammation keeps tissue in a constant cycle of injury and repair. Long-standing hepatitis, H. pylori gastritis, and inflammatory bowel disease all do this. Every extra round of division is another chance for a mutation to slip in. Second, your immune system normally patrols for abnormal cells and destroys them. That process is called immune surveillance. Cancer cells that learn to hide from these patrols, or to wear them out, escape destruction. This is why patients on immune-suppressing drugs often have higher cancer rates.
Stack exposures in the model below and drag the age. Watch the gene board fill as hits add up, and watch the odds curve bend away from the clean one.
- Cancer starts when DNA damage disables the normal controls on cell division. The cell can then divide without limit and dodge apoptosis.
- Carcinogens cause cancer mostly by damaging DNA. They are chemical (tobacco), radiation (UV), and viral or microbial (HPV, EBV, hepatitis B and C, HHV-8, H. pylori). Many are preventable through vaccines and lifestyle.
- Oncogenes are a stuck gas pedal (gain of function). Tumor suppressors like p53 (guardian of the genome) and BRCA1/2 are failed brakes (loss of function).
- Most mutations are acquired over a lifetime. Inherited germline mutations give a head start toward cancer, which explains earlier onset and family clusters.
- Chronic inflammation and failed immune surveillance also play a part. They let mutated cells pile up and escape destruction.
Section 5Grading, staging & living with cancer
Your cells normally follow strict rules. They divide only when told to. They mature into a specific job, such as a skin cell or a colon cell. And they stay in their own neighborhood. Cancer breaks all three rules. The cells divide without permission, they fail to mature, and they invade and travel. Once a tumor exists, the care team asks two early questions. How odd do these cells look under the microscope? And how far has this spread? Those are two different questions. Mixing them up is one of the most common mistakes.
Grading vs staging
Grading is about appearance. A pathologist looks at the tumor cells and asks how much they still look like the normal tissue they came from. Well-differentiated (low-grade) cells still look and act a lot like the parent tissue. They tend to grow slowly. Poorly differentiated or anaplastic (high-grade) cells look wild and disordered. They usually behave more aggressively. Grading is usually reported as G1 through G4.
Staging is about spread. It asks how big the tumor is and how far it has traveled. The most widely used framework is the TNM system. T is the size and reach of the primary tumor. N is how many nearby lymph nodes are involved. M is distant metastasis, which means spread to far-off organs. Higher numbers mean more advanced disease. Staging drives treatment choices and outlook more powerfully than grade does.
| Feature | Grading | Staging |
|---|---|---|
| Question it answers | How abnormal do the cells look? | How far has it spread? |
| How it is measured | Differentiation under the microscope | TNM: Tumor, Nodes, Metastasis |
| Typical scale | G1 (well-differentiated) to G4 (anaplastic) | Stage I to Stage IV |
| Main use | Predicts how aggressive it is | Guides treatment and overall outlook |
The CAUTION warning signs
The American Cancer Society mnemonic CAUTION lists classic early clues. Each one should prompt a checkup. They matter because early detection usually means a lower stage and a better outcome:
- C → Change in bowel or bladder habits
- A → A sore that does not heal
- U → Unusual bleeding or discharge
- T → Thickening or a lump (breast or elsewhere)
- I → Indigestion or trouble swallowing
- O → Obvious change in a wart or mole
- N → Nagging cough or hoarseness
When the tumor causes trouble from a distance
Paraneoplastic syndromes happen when a tumor makes hormones or hormone-like substances. The symptoms then show up far from the tumor itself. Two classic examples: SIADH, where small cell lung cancer makes ADH and drives sodium down, and hypercalcemia, from PTH-related peptide or from bone breakdown.
Tumor lysis syndrome (TLS) is an oncologic emergency. Large numbers of cancer cells can die very fast, often right after chemotherapy starts. They dump their contents into the blood. The result is high potassium (hyperkalemia), high phosphate, high uric acid, and low calcium. That mix can trigger fatal arrhythmias and acute kidney injury. That is why the labs are watched closely and fluids are given.
The four treatment pillars
Most cancer care combines four approaches. Surgery removes the tumor. Radiation damages the DNA of cells in a targeted area. Chemotherapy uses drugs that travel the whole body to kill dividing cells. Immunotherapy retrains or unleashes the patient’s own immune system to find and attack cancer.
Here is the key mechanism behind chemo’s side effects. Most chemotherapy targets rapidly dividing cells, because that is what cancer does. But some healthy tissues divide fast too, so they take collateral damage. That is exactly why chemo predictably causes hair loss (alopecia), since hair follicles divide fast. It causes nausea, vomiting, and mouth sores (mucositis), since the gut lining turns over fast. And it causes bone marrow suppression (myelosuppression), which drops white cells, red cells, and platelets. The low white count (neutropenia) is the scary one. It leaves the patient wide open to infection.
Build a stage yourself below. Set the depth, the nodes, and the distant spread one at a time, and watch the same T land in four different stages.
- Grade describes how abnormal the cells look (differentiation, G1 to G4). Stage describes how far cancer has spread, using TNM (Tumor, Nodes, Metastasis).
- The CAUTION mnemonic flags early warning signs that need a checkup. It can catch cancer at a lower, more treatable stage.
- Paraneoplastic syndromes (such as SIADH and hypercalcemia) cause hormone-driven symptoms far from the tumor. Tumor lysis syndrome is an emergency with hyperkalemia, hyperphosphatemia, hyperuricemia, and hypocalcemia.
- The four pillars are surgery, radiation, chemotherapy, and immunotherapy.
- Chemo harms fast-dividing normal cells too. That causes alopecia, mucositis and GI upset, and myelosuppression. Watch for neutropenic fever.
The chapter in one breath
- Carcinogenesis is a stepwise loss of control. A normal cell mutates until it ignores stop signals, dodges apoptosis, and divides on its own. It becomes a clone of rogue cells.
- Cancer arises when proto-oncogenes mutate into oncogenes that are stuck on, the accelerator. At the same time tumor suppressor genes like p53 fail, the brakes. Growth control and DNA-repair checkpoints stop working.
- Benign tumors are usually slow, encapsulated, well-differentiated, and they stay put. Malignant tumors grow fast, lack a capsule, look abnormal, and spread.
- Invasion is local spread. Cancer cells release enzymes to chew through the basement membrane and move into nearby tissue. This is why surgical margins matter.
- Metastasis is distant spread through blood or lymph, forming secondary tumors. Common landing sites are lung, liver, bone, and brain, and it signals advanced disease.
- Causes are many. Carcinogens and risk factors include tobacco, radiation, UV light, certain chemicals, cancer-causing viruses (HPV, hepatitis, EBV), chronic inflammation, and inherited mutations such as BRCA.
- Grading says how abnormal the cells look under the microscope (differentiation). Staging, often TNM for Tumor size, Nodes, and Metastasis, says how far it has spread, and it drives the outlook.
- Treatment follows a few core ideas. Surgery removes local disease, radiation targets one region, and chemotherapy works through the whole body by hitting fast-dividing cells. They are often combined for better cure rates.
- Chemotherapy is not selective, so it also harms fast-turnover normal cells. That explains the classic toxicities: bone marrow suppression, hair loss, nausea, and mucositis.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Anaplasia
- Anaplasia is the extreme loss of a cell’s normal look and order. The cancer cells look so wild and disordered, with big uneven nuclei and chaotic mitoses, that you often cannot tell what tissue they came from. It marks a highly malignant tumor.
- Angiogenesis
- Angiogenesis is the growing of new blood vessels. A tumor hijacks it by releasing signals like VEGF, so it can build its own blood supply and keep growing past a couple of millimeters.
- Benign
- A benign tumor is a growth that stays put. It grows slowly, is usually well-differentiated and inside a capsule, and does not invade nearby tissue or spread to distant sites. It can still cause harm by pressing on nearby structures.
- Carcinogen
- A carcinogen is any agent that can cause cancer by damaging DNA or pushing abnormal growth. Examples are tobacco smoke, UV and ionizing radiation, certain chemicals, and cancer-causing viruses such as HPV.
- Carcinoma
- A carcinoma is a cancer that starts in epithelial cells. Those are the cells that line and cover body surfaces and glands, such as skin, breast, lung, colon, and prostate. It is the most common group of cancer.
- Carcinoma in situ
- Carcinoma in situ is an early cancer whose malignant cells are still held in their original layer. They have not yet broken through the basement membrane to invade. So it is often curable if it is found and removed at this stage.
- Differentiation
- Differentiation is how closely a cell looks like the mature, specialized tissue it came from. Well-differentiated cells look and act almost normal. Poorly differentiated ones look primitive and tend to be more aggressive.
- Dysplasia
- Dysplasia is disordered cell growth that can still reverse. The cells vary in size, shape, and order. It is a pre-cancerous change that can turn into cancer if the trigger keeps going.
- Malignant
- A malignant tumor is a cancerous growth. It invades nearby tissue, tends to be poorly differentiated, and can spread (metastasize) to distant parts of the body. That makes it life-threatening if it is not treated.
- Metastasis
- Metastasis is the spread of cancer cells from the first (primary) tumor to distant sites through the blood or lymph system. There they seed new (secondary) tumors. It is the main reason cancer becomes deadly.
- Neoplasm
- A neoplasm, literally "new growth," is a mass of cells that keep dividing past normal limits and serve no useful purpose. It may be benign or malignant.
- Oncogene
- An oncogene is a mutated or overactive version of a normal growth-promoting gene called a proto-oncogene. Once switched on, it pushes a cell to divide nonstop, like a gas pedal stuck to the floor.
- Paraneoplastic syndrome
- A paraneoplastic syndrome is a set of symptoms caused by substances a tumor releases, such as hormones or cytokines, rather than by the tumor’s bulk. So a patient may show effects, such as low sodium or high calcium, far from the cancer itself.
- Sarcoma
- A sarcoma is a cancer that starts in connective and supporting tissues, such as bone, cartilage, muscle, fat, or blood vessels. It is far less common than carcinoma.
- TNM staging
- TNM staging is the standard way to describe how far a cancer has gone. It rates three things: T for the size and reach of the primary tumor, N for spread to nearby lymph nodes, and M for distant metastasis.
- Tumor-suppressor gene
- A tumor-suppressor gene, such as p53 or BRCA, normally slows cell division, repairs DNA, or tells a damaged cell to self-destruct. When it is lost or switched off, the cell’s brakes fail and cancer can develop.
DrillFlashcards for this unit
These are the Week 3 cards. They are the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
Pain
Pain is the body’s alarm system. It is usually protective, sometimes broken, and always personal. This chapter traces a pain signal from the nerve ending that spots damage all the way to the brain that feels it. It sorts pain into its types, explains why rubbing a bump helps, and covers how pain is assessed and relieved safely.
By the end of this chapter you can
- Trace the pain pathway through transduction, transmission, perception, and modulation.
- Tell somatic, visceral, and neuropathic pain apart, and acute from chronic.
- Explain the gate control theory and the body’s own pain-relief system.
- Predict referred-pain patterns. Assess pain in patients who cannot speak for themselves.
- Use the WHO analgesic ladder. Name the key risks of opioids.
Section 1Nociception & the pain pathway
Pain feels like a problem. But in most cases it is your body’s alarm system doing exactly what it should. When tissue is threatened or damaged, special nerve endings fire. They send a warning racing toward your brain: stop, protect this spot, something is wrong. So you need to know three things. How that signal is born, how it travels, and how the body turns the volume up or down. That is the foundation for everything you will do in pain management.
Nociceptors: the sensors that spot damage
The journey starts with nociceptors, which are free nerve endings scattered through the skin, muscles, joints, and internal organs. Think of them as tiny smoke detectors. They do not answer to gentle touch. They wake up only when a stimulus is strong enough to mean real or possible tissue damage. That trigger can be mechanical (a cut or a crush), thermal (a hot stove), or chemical. When cells are injured they spill out a soup of substances. It holds prostaglandins, bradykinin, histamine, substance P, and hydrogen ions. This inflammatory soup lowers the firing threshold, so the nociceptors go off more easily. That is why a sunburned shoulder screams at a light pat. The sensors have been sensitized.
The four steps of nociception
Textbooks break the pain process into four linked steps. Learn them in order, because each treatment targets a specific step.
- Transduction: the harmful stimulus is turned into an electrical signal at the nociceptor. This is where NSAIDs work. They block prostaglandin production, so the sensors stay quieter.
- Transmission: the electrical impulse travels along peripheral nerve fibers to the dorsal horn of the spinal cord, then up to the brain. Local anesthetics cut this step off.
- Perception: the brain (the cortex and limbic system) becomes aware of the pain and gives it meaning and emotion. This is where distraction, relaxation, and imagery help.
- Modulation: the nervous system turns the signal up or down. Descending pathways release the body’s own endogenous opioids (endorphins and enkephalins), plus serotonin and norepinephrine. These dampen the message. Opioids and many antidepressants boost this natural braking system.
Two kinds of fibers, two kinds of pain
Not all pain messages travel at the same speed. That explains a common experience. Stub your toe and you feel a sharp jolt first, then a throbbing ache a moment later. Two different fibers are talking. A-delta fibers have a light myelin coat, so they conduct fast. They carry the sharp, bright, easy-to-pinpoint pain that makes you pull your hand away at once. C fibers have no myelin and are slow. They carry the dull, aching, burning pain that is hard to place and lingers afterward. Both fibers hand their signal off in the dorsal horn and cross to the other side. Then they ride the spinothalamic tract up to the thalamus, which relays it to the cortex for perception.
| Feature | A-delta fibers | C fibers |
|---|---|---|
| Myelin | Thin myelin coat | No myelin |
| Speed | Fast | Slow |
| Quality of pain | Sharp, pricking | Dull, aching, burning |
| Where it is felt | Easy to pinpoint | Spread out, hard to pinpoint |
| Timing | First (fast) pain | Second (slow) pain |
Why pain protects us, and what happens when it is gone
All of this machinery exists for one reason: survival. Pain makes you pull back from harm, guard an injured limb, and seek help. It is protective. That is exactly why losing the ability to feel pain is so dangerous. In diabetic peripheral neuropathy, years of high blood glucose damage the small sensory nerves in the feet. The nociceptors and their fibers can no longer sound the alarm. A patient may step on a tack, get a blister from tight shoes, or walk on an open ulcer for days. They have no idea. Without the warning, small injuries go unnoticed, get infected, and can turn into deep wounds or even cost a limb. The lesson for practice is strong. Absent pain is not a blessing but a hazard. That is why we teach daily foot checks and protective shoes for anyone with sensory loss.
Explore the pathway below. Trace a single signal from the moment of injury, up the spinothalamic tract, all the way to conscious perception in the brain.
- Nociceptors are free nerve endings. They spot mechanical, thermal, and chemical stimuli that signal tissue damage. Injury releases prostaglandins and bradykinin, which sensitize them.
- Nociception has four steps: transduction, transmission, perception, and modulation. Each one is a separate target for pain relief.
- A-delta fibers carry fast, sharp pain that is easy to pinpoint. C fibers carry slow, dull, aching pain. Both climb the spinothalamic tract to the brain.
- The body modulates pain by releasing endogenous opioids (endorphins and enkephalins) through descending pathways. That is why opioids and some antidepressants relieve pain.
- Pain is protective. When it is absent, as in diabetic neuropathy, unnoticed foot injuries can turn into ulcers, infection, and amputation. So protective foot care is essential.
Section 2The types of pain
Pain is not a design flaw. In a healthy body it is one of your best-working alarm systems. Special nerve endings called nociceptors sit in your skin, muscles, joints, and organs, waiting quietly. When something threatens to damage tissue, they fire. The signal runs up the spinal cord to the brain, which reads it as "that hurts, do something." This protective alarm makes you pull your hand off a hot stove before you even think. The trouble starts when the alarm rings for the wrong reason, keeps ringing after the danger is gone, or wires itself into a permanent problem. So the first step is knowing what kind of pain you are dealing with. Different pain comes from different places, and it answers to different treatments.
Nociceptive pain: the normal alarm working as it should
Nociceptive pain is the pain of real or threatened tissue damage, picked up by nociceptors. It is the most familiar type. It splits into two flavors, depending on where those nerve endings live.
Somatic pain comes from the "body wall" tissues you can point to, such as skin, muscle, bone, and joints. These areas are packed with nerves and mapped closely in the brain. So somatic pain is usually sharp, throbbing, and easy to place. A sprained ankle or a surgical cut hurts right there, and the patient can put a finger on it.
Visceral pain comes from the internal organs, such as the gut, bladder, and heart. These organs have fewer nociceptors, spread farther apart. Their signals also travel on nerves that share spinal pathways with the skin. So the pain is usually dull, deep, cramping, and hard to place. Patients often say it is "somewhere in my belly." That shared wiring means visceral pain is often referred. In other words, it is felt in a body-wall spot away from the real organ. The classic example is cardiac pain felt in the left arm or jaw. Visceral pain also tends to bring nausea, sweating, and restlessness. It switches on the autonomic nervous system.
| Feature | Somatic | Visceral |
|---|---|---|
| Source | Skin, muscle, bone, joints | Internal organs |
| Quality | Sharp, throbbing, aching | Dull, deep, cramping |
| Where it is felt | Easy to point to | Vague, hard to place |
| Referred? | Rarely | Often (for example, MI to arm or jaw) |
Neuropathic pain: the alarm system itself is damaged
Neuropathic pain is different in kind. The problem is not tissue damage sending a signal. The problem is the wiring itself. The nerves that carry the signal are damaged, or they work wrong. Injured nerves get jumpy and fire on their own. So the alarm sounds with no real threat. Patients reach for electrical, burning words: burning, shooting, stabbing, tingling, or "pins and needles." They may also have allodynia. That is pain from something that should not hurt, like a bedsheet. They may have hyperalgesia too. That is an outsized response to a mildly painful touch. Common causes are diabetic peripheral neuropathy and phantom limb pain after amputation. Sciatica, from a squeezed nerve root, is another. This matters in the clinic. Ordinary painkillers often barely touch it.
Acute versus chronic: how long the alarm rings
Another way to sort pain is by how long it lasts. Acute pain is the protective alarm doing its job. It starts with an injury you can name, it warns you, and it usually clears as the tissue heals. That is typically days to a few weeks. It often brings visible sympathetic signs, such as a faster heart rate, higher blood pressure, and sweating.
Chronic pain is pain that lasts beyond about three months, or past the expected healing time. By then the nervous system can go through central sensitization. It gets better and better at carrying and amplifying pain. So the pain outlives its usefulness and becomes its own disease. Chronic pain often loses the obvious sympathetic signs. Instead it shows up as fatigue, depression, poor sleep, and pulling away from life. Treating it means looking past the original injury to the whole person.
Why the type steers the treatment
Matching the mechanism to the therapy is the whole point of sorting pain. Nociceptive pain usually answers to NSAIDs and acetaminophen. When it is severe, add opioids. Neuropathic pain usually needs anticonvulsants or antidepressants. Those drugs calm overactive nerves. Acute pain is treated hard and briefly, so healing can happen. Chronic pain calls for a multimodal plan. That means medicine plus physical therapy. It also means psychological support and non-drug strategies.
Try the sorter below. Give it the real features of a case and watch it weigh the evidence for each mechanism, then place the pain on the acute to chronic line.
- Nociceptive pain reflects tissue damage. Somatic pain is sharp and easy to place. Visceral pain is dull, hard to place, and often referred.
- Neuropathic pain comes from damaged nerves firing on their own. It feels burning or shooting, and it shows up in diabetic neuropathy, phantom limb, and sciatica.
- Acute pain is protective and clears with healing. Chronic pain lasts beyond about 3 months and becomes its own problem through central sensitization.
- The type of pain guides therapy: NSAIDs and opioids for nociceptive pain, anticonvulsants and antidepressants for neuropathic pain, and multimodal plans for chronic pain.
Section 3How pain is modulated
Here is something strange but true. Pain is not a fixed signal traveling a one-way wire from your finger to your brain. The nervous system is always editing the pain message on its way up. It turns the volume up or down before you ever feel it. This editing is called pain modulation, and it happens at every level, from the spinal cord to the brain. It explains a lot of everyday things. Why rubbing a stubbed toe helps. Why a soldier or an athlete can keep going with a serious injury. And why some people hurt for years after the tissue has fully healed.
The gate control theory: crowding out the pain signal
In 1965, Melzack and Wall proposed the gate control theory, and it still guides pain care today. Picture a gate in the dorsal horn of the spinal cord. Incoming signals compete there for passage to the brain. Pain travels on small, slow fibers: A-delta fibers with a thin myelin coat carry sharp, fast pain, and C fibers with no myelin carry dull, aching, burning pain. Touch, pressure, and vibration travel on large, fast A-beta fibers.
Here is the key idea. When you fire the big A-beta fibers, they switch on inhibitory interneurons in the dorsal horn. Those cells partly close the gate on the pain fibers. The non-painful input literally crowds out some of the painful input. That is the mechanism behind rubbing a bumped elbow, using heat or cold, massage, and TENS (transcutaneous electrical nerve stimulation). TENS sends a mild buzzing current to flood those large fibers and dampen the pain message.
The brain talks back: endogenous opioids and descending inhibition
The gate is not run only from below. The brain also sends signals downward to the spinal cord to quiet pain. That is called descending inhibition. Nuclei in the midbrain (the periaqueductal gray) and the brainstem release neurotransmitters, including serotonin and norepinephrine. These hold back transmission in the dorsal horn. It is also why certain antidepressants (SNRIs and tricyclics) help chronic pain. They boost these descending pathways.
The body also makes its own opioids, called endogenous opioids. The main families are endorphins and enkephalins, plus dynorphins. Each family has a favorite opioid receptor. Endorphins prefer mu, enkephalins prefer delta, and dynorphins prefer kappa. Morphine works mainly at mu, so it pulls on the same brake. These opioids block the release of pain neurotransmitters such as substance P. This is the chemistry behind the calm after hard exercise. It also explains reduced pain during a crisis, and part of why placebo relief is real, not imaginary.
| Feature | Gate closes (less pain) | Gate opens (more pain) |
|---|---|---|
| Fiber activity | Large A-beta touch fibers firing | A-delta and C pain fibers firing |
| From the brain | Descending inhibition is working | Descending pathways are weak or worn out |
| Chemistry | Endorphins, enkephalins, serotonin, norepinephrine | Substance P, glutamate |
| State of mind | Relaxed, distracted, hopeful | Anxious, worn out, focused on the pain |
| Levers | Heat or cold, massage, TENS, distraction, opioids | Untreated anxiety, poor sleep, fear |
When the volume knob gets stuck: central sensitization and wind-up
Normally, modulation keeps pain in proportion to the injury. But pain signaling can run hard, over and over. Then the nervous system starts to amplify itself. Fast, repeated firing of C fibers causes wind-up. Each stimulus triggers a bigger response in dorsal horn neurons than the one before. This often runs through too much NMDA receptor activity, driven by glutamate. Over time it settles into central sensitization. The spinal cord and brain turn up their own gain, and they stay over-responsive.
Two classic signs follow. In hyperalgesia, a painful stimulus hurts far more than it should. In allodynia, something that should not hurt at all is felt as pain. A bedsheet, a light touch, or a breeze can do it. These are not exaggeration or drug-seeking. They are the fingerprint of a sensitized nervous system.
Why chronic pain outlasts the injury
This is the crux of chronic pain. Once central sensitization is set, the nervous system keeps making pain. It does this even after the tissue has healed. The alarm keeps ringing after the fire is out. Several things drive it. Dorsal horn wiring changes for good. Descending inhibition weakens. And pain-processing brain regions remodel. So chronic pain is now seen as a disease of the nervous system in its own right. It is usually defined as pain lasting more than about three months. It is not simply ongoing tissue damage. That also explains why it needs a broad plan. SNRIs or tricyclics help. So do gabapentinoids, graded activity, thinking strategies, and good sleep. Opioids alone are not the answer. The problem lives largely in the modulation system itself.
Work the gate below. Change the touch input, the state of mind and the strength of the brake, then fire a run of fast volleys and watch wind-up build.
- Pain is modulated, not fixed. The spinal cord and brain turn the signal up or down before you feel it.
- Gate control: large A-beta touch fibers can close the spinal gate on A-delta and C pain fibers. That is why rubbing, heat or cold, and TENS help.
- The brain fights back. Descending inhibition plus endogenous opioids (endorphins and enkephalins), serotonin, and norepinephrine hold pain back in the dorsal horn.
- Central sensitization and wind-up turn up the nervous system’s own volume. That produces hyperalgesia and allodynia.
- Chronic pain can last after healing, because the sensitized nervous system keeps sounding the alarm. So it often needs a multimodal plan that is not centered on opioids.
Section 4Referred pain & special patterns
Normally your brain is very good at telling you where something hurts. A nerve carries a pain signal from one spot, reaches a set level of the spinal cord, and your brain reads the return address and points to the right place. This mapping is usually right for skin and muscle, which have dense, well-ordered sensory nerves. But some pain does not follow the rules. Knowing why helps you catch dangerous problems and treat pain you cannot easily see.
Referred pain: the crossed-wire problem
Referred pain is pain felt in a body area away from the organ that is causing it. Here is the classic example. A heart attack (myocardial infarction) often hurts in the left arm, jaw, neck, or shoulder rather than only the chest. Why? The nerves carrying pain from the heart enter the spinal cord at the same segments, roughly T1 to T4, as the nerves from the skin of the arm and chest wall. This is called convergence. Visceral (organ) signals and somatic (skin) signals share the same second-order neurons on the way up. Your brain has spent your whole life feeling your arm and almost never feeling your heart. So when a shared pathway fires, it guesses the familiar source and projects the pain out to the skin.
Organs give vague pain that is hard to place, because their sensory nerves are sparse. That is why visceral pain is often called deep, dull, cramping, or squeezing. Somatic pain from skin or bone is sharp and easy to pinpoint. Knowing the common referral patterns is a safety skill. Diaphragm irritation refers to the shoulder tip. Gallbladder pain refers to the right shoulder or scapula. Cardiac pain refers to the left arm or jaw.
Phantom limb pain
After an amputation, many people still feel the missing limb. A large share feel pain in it. It can burn, cramp, or shoot. This is phantom limb pain. The limb is gone. But the nerves and the spinal cord are still there. So is the brain’s somatosensory map that once served it. Cut nerve endings can form tangles called neuromas that fire on their own. The spinal cord becomes over-excitable, which is central sensitization. And the brain’s map rewires. It may then read nearby signals as coming from the lost limb. It is real neuropathic pain, not imagination. Saying so to the patient matters. Treatments target the nervous system. They include gabapentin and certain antidepressants. Mirror therapy helps too. It uses the reflection of the intact limb to help the brain remap.
Assessing pain when the person cannot tell you
Pain is whatever the person says it is. But some people cannot say. Infants, patients who are sedated or intubated, and people with advanced dementia or thinking problems need behavioral (observational) pain scales. You watch the body instead of asking for a number.
| Population | Tool | What you watch |
|---|---|---|
| Older adult who cannot speak, or has dementia | PAINAD | Breathing, sounds, face, body language, how easily they settle |
| Critically ill or intubated adult | CPOT or BPS | Face, muscle tension, how they take the ventilator |
| Infant or young child | FLACC | Face, Legs, Activity, Cry, Consolability |
Look for grimacing, guarding, restlessness, moaning, or a stiff body. Also watch for physiologic clues, though these get less reliable over time: a higher heart rate, blood pressure, and breathing rate. Think about the situation too. If a procedure or condition would hurt you, assume it hurts them, and treat it.
Why pain is under-treated in older adults
Older adults often get too little pain medicine. It usually comes from several barriers stacked up, not one cause:
- Communication gaps: dementia, aphasia, or delirium make self-report hard, so pain gets missed.
- False beliefs: patients and staff may both assume pain is a normal part of aging, so no one treats it.
- Toughing it out and fear: older patients may under-report to avoid being a burden. Others fear addiction and side effects.
- Prescriber caution: real worries about falls, confusion, kidney function, and drug interactions make clinicians hold back. Sometimes they hold back too far.
Untreated pain is not harmless. It drives delirium, poor sleep, and staying still. Staying still raises the risk of pneumonia, pressure injuries, and clots. It also drives depression and slower recovery. The goal is honest, up-front assessment with the right tool, then pushing for enough relief, carefully titrated.
Open the map below. Pick an organ, see which patch of skin lights up, and read the spinal levels the two have in common. Tap a patch to run it backward.
- Referred pain happens because visceral and somatic nerves meet at the same spinal segment. Cardiac pain classically refers to the left arm, jaw, or shoulder.
- Learn the common referral patterns. Treat atypical signs, such as jaw pain, nausea, or trouble breathing, as a possible MI, above all in women, older adults, and people with diabetes.
- Phantom limb pain is real neuropathic pain. It comes from neuroma firing, central sensitization, and remapping in the cortex. Mirror therapy and neuropathic drugs help.
- When patients cannot self-report, use behavioral scales: FLACC for infants, PAINAD for dementia, and CPOT or BPS for the critically ill. Watch the face, the body, and how easily they settle.
- Pain in older adults is often under-treated, because of communication barriers and false beliefs. Untreated pain fuels delirium, loss of movement, and complications. So assess early and speak up.
Section 5Assessing & managing pain
Pain is your body’s alarm system, and it usually does an important job. When tissue is threatened or damaged, special nerve endings called nociceptors fire. The signal runs up the spinal cord to the brain, where it is read as "that hurts." This pathway has four parts: transduction, transmission, perception, and modulation. It is protective. It makes you pull your hand off a hot stove, and guard a sprained ankle so it can heal. The trouble is that the alarm is invisible. You cannot see it on a monitor or draw it in a tube. That is exactly why pain is one of the hardest things to assess.
Pain is whatever the patient says it is
The guiding rule is that pain is a subjective, self-reported experience. Margo McCaffery’s classic definition still holds. Pain is whatever the person says it is, and it exists whenever they say it does. Two people with the same surgery can report a 3 and a 9, and both are right. Pain is shaped by nerves and by fear, culture, past experience, and mood. So we ask the patient instead of guessing.
To turn that report into something we can track, we use rating scales. The tool has to match the patient in front of you.
- 0-10 Numeric Rating Scale: for alert adults who can think in numbers. Zero is no pain, ten is the worst you can imagine.
- Wong-Baker FACES: cartoon faces from smiling to crying. It is useful for young children, usually around age 3 and up, or for anyone who struggles with numbers.
- FLACC: a behavior score (Face, Legs, Activity, Cry, Consolability) for infants and children too young to self-report.
- PAINAD: Pain Assessment in Advanced Dementia. It reads breathing, sounds, face, body language, and how easily the person settles, in older adults who cannot speak.
Whichever scale you pick, keep using the same one for that patient, so the numbers can be compared. Pair the score with a fuller assessment such as OLDCARTS or PQRST: location, quality, radiation, timing, and what makes it better or worse.
Climbing the WHO analgesic ladder
The World Health Organization (WHO) analgesic ladder is a simple, stepwise plan. It matches drug strength to pain intensity. It was built for cancer pain, but the logic guides much of pain management. WHO withdrew the three-step ladder in 2018. It is still kept as a teaching frame, because the stepwise idea is sound.
- Step 1, mild pain: non-opioid analgesics such as acetaminophen or NSAIDs, with or without an adjuvant. An adjuvant is a helper drug, like an antidepressant or anticonvulsant for nerve pain.
- Step 2, moderate pain: add a weak opioid, for example codeine or tramadol, to the non-opioid.
- Step 3, severe pain: a strong opioid such as morphine, hydromorphone, or fentanyl, still combined with non-opioids and adjuvants.
Two ideas make the ladder work. Use multimodal analgesia, which means drugs that attack pain by different mechanisms, so you need less of any one. And dose around the clock for constant pain, instead of waiting for it to spike.
Non-opioids vs opioids
Non-opioids work mostly at the site of injury. NSAIDs (ibuprofen, ketorolac, naproxen) block cyclooxygenase (COX) enzymes. So less prostaglandin is made, and the nociceptors quiet down. This also fights inflammation. But it can irritate the stomach lining and stress the kidneys. Acetaminophen works in the brain instead. It relieves pain and fever, with little effect on inflammation. It carries no risk of GI bleeding, which matters. But too much can harm the liver, which is called hepatotoxicity. The usual limit is about 4 grams a day. Opioids act differently. They bind mu receptors in the brain and spinal cord. That dampens how pain is carried and felt. They are powerful, and they have no organ-damaging ceiling. But they carry serious risks.
| Feature | Non-opioids | Opioids |
|---|---|---|
| Main site of action | At the injury site; acetaminophen acts more centrally | Central mu receptors (brain, spinal cord) |
| Dose ceiling | Yes, a max daily dose to protect liver, gut, and kidney | No true ceiling; titrate to effect |
| Key risks | GI bleed and kidney injury (NSAIDs); liver damage (acetaminophen) | Respiratory depression, constipation, sedation, tolerance, dependence |
| Best for | Mild pain, inflammation, fever | Moderate to severe pain |
The opioid risk you watch hardest is respiratory depression. Mu receptors in the brainstem blunt the drive to breathe. So an over-sedated patient breathes slowly and shallowly. That happens before the rate ever crashes. Rising sedation is the early warning sign. Check level of consciousness and breathing rate. Keep naloxone, the opioid blocker, close by. Nearly every patient also gets constipation. Mu receptors in the gut slow it down. So a bowel plan starts alongside the opioid. Over time patients may build tolerance. That means they need more drug for the same relief. They may also build physical dependence. That means withdrawal if the drug stops suddenly. Both are normal body adaptations. Neither is the same as addiction, which is compulsive use despite harm.
Non-drug methods
Medicine is not the whole plan. Non-drug measures work through the gate control theory. Competing signals and input from the brain can partly "close the gate" in the spinal cord, so less pain reaches awareness. Cold numbs, slows nerve conduction, and eases swelling in fresh injuries. Heat relaxes muscle and boosts blood flow for stiffness and cramping. Positioning and support take the load off strained tissue. Distraction, guided imagery, music, and relaxation or slow breathing lower anxiety and muscle tension, which turns the pain volume down. These pair with drugs, and they often let you use lower doses.
Build a plan below. Pick the classes, set the relative dose and the route, and watch relief and risk move together across twelve hours.
- Pain is subjective and self-reported. Believe the patient, and match the scale to them: 0-10 for alert adults, FACES for children, FLACC for the preverbal, PAINAD for advanced dementia.
- The WHO ladder steps from non-opioids up to strong opioids. Use multimodal, around-the-clock dosing for constant pain.
- Non-opioids act mostly at the injury site and have organ-based dose ceilings (NSAIDs: gut and kidney; acetaminophen: liver). Opioids act centrally on mu receptors with no true ceiling.
- Watch opioids for respiratory depression. Rising sedation is the earliest sign. Expect constipation, tolerance, and dependence, and keep naloxone ready.
- Non-drug methods (heat or cold, positioning, distraction, relaxation) work through gate control. They let you reach comfort with lower drug doses.
The chapter in one breath
- Nociception has four steps. In transduction, tissue damage releases prostaglandins, bradykinin, and substance P, which fire the nerve ending. Then comes transmission up the spinal cord, perception in the brain, and modulation, which dials the signal up or down.
- Fast, sharp pain that is easy to place travels on myelinated A-delta fibers. Dull, aching pain that is hard to place crawls along unmyelinated C fibers. That is why you feel a pinprick before the throb.
- Nociceptive pain comes from real tissue injury. Somatic pain is sharp and easy to place, visceral pain is deep and cramping. Neuropathic pain comes from nerve damage itself, and feels burning, shooting, or electric.
- The gate control theory explains why rubbing a bump helps. Large A-beta touch fibers "close the gate" in the dorsal horn and block the smaller pain fibers. Heat, massage, and TENS use the same principle.
- Descending modulation from the brainstem releases the body's own endogenous opioids (endorphins and enkephalins), plus serotonin and norepinephrine, to quiet pain signals naturally.
- Referred pain is felt away from its source, because visceral and somatic nerves meet on the same spinal segment. The classic case is cardiac pain spreading to the left arm or jaw.
- Pain is subjective, so the standard is "whatever the patient says it is." Use a validated tool (0–10 numeric, Wong-Baker FACES, or the behavioral FLACC/PAINAD for patients who cannot speak) plus a full OLDCARTS/PQRST assessment.
- Treat pain with a multimodal, stepwise plan, the WHO ladder. Pair non-opioids like acetaminophen and NSAIDs with adjuvants, and add opioids only as needed, to reach the lowest dose that works.
- The most dangerous opioid side effect is respiratory depression. Watch for a rate < 12 and rising sedation, since sedation comes before respiratory depression. Keep naloxone ready, and manage the near-universal constipation up front.
Pull the whole chapter together below. Every answer updates a mastery estimate for its section, so the thin spots show themselves.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- A-delta fiber
- A thin nerve fiber with a myelin coat that carries pain signals fast. It brings the sharp "first pain," easy to place, that you feel the instant you touch something harmful.
- Analgesic
- Any drug or agent that relieves pain without putting you to sleep, such as acetaminophen, NSAIDs, or opioids.
- C fiber
- A small nerve fiber with no myelin that carries pain slowly. It brings the dull, aching "second pain" that is hard to place and lingers after an injury.
- Central sensitization
- A state in which the central nervous system becomes over-excitable and amplifies pain signals. Even stimuli that should not hurt begin to hurt. It is often part of chronic pain.
- Endorphin
- An opioid-like chemical the body makes on its own. It binds opioid receptors, blocks pain transmission, and brings a sense of relief or well-being.
- Gate control theory
- The idea that the spinal cord holds a nerve "gate." Non-painful input, such as rubbing the skin, can close that gate and cut how many pain signals reach the brain.
- Modulation
- The fourth step of pain processing. The body dampens or boosts pain signals along the pathway, often by releasing its own chemicals such as endorphins and serotonin.
- Neuropathic pain
- Pain caused by damage to the nerves themselves, or by a fault in how they work. It is usually described as burning, shooting, tingling, or "pins-and-needles."
- Nociceptor
- A special sensory nerve ending that spots real or possible tissue damage. It starts the pain signal on its way to the spinal cord and brain.
- Perception
- The third step of pain processing. The brain becomes aware of the pain and gives it meaning, strength, and emotional weight.
- Phantom limb pain
- Pain that feels as if it comes from a body part that has been amputated. It is thought to come from nerves and the brain still signaling after the limb is gone.
- Referred pain
- Pain felt in a body area away from its real source, such as jaw or left-arm pain during a heart attack. It happens because sensory nerves share spinal cord pathways.
- Somatic pain
- Pain from the skin, muscles, bones, or joints. It is usually sharp, aching, and easy to pinpoint.
- Transduction
- The first step of pain processing. A harmful stimulus (heat, pressure, or chemicals) is turned into an electrical nerve impulse at the nociceptor.
- Transmission
- The second step of pain processing. The electrical impulse travels from the injury site along nerve fibers to the spinal cord and up to the brain.
- Visceral pain
- Pain from the internal organs. It is typically dull, cramping, or squeezing, hard to place, and often comes with nausea or sweating.
DrillFlashcards for this unit
These are the Week 4 cards. They are the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
Neurology
The nervous system is the body’s command center. When it fails, the stakes are immediate. Minutes decide the outcome of a stroke. Rising pressure inside the skull can be deadly. This chapter walks through the major neurologic emergencies and diseases. You will cover stroke, raised intracranial pressure, head and spinal trauma, seizures, and the slow diseases that wear down the brain and nerves.
By the end of this chapter you can
- Tell an ischemic stroke from a hemorrhagic one, and use FAST.
- Explain raised intracranial pressure, the Monro-Kellie doctrine, and Cushing’s triad.
- Compare an epidural and a subdural hematoma, and know where a spinal cord injury does the most harm.
- Describe the seizure types, status epilepticus, and how to keep a person safe.
- Contrast Alzheimer, Parkinson, MS, myasthenia gravis, and Guillain-Barre.
Section 1Stroke
Your brain is the hungriest organ you have. It is only about 2 percent of your body weight. Yet it uses roughly 20 percent of your oxygen and glucose. It also has almost no way to store fuel of its own. So brain tissue needs a constant supply of oxygen-rich blood, second by second. That blood arrives through the carotid and vertebral arteries. When the supply stops, neurons cannot switch to a backup plan the way muscle can. Within minutes they start to fail. Soon after, they start to die. That is just what a stroke is. Blood flow to part of the brain stops suddenly, so that region loses its function. Another name for it is a cerebrovascular accident, or CVA.
Two ways the flow fails: ischemic vs hemorrhagic
Two very different problems can starve brain tissue. Telling them apart drives everything you do next. Explore the figure below to see them side by side.
An ischemic stroke is a plumbing blockage. A vessel gets clogged, and the tissue past the clog is cut off. This is by far the most common type. It makes up about 87 percent of strokes. Hemorrhagic strokes make up the other 13 percent or so. The clog comes in two forms. In a thrombotic stroke, a clot forms right there in a brain artery, on top of atherosclerotic plaque. Plaque is a fatty buildup in the vessel wall. In an embolic stroke, the clot forms somewhere else and travels. It is often a piece thrown from the heart during atrial fibrillation. It rides the bloodstream and lodges in a smaller brain vessel.
A hemorrhagic stroke works the other way. It is a leak. A weak or overstretched vessel ruptures and bleeds into or around the brain. Now two injuries happen at once. The tissue past the rupture loses its blood flow. And the escaping blood forms a mass. That mass raises intracranial pressure and irritates nearby tissue. Long-standing hypertension and ruptured aneurysms are common causes. Hemorrhagic strokes are less common, but they are often more deadly.
| Feature | Ischemic (~87%) | Hemorrhagic |
|---|---|---|
| Core problem | A blockage; a clot cuts off flow | A bleed; the vessel ruptures |
| Common causes | Atherosclerosis (thrombotic), A-fib emboli (embolic) | Hypertension, ruptured aneurysm |
| Clot-buster tPA | Can help if given in time | Never give it; absolutely contraindicated |
| Typical headache | Often mild, or none at all | Often sudden and severe, the "worst of my life" |
The penumbra, and why time is brain
When an artery blocks, the tissue at the center of the blocked zone dies fast. Around that dead core sits a rim of tissue. It is called the ischemic penumbra. These neurons are starving and silent, so they have stopped working. But they are not yet dead. Trickles of blood from nearby vessels keep them barely alive. This rim is the whole reason we rush. Restore the flow fast and those neurons can wake back up. The deficit can then shrink. Wait too long and the rim you could have saved turns into dead tissue for good.
Experts figure the brain loses about 1.9 million neurons every minute that an ischemic stroke goes untreated. That rate is why we say time is brain. Every minute of delay is brain tissue you cannot get back.
Recognizing it fast: FAST
Because minutes matter, there is a quick screen called FAST:
- F - Face: Ask the person to smile. Does one side droop?
- A - Arm: Ask them to raise both arms. Does one drift downward?
- S - Speech: Is speech slurred, absent, or strange? Can they repeat a simple sentence?
- T - Time: If you see any of these, note the time the symptoms began. Then call for emergency help right away.
That last letter is easy to skip. It may be the most important one. Whether a patient can get treatment rests on knowing when the patient was last known well.
Why the CT scan comes before the clot-buster
The main clot-dissolving drug is tPA (tissue plasminogen activator, also called alteplase). It works beautifully on a clot. But it is a clot-dissolving (thrombolytic) drug. If the stroke is really a bleed, tPA pours fuel on the fire. It would make the hemorrhage much worse. Here is the catch. Ischemic and hemorrhagic strokes can look the same. You cannot tell them apart by symptoms alone.
That is why an emergency non-contrast CT scan of the head comes first, every time. Its main job is to rule out a bleed. Only after blood is ruled out can tPA be considered. Even then the window is strict. For patients who qualify, it is usually within 3 to 4.5 hours of symptom onset. Some patients also qualify for a mechanical thrombectomy. There the clot is pulled out by hand, and the window is longer.
Which side, which deficit
Motor nerve tracts cross over in the lower medulla. That crossing is called the pyramidal decussation. So a stroke on one side of the brain causes weakness on the opposite (contralateral) side of the body. A right-brain stroke causes left-sided weakness. A left-brain stroke causes right-sided weakness. Language adds another twist. In most people the language centers sit in the left hemisphere. So a left-brain stroke often causes aphasia, which is trouble making or understanding language. It comes along with right-sided weakness. A right-brain stroke more often spares speech. But it may cause left-sided neglect, where the patient ignores their affected side completely.
- Ischemic strokes (~87%) are blockages, either thrombotic or embolic. Hemorrhagic strokes are bleeds. The treatment for one would harm the other.
- The ischemic penumbra is tissue you can still save around the dead core. Fast blood flow rescues it. That is why time is brain.
- Screen quickly with FAST: Face droop, Arm drift, Speech trouble, Time to call for help and note onset.
- A non-contrast CT must rule out a bleed before tPA, because the clot-buster would make a hemorrhage worse. tPA is usually given within 3 to 4.5 hours of onset.
- Deficits are contralateral, which means on the opposite side. A left-brain stroke often causes aphasia plus right-sided weakness.
Section 2Raised intracranial pressure
Picture the brain as a delicate organ inside a hard, sealed box. That box is the skull. In a healthy person the box holds three things, and they share the space in a careful balance. There is the brain tissue itself, about 80% of the volume. There is the blood in its vessels, about 10%. And there is the clear cerebrospinal fluid (CSF) that cushions and bathes it, also about 10%. The skull cannot stretch, so the total volume inside is fixed. The gentle pressure these three create is the intracranial pressure (ICP). Normally it sits around 5 to 15 mmHg.
The Monro-Kellie doctrine: a box that cannot expand
One rule governs all of this. It is the Monro-Kellie doctrine. The skull is a rigid, fixed container. So the three volumes inside must always add up to the same total. If one grows, another has to shrink to make room. If neither shrinks, the pressure climbs. At first the brain is clever about this. It buys time through compensation. It shunts CSF down into the spinal canal. It also squeezes some venous blood out of the skull. That is why a slow-growing problem can stay quiet for a while. But this wiggle room runs out. Once those buffers are used up, even a tiny added volume sends the pressure up steeply. The patient falls off a compensation cliff. Now small changes cause big, dangerous swings in ICP.
What raises the pressure
Anything that adds volume to that sealed box can raise ICP. The usual causes line up with the three normal contents, plus a few new intruders:
- Bleeding (hemorrhage) - an epidural, subdural, subarachnoid, or intracerebral bleed adds a pool of blood that takes up space.
- Tumor (mass lesion) - a growing mass literally crowds out brain, blood, and CSF.
- Cerebral edema - swelling of the brain tissue itself. Fluid leaks into or around the cells. It often follows trauma, a stroke, or an infection.
- Hydrocephalus - a backup of CSF. The body makes too much, the flow is blocked, or it is not taken back up. Fluid then builds up in the ventricles.
The earliest warning: a change in consciousness
Here is the single most important point. The earliest and most sensitive sign of rising ICP is a change in level of consciousness (LOC). The brain's alertness centers react fast to pressure and to falling oxygen. So before anything dramatic happens, the patient just seems different. They may be restless, confused, drowsy, hard to wake, slow to answer, or newly agitated. Families often notice it first ("she's just not herself"). Trust that. A falling Glasgow Coma Scale (GCS) score is your red flag. It comes long before the classic textbook signs. Do not wait for the pupils to change.
Cushing's triad: the late, ominous sign
The pressure inside the skull can rise high enough to threaten blood flow to the brainstem. Then the body tries one last rescue. To keep pushing blood past that crushing pressure, it drives the systolic blood pressure up. Baroreceptors sense the surge. They reflexively slow the heart, which gives bradycardia. At the same time, the pressure squeezes the brainstem's respiratory centers. Breathing turns irregular, as in Cheyne-Stokes breathing. Those three signs together make up Cushing's triad. It is a late and grave finding. It tells you the brainstem is in trouble.
| Feature | Early rising ICP | Cushing's triad (late) |
|---|---|---|
| Consciousness | Mild confusion, restlessness, drowsiness, a falling GCS | Deeply obtunded, meaning barely rousable, or in a coma |
| Blood pressure | Often normal | Rising systolic with widening pulse pressure |
| Heart rate | Often normal | Bradycardia |
| Breathing | Usually normal | Irregular (e.g., Cheyne-Stokes) |
| Meaning | Act now; it can still be turned around | The brainstem is in trouble; herniation is near |
Herniation: the feared end result
If the pressure is not relieved, the brain gets forced across its normal walls. It may push under the falx, across the tentorial notch, or down through the foramen magnum at the base of the skull. This shift of brain tissue past its normal borders is called herniation. As tissue is pushed down, it crushes the brainstem, which runs breathing, heart rate, and consciousness. The results are catastrophic. You see a fixed, dilated pupil on the affected side, from pressure on cranial nerve III. Protective reflexes are lost. Breathing stops, and the patient dies. Herniation is where untreated intracranial hypertension ends up. Everything above is about catching the problem long before this point. Explore the figure below to see how a growing volume drives the pressure up and pushes the brain toward herniation.
- The Monro-Kellie doctrine: the skull is a fixed box holding brain, blood, and CSF. When one volume grows, another must shrink, or ICP rises. Compensation buys time, then fails sharply.
- Common causes are a bleed, tumor, cerebral edema, or hydrocephalus - anything that adds volume to the sealed skull.
- The earliest sign is a change in level of consciousness (restlessness, confusion, drowsiness, a falling GCS). Act on it early.
- Cushing's triad - rising systolic BP with a widening pulse pressure, bradycardia, and irregular breathing - is a late, ominous sign that the brainstem is in trouble.
- Herniation, brain tissue forced through the foramen magnum onto the brainstem, is the feared and often fatal end result.
Section 3Brain & spinal cord injury
Your brain is soft, delicate tissue. It floats inside a hard, unforgiving skull, cushioned by a thin layer of cerebrospinal fluid. That fluid normally works like a shock absorber. But in trauma the same skull that protects your brain becomes the problem. The brain can slam against the bone. And swelling has nowhere to go. That is why head injuries are so dangerous. The box is sealed, so any extra blood or swelling presses on the brain itself.
Concussion vs contusion, and the coup-contrecoup pattern
A concussion is a functional injury. The brain gets shaken hard enough to upset how neurons signal. But a scan usually shows no bleeding and no bruising. Patients often have a brief loss of consciousness, confusion, headache, and amnesia around the event. A contusion is a step worse. It is a real bruise of brain tissue, with capillary bleeding and swelling you can often see on CT. Contusions can grow over hours, so repeat neuro checks matter.
A coup-contrecoup injury often causes both. Picture a moving head striking a dashboard. The brain first bruises right under the point of impact. That is the coup. Then it rebounds and slams into the other side of the skull. That is the contrecoup. One blow, two injured areas.
Bleeding between the layers: epidural vs subdural hematoma
Three membranes wrap the brain. The tough outer one is the dura mater. The middle one is the arachnoid. The delicate pia mater lies right against the brain. Two things change how fast the patient crashes. One is where the blood collects. The other is which vessel is torn.
An epidural hematoma is bleeding above the dura. The classic source is a torn middle meningeal artery after a temporal skull fracture. It is arterial, so it fills fast under high pressure. The textbook picture is a lucid interval. The patient is knocked out. Then they wake up and seem fine. Then they go downhill fast, as the clot grows and presses on the brain. This is a neurosurgical emergency.
A subdural hematoma is bleeding below the dura, from torn bridging veins. It is venous, so it oozes slowly. Symptoms can take hours, days, or even weeks to show up. It is common in older adults and in people with chronic alcohol use. In both, brain atrophy stretches those bridging veins and leaves them fragile.
| Feature | Epidural hematoma | Subdural hematoma |
|---|---|---|
| Vessel | Artery (middle meningeal) | Bridging veins |
| Speed | Fast, high pressure | Slow ooze |
| Classic clue | A lucid interval, then a decline | Slow symptoms that come and go |
| Typical patient | Temporal skull fracture | Older adults, chronic alcohol use |
Spinal cord injury by level
The spinal cord is the main data cable between the brain and the body. Where it is damaged sets what is lost below that point, because signals can no longer travel past the injury. As a rule, the higher the injury, the more of the body is affected.
- Lumbar/sacral injuries may affect the legs, bladder, and bowel.
- Thoracic injuries can cause paraplegia, loss of function in the legs and lower trunk.
- Cervical injuries can cause tetraplegia (quadriplegia), affecting all four limbs.
The scariest zone is the high cervical cord. The line to memorize is "C3, C4, C5 keep the diaphragm alive." The phrenic nerve drives the diaphragm, and it comes off those levels. An injury at or above C3-C5 can paralyze the diaphragm. Then the patient cannot breathe on their own and needs a ventilator right away. That is why airway and breathing come first in any suspected cervical injury.
Two shock states to keep straight
Spinal shock comes right after trauma. All reflexes, movement, and feeling below the injury drop out for a time. Think of the cord as stunned. It can last days to weeks. Neurogenic shock is a circulatory problem. A high injury wipes out sympathetic tone, so vessels cannot hold their squeeze. That gives the classic triad of hypotension, bradycardia, and warm dry skin. The circulatory instability usually runs one to three weeks. Autonomic dysreflexia shows up later. It is a dangerous, overblown reflex in injuries at or above T6. A full bladder or bowel usually sets it off. Blood pressure spikes suddenly, and that is a true emergency.
Explore the figure below to see how these head injuries take shape.
- Concussion is functional, with no bleeding. Contusion is a true bruise. Coup-contrecoup hurts both the impact site and the opposite side.
- Epidural is arterial and fast, with the classic lucid interval. Subdural is venous and slower. It is common in older adults and in people with chronic alcohol use.
- Higher spinal injuries affect more of the body. A C3-C5 injury threatens the phrenic nerve and the diaphragm, so breathing is the priority.
- Spinal shock is a short-term loss of reflexes. Neurogenic shock is hypotension with bradycardia. Autonomic dysreflexia is a dangerous BP spike at or above T6.
Section 4Seizures & epilepsy
To understand a seizure, start with the normal brain. Your neurons talk to each other all day with tiny electrical signals. In health that chatter is coordinated but not synchronized. Different regions fire at different times for different jobs. Think of a huge orchestra, where each section plays its own part. A tug-of-war keeps that balance. On one side are excitatory signals, mostly the neurotransmitter glutamate, which says "fire." On the other side are inhibitory signals, mostly GABA, which says "settle down." As long as the balance holds, the brain hums along smoothly.
A seizure happens when that balance breaks. A group of neurons suddenly fires all at once. It is a burst of abnormal, hypersynchronous electrical activity. Hypersynchronous means they all fire in lockstep. Instead of the orchestra playing its parts, every instrument blasts the same note. The outward signs depend on where this starts and how far it spreads. Keep one difference clear. A seizure is a single event. Epilepsy is a chronic condition. It is a tendency toward recurrent, unprovoked seizures. It is usually diagnosed after two or more, or after one seizure plus a high risk of another.
Focal vs. generalized: where the storm begins
Seizures are grouped by where the abnormal firing starts. A focal seizure begins in one area of one hemisphere. The older term for it was partial. Only part of the brain is involved, so the signs match that region. You may see a twitching hand, an odd smell, a rising feeling in the stomach, or a spell of staring and confusion. The person may stay aware (focal aware). Or their awareness may change (focal impaired awareness). A focal seizure can also spread and become generalized.
A generalized seizure involves both hemispheres from the start. So consciousness is lost right away. The two you will see most on exams are tonic-clonic and absence.
| Feature | Tonic-clonic (generalized) | Absence |
|---|---|---|
| Classic look | Stiffening then rhythmic jerking | Brief blank staring spell |
| Phases | Tonic (muscles rigid) then clonic (rhythmic jerks) | No motor phases; the eyelids may flutter |
| Duration | Usually 1 to 3 minutes | Often 5 to 10 seconds |
| Awareness | Lost, and the person falls | Lost for a moment, with no fall |
| After the event | Postictal confusion, fatigue, sore muscles | Goes right back to the task, often unaware |
| Typical patient | Any age | Often school-age children |
In a tonic-clonic seizure you may also see cyanosis, a blue tint from pauses in breathing during the tonic phase. Tongue-biting and loss of bladder control are common too. Whole-brain firing overrides normal muscle and autonomic control, which explains all of it. Absence seizures are so short that people mistake them for daydreaming. That is why a child who seems "not to be paying attention" sometimes turns out to be seizing dozens of times a day.
What sets a seizure off: common triggers
Two kinds of things lower the seizure threshold. One is anything that pushes the brain toward excitation. The other is losing something that was calming it:
- Fever in young children - rapid temperature spikes cause febrile seizures, usually between 6 months and 5 years.
- Low sodium (hyponatremia) or low glucose (hypoglycemia) - with a low sodium the blood outside the cells is dilute, so water moves into brain cells by osmosis and the brain swells. That swelling is what sets the seizure off. A low glucose is different. It starves neurons of the fuel they need to hold a steady membrane.
- Missed antiseizure medication - the drug level that was calming the brain falls too low. This is the most common reason a person with epilepsy breaks through.
- Alcohol withdrawal - alcohol holds the brain down. Stop it suddenly and the brain rebounds into a hyperexcitable state.
- Others: sleep deprivation, flashing lights, and infections such as meningitis.
Status epilepticus: the emergency
Status epilepticus is a seizure that lasts 5 minutes or longer. It also counts when seizures repeat without full recovery of consciousness in between. This is a true neurologic emergency. Nonstop firing burns through oxygen and glucose faster than the brain can supply them. The steady muscle activity drives the temperature up and can injure neurons. The result is hypoxia, acidosis, and lasting damage. Treatment is fast IV benzodiazepines, such as lorazepam, plus airway support.
Priorities during a seizure
Your job is protection, not stopping the seizure itself. You cannot switch off the electrical activity by hand. So focus on preventing injury:
- Protect the airway and head - turn the person on their side, the recovery position. That lets secretions drain and lowers the risk of aspiration. Cushion the head and clear away nearby hazards.
- Do not restrain - holding the limbs down can cause fractures or dislocations. Let the movements run their course.
- Nothing in the mouth - never put in objects or fingers. You risk broken teeth, bites, and a blocked airway.
- Time it - note the start time. If it reaches 5 minutes, treat it as status epilepticus and get help.
- Stay and observe - loosen tight clothing and give the person privacy. Write down what you saw for the provider: the movements, how long it lasted, and any incontinence.
Tip the balance yourself in the figure below, then watch the trace and the clock.
- A seizure is a burst of abnormal, hypersynchronous electrical firing. Epilepsy is a tendency toward recurrent, unprovoked seizures.
- Focal seizures start in one area, so the signs match that region. Generalized seizures involve both hemispheres. Tonic-clonic means stiffen then jerk, with postictal confusion. Absence means a brief staring spell, common in children.
- Common triggers lower the seizure threshold: fever in children, low sodium or glucose, missed medication, and alcohol withdrawal. Correct the cause you can fix.
- Status epilepticus is a seizure of 5 minutes or longer, or back-to-back seizures with no recovery. It is an emergency. It needs IV benzodiazepines and airway support.
- During a seizure: turn side-lying to protect the airway, cushion the head, do NOT restrain or put anything in the mouth, and time it.
Section 5Neurodegenerative disease
Your brain runs on about 86 billion neurons. Here is the humbling part. You were born with nearly all of them, and adult brains make very few new ones. Neurons are not like skin or blood cells, which replace themselves all the time. Neurons are built to last a lifetime. That is exactly why the diseases in this section are so devastating. When these cells die, the body usually cannot grow replacements. The losses stack up, so the damage is progressive and irreversible. Picture a city slowly losing its power lines, one by one, with no crew coming to fix them.
Healthy neurons keep themselves tidy. They fold their proteins the right way. They clear out cell garbage. And they pass chemical messages, called neurotransmitters, across tiny gaps called synapses. Each neurodegenerative disease is a different way this housekeeping and signaling breaks down. Each one hits a different neighborhood of the nervous system.
Alzheimer disease: the memory system clogs first
Alzheimer disease is the most common cause of dementia. The trouble is misfolded protein. Two abnormal proteins build up. Beta-amyloid plaques collect in the spaces between neurons. Tau tangles, also called neurofibrillary tangles, twist up inside them. These deposits are toxic. They jam the machinery neurons use to talk and to stay alive, so the cells wither and die. The damage often starts in the hippocampus, the brain's memory-forming hub. So the first and loudest symptom is usually short-term memory loss. The person forgets recent conversations, while old memories stay clear much longer. As it spreads across the cortex, it takes language and judgment. In the end it takes the ability to recognize loved ones and to handle basic self-care.
Parkinson disease: a dopamine shortage in the movement circuit
Parkinson disease targets one spot deep in the brain. It is called the substantia nigra, a cluster of neurons that make dopamine. Dopamine is the chemical that starts and smooths your movements. As these neurons die off, dopamine drops. The movement circuit, called the basal ganglia, loses its balance. The classic picture goes by the word TRAP:
- Tremor at rest, often a "pill-rolling" motion of the fingers that eases with purposeful movement
- Rigidity, stiff, cogwheel-like resistance in the limbs
- Akinesia/Bradykinesia, slow and shrinking movements, such as small handwriting, a masked face, and a shuffling gait
- Postural instability, poor balance and a tendency to fall, usually a later sign
ALS: the motor neurons fail while the mind stays largely intact
Amyotrophic lateral sclerosis (ALS) is also called Lou Gehrig disease. It attacks the motor neurons, the wiring that carries "move" commands from the brain and spinal cord to the muscles. Both upper and lower motor neurons break down. So patients develop steady muscle weakness, atrophy, and fasciculations. Atrophy means wasting, and fasciculations are muscle twitches. It often starts in one hand or foot and spreads from there. Here is the cruel twist. In most patients, cognition, senses, and awareness stay largely intact. The person stays alert inside a body that is losing the power to move, to swallow, and in time to breathe. The brain is not untouched, though. About 15 percent go on to develop frontotemporal dementia, which changes behavior and language. Failure of the breathing muscles is usually what limits life.
| Feature | Alzheimer | Parkinson | ALS |
|---|---|---|---|
| Cells lost | Cortical and hippocampal neurons | Dopamine neurons (substantia nigra) | Upper & lower motor neurons |
| Hallmark pathology | Amyloid plaques + tau tangles | Dopamine loss (Lewy bodies) | Motor neuron degeneration |
| First symptom | Short-term memory loss | Resting tremor, slowness | Weakness in one spot |
| Cognition | Lost step by step | Often kept early on | Usually kept |
One common thread ties all three together, and it is worth memorizing. A specific group of neurons is slowly and permanently lost. So the symptoms only get worse over time. Current treatments slow progression or ease symptoms. They do not regrow the lost cells, and they do not cure the disease. That is why care centers on safety, function, dignity, and family support. Explore the figure below to see where each disease strikes in the nervous system.
- Neurodegenerative diseases share one theme: progressive, irreversible loss of specific neurons that the body cannot replace.
- Alzheimer = beta-amyloid plaques + tau tangles, starting in the hippocampus, so short-term memory loss comes first.
- Parkinson = dopamine-neuron loss in the substantia nigra, causing resting tremor, rigidity, bradykinesia, and postural instability (TRAP).
- ALS = upper and lower motor-neuron death causing spreading weakness and atrophy, while cognition and senses usually stay intact.
- Treatments slow or ease symptoms but do not reverse the neuron loss, so care emphasizes safety, function, and support.
Section 6Demyelinating & neuromuscular disorders
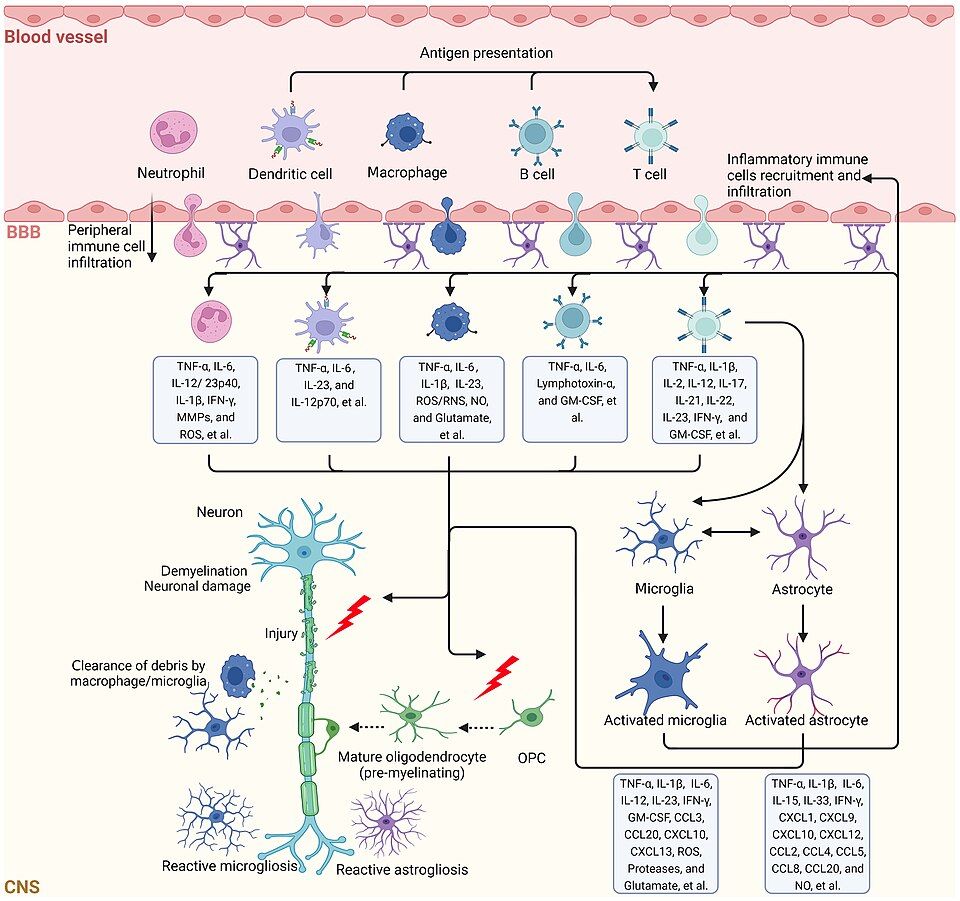
Every time you lift a coffee cup, wiggle your toes, or take a breath, a tiny chemical talk happens between a nerve and a muscle. It takes place at the neuromuscular junction (NMJ). That is the special synapse where a motor nerve meets a muscle fiber. Learn this handshake and you will see why the disorders in this section cause weakness in such different patterns.
The neuromuscular junction: how the signal crosses
An electrical impulse races down a motor neuron. That impulse is an action potential. When it reaches the nerve ending, it triggers the release of a neurotransmitter called acetylcholine (ACh). The ACh floats across the tiny gap, called the synaptic cleft. It binds to nicotinic ACh receptors on the muscle membrane. That binding opens ion channels. The muscle membrane depolarizes, and the muscle contracts. Then an enzyme called acetylcholinesterase chews up the ACh. The signal switches off cleanly, so the muscle can relax. Three things have to be in place. Enough ACh must be released. Enough working receptors must be there to catch it. And a healthy nerve must carry the impulse in the first place. Break any one link and you get weakness. But the pattern of that weakness tells you which link failed.
Multiple sclerosis: the insulation frays
Nerve fibers in the central nervous system are wrapped in myelin. Myelin is a fatty insulation. It lets impulses jump quickly from gap to gap. In multiple sclerosis (MS), the body's own immune cells attack that myelin and strip it off CNS neurons. The CNS means the brain, the spinal cord, and the optic nerves. This is autoimmune demyelination. Where myelin is lost, a plaque, or patch of sclerosis, forms. Signals then slow, scatter, or stop for good. Myelin can be damaged almost anywhere in the CNS. So the symptoms are famously scattered. They include blurred or double vision from optic neuritis, numbness and tingling, weakness, spasticity, fatigue, and bladder problems. The classic course is relapsing-remitting. Flares appear, then partly fade as the inflammation settles and some remyelination happens. Even so, scarring builds up over the years. A handy phrase is lesions separated in space and time.
Myasthenia gravis: the receptors get blocked
In myasthenia gravis (MG), the nerve and its ACh are fine. The muscle's receptors are the ones under attack. The immune system makes anti-ACh receptor antibodies. These block and destroy nicotinic receptors at the NMJ. With fewer receptors to catch ACh, each signal lands weakly. The hallmark is fatigable weakness. Muscles work at first, then tire fast with repeated use, and they recover with rest. That is why symptoms are usually worse at the end of the day. It classically strikes muscles that work all the time. So you see ptosis (drooping eyelids), diplopia (double vision), and trouble chewing, swallowing, or holding the head up. The feared complication is myasthenic crisis. There the respiratory muscles weaken and breathing fails.
Guillain-Barre syndrome: the nerves lose their coating from the outside in
In Guillain-Barre syndrome (GBS), the immune system attacks the myelin of peripheral nerves. It often starts a week or two after an infection, usually a gut or airway illness. The commonest germ identified is Campylobacter jejuni, a bacterium that causes diarrhea. The reason is molecular mimicry. Antibodies aimed at the bug also react with nerve myelin, because the two look alike. The signature is ascending paralysis. Weakness and reduced reflexes begin in the feet and climb upward. They can reach the diaphragm, and then the patient needs a ventilator. Unlike MG, the weakness is usually symmetric and steadily progressive, not fatigable. It tends to peak, then slowly recover.
| Feature | Myasthenia gravis | Guillain-Barre |
|---|---|---|
| Target | ACh receptors at NMJ | Peripheral nerve myelin |
| Pattern | Fatigable, often eyes first | Ascending, feet upward |
| Reflexes | Usually normal | Reduced or gone |
| Trigger | Autoimmune, linked to the thymus | Often after an infection |
| Feared crisis | Myasthenic crisis (breathing) | Respiratory failure |
Explore the neuromuscular junction in the figure below to see where ACh crosses and where these diseases strike.
- At the neuromuscular junction, acetylcholine crosses from nerve to muscle and binds receptors to trigger contraction, then acetylcholinesterase clears it.
- Multiple sclerosis is autoimmune demyelination of the CNS, often relapsing-remitting, with scattered symptoms separated in space and time.
- Myasthenia gravis is caused by antibodies against ACh receptors, producing fatigable weakness that worsens with use and improves with rest.
- Guillain-Barre syndrome is peripheral demyelination causing ascending paralysis, often after an infection, with lost reflexes.
- MG and GBS can both weaken the diaphragm, so respiratory monitoring is a top priority.
The chapter in one breath
- Ischemic stroke (about 87%) is a clot blocking flow. Hemorrhagic stroke is a burst vessel. The FAST screen catches both fast, because time is brain. FAST is Face droop, Arm drift, Speech slurred, Time to call 911.
- Only ischemic strokes get tPA, within roughly 3 to 4.5 hours. A stat CT must rule out bleeding first. Giving a clot-buster into a hemorrhage is deadly.
- Raised intracranial pressure shows up late as Cushing's triad: rising BP with a widening pulse pressure, bradycardia, and irregular breathing. A sluggish, blown pupil goes with it. All of it warns that the brain is being squeezed toward herniation.
- Traumatic brain injury is tracked with the Glasgow Coma Scale, which scores eyes, verbal, and motor. A score of 8 or less usually means secure the airway. Watch for the lucid-interval pattern of an epidural hematoma.
- Spinal cord injury above T6 risks neurogenic shock early. That looks like warm, dry skin with hypotension and bradycardia. Later it risks autonomic dysreflexia: a pounding headache with dangerously high BP, often from a full bladder.
- Seizures call for protecting the patient and timing them. Turn them side-lying, put nothing in the mouth, and never restrain. A seizure lasting over 5 minutes is status epilepticus, a true emergency.
- Neurodegenerative diseases differ by mechanism. Parkinson's comes from dopamine loss, with resting tremor, rigidity, and bradykinesia. Alzheimer's comes from plaques and tangles, with steady memory loss. Multiple sclerosis comes from demyelination, with relapsing-remitting deficits.
- Myasthenia gravis causes fatigable weakness that worsens with use, such as ptosis and diplopia. Antibodies against acetylcholine receptors are the cause. Guillain-Barre syndrome is an ascending paralysis that threatens the diaphragm. In both, watch respiratory function closely.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Bradykinesia
- Slowness in starting and carrying out movement. It is a core motor sign of Parkinson disease. Dopamine-producing neurons in the substantia nigra break down, so the basal ganglia can no longer start voluntary movement smoothly.
- Cushing's triad
- A late and ominous set of three vital-sign changes: hypertension with a widening pulse pressure, bradycardia, and irregular (often slow) respirations. It signals dangerously high intracranial pressure, with brainstem herniation close behind.
- Demyelination
- The loss or breakdown of the fatty myelin sheath that insulates axons. Nerve signals then slow down or stop. That is what produces the neurologic deficits seen in diseases like multiple sclerosis.
- Epidural hematoma
- A pool of blood between the skull and the outer dura mater. It usually comes from a torn middle meningeal artery after temporal trauma. The classic pattern is a brief lucid interval, then a fast decline.
- Hemorrhagic stroke
- A stroke caused by a ruptured blood vessel that bleeds into or around the brain. It starves tissue of blood. It also raises intracranial pressure, as the growing pool of blood presses on nearby neurons.
- Herniation
- The life-threatening shift of brain tissue across or through rigid structures inside the skull, when pressure builds. It may pass under the falx, or through the tentorium or foramen magnum. It often presses on the brainstem and its vital centers.
- Intracranial pressure
- The pressure inside the skull from the brain, blood, and cerebrospinal fluid together. It is normally about 5–15 mmHg. It turns dangerous when a mass, a bleed, or swelling pushes it higher.
- Ischemic stroke
- The most common type of stroke. A clot or narrowing blocks an artery and cuts off blood flow. The brain tissue it fed is starved of the oxygen and glucose it needs to survive.
- Monro-Kellie doctrine
- The rule that the skull is a fixed, rigid box. It holds three contents: brain, blood, and cerebrospinal fluid. If one of them grows, another must shrink to match. If not, intracranial pressure rises.
- Multiple sclerosis
- A chronic autoimmune disease. The body attacks myelin in the central nervous system. Scattered plaques form, and symptoms follow a relapsing-remitting pattern. They include vision changes, weakness, and numbness.
- Myasthenia gravis
- An autoimmune disorder. Antibodies block or destroy acetylcholine receptors at the neuromuscular junction. Muscle weakness then comes and goes. It worsens with use and improves with rest.
- Penumbra
- The ring of at-risk but still salvageable brain tissue around the dead core of an ischemic stroke. Restore blood flow quickly and it can be saved. That is why we say "time is brain."
- Seizure
- A sudden burst of abnormal, excessive electrical activity in the brain's neurons. It can change movement, sensation, behavior, or consciousness.
- Status epilepticus
- A neurologic emergency. It is a seizure lasting 5 minutes or longer, or repeated seizures with no full recovery in between. It risks permanent brain injury and needs treatment right away.
- Subdural hematoma
- A pool of blood between the dura and the arachnoid, usually from torn bridging veins. It often bleeds slowly, so it may show up days to weeks later. Older adults and people on anticoagulants are most at risk.
- tPA
- Tissue plasminogen activator, a clot-dissolving (thrombolytic) drug. It is given within a strict time window for ischemic stroke, to break down the blocking clot and restore blood flow. It is never used in hemorrhagic stroke.
DrillFlashcards for this unit
These are the Week 5 cards. It is the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
| Feature | Epidural | Subdural |
|---|---|---|
| Bleed source | Artery (fast) | Vein / bridging veins (slower) |
| Location | Above the dura | Below the dura |
| Onset | Fast, often with a lucid interval | Minutes to weeks; often chronic in older adults |
| CT shape | Lens / convex (lemon) | Crescent (banana) |
| Feature | Alzheimer | Parkinson |
|---|---|---|
| Core deficit | Memory / cognition | Movement |
| Pathology | Amyloid plaques & tau tangles | Dopamine loss in substantia nigra |
| Hallmark signs | Short-term memory loss, disorientation | Resting tremor, rigidity, bradykinesia, shuffling gait |
The Endocrine System
The endocrine system is the body’s chemical messaging service. It works more slowly than nerves. But its effects last for hours or even days. When one gland makes too much or too little of a hormone, the ripples show up everywhere. Blood sugar, heart rate, blood pressure, mood, growth, and water balance all shift. This chapter hands you the one idea that unlocks all of it. That idea is feedback. Then we walk each major gland from healthy to broken, mechanism by mechanism.
By the end of this chapter you can
- Trace how the hypothalamus and pituitary give orders to the other glands. Tell a tropic hormone from a direct one.
- Use negative feedback to predict a lab. Then use a stimulating-hormone level to place a problem as primary (the gland) or secondary (the pituitary).
- Contrast the too-much state with the too-little state for the adrenal (Cushing’s and Addison’s), the thyroid, and ADH (SIADH and DI).
- Read the electrolyte shifts that give a disorder away. Watch potassium in Addison’s, and sodium in SIADH and DI.
- Explain why Type 1 and Type 2 diabetes are different diseases. Name the diagnostic numbers. Tell DKA from HHS.
- Spot growth-hormone excess by its timing. Gigantism comes before the growth plates close. Acromegaly comes after.
- Flag the endocrine emergencies: Addisonian crisis, thyroid storm, myxedema coma, DKA, HHS, and severe hyponatremia.
Section 1The chain of command
The normal wiring: how orders travel down
Picture the endocrine system as a company. The hypothalamus is the boss on the top floor. It reads the body's status all day long. It checks temperature, blood pressure, stress, and hunger. It also checks the hormones already moving in the blood. Then it decides what needs to change. Just below it sits its manager, the pituitary gland. The pituitary rests in a bony pocket at the base of the brain. That pocket is the sella turcica. A short stalk joins the two, called the infundibulum. How they talk depends on which half of the pituitary you mean.
The front half gets no nerve signals. It gets chemical notes instead. The hypothalamus makes tiny releasing hormones and inhibiting hormones. These include TRH, CRH, GnRH, GHRH, and the blocker somatostatin. It drips them into a private set of blood vessels inside the stalk. That set is the hypophyseal portal system. Think of a mail tube running between two offices. This small bed of vessels carries the note straight to the anterior pituitary. The note never gets watered down in the rest of the blood first.
The anterior pituitary: a six-product factory
The anterior pituitary is a real factory. It builds six hormones. Several of them are tropic. That word comes from a Greek root meaning to turn toward. A tropic hormone does not act on body tissue. It turns on another gland. The others are direct hormones. They act on the body's own tissues. One way to recall them is FLAT PiG. FLAT is the tropic four: FSH, LH, ACTH, and TSH. PiG is the two direct ones: Prolactin and GH.
| Hormone | Target | Type |
|---|---|---|
| TSH | The thyroid gland | Tropic |
| ACTH | The adrenal cortex | Tropic |
| FSH & LH | The gonads (ovaries and testes) | Tropic |
| GH | The whole body, plus the liver (through IGF-1) | Direct |
| Prolactin | The breast | Direct |
Notice that GH works partly through a helper. It tells the liver to release IGF-1 (insulin-like growth factor-1). IGF-1 then does much of the real growth work in bone and muscle.
The posterior pituitary: a storage locker, not a factory
The back half is different, and it is easy to mix up. The posterior pituitary makes nothing. It is a storage locker. It releases two hormones. One is ADH (antidiuretic hormone, also called vasopressin). ADH tells the kidneys to hold on to water. The other is oxytocin. Oxytocin squeezes the uterus in labor and lets milk flow. Both are built up in the hypothalamus. The parent nerve cells send long axons down the stalk. The hormone rides down the nerve and waits in the tip. It sits there until a signal says release. So the front lobe gets chemical notes through blood vessels. The back lobe gets the finished product down a nerve.
Negative feedback: the body's thermostat
The whole system governs itself with negative feedback. It works just like a home thermostat. Set the dial to 70 degrees. When the room warms past that point, the furnace shuts off. When the room cools, the furnace fires back up. Hormones do the same thing. Walk the thyroid axis and watch. The hypothalamus puts out TRH. TRH tells the pituitary to put out TSH. TSH tells the thyroid to put out T4 (and T3). When T4 in the blood climbs high enough, it loops back. It switches off both TRH and TSH. The furnace turns off. If T4 falls, the pituitary senses the shortage. It cranks TSH up to push the thyroid harder. So here is the most useful line in endocrine care: low thyroid hormone usually means high TSH.
Positive feedback: the rare exception
Now and then the body wants the opposite. It wants a signal that builds on itself until a job is done. That is positive feedback. It is rare for a good reason. It is explosive. Two classic cases stand out. The first is the oxytocin surge in labor. Stretch of the cervix drives more oxytocin. More oxytocin drives stronger contractions. Stronger contractions stretch the cervix even more. The loop runs until the baby is born. The second is the LH surge at mid-cycle. That surge sets off ovulation. Both loops shut off once the goal is met.
The master skill: primary vs secondary vs tertiary
Here is the reasoning trick that cracks most of these cases. When a hormone level is off, ask where the fault lives. Let the tropic hormone point you to it. A primary problem sits in the target gland itself. That means the thyroid, the adrenal, or a gonad. A secondary problem sits in the pituitary. A tertiary problem sits up in the hypothalamus.
| Level | Broken part | Thyroid example (low T4) |
|---|---|---|
| Primary | The target gland | Low T4, high TSH (the pituitary is shouting) |
| Secondary | The pituitary | Low T4, low TSH (no one is shouting) |
| Tertiary | The hypothalamus | Low T4, low TSH, low TRH |
Once the chain of command sinks in, endocrine disease stops being memory work. It turns into detective work. Explore the wiring below.
- The hypothalamus sends releasing and inhibiting hormones through the hypophyseal portal blood vessels to the anterior pituitary. That lobe builds six hormones: TSH, ACTH, FSH, LH, GH, and prolactin.
- The posterior pituitary makes nothing. It only stores and releases ADH and oxytocin. The hypothalamus builds those two and sends them down the nerve.
- Tropic hormones (TSH, ACTH, FSH, LH) act on other glands. Direct hormones (GH, prolactin) act on body tissue.
- Negative feedback works like a thermostat. When the final hormone rises, it shuts off its own signals. So low thyroid hormone usually drives TSH up. Positive feedback is the rare kind that builds on itself, as in labor oxytocin and the LH surge.
- Use the tropic hormone level to place the lesion. Primary is the target gland. Secondary is the pituitary. Tertiary is the hypothalamus.
Section 2Adrenal glands: the cortisol problem
The normal adrenal gland: two organs stacked in one
The adrenal glands sit like small caps on top of each kidney. Each one is really two organs fused together. The outer cortex builds steroid hormones out of cholesterol. The inner medulla makes the fight-or-flight catecholamines. Those are epinephrine and norepinephrine. The cortex has three layers. A handy way to recall them is salt, sugar, sex as you travel inward. The outer zona glomerulosa makes aldosterone. Aldosterone is the mineralocorticoid that holds on to salt and water. The middle zona fasciculata makes cortisol. Cortisol is the glucocorticoid that handles sugar and stress. The inner zona reticularis makes weak androgens, which are the sex steroids.
What cortisol actually does
Cortisol is your built-in stress hormone. It rises and falls on a daily rhythm. It surges whenever you are sick, hurt, or scared. It raises blood glucose by driving gluconeogenesis. That is the liver building brand new glucose. Your brain and muscles then have fuel in a crisis. Cortisol is also strongly anti-inflammatory and immunosuppressive. It calms swelling and quiets the immune system. That is exactly why we bottle it as drugs like prednisone. Cortisol helps maintain blood pressure too. It keeps blood vessels able to answer catecholamines. Control runs through the HPA axis. The pituitary puts out ACTH. ACTH tells the cortex to make cortisol. Rising cortisol then shuts ACTH back off, which is negative feedback. Hold on to that loop. It is the key to telling these diseases apart.
Cushing: too much cortisol
Start with the words. Cushing syndrome is the umbrella term. It covers any cause of too much cortisol. Cushing disease means one thing only. It is a pituitary ACTH-secreting adenoma that drives the adrenals. But the single most common cause overall is neither of those. It is exogenous steroid medication taken for a long time. People take it for asthma, autoimmune disease, or a transplant. Adrenal tumors that make cortisol on their own are a third route.
Every classic sign traces back to too much cortisol. Cortisol moves fat to the center of the body. So patients get a round moon face and a buffalo hump between the shoulders. They also get truncal obesity with thin arms and legs. Fat piles up in the middle while cortisol breaks down limb muscle. Cortisol thins the skin and weakens collagen. So you see thin, fragile, easily-bruised skin. You also see stretched purple striae across a belly that outgrew its weakened skin. Nonstop gluconeogenesis causes hyperglycemia, also called steroid-induced diabetes. Cortisol spills over onto mineralocorticoid receptors and holds sodium and water. That causes hypertension and drops the potassium. Aldosterone itself is normal or low in Cushing, so the sodium usually sits normal or only slightly high. It is the cortisol doing the mineralocorticoid job. Bone breakdown leads to osteoporosis. The quieted immune system brings poor wound healing and infection risk. Mood swings, a short temper, and even psychosis round out the picture.
Addison: too little cortisol (primary insufficiency)
Addison disease is primary adrenal insufficiency. The gland itself is destroyed. Most often an autoimmune attack does it. The whole cortex fails, so the patient loses all three outputs. Those are cortisol, aldosterone, and adrenal androgens. Low aldosterone lets sodium and water leak out while potassium builds up. So expect hyponatremia, HYPERkalemia, hypotension, and a strong salt craving. Low cortisol brings hypoglycemia, deep weakness and fatigue, and weight loss. The giveaway finding is bronze hyperpigmentation. With cortisol gone, feedback is lost. The pituitary floods the body with ACTH. ACTH also stirs up melanocytes, the pigment cells in the skin.
Secondary insufficiency: a pituitary problem
Now say the pituitary fails instead. Then ACTH is low. Two clues follow. There is no hyperpigmentation, since no extra ACTH darkens the skin. And aldosterone is largely spared. Aldosterone is driven mainly by the renin-angiotensin system, not by ACTH. So these patients have low cortisol. But their sodium and potassium usually stay closer to normal.
Pheochromocytoma: the medulla's turn
A pheochromocytoma is a tumor of the adrenal medulla. It dumps catecholamines in sudden surges you cannot predict. Recall the 5 P's. Pressure means bursts of high blood pressure, often severe. Pain means a pounding headache. The rest are Palpitations, Perspiration, and Pallor. Between surges the patient may feel completely normal. That is what makes it sneaky.
Putting it together
The fastest way to keep Cushing and Addison straight is a side-by-side look. Explore the interactive figure below, too.
| Feature | Cushing (excess) | Addison (deficiency) |
|---|---|---|
| Cortisol | High | Low |
| Blood glucose | High | Low |
| Blood pressure | High | Low |
| Sodium / Potassium | Na normal to slightly high / K low | Na low / K high |
| Weight & fat | Gain in the middle, moon face | Loss and wasting |
| Skin | Thin, bruises, striae | Bronze hyperpigmentation |
One last feedback check ties it all together. An adrenal tumor making its own cortisol pushes ACTH down, because feedback shuts the pituitary off. A failed adrenal gland lets ACTH climb up. The way ACTH moves tells you where the problem lives.
- The cortex makes salt (aldosterone), sugar (cortisol), and sex steroids (androgens). The medulla makes catecholamines. Cortisol raises glucose, calms inflammation, and props up blood pressure.
- Cushing is too much cortisol only, with aldosterone normal or low. Most often it comes from steroid medication. Look for central obesity, moon face, striae, hyperglycemia, hypertension, hypokalemia, a normal or slightly high sodium, thin skin, and infection risk.
- Addison (primary) destroys the whole cortex. Cortisol AND aldosterone fall, so you get hypotension, hyponatremia, HYPERkalemia, hypoglycemia, salt craving, and bronze skin from high ACTH.
- Secondary insufficiency (pituitary) means low ACTH. There is no hyperpigmentation and aldosterone is spared. Never stop long-term steroids all at once. Taper to avoid an Addisonian crisis.
- Pheochromocytoma is a medulla tumor with catecholamine surges (the 5 P's). Low ACTH points to an adrenal tumor. High ACTH points to a failed adrenal gland.
Section 3Thyroid: the metabolic thermostat
Think of your thyroid as the body's metabolic thermostat. It is a small gland shaped like a butterfly. It sits at the front of your neck. It decides how fast every cell runs its engine. Turn the setting up and your heart beats faster. You burn more fuel and you feel warm. Turn it down and everything slows. Heart, gut, brain, and body heat all ease off. Almost every confusing thyroid symptom makes sense from that one idea. This gland sets the pace of your metabolism.
The normal axis: a three-station relay
Control starts up in the brain. The hypothalamus puts out TRH (thyrotropin-releasing hormone). TRH travels a short way to the anterior pituitary. It tells that lobe to put out TSH (thyroid-stimulating hormone). TSH then rides the blood to the thyroid and says, make hormone. The thyroid answers with mostly T4 (thyroxine), the bulk of its output. It also makes a smaller amount of T3 (triiodothyronine). T3 is the more active form. Much of the T4 is changed into T3 out in the tissues. So think of T4 as the storage and delivery form. T3 is the one that actually revs the cell.
Two more facts anchor the whole system. First, the thyroid cannot build these hormones without iodine. Iodine is a required raw ingredient. That is exactly why iodized salt exists. Second, the thyroid has a side job that has nothing to do with metabolism. Its C-cells release calcitonin. Calcitonin gently lowers blood calcium by tucking it back into bone. It is a minor player in people. Still, it is worth knowing it comes from the thyroid.
Hypothyroidism: the thermostat turned down
When the thyroid makes too little hormone, metabolism idles. Every symptom is that slowdown showing up in a different organ. In countries with enough iodine, the number-one cause is Hashimoto's thyroiditis. That is an autoimmune attack that slowly destroys thyroid tissue. Worldwide, iodine deficiency is still the leading cause. Other causes come after treatment. Those include surgery to remove the thyroid and radioactive iodine ablation. Some drugs do it too, such as lithium and amiodarone.
Trace the mechanism and the signs write themselves. A slow metabolism burns less fuel. So patients feel fatigued. They gain weight even with a normal appetite. They cannot make heat well, which gives cold intolerance. A slowed cardiac pace gives bradycardia. Skin turns over slowly and sweats less, so skin is dry and hair gets coarse and thin. A slow gut means constipation. Reproductive hormones drift, which brings menstrual changes. Periods are often heavier or irregular. Even the nervous system lags. That gives the classic slowed, delayed deep-tendon reflexes. Severe, long-standing disease is called myxedema. That is a puffy, non-pitting swelling from mucin building up in the skin. Its life-threatening extreme is myxedema coma. Look for low body temperature, low blood pressure, and a dulled level of consciousness. That is a true emergency.
Hyperthyroidism: the thermostat cranked up
Too much hormone and metabolism races. The leading cause is Graves' disease. In Graves', antibodies attack the TSH receptor. We call them TSH-receptor antibodies, or TRAb. The stimulating kind are TSI (thyroid-stimulating immunoglobulins). They bind that receptor and switch it on. The gas pedal stays floored no matter what the pituitary wants. Other causes include a toxic multinodular goiter. Those are nodules that make hormone on their own. Thyroiditis can do it too, when an inflamed gland leaks stored hormone.
The signs mirror hypothyroidism in reverse. Burning fuel too fast causes weight loss despite a big appetite. It also causes heat intolerance. The heart speeds up into tachycardia and palpitations, and sometimes atrial fibrillation. The overdriven nervous system brings anxiety, a fine tremor, and brisk hyperreflexia. A fast gut causes diarrhea. Graves' adds two things of its own, both from the antibody attack. One is bulging eyes, or exophthalmos, from tissue swelling behind the eye. The other is pretibial myxedema, a thickened patch of skin over the shins. The emergency here is thyroid storm. Look for a dangerous fever, extreme tachycardia, and agitation or delirium.
Reading the labs: let TSH tell the story
Negative feedback means the TSH and T4 pattern tells you two things. It says whether there is a problem. It also says where the problem lives. In a primary problem the thyroid itself is the culprit. In a secondary problem the pituitary fails to give proper orders. That flips the relationship you expect.
| Pattern | TSH | T4 |
|---|---|---|
| Primary hypothyroid | High | Low |
| Primary hyperthyroid | Low | High |
| Secondary (pituitary) hypothyroid | Low, or normal when it should be high | Low |
Here is the tell for a secondary problem. A low T4 should drive TSH up. So a low T4 paired with a TSH that is low or normal does not fit. The pituitary is not doing its job.
Hypo vs hyper at a glance
| Feature | Hypothyroid | Hyperthyroid |
|---|---|---|
| Heart rate | Slow (bradycardia) | Fast (tachycardia, AFib) |
| Weight | Goes up | Goes down |
| Temperature | Cold intolerance | Heat intolerance |
| GI | Constipation | Diarrhea |
| Mood | Sluggish and low | Anxious and restless |
| Skin | Dry and coarse | Warm and moist |
Keep that one thermostat image in mind and the whole gland makes sense. Explore the interactive figure below to see the axis and its feedback in motion.
- The thyroid sets metabolic speed. Hypothyroid slows everything, with fatigue, weight gain, cold, bradycardia, and constipation. Hyperthyroid speeds everything, with weight loss, heat, tachycardia, anxiety, and diarrhea.
- The axis runs TRH (hypothalamus) → TSH (pituitary) → T4 and active T3 (thyroid), and it needs iodine. Negative feedback makes TSH the key lab.
- Hashimoto's is the top cause of hypothyroidism where iodine is plentiful. Graves', through TSI and TRAb antibodies, is the top cause of hyperthyroidism, and it can add exophthalmos.
- Labs: primary hypothyroid is high TSH with low T4. Primary hyperthyroid is low TSH with high T4. A low T4 with a TSH that is low or wrongly normal points to a secondary (pituitary) cause.
- The emergencies are myxedema coma (hypo) and thyroid storm (hyper). After thyroid surgery, watch for hypocalcemia with the Trousseau and Chvostek signs.
Section 4Diabetes mellitus
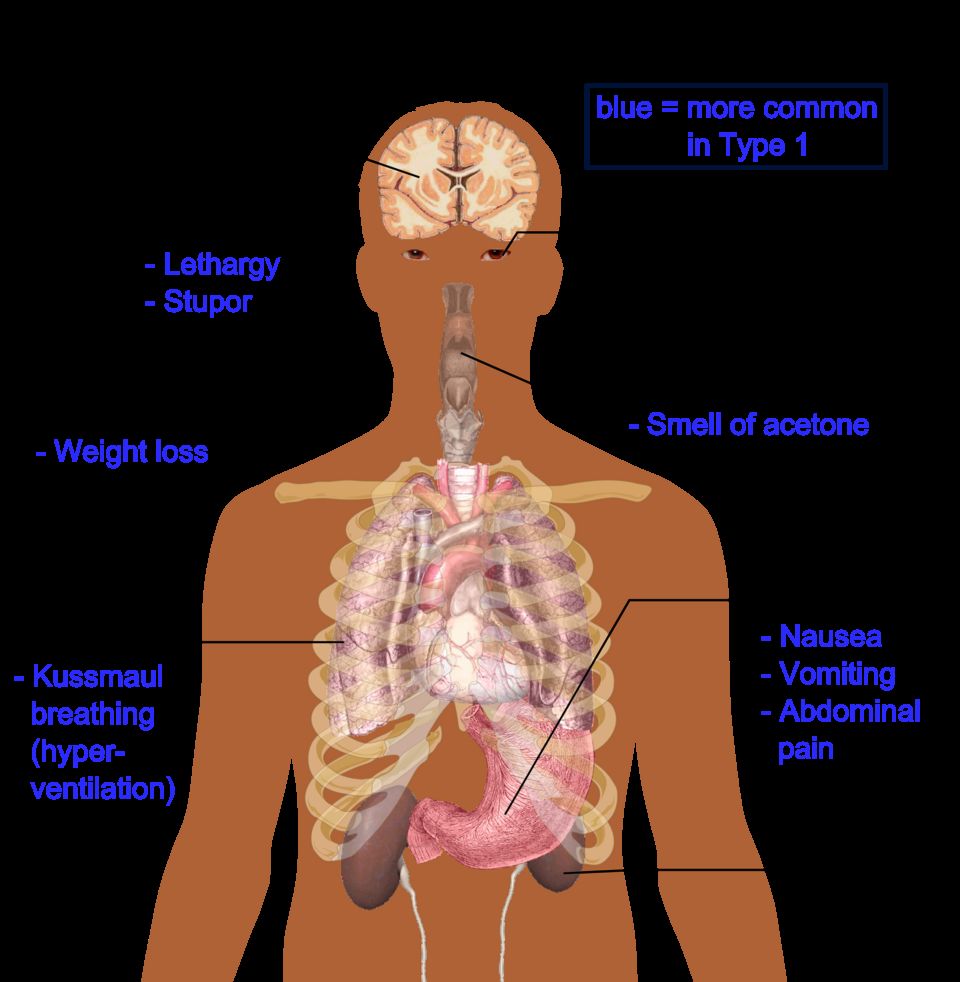
Before we talk about what breaks in diabetes, look at how the body normally handles fuel. Picture your bloodstream as a delivery highway. Glucose (blood sugar) is the cargo every cell wants for energy. The traffic controller is your pancreas. More exactly, it is tiny clusters of cells inside it called the islets of Langerhans.
Normal fuel control: the fed state and the fasting state
Inside those islets, beta cells make insulin and alpha cells make glucagon. These two hormones pull in opposite directions. That tug-of-war keeps blood sugar in a safe range. After a meal you are in the fed state. Glucose rises, beta cells release insulin, and insulin acts like a key. It unlocks cells so glucose can move in to be burned or stored. It also tells the liver to bank extra glucose as glycogen. Between meals or overnight you are in the fasting state. Glucose falls, so alpha cells release glucagon. Glucagon tells the liver to break glycogen back down and release glucose. Your brain never runs dry. In short, insulin stores fuel and lets glucose into cells. Glucagon raises blood sugar. Diabetes is what happens when the insulin side of that system fails.
Type 1: an absolute insulin deficiency
In type 1 diabetes, the immune system attacks the beta cells by mistake and destroys them. This is an autoimmune process. We can often find islet autoantibodies in the blood. The beta cells are gone, so there is essentially no insulin at all. We call that an absolute insulin deficiency. It usually shows up in younger, leaner people. The body cannot make insulin, so these patients always require insulin shots to live. Without insulin, glucose cannot get into cells. It piles up in the blood while the cells starve.
Type 2: insulin resistance plus a relative shortfall
In type 2 diabetes, insulin is present. But the cells stop answering it well. That is insulin resistance. The pancreas makes up for it by pumping out extra insulin. Over time it cannot keep up. That leaves a relative insulin deficiency. Type 2 comes on slowly and is often silent for years. It is strongly tied to obesity, metabolic syndrome, and older age. One physical clue is acanthosis nigricans. Those are velvety dark patches in skin folds like the neck and armpits. They signal long-standing high insulin.
Why the three P's happen: osmotic diuresis
Either type can do this. Once blood glucose climbs high enough, the kidneys cannot soak it all back up. Glucose spills into the urine. Sugar in the urine acts like a sponge and drags water out with it. That is osmotic diuresis. It explains the classic three P's. Polyuria means passing large amounts of urine. That causes dehydration, which sets off polydipsia, or intense thirst. Starving cells drive polyphagia, or constant hunger. Weight loss and blurry vision often ride along.
How we diagnose it
Diagnosis rests on standard numbers. Any one of these makes the diagnosis, and we usually confirm it on a repeat test:
- Fasting plasma glucose ≥ 126 mg/dL
- Random glucose ≥ 200 mg/dL along with classic symptoms
- A1c ≥ 6.5 percent (an average of blood sugar over about 3 months)
- 2-hour OGTT ≥ 200 mg/dL (the oral glucose tolerance test)
The long game: chronic complications
Years of high glucose damage blood vessels in two patterns. Microvascular damage hits the small vessels. It causes retinopathy (vision loss), nephropathy (kidney failure), and neuropathy (nerve damage, often numb, tingling feet). Macrovascular damage hits the large vessels. It speeds up coronary artery disease, stroke, and peripheral arterial disease. Put numb feet together with poor blood flow and you get the feared diabetic foot ulcers. Wounds heal slowly and badly.
Gestational diabetes
Pregnancy hormones cause some insulin resistance on their own. When the pancreas cannot keep up, gestational diabetes results. It is often silent, so we screen every pregnant patient. Screening usually happens around 24 to 28 weeks. Extra sugar in the mother's blood crosses to the baby. The baby makes too much insulin and grows too large. That is called macrosomia. After delivery that sugar supply vanishes. But the baby's high insulin keeps going, which causes neonatal hypoglycemia.
The two emergencies: DKA vs HHS
In type 1 there is no insulin at all. The body burns fat for fuel and makes acidic ketones. That tips into diabetic ketoacidosis (DKA). In type 2 there is usually just enough insulin to block ketones. But sugar and dehydration climb to extremes. That is hyperosmolar hyperglycemic state (HHS).
| Feature | DKA | HHS |
|---|---|---|
| Usual type | Type 1 | Type 2 |
| Glucose | Usually > 250 mg/dL | Often > 600 mg/dL |
| Ketones | Present | Little or none |
| Blood pH | Acidotic (low) | Near normal |
| Breathing | Kussmaul (deep and rapid) | Not Kussmaul |
| Onset | Fast (hours) | Slow (days) |
| Core treatment | IV fluids, insulin, careful potassium | IV fluids, insulin, careful potassium |
Both get the same core plan. Rehydrate with IV fluids. Give insulin to lower glucose and shut off ketone production. Replace potassium with care, because insulin drives potassium into cells and levels can crash. Explore the comparison figure below.
- Insulin, from beta cells, lets glucose into cells and stores fuel. Glucagon, from alpha cells, raises blood sugar between meals.
- Type 1 is autoimmune. It is an absolute insulin deficiency that always needs insulin, and it is prone to DKA. Type 2 is insulin resistance plus a relative deficiency, tied to obesity, and it is prone to HHS.
- High glucose spills into urine and drags water with it. That is osmotic diuresis, and it produces the three P's: polyuria, polydipsia, and polyphagia.
- Diagnose with fasting glucose ≥ 126 mg/dL, random ≥ 200 mg/dL with symptoms, A1c ≥ 6.5 percent, or a 2-hour OGTT ≥ 200 mg/dL. Long-term highs cause microvascular and macrovascular damage.
- DKA (type 1) has ketones, acidosis, and Kussmaul breathing. HHS (type 2) has very high glucose with little ketosis. Both need IV fluids, insulin, and careful potassium. Cold and clammy means give sugar fast.
Section 5Growth hormone: timing is everything
Near the base of your brain sits a gland the size of a pea. It is the anterior pituitary. It releases growth hormone (GH, somatotropin) in bursts, mostly overnight. GH is the body's build order. It tells bone, muscle, and soft tissue to grow. Like most hormones, it runs on a push-pull system. The hypothalamus sends down GHRH (growth hormone-releasing hormone) to press the gas. It sends somatostatin to press the brake. The balance of those two decides how much GH gets out. Sleep, stress, exercise, and low blood sugar all have a say.
How GH actually builds you
GH works two ways at once. It acts directly on tissues. It also acts indirectly. It travels to the liver and tells the liver to make IGF-1 (insulin-like growth factor 1). IGF-1 is the messenger that does much of the real growth work at bone and muscle. That is why we lean on it for testing later. Together they lengthen and thicken bone at the growth zones. They add muscle. They support organs and connective tissue. GH also nudges metabolism. It pushes the body to burn fat. And it tends to raise blood glucose by working against insulin. Hold on to that last fact. It explains a lot of what goes wrong when there is too much GH.
When there is too little GH
In a child, too little GH means the skeleton grows slowly but proportionally. You see a smaller child who is still nicely in proportion, head to limbs to trunk. That is proportional short stature. It differs from conditions where the limbs and trunk do not match. In an adult, growth is already done. So GH deficiency shows up more quietly. Look for fatigue, less muscle and strength, more fat around the middle, and low vitality. These are changes in body composition rather than height.
Too much GH: why timing decides everything
Here is the single most important idea. It is all about the epiphyseal (growth) plates. Those are the cartilage zones at the ends of long bones. New bone is laid down there to make you taller. While those plates are open, bone can still get longer. That covers childhood and adolescence. Once they fuse after puberty, that door closes for good.
So extra GH lands very differently depending on when it strikes. Before the plates close, extra GH lets the whole skeleton keep lengthening. The child grows abnormally tall all over. That is gigantism. After the plates fuse, bone can no longer get longer. The growth signal has nowhere to go but outward. Bone and soft tissue thicken instead. That is acromegaly.
Acromegaly, sign by sign, and why
Acromegaly builds outward. So the clues are about things getting bigger and coarser over years. It is often so slow the patient does not notice. Bone and soft tissue in the hands and feet expand. Patients report a rising ring and shoe size. The face coarsens. The brow and jaw thicken, which gives a jutting jaw called prognathism. The teeth may spread apart as the jaw enlarges. The tongue enlarges (macroglossia) and the voice may deepen. Inside the body, organs enlarge too, which is organomegaly. Soft-tissue swelling in the wrist squeezes the median nerve. That gives carpal tunnel syndrome, with numbness and tingling in the hand. GH works against insulin, so many patients develop glucose intolerance or frank diabetes. Overactive sweat glands cause heavy sweating, or hyperhidrosis.
The usual culprit, and its neighbors
Both conditions almost always come from a GH-secreting pituitary adenoma. That is a benign tumor of the anterior pituitary. The tumor sits in a tight bony pocket near important structures. So as it grows it can press on them. We call those mass effects. One is headache from local pressure. The classic one is bitemporal hemianopsia. The patient loses the outer (temporal) half of each visual field. It happens when the tumor presses upward on the optic chiasm. That is where the nasal retinal fibers cross.
| Feature | Gigantism | Acromegaly |
|---|---|---|
| Timing of GH excess | Before the growth plates close (childhood) | After the growth plates fuse (adulthood) |
| Growth plates | Still open | Fused |
| What changes | The whole skeleton gets longer | Bone and tissue get thicker |
| Main result | Abnormally tall height | Bigger hands, feet, and face (thickness) |
| Usual cause | A GH-secreting pituitary adenoma | A GH-secreting pituitary adenoma |
Picture a growth plate opening and closing and it all clicks into place. Explore it below.
- GH comes from the anterior pituitary. GHRH stimulates it and somatostatin blocks it. GH acts partly through liver-made IGF-1, and it tends to raise blood glucose.
- For GH excess, the deciding factor is whether the epiphyseal growth plates are open. Open plates give gigantism, which is tall all over. Fused plates give acromegaly, where bones thicken.
- Acromegaly shows bigger hands and feet, prognathism with spreading teeth, macroglossia, carpal tunnel syndrome, glucose intolerance, and sweating. All of it comes from outward growth.
- The usual cause is a GH-secreting pituitary adenoma. It can also cause headache and bitemporal hemianopsia by pressing on the optic chiasm.
- Diagnose with an elevated IGF-1 plus a GH that fails to drop after an oral glucose load.
Section 6ADH: the body’s water valve
The normal setup: one hormone, one job
Antidiuretic hormone (ADH) is also called vasopressin. It really does have a single mission. It tells the kidneys to hang on to water. To learn its disorders, start with how the body decides when to hold water. Tucked in the hypothalamus are tiny sensors called osmoreceptors. Their whole job is to taste the blood. They do not check for sugar or salt by itself. They check how concentrated the blood is. That is its osmolality. Sweat on a hot day, or forget to drink, and the blood gets saltier and more concentrated. The osmoreceptors feel that and sound the alarm.
Here is a detail worth holding on to. The hypothalamus makes ADH. But it does not release it. It sends the hormone down to the posterior pituitary. That lobe is the storage tank and the release valve. When the osmoreceptors fire, the posterior pituitary squirts stored ADH into the blood. ADH then travels to the kidney and lands on the collecting duct. That is the last stretch of tubing before urine leaves the kidney. There ADH puts little water doorways into the tubule wall. Those doorways are aquaporins. Water slips out of the forming urine and back into the blood. The blood is thinned again. Only a small amount of concentrated urine leaves the body. When you are well hydrated, ADH switches off. The aquaporins pull back. You pass lots of pale, dilute urine. That is the water valve, opening and closing all day.
Now the two disorders. They are near-perfect mirror images. Learn one and you almost get the other for free.
SIADH: too much ADH (the body is soaked)
SIADH stands for syndrome of inappropriate antidiuretic hormone. The key word is inappropriate. ADH is being released when the body does not need it. The valve is jammed open. Common culprits include central nervous system injury. That covers head trauma, stroke, brain surgery, and meningitis. Small-cell lung cancer is another, since the tumor makes its own ADH. Certain medications do it too, such as SSRIs, carbamazepine, and some chemo drugs. So do the stress states of surgery, pain, and nausea. All of those nudge ADH upward.
With ADH stuck on, the kidneys take back too much water. That extra water thins everything in the blood. So the serum sodium falls. We call it a dilutional hyponatremia. Notice this is a water problem, not a salt-loss problem. Total body sodium is about normal. It is just swimming in too much fluid. The retained water spreads through the whole body instead of pooling as obvious swelling. So patients usually look euvolemic. They may gain a little weight, but often have no clear edema. Meanwhile the urine is the opposite of the blood. It is small in volume and highly concentrated, because the kidney is clinging to water.
The danger is neurologic. Sodium keeps the fluid balance around brain cells steady. When sodium drops, water shifts into the neurons and the brain swells. Expect headache, confusion, lethargy. If the drop is severe or fast, expect seizures. The core fix is simple in concept. Use fluid restriction. Take away the extra water and the sodium drifts back up.
Diabetes insipidus: too little ADH (the body cannot hold water)
Diabetes insipidus (DI) is the flip side. Either the brain does not make or release enough ADH. That is central DI, often after head injury, pituitary surgery, or a tumor. Or the kidney simply cannot respond to the ADH it receives. That is nephrogenic DI, from kidney disease or drugs like lithium. Either way, the aquaporins never open. Water pours straight through into the urine.
The picture is dramatic. You see huge volumes of dilute, pale urine, sometimes many liters a day. The patient slides into dehydration. The serum sodium rises, which is hypernatremia. Water is leaving while sodium stays behind and gets concentrated. The body fights back with intense, unrelenting thirst. Central DI is treated by replacing the missing hormone. We use desmopressin (DDAVP), a synthetic ADH.
A quick word on the name
Do not let the word diabetes fool you. DI has nothing to do with blood sugar. The word diabetes just means a large flow of urine. The second word tells you the type. Insipidus means tasteless. The old test was to taste the dilute urine. Mellitus means sweet, from the sugar spilling over in diabetes mellitus. Same big-urine complaint, completely different cause.
SIADH vs DI side by side
| Feature | SIADH (too much ADH) | DI (too little ADH, or no response) |
|---|---|---|
| ADH level / action | High, so the valve is stuck open | Low or useless, so the valve is stuck shut |
| Serum sodium | Low (hyponatremia) | High (hypernatremia) |
| Urine concentration | Concentrated | Dilute |
| Urine volume | Low | Very high |
| Volume status | Euvolemic or fluid-overloaded | Dehydrated (volume depleted) |
| Core treatment | Fluid restriction | Desmopressin (central DI) |
These two live at opposite ends of the same dial. That dial is the ADH water valve. Picture it opening and closing on the kidney tubule, then explore it below.
- ADH is made in the hypothalamus and stored and released by the posterior pituitary. It tells the kidney collecting duct to take water back by adding aquaporins. Osmoreceptors trigger it when blood is too concentrated.
- SIADH means too much ADH. You get water retention, a dilutional euvolemic hyponatremia, low-volume concentrated urine, and neuro symptoms. Treat it with fluid restriction. Remember: Soaked, Sodium low.
- DI means too little ADH (central) or a kidney that cannot respond (nephrogenic). You get large volumes of dilute urine, dehydration, hypernatremia, and intense thirst. Central DI is treated with desmopressin.
- SIADH and DI are exact opposites on sodium, urine, and volume status. Learn one and flip it for the other.
- Diabetes insipidus has nothing to do with blood sugar. Insipidus means tasteless urine, and mellitus means sweet.
The chapter in one breath
- Negative feedback is the master key. A low target hormone drives its pituitary signal up, so low T4 means high TSH. A high target hormone shuts the signal off.
- Cushing's is too much cortisol, with moon face, central obesity, hyperglycemia, thin easily-bruised skin, and hypertension. Addison's is too little, with hypotension, weight loss, hyperkalemia, and bronze hyperpigmentation.
- Thyroid logic is simple. Hypo runs slow, with fatigue, cold, and weight gain. Hyper runs fast, with tachycardia, heat, and weight loss. A goiter can come with either one.
- Type 1 diabetes is an absolute insulin deficiency prone to DKA, which brings ketones, acidosis, and Kussmaul breathing. Type 2 is insulin resistance prone to HHS, which brings extreme hyperglycemia, deep dehydration, and few ketones.
- Growth hormone excess before the growth plates fuse causes gigantism. The same excess after they fuse causes acromegaly.
- ADH extremes mirror each other. Too much is SIADH, with water retention and dilutional hyponatremia. Too little is diabetes insipidus, with massive water loss and hypernatremia.
- Never stop steroids all at once. Taper corticosteroids to prevent an adrenal crisis, and raise the dose during illness or surgery.
- After a thyroidectomy, stay alert. Watch for hypocalcemia from parathyroid injury, with Chvostek and Trousseau signs, tingling, and tetany. Watch the airway too, since neck swelling can block it.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Aldosterone
- A mineralocorticoid hormone from the adrenal cortex. It tells the kidneys to take back sodium and water and to dump potassium, which raises blood volume and blood pressure.
- Aquaporin
- A water-channel protein. Antidiuretic hormone puts it into kidney tubule walls so water can be taken back, which concentrates the urine.
- Catecholamines
- The fight-or-flight hormones epinephrine and norepinephrine, released by the adrenal medulla. They raise heart rate, blood pressure, and blood glucose.
- Cortisol
- The main glucocorticoid from the adrenal cortex. It raises blood glucose, pulls fat and protein out of storage, and calms inflammation as part of the stress response.
- Exophthalmos
- Eyeballs that bulge forward abnormally. It is classic in Graves disease, where immune-driven tissue swelling pushes the eyes out.
- Goiter
- A visibly enlarged thyroid gland. It can happen whether thyroid hormone output is high, low, or normal.
- Hyperpigmentation
- Darkening of the skin. It happens in primary adrenal insufficiency because high ACTH also stirs up the cells that make melanin.
- IGF-1
- Insulin-like growth factor 1. The liver makes most of it in answer to growth hormone, and it carries out most of growth hormone's effects on tissue growth.
- Insulin resistance
- A state in which body cells answer insulin poorly. The pancreas must then put out more insulin to keep blood glucose in range.
- Ketoacidosis
- A dangerous metabolic state, typical of type 1 diabetes. A severe lack of insulin forces fat breakdown into acidic ketones, and those ketones lower blood pH.
- Myxedema
- The severe, advanced form of hypothyroidism. The face and tissues swell without pitting, from mucopolysaccharide buildup. In crisis, body functions slow down profoundly.
- Negative feedback
- A self-correcting loop. A rising hormone level signals its own source to stop releasing more, which keeps the hormone in a steady range.
- Osmotic diuresis
- Heavy urine output that happens when high blood glucose spills into the urine and pulls water along with it. The result is dehydration.
- Primary vs secondary endocrine disorder
- A primary disorder starts with a fault in the hormone-making gland itself. A secondary disorder starts in the pituitary, which sends too little stimulating hormone. A tertiary disorder starts in the hypothalamus above it, and many texts group both of those under secondary.
- Thyroid storm
- A life-threatening surge of thyroid hormone activity. It brings high fever, a racing heart, agitation, and possible cardiovascular collapse.
- Tropic hormone
- A hormone, usually from the pituitary, whose target is another endocrine gland. It stimulates that gland to release its own hormone.
DrillFlashcards for this unit
These are the Week 6 cards. They are the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
| Feature | Cushing | Addison |
|---|---|---|
| Cortisol | High | Low |
| Blood glucose | High | Low |
| Blood pressure | High | Low |
| Serum sodium | Normal to slightly high | Low |
| Serum potassium | Low | High |
| Weight | Gain in the middle | Loss |
| Feature | Type 1 | Type 2 |
|---|---|---|
| Core defect | Autoimmune beta-cell loss | Insulin resistance |
| Insulin level | Absent | Normal to high early on |
| Typical onset | Young and lean | Adult, often obese |
| Ketosis risk | High (DKA) | Low (HHS instead) |
Growth hormone excess
Gigantism is GH excess before the growth plates close, so the patient grows very tall. Acromegaly is GH excess after they close, so the hands, feet, jaw, and facial features enlarge instead of height.
Posterior pituitary and ADH
SIADH is too much ADH. Water is held back, urine is concentrated, and serum sodium falls. That is a dilutional hyponatremia. DI (diabetes insipidus) is too little ADH, or a kidney that will not respond. You get huge volumes of dilute urine, thirst, and a rising serum sodium.
| Feature | SIADH | DI |
|---|---|---|
| ADH effect | Too much | Too little |
| Urine output | Low and concentrated | High and dilute |
| Serum sodium | Low | High |
| Volume status | Water held back | Dehydration |
Hematology: The Blood
Blood is a liquid organ. It carries oxygen, stops leaks, and defends the body. So when blood goes wrong, the whole body feels it. This chapter shows how blood cells are made. It covers the anemias that starve tissues of oxygen. It covers bleeding and clotting disorders. It covers the rules of blood typing and transfusion. And it covers the cancers of the blood itself.
By the end of this chapter you can
- Describe how blood cells are made (hematopoiesis) and what erythropoietin does.
- Sort the common anemias and match each one to its cause.
- Explain hemostasis and the main bleeding and clotting disorders.
- Use ABO/Rh matching rules and act on a transfusion reaction.
- Tell leukemia, lymphoma, and multiple myeloma apart.
Section 1Blood, marrow & how cells are made
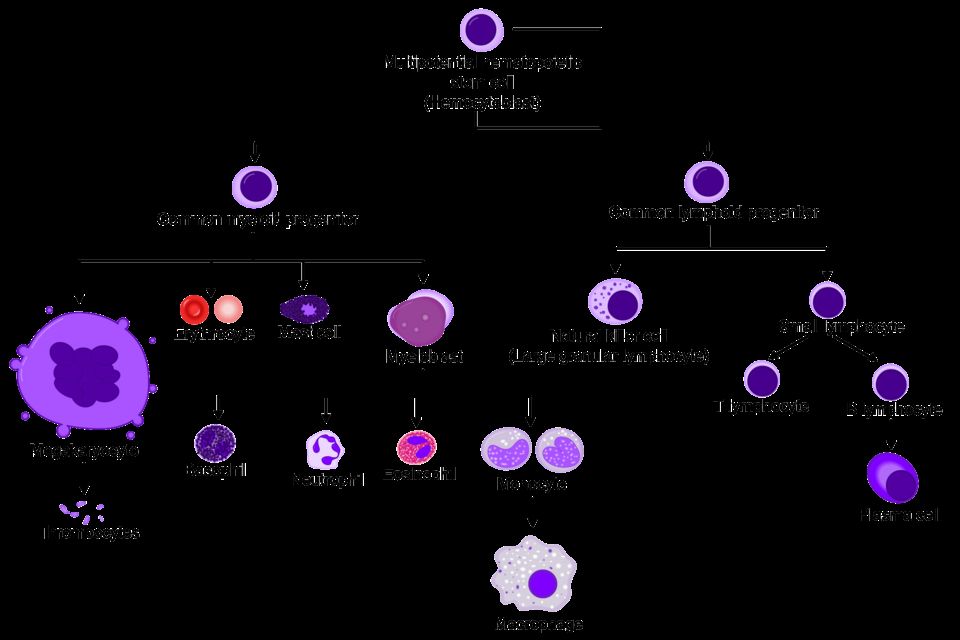
Think of blood as a river that touches every cell you own. It looks like a simple red liquid. It is really a connective tissue, which means living cells floating in fluid. Blood brings oxygen and nutrients to cells. It hauls away carbon dioxide and waste. It moves hormones and immune defenders around. It helps clot a wound. It even steadies your temperature and your pH. So when something goes wrong with blood, the effects show up everywhere at once. Everything depends on it.
What blood is made of
Spin a tube of blood in a centrifuge and it splits into layers. The top ~55% is plasma, a straw-colored fluid that is mostly water. Plasma also carries proteins, electrolytes, glucose, and wastes. The key proteins are albumin, which holds fluid inside vessels, plus clotting factors and antibodies. The bottom ~45% is packed red cells. That percentage is the hematocrit. A thin middle layer, the buffy coat, holds white cells and platelets.
- Red blood cells (erythrocytes) - carry oxygen. There are far more of these than any other blood cell.
- White blood cells (leukocytes) - the immune army. They include neutrophils, lymphocytes, monocytes, eosinophils, and basophils.
- Platelets (thrombocytes) - bits of cells that plug leaks and start clotting.
| Feature | Red cells | Platelets |
|---|---|---|
| Main job | Carry oxygen | Stop bleeding (hemostasis) |
| Has a nucleus? | No (mature RBCs) | No - they are pieces of cells |
| Typical lifespan | About 120 days | About 8 to 10 days |
| Made from | Bone marrow stem cells | Megakaryocytes in marrow |
Hematopoiesis - where blood cells are born
Every blood cell traces back to one ancestor. It is the hematopoietic stem cell (HSC), and it lives in the red bone marrow. In adults that marrow sits mainly in the pelvis, sternum, vertebrae, and the ends of long bones. The whole building process is called hematopoiesis. A stem cell is pluripotent, so it can turn into any blood cell. It also copies itself, so the factory never runs out. As daughter cells grow up, they commit to one of two big lines. The myeloid line makes red cells, platelets, and most white cells. The lymphoid line makes B and T lymphocytes. The marrow replaces worn-out cells all day long. So anything that harms the marrow can drop all the cell lines at once. Chemotherapy, radiation, leukemia crowding it out, and aplastic anemia all do that. Low counts in every line is called pancytopenia.
Erythropoietin - the kidney's oxygen alarm
How does the body know to make more red cells? The kidneys work as oxygen sensors. They notice when too little oxygen reaches their own tissue. That low-oxygen state is hypoxia. It can come from blood loss, high altitude, or lung disease. The kidneys then release a hormone called erythropoietin (EPO). EPO travels to the bone marrow and tells it to ramp up red cell production. This is a beautiful negative-feedback loop. More red cells means more oxygen delivered. That quiets the alarm, so EPO drops again.
This explains a classic clinical picture. In chronic kidney disease, the damaged kidneys stop making enough EPO. The marrow never gets the signal. So the patient gets anemia of chronic kidney disease, even though the marrow itself is healthy. That is why these patients are often treated with man-made EPO. The same loop explains why athletes and people living high in the mountains run higher red cell counts.
Hemoglobin - how red cells carry oxygen
A red cell is basically a bag stuffed with hemoglobin (Hgb). Hemoglobin is the iron-containing protein that actually binds oxygen. Each hemoglobin molecule has four heme groups. Each heme holds one iron atom, and each iron grabs one oxygen molecule. So one hemoglobin carries up to four oxygen molecules. The red cell is a bendy biconcave disc, dented on both sides. That shape gives it lots of surface area. It also lets the cell squeeze through tiny capillaries.
This is why the pieces all have to line up. You need enough iron to build heme. You need enough vitamin B12 and folate to build the cell. And you need a healthy marrow that answers EPO. Take away any one of these and oxygen delivery falls. Low hemoglobin is anemia, and its symptoms flow straight from the mechanism. Tissues are starved of oxygen, so you see fatigue and pallor, which means pale skin. The heart speeds up to move the oxygen that is left. That brings tachycardia, a fast heart rate, plus shortness of breath. The hemoglobin and hematocrit are usually watched together. That pair is the fastest read on how much oxygen a patient's blood can carry.
Explore the loop in the figure below. Watch the spun tube, the kidney, and the marrow move together.
- Blood is a connective tissue. About 55% is plasma (water plus albumin, clotting factors, antibodies). About 45% is cells: red cells, white cells, and platelets.
- Hematopoiesis makes all blood cells from pluripotent stem cells in the red bone marrow. The cells split into myeloid and lymphoid lines. Marrow damage can cause pancytopenia.
- The kidneys sense low oxygen and release erythropoietin to drive red cell production. So chronic kidney disease causes anemia from lost EPO.
- Hemoglobin is the iron-based protein that binds oxygen. Each molecule carries up to four O2. Building it needs iron, B12, and folate.
- Low hemoglobin (anemia) starves tissues of oxygen. That brings fatigue, pallor, and a fast heart rate. Watch Hgb and hematocrit together.
Section 2Anemias
Every one of your cells needs a steady supply of oxygen to make energy. Oxygen does not travel through blood on its own. It rides on hemoglobin, the iron-rich protein packed inside your red blood cells (RBCs). Healthy bone marrow builds new RBCs all the time. It stuffs them with hemoglobin and sends them out to circulate for about 120 days. Anemia means there is not enough working hemoglobin to carry the oxygen your tissues need. Notice the wording. Anemia is not simply "low blood." It is low oxygen-carrying power. The cause may be too few RBCs, too little hemoglobin per cell, or hemoglobin that does not work.
The real problem is oxygen delivery to tissue. So the classic symptoms make sense once you trace the mechanism. Tissues starved of oxygen make less energy, so patients feel fatigue and weakness. Fewer red cells means less color showing through skin and mucous membranes. That shows up as pallor: pale skin, conjunctiva, and nail beds. The heart tries to make up for it by pumping faster to move what little oxygen there is. That causes tachycardia. The blood is also oxygen-poor, so patients breathe faster and feel short of breath, especially with effort. That is dyspnea. Almost every anemia shares these signs. The differences lie in why the hemoglobin is missing.
Iron-deficiency anemia (microcytic)
Iron sits at the core of the heme molecule that binds oxygen. Without enough iron, the marrow makes red cells that are small and pale. Small means microcytic, so the MCV is low. Pale means hypochromic. The cells simply cannot fill up with hemoglobin. This is the most common anemia worldwide. The causes fall into three buckets. Blood loss covers heavy menstrual periods, plus slow GI bleeding from ulcers or colon cancer that quietly drains iron. Increased demand covers pregnancy, infancy, and rapid growth. Poor intake or absorption covers diets low in iron and gut conditions. Lab clues include a low ferritin and a low serum iron. Ferritin is the body's storage form of iron.
B12 and folate deficiency (macrocytic)
Vitamin B12 and folate are both needed to build DNA. When they run short, developing red cells cannot divide properly. They grow large and fragile instead. That gives macrocytic (high MCV) megaloblastic anemia. Folate deficiency comes from a poor diet with few leafy greens, from alcohol use, or from the demands of pregnancy. B12 deficiency has one special cause worth memorizing: pernicious anemia. Absorbing B12 from food takes intrinsic factor, a protein made by the stomach's parietal cells. In pernicious anemia an autoimmune attack destroys those cells. Intrinsic factor disappears, so B12 cannot be absorbed no matter how much is eaten. It must be replaced by injection. One key distinction: B12 also maintains the nervous system. So its deficiency adds neurologic signs like numbness, tingling, and balance problems. Folate deficiency does not.
| Feature | Iron deficiency | B12 / folate deficiency |
|---|---|---|
| Cell size (MCV) | Small (microcytic) | Large (macrocytic) |
| Core problem | Too little hemoglobin | DNA and cell division fail |
| Typical cause | Blood loss, low intake | Poor diet, pernicious anemia |
| Neuro symptoms | No | Yes (B12 only) |
Hemolytic anemias and sickle cell disease
Hemolytic anemias happen when red cells are destroyed faster than the marrow can replace them. Hemolysis means RBC breakdown. Dying cells spill their contents, so you often see jaundice from the bilirubin released. The classic inherited example is sickle cell disease. A single genetic change makes abnormal hemoglobin called HbS. HbS molecules stick together when oxygen levels drop. Dehydration, infection, and cold can set that off too. The soft round RBC then warps into a rigid crescent, or sickle, shape. These stiff cells jam small vessels and block blood flow. That event is a vaso-occlusive crisis: sudden, severe pain as tissue downstream is starved of oxygen. Sickled cells are also fragile and are destroyed early. That drives long-term anemia.
Finally, aplastic anemia is a marrow-failure state. The bone marrow stops making blood cells at all. So RBCs, white cells, and platelets all fall together (pancytopenia). Explore the different anemia types in the figure below.
- Anemia is low working hemoglobin, so less oxygen reaches tissue. The shared signs are fatigue, pallor, fast heart rate, and shortness of breath. They all come from tissue hypoxia and the heart working harder.
- Iron-deficiency anemia is microcytic and the most common kind. A new case in an older adult means rule out GI bleeding.
- B12 and folate deficiencies are macrocytic. Only B12 deficiency causes nerve signs. Pernicious anemia is loss of intrinsic factor, which blocks B12 absorption.
- Sickle cell disease (HbS) sickles when oxygen is low, which causes painful vaso-occlusive crises. Manage with oxygen, fluids, and pain control.
- Aplastic anemia is bone marrow failure, and it produces pancytopenia.
Section 3Bleeding & clotting disorders
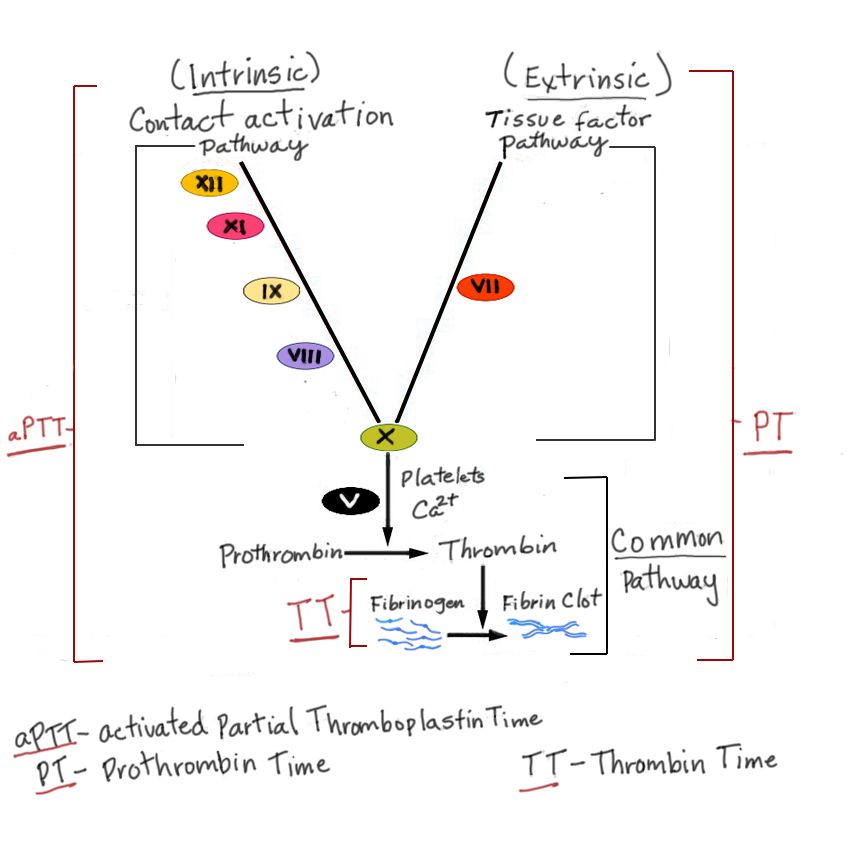
Every time you get a paper cut, a well-rehearsed emergency crew goes to work. The bleeding stops within minutes. This process is called hemostasis, which literally means "blood standing still." It runs in steps that overlap. Learn the normal order and you can see exactly what breaks in bleeding and clotting disorders.
Normal hemostasis: how the body plugs a leak
Three things happen fast the moment a blood vessel is injured. First comes vasoconstriction. The vessel clamps down to slow blood flow to the area. Second, the platelet plug forms. Platelets are tiny cell fragments that normally glide past smooth vessel walls. At an injury they touch exposed collagen. Then they stick, switch on, change shape, and clump together. A bridging protein called von Willebrand factor (vWF) helps them hold on. This soft plug is a quick fix. Third comes the coagulation cascade. It is a chain reaction of clotting proteins, called factors, that switch one another on in order. The cascade has an intrinsic and an extrinsic pathway, and the two meet. They turn prothrombin into thrombin. Thrombin then turns fibrinogen into fibrin, tough protein threads. Fibrin weaves through the platelet plug like rebar in concrete and makes the clot stable. Later, once healing is under way, fibrinolysis dissolves the clot.
Thrombocytopenia and ITP: too few platelets
Thrombocytopenia means a low platelet count. That usually means below 150,000/mm3. Serious bleeding risk often starts under 20,000. With too few platelets, the first plug is weak. Patients show petechiae, which are pinpoint red spots. They also show purpura, easy bruising, nosebleeds, and gum bleeding. In immune thrombocytopenic purpura (ITP), the immune system makes antibodies that tag the patient's own platelets. The spleen then destroys them. In children it often follows a viral illness. In adults it tends to be more long-lasting. Treatment targets the immune attack. Options are corticosteroids, IVIG, and sometimes removing the spleen (splenectomy).
Hemophilia and von Willebrand disease: the factor problems
Hemophilia is an inherited shortage of a clotting factor. The platelet plug forms fine, but the fibrin mesh never sets properly. Both common types are X-linked recessive. That is why they classically affect males, whose mothers are carriers. Hemophilia A is a lack of factor VIII. Hemophilia B (Christmas disease) is a lack of factor IX. The two look identical. You see hemarthrosis, which is deep bleeding into joints. You also see muscle bleeds and long bleeding after surgery or trauma. Lab work shows a prolonged aPTT with a normal platelet count. Treatment is to replace the missing factor.
Von Willebrand disease is the most common inherited bleeding disorder. It is usually autosomal, so it affects both sexes equally. vWF is missing or faulty, so platelets cannot stick well. vWF also carries factor VIII, so that factor drops too. The result blends both worlds. You get mucosal, platelet-type bleeding such as heavy menstrual periods and nosebleeds. You also get a mild factor picture.
| Feature | ITP | Hemophilia A/B | von Willebrand |
|---|---|---|---|
| Core defect | Platelets destroyed | Factor VIII or IX missing | vWF missing or faulty |
| Inheritance | Acquired (autoimmune) | X-linked recessive | Usually autosomal |
| Bleeding type | Petechiae, mucosal | Deep joints, muscles | Mucosal, menstrual |
| Key lab | Low platelet count | Prolonged aPTT | Low vWF antigen and activity (ristocetin cofactor assay), sometimes low VIII |
DIC and DVT: when clotting itself becomes the disease
Disseminated intravascular coagulation (DIC) is a dangerous paradox. Sepsis, trauma, childbirth problems, or cancer can trigger it. The cascade fires everywhere at once and throws tiny clots all through the smallest vessels. This consumes platelets and clotting factors faster than the body can replace them. The result is a patient who clots and bleeds at the same time. The microclots damage organs. The used-up supply leaves the patient oozing from IV sites, gums, and incisions. Labs show low platelets, prolonged PT and aPTT, low fibrinogen, and a high D-dimer. DIC is always secondary to something else. So treatment means fixing the underlying cause.
Clotting can also go wrong in a single vessel. A deep vein thrombosis (DVT) is a clot in a deep vein, usually in the leg. Virchow's triad names the three ingredients that promote it. Venous stasis is slow blood flow from not moving. Endothelial injury is damage to the vessel wall. Hypercoagulability is blood that clots too readily. The feared complication is a piece breaking off. It then travels to the lungs as a pulmonary embolism.
You can explore hemostasis, bleeding, and clotting in the interactive figure below.
- Hemostasis runs in order: vasoconstriction, then the platelet plug (which needs vWF), then the coagulation cascade making thrombin and fibrin.
- Platelet or vWF problems cause immediate, superficial bleeding such as petechiae and mucosal ooze. Factor problems cause delayed, deep bleeding into joints and muscles.
- ITP is autoimmune platelet destruction. Hemophilia A (factor VIII) and B (factor IX) are X-linked. Von Willebrand disease is the most common inherited bleeding disorder.
- DIC consumes platelets and factors, so the patient clots AND bleeds at once. The D-dimer is high. DIC is always secondary to another problem.
- A DVT forms through Virchow's triad: stasis, endothelial injury, and easy clotting. It can embolize to the lungs.
Section 4Blood types & transfusion
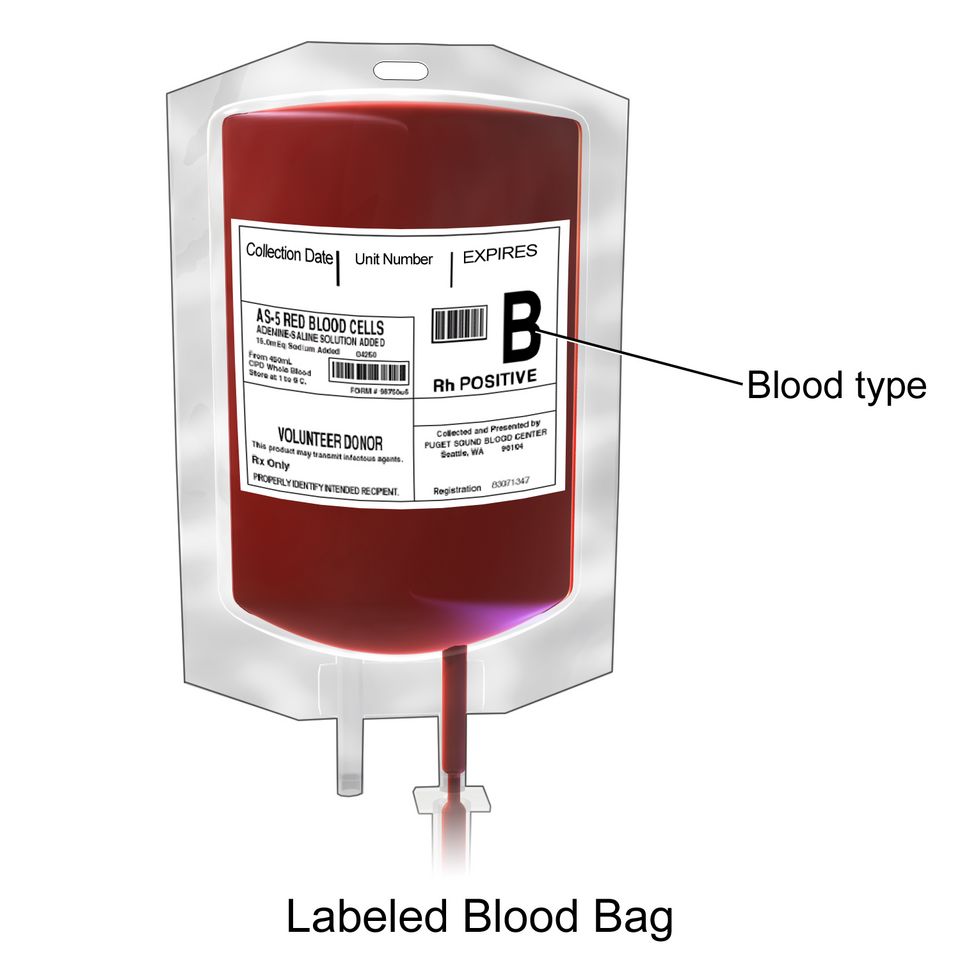
Every drop of blood carries a kind of ID badge. Tiny protein and sugar markers called antigens sit on the surface of your red blood cells. Floating in your plasma are antibodies, immune proteins that attack any antigen your body does not know as its own. Early in life your immune system learns to leave your own red cells alone. It stays armed against foreign ones. This self-versus-nonself check is the whole reason transfusions must be matched. Give someone blood carrying an antigen their plasma has antibodies against, and those antibodies clamp onto the donor cells and destroy them. Sometimes that happens fast enough to threaten life.
The ABO system
The ABO system sorts blood into four types. The sorting depends on which antigens sit on the red cells. Type A cells carry the A antigen. Type B cells carry B. Type AB cells carry both. Type O cells carry neither. Here is the elegant part, and it feels backward at first. Your plasma automatically makes antibodies against whatever antigen you lack. So type A blood has anti-B antibodies. Type B has anti-A. Type O has both anti-A and anti-B. Type AB has neither.
Type O cells carry no A or B antigen. So there is nothing on them for a recipient's antibodies to attack. That is why O-negative is called the universal donor. It is the go-to unit in a trauma emergency, before typing is done. Type AB plasma carries no anti-A or anti-B antibodies. So an AB person can receive any ABO type. That makes AB-positive the universal recipient.
| Blood type | Antigen on red cell | Antibody in plasma |
|---|---|---|
| A | A | anti-B |
| B | B | anti-A |
| AB | A and B | none |
| O | none | anti-A and anti-B |
The Rh factor and hemolytic disease of the newborn
A second marker sits on top of ABO. It is the Rh factor, also called the D antigen. If your red cells carry it, you are Rh-positive. If not, you are Rh-negative. Rh differs from ABO in one way. Rh-negative people do not come with ready-made anti-Rh antibodies. They build them only after they are exposed to Rh-positive blood. That build-up is called sensitization.
This matters most in pregnancy. Say an Rh-negative mother carries an Rh-positive baby. A small leak of fetal blood, often during delivery, can sensitize her. The first baby is usually fine. But in a later Rh-positive pregnancy her anti-Rh antibodies can cross the placenta. They then destroy the fetal red cells. This is hemolytic disease of the newborn (HDN), also called erythroblastosis fetalis. It causes fetal anemia, jaundice, and heart failure.
The fix is RhoGAM (Rh immune globulin). It is given around 28 weeks and again within 72 hours of delivery. RhoGAM mops up any stray Rh-positive fetal cells. It does this before the mother's immune system can notice them and start making its own permanent antibodies. So sensitization never happens.
Type, screen, and crossmatch
Before any transfusion the lab does three things. It types the blood, which means finding the ABO and Rh. It screens the plasma for unexpected antibodies. And it crossmatches, mixing donor cells with recipient plasma to confirm they do not clump. Clumping is called agglutination. It is the visible warning that antibodies are attacking, and it means that unit is unsafe. This careful matching is why transfusion is normally so safe.
When a transfusion goes wrong
Reactions still happen, and telling them apart guides your response.
- Acute hemolytic reaction is the feared one. It usually comes from an ABO mismatch, often a clerical or ID error. Recipient antibodies destroy the donor cells and release hemoglobin. That can trigger fever, chills, flank or back pain, dark urine, hypotension (low blood pressure), and kidney failure.
- Febrile non-hemolytic reaction is the most common one. The recipient reacts to donor white blood cells and gets fever and chills. It is uncomfortable but usually not dangerous.
- Allergic reaction is a response to donor plasma proteins. It ranges from hives and itching up to anaphylaxis.
For any suspected reaction the priority is the same. Stop the transfusion immediately. Keep the IV line open with normal saline, using fresh tubing so no more blood enters. Then check vital signs. Notify the provider and the blood bank. Send the blood bag and tubing back for analysis.
Work through a reaction in the figure below. See what stopping the unit early saves.
Explore the ABO and Rh types in the figure below.
- ABO type is set by antigens on the red cells. Plasma carries antibodies against the antigens you lack. So O-negative is the universal donor and AB-positive is the universal recipient.
- Rh-negative people make anti-Rh antibodies only after exposure. RhoGAM prevents maternal sensitization and hemolytic disease of the newborn.
- Blood is typed, screened, and crossmatched to catch agglutination before it reaches the patient.
- Acute hemolytic reactions from an ABO mismatch are the most dangerous. Febrile and allergic reactions are more common but usually milder.
- For any suspected transfusion reaction, stop the transfusion first. Then keep the line open with saline and notify the provider and blood bank.
Section 5Blood cancers
Your bone marrow is a busy blood factory. Deep inside your big bones, hematopoietic stem cells divide and mature. They become three great families of blood cells. Red cells carry oxygen. Platelets plug leaks. White cells fight infection. Normally this factory is tightly controlled. Every cell knows when to grow, when to stop, and when to die. Blood cancers happen when one line of blood cells loses that control. The cells then multiply with no brake. The trouble is not just the abnormal cells themselves. They also take up space, resources, and jobs that healthy cells need. Work out which cell went rogue and where it piles up. That explains almost every symptom your patient will have.
Leukemia: the marrow gets crowded out
Leukemia is cancer of the white-cell-forming lines in the bone marrow. Immature, useless white cells, often called blasts, reproduce so fast that they physically crowd out normal production. Picture a factory floor jammed with defective units, so nothing else can be built. That single mechanism explains the classic triad. Too few red cells means anemia, with fatigue, pallor, and shortness of breath. Too few platelets means thrombocytopenia, with easy bruising, petechiae, and bleeding gums. Too few functional white cells means dangerous infection risk. That risk holds even though the total white count on the lab report may look high.
Leukemias are sorted two ways. Acute versus chronic describes tempo. Acute leukemias explode with immature blasts and make patients sick in days to weeks. Chronic leukemias smolder for months to years, with more mature-looking cells. Myeloid versus lymphocytic describes the parent line. Myeloid cells give rise to red cells, platelets, and granulocytes. Lymphocytic cells give rise to lymphocytes. Combine the two pairs and you get the four big names.
| Type | Who it usually affects | Key feature |
|---|---|---|
| ALL (acute lymphocytic) | Children most often | The most common cancer in childhood; responds well to treatment |
| AML (acute myeloid) | Older adults | Blasts may show Auer rods |
| CLL (chronic lymphocytic) | Older adults | Often found by chance on routine bloodwork |
| CML (chronic myeloid) | Middle-aged adults | Linked to the Philadelphia chromosome |
Lymphoma: cancer that builds tumors in lymph tissue
Leukemia floods the marrow and blood. Lymphoma works differently. It is a solid cancer of lymphocytes that grows into masses. Those masses sit inside lymph nodes and lymphoid organs like the spleen. The hallmark sign is painless lymphadenopathy. That means a firm, swollen, non-tender node in the neck, armpit, or groin. Patients often also have B symptoms. That is the textbook name for three findings together: drenching night sweats, fever with no clear cause, and weight loss.
Lymphomas split into two branches. Hodgkin lymphoma is defined by one giant abnormal cell on biopsy, the Reed-Sternberg cell. It usually starts in one node region. It then spreads in an orderly, predictable pattern, which helps make it one of the more curable cancers. Non-Hodgkin lymphoma is a large, diverse group with no Reed-Sternberg cells. It tends to be more scattered and less predictable at diagnosis. It is also far more common overall.
Multiple myeloma: rogue plasma cells attack bone and kidney
Plasma cells are the mature antibody-factory version of B lymphocytes. In multiple myeloma, one plasma cell line turns malignant. It churns out a single useless antibody, called a monoclonal (M) protein, while crowding the marrow. Its damage spells out neatly with the mnemonic CRAB: Calcium elevated, Renal (kidney) injury, Anemia, and Bone lesions.
- Bone lesions: myeloma cells activate osteoclasts that eat away bone. That leaves punched-out lytic lesions, deep bone pain, and pathologic fractures.
- Hypercalcemia: the dissolving bone dumps calcium into the blood. That causes confusion, constipation, and thirst.
- Kidney injury: the flood of M protein and calcium clogs and damages the renal tubules.
- Anemia and infection: the marrow is crowded, and the antibodies made do not actually work.
Explore the interactive figure below to see how leukemia fills the marrow, how lymphoma builds masses in nodes, and how myeloma eats into bone.
- Leukemia crowds the bone marrow with abnormal white cells. That causes anemia, bleeding from low platelets, and infection. It is classified acute versus chronic and myeloid versus lymphocytic (ALL, AML, CLL, CML).
- Lymphoma forms solid masses in lymph nodes. Hodgkin shows Reed-Sternberg cells and spreads in a set pattern. Non-Hodgkin is more common and more scattered. Watch for painless lymphadenopathy plus B symptoms.
- Multiple myeloma is malignant plasma cells. Remember CRAB: hyperCalcemia, Renal injury, Anemia, and Bone lytic lesions. A monoclonal M protein drives it.
- The shared red flags across blood cancers are fatigue, frequent infections, and easy bruising. A high WBC in leukemia still means the patient is immunocompromised.
The chapter in one breath
- Hematopoiesis builds every blood cell from a single kind of bone-marrow stem cell. Erythropoietin from the kidney drives red-cell production, so kidney failure often causes anemia.
- Blood splits into plasma (fluid, proteins, clotting factors) and formed elements. RBCs carry oxygen on hemoglobin. WBCs fight infection. Platelets plug leaks.
- Iron-deficiency anemia makes RBCs small and pale (microcytic, hypochromic) with a low ferritin. It causes fatigue, pallor, and pica.
- Vitamin B12/folate deficiency makes large immature cells (macrocytic, megaloblastic anemia). Only B12 loss adds nerve signs, and B12 needs stomach intrinsic factor to be absorbed.
- Sickle cell anemia is inherited hemoglobin S. It warps RBCs when they lose oxygen and sets off painful vaso-occlusive crises. Hemolytic anemias destroy cells early and raise bilirubin.
- Clotting fails from too few platelets (thrombocytopenia), missing factors (hemophilia), or widespread clotting-then-bleeding (DIC). Watch for petechiae, bruising, and prolonged bleeding.
- Transfusion safety rests on ABO and Rh typing. Type O is the universal RBC donor and AB the universal recipient. A mismatch triggers a life-threatening hemolytic reaction.
- Leukemias flood the marrow with abnormal white cells and crowd out normal lines. Lymphomas grow in lymph nodes (Hodgkin vs non-Hodgkin). Multiple myeloma is malignant plasma cells eating bone.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- ABO system
- The main way red cells are grouped (A, B, AB, O), based on which sugar antigens sit on the red-cell surface. Your plasma carries antibodies against the antigens you lack, so a mismatched transfusion sets off a dangerous hemolytic reaction.
- Anemia
- Too few red blood cells, or too little hemoglobin, so the blood carries less oxygen. It usually brings fatigue, pallor, and shortness of breath.
- DIC (disseminated intravascular coagulation)
- A life-threatening emergency. Clotting switches on all through the small vessels and uses up clotting factors and platelets so fast that the patient both clots and bleeds at the same time.
- Erythropoietin
- A hormone released mainly by the kidneys when oxygen is low. It tells the bone marrow to make more red blood cells.
- Hematopoiesis
- The ongoing process, mostly in red bone marrow, in which stem cells mature into all the formed elements of blood: red cells, white cells, and platelets.
- Hemoglobin
- The iron-containing protein inside red blood cells. It binds oxygen in the lungs and releases it to the tissues. It also gives blood its red color.
- Hemophilia
- An inherited bleeding disorder, usually X-linked, caused by a missing or low clotting factor (factor VIII in type A, factor IX in type B). Bleeding is prolonged and often goes into joints and muscles.
- Hemostasis
- The body's step-by-step way of stopping bleeding. It moves from blood-vessel spasm to a platelet plug and finally to a stable fibrin clot.
- Intrinsic factor
- A protein made by the stomach's parietal cells. It binds vitamin B12 so B12 can be absorbed in the small intestine. Without it, B12 deficiency develops.
- Leukemia
- A cancer of blood-forming tissue. The marrow makes too many abnormal, immature white blood cells, and these crowd out healthy cells. The patient is then prone to infection, bleeding, and anemia.
- Macrocytic
- A word for red blood cells that are abnormally large. This pattern is often seen in vitamin B12 or folate deficiency.
- Microcytic
- A word for red blood cells that are abnormally small. This pattern is classic for iron-deficiency anemia.
- Pernicious anemia
- A macrocytic anemia caused by loss of intrinsic factor, often from autoimmune damage to the stomach lining. Vitamin B12 cannot be absorbed, so red cells do not mature properly.
- Sickle cell disease
- An inherited disorder in which abnormal hemoglobin S makes red cells stiffen into a crescent shape under low-oxygen stress. The rigid cells block small vessels and cause painful crises, hemolysis, and organ damage.
- Thrombocytopenia
- An abnormally low platelet count. It raises the risk of easy bruising and of bleeding that is prolonged or starts on its own.
- Virchow's triad
- The three conditions that together invite an abnormal clot: sluggish blood flow (stasis), vessel-wall injury, and blood that clots too easily (hypercoagulability).
DrillFlashcards for this unit
These are the Week 8 cards. It is the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
Cardiovascular
The cardiovascular system is a pump and a plumbing network that never rests. When one small part fails, the trouble spreads everywhere. This chapter starts with the pressure inside the pipes and ends with the muscle of the pump itself. You will cover hypertension, coronary disease and heart attack, heart failure, valve problems, the rhythms on the EKG, and the diseases of the peripheral vessels.
By the end of this chapter you can
- Explain what sets blood pressure, and how hypertension damages organs.
- Tell stable angina apart from a myocardial infarction, and name its markers.
- Compare left- and right-sided failure, and systolic with diastolic heart failure.
- Tell valve stenosis from regurgitation.
- Read the basic EKG waves. Spot dangerous arrhythmias and peripheral vascular disease.
Section 1Blood pressure & hypertension
Every time your heart beats, it pushes blood against the walls of your arteries. Blood pressure is the force of that push. We write it as two numbers, like 120/80 mmHg. The top number (systolic) is the pressure while the heart squeezes. The bottom number (diastolic) is the pressure while the heart relaxes between beats. Healthy pressure keeps blood moving to every organ. It does that without pounding the vessels hard enough to damage them.
What actually sets the pressure
Two things multiply together to set your blood pressure. One is how much blood the heart pumps each minute. The other is how tight the pipes are. In textbook terms, BP = cardiac output (CO) times systemic vascular resistance (SVR). Cardiac output is heart rate times stroke volume. Stroke volume is how much blood leaves the heart with each beat. Systemic vascular resistance is how narrow or squeezed down the arterioles are. Think of a garden hose. Turn the water up, and the pressure rises. Pinch the nozzle tighter, and the pressure rises too. That is why a racing heart, extra fluid, or clamped-down vessels all push the number up.
How the body keeps it steady
Your body corrects blood pressure minute by minute and day by day. It uses two main systems.
Baroreceptors are stretch sensors in the carotid arteries and the aortic arch. When pressure drops, they feel less stretch. They tell the brainstem to speed the heart and tighten the vessels. When pressure spikes, they do the opposite. This is the fast reflex, working second by second. It is also why you may feel dizzy if you stand up too quickly. The reflex needs a moment to catch up.
The RAAS (renin-angiotensin-aldosterone system) is the slower controller for the long run. When the kidneys sense low pressure or low blood flow, they release renin. Renin starts a chain that makes angiotensin II. Angiotensin II is a powerful vasoconstrictor, so it tightens vessels and raises SVR. It also tells the adrenal glands to release aldosterone. Aldosterone tells the kidneys to hold on to sodium and water. That raises blood volume, and so it raises cardiac output. Both actions raise pressure. Many blood pressure drugs (ACE inhibitors, ARBs) work by cutting into this exact pathway.
When pressure stays too high: hypertension
Hypertension means blood pressure that stays up over time. The usual cutoff is 130/80 mmHg or higher on repeated readings. It shows up in two flavors.
| Feature | Primary (essential) | Secondary |
|---|---|---|
| How common | About 90-95% of cases | About 5-10% of cases |
| Cause | No single cause you can point to. Genes, aging, salt, weight, and stress all add up | One underlying illness you can name |
| Typical triggers | Family history, obesity, a high-sodium diet, too little activity | Kidney disease, a narrowed renal artery, pheochromocytoma, sleep apnea, certain drugs |
| Onset clue | Slow, and often starts in midlife | Sudden, very high, or hard to treat. Sometimes in young patients |
| Treatment focus | Lifestyle plus medication | Fix the cause underneath |
Primary hypertension has no single cause you can fix. It grows out of genes, aging vessels, a lot of sodium, and often extra weight. Secondary hypertension is driven by one specific problem you can name. Treat that problem, and the high pressure can actually go away.
The silent killer and its targets
Hypertension has earned the nickname the silent killer. It usually causes no symptoms for years. There is no headache and no warning. The person feels fine while the high pressure quietly grinds away at organs. By the time the damage shows, it can be far along.
That damage is called target-organ damage, and it strikes the organs packed with blood vessels:
- Heart: the left ventricle must pump against higher resistance, so its wall thickens (left ventricular hypertrophy). In time it can fail. The coronary arteries also stiffen, which raises the risk of a heart attack.
- Brain: weak, pressure-battered vessels can burst or clot, which causes a stroke. Years of damage also feed vascular dementia.
- Kidneys: the tiny filtering vessels scar and narrow. That leads to chronic kidney disease, and in the end to kidney failure.
- Eyes: the vessels in the retina are a visible window onto this damage. Hypertensive retinopathy can blur or steal vision.
- Blood pressure equals cardiac output times systemic vascular resistance. More fluid, a faster heart, or tighter vessels all raise it.
- Baroreceptors correct pressure fast, moment to moment. The RAAS is slower. It tightens vessels (angiotensin II) and holds on to salt and water (aldosterone).
- Primary (essential) hypertension is 90-95% of cases and has no single cause. Secondary hypertension has a cause you can name, and often treat.
- Hypertension is the silent killer. It causes no symptoms while it quietly harms the heart, brain, kidneys, and eyes. That is target-organ damage.
- Patients feel fine, so teaching them to keep taking their drugs is critical. ACE inhibitors and ARBs work by blocking the RAAS pathway.
Section 2Coronary artery disease, angina & MI
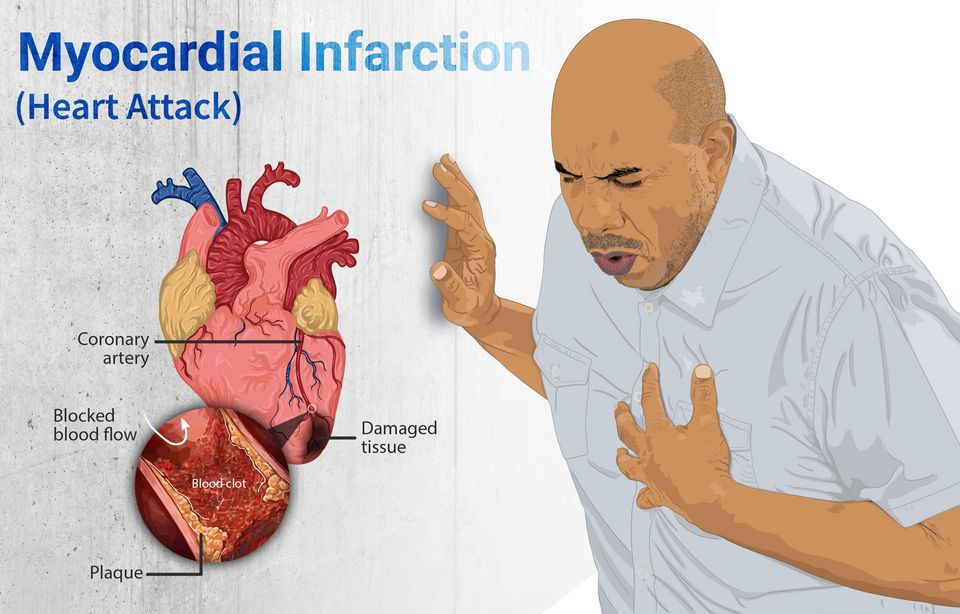
Your heart is a muscle. Like any muscle, it needs a steady supply of oxygen-rich blood to keep working. But here is the twist. Gallons of blood rush through its chambers every hour, and the heart muscle cannot use that blood. It feeds itself through its own private plumbing, the coronary arteries. These vessels branch off the aorta and wrap around the outside of the heart. When they are open and healthy, supply keeps up with demand easily, and the muscle never notices. Trouble begins when the pipes get narrow.
How the coronary arteries get clogged
Over years, cholesterol, inflammatory cells, and cell debris build up inside the artery wall. That fatty deposit is called a plaque. This slow, silent process is atherosclerosis. As a plaque grows, it stiffens the vessel and squeezes the channel (the lumen) smaller. Less blood can get through. That is coronary artery disease (CAD). For a long time the narrowing causes no symptoms, because a resting heart does not ask for much. The problem shows up when the heart has to work harder.
Angina: the heart's cry for oxygen
Angina is chest pain or pressure caused by myocardial ischemia. Ischemia means the muscle is not getting enough oxygen for the work it is doing. It is a problem of demand versus supply. In stable angina, a fixed plaque leaves just enough room for blood flow at rest. Then the person climbs stairs, shovels snow, or gets upset. Heart rate and force climb, so oxygen demand outruns the narrowed supply. The muscle aches. The classic tip-off is that the pain is predictable. It comes on with exertion. It fades within minutes of rest or a nitroglycerin tablet, which widens vessels and eases the heart's workload. In stable angina the muscle is starved, but it is not yet dying.
Unstable angina is a different and far more dangerous animal. Here a plaque has turned fragile and has partly broken open. Pain now comes at rest, lasts longer, or is suddenly worse than the patient's usual pattern. It is one of the acute coronary syndromes (ACS). It warns you that a heart attack may be brewing.
| Feature | Stable angina | Unstable angina |
|---|---|---|
| Trigger | Exertion or stress you can predict | Often at rest, with no clear trigger |
| Plaque | Fixed, stable narrowing | Broken open and unstable |
| Relief | Rest or nitroglycerin, within minutes | Poorly relieved, and may keep going |
| Muscle status | Ischemic, meaning starved of oxygen, but not dying | At high risk. An emergency |
When the pipe closes: myocardial infarction
A myocardial infarction (MI) is a heart attack. It happens when an unstable plaque ruptures. The body treats the exposed plaque like a wound. Platelets and clotting factors rush in and build a blood clot, called a thrombus. If that clot blocks the artery all the way, blood flow stops cold. The muscle downstream is cut off from oxygen at once. The starved heart muscle begins to die within about 20 to 30 minutes, and the damage spreads over the next few hours. This is infarction, which means irreversible tissue death (necrosis). It is not the reversible starvation of angina. That is why the phrase time is muscle matters so much. Every minute the artery stays blocked, more heart is lost for good.
Recognizing an MI
The hallmark is chest pain. It is often crushing, heavy, or squeezing pressure. It may spread to the left arm, the jaw, or the back. It often comes with sweating (diaphoresis), nausea, and shortness of breath. But atypical presentations are common and easy to miss. Women, older adults, and people with diabetes may feel only fatigue, indigestion, or breathlessness. There may be no dramatic chest pain at all, because neuropathy and different symptom patterns blunt the classic warning. Three tools confirm the diagnosis:
- ECG: a STEMI (ST-elevation MI) shows a raised ST segment. That means the full thickness of the muscle is being injured by a completely blocked artery. It is a true emergency, and the vessel must be reopened right away.
- Troponin: when heart cells die, they leak the protein troponin into the blood. A rising troponin level over serial draws is the most specific sign that muscle has truly been damaged.
- The story: the pattern and timing of the pain ties it all together.
- Atherosclerosis narrows the coronary arteries over years, so less blood reaches the heart muscle. That is coronary artery disease.
- Stable angina is reversible ischemia from a demand-supply mismatch, and rest or nitroglycerin relieves it. Unstable angina comes at rest and warns of an MI to come.
- A myocardial infarction follows plaque rupture and a thrombus that blocks the artery. Muscle dies, and that death is permanent.
- Spot an MI by chest pain (watch for atypical presentations), ST-elevation on the ECG, and rising troponin. Remember that time is muscle.
Section 3Heart failure
Picture the heart as a two-sided pump that works every second of your life. The right side collects oxygen-poor blood coming back from the body and pushes it to the lungs. The left side takes freshly oxygenated blood from the lungs and drives it out to every organ. In a healthy heart, the blood coming in matches the blood going out, and tissues get just the oxygen they need. Heart failure is what happens when the pump can no longer keep up with the body's demand. It does not mean the heart has stopped. It means the heart cannot move blood forward well. Blood backs up behind the weak side, and organs downstream are left short.
Left-sided failure: the backup floods the lungs
The left ventricle is the strongest chamber, because it must push blood to the whole body. When it weakens, blood cannot move forward fast enough. It dams up behind the left side, back into the capillaries of the lungs. The rising pressure forces fluid out of those capillaries and into the air sacs. That state is pulmonary congestion, also called pulmonary edema. This is why left-sided failure is a lung story. Patients feel short of breath (dyspnea), above all with exertion. Lying flat lets fluid shift toward the lungs, so they wake up gasping or prop themselves up on pillows. Those two signs are orthopnea and paroxysmal nocturnal dyspnea. On auscultation, which just means listening to the chest, you hear crackles (rales). That is the sound of air bubbling through fluid-filled alveoli. A frothy or pink-tinged cough can appear as fluid leaks into the airways.
Right-sided failure: the backup floods the body
When the right ventricle fails, blood dams up behind it. It backs into the systemic veins that were trying to return blood to the heart. Now the congestion shows up in the body, not the lungs. Neck veins bulge under the backed-up pressure, which is jugular venous distention (JVD). Leaked fluid settles in the ankles and legs where gravity pulls it, giving peripheral edema. Blood engorges the liver and enlarges it, which is hepatomegaly. The single most common cause of right-sided failure is left-sided failure itself. Lung congestion strains the right ventricle over time. That is why untreated left failure often becomes biventricular, meaning both sides fail.
| Feature | Left-sided failure | Right-sided failure |
|---|---|---|
| Blood backs up into | Lungs (pulmonary circulation) | Body (systemic veins) |
| Hallmark signs | Dyspnea, orthopnea, crackles | JVD, peripheral edema, hepatomegaly |
| Classic complaint | Cannot breathe lying flat | Swollen legs, weight gain |
| Common cause | Hypertension, an earlier MI | Left-sided failure, lung disease |
Systolic vs diastolic: a squeeze problem or a filling problem
Failure can come from two different mechanical faults. In systolic failure, the ventricle is weak and cannot contract forcefully. It pushes out a smaller share of the blood it holds. We measure that share as the ejection fraction (EF), which here is often under 40%. Normal is usually 55 to 70%. This type is called HFrEF (heart failure with reduced ejection fraction). In diastolic failure, the squeeze is fine, but the ventricle is stiff. It cannot relax and fill properly, so less blood is there to pump even though the squeeze percentage looks normal. This type is HFpEF (preserved ejection fraction). Here is the key point. A normal EF does not rule out heart failure.
Compensation that turns against you
When cardiac output drops, the body reacts as if it were bleeding. The sympathetic nervous system fires. It speeds the heart and squeezes vessels to prop up blood pressure. The kidneys sense low flow and switch on the renin-angiotensin-aldosterone system (RAAS), which holds on to sodium and water and tightens arteries. In the short run these moves buy time. Over weeks they backfire. The extra fluid worsens the congestion. The higher pressure makes the failing heart work harder. Constant overdrive also drives ventricular remodeling, in which the heart enlarges and stiffens. This vicious cycle explains the mainstay drugs. ACE inhibitors, ARBs, and beta-blockers all work by blocking these compensations.
The stretched, overworked ventricles release B-type natriuretic peptide (BNP), a hormone that tries to make the body shed fluid. Because BNP rises when the wall is stretched, a high level is a useful marker. It points to heart failure, rather than the lungs, as the cause of shortness of breath. Explore the left- versus right-sided comparison below.
- Heart failure is a pump that cannot meet the body's demand. Blood backs up behind the failing side.
- Left-sided failure floods the lungs: dyspnea, orthopnea, crackles. Right-sided failure floods the body: JVD, peripheral edema, hepatomegaly.
- Systolic failure (HFrEF) is a weak squeeze with a low EF. Diastolic failure (HFpEF) is a stiff ventricle that fills poorly, with a normal EF.
- RAAS and sympathetic activation help at first. In time they worsen congestion and drive remodeling.
- BNP rises when the ventricle is stretched, so it helps confirm that dyspnea is coming from the heart.
Section 4Valve disorders
Picture your heart as a house with four rooms and four one-way doors between them. Those doors are your valves, and their whole job is simple. Let blood move forward, and never let it slip backward. When the heart squeezes, the doors ahead swing open easily. When it relaxes, they snap shut tight so nothing leaks back. Two of these doors do the heavy lifting on the left side of the heart, the side that pushes blood out to the whole body. The mitral valve sits between the left atrium and the left ventricle. The aortic valve sits between the left ventricle and the aorta. When a valve stops opening well, or stops sealing well, the heart has to work harder for every single beat. Over time that extra work reshapes the chamber behind it.
The two ways a valve fails: stenosis vs. regurgitation
There are really only two things that can go wrong with a door. Either it is hard to push open, or it does not shut all the way. That is the entire concept.
Stenosis means the valve has grown stiff, thick, or narrow, so the opening is too small. The chamber behind it must build much higher pressure to force blood through the tight gap. It is like trying to breathe through a pinched straw. Regurgitation means the valve does not seal, so some blood sloshes backward with each beat. It is also called insufficiency, or a leaky or incompetent valve. Now the chamber has to pump the same blood twice. It handles the normal load plus the volume that leaked back. Stenosis is mainly a pressure problem. Regurgitation is mainly a volume problem. That difference predicts how the heart changes.
| Feature | Stenosis | Regurgitation |
|---|---|---|
| Basic defect | Valve too narrow, hard to open | Valve leaks, does not close |
| Main burden | Pressure overload | Volume overload |
| Chamber response | Concentric hypertrophy (thick walls) | Eccentric hypertrophy and dilation (stretched) |
| Classic murmur timing | Systolic (aortic) or diastolic (mitral) | Depends on the valve. For example, holosystolic in MR |
The two lesions you will see most
Aortic stenosis (AS) is the classic pressure problem. The aortic door stiffens, often from calcium buildup with age (calcification). So the left ventricle must slam against a tight opening to eject blood. To make that pressure, the ventricle wall thickens (concentric hypertrophy). The classic triad you learn for symptomatic AS is angina, syncope, and dyspnea on exertion. Those symptoms often signal that the valve area has grown narrow. Patients frequently have a crescendo-decrescendo systolic murmur.
Mitral regurgitation (MR) is the classic volume problem. The mitral door does not seal. So with each squeeze, blood jets backward into the left atrium instead of only moving forward into the aorta. The left atrium and left ventricle stretch and enlarge (eccentric hypertrophy) to hold the extra volume. A holosystolic (pansystolic) murmur, heard best at the apex, is typical.
Rheumatic heart disease: a delayed autoimmune injury
One cause deserves its own spotlight, because it is so important and so preventable. Rheumatic heart disease follows acute rheumatic fever, which itself follows an untreated group A streptococcal throat infection. Think of strep throat that was never treated. The immune system makes antibodies against the bacteria. But through molecular mimicry, those antibodies also attack the body's own tissues, including the heart valves. Years of smoldering inflammation scar the valve leaflets and fuse them together. The mitral valve is damaged most often, and the classic result is mitral stenosis. This is why treating strep throat with antibiotics truly protects the heart.
Why chronic valve disease drifts toward heart failure
Here is the through-line that ties it all together. The chamber may strain against high pressure (stenosis) or drown in extra volume (regurgitation). Either way it copes for a while by remodeling, thickening or stretching to keep output up. This compensation can last years, and patients often feel fine. But muscle that is overworked for years cannot keep up forever. Thick, stiff walls relax poorly and fill poorly. Stretched, dilated walls squeeze weakly. Either way the ventricle moves less blood forward, pressure backs up into the lungs, and you get the picture of heart failure: dyspnea, fatigue, and fluid congestion. Work out which chamber is overloaded and how. That tells you exactly where the backup and the symptoms will appear. Explore the figure below to see stenosis and regurgitation side by side.
- Two failure modes: stenosis is a stiff, narrowed valve (pressure overload). Regurgitation is a leaky valve that lets blood flow backward (volume overload).
- Signature lesions: aortic stenosis drives concentric hypertrophy of the left ventricle. Mitral regurgitation dilates the left atrium and ventricle (eccentric hypertrophy).
- Rheumatic heart disease comes from untreated group A strep by way of molecular mimicry. It classically scars the mitral valve, so treating strep throat protects the heart.
- The common endpoint: chronic pressure or volume overload is compensated for years. Then the overworked chamber fails, and blood backs up into the lungs as heart failure.
- Watch symptom onset: a compensated patient can feel well for years. New symptoms, especially in aortic stenosis, signal decompensation and need prompt evaluation.
Section 5The EKG & arrhythmias
Your heart has its own built-in electrical wiring, and every heartbeat starts as a tiny spark. Before we talk about what goes wrong, let us walk the normal path that spark travels. Every arrhythmia is really just a detour, a delay, or a short circuit somewhere along that road.
The normal conduction system: the heart's spark and wire
The signal begins in the sinoatrial (SA) node, a patch of cells high in the right atrium. The SA node is the heart's natural pacemaker because it fires fastest, usually 60 to 100 times a minute in an adult at rest. Its spark spreads across both atria and squeezes them. Then it funnels down to the atrioventricular (AV) node. The AV node is the gatekeeper. It holds the signal back a fraction of a second on purpose. That pause lets the atria finish emptying blood into the ventricles before the ventricles contract. From there the current races down the bundle of His and splits into the right and left bundle branches. It fans out through the Purkinje fibers, which fire both ventricles almost at once for a strong, coordinated pump.
Reading the P-QRS-T
An EKG (ECG) is simply a voltage recording of that electrical trip. Each normal beat draws three shapes:
- P wave = atrial depolarization. The atria fire and contract.
- QRS complex = ventricular depolarization. The ventricles fire. It is tall and narrow because the Purkinje system spreads the current so fast.
- T wave = ventricular repolarization. The ventricles reset for the next beat.
To read a strip, check the rate and the rhythm. For rate, count the QRS complexes in a 6-second strip and multiply by 10. You can also use the interval between beats. For rhythm, ask three questions. Is there a P wave before every QRS? Is every QRS narrow? Are the intervals regular? In a normal sinus rhythm the answer is yes to all three. When one of those answers turns to no, you have an arrhythmia (dysrhythmia).
Atrial fibrillation and its stroke risk
In atrial fibrillation (AFib) the atria stop taking their cue from the SA node. Instead they quiver chaotically from many misfiring spots. On the strip the P waves disappear and leave a wavy baseline. The QRS complexes march by irregularly irregular, with no pattern at all. The real danger is not the fast pulse. It is what happens to the blood. The atria only quiver instead of squeezing, so blood pools and sits still, above all in the left atrial appendage. Stagnant blood clots. Recall Virchow's triad, where stasis is one of the three legs. A clot that breaks loose travels to the brain and causes an embolic stroke. That is why patients with AFib are usually placed on anticoagulants.
Heart blocks: a traffic jam at the AV node
A heart block is a delay or a failure of the signal passing from the atria to the ventricles. In first-degree block every beat gets through, just slowly, which shows as a long PR interval. In second-degree block some atrial signals reach the ventricles and some are dropped. In third-degree (complete) block nothing gets through. The atria and ventricles beat on their own and ignore each other. The ventricles fall back on a slow backup pacemaker, often too slow to hold up blood pressure. Complete block frequently needs a pacemaker.
The lethal rhythms
Some arrhythmias are true emergencies. The ventricles are the pumping chambers, and in these rhythms they fail to move blood.
| Rhythm | What the ventricles do | Response |
|---|---|---|
| Ventricular tachycardia (VT) | Fire far too fast from a spot in the ventricle. Wide QRS, little time to fill | Emergency. If there is no pulse, defibrillate and start CPR |
| Ventricular fibrillation (VF) | Only quiver. No organized squeeze, so no cardiac output | Defibrillate right away, plus CPR |
| Asystole | No electrical activity at all. A flatline | CPR plus epinephrine. Not shockable |
VT and VF are shockable because a defibrillator can reset chaotic ventricular activity back into a coordinated rhythm. Asystole is not shockable. There is no electrical activity to reorganize. So the answer is high-quality CPR and drugs, not a shock.
When an arrhythmia is an emergency
The name of the rhythm matters less than how the patient looks. Watch for signs of poor perfusion, which means not enough blood flow to the tissues. Look for chest pain, shortness of breath, low blood pressure, cool clammy skin, confusion, or fainting (syncope). Some rhythms leave the patient with no pulse: VT without a pulse, VF, or asystole. Start CPR and call a code right away. A patient who is awake but unstable still needs urgent treatment. Explore the interactive EKG below to practice spotting P waves and QRS complexes, and the difference between an organized strip and a chaotic one.
- The impulse travels from the SA node to the AV node, which delays it, then to the bundle of His and the Purkinje fibers. The EKG records this as the P wave (atria), the QRS (ventricles firing), and the T wave (ventricles resetting).
- Read a strip by checking rate and rhythm. A P wave before every narrow QRS at a regular interval is normal sinus rhythm.
- Atrial fibrillation is irregularly irregular with no P waves. Quivering atria let blood pool and clot, which raises stroke risk, so patients are usually anticoagulated.
- Heart blocks are delays in AV conduction. Complete (third-degree) block often needs a pacemaker.
- VT, VF, and asystole are lethal. VF and pulseless VT are shockable with defibrillation. Asystole is not, so treat it with CPR and epinephrine.
Section 6Peripheral vascular disease
Your legs are fed by a two-way plumbing system. Arteries carry bright, oxygen-rich blood down from the heart under high pressure to feed the muscles, skin, and nerves. Veins carry the used, oxygen-poor blood back up to the heart against gravity. One-way valves and the squeeze of your calf muscles help push it along. When either half of this system fails, the tissue downstream suffers. It suffers in very different ways, though. It depends on whether the fault is inflow (arterial) or outflow (venous). Peripheral vascular disease is the umbrella term for both.
Arterial disease (PAD): not enough blood getting in
Peripheral arterial disease (PAD) is usually caused by atherosclerosis. It is the same cholesterol plaque that clogs coronary arteries, now narrowing the arteries of the legs. Less blood can squeeze past the plaque, so the muscles are starved of oxygen, above all when they demand more.
The classic early sign is intermittent claudication. It is a cramping, aching pain in the calf, thigh, or buttock. It comes on with walking, in a predictable way, and it reliably eases with rest. The mechanism is simple supply and demand. Exercising muscle needs more oxygen than the narrowed artery can deliver. The muscle switches to anaerobic metabolism, lactic acid builds up, and that causes pain. Rest lowers the demand, the ache resolves, and the cycle repeats at about the same walking distance.
As the disease worsens, the limb shows the hallmark six P's of limb ischemia. There is pain, in time even at rest, and rest pain is often worst at night when the leg is elevated in bed. There is pallor, so the limb turns pale, because little blood is filling the skin. It goes pulseless, or the distal pulses grow faint. Paresthesia is pins and needles from a nerve starved of blood. Paralysis is loss of movement. And poikilothermia means the limb drifts to room temperature, so it feels cool, because warm blood is not arriving. Chronic ischemia leaves the skin shiny, hairless, and thin, with thickened nails, because starved tissue cannot keep up normal growth. Patients often report that dangling the leg over the side of the bed relieves rest pain. Gravity helps pull the meager blood flow downhill.
Venous disease: not enough blood getting out
Chronic venous insufficiency (CVI) is the mirror image. Here the arteries deliver blood fine, but the veins cannot return it. Damaged or incompetent valves let blood flow backward and pool in the legs. That valve damage often follows years of standing, obesity, pregnancy, or a prior clot. Pressure then rises in the veins and capillaries, a state called venous hypertension.
That backed-up pressure pushes fluid out into the tissues. The result is chronic edema that is usually worst by the end of the day and improves overnight. Red blood cells also leak out and break down, leaving iron behind (hemosiderin). The iron stains the skin a permanent brownish color around the lower leg and ankle, a change called stasis dermatitis. Over time the skin becomes leathery and tight (lipodermatosclerosis). The tissue is congested and poorly nourished, so it breaks down into venous ulcers. These classically sit over the inner ankle (the medial malleolus), where venous pressure is highest.
Telling an arterial ulcer from a venous ulcer
Ulcers are where these two get mixed up most often, so match the wound to its mechanism. An arterial ulcer forms because tissue is starved. So it appears where flow is poorest, and it looks dead. A venous ulcer forms because tissue is congested and weepy. So it appears where pooling is worst, and it looks wet.
| Feature | Arterial ulcer | Venous ulcer |
|---|---|---|
| Usual location | Toes, heels, bony points, the lateral (outer) foot | Around the medial (inner) ankle |
| Wound edges | Sharp, punched-out, deep | Uneven, shallow, sloping |
| Wound bed | Pale, gray, or dry. Little drainage | Ruddy, beefy red. Heavy drainage |
| Surrounding skin | Cool, pale, shiny, hairless | Warm, brown-stained, swollen |
| Pain | Severe, and worse when raised | Mild to moderate, better when raised |
| Pulses | Faint or absent | Usually present |
DVT, PE, and one word on aneurysm
A deep vein thrombosis (DVT) is a clot in a deep leg vein. Virchow's triad sets it up: slow venous flow (stasis), injury to the vessel wall, and blood that clots too easily (hypercoagulability). Immobility, surgery, and estrogen are common real-world triggers. The leg is often warm, red, swollen, and tender. The danger is not the leg itself. A piece of clot can break loose, travel to the lungs, and lodge there as a pulmonary embolism (PE). That causes sudden shortness of breath, sharp chest pain with each breath (pleuritic pain), and a drop in oxygen. This is why we never vigorously massage a suspected DVT. Separately, an abdominal aortic aneurysm (AAA) is a balloon-like weak spot in the aortic wall. It may show up as a pulsing (pulsatile) mass in the belly, and it can be fatal if it ruptures. Explore the arterial-versus-venous figure below to see these patterns side by side.
- PAD starves tissue of inflow. You see intermittent claudication, meaning pain with walking that rest relieves, plus a limb that is cool, pale, pulseless, and painful. The pain is worse when the leg is raised.
- Chronic venous insufficiency is an outflow and pooling problem. You see edema, brownish hemosiderin staining, and ulcers around the inner ankle. Raising the leg helps.
- Arterial ulcers are punched-out, dry, and sit on toes and pressure points. Venous ulcers are shallow, wet, and sit around the inner ankle.
- DVT grows out of Virchow's triad. It can throw a clot to the lungs as a pulmonary embolism, which can kill. Do not massage the leg.
- An abdominal aortic aneurysm is a weakened, ballooning aorta that can be fatal if it ruptures.
The chapter in one breath
- Blood pressure is cardiac output times systemic vascular resistance. Hypertension (usually ≥130/80) is the silent disease that is mostly asymptomatic, meaning it causes no symptoms. It thickens vessels and overworks the heart, and it damages the brain, kidneys, and eyes.
- Coronary artery disease is atherosclerotic plaque starving the myocardium. When a plaque ruptures and a clot blocks flow fully, the muscle downstream infarcts. That gives the crushing chest pain, the elevated troponin, and the ST changes of an MI.
- Left-sided heart failure backs blood up into the lungs, so the classic signs are lung signs: crackles, dyspnea, orthopnea, and frothy sputum from pulmonary edema.
- Right-sided heart failure backs blood up into the body, so you see congestion out in the tissues: dependent edema, jugular venous distention, ascites, and a congested, tender liver.
- Valve disorders come in two flavors. Stenosis is a stiff, narrow valve the heart must strain to push through. Regurgitation is a leaky valve that lets blood flow backward. Both force the chamber behind them to thicken or stretch over time.
- The EKG tracks the electrical wave through the heart. The P wave is atrial depolarization, the QRS is ventricular depolarization, and the T wave is ventricular repolarization.
- Atrial fibrillation is the most common serious arrhythmia. It is an irregularly irregular quiver that pools blood in the atria and throws clots. That is why these patients need anticoagulation to prevent stroke.
- Lethal rhythms demand instant action. Ventricular fibrillation and pulseless ventricular tachycardia are shockable, so defibrillate and do CPR. True asystole is not shocked, and is treated with CPR and epinephrine.
- Peripheral vascular disease splits by side. Arterial insufficiency gives pain with walking (claudication), cool pale pulseless feet, and painful wounds far down the limb. Venous insufficiency gives warm swollen legs, brownish skin, and weepy ulcers at the inner ankle.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Angina
- Angina is chest pain or pressure that happens when a patch of heart muscle briefly gets less oxygen-rich blood than it needs. The usual reason is a coronary artery narrowed by plaque.
- Atherosclerosis
- Atherosclerosis is the slow buildup of fatty, cholesterol-rich plaque inside artery walls. It stiffens and narrows the vessel, and it can finally block blood flow.
- Atrial fibrillation
- Atrial fibrillation is a fast, disorganized quivering of the atria in place of a coordinated squeeze. Blood pools in the atria, which raises the risk of clots and stroke.
- BNP (B-type natriuretic peptide)
- BNP is a hormone released by stretched, overworked heart muscle. A high blood level often means the heart cannot keep up with its fluid load.
- Cardiac output
- Cardiac output is the amount of blood the heart pumps each minute. It equals heart rate times stroke volume, and in adults it is usually about 4 to 8 L/min.
- Claudication
- Claudication is cramping leg pain that comes on with walking and eases with rest. Narrowed arteries cannot deliver enough blood to working muscle.
- Ejection fraction
- Ejection fraction is the share of blood in a filled ventricle that gets pumped out with each beat, written as a percentage. Normal is about 55 to 70 percent.
- Embolus
- An embolus is a clot, a piece of plaque, an air bubble, or another mass that travels in the bloodstream. It keeps going until it lodges in a smaller vessel and blocks it.
- Heart failure
- Heart failure is the state in which the heart can no longer pump strongly enough, or fill well enough, to meet the body's needs. Fluid backs up and the patient tires easily.
- Hypertension
- Hypertension is blood pressure that stays high, usually 130/80 mmHg or above. It forces the heart to work harder and slowly damages vessel walls and organs.
- Myocardial infarction
- Myocardial infarction, or heart attack, is the death of heart muscle. It happens when a coronary artery is fully blocked and that patch of tissue is starved of oxygen.
- RAAS (renin-angiotensin-aldosterone system)
- RAAS is a hormone cascade that raises blood pressure when blood flow drops. It tightens blood vessels and tells the kidneys to hold on to salt and water.
- Regurgitation
- Regurgitation is blood leaking backward through a heart valve that does not close tightly. The heart must pump extra to make up for what flows the wrong way.
- Stenosis
- Stenosis is abnormal narrowing or stiffening of a heart valve or a vessel. It holds back forward blood flow, so the heart must push harder to move blood through.
- Systemic vascular resistance
- Systemic vascular resistance is the total opposition to blood flow set by the tone of the body's arteries, meaning how tight or relaxed they are. It is a major driver of blood pressure.
- Troponin
- Troponin is a protein released into the blood when heart muscle cells are injured. A rising level is a key marker used to confirm a myocardial infarction.
DrillFlashcards for this unit
These are the Week 9 cards. It is the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
Pulmonary
Every cell in your body runs on oxygen. The lungs are where oxygen gets in and carbon dioxide gets out. This chapter follows one breath from the air into the blood and back. You will see why ventilation and perfusion have to match, what happens when airways narrow or a clot lodges, and how to read the story in a patient’s lung sounds.
By the end of this chapter you can
- Explain ventilation, perfusion, and V/Q mismatch (dead space vs shunt).
- Tell chronic bronchitis apart from emphysema in COPD.
- Describe the three problems in asthma, and rescue vs controller inhalers.
- Spot a pulmonary embolism and what sets it up (Virchow’s triad).
- Match lung sounds (crackles, wheezes, stridor) to their causes.
Section 1How breathing works: ventilation, perfusion & V/Q
Every breath does two jobs at once, and the two jobs have to line up. Ventilation is air moving in and out of the lungs. It carries fresh oxygen down to the tiny air sacs called alveoli, and it carries carbon dioxide away. Perfusion is blood flowing through the pulmonary capillaries that wrap around those air sacs. Picture a loading dock. Ventilation drops off the packages, which are oxygen. Perfusion is the fleet of trucks that picks them up. If the packages arrive and no trucks come, nothing moves. If the trucks arrive and there are no packages, nothing moves either. Gas exchange needs air and blood in the same place at the same time.
Matching air to blood: the V/Q ratio
The V/Q ratio says how well air and blood line up. V stands for ventilation, and Q stands for perfusion, which is blood flow. In a healthy lung, the whole-lung ratio sits near 0.8. It lands just under 1 because blood flow is a bit greater than airflow. The ratio is not the same in every part of the lung. Gravity pulls blood downward, so the bases (the bottoms) get more blood flow. The apices (the tops) get relatively more air. So the ratio shifts as you move from top to bottom. What matters is balance. When air and blood are close to matched, oxygen crosses into the blood and carbon dioxide is blown off well. When they fall out of balance, you have a V/Q mismatch. It happens in two ways.
Two ways it goes wrong: dead space and shunt
A high V/Q means air arrives with no matching blood flow. The air gets there, but no blood is waiting to pick up the oxygen. That wasted air is called dead space. The classic cause is a pulmonary embolism, a clot that blocks a pulmonary artery. The air sacs fill with air, but the blood truck never shows up.
A low V/Q means blood arrives with no matching air. Blood keeps flowing past air sacs that are not getting fresh air. It returns to the heart still low on oxygen. This is called a shunt. Think of pneumonia filling air sacs with pus. Think of pulmonary edema flooding them with fluid. Think of atelectasis, which means collapsed air sacs. Here is one useful clue. A pure shunt responds poorly to extra oxygen. That oxygen cannot reach blood that is flowing past blocked sacs.
| Feature | Dead space (high V/Q) | Shunt (low V/Q) |
|---|---|---|
| What is missing | Perfusion (blood flow) | Ventilation (air) |
| The picture | Air arrives, no blood to load it | Blood arrives, no fresh air to load |
| Classic cause | Pulmonary embolism | Pneumonia, pulmonary edema, atelectasis |
| Response to oxygen | Usually helps (the open areas still load the extra oxygen) | Poor (the air cannot reach that blood) |
Gas exchange across the alveolar membrane
Air and blood actually meet at the alveolar-capillary membrane. This barrier is amazingly thin, only a few cells thick. Gases cross it by diffusion, which means they drift from high pressure to low pressure. Oxygen is more crowded in the air sac than in the arriving blood, so it moves into the blood. Carbon dioxide is more crowded in the blood, so it moves out into the air sac and gets exhaled. Anything that thickens this membrane slows diffusion down. Fluid, scar tissue, and swelling all do that. Gas exchange then gets worse, even when air and blood both show up.
Hypoxemia vs hypoxia, and how oxygen travels
These two words sound alike, but they mean different things. The difference matters a great deal. Hypoxemia is a low oxygen level in the blood. You see it as a low PaO2 on an arterial blood gas, or a low SpO2 on the pulse oximeter. Hypoxia is low oxygen reaching the tissues. The two often travel together, but not always. Severe anemia is a good example. It can starve the tissues of oxygen while the blood oxygen level (PaO2) still looks normal. There are simply not enough carriers to deliver it.
Those carriers hold the whole system up. About 97 percent of the oxygen in blood rides on hemoglobin inside red blood cells. Only a tiny share dissolves in the plasma. Play with the figure below to watch ventilation, perfusion, and V/Q matching work together.
- Ventilation is air moving in and out. Perfusion is blood flowing past the air sacs. The two must match in the same place at the same time. The normal V/Q ratio is about 0.8.
- Dead space is air with no blood flow (high V/Q). The classic cause is a pulmonary embolism. Shunt is blood flow with no air (low V/Q). Classic causes are pneumonia, edema, and atelectasis.
- Gases cross the thin alveolar-capillary membrane by diffusion, from high pressure to low. A thickened membrane slows oxygen uptake.
- Hypoxemia is low oxygen in the blood. Hypoxia is low oxygen in the tissues. You can have one without the other.
- About 97 percent of oxygen rides on hemoglobin. So delivery depends on the carriers too, not just on the lungs.
Section 2Obstructive disease: COPD

Each breath travels down your windpipe and splits into smaller and smaller tubes. Those tubes are the bronchi and the bronchioles. At the end sit millions of tiny balloon-like sacs called alveoli. Oxygen slips into the blood there, and carbon dioxide slips out. Two things make this work. The airways have to stay open, and the lung tissue has to stay springy. That springiness is called elastic recoil, and it quietly squeezes air back out when you exhale. Breathing out is normally passive and takes no work.
In chronic obstructive pulmonary disease (COPD), that easy exhale falls apart. The airways narrow and the springiness is lost. Air flows in, then gets stuck on the way out. So think of COPD as trouble getting air OUT, not in. Stale air piles up behind the narrowing. That pile-up is called air trapping, and it leaves the lungs over-inflated. This is why patients push air out through pursed lips, and why their exhale drags on so long.
Why air gets trapped
COPD is really two problems that overlap. Most patients have some of each.
Chronic bronchitis is an airway problem. Years of irritation inflame the lining of the bronchi, so the walls swell. The mucus glands grow bigger and pump out thick, sticky secretions. Now the airway is narrowed by swelling and by mucus. The tiny sweeping hairs that clear mucus, called cilia, are damaged too. Mucus sits still and grows bacteria, so infections keep coming back. The clinical definition is a productive cough for at least 3 months in each of 2 years in a row.
Emphysema is a tissue problem. The walls between air sacs break down and merge into fewer, bigger, floppy sacs. That costs surface area for gas exchange. It also costs the elastic recoil that props small airways open and drives the exhale. Without that support, airways collapse as you breathe out and trap even more air.
| Feature | Chronic bronchitis (blue bloater) | Emphysema (pink puffer) |
|---|---|---|
| Core problem | Swollen, mucus-clogged airways | Broken-down air sac walls, lost recoil |
| Classic look | Bluish, often heavy, swollen with fluid | Thin, barrel chest, leaning forward |
| Cough & mucus | Heavy wet cough | Little cough, little sputum |
| Oxygen level | Lower early (hypoxemia, blue tint) | Held closer to normal by fast breathing |
| Breathing style | Wet, congested | Pursed-lip, working hard to exhale |
The nicknames are memory hooks, not real patient types. The blue bloater looks blue and puffy because fluid backs up. The pink puffer stays pinker by breathing fast and hard. When the trapped air makes the chest round and stiff, we call it a barrel chest. That means the chest has grown deeper from front to back (an increased anteroposterior diameter).
The leading cause
Cigarette smoking is by far the number-one cause. Smoke keeps the airways inflamed. It also floods the lung with enzymes that chew up the walls of the air sacs, and it overwhelms the body’s natural guard against those enzymes. Over years that drives both the bronchitis and the emphysema. A smaller group inherits alpha-1 antitrypsin deficiency. That takes the natural guard away, so emphysema can show up even in people who never smoked. Quitting smoking is the single most powerful way to slow the disease.
When the strain reaches the heart
Low oxygen in the lungs for a long time makes lung blood vessels clamp down. That response is called hypoxic pulmonary vasoconstriction. It raises the pressure in the pulmonary arteries, which is pulmonary hypertension. Now the right side of the heart has to pump against that pressure. Over time the right ventricle gets bigger and then fails, and that is cor pulmonale. You see bulging neck veins, a large liver, and peripheral edema. That swelling is part of why the blue bloater looks puffy.
You can explore how a clogged airway and a broken-down air sac differ in the figure below.
- COPD is trouble getting air OUT. Narrowed airways and lost elastic recoil cause air trapping and a long, labored exhale.
- Chronic bronchitis is swollen, mucus-filled airways, with a wet cough (blue bloater). Emphysema is broken-down air sac walls with lost recoil (barrel chest, pink puffer).
- Smoking is the leading cause, and quitting slows the disease more than anything else.
- Low oxygen over time plus pulmonary hypertension can strain the right heart into cor pulmonale, with edema and bulging neck veins (JVD).
- Give oxygen with care, usually to a target SpO2 of 88 to 92 percent. Very high-flow oxygen can make CO2 retention worse.
Section 3Asthma
Take a slow breath in. Air rushes down your windpipe and splits into two bronchi. Those branch again and again into ever-smaller bronchioles, and then reach the tiny sacs where gas exchange happens. A thin layer of smooth muscle wraps those small airways, and a moist lining coats the inside. They are built to stay open and springy, so air moves with almost no effort. In a healthy lung, breathing out is passive and quiet. The airways stay wide and the air just leaves.
In asthma, those small airways turn hyperreactive, which means they overreact. Things that should be harmless set them off, and the airway narrows. The key word in asthma is reversible obstruction. Emphysema causes fixed damage, but an asthma attack can open back up with treatment, or even on its own. While it is happening, though, air gets trapped and the person has to fight to move it.
Three problems at once
An asthma attack is not one thing going wrong. Three processes hit the airway together, which is why it can get worse so fast.
- Bronchospasm. The ring of smooth muscle around the bronchioles squeezes tight. That narrows the tube itself. This is the fast part, and it is what rescue inhalers go after.
- Airway inflammation. The lining swells up with fluid (edema) as immune cells release histamine, leukotrienes, and other chemical messengers. A swollen wall makes a narrow tube even tighter.
- Mucus. Irritated airways pour out thick mucus, which plugs the passage from the inside.
So you have muscle squeeze, plus swollen walls, plus mucus plugs. The same amount of air now has a much smaller opening to move through. Use the figure below to see how bronchospasm and swelling stack up.
What sets it off
Asthma airways are twitchy, and each person has their own triggers. Common ones are allergens like pollen, dust mites, pet dander, and mold. Others are exercise, which is worse in dry air, cold air, and respiratory infections such as a common cold. Cigarette smoke, strong smells, and air pollution set it off too. Part of good asthma care is helping your patient name and dodge their own triggers.
Why it sounds the way it does
Air forced through those narrowed airways makes a high-pitched musical whistle. That sound is a wheeze, and you classically hear it on expiration. One part of this is easy to get backwards. Getting air in is easier than getting it out. Breathing in pulls the airways wider. Breathing out lets them narrow a little. So air gets trapped, and you see prolonged expiration, a long and labored breath out, as your patient fights to empty the lungs.
The two inhalers
Patients often carry two inhalers that do very different jobs. Mixing them up is dangerous.
| Feature | Rescue (reliever) | Controller (preventer) |
|---|---|---|
| Drug class | Short-acting beta-agonist (SABA), such as albuterol | Inhaled corticosteroid (ICS) |
| What it does | Relaxes airway muscle fast (bronchodilation) | Calms the swelling in the airway over time |
| When to use | During an attack, for quick relief | Every day, even on good days |
| Onset | Minutes | Days to weeks of steady use |
The rescue inhaler breaks the muscle spasm in minutes, but it does nothing for the swelling. The controller quiets the swelling, but it is useless in a sudden attack. A patient who reaches for the rescue inhaler more and more often is telling you the asthma is not controlled.
When it will not break: status asthmaticus
Status asthmaticus is a severe, drawn-out attack that does not answer the usual rescue treatment. It is a medical emergency. The patient wears out, gas exchange fails, and carbon dioxide climbs. Watch for a silent chest and for neck and shoulder muscles pulling with each breath. Watch the breathing rate rise and then slow down as the patient tires. Look for a bluish color, and for a rising PaCO2 on a blood gas. That rising PaCO2 is dangerous, because a tiring asthma patient should be blowing CO2 off, not holding it in. These patients need aggressive care, and often close monitoring in an intensive care unit.
- Asthma is reversible airway narrowing from three things at once: bronchospasm, inflammation with swelling (edema), and mucus.
- Common triggers are allergens, exercise, cold air, and respiratory infections.
- Expect wheezing and prolonged expiration. A silent chest means almost no air is moving, and that is an emergency sign.
- Rescue SABA inhalers such as albuterol break the spasm fast. Daily controller inhaled corticosteroids treat the swelling, but they do not help an attack in progress.
- Status asthmaticus is a severe attack that standard treatment does not fix. A rising PaCO2 warns that respiratory failure is close.
Section 4Pulmonary embolism
Breathing in is only half the job. Your lungs pull in oxygen, but that oxygen does nothing unless blood flows past the air sacs to pick it up. Normally the right side of your heart pumps blood through the pulmonary arteries into a lacy net of capillaries. Those capillaries wrap around millions of tiny air sacs called alveoli. There, oxygen loads onto red blood cells and carbon dioxide unloads. Air and blood work as partners. A pulmonary embolism (PE) is what happens when a plug in the pipe suddenly breaks that partnership.
What actually goes wrong
A PE is a clot that lodges in a pulmonary artery and blocks blood flow to part of the lung. Most of the time the clot did not form in the lung at all. It usually starts as a deep vein thrombosis (DVT) in a leg vein or a pelvic vein. Then a piece breaks loose. Once it is traveling, we call that clot an embolus. It rides the blood up to the right heart, gets pumped into the lung circulation, and wedges where the vessel gets too narrow to pass. The lung tissue past the clot still gets air. No blood arrives to pick up its oxygen.
Why the clot forms: Virchow’s triad
Clots do not show up at random. In the 1800s, Rudolf Virchow named three conditions that set the stage. We still use his triad to spot patients at risk:
- Venous stasis, which means blood pooling and sitting still. Long flights, bed rest, surgery, not moving, and heart failure all slow the flow. Clotting factors build up instead of washing away.
- Hypercoagulability, which means blood that clots too easily. Pregnancy, birth control with estrogen, cancer, dehydration, and inherited clotting disorders all tip the balance toward clotting.
- Endothelial injury, which means damage to the inner lining of the vessel. Trauma, surgery, central lines, and inflammation expose surfaces that start a clot.
When two or three of these overlap, a DVT gets much more likely. And a DVT is the seed of most PEs.
Dead space: ventilation without perfusion
Here is the core problem in one phrase: ventilation without perfusion. That blocked part of the lung still fills with air, but no blood flows past it. So the air is wasted. Air with no blood flow is called alveolar dead space. Gas exchange simply cannot happen there. Meanwhile the blood that should have gone to that area gets shoved into the vessels that are still open. The mismatch drops the oxygen level in the blood, which is hypoxemia. This is why a PE is a true medical emergency. A large clot can crash the oxygen level and strain the right heart within minutes.
Why the signs happen
PE symptoms come on suddenly. Each one traces straight back to the mechanism:
- Sudden dyspnea, which means shortness of breath, along with hypoxia. A chunk of lung can no longer load oxygen onto blood, so the body runs short and cries out for more air.
- Pleuritic chest pain, a sharp pain that gets worse with a deep breath. The oxygen-starved lung tissue and its lining, the pleura, get irritated and inflamed.
- Tachycardia, which means a fast heart rate. The heart speeds up to push blood past the blockage and to make up for the falling oxygen. You may also see fast breathing, worry, and a cough.
| Feature | Normal lung unit | Pulmonary embolism |
|---|---|---|
| Air in alveoli | Yes | Yes (still gets air) |
| Blood flow past alveoli | Yes | No (the clot blocks it) |
| Gas exchange | Works well | Fails in the blocked zone |
| Result | Normal oxygen | Dead space, hypoxemia |
Explore the figure below to see a clot stuck in a pulmonary artery, and how it cuts off blood flow to the lung past it.
- A PE is usually a leg DVT that broke loose, traveled as an embolus, and lodged in a pulmonary artery. It blocks blood flow to part of the lung.
- Virchow’s triad sets up the clot in the first place: stasis, hypercoagulability, and endothelial injury. Prevention targets all three.
- The blocked lung gets air but no blood flow. That makes alveolar dead space, which is ventilation without perfusion, and the blood oxygen drops.
- Classic signs are sudden dyspnea, pleuritic chest pain, tachycardia, and hypoxia. Each one comes from lost gas exchange and the body trying to make up for it.
- PE is a medical emergency. A swollen, tender calf is an early clue that a DVT could break loose.
Section 5Pneumonia & respiratory infections
Each breath you take travels down to about 300 million tiny air sacs called alveoli. A fine mesh of capillaries wraps around each sac. Their walls are amazingly thin, roughly one cell thick. That lets oxygen slip across into the blood while carbon dioxide slips out. This trade is gas exchange, and it needs those sacs to stay open, dry, and full of air. Pneumonia is what happens when that clean, air-filled space turns into a battleground.
What goes wrong: the alveoli flood
Pneumonia is an infection of the lung tissue itself. Bacteria cause it most often, classically Streptococcus pneumoniae, but viruses and fungi can too. When a germ reaches the air sacs, the immune system rushes in. White blood cells, fluid, and cell debris pour into the sacs and build up pus and inflammatory exudate. Here is the problem. A sac full of fluid and pus cannot hold air. Oxygen crosses a wall of liquid far worse than it crosses air, so gas exchange breaks down. That is why the hallmark of pneumonia is hypoxemia, which is low blood oxygen, along with shortness of breath, or dyspnea. When enough neighboring sacs fill and clump into one solid, airless area, we call it consolidation. It shows up as a white patch on a chest X-ray.
The classic signs, and the mechanism behind each
Pneumonia tends to announce itself with a cluster you learn to recognize:
- Fever and chills are the body answering an infection. Chemical signals called pyrogens turn the brain’s thermostat up, which makes the body a harsher place for germs.
- Productive cough brings up thick sputum, often yellow, green, or rust-colored. That is the pus and debris being cleared out of flooded airways.
- Tachypnea and tachycardia, meaning fast breathing and a fast heart rate, are the body making up for lost oxygen. It moves more air and pumps the oxygen-poor blood faster.
- Pleuritic chest pain is a sharp pain that gets worse with a deep breath. It shows up when the swelling reaches the lining of the lung.
On imaging, that patch of consolidation confirms the flooded area. In older patients and in patients with weak immune systems, the picture is often quieter. Confusion, or simply "not acting right," may be the only early sign.
Where you caught it matters
Care changes with where the infection started. The likely germs differ, and so does how well drugs work on them.
| Feature | Community-acquired (CAP) | Hospital-acquired (HAP / VAP) |
|---|---|---|
| Where acquired | Out in daily life; starts before admission or within 48 hrs of it | 48+ hrs after admission; VAP is the type tied to a ventilator |
| Common germs | S. pneumoniae, respiratory viruses, atypicals | Often Pseudomonas, Staph aureus including MRSA |
| Drug resistance | Usually lower | Often higher, and harder to treat |
| Typical severity | Mild to severe | Often sicker, with higher mortality |
Ventilator-associated pneumonia (VAP) is worth a note of its own. A breathing tube goes right past the filtering and coughing defenses of the upper airway. That hands bacteria a direct highway into the lungs. This is why care teams follow a "VAP bundle," which includes keeping the head of the bed raised and giving regular mouth care.
Who is most at risk
Anyone with weaker defenses is more open to pneumonia. That includes the very young and adults over 65, people who smoke, and people with chronic lung disease such as COPD. It also includes patients with weak immune systems and patients who have trouble swallowing. Those patients may aspirate, which means food or secretions go down into the lungs. Add anyone whose cough reflex is dulled by sedation or by a decreased level of consciousness.
A word on tuberculosis
Tuberculosis (TB) is a different infection, spread through the air by Mycobacterium tuberculosis. The immune system walls the bacteria inside a shell called a granuloma. TB can sit quiet for years as latent TB, with no symptoms and no spread to others. Later it can wake up into active TB, with cough, weight loss, and night sweats. Explore the figure below to see how infection fills the air sacs.
- Pneumonia fills the air sacs with fluid and pus. Oxygen cannot cross into the blood, so you get hypoxemia, dyspnea, and consolidation on imaging.
- Classic signs are fever, a wet cough, crackles from air sacs popping open, and pleuritic chest pain. Older adults may show only confusion.
- Community-acquired pneumonia (CAP) is usually less drug resistant. Hospital-acquired (HAP) and ventilator-associated (VAP) pneumonia bring tougher germs like Pseudomonas and MRSA.
- Highest risk: the very young, adults over 65, smokers, COPD, weak immune systems, and patients who aspirate. Vaccines and deep breathing help prevent it.
- TB is a separate infection spread through the air and walled into granulomas. It is either latent, meaning quiet and not contagious, or active disease.
Section 6Lung sounds & assessment
Each breath rushes down the windpipe, splits into smaller and smaller tubes, and ends at millions of tiny air sacs called alveoli. When the airways are open and the sacs are dry and springy, air moves smoothly and quietly. That smooth flow is exactly what a stethoscope listens for. Put your stethoscope on someone’s chest and you are listening in on how easily air gets in and out. You are also listening for anything in the way, such as fluid, mucus, swelling, or scarring.
Normal breath sounds: the quiet baseline
Over most of the lung you should hear vesicular breath sounds. They are a soft, low, rustling whoosh, louder when the patient breathes in and fading fast when they breathe out. Over the big central airways, the trachea and the area near the sternum, sounds are naturally louder and more hollow. Those are bronchial and bronchovesicular sounds. Here is the key idea. Normal air movement is clear and quiet. Anything extra layered on top is an adventitious sound, which simply means an added sound. Each type tells you a different story about what is happening inside the airways.
Crackles: air popping open through fluid
Crackles, once called rales, are brief popping or bubbling sounds that come in bursts. People compare them to Velcro pulling apart, or to hair rubbed between your fingers. They happen when air suddenly pushes open small airways and air sacs that were stuck shut or full of fluid. You hear them most when the patient breathes in, because that is when the collapsed spaces snap open. Crackles usually point to fluid or collapse in the air sacs. The classic causes are pneumonia, from inflammatory exudate, and heart failure, where fluid backs up into the lungs as pulmonary edema. In heart failure they often start at the lung bases, because gravity pools the fluid there.
Wheezes: air squeezing through narrowed tubes
Wheezes are high-pitched musical whistling sounds, usually loudest when the patient breathes out. Picture blowing through a straw that is almost pinched shut. They happen when airways are narrowed by bronchospasm, swelling (edema), or mucus. Air is forced through a tight channel and the walls vibrate. Wheezes are the signature of asthma and COPD. One safety note matters here. If a wheeze suddenly goes silent in someone struggling to breathe, that is ominous. Airflow may have dropped so low that no sound is being made, which is called a "silent chest." That is an emergency, not an improvement.
Stridor: the upper-airway alarm bell
Stridor is a harsh, high-pitched crowing sound. You can hear it without a stethoscope, and you usually hear it when the patient breathes in. It comes from a blockage high up in the upper airway, in the larynx or trachea. Causes include swelling from croup, epiglottitis, or anaphylaxis, and a stuck foreign body. Treat stridor as an airway emergency. The tube that keeps a person alive is narrowing, and it can close.
Pleural friction rub: surfaces that should glide, grating instead
Two thin membranes wrap the lungs. They are the pleura, and they normally slide past each other in silence. When they get inflamed, a problem called pleuritis that often follows an infection, they grate together instead. That makes a pleural friction rub, a low-pitched, grating, leathery sound. You hear it both when the patient breathes in and when they breathe out, and it often comes with pain on breathing.
| Feature | Crackles | Wheezes |
|---|---|---|
| Sound | Popping / bubbling | Musical / whistling |
| Cause | Fluid or collapsed air sacs | Narrowed airways |
| Timing | Mainly breathing in | Mainly breathing out |
| Points toward | Pneumonia, heart failure | Asthma, COPD |
Pulse oximetry: seeing the result of all this airflow
Listening tells you how air is moving. The pulse oximeter (SpO2) tells you the result, which is how much oxygen is reaching the blood. It clips on a finger and estimates the percent of hemoglobin carrying oxygen. In healthy adults that runs 95 to 100%. When crackles, wheezes, or a blockage keep oxygen from reaching the air sacs, the SpO2 often falls. That fall is hypoxemia.
Tie this back to the arterial blood gas (ABG) from Week 1. The pulse oximeter is a quick estimate, and it needs no needle. The ABG is the exact lab measurement, and it gives you true PaO2, PaCO2, and pH. Remember the oxyhemoglobin dissociation curve. Its S-shape means that once SpO2 drops below about 90%, the PaO2 has often fallen much further than the number makes it look. Trust the ABG for the full picture. Trust it especially for carbon dioxide, which the pulse oximeter cannot see at all.
Explore the figure below to hear how normal breath sounds differ from crackles, wheezes, stridor, and a friction rub.
- Normal breath sounds are clear and quiet. Any added (adventitious) sound means something is getting in the way of airflow.
- Crackles mean fluid or air sacs popping open, as in pneumonia and heart failure, and you hear them mostly on the breath in. Wheezes mean narrowed airways, as in asthma and COPD, mostly on the breath out.
- Stridor is a harsh sound on the breath in, from a blocked upper airway. Treat it as an emergency. A pleural friction rub is grating and painful, from inflamed pleura.
- Pulse oximetry (SpO2, usually 95 to 100%) estimates oxygen saturation with no needle, but it cannot measure CO2 and it can read falsely.
- The ABG confirms true oxygen, CO2, and pH. Always weigh the numbers against how your patient actually looks.
The chapter in one breath
- Ventilation is air moving in and out of the air sacs. When it drops, which is hypoventilation, CO2 backs up and the pH falls. That is respiratory acidosis.
- Perfusion is blood flow through the pulmonary capillaries. Gas exchange only works where air-filled sacs meet blood-filled capillaries.
- A normal V/Q ratio is about 0.8. A blocked airway, as in pneumonia or mucus, makes a low-V/Q shunt. A blocked vessel, as in PE, makes a high-V/Q dead space.
- COPD is lasting airflow limitation from emphysema plus chronic bronchitis. Air trapping and a barrel chest give a long breath out and chronically held CO2.
- Asthma is reversible bronchospasm with airway swelling and mucus, and it gives wheezing on the breath out. A silent chest with a rising CO2 means dangerous fatigue, not improvement.
- Pulmonary embolism is a clot, often from a DVT, lodging in the pulmonary artery. It causes sudden dyspnea, pleuritic chest pain, tachycardia, and hypoxemia, with a low CO2 from breathing fast.
- Pneumonia fills air sacs with inflammatory exudate. You see fever, a wet cough, crackles, and consolidation that blocks oxygen uptake.
- Adventitious lung sounds place the problem for you. Crackles mean fluid or sacs popping open, wheezes mean narrowed airways, and stridor means a dangerous upper-airway blockage.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Bronchospasm
- A sudden tightening of the smooth muscle wrapped around the bronchi and bronchioles. It narrows the airways, makes air harder to move (especially out), and often causes wheezing.
- Chronic bronchitis
- A form of COPD. The clinical definition is a productive cough lasting at least 3 months in each of 2 years in a row. It comes from lasting airway inflammation, mucus glands that grow larger (mucus-gland hypertrophy), and too much sputum.
- Consolidation
- Lung tissue filled with fluid, pus, blood, or inflammatory cells instead of air, as in pneumonia. That area turns solid, and gas exchange suffers.
- COPD (chronic obstructive pulmonary disease)
- A disease that limits airflow, gets worse over time, and is largely not reversible. It usually comes from smoking. It blends emphysema and chronic bronchitis, and it traps air on the breath out.
- Crackles
- Brief popping or bubbling sounds that come in bursts, heard mostly on the breath in. They happen when collapsed or fluid-filled air sacs and small airways snap open. They often signal fluid or infection.
- Dead space
- Air that you breathe in but that never takes part in gas exchange. It is either the conducting airways (anatomic) or air sacs that get air but no blood flow (physiologic).
- Emphysema
- A form of COPD in which the walls of the air sacs are destroyed and the sacs enlarge. That cuts the surface area for gas exchange and the elastic recoil that normally pushes air out.
- Hypoxemia
- A lower than normal oxygen level in the arterial blood, usually a PaO2 under about 80 mmHg or an SaO2 under about 95%. Left uncorrected, it starves the tissues of oxygen.
- Perfusion
- Blood flowing through the pulmonary capillaries that surround the air sacs. The blood releases carbon dioxide to be exhaled and picks up oxygen from the air in the sacs.
- Pulmonary embolism
- A blockage of a pulmonary artery, most often by a clot that traveled from a deep vein. It suddenly cuts off blood flow to part of the lung, creates dead space, and often causes sharp dyspnea and hypoxemia.
- Shunt
- Blood that passes through the lungs without picking up oxygen, because it flows past air sacs that get blood but no air, as in consolidation or collapse. It causes hypoxemia that oxygen alone often cannot fix.
- Status asthmaticus
- A severe, drawn-out asthma attack that does not respond to the usual bronchodilators. It is a medical emergency and can turn into respiratory failure.
- Stridor
- A harsh, high-pitched sound heard mainly on the breath in. It signals narrowing or blockage of the upper airway, in the larynx or trachea, and it needs urgent attention.
- Ventilation
- Air moving in and out of the lungs. It brings oxygen to the air sacs and carries carbon dioxide away.
- V/Q ratio
- The balance between ventilation (V, airflow) and perfusion (Q, blood flow) in a region of lung, normally about 0.8. A mismatch in either direction hurts gas exchange.
- Wheeze
- A steady, musical, usually high-pitched whistling sound, often loudest on the breath out. Air forced through narrowed lower airways makes it, as in asthma or COPD.
DrillFlashcards for this unit
These are the Week 10 cards, the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
Renal & Urinary
The kidneys are the body’s quiet housekeepers. They filter waste, balance water and salts, and steady blood pressure. They even help make blood. This chapter starts at the nephron. From there it works outward to the ways kidneys fail fast or slowly, the stones and infections of the urinary tract, and what the labs are telling you.
By the end of this chapter you can
- Describe the nephron. Say what GFR, creatinine, and BUN mean.
- Sort acute kidney injury into prerenal, intrarenal, or postrenal.
- Explain chronic kidney disease, uremia, and the problems they cause.
- Tell nephrotic syndrome from nephritic syndrome.
- Tell cystitis from pyelonephritis. Spot renal colic.
Section 1The nephron: how the kidney cleans blood
Every minute, more than a liter of blood pours into your kidneys. By the time it leaves, it has been cleaned, balanced, and fine-tuned. The kidney does this with millions of tiny units called nephrons. There are roughly one million in each kidney. The nephron is the kidney's functional unit. That means it is the smallest structure that can do the whole job of making urine. So when we talk about kidney disease, we are really talking about nephrons. They get damaged, overworked, or they die.
The nephron in three steps: filter, reabsorb, secrete
Think of the nephron as a factory with three stations. First comes filtration. Blood enters a tuft of leaky capillaries called the glomerulus. The glomerulus sits inside a cup called Bowman's capsule. Blood pressure pushes water and small molecules through the filter and into the tubule. Sodium, glucose, urea, and potassium all pass through. This early fluid is called filtrate. Big things like blood cells and proteins are too large to pass, so normally they stay in the blood. That is why protein or blood in the urine is a red flag. It usually means the filter is leaking.
Next comes reabsorption along the tubule. The tubule has three parts: the proximal tubule, the loop of Henle, and the distal tubule. The body cannot afford to dump everything it just filtered. So about 99% of the water goes back into the blood. Nearly all the glucose goes back, and so does the sodium the body needs. Last comes secretion. Here the tubule actively adds unwanted substances into the filtrate to be peed out. Certain drugs, extra hydrogen ions, and extra potassium get added this way. What is left after all three steps is urine.
GFR: the number that tells you how well the kidney works
The best single measure of kidney function is the glomerular filtration rate (GFR). It is how many milliliters of filtrate all the glomeruli make each minute. A normal GFR is usually around 90-120 mL/min. When GFR falls, the kidney filters less. Wastes then start to back up in the blood. GFR is also how we stage chronic kidney disease (CKD). A GFR under 60 for three or more months defines CKD. A GFR under 15 signals kidney failure. We usually estimate it (eGFR) from a blood test instead of measuring it directly.
The kidney's other jobs (it is not just a filter)
Losing kidney function causes trouble far beyond waste buildup. That is because the kidney holds down several side jobs:
- Blood pressure, through the renin-angiotensin-aldosterone system (RAAS). When blood flow or pressure drops, the kidney releases renin. Renin sets off a chain of events that tightens vessels. It also holds on to sodium and water. Both raise blood pressure.
- Red blood cells. The kidney makes erythropoietin (EPO), the hormone that tells bone marrow to build red cells. This is why patients with failing kidneys often develop anemia.
- Activating vitamin D. The kidney turns vitamin D into its active form. Active vitamin D lets the gut absorb calcium. So kidney disease weakens bones and upsets calcium balance.
- Acid-base balance. The kidney gets rid of hydrogen ions and takes back bicarbonate. That keeps blood pH steady. Failing kidneys tend to drift toward metabolic acidosis.
Reading the labs: creatinine and BUN
Two blood tests show how the nephrons are doing. Creatinine is a waste product from normal muscle breakdown. The body makes it at a steady rate, and the kidney clears it. So when creatinine rises, it usually means filtration is falling. Creatinine is our everyday marker of GFR. BUN (blood urea nitrogen) measures urea, a waste from protein breakdown. BUN also rises when the kidney struggles. But it is thrown off more easily by dehydration, bleeding, and a high-protein diet. So it is read alongside creatinine rather than alone. Explore the nephron below to see filtration in action.
| Feature | Creatinine | BUN |
|---|---|---|
| Comes from | Muscle breakdown | Protein breakdown (urea) |
| Usual range | ~0.6-1.2 mg/dL | ~7-20 mg/dL |
| Best for | Estimating GFR, the true kidney function | Hydration and overall status |
| Thrown off by | Muscle mass, less so by diet | Dehydration, bleeding, high protein |
- The nephron is the kidney's functional unit. It cleans blood in three steps: filtration at the glomerulus, then reabsorption and secretion along the tubule.
- GFR (usually about 90-120 mL/min) is the key measure of kidney function. A falling GFR defines and stages chronic kidney disease.
- The kidney also controls blood pressure (RAAS), makes erythropoietin for red cells, activates vitamin D for calcium and bone, and manages acid-base balance.
- Creatinine is the everyday marker of filtration. A rising level usually means GFR is falling.
- BUN tracks kidney function too. But dehydration, bleeding, and diet skew it easily, so read it next to creatinine.
Section 2Acute kidney injury
Your kidneys are the body's quiet, steady filters. Every minute, about a fifth of the blood your heart pumps flows through them. Inside each kidney sit roughly a million tiny filtering units called nephrons. Each nephron starts with a knot of capillaries called the glomerulus. Blood pressure pushes fluid and waste across that filter to form urine. The tubules that follow reclaim the water, sodium, and other things your body wants to keep. Working normally, the kidneys clear metabolic garbage and balance fluid and electrolytes. They also help control blood pressure and red blood cell production. When they stumble suddenly, waste backs up fast.
Acute kidney injury (AKI) is a sudden drop in kidney function. It unfolds over hours to days. The key word is sudden. Chronic kidney disease, by contrast, creeps along for months to years. Here is the good news. Because AKI is abrupt, it is often reversible. You have to catch and fix the cause before the nephrons are damaged for good.
How we know the kidneys are failing
Two blood tests tell the story. Creatinine is a waste product from muscle that the kidneys normally clear at a steady rate. When filtering drops, creatinine rises. BUN (blood urea nitrogen) is a nitrogen waste from protein breakdown, and it climbs too. A rising creatinine means the glomerular filtration rate (GFR) is falling. GFR is the amount of blood filtered per minute. At the same time, the kidneys usually make less urine. Oliguria means putting out less than about 400 mL of urine in 24 hours. It is often described as under roughly 0.5 mL/kg/hr. Put simply: labs go up, urine goes down.
The three categories: where the problem lives
We sort AKI by where the trouble sits relative to the kidney itself. This matters because the fix is completely different for each.
| Feature | Prerenal | Intrarenal | Postrenal |
|---|---|---|---|
| Core problem | Poor blood flow to the kidney | Direct damage inside the kidney | Blocked outflow after the kidney |
| Typical causes | Dehydration, hemorrhage, heart failure, shock | Acute tubular necrosis, nephrotoxins, long-lasting ischemia | Kidney stones, enlarged prostate, tumors, blocked catheter |
| Is tissue damaged yet? | Not yet. Usually reversible if flow comes back fast | Yes. Tubule cells are injured | Not at first. Backed-up pressure damages tissue over time |
Prerenal AKI is the most common. Anything that drops blood flow can cause it. Low volume from vomiting or bleeding, a weak heart, or wide-open vessels in sepsis all count. The glomerulus loses the pressure it needs to filter. The kidney tissue is still healthy. So if you restore blood flow quickly, function bounces back. Give fluids, treat the heart, stop the bleeding. If it is ignored, long-lasting low flow becomes ischemic damage. Then it tips into the intrarenal category.
Intrarenal (intrinsic) AKI means the nephron itself is injured. The classic form is acute tubular necrosis (ATN). The delicate tubule cells die. The cause is either long-lasting ischemia or toxins. Toxins include certain antibiotics (aminoglycosides), IV contrast dye, and myoglobin released in rhabdomyolysis. Dead tubule cells slough off and clog the tubules. They also cannot reabsorb properly.
Postrenal AKI is a plumbing problem downstream. Urine cannot get out. A stone, an enlarged prostate, a tumor, or even a kinked catheter blocks the flow. Pressure backs up into the kidney and filtration stops. This type is often the quickest to reverse. Relieve the blockage and urine pours out. But that only works if you catch it before back-pressure scars the tissue.
The phases of recovery
When AKI does progress, recovery classically moves through phases. The oliguric phase often lasts days to a couple of weeks. Urine output is low. Waste, potassium, and fluid pile up. This is the dangerous stretch. Watch closely for hyperkalemia, which means high potassium. It can trigger deadly heart rhythms. Watch for fluid overload and metabolic acidosis too.
As the tubules heal, the kidney enters the diuretic phase. The nephrons can filter again. But they have not regained the power to concentrate urine. So urine output surges, sometimes several liters a day. Now the risk flips. Patients can become dehydrated and lose too much sodium and potassium. Careful fluid and electrolyte replacement is essential. A slower recovery phase follows as function returns to normal. Some patients never fully get back to baseline.
Curious how the different causes stack up? Explore them in the figure below.
- AKI is a sudden, often reversible drop in kidney function. Creatinine and BUN rise while GFR and urine output fall (oliguria).
- Prerenal AKI is poor blood flow to the kidney. Intrarenal is direct damage, classically acute tubular necrosis. Postrenal is a block in urine outflow.
- Prerenal causes are the most common. They reverse if blood flow returns before ischemia damages tissue.
- Recovery moves through an oliguric phase, so watch for hyperkalemia and fluid overload. Then comes a diuretic phase, so watch for dehydration and electrolyte loss.
- Finding the correct category is critical, because each one is treated differently: restore flow, remove the insult, or relieve the blockage.
Section 3Chronic kidney disease
Your kidneys are quiet workhorses. Each kidney holds about a million tiny filtering units called nephrons. Every day they strain your blood. They pull out waste and extra fluid to make urine. They keep the good stuff in circulation: protein, blood cells, and most electrolytes. They also do jobs that have nothing to do with peeing. They make erythropoietin (EPO), which tells your bone marrow to build red blood cells. They activate vitamin D so your intestines can absorb calcium, which then strengthens bone. And they balance the blood's acid level. In chronic kidney disease (CKD), nephrons are slowly and permanently destroyed. So all of those jobs start to fail at once.
What CKD is and how we stage it
CKD is a slow, permanent loss of nephrons over months to years. Kidneys have huge reserve. So a person can lose a lot of function before feeling sick. We measure the damage with the glomerular filtration rate (GFR). Roughly, that is how many milliliters of blood the kidneys clean per minute. A normal GFR is usually around 90-120 mL/min. CKD is defined as kidney damage or a GFR below 60 for at least 3 months. It is staged from 1 (mild) to 5 (kidney failure).
| Stage | GFR (mL/min) | What it means |
|---|---|---|
| 1-2 | ≥60 (with damage) | Often silent. Caught on labs or urine protein |
| 3 | 30-59 | Problems begin, such as anemia and bone changes |
| 4 | 15-29 | Severe. Get ready for dialysis or transplant |
| 5 | <15 | Kidney failure. Dialysis is usually needed |
Why it happens: diabetes and hypertension
The two leading causes are the same two conditions seen everywhere. In diabetes, long-term high blood glucose damages the delicate glomerular capillaries. That damage is called diabetic nephropathy. One of the earliest warning signs is small amounts of protein leaking into the urine (albuminuria). In hypertension, the constant high pressure batters those same tiny vessels. They thicken and scar. Cruelly, failing kidneys also raise blood pressure. They hold on to salt and water and fire the renin-angiotensin system. So hypertension both causes CKD and gets worse because of it. It is a vicious cycle.
Uremia: when wastes build up
As filtering fails, nitrogen wastes climb in the blood. Urea and creatinine are the main ones. This toxic buildup is called uremia. Blood reaches every organ, so the symptoms are body-wide. Patients often feel exhausted, sick to the stomach, and itchy. The itch is pruritus, from waste left in the skin. They may lose their appetite, taste metal, and think slowly. In severe uremia, wastes irritate the heart lining (pericarditis) and the brain. Brain involvement is uremic encephalopathy. It causes confusion and even seizures. Uremia is why the kidneys become a whole-body problem.
The complications and why each one happens
To understand CKD, trace each problem back to a kidney job that was lost:
- Anemia. Fewer working cells make less EPO, so the marrow builds fewer red cells. Patients are pale, tired, and short of breath.
- Bone disease (renal osteodystrophy). Kidneys can no longer activate vitamin D or get rid of phosphate. Low calcium and high phosphate drive the parathyroids to pump out PTH. PTH pulls calcium out of bones and leaves them weak.
- Hyperkalemia. The kidneys normally dump extra potassium. When they cannot, potassium rises. That threatens dangerous cardiac arrhythmias. This is often the most urgent lab.
- Fluid overload. Salt and water that are not excreted back up. The result is edema, hypertension, and fluid in the lungs.
- Metabolic acidosis. Kidneys normally excrete acid and make new bicarbonate. As that fails, acid builds up. It adds to fatigue, bone loss, and rapid breathing.
When the kidneys fail
Stage 5 is often called end-stage renal disease (ESRD). The kidneys can no longer keep the body's chemistry safe. There are two options. Dialysis filters the blood artificially, either with a machine (hemodialysis) or through the lining of the belly (peritoneal dialysis). The other option is a kidney transplant. Dialysis manages the disease but does not cure it. It replaces only a fraction of true kidney function. That is why prevention and slowing the disease matter so much. Explore the stages in the interactive figure below.
- CKD is a slow, permanent loss of nephrons, staged 1 to 5 by GFR. A GFR below 60 for over 3 months defines it.
- Diabetes and hypertension are the top two causes, and they often make each other worse.
- Uremia is the buildup of urea and other wastes. It causes body-wide symptoms like fatigue, nausea, itching, and confusion.
- Key problems trace to lost kidney jobs: anemia (low EPO), bone disease (low active vitamin D, high PTH), hyperkalemia, fluid overload, and metabolic acidosis.
- At stage 5 (ESRD), dialysis or a transplant takes over for the failing kidneys. Dialysis manages the disease but does not cure it.
Section 4Glomerular disease: nephrotic vs nephritic
Every minute, your kidneys pull a huge amount of blood through roughly a million tiny filters called glomeruli. Picture each glomerulus as a wadded-up tuft of capillaries wrapped in a cup. Its filtering wall has three layers. First is the capillary lining (endothelium). Next is a middle mesh called the glomerular basement membrane (GBM). Last are special cells with interlocking foot processes, called podocytes. This wall is a smart sieve. It lets water, salts, and small wastes pass into the urine. But it holds back big things the body wants to keep, above all albumin (the main blood protein) and red blood cells. Two features make that possible. The pores sort by size. And the wall carries a negative charge that pushes away albumin, which is negative too. When this filter breaks, it tends to fail in one of two patterns. Telling them apart is one of the most important ideas in kidney disease.
Nephrotic syndrome: a very leaky filter
In nephrotic syndrome, the filter becomes too leaky without much inflammation. The podocytes and the charge barrier are damaged, so albumin pours out. The hallmark is massive proteinuria. That usually means more than 3.5 grams of protein in the urine per day. Losing that much protein drops the blood albumin. Low blood albumin is hypoalbuminemia. Albumin normally holds fluid inside vessels by oncotic (pulling) pressure. Lose it and fluid leaks into the tissues. That causes the heavy, all-over edema classic for this syndrome. Think puffy eyes in the morning and swollen legs and belly by evening. The liver senses the low protein and makes more of many proteins, including lipoproteins. So cholesterol and triglycerides climb (hyperlipidemia), and fatty casts can show up in urine. Patients also lose proteins that keep clotting in check, plus immunoglobulins. That raises the risk of thrombosis and infection. A classic cause in children is minimal change disease. In adults, membranous nephropathy and diabetic or lupus-related disease are common.
Nephritic syndrome: an inflamed filter
In nephritic syndrome, the problem is inflammation. Usually immune complexes lodge in the glomerulus and set off an immune attack. That inflammation physically breaks the capillary wall. Red blood cells then escape into the urine. The hallmark is hematuria, often tea- or cola-colored. Sometimes you also see red blood cell casts, which are tiny cell-molds shaped in the tubules. Those casts all but prove the bleeding comes from the glomerulus. Protein leaks too, but usually in smaller amounts, typically less than 3.5 g/day. Inflammation also swells and clogs the filter, so filtration drops. The kidney holds on to salt and water. That drives hypertension and a milder edema, often in the face. Creatinine also rises (azotemia) and urine output drops. The teaching classic is post-streptococcal glomerulonephritis (PSGN). A child develops cola-colored urine, puffy eyes, and high blood pressure roughly 1 to 3 weeks after a strep throat or skin infection. Immune complexes deposit in the glomeruli.
How to keep the two straight
Here is a simple anchor. NephrOtic = prOtein, which means a huge protein loss. NephrItic = Inflammation and hematurIa, which means blood. Nephrotic is a quiet, leaky sieve. Nephritic is an angry, bleeding, high-pressure one. Real patients can overlap. But the dominant pattern usually declares itself.
| Feature | Nephrotic | Nephritic |
|---|---|---|
| Core problem | Very leaky filter (podocyte and charge injury) | Inflamed filter (immune-driven) |
| Proteinuria | Massive (usually >3.5 g/day) | Mild to moderate (usually <3.5 g/day) |
| Hematuria | Absent or very little | Present, often with RBC casts |
| Albumin & lipids | Low albumin, high lipids | Usually near normal |
| Edema | Heavy, all over (oncotic) | Mild, often in the face and around the eyes |
| Blood pressure | Often normal | High (salt and water held back) |
| Classic example | Minimal change disease | Post-streptococcal GN |
Explore the interactive figure below. It puts the leaky nephrotic filter next to the inflamed nephritic one.
- Nephrotic = protein. A leaky filter causes massive proteinuria (usually >3.5 g/day), low albumin, heavy all-over edema, and high lipids.
- Nephritic = inflammation and blood. An inflamed filter causes hematuria (often with RBC casts), milder proteinuria, hypertension, and mild edema.
- Mechanism drives the signs: lost albumin lowers oncotic pressure, which makes nephrotic edema. Inflammation clogs filtration and holds salt and water, which makes nephritic hypertension.
- Classic examples: minimal change disease (nephrotic) and post-streptococcal glomerulonephritis, appearing 1 to 3 weeks after strep (nephritic).
- Memory hook: nephrOtic = prOtein, nephrItic = Inflammation and hematurIa.
Section 5Kidney stones

Your kidneys filter your blood all day long. The leftover minerals and salts dissolve into your urine. Think of urine as a river carrying dissolved cargo. As long as enough water is flowing, the minerals stay dissolved and wash out harmlessly. Kidney stones (nephrolithiasis) form when that balance tips. The urine becomes supersaturated. That means it holds more mineral than it can keep dissolved. The extra starts to crystallize, and those tiny crystals clump together into a hard stone. It is the same physics as making rock candy. The difference is that it happens inside the collecting system of the kidney, and nobody wants it.
Why the urine becomes supersaturated
Two things push urine past its saturation point. First, too little water (dehydration) concentrates the minerals. The same amount of solute is packed into less fluid. Second, too much mineral overloads the urine. That extra load comes from diet, genetics, or metabolic conditions. When calcium, oxalate, uric acid, or other salts climb high enough, crystals drop out of solution. Sluggish, concentrated, standing urine is the perfect place for a stone to grow. That is why low fluid intake over time is the single biggest risk factor you can change.
The pain: renal colic
A stone sitting quietly in the kidney may cause nothing at all. The trouble starts when it drops into the ureter, the narrow tube that drains urine to the bladder. The stone lodges and blocks the flow. Urine backs up. The ureter stretches and spasms as it tries to squeeze the stone along. That produces renal colic. It is sudden, awful, wave-like flank pain that classically radiates to the groin as the stone travels downward. Patients are famously restless and cannot find any position that helps. Compare that with peritonitis, where the patient lies still and guards the belly. The stone also scrapes the lining of the ureter. So you often see hematuria, which is blood in the urine. Sometimes you can see it, and sometimes only the dipstick finds it. Nausea, vomiting, and urinary urgency are common companions, because the kidney and gut share nerve pathways.
Types of stones
Calcium stones are by far the most common. They are usually calcium oxalate, and they make up roughly 75 to 80 percent of cases. Knowing the type matters, because prevention differs.
| Feature | Calcium stones | Uric acid stones |
|---|---|---|
| Frequency | Most common (~75-80%) | Less common |
| Urine condition | Often normal to alkaline | Favored by acidic urine |
| Key contributors | High calcium or oxalate, dehydration | High purine intake, gout |
| X-ray visibility | Usually radiopaque, so they show up | Often radiolucent, so they are hard to see |
Here is a common point of confusion. Cutting calcium in the diet usually backfires. Normal calcium intake binds oxalate in the gut, so the oxalate leaves in the stool instead of the urine. That actually lowers the risk of calcium-oxalate stones. The real fix is fluid.
Care priorities
Management rests on three pillars while the stone passes or is treated:
- Pain control. Renal colic is genuinely one of the worst pains people report. NSAIDs like ketorolac are often first-line, because they reduce ureteral spasm and inflammation. Opioids may be added. Treat pain hard and early.
- Hydration. Push generous oral or IV fluids. Dilute, flowing urine helps flush the stone along and stops new crystals from forming. This is prevention and treatment in one.
- Strain all urine. Have the patient void through a fine mesh strainer to catch the stone. This confirms the stone passed. It also lets the lab analyze what the stone is made of, so prevention can be targeted.
Watch for warning signs that need escalation. Fever is one, because a blocked, infected kidney is an emergency. So are signs of complete obstruction, and pain or vomiting you cannot control. Larger stones that will not pass may need lithotripsy, which uses shock waves to break the stone apart. Some need surgical removal. The interactive figure below shows how a stone lodges in the ureter and produces colic. Explore it once you have the mechanism in mind.
- Stones form when urine becomes supersaturated with minerals. The usual drivers are dehydration and too much mineral.
- Renal colic is sudden, severe, wave-like flank pain that radiates to the groin. Expect hematuria and a restless patient.
- Calcium (oxalate) stones are the most common type. Normal calcium in the diet usually protects rather than harms.
- The three priorities are pain control, heavy hydration, and straining the urine to catch and analyze the stone.
- Escalate right away for fever, complete obstruction, or pain and vomiting you cannot control.
Section 6UTIs & incontinence
Your urinary tract is basically a plumbing system with one-way flow and a built-in rinse. The kidneys make urine. The ureters carry it down. The bladder stores it. The urethra lets it out. From the bladder up, that flow is normally sterile. Every time you empty your bladder, you flush out stray bacteria trying to swim upstream. The lining fights back too, with a slightly acidic pH and mucus that makes it hard for microbes to stick. A urinary tract infection (UTI) happens when bacteria settle in the urethra and climb upward faster than the body can rinse them away. The usual culprit is Escherichia coli from the bowel.
Lower UTI (cystitis) vs upper UTI (pyelonephritis)
Where the bacteria land decides how sick the patient looks. In a lower UTI (cystitis), the infection stays in the bladder and urethra. The bladder wall becomes inflamed and touchy. So patients feel dysuria (burning when they pee), frequency, and urgency. Urine is often cloudy or foul-smelling, and there may be low suprapubic discomfort just above the pubic bone. The infection is local, so patients usually stay afebrile, meaning they run no fever. They do not feel sick all over.
An upper UTI (pyelonephritis) means bacteria have climbed the ureters into one or both kidneys. Kidney tissue is rich with blood, so the infection now reaches the bloodstream. The body mounts a full systemic response: fever, chills, nausea, and the classic flank pain. You will find costovertebral angle (CVA) tenderness when you tap over the kidney. Pyelonephritis is the more dangerous picture. It can progress to urosepsis, and over time it can scar the kidney.
| Feature | Cystitis (lower) | Pyelonephritis (upper) |
|---|---|---|
| Location | Bladder and urethra | Kidney(s) |
| Hallmark symptoms | Dysuria, frequency, urgency | Fever, chills, flank pain |
| Exam finding | Suprapubic tenderness (above the pubic bone) | CVA tenderness |
| Systemic illness | Usually none | Often. Can lead to sepsis |
Why women get more UTIs, and the catheter problem
Anatomy is the main reason women get far more UTIs than men. The female urethra is much shorter, roughly 4 cm versus about 20 cm in men. So bacteria have a shorter climb to the bladder. The opening also sits close to the vagina and anus, which gives perineal E. coli an easy route. Sexual activity pushes bacteria toward the urethra. And after menopause, lower estrogen thins the tissue and shifts the protective vaginal flora. That raises the risk again.
An indwelling (Foley) catheter is a major risk, because it bypasses every one of those natural defenses at once. The tube is a direct highway into the bladder. Bacteria form a biofilm along its surface, where antibiotics and immune cells cannot reach. Nonstop drainage also removes the flushing effect of a normal void. This is why catheter-associated UTIs (CAUTIs) are among the most common hospital-acquired infections. It is also why the single best prevention is simple: remove the catheter as early as possible.
The older adult who just gets confused
Older adults often skip the textbook burning-and-fever story entirely. A UTI may show up instead as new-onset confusion, delirium, or a sudden functional decline. That decline can look like new incontinence, falls, or refusing to eat. Part of the reason is a blunted immune response, which mutes fever. Part is that an aging brain is very sensitive to the systemic inflammation and dehydration that infection brings. The key point: an acute change in mental status in an older adult always deserves a workup that includes a urinalysis.
Urinary incontinence at a glance
Incontinence is leaking urine you did not mean to pass. It is a symptom, not a normal part of aging. The main types:
- Stress incontinence. Leaking with a cough, a laugh, or lifting. Weak pelvic floor support lets pressure overcome the sphincter.
- Urge incontinence. A sudden need to void that you cannot control. The detrusor muscle contracts on its own.
- Overflow incontinence. Constant dribbling from a bladder that never fully empties. The cause is often an obstruction, such as an enlarged prostate, or a weak, underactive detrusor.
- Functional incontinence. The urinary tract is normal. But a physical or thinking barrier, like poor mobility or dementia, keeps the person from reaching the toilet in time.
You can explore the layered urinary tract in the interactive figure below. It shows exactly where cystitis and pyelonephritis take hold.
- Cystitis (lower UTI) causes dysuria, frequency, and urgency with no fever. Pyelonephritis (upper UTI) adds fever, chills, and flank or CVA tenderness, and it can progress to sepsis.
- Women get more UTIs because the urethra is short and sits near the perineum. E. coli is the usual culprit.
- Indwelling catheters bypass natural defenses and cause CAUTIs, so remove them as early as possible.
- In older adults, new confusion or delirium may be the only sign of a UTI, even with no fever.
- Incontinence types: stress (leaks with pressure), urge (overactive detrusor), overflow (the bladder never empties), and functional (a barrier to reaching the toilet).
The chapter in one breath
- The nephron filters about 180 L a day at the glomerulus. GFR (usually about 90-120 mL/min) is the single best marker of kidney function, and it falls before symptoms appear.
- Acute kidney injury (AKI) is a rapid, often reversible rise in creatinine with a drop in urine output. Sort it as prerenal (low blood flow, as in dehydration or shock), intrarenal (tubule damage like ATN), or postrenal (obstruction).
- Chronic kidney disease (CKD) is permanent nephron loss over months to years, with a GFR under 60 for 3 or more months. It drives anemia (low erythropoietin), bone disease (low active vitamin D), and metabolic acidosis.
- In CKD the kidney stops excreting potassium and phosphate. Watch for hyperkalemia, the most urgent electrolyte threat, with peaked T waves and lethal arrhythmias.
- Nephrotic syndrome is a leaky filter: massive proteinuria (>3.5 g/day), low albumin, all-over edema, and high cholesterol. Think holes letting protein out.
- Nephritic syndrome is an inflamed filter: hematuria (often tea-colored urine with RBC casts), hypertension, and mild to moderate proteinuria. Think inflammation letting blood out.
- Kidney stones (nephrolithiasis) are most often calcium oxalate. They cause sudden severe flank pain radiating to the groin (renal colic) along with hematuria. The patient writhes and cannot get comfortable.
- UTIs usually start as cystitis, with dysuria, frequency, urgency, and suprapubic pain. They can ascend to pyelonephritis, with flank pain, fever, and CVA tenderness. Confusion may be the only sign in older adults.
- Urinary incontinence comes in distinct types. Stress leaks with a cough or sneeze from a weak pelvic floor. Urge is a sudden strong need from an overactive detrusor. Each is managed differently.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Acute kidney injury (AKI)
- A sudden drop in kidney function over hours to days. It is often reversible. Waste products like creatinine and BUN build up in the blood, and urine output usually falls.
- Acute tubular necrosis (ATN)
- The most common intrarenal cause of AKI. The tubule cells are injured and die. The usual causes are long-lasting ischemia (low blood flow) or nephrotoxins such as certain antibiotics or contrast dye.
- BUN (blood urea nitrogen)
- A blood test that measures urea, a nitrogen waste from protein breakdown that the kidneys normally clear. A rising BUN often signals reduced kidney function or dehydration.
- Chronic kidney disease (CKD)
- A slow, permanent loss of kidney function lasting three months or longer. It is staged by the GFR and is usually caused over time by diabetes or hypertension.
- Creatinine
- A waste product from normal muscle metabolism that the kidneys filter and excrete steadily. So a rising serum creatinine is one of the most reliable signs that kidney function is declining.
- Dialysis
- A treatment that artificially filters wastes, extra fluid, and electrolytes from the blood, by hemodialysis or peritoneal dialysis, when the kidneys can no longer do the job well enough.
- Erythropoietin (EPO)
- A hormone made mostly by the kidneys that tells the bone marrow to produce red blood cells. That is why failing kidneys often cause anemia.
- GFR (glomerular filtration rate)
- The volume of blood the glomeruli filter each minute, normally about 90–120 mL/min. It is the best overall measure of how well the kidneys are working.
- Glomerulus
- The tiny tuft of capillaries at the start of each nephron, where blood is first filtered. Water and small wastes pass through, while blood cells and large proteins normally stay behind.
- Nephron
- The working filter unit of the kidney, with about one million per kidney. It filters blood and fine-tunes the urine through its glomerulus and connected tubules.
- Nephritic syndrome
- A pattern of glomerular inflammation. It is marked by blood in the urine (hematuria), mild to moderate protein loss, hypertension, and often a reduced GFR.
- Nephrotic syndrome
- A pattern of glomerular damage marked by heavy protein loss in the urine, usually more than 3.5 g/day. It also brings low blood albumin, widespread edema, and high blood lipids.
- Oliguria
- Urine output that is too low, usually defined as less than about 400 mL in 24 hours. It is a key warning sign of acute kidney injury.
- Pyelonephritis
- A bacterial infection of the kidney and its collecting system, often from a bladder infection that ascended upward. It typically causes fever, chills, and flank pain.
- Renal colic
- Severe, cramping, wave-like flank pain that radiates toward the groin. It is classically caused by a kidney stone that blocks and stretches the ureter.
- Uremia
- The toxic illness of advanced kidney failure, in which retained nitrogen wastes cause symptoms such as nausea, fatigue, itching, and confusion.
DrillFlashcards for this unit
These are the Week 11 cards. It is the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
| Feature | Prerenal | Intrarenal |
|---|---|---|
| Problem site | Before the kidney (blood flow in) | Inside kidney tissue (nephron) |
| Classic cause | Hypovolemia, shock, heart failure | Acute tubular necrosis, nephrotoxins, contrast, glomerulonephritis |
| Reversible? | Yes, if blood flow is restored quickly | Slower. It depends on tissue recovery |
| Feature | Nephrotic | Nephritic |
|---|---|---|
| Core problem | Leaky filter loses protein | Inflamed, bleeding glomerulus |
| Proteinuria | Massive (usually >3.5 g/day) | Mild to moderate |
| Urine/blood | Foamy urine, low albumin, edema, high lipids | Hematuria (tea-colored), RBC casts, hypertension |
| Feature | Cystitis (bladder) | Pyelonephritis (kidney) |
|---|---|---|
| Location | Lower urinary tract | Upper tract, kidney |
| Symptoms | Dysuria, frequency, urgency, suprapubic pain | All of those PLUS high fever, chills, flank or CVA tenderness, nausea |
| Severity | Usually local and low-grade | Systemic. Can lead to sepsis |
- Vitamin D: the kidney does the final activation step. It turns vitamin D into its active form (calcitriol) so the gut can absorb calcium. This is why CKD causes bone disease.
- Blood pressure: the kidney releases renin. Renin triggers the renin-angiotensin-aldosterone system (RAAS), which holds on to sodium and water and raises BP.
- Acid-base: the kidney excretes hydrogen ions and reabsorbs or regenerates bicarbonate. So kidney failure often causes a metabolic acidosis.
Reproductive
The reproductive systems bring their own set of disorders. Some are hormonal. Some are structural. Some are infections, and some are cancers. This chapter covers the common female and male conditions that turn up most often. It covers the cancers to screen for. And it covers the sexually transmitted infections that quietly cause the most harm over time.
By the end of this chapter you can
- Recognize common female disorders (PCOS, endometriosis, fibroids, PID).
- Name the female cancers. Say how cervical and breast cancer are screened.
- Explain BPH, and tell it apart from prostate cancer.
- Spot testicular torsion as an emergency.
- Tell the major bacterial and viral STIs apart.
Section 1Female reproductive disorders
Every month, a healthy uterus rehearses for a pregnancy that usually does not come. This rehearsal is the menstrual cycle. Learn its normal rhythm first. Then almost every female disorder gets easier to reason through. The first half is the follicular phase. The pituitary releases FSH. An ovarian follicle matures. Rising estrogen thickens the uterine lining, the endometrium. Then a surge of LH triggers ovulation, around day 14. The emptied follicle becomes the corpus luteum. It pumps out progesterone to hold the lining steady. That is the luteal phase. If no pregnancy implants, the corpus luteum dies. Hormones fall. The lining sheds as menstruation. The loop runs about 28 days. But 21 to 35 days is often normal.
When the cycle misbehaves: menstrual disorders
Dysmenorrhea is painful periods. The primary type comes from too many prostaglandins. They make the uterine muscle cramp hard. That cramp briefly cuts off its own blood supply. Less blood flow is called ischemia. It is what makes the pain crampy, like labor. NSAIDs block prostaglandins, so they work well here. Secondary dysmenorrhea points to another problem. Think endometriosis or fibroids.
Amenorrhea means absent periods. Primary means they never started by about age 15. Secondary means regular cycles stopped for 3 months or more. Pregnancy is the top cause of the secondary kind. So rule it out first. Other causes can also shut the cycle down. Stress, hard exercise, low body weight, and thyroid or prolactin problems all can. They quiet the hypothalamic-pituitary-ovarian axis, the hormone chain that runs the cycle.
Abnormal uterine bleeding (AUB) covers three things. Bleeding that is too heavy (menorrhagia). Bleeding that comes too often. And bleeding between periods (metrorrhagia). Often the cause is anovulation, which means no egg is released. With no ovulation there is no progesterone. So estrogen builds the lining with nothing to balance it. The lining outgrows its blood supply and sheds in a ragged way. Heavy loss month after month often causes iron-deficiency anemia.
PCOS: the hormone-and-metabolism tangle
Polycystic ovary syndrome is the most common hormone disorder in women of child-bearing age. Think of three linked problems. First, irregular or absent cycles, from months of anovulation. Second, androgen excess. That brings extra hair growth (hirsutism), acne, and thinning scalp hair. Third, insulin resistance. The insulin piece is the engine. High insulin pushes the ovaries to make more androgens. It also lowers SHBG, so even more testosterone runs free. The ovaries fill with many small young follicles. That is the "polycystic" look on ultrasound. Cycles never finish, so the lining sits under unopposed estrogen. Over years that raises the risk of endometrial hyperplasia. PCOS also raises the risk of type 2 diabetes and metabolic syndrome. So lifestyle change comes first, and sometimes metformin.
Endometriosis: the right tissue in the wrong place
In endometriosis, tissue that acts like endometrium grows outside the uterus. It lands on the ovaries, the ligaments, and the lining of the pelvis. It still answers the monthly hormone cues. So it thickens and bleeds with each cycle. But that blood has nowhere to drain. The result is lasting inflammation and scarring. Scar bands called adhesions glue pelvic organs together. The classic signs are pelvic pain that tracks the cycle and gets worse with menses. Add dyspareunia, which is painful intercourse, and infertility. On the ovary, trapped old blood can form a "chocolate cyst," called an endometrioma. Laparoscopy often confirms the diagnosis.
Fibroids and pelvic inflammatory disease
Uterine fibroids (leiomyomas) are benign tumors of the smooth muscle in the uterine wall. They are estrogen-sensitive. So they tend to grow during the child-bearing years. They shrink after menopause. Many cause no symptoms at all. Larger ones cause heavy or long periods, and pelvic pressure. Some press on the bladder, so the woman needs to urinate often.
Pelvic inflammatory disease (PID) is an infection that climbs upward. It usually starts with Chlamydia or gonorrhea. It travels from the cervix up into the uterus, the tubes, and the ovaries. The inflammation scars the fallopian tubes. That is why PID is a leading cause of ectopic pregnancy and infertility. Watch for lower belly pain, fever, and discharge. Watch too for cervical motion tenderness, which means pain when the cervix is moved.
| Feature | Endometriosis | Uterine fibroids |
|---|---|---|
| What it is | Endometrial-type tissue outside the uterus | Benign smooth-muscle tumor in the uterine wall |
| Hallmark pain | Pain that tracks the cycle, plus dyspareunia | Pressure and heaviness; often no pain |
| Bleeding | Varies | Heavy or long periods |
| Effect on fertility | Common, from adhesions | Depends on size and location |
You can explore these disorders side by side in the interactive figure below.
Pregnancy adds another layer. The figure below covers what can harm a developing fetus, and two genetic ideas that sit beside it.
- The cycle runs on FSH and LH. Estrogen builds the lining. Then progesterone steadies it. When ovulation fails, estrogen is unopposed. That causes abnormal bleeding, and it raises endometrial cancer risk.
- Primary dysmenorrhea comes from prostaglandins that cramp the uterus and cut its blood flow. So NSAIDs help. In secondary amenorrhea, rule out pregnancy first.
- PCOS links three things: no ovulation, too much androgen, and insulin resistance. The insulin resistance often drives the androgen excess.
- Endometriosis is uterine-type tissue outside the uterus. It causes pain that tracks the cycle, plus adhesions and infertility. Fibroids are benign muscle tumors that answer to estrogen. They cause heavy bleeding and pressure.
- PID is an STI-related infection that climbs upward and scars the tubes. That raises the risk of ectopic pregnancy and infertility.
Section 2Cancers of the female system

During the child-bearing years, the ovaries release estrogen and progesterone on a careful schedule. Estrogen tells the endometrium, the uterine lining, to grow and thicken. Progesterone comes after ovulation. It matures that lining, then lets it shed as a period. The cervix is the neck of the uterus. It is lined by fast-turnover cells, right where two tissue types meet. The breast is built from milk-making glands and ducts. They answer those same hormones. Cancer starts when the instructions for cell growth get corrupted. Cells then divide with no stop signal. Here is where that goes wrong in the female system, and why each cancer acts the way it does.
Cervical cancer: a virus you can vaccinate against
Nearly all cervical cancer starts with human papillomavirus (HPV). HPV is a common sexually transmitted virus. High-risk strains matter most, above all types 16 and 18. They slip proteins into cervical cells. Those proteins switch off the body’s tumor-suppressor genes. So damaged cells keep dividing instead of self-destructing. This usually happens slowly. Normal cells first become dysplasia, which is pre-cancer. Only years later does it turn into invasive cancer. That slow lag is what makes cervical cancer so preventable. A Pap smear scrapes cells from the cervix. It catches dysplasia before it turns malignant. HPV co-testing looks for the virus itself. The HPV vaccine blocks infection in the first place. It works best around ages 11 to 12, before exposure. Early cervical cancer is often silent. One classic later sign is postcoital bleeding, which is bleeding after sex. Other odd spotting counts too.
Endometrial (uterine) cancer: too much estrogen, unopposed
Estrogen builds the endometrium. Progesterone holds that growth in check and triggers shedding. Sometimes estrogen acts without enough progesterone to balance it. Then the lining keeps thickening. This is called unopposed estrogen. Over time it drives endometrial hyperplasia, which can turn into cancer. That explains the risk factors. Obesity matters, because fat tissue makes extra estrogen. So does never having been pregnant. Early menarche and late menopause add up to more lifetime estrogen. PCOS raises risk. So does taking estrogen therapy without progesterone. The good news is that this cancer speaks up early. It shows postmenopausal bleeding, or other abnormal uterine bleeding. Any bleeding after menopause is endometrial cancer until proven otherwise. It needs a prompt workup.
Ovarian cancer: the quiet one
The ovaries sit deep in the pelvis, with room to grow unnoticed. So ovarian cancer often causes no clear signs until it has spread. When signs do appear they are vague and easy to brush off. Look for bloating, and early satiety, which means feeling full fast. Add pelvic or belly discomfort and a sudden urge to urinate. There is no reliable screening test for women at average risk. So it is often found late. That is why it kills so many. Risk rises with BRCA1/BRCA2 gene mutations and with family history. It also rises with more lifetime ovulations. That makes one habit matter. Take new, lasting bloating or fullness seriously.
Breast cancer: risk, warning signs, and screening
Breast tissue answers to estrogen. So most risk factors trace back to lifetime estrogen and to genes. They include early menarche, late menopause, never breastfeeding, and older age. Inherited BRCA1/BRCA2 mutations matter most. They sharply raise both breast and ovarian risk. The warning signs come from a growing mass pulling normal tissue out of shape. Look for a hard, fixed, painless lump. Look for skin dimpling, or a peau d’orange texture, which looks like orange peel. Watch for a nipple pulled inward, or bloody nipple discharge. Screening mammography finds tumors before anyone can feel them. It usually starts around age 40 to 50, then repeats on a schedule.
| Feature | Cervical | Endometrial |
|---|---|---|
| Main driver | HPV infection | Unopposed estrogen |
| Key prevention or screen | Pap smear, HPV vaccine | Watch for abnormal bleeding |
| Classic warning sign | Bleeding after intercourse | Bleeding after menopause |
| When it is found | Often early, because we can screen | Often early, because it bleeds |
Notice the pattern. Cancers that bleed are caught early. So are cancers we can screen for. The quiet ovaries are caught late. That one idea organizes most of what you need to remember.
Run the years in the figure below and see what each screening plan catches.
- Cervical cancer is caused by HPV. The Pap smear catches pre-cancer. The vaccine stops the infection. So this cancer is highly preventable.
- Endometrial cancer is driven by unopposed estrogen. Risk rises with obesity, with never having been pregnant, and with estrogen-only therapy. Bleeding after menopause is the key early sign.
- Ovarian cancer is the quiet one. It is usually found late, with vague bloating and fullness. There is no reliable screening test.
- Breast cancer risk rises with estrogen exposure and with BRCA1/BRCA2. Watch for a hard fixed lump, skin dimpling, or nipple changes. Screen with mammography.
- Any bleeding after menopause is cancer until proven otherwise. It needs a prompt workup.
Section 3Male reproductive disorders
The male reproductive system is built around a simple plumbing problem. One tube, the urethra, has two jobs. It carries urine out of the bladder. It also carries semen out during ejaculation. That urethra runs straight through the middle of the prostate. The prostate is a walnut-sized gland. It sits just below the bladder and adds fluid to semen. Blood flow matters too. An erection is really a vascular event. Arteries relax, and blood pools inside the penis. Keep those two ideas in mind. The tube runs through the prostate, and blood flow drives the erection. Most male disorders then start to make sense.
Benign prostatic hyperplasia (BPH)
BPH is exactly what the name says. It is benign, which means not cancer. And it is hyperplasia, which means too many cells. With age, the prostate slowly enlarges. A lifetime of androgen exposure drives it, mostly DHT (dihydrotestosterone). The urethra passes right through the gland. So that growth squeezes the tube, like a hand closing gently around a straw. Everything else follows from the pinch. The stream turns weak and hesitant, because urine is harder to push past the narrowing. The bladder muscle, the detrusor, has to work harder. It thickens and gets irritable. That drives urinary frequency and urgency. It also drives nocturia, which means waking at night to void. In time the bladder cannot empty fully. Residual urine is left behind. In the worst case flow stops completely. That is acute urinary retention. These lower urinary tract symptoms are often grouped as LUTS.
Prostatitis
Prostatitis is inflammation of that same gland. It feels very different from BPH. Acute bacterial prostatitis usually comes from gut or urine organisms, often E. coli. They track into the prostate. This is an active infection, so the man is truly sick. Expect fever, chills, and malaise. Add pelvic or perineal pain, and painful, hard urination (dysuria). On exam the prostate is boggy, swollen, and very tender. Chronic prostatitis is the slow-burn version. It brings lasting pelvic discomfort and repeat urine infections. But it causes few whole-body signs.
| Feature | BPH | Acute prostatitis |
|---|---|---|
| Cause | Age-related growth, driven by androgens | Bacterial infection |
| Fever or feeling sick | No | Yes, often high fever |
| Onset | Slow, over years | Sudden, over hours to days |
| Prostate on exam | Enlarged, smooth, firm | Swollen, boggy, very tender |
| Main problem | Blocked flow | Infection plus painful urination |
Erectile dysfunction (ED)
Erectile dysfunction is the ongoing inability to get or keep an erection firm enough for sex. An erection needs arteries to widen and fill the penis with blood. So ED is most often a vascular problem. The same processes that clog coronary arteries hurt the small penile vessels. Those are atherosclerosis, diabetes, hypertension, and smoking. They also damage the endothelium, the thin vessel lining. That lining releases nitric oxide, the signal that tells smooth muscle to relax. This is why ED is often an early warning sign. The small vessels narrow before the big ones cause a heart attack. Nerve damage adds to the picture, as in diabetes or after prostate surgery. So do low testosterone, some medicines, and psychological factors.
Testicular torsion
Testicular torsion is a true surgical emergency. The testicle twists on its spermatic cord. That kinks the blood supply, exactly like stepping on a garden hose. With no arterial flow the testicle becomes ischemic, meaning starved of blood. If it is not fixed fast, it dies. It classically strikes adolescents. The pain is sudden and severe, on one side of the scrotum. Nausea and vomiting often come with it. The affected testicle may sit high and horizontal. The cremasteric reflex is typically absent. Normally, stroking the inner thigh lifts the testicle. Time is the whole story. Salvage rates are best within about 6 hours. So torsion goes straight to surgery. Often it is not imaged first, if the diagnosis is clear.
Explore the figure below. See where each of these disorders sits in the male body.
- BPH is benign, age-related prostate growth. It squeezes the urethra, so the stream gets weak. Expect frequency, nocturia, and sometimes retention.
- Prostatitis is inflammation of the prostate. The acute bacterial form brings fever, pelvic pain, and a boggy, tender gland. BPH enlarges the gland without pain.
- Erectile dysfunction is usually vascular. It can be an early warning sign of heart and vessel disease, such as atherosclerosis or diabetes.
- Testicular torsion is a surgical emergency. The pain is sudden and severe, and the cremasteric reflex is absent. The testicle is best saved within about 6 hours.
- The urethra runs through the prostate. So most prostate disorders show up first as a change in the stream.
Section 4Cancers of the male system
The male reproductive system runs on two organs with very different jobs. The testes sit outside the body, in the scrotum. It is slightly cooler there. That lets them make sperm and pump out testosterone. The prostate is a walnut-sized gland. It wraps around the urethra, just below the bladder. Its job is to add fluid to semen. The prostate hugs the urine tube. So anything that makes it swell can squeeze that tube and change how a man urinates. Keep that anatomy in mind. It explains almost every symptom in this section.
Prostate cancer: common and often patient
Prostate cancer is the most common non-skin cancer in men. The risk climbs steeply with age, above all after 65. It is also often slow-growing. So many men live for years with disease that never threatens them. The tumor usually starts in the peripheral zone, the outer part of the gland. That is why it often causes no early symptoms. It is also why a clinician can sometimes feel a hard, uneven nodule. The test for that is a digital rectal exam (DRE). Screening pairs the DRE with a blood test for PSA (prostate-specific antigen). The prostate normally leaks a little PSA. Cancer cells disrupt the gland, so more PSA escapes into the blood. A rising level is a red flag. It is not a diagnosis. Prostate cancer likes to spread to bone. So a later sign can be deep, unexplained back or hip pain.
Cancer versus BPH: same gland, different problem
These two get mixed up all the time. Both make the prostate bigger, and both upset urination. The key difference is where the growth sits, and what kind it is. Benign prostatic hyperplasia (BPH) is overgrowth that is not cancer. It starts in the inner, or transitional, zone. That is the part closest to the urethra. So it squeezes the tube early and loudly. Cancer usually grows in the outer zone. So it stays quiet until it is further along.
| Feature | BPH (benign) | Prostate cancer |
|---|---|---|
| What it is | Overgrowth of normal cells | Malignant cells that can spread |
| Usual zone | Inner or transitional, near the urethra | Peripheral, the outer zone |
| Early urinary symptoms | Common and obvious | Often none until advanced |
| DRE finding | Smooth, rubbery, even | Hard, uneven nodule |
| PSA | Mildly raised | Often higher, or rising |
The urinary symptoms of BPH follow straight from the squeezed urethra. Expect a weak stream. Expect hesitancy, which means waiting for flow to start. Expect dribbling, and nocturia, which means waking to urinate. The bladder never empties fully. These same symptoms can show up in advanced cancer. So symptoms alone cannot tell the two apart. That is exactly why the exam and the PSA matter.
Testicular cancer: the young man's cancer
Testicular cancer flips the age script. It is the most common solid cancer in men roughly 15 to 35 years old. The biggest risk factor is an undescended testicle (cryptorchidism). That holds true even if surgery fixed it in childhood. The classic sign is a painless, firm lump or swelling in one testicle. It is often found by chance, or in the shower. It does not hurt, so men easily ignore it. That is dangerous, because these tumors can grow fast. Many start in germ cells. They can raise tumor markers such as AFP, beta-hCG, and LDH, which help with diagnosis and tracking. Here is the reassuring part. Testicular cancer responds very well to treatment. Cure rates stay excellent even after it has spread. So finding it early changes a lot.
When to worry and refer
Refer promptly when you find a hard or nodular prostate on exam. Refer for a rising or clearly raised PSA. Refer for new bone pain in a man with a prostate history. For the testes, any painless testicular mass needs an urgent workup. So does new firmness, or a change in size. That usually means a scrotal ultrasound, before anyone calls it harmless. Other red flags count too. Watch for blood in the urine or semen, weight loss with no clear cause, and trouble urinating. Your job is not to diagnose. It is to notice, document, and route. It is also to make screening feel normal, so men actually show up.
Grow each zone in the figure below and watch the stream, the PSA, and the exam.
- Prostate cancer is common and often slow-growing, and it favors older men. It grows in the outer zone of the gland. Screening uses PSA plus a digital rectal exam.
- BPH is benign inner-zone overgrowth. It squeezes the urethra early, so expect weak stream, hesitancy, and nocturia. Cancer stays outer and quiet until late. So exam and PSA tell them apart.
- PSA is a clue, not a diagnosis. Infection, BPH, and a recent exam can raise it. A rising level earns a referral.
- Testicular cancer strikes young men, usually 15 to 35. It is typically a painless firm mass, and it is highly curable. So monthly self-exam and early reporting matter.
- Refer promptly for a hard or nodular prostate. Refer for a rising PSA, new bone pain, or any painless testicular mass.
Section 5Sexually transmitted infections

The reproductive tract has built-in defenses. The vagina keeps an acidic pH, thanks to bacteria called lactobacilli. Cervical mucus forms a physical plug. The lining of the urethra, cervix, and rectum is coated in immune cells. They stand ready to trap invaders. Sexually transmitted infections (STIs) happen when a germ gets past those defenses. It may be a bacterium, a virus, or a protozoan. It passes through vaginal, anal, or oral contact. Then it settles on mucosa, or enters the bloodstream. Here is the tricky part. Many STIs are silent. The person feels fine. Meanwhile the germ quietly climbs the tract, or spreads through the body.
Bacterial STIs: chlamydia and gonorrhea
Chlamydia trachomatis and Neisseria gonorrhoeae are the two most reported bacterial STIs. They often travel together. Both infect the tall, column-shaped lining cells of the cervix and urethra. Symptoms, when they come, are few. Expect dysuria, which means painful urination. Expect thick cloudy discharge, or bleeding after sex. But roughly 70% of women have no symptoms at all. Many men have none either. That is exactly why these infections spread. The silence is dangerous. The germ can climb from the cervix into the uterus and tubes. Then it triggers pelvic inflammatory disease (PID). Inflammation and scarring can block the tubes, so the egg cannot pass. That causes infertility. It also raises the risk of a life-threatening ectopic pregnancy. Gonorrhea can spread into blood and joints too. That is called disseminated gonococcal infection. Antibiotics treat both. Chlamydia gets doxycycline, and gonorrhea gets ceftriaxone. But treatment cannot undo scarring that is already there.
Syphilis and its stages
Syphilis comes from the spiral bacterium Treponema pallidum. It is called the great imitator. It moves through the body in clear stages. Each stage brings different signs. The germ spreads from local tissue, to the bloodstream, and in the end to the nervous system.
| Stage | What you see | Why |
|---|---|---|
| Primary | A single painless chancre at the entry site, which heals on its own | The spirochete is multiplying locally; it is often missed, because it does not hurt |
| Secondary | Widespread rash, often on palms and soles, with fever and swollen lymph nodes | The organism has spread through the blood, so the whole immune system reacts |
| Latent | No symptoms, but blood tests are positive | The bacteria persist quietly; early on it can still be passed to others |
| Tertiary | Gummas, heart and vessel damage, neurosyphilis | Years of unchecked damage to tissue and vessels |
Penicillin is still the treatment. The early sores are painless, and they heal on their own. That is exactly why untreated syphilis keeps moving forward. The patient assumes it is gone.
Viral STIs
Viral STIs differ in a key way. Antibiotics do nothing against them. And several last for life. The virus either slips into host DNA, or it hides inside host cells.
- Human papillomavirus (HPV): infects flat surface cells, called squamous epithelium. Low-risk strains cause genital warts. High-risk strains, 16 and 18, disable tumor-suppressor genes. They drive cervical, anal, and oropharyngeal cancers. The HPV vaccine prevents the high-risk strains. Pap and HPV screening catch pre-cancer early.
- Herpes simplex virus (HSV): causes painful blister-like genital sores. Then it retreats into nerve clusters near the tailbone, the sacral ganglia. It stays there for life and flares under stress. Antivirals such as acyclovir hold outbreaks down. They do not cure it.
- HIV: attacks CD4 T-helper cells. Immunity slowly falls apart. In the end, infections that a healthy body shrugs off define AIDS. Modern antiretroviral therapy lets people live long lives. When the viral load is undetectable, it also stops transmission.
- Hepatitis B: spreads through blood and through sex. It inflames the liver. Over years it can cause chronic hepatitis, cirrhosis, and liver cancer. A vaccine prevents it.
Why screening and prevention matter
So many STIs cause no symptoms. That is why screening is what finds them before damage sets in. Treating partners breaks the reinfection loop. Prevention layers together. Barrier methods such as condoms cut transmission. Vaccines stop HPV and hepatitis B before exposure. Prompt treatment shortens the window when a person can pass it on. Patient teaching here is practical and free of judgment. It rests on one truth. Catching an STI early is almost always easier than treating what it becomes.
Move through the stages in the figure below, then treat and see what is left.
- Chlamydia and gonorrhea are often silent. But they can climb upward and cause PID, infertility, and ectopic pregnancy. Treat the patient, and treat the partners.
- Syphilis moves through four stages. Primary brings a painless chancre. Secondary brings a body-wide rash. Then comes latent, then tertiary, with neurosyphilis and damage to the heart and vessels. Penicillin treats it.
- Viral STIs are HPV, HSV, HIV, and hepatitis B. Antibiotics do not touch them, and they are often lifelong. Vaccines prevent HPV and hepatitis B.
- High-risk HPV drives cervical and other cancers. HIV destroys CD4 cells and the immunity they run.
- Four things prevent the worst outcomes: screening, partner treatment, barrier methods, and vaccination.
The chapter in one breath
- Endometriosis is endometrial tissue in the wrong place. It still bleeds each cycle. That causes chronic pelvic pain and dysmenorrhea. Adhesions and scarring then cause infertility.
- PID is usually chlamydia or gonorrhea climbing upward. It inflames the upper tract. Its scarring is a leading cause of ectopic pregnancy and infertility.
- Cervical cancer is nearly always caused by lasting high-risk HPV, types 16 and 18. That is why the vaccine plus Pap and HPV co-testing catch it early.
- Breast cancer risk climbs with lifetime estrogen and with BRCA1/BRCA2 mutations. A new hard, fixed, painless lump calls for mammography. So does a nipple change.
- BPH is enlargement of the prostate’s inner zone, and it is not cancer. It squeezes the urethra. That causes hesitancy, weak stream, nocturia, and urinary retention.
- Prostate cancer usually starts in the outer zone. So it can be felt on DRE, and it rarely blocks flow early. It is often silent until the PSA rises, or until bone metastases appear.
- Testicular cancer is the most common solid tumor in young men, ages 15 to 35. It typically shows up as a painless, firm lump in one testicle.
- STIs often hide in silence. Chlamydia and gonorrhea may cause no symptoms, yet still cause PID and infertility. Untreated syphilis moves from a primary chancre, to a secondary rash, to tertiary organ damage.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Amenorrhea
- Having no menstrual periods. Primary means they never started by the expected age. Secondary means they stopped for three or more cycles in someone who used to menstruate. It often signals pregnancy, a hormone imbalance, or too much stress or exercise.
- Benign prostatic hyperplasia (BPH)
- A non-cancerous enlargement of the prostate gland, common in aging men. It squeezes the urethra and causes urinary symptoms such as a weak stream, hesitancy, frequency, and waking at night to urinate (nocturia).
- BRCA
- The BRCA1 and BRCA2 tumor-suppressor genes. Inherited mutations in them sharply raise lifetime risk of breast and ovarian cancer, and some prostate cancer, because the damaged gene can no longer help repair DNA.
- Chlamydia
- A very common bacterial sexually transmitted infection caused by Chlamydia trachomatis. It is often silent, with no symptoms, yet it can quietly scar the reproductive tract and lead to pelvic inflammatory disease and infertility if it is not treated.
- Dysmenorrhea
- Painful menstrual cramping, caused mainly by prostaglandin-driven uterine contractions. Primary means there is no underlying disease. Secondary means it comes from a condition such as endometriosis or fibroids.
- Endometriosis
- A condition in which tissue like the uterine lining grows outside the uterus. It bleeds with each period, which causes chronic pelvic pain, painful intercourse, and often infertility.
- Fibroid
- A benign, non-cancerous tumor of uterine smooth muscle, also called a leiomyoma. It can enlarge the uterus and cause heavy menstrual bleeding, pelvic pressure, and pain.
- Gonorrhea
- A bacterial sexually transmitted infection caused by Neisseria gonorrhoeae. It inflames the urethra, cervix, or other mucous membranes. Left untreated, it can spread and cause pelvic inflammatory disease or whole-body infection.
- HPV (human papillomavirus)
- A very common sexually transmitted virus. Its high-risk strains can cause cervical, anal, and other cancers. Its low-risk strains cause genital warts.
- HPV vaccine
- A vaccine, such as Gardasil, that protects against the high-risk human papillomavirus strains most likely to cause cervical and other cancers. It works best given before a person becomes sexually active.
- Pap smear
- A screening test that samples cells from the cervix to find pre-cancerous or cancerous changes early. It is often paired with HPV testing, to catch problems before they become cancer.
- Pelvic inflammatory disease (PID)
- An infection of the upper female reproductive organs: the uterus, fallopian tubes, and ovaries. It usually spreads upward from an untreated STI such as chlamydia or gonorrhea. It can scar the tubes and cause infertility or ectopic pregnancy.
- Polycystic ovary syndrome (PCOS)
- A common hormone disorder marked by irregular or absent ovulation, high androgens (which cause acne and extra hair growth), and often insulin resistance. Ultrasound frequently shows many small ovarian follicles.
- PSA (prostate-specific antigen)
- A protein made by the prostate and measured in the blood as a screening marker. Higher levels can point to prostate cancer, but they also rise with benign prostatic hyperplasia, infection, or inflammation.
- Syphilis
- A sexually transmitted infection caused by the bacterium Treponema pallidum. It moves through stages, starting with a painless sore called a chancre. Untreated, it can eventually damage the heart, brain, and other organs.
- Testicular torsion
- A surgical emergency in which the testicle twists on its spermatic cord. That cuts off blood flow and causes sudden severe scrotal pain and swelling. It must be relieved within hours to save the testicle.
DrillFlashcards for this unit
These are the Week 12 cards. They are the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
Digestive: GI, Liver & Pancreas
The digestive tract is one long tube with a few powerful helper organs beside it. Trouble anywhere along that tube shows up fast. This chapter starts with the reflux and ulcers of the upper GI tract. It moves down through inflammatory bowel disease and blockages. Then it turns to the liver, gallbladder, and pancreas, and the jaundice that warns you something is backing up.
By the end of this chapter you can
- Explain GERD and peptic ulcer disease, and why each one is risky.
- Tell Crohn disease apart from ulcerative colitis.
- Spot a bowel blockage, and tell an upper GI bleed from a lower one.
- Describe cirrhosis and what follows it: portal hypertension, varices, ascites, and encephalopathy.
- Explain gallstones, pancreatitis, and the three types of jaundice.
Section 1Upper GI: GERD & peptic ulcers
Your stomach makes acid on purpose. Parietal cells in the stomach lining pump out hydrochloric acid (HCl). That acid starts to break down food. It also kills germs you swallow. It is strong enough to burn skin, so the body has to guard itself. It does that in two ways. First, a ring of muscle sits at the bottom of the esophagus. It is called the lower esophageal sphincter (LES), and it stays shut tight. That keeps acid down in the stomach where it belongs. Second, the stomach and duodenum wear a thick coat of mucus and bicarbonate. Think of it as a chemical raincoat. It keeps acid off the soft cells below. Almost every upper GI problem starts when one of these two guards fails.
GERD: when the sphincter leaks
Gastroesophageal reflux disease (GERD) is stomach acid washing backward into the esophagus. It happens when the LES is weak or opens at the wrong time. The esophagus has no mucus raincoat, so the acid stings its lining. That is why the classic symptom is heartburn (pyrosis), a burning behind the breastbone. It is often worse after big meals or when lying down, since lying flat takes gravity out of the fight. Patients may also bring up sour fluid, which is called regurgitation. Some have a cough that will not quit, or a hoarse voice when acid reaches the throat.
A little reflux now and then is normal. GERD is reflux often enough to cause symptoms or damage. The long-term worry is what repeated acid does to the lining. Over years, the normal flat squamous cells can turn into gut-type columnar cells. That change is called Barrett esophagus. The body is adapting so the lining can survive the acid. But this kind of cell swap is a form of metaplasia, and it raises the risk of esophageal adenocarcinoma, a cancer of the esophagus. That is why long-term GERD is watched, not just medicated.
Peptic ulcer disease: when the raincoat wears through
A peptic ulcer is an open sore. It eats through the protective mucosa and into the wall of the stomach or duodenum. Two causes do most of the damage, and both attack the mucus guard. The first is Helicobacter pylori, a spiral-shaped bacterium. It burrows into the mucus layer and sets off inflammation that weakens it. The second is long-term use of NSAIDs, such as ibuprofen and aspirin. NSAIDs block prostaglandins. Those are the very chemicals that tell the stomach to make protective mucus and bicarbonate. Take away the prostaglandins and you take away the raincoat. Then acid digests the tissue itself. Together, H. pylori and NSAIDs cause the large majority of peptic ulcers.
Gastric vs. duodenal: read the pain
Where the ulcer sits changes when the pain comes, and exams love this point. The trick is to think about where the food goes.
| Feature | Gastric ulcer | Duodenal ulcer |
|---|---|---|
| Location | In the stomach lining | In the first part of the small intestine |
| Pain timing | Often worse with food (usually 30 min after eating) | Often eased by food, then back 2-3 hours later |
| Classic clue | May skip meals, can lose weight | Night pain that food settles; may gain weight |
| Usual cause | More often from NSAIDs | More often from H. pylori |
Here is the logic. With a gastric ulcer, food makes the stomach pour out more acid right on top of the sore. So eating hurts. With a duodenal ulcer, food soaks up acid. It also makes the stomach shut its outlet for a while. So eating soothes the pain until the meal moves through.
When an ulcer turns dangerous
Ulcers matter because they can dig deeper. Two problems are emergencies. Bleeding starts when the ulcer eats into a blood vessel. Watch for hematemesis, which means vomiting blood. It can look like coffee grounds once acid has worked on it. Watch for melena too, which is black, tarry, foul stool. That is blood that has traveled the whole gut. Slow, steady bleeding shows up as iron-deficiency anemia and fatigue. The second problem is perforation. The ulcer bores all the way through the wall and spills acid and gut contents into the belly. Pain comes on hard and fast, and the abdomen turns rigid, a board-like abdomen. That is a sign of peritonitis, and it needs surgery right away.
Take a look at the interactive figure below. It shows how a weak sphincter lets acid climb back into the esophagus.
- GERD is acid washing back past a weak LES. Years of acid can lead to Barrett esophagus and raise the risk of esophageal cancer.
- Peptic ulcers form when the mucus guard fails. The usual causes are H. pylori and NSAIDs, which block protective prostaglandins.
- Gastric ulcer pain is often worse with food. Duodenal ulcer pain is often eased by food and returns hours later.
- The dangerous problems are bleeding (hematemesis, melena, anemia) and perforation (sudden pain, rigid board-like belly, peritonitis).
Section 2Inflammatory bowel disease
Your gut is a long tube that runs from your mouth to your anus. Its inner lining has a hard job. It has to pull nutrients out of food. At the same time it has to keep trillions of bacteria inside the tube and out of your blood. That lining is the mucosa. It sits on top of your immune system like a screen door. Good things pass through, and invaders are held back. Normally your immune cells and your gut bacteria keep a quiet truce. In inflammatory bowel disease (IBD), that truce breaks down. The immune system starts attacking the bowel wall itself. The result is immune-mediated inflammation, which means the body's own defenses drive it. It flares and settles, flares and settles, for the rest of a person's life.
Two diseases, one family
IBD is an umbrella term for two related conditions. They are Crohn disease and ulcerative colitis (UC), and they share a lot. Both are chronic, which means long-lasting. Both are relapsing, so they cycle between flares of active inflammation and misery, and remission, when things calm down. In both, the immune system overreacts to a normal gut. Genes and triggers in the world around us both play a part. Both can also make the whole body feel sick, not just the belly. Fatigue, weight loss, and a low fever are common, since wide inflammation is a whole-body event. What sets them apart is where they attack and how deep they go.
Crohn disease: patchy and deep
Crohn can strike anywhere from the mouth to the anus. It favors the terminal ileum, the tail end of the small intestine, and the colon. Its signature is skip lesions. Patches of angry, swollen bowel sit right next to healthy tissue, so the pattern looks moth-eaten. The inflammation is also transmural. That means it burrows through all the layers of the bowel wall, not just the surface.
That depth explains Crohn's worst problems. When inflammation tunnels through the wall, it can carve an odd passage between two structures. That passage is a fistula. It may run from bowel to skin, or from bowel to bladder. Long-term transmural damage also scars the tube and narrows it. Those tight spots are strictures, and they can block the bowel. The small intestine does most of the work of soaking up nutrients. So Crohn often causes malabsorption, which means poor nutrient uptake, along with weight loss and vitamin shortfalls. The diarrhea is often not bloody. Patients may have pain in the right lower belly that looks a lot like appendicitis.
Ulcerative colitis: shallow but continuous
UC follows a steadier map. It is limited to the colon only. It almost always starts in the rectum. From there it spreads continuously upward, one unbroken zone of inflammation, with no skip areas. It is also shallow. The damage stays in the mucosa and submucosa, and it spares the deeper muscle layers. Because it does not go transmural, UC rarely causes fistulas or strictures.
But that swollen, ulcerated surface bleeds easily. So the hallmark symptom is bloody diarrhea mixed with mucus. Patients often have crampy pain low in the belly and a constant urge to go, which is called tenesmus. Losing blood and fluid stool many times a day can leave them anemic and dried out. A feared emergency is toxic megacolon. The colon balloons out and can burst. Long-standing UC also raises the risk of colorectal cancer, so these patients need regular colonoscopy checks.
Side by side
| Feature | Crohn disease | Ulcerative colitis |
|---|---|---|
| Location | Mouth to anus (often terminal ileum) | Colon only, starts in rectum |
| Pattern | Skip lesions (patchy) | Continuous |
| Depth | Transmural (all layers) | Mucosa/submucosa only |
| Classic stool | Diarrhea, often not bloody | Bloody diarrhea with mucus |
| Complications | Fistulas, strictures, malabsorption | Toxic megacolon, higher colon cancer risk |
IBD is not IBS
One last split trips people up, because the letters look so much alike. IBD is structural. The inflammation and tissue damage are real, and you can see them on a scope and a biopsy. IBS (irritable bowel syndrome) is functional. The gut hurts and acts up, but the tissue itself looks normal. Explore the interactive figure below to compare the Crohn and UC patterns side by side.
- IBD is long-term, immune-mediated inflammation of the bowel. It relapses in flares and settles into remission, and it splits into Crohn disease and ulcerative colitis.
- Crohn can hit anywhere from mouth to anus, with skip lesions and transmural inflammation. That is why it causes fistulas, strictures, and malabsorption.
- Ulcerative colitis stays in the colon only, spreads continuously from the rectum, and stays mucosal. Its hallmark is bloody diarrhea.
- Deep versus shallow explains the problems. Crohn tunnels through the wall and makes fistulas. UC ulcers the surface, so it bleeds and risks toxic megacolon and cancer.
- Do not mix up IBD (real inflammation with visible damage) and IBS (a functional disorder with normal-looking tissue).
Section 3Bowel obstruction & GI bleeding
Picture your intestines as a long, muscular hose. There are roughly 20 feet of it, and it never stops working. The gut moves its contents forward with waves of squeezing called peristalsis. Smooth muscle does the squeezing. The enteric nervous system, the gut's own built-in wiring, keeps the rhythm. Food, fluid, gas, and in the end stool all travel one way: down and out. When that forward flow stops, everything piles up behind the block. That is when the trouble begins.
Mechanical obstruction vs paralytic ileus
Two very different things can shut the highway down. In a mechanical obstruction, something plugs the lumen, which is the open space inside the tube. The top cause is adhesions, bands of scar tissue inside the belly, usually from past surgery. Next come a hernia, where a loop of bowel gets trapped as it pokes through the belly wall, and tumors, most often in the colon. The muscle still wants to push. So early on it squeezes harder against a wall it cannot get past.
In a paralytic ileus, nothing is plugging the tube. The muscle simply stops moving. Peristalsis goes quiet. This shows up after belly surgery, when the gut is famously slow for a day or two. It also comes with peritonitis and with electrolyte trouble, especially hypokalemia, which means low potassium. Smooth muscle needs potassium to contract. Opioids do it too, since they slow the gut down. The difference matters a lot. A mechanical block often needs a procedure to open it. An ileus usually needs the cause fixed and the bowel rested.
| Feature | Mechanical obstruction | Paralytic ileus |
|---|---|---|
| Problem | Something plugs the lumen | Gut muscle stops squeezing |
| Common causes | Adhesions, hernia, tumor | After surgery, low potassium, opioids, peritonitis |
| Bowel sounds (early) | High-pitched, overactive, tinkling | Faint to absent from the start |
| Pain pattern | Crampy, wave-like (colicky) | Steady, spread-out ache |
| Usual fix | Often surgery or decompression | Treat the cause, rest the bowel |
The cardinal signs and why they happen
Whatever the cause, obstruction brings a classic set of four. Abdominal distension comes because fluid and swallowed air pile up behind the block, and the bowel balloons outward. Vomiting follows, since the backed-up contents have nowhere to go but up. A low (distal) block often brings foul, feculent vomiting, which smells like stool. A high (proximal) small-bowel block causes earlier, more forceful vomiting. Obstipation is the third sign. It means no stool and no gas passes at all, and it tells you nothing is getting through.
Bowel sounds are the fourth sign, and they tell a story over time. Early in a mechanical obstruction, listen for high-pitched, hyperactive, tinkling sounds as the muscle strains against the block. After hours the muscle tires out, or an ileus sets in. Then those sounds fade to absent. The classic teaching: sounds go high-pitched, then silent.
Why obstruction is an emergency
Trapped bowel does not just hurt. It dies. Fluid pours into the swollen loop, a shift called third-spacing. That drops the volume of blood in circulation. Now the patient risks hypovolemic shock plus metabolic trouble from all the lost fluid and electrolytes. Worse, the swelling can pinch off the bowel's own blood supply. Then the tissue is strangulated, it turns ischemic, which means starved of blood, and it can perforate. Gut contents spill into the belly and set off peritonitis and sepsis, both of which can kill. Fever, a rising heart rate, and sudden severe pain mean a simple block has become a surgical emergency.
GI bleeding: upper vs lower
Bleeding in the digestive tract is sorted by where it starts, because the look of the blood is a built-in clue. An upper GI bleed comes from above the ligament of Treitz. That means the esophagus, stomach, or duodenum. It is often caused by peptic ulcers or esophageal varices, which are swollen veins near the bottom of the esophagus. It shows up as hematemesis, or vomited blood. The blood may look like coffee grounds once stomach acid has partly digested it. It also shows up as melena, which is black, tarry, sticky stool. The stool is black because hemoglobin gets broken down on its long trip through the gut.
A lower GI bleed starts in the jejunum, ileum, or colon. Common causes are diverticulosis, angiodysplasia, hemorrhoids, and colorectal cancer. The blood leaves fast, with no time to be digested. So it shows up as hematochezia: bright red or maroon blood mixed with the stool or coating it.
Why a major bleed is an emergency
A big GI bleed can quietly drain enough blood to cause hypovolemic shock before anyone finds the source. Watch for tachycardia, a fast heart rate, and falling blood pressure. Watch for orthostatic dizziness on standing, pallor, and a dropping hemoglobin and hematocrit. Vital signs often change before the labs do. So trending them and getting IV access in place is the priority.
- Mechanical obstruction (adhesions, hernia, tumor) plugs the bowel. In paralytic ileus the gut muscle simply stops moving.
- The cardinal signs are distension, vomiting, obstipation (no stool or gas), and bowel sounds that go high-pitched then absent.
- Upper GI bleed = hematemesis and melena (black, tarry, digested blood). Lower GI bleed = hematochezia (bright red or maroon).
- A blockage can lead to strangulation, perforation, and peritonitis. A major bleed can cause hypovolemic shock. Both are true emergencies.
- Trend the vital signs, look for tachycardia and low blood pressure, and watch for third-spacing and lost electrolytes.
Section 4The liver: hepatitis & cirrhosis
Think of your liver as the body's busiest chemistry lab. It sits under your right ribs and quietly runs hundreds of jobs at once. Three of those jobs explain most of what goes wrong. First, the liver is the body's detox center. It filters drugs, alcohol, and waste out of the blood. It also turns toxic ammonia, a waste product of protein breakdown, into urea so the kidneys can flush it out. Second, the liver is a factory. It builds most of the body's clotting factors and albumin, the protein that holds fluid inside blood vessels. Third, it handles bilirubin, the yellow-orange pigment left over when old red blood cells are recycled. The liver packs it up so it can leave the body in bile and stool. Hold on to those three jobs. Nearly every sign of liver disease traces back to one of them failing.
Hepatitis: when the liver gets inflamed
Hepatitis simply means the liver is inflamed. Viruses cause most cases. Alcohol and some drugs do the same damage, and acetaminophen in overdose is a big one. The three viral players act in different ways, and that difference drives treatment.
| Feature | Hepatitis A | Hepatitis B & C |
|---|---|---|
| How it spreads | Fecal-oral (food or water with stool in it) | Blood & body fluids (needles, sex, birth) |
| Course | Sudden, then clears on its own; usually full recovery | Often turns chronic; can smolder for years |
| Long-term risk | Rarely leaves lasting damage | Cirrhosis & liver cancer |
| Prevention | Vaccine; clean hands | Hep B vaccine; no Hep C vaccine yet |
During acute hepatitis, patients often feel worn out and sick to the stomach. Many turn jaundiced, with yellow skin and eyes, because the inflamed liver cannot keep up with bilirubin. Alcoholic and drug-induced hepatitis follow the same theme. The toxin harms liver cells, called hepatocytes, faster than they can heal.
Cirrhosis: scarring that does not undo
When injury to the liver goes on long enough, the healing itself becomes the problem. The liver stops rebuilding normal tissue. Instead it lays down fibrosis, which is scar tissue. Cirrhosis is the end-stage result. The once-soft organ turns hard, lumpy, and shrunken. Scar tissue cannot do liver work. It also will not let blood flow through the way it should. Those two facts explain the chain of problems that follows.
Portal hypertension and its downstream chaos
Normally, blood from the intestines drains through the portal vein into the liver. Cirrhotic scar tissue squeezes those channels, so pressure backs up. That state is called portal hypertension. The high pressure pushes blood into detours through smaller veins that were never built for the load. Where those veins swell, problems show up:
- Esophageal varices are ballooned, fragile veins at the base of the esophagus. They can burst and bleed fast enough to kill.
- Ascites is fluid pooling in the belly. Two forces drive it. The high portal pressure pushes fluid out of the vessels. And the failing liver makes too little albumin to hold fluid in. Low albumin means low oncotic pressure, the inward pull that keeps water in vessels. So water leaks into the belly.
Why liver failure causes bleeding and jaundice
Remember the factory job. A failing liver stops making enough clotting factors. Patients bruise and bleed easily, and lab tests show a long PT/INR. Pair that with fragile varices, and bleeding becomes a true emergency. Remember the bilirubin job too. As the liver fades, bilirubin builds up in the blood. It stains the skin and the sclera, the white of the eye, yellow. That is the classic jaundice.
Hepatic encephalopathy: the toxin job fails
When the detox center goes down, ammonia from protein digestion is no longer turned into urea. It builds up and crosses into the brain. The result is hepatic encephalopathy: confusion, changes in personality, and a flapping tremor of the hands called asterixis. Early confusion is an important warning sign. The drug lactulose is given to trap ammonia in the gut and pull it out in the stool.
- The liver detoxifies, turning ammonia into urea. It builds clotting factors and albumin, and it processes bilirubin. Remember these jobs and the symptoms make sense.
- Hepatitis is liver inflammation. Hep A spreads fecal-oral and clears up. Hep B and C spread through blood, often turn chronic, and lead to cirrhosis.
- Cirrhosis is scarring that cannot be undone. The scar tissue blocks blood flow and causes portal hypertension, which drives esophageal varices and ascites.
- Liver failure causes bleeding (too few clotting factors, high PT/INR) and jaundice (bilirubin building up).
- Rising ammonia causes hepatic encephalopathy (confusion, asterixis), usually treated with lactulose.
Section 5Gallbladder & pancreas

Your gallbladder and pancreas are two quiet helpers. They sit just under your liver and stomach. The gallbladder is a small green sac that stores bile. Bile is a soap-like fluid the liver makes to break up fat. When you eat a greasy meal, a hormone called cholecystokinin (CCK) tells the gallbladder to squeeze. Bile then runs down the common bile duct into the small intestine. The pancreas pours strong digestive enzymes down its own pancreatic duct. That duct usually joins the bile duct right before both empty into the duodenum. Those enzymes are supposed to stay switched off until they reach the gut. Trouble starts when a stone plugs the plumbing, or when the enzymes switch on too early.
Gallstones and cholecystitis
Bile with too much cholesterol can harden into gallstones. So can bile that sits too long. The medical name is cholelithiasis. Many stones are silent. But a stone can lodge in the neck of the gallbladder or in the cystic duct. Then the gallbladder keeps squeezing against a locked door. It becomes trapped, inflamed, and infected. That is acute cholecystitis. Fatty food is what makes the gallbladder squeeze. So the classic story is right-upper-quadrant (RUQ) pain 30 minutes to a few hours after a fatty meal. The pain often spreads to the right shoulder or shoulder blade, with nausea and vomiting. It can be severe and cramping, which is called biliary colic.
One useful clue is Murphy's sign. Place your hand under the right rib margin. Ask the patient to take a deep breath. The inflamed gallbladder drops onto your fingers. The patient catches their breath and stops from the pain. A positive Murphy's sign points strongly to cholecystitis. For the classic risk profile, think of the 4 F's: female, forty, fertile, and overweight.
When a stone blocks the ducts
A stone that escapes the gallbladder can travel and wedge in deeper. If it blocks the common bile duct, bile backs up. The name for that stone is choledocholithiasis. Bilirubin spills into the blood, so the skin and eyes turn yellow. That is jaundice. The urine darkens, and stools turn clay-pale, because bile pigment no longer reaches the gut. Trapped, still bile invites infection of the whole bile duct system, which is called cholangitis.
Here is the dangerous overlap. The bile duct and the pancreatic duct usually share one final channel. So one stone can dam both. If it blocks the spot where the pancreatic duct drains, enzymes cannot escape. Pressure rises. Now the pancreas is set up to attack itself.
Acute pancreatitis: the organ that digests itself
Acute pancreatitis happens when those digestive enzymes switch on inside the pancreas instead of the intestine. Trypsin turns on too early and wakes up the rest. The gland then starts to digest its own tissue. That self-digestion is called autodigestion. The result is fierce inflammation, swelling, and sometimes bleeding.
The hallmark is severe, constant epigastric pain that bores straight through to the back. Epigastric means the upper middle belly. Patients often feel worse lying flat and better leaning forward. Nausea and vomiting are common, and the belly may be tender and swollen. On labs, lipase rises sharply, usually more than three times the upper normal limit. It also stays up longer than amylase. That makes lipase the more specific marker.
What causes it
Two causes lead by a wide margin: gallstones and alcohol. A handy memory hook is "I GET SMASHED," in which the first culprits are Idiopathic, Gallstones, and Ethanol. Gallstones block the shared duct. Alcohol is directly toxic to pancreatic cells and thickens their secretions.
| Feature | Cholecystitis | Acute pancreatitis |
|---|---|---|
| Core problem | Blocked, inflamed gallbladder | Pancreas digesting itself |
| Pain location | Right upper quadrant, to right shoulder | Epigastric, boring to the back |
| Trigger | Fatty meal | Alcohol or a gallstone |
| Key exam/lab | Positive Murphy's sign | High lipase |
- Gallstones can block bile flow. If the neck or cystic duct is blocked, the gallbladder inflames (cholecystitis), with RUQ pain after fatty meals and a positive Murphy's sign.
- A stone in the common bile duct causes jaundice, dark urine, and pale stools. Because the ducts share a channel, one stone can block the pancreatic duct too.
- Acute pancreatitis is autodigestion. Enzymes switch on early and the pancreas attacks itself, causing severe epigastric pain that bores to the back.
- Lipase is the key lab. It is usually more than triple the upper limit, and it is more specific than amylase.
- The top two causes of pancreatitis are gallstones and alcohol.
Section 6Jaundice & bilirubin
Every day, your body quietly retires about 1% of its red blood cells. Most have simply worn out after roughly 120 days in circulation. When a red cell breaks down, the hemoglobin inside it is taken apart. The heme part becomes a yellow-orange pigment called bilirubin. This first form is unconjugated (indirect) bilirubin, and it has a problem. It is fat-loving and does not dissolve in water. So it cannot simply be flushed out in urine. Instead it rides through the blood stuck to albumin, and it is dropped off at the liver.
How the liver handles bilirubin
The liver is the cleanup station. Liver cells, or hepatocytes, take in unconjugated bilirubin. They attach sugar molecules to it using an enzyme called UDP-glucuronyl transferase. This step is conjugation. It turns the pigment into conjugated (direct) bilirubin, which now dissolves in water. The liver sends conjugated bilirubin into bile. Bile drains through the bile ducts into the small intestine. There, gut bacteria change it into urobilinogen and then stercobilin. Stercobilin is the pigment that gives stool its normal brown color. A small amount is taken back up and leaves in urine as urobilin, which gives urine its yellow tint.
Jaundice, also called icterus, is the yellowing of skin, mucous membranes, and the sclera of the eyes. It appears when serum bilirubin rises above roughly 2 to 3 mg/dL. Bilirubin loves fatty tissue and tissue rich in elastin. That is why the sclera and skin show it first. Jaundice is never a disease by itself. It is a signal that one of the steps above has broken down. To find the break, jaundice is sorted by where in the pathway the problem sits.
The three types of jaundice
Prehepatic (hemolytic) jaundice starts before the liver. Red cells are destroyed faster than the liver can keep up. Causes include hemolytic anemias, sickle cell crisis, and transfusion reactions. The liver is healthy but swamped. So unconjugated bilirubin piles up in the blood.
Hepatic (intrahepatic) jaundice comes from the liver itself being sick. In hepatitis, cirrhosis, or drug injury, damaged hepatocytes cannot conjugate and clear bilirubin well. Both unconjugated and conjugated forms often rise.
Posthepatic (obstructive) jaundice starts after the liver, when bile cannot drain. A gallstone in the common bile duct can block the flow, and so can a tumor in the head of the pancreas. Conjugated bilirubin already dissolves in water, so it backs up and spills into the blood.
| Feature | Prehepatic (hemolytic) | Posthepatic (obstructive) |
|---|---|---|
| Problem | Too many red cells breaking down | Bile cannot drain |
| Main bilirubin type | Unconjugated (indirect) | Conjugated (direct) |
| Urine color | Usually normal | Dark (tea-colored) |
| Stool color | Normal or dark | Pale/clay-colored |
| Itching (pruritus) | Not common | Common |
Why urine darkens and stool turns pale
This clue is one of the most useful of all, and it makes sense once you follow the plumbing. In obstruction, conjugated bilirubin cannot reach the intestine. No stercobilin is made, so stool loses its brown pigment and turns pale or clay-colored. Meanwhile the water-soluble conjugated bilirubin backs up into the blood. The kidneys can filter this water-soluble form. So it shows up in urine, turning it dark, tea-colored. Bile salts also build up under the skin, which often causes intense pruritus, or itching.
Newborn jaundice in one line
Physiologic jaundice of the newborn is common and usually harmless. A baby's young liver has not yet made enough UDP-glucuronyl transferase to conjugate bilirubin quickly. So unconjugated bilirubin rises for a few days. It is often treated with phototherapy, a special light that breaks the pigment down.
An interactive figure below lets you explore how rising bilirubin turns tissues yellow.
- Bilirubin is a pigment from broken-down red cells. The liver conjugates it, which makes it dissolve in water, and sends it out in bile.
- Jaundice shows up when serum bilirubin passes about 2 to 3 mg/dL. It is sorted as prehepatic (hemolysis, unconjugated), hepatic (liver disease, both), or posthepatic (blocked bile, conjugated).
- Blocked bile causes dark urine, since water-soluble conjugated bilirubin spills into urine. It also causes pale stool, since no stercobilin reaches the gut. Itching is common.
- Hemolytic jaundice usually leaves urine and stool color normal, because the extra bilirubin is unconjugated and cannot enter urine.
- Newborn physiologic jaundice comes from a young liver enzyme system and is often treated with phototherapy. Severe cases risk kernicterus.
The chapter in one breath
- GERD happens when a weak lower esophageal sphincter lets acid stomach contents wash back up. The acid burns the esophageal lining and causes heartburn and regurgitation. Over time it can drive Barrett esophagus.
- Peptic ulcers are breaks in the stomach or duodenal wall. Most come from H. pylori infection or NSAIDs stripping the protective mucus barrier, so acid digests the tissue itself. Watch for coffee-ground emesis or melena, which signal a bleed.
- Crohn disease causes patchy, full-thickness (transmural) inflammation anywhere from mouth to anus, with skip lesions and fistulas. Ulcerative colitis is continuous, mucosa-only inflammation limited to the colon, with bloody diarrhea.
- A bowel obstruction blocks flow through the intestine. Gas and fluid back up, causing distension, vomiting, and bowel sounds that go high-pitched then absent. Strangulation cuts off the blood supply and threatens ischemic necrosis, meaning tissue death.
- A GI bleed from an upper source shows as black tarry melena or hematemesis. A lower source shows bright red hematochezia. Either one can drop hemoglobin and push the patient toward hypovolemic shock.
- Hepatitis is liver inflammation from viruses (A-E), alcohol, or toxins, and it blocks the liver's jobs. Repeated injury drives scarring into cirrhosis, where fibrosis raises portal hypertension and causes ascites, esophageal varices, and bleeding from lost clotting factors.
- Gallstones form when bile holds too much cholesterol. A stone stuck in the cystic duct triggers cholecystitis, with RUQ pain that worsens after fatty meals. A stone blocking the common duct can back bile into the pancreas.
- Pancreatitis is the pancreas digesting itself with its own switched-on enzymes, usually after gallstones or alcohol. It causes severe epigastric pain that spreads to the back, with sharply raised lipase and amylase.
- Jaundice is yellow skin and sclera from bilirubin building up, and its type points to the problem. Unconjugated comes from too much hemolysis or a young or failing liver. Conjugated comes from blocked bile flow, which also gives dark urine and clay-colored stools.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Ascites
- Protein-rich fluid building up inside the peritoneal cavity, which is the belly. Portal hypertension and low blood albumin usually drive it. The abdomen swells and feels tight.
- Barrett esophagus
- A change in the lower esophageal lining after years of acid reflux. Normal squamous cells turn into gut-type columnar cells, a change called metaplasia. It raises the risk of esophageal cancer.
- Bilirubin
- The yellow pigment made when the body breaks down old red blood cells. When it builds up in the blood it causes jaundice and turns the skin and the whites of the eyes yellow.
- Cholecystitis
- Inflammation of the gallbladder, usually because a gallstone blocks the cystic duct. It causes right-upper-quadrant pain, fever, and often a positive Murphy sign.
- Cirrhosis
- Lasting scarring, or fibrosis, of the liver. Hard nodules replace working tissue, so the liver slowly loses its ability to filter blood, make proteins, and clear toxins.
- Crohn disease
- A long-term inflammatory bowel disease that can inflame any part of the GI tract from mouth to anus in patchy skip lesions. The inflammation goes through the full thickness of the bowel wall, which is called transmural.
- GERD
- Gastroesophageal reflux disease. Stomach acid flows back into the esophagus again and again, because the lower esophageal sphincter is weak or opens too easily. It causes heartburn and regurgitation.
- Hematochezia
- Bright red or maroon blood passing through the rectum. It usually means bleeding low in the GI tract, in the colon, rectum, or anus. A very fast upper GI bleed can look the same.
- Hepatic encephalopathy
- A drop in brain function, from confusion all the way to coma. It happens when a failing liver can no longer clear ammonia and other toxins from the blood, so they reach the brain.
- H. pylori
- Helicobacter pylori, a spiral-shaped bacterium that burrows into the stomach's protective mucus layer. It is the leading cause of peptic ulcers and long-term gastritis.
- Ileus
- A short-term loss of the normal muscle waves, or peristalsis, of the intestine. It often follows belly surgery. Contents stop moving even though nothing is physically blocking them.
- Melena
- Black, tarry, foul-smelling stool. It forms when blood from an upper GI bleed is digested on its way through the gut, which turns the hemoglobin dark.
- Pancreatitis
- Inflammation of the pancreas. Its digestive enzymes switch on too early and begin to digest the organ itself. Gallstones or alcohol usually trigger it, and it causes severe epigastric pain that spreads to the back.
- Peptic ulcer
- An open sore in the lining of the stomach or duodenum, where acid and pepsin have eaten through the protective mucosa. H. pylori or NSAID use causes most of them.
- Portal hypertension
- Blood pressure that is too high in the portal venous system feeding the liver, usually because cirrhosis backs up blood flow. It drives ascites, esophageal varices, and an enlarged spleen.
- Ulcerative colitis
- A long-term inflammatory bowel disease limited to the colon and rectum. It inflames only the innermost lining, the mucosa, in one continuous stretch. It causes bloody diarrhea and urgency.
DrillFlashcards for this unit
These are the Week 13 cards, the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track how well you know the whole deck, open the full flashcards page.
Check yourself
Musculoskeletal & Integumentary
This last chapter covers the frame and the wrapping. The frame is the bones and joints that hold you up. The wrapping is the skin that keeps the world out. We start with broken bones and the dangers that follow. Then come the common joint diseases. Then we move to the skin: its own disorders, its infections, and the whole-body emergency of a bad burn.
By the end of this chapter you can
- Name the fracture types and the stages of bone healing.
- Spot compartment syndrome and fat embolism as emergencies.
- Tell osteoarthritis from rheumatoid arthritis, and spot gout and osteoporosis.
- Stage pressure injuries and spot melanoma with ABCDE.
- Judge how deep and how big a burn is, and name the first jobs.
Section 1Fractures & bone healing
Bone looks solid and fixed. In truth it is living tissue that rebuilds itself all the time. A hard outer shell of compact (cortical) bone wraps a spongy inner layer. The whole bone wears a thin skin called the periosteum, packed with blood vessels and nerves. Inside, two cell crews work in a lifelong team. Osteoblasts lay down new bone matrix. Osteoclasts break old matrix down. Because bone is full of vessels and nerves, a break bleeds and hurts a lot. A fracture is simply a break in the continuity of a bone. It happens when the force on the bone is more than the bone can soak up. The cause may be a fall, a crash, stress over and over, or a bone already weak from disease.
Types of fractures
The name of a fracture tells you what happened to the bone. That guides the care. The first question is always the same. Is the skin broken?
| Feature | Closed (simple) | Open (compound) |
|---|---|---|
| Skin | Whole over the break | Bone pokes through skin, or a wound reaches the bone |
| Infection risk | Lower | High. It is an orthopedic emergency |
| Priority | Line the bone up and hold it still | Keep infection out (osteomyelitis), then repair |
Next we name the break pattern. A complete fracture goes all the way through and splits the bone into pieces. An incomplete fracture cracks only part way. The classic one is a greenstick fracture. A soft child's bone bends and splinters on one side, like a young twig. Other patterns are easy to picture. Comminuted means the bone shatters into three or more pieces, often from a hard, fast hit. Transverse is a straight break across the shaft. Oblique is an angled line. Spiral comes from a twisting force, and it can be a red flag for abuse. Compression means the bone is crushed, which is typical in spine bones thinned by osteoporosis. Pathologic means the break runs through bone already weak from a tumor or disease. A stress fracture is a tiny crack from doing one thing over and over.
How bone heals
Bone is one of the few tissues that can heal with no scar. It rebuilds itself back into living bone. Healing moves through stages that overlap. The whole job takes weeks to months.
- Hematoma formation (first hours to days): torn vessels bleed, and a clot forms at the break. This fracture hematoma seals the bone ends. It also brings in cells that clean up debris. That is why the spot is swollen, warm, and sore early on.
- Soft callus (roughly days to 2-3 weeks): fibroblasts and chondroblasts build a soft bridge across the gap. The bridge is fibrous tissue and cartilage. It is weak, which is just why the bone must stay still now.
- Hard callus (about 3 weeks to several months): osteoblasts swap the soft bridge for woven bone. This lumpy but sturdy bony callus joins the pieces.
- Remodeling (months to years): osteoclasts and osteoblasts reshape the callus along the lines of stress. The bone gets its old strength and shape back.
Signs of a fracture, and why we line it up and hold it still
Think fracture when pain gets worse with movement. Look for swelling, bruising (ecchymosis), and clear deformity or a shorter limb. The part may also show loss of function. Sometimes you hear or feel crepitus, a grating as bone ends rub. Alignment (reduction) puts the pieces back where they belong. Then the callus bridges the gap in the right place and the limb heals straight. Immobilization with a cast, splint, or fixation holds that line so healing can go on. Just as important, it keeps sharp bone ends from tearing nearby nerves and vessels.
Why osteoporosis raises fracture risk
In a healthy adult, bone breakdown and rebuilding stay even. In osteoporosis, osteoclasts work faster than osteoblasts. Bone is taken away faster than it is put back. The result is low bone mass and deteriorated microarchitecture, which means a damaged inner structure. The bone is left porous and brittle. People call it a silent disease, since nothing hurts until a bone breaks. Falling estrogen after menopause is a big driver. Estrogen normally holds osteoclasts back. So postmenopausal women often get fragility fractures of the hip, wrist, and spine. These come from forces that would never break healthy bone, such as a small bump or even a hard cough.
The interactive figure lets you compare fracture patterns. You can also walk through the healing stages. Go explore it below.
- A fracture is a break in bone continuity. Describe it by the skin (open or closed) and by the pattern (complete, greenstick, comminuted, and others), since those details guide care.
- Healing runs hematoma, soft callus, hard callus, then remodeling. The soft callus stage is weak, which is why we hold the bone still.
- Classic signs are pain, swelling, deformity, loss of function, and crepitus. Always check nerves and blood flow with the 5 P's: pain, pulse, pallor, paresthesia, and paralysis, below (distal to) the injury. An abnormal check is the cue to move to the 6 P's.
- Reduction puts the bone back in line, and immobilization holds it there. The bone heals straight and nearby nerves and vessels stay safe.
- Osteoporosis tips the balance toward breakdown. Bone turns porous and brittle, and fragility fractures follow, above all in postmenopausal women.
Section 2Fracture complications
When a bone breaks, the body starts a well-ordered repair job. Blood pools at the break and clots into a hematoma. Cleanup cells clear the debris. A soft cartilage callus bridges the gap. Over weeks, hard bone replaces that callus, and then it is reshaped. For all this to work, the tissue around the break needs steady blood flow, oxygen, and room to swell. Most fracture complications start when one of those is lost. Pressure builds where it cannot escape. Clots or fat drops travel where they should not. Or the healing timeline stalls. Explore the interactive figure below as you read.
Compartment syndrome: pressure with nowhere to go
Muscles sit in compartments wrapped in tough fascia that does not stretch. After a fracture, often the tibia or forearm, bleeding and swelling raise the pressure in that closed box. The fascia will not give. So the thin-walled veins squash shut first, blood backs up, and swelling gets worse. Then the pressure squeezes the capillaries until tissue no longer gets oxygen. This is acute compartment syndrome, and it is a surgical emergency. Without a fast fasciotomy to open the compartment, muscle and nerve die within hours. That can cost the limb.
Work through the 6 P's. The earliest and most reliable is pain out of proportion to the injury. Pain when you gently stretch the fingers or toes is a strong clue. The rest are paresthesia (pins and needles, from nerve starved of blood), pallor, poikilothermia (a limb that drifts to room temperature), paralysis, and pulselessness. A tight, tense feel to the compartment goes with them, though it is not one of the six. Here is the key point. Pulselessness is a late sign. If you wait for the pulse to vanish, the muscle is already dying.
Fat embolism syndrome: droplets on the move
Long bones such as the femur hold fatty yellow marrow, and so does the pelvis. When they break, marrow fat can slip into torn venous channels. It travels to the lungs and sets off a storm of inflammation. Classic fat embolism syndrome (FES) shows up 24 to 72 hours after the injury as a triad. First comes respiratory distress: low blood oxygen (hypoxemia), fast breathing (tachypnea), and shortness of breath (dyspnea) as fat plugs lung capillaries. Second come neurologic changes: confusion, restlessness, and a drop in alertness. Third is a petechial rash across the chest, the armpits, and the eye linings (conjunctivae). Those tiny red spots are fairly specific, so watch for them. Care is mostly supportive with oxygen. The best medicine is prevention, which means fixing the fracture early.
Clots from lying still: DVT and PE
Lying still after a fracture ticks every box of Virchow's triad. There is venous stasis, since the calf muscles are not pumping. There is hypercoagulability, because the injury itself makes blood clot more easily. And there is endothelial injury, damage to the vessel lining. The result is a deep vein thrombosis (DVT), usually in the calf, with swelling, warmth, and tenderness in one leg. The feared next step is a piece breaking off and lodging in the lung. That is a pulmonary embolism (PE). It brings sudden shortness of breath (dyspnea), sharp chest pain with each breath (pleuritic pain), a fast heart rate (tachycardia), and low oxygen (hypoxia). Prevention is gold: get patients moving early, use sequential compression devices, and give prophylactic anticoagulation, which means blood thinners to head off clots.
| Feature | Fat embolism | Pulmonary embolism (from DVT) |
|---|---|---|
| Usual timing | 24 to 72 hours after the break | Days to weeks (from lying still) |
| What travels | Drops of marrow fat | A blood clot |
| Telltale sign | Petechiae plus confusion | Sudden sharp chest pain, DVT in the leg |
| Fracture link | Long bone or pelvis | Any, from lying still |
When healing stalls: delayed union, nonunion, and infection
Healing needs three things: blood supply, a steady hold, and bone ends that meet. Delayed union means healing is slower than expected but still moving. Nonunion means a fracture has stopped healing. Common reasons are poor blood flow, too much motion, a wide gap, or infection, and it usually needs surgery or a bone graft. Malunion means the bone healed crooked. Osteomyelitis is a bone infection. It is a special threat in open fractures, where broken skin lets bacteria reach bone straight away. It shows up as local pain, warmth, drainage, and fever, and it is famously hard to clear.
- Compartment syndrome is a surgical emergency. Pain out of proportion is the earliest sign and pulselessness is late. Treat with fasciotomy, and never ice or raise the limb above the heart.
- The 6 P's: pain, paresthesia, pallor, poikilothermia, paralysis, pulselessness.
- Fat embolism follows long bone or pelvic fractures at 24 to 72 hours, with trouble breathing, confusion, and petechiae. Prevent it by fixing the fracture early.
- Lying still (immobility) drives DVT and PE through Virchow's triad. Prevent them with early movement, SCDs, and blood thinners.
- Nonunion, malunion, and osteomyelitis stall recovery. Frequent neurovascular checks are the priority for catching trouble early.
Section 3Musculoskeletal disorders
Bone can feel like the most lifeless part of you. In truth it is living, changing tissue. Two crews work on it your whole life. Osteoblasts lay down new bone, and osteoclasts chew old bone away. This steady teardown and rebuild is called remodeling. While the two crews stay even, bone stays strong. Joints glide for another reason. The bone ends wear a slick cap of articular cartilage and float in synovial fluid. When that balance or that cushion fails, you get the disorders below. Explore the interactive figure below to see each one.
Osteoporosis: quietly losing bone
In osteoporosis, the osteoclasts outwork the osteoblasts. More bone is removed than replaced. The bone left behind has normal chemistry. There is simply less of it. Bone mineral density (BMD) drops, and the inner scaffold grows thin and porous. The result is fragility. Bones snap under loads a strong skeleton would shrug off. A minor fall, or even a hard cough, can cause a fragility fracture. The classic sites are the hip, wrist, and vertebrae. Crushed spine bones explain the lost height and the stooped upper back (kyphosis) seen in many older adults.
The scary part is that it is usually silent until something breaks. Patients feel nothing while density slips away. Risk climbs with age and with being female. Estrogen normally holds osteoclasts back, so density can drop sharply after menopause. Other risks are a small body frame, smoking, low calcium and vitamin D, and long-term corticosteroid use. Screening uses a DEXA scan, reported as a T-score. A value of -2.5 or lower usually means osteoporosis.
Osteoarthritis vs rheumatoid arthritis
Both get called "arthritis," but they are not the same problem at all. Osteoarthritis (OA) is a mechanical, wear-and-tear process. Over years, the articular cartilage that cushions a joint frays and thins, until bone rubs on bone. It targets the weight-bearing joints, which are the knees, hips, and spine. It also hits the small joints at the fingertips. The pain is use-related. It is worse after activity and at the end of the day, and better with rest. The damage is local and mechanical, so there are no systemic signs. No fever, no whole-body tiredness. Morning stiffness is brief, usually under 30 minutes.
Rheumatoid arthritis (RA) is an autoimmune disease. The immune system attacks the synovium, which is the joint lining. The lining swells into a damaging tissue called pannus that eats cartilage and bone from within. RA is symmetric, hitting both hands and both wrists. It favors the small joints of the hands and feet. Its hallmark is morning stiffness lasting longer than an hour. Because the whole immune system is at work, it brings systemic signs: tiredness, low-grade fever, and high inflammatory markers (ESR, CRP). Over time it can bend joints into set patterns, such as ulnar deviation.
| Feature | Osteoarthritis | Rheumatoid arthritis |
|---|---|---|
| Cause | Wear-and-tear cartilage loss | Autoimmune attack on the joint lining |
| Joints | Weight-bearing, often asymmetric (not matched side to side) | Small joints, symmetric (matched side to side) |
| Pain pattern | Worse with use, better with rest | Stiff after rest, eases with movement |
| Morning stiffness | Usually < 30 min | Usually > 1 hour |
| Systemic signs | None | Tired, fever, high ESR/CRP |
Gout: crystals in the joint
Gout comes from too much uric acid, which is waste from breaking down purines. When blood uric acid stays high (hyperuricemia), needle-shaped monosodium urate crystals form inside a joint. The immune system treats the crystals as invaders and attacks hard. The attack is sudden and severe, and it often starts overnight. The joint turns red, hot, and swollen. It gets so tender that even a bedsheet hurts. The classic first target is the big toe, at the first metatarsophalangeal joint, and that picture is called podagra. Attacks are often set off by red meat, shellfish, alcohol, or too little fluid.
Telling them apart
A few quick questions usually sort these out. Ask about tempo. Gout blows up in hours, while OA and RA build over years. Ask about pattern. OA hits big weight-bearing joints and gets worse with use. RA hits small joints symmetrically, on both sides, with long morning stiffness. Gout usually strikes one joint, classically the toe. Ask about the whole body. Tiredness and fever point toward RA, or toward a gout flare. OA stays purely local. And remember that osteoporosis sits in its own lane. It is painless until a fragile bone fractures.
- Osteoporosis is silent low bone density (osteoclasts > osteoblasts). It leads to fragility fractures of the hip, wrist, and spine, and a DEXA T-score makes the call.
- Osteoarthritis is mechanical cartilage wear in weight-bearing joints. It is worse with use, stiffness is brief, and there are no systemic signs.
- Rheumatoid arthritis is autoimmune synovitis: symmetric small joints, morning stiffness > 1 hour, and whole-body signs such as tiredness, fever, and high ESR/CRP.
- Gout is urate crystals in a joint. It causes a sudden, severe, single hot joint, classically the big toe (podagra).
- Sort by tempo, pattern, and systemic signs: hours or years, one joint or both sides, local or whole-body.
Section 4Skin conditions
Your skin is the largest organ you have. Its main job is to be a barrier, a smart wall that repairs itself, between your insides and the outside world. It keeps water in and germs out. It senses touch and heat, and it helps hold your body heat steady. Once you see that barrier job, most skin disease starts to make sense. These are the ways the wall goes wrong: it gets inflamed, overbuilt, broken down, or invaded.
Skin has three layers. The epidermis is the thin, tough top layer. It makes the waterproof keratin shell, and it sheds and regrows all the time. Under it, the dermis holds collagen, blood vessels, nerves, hair follicles, and sweat glands. Below that sits the subcutaneous (hypodermis) layer of fat and connective tissue, for insulation and padding. Damage that stays in the epidermis usually heals cleanly. Damage that reaches the dermis or deeper is where scars and serious injury begin.
Dermatitis (eczema) and psoriasis
Dermatitis is inflammation of the epidermis. In its atopic form it is often called eczema. The skin barrier leaks, so water escapes and irritants and allergens get in. The immune system overreacts. The skin turns red and itchy, and it may weep or crust. The problem is inflammatory and often allergic. So it flares with triggers like soaps, stress, and dry air. It gets better with moisturizers and with steroid creams that calm the inflammation.
Psoriasis looks different because the mechanism is different. Here the trouble is fast epidermal turnover. Skin cells that should take about a month to rise and shed do it in days. An overactive immune response (T cells) drives that speed. The cells pile up faster than they can mature. They form thick plaques topped with silvery scales, classically on the elbows, knees, and scalp. It is long-lasting and autoimmune in nature, so we manage it rather than cure it.
| Feature | Eczema/Dermatitis | Psoriasis |
|---|---|---|
| Core mechanism | Leaky barrier plus allergic inflammation | Fast cell turnover (autoimmune) |
| Look | Red, weepy, crusted, very itchy | Thick plaques with silvery scale |
| Typical sites | Flexural folds (skin creases), hands, face | Elbows, knees, scalp (extensor) |
Pressure injuries
A pressure injury used to be called a pressure ulcer or bedsore. It starts when steady pressure squeezes blood vessels shut. The spot is usually over a bone, such as the sacrum, the heels, or the hips. With no blood flow, tissue runs out of oxygen (ischemia) and starts to die. Shear and moisture make it worse. That is why patients who cannot move are at such risk, and why prevention is such a priority. Here is the standard staging:
- Stage 1: skin is still whole, with redness that does not blanch.
- Stage 2: partial-thickness loss into the dermis. You see a shallow open sore or a blister.
- Stage 3: full-thickness loss with fat in view.
- Stage 4: full-thickness loss with muscle, tendon, or bone in view.
- Unstageable means slough or eschar hides the base. Deep tissue injury means a lasting maroon or purple patch. Both are their own categories.
Prevention is all about taking the pressure off. Turn the patient, usually every 2 hours. Float the heels. Use support surfaces. Keep skin clean and dry. Keep food and fluids up, so tissue can repair.
Skin cancers and the ABCDE rule
Most skin cancer traces back to UV damage to DNA in epidermal cells. Those cells then grow out of control. The three big ones differ sharply in how dangerous they are.
- Basal cell carcinoma: the most common and the least aggressive. It starts in basal keratinocytes. It often looks like a pearly, pink, or waxy bump that may break open. It rarely spreads (metastasizes), but it does eat local tissue.
- Squamous cell carcinoma: starts in upper keratinocytes. It looks scaly or crusted, or like a firm red lump. It spreads more often than basal cell if it is ignored.
- Melanoma: the deadliest. It starts in melanocytes, the cells that make pigment. It grows and spreads fast, so catching it early saves lives.
Screen odd moles with ABCDE. Asymmetry means one half does not match the other. Border means a ragged edge. Color means more than one shade. Diameter means wider than about 6 mm, the size of a pencil eraser. Evolving means any change in size, shape, or color, or new bleeding or itching.
Take a look at the interactive figure below. It shows how these common skin conditions really appear.
- The skin's three layers (epidermis, dermis, subcutaneous) form a barrier. Most skin disease is that barrier inflamed, overbuilt, broken down, or invaded.
- Eczema is a leaky barrier with allergic inflammation, so the skin is red, weepy, and itchy. Psoriasis is fast autoimmune turnover, making thick, silvery plaques.
- Pressure injuries come from ischemia under steady pressure. They run from stage 1 (redness that will not blanch) to stage 4 (muscle or bone in view), and we prevent them with turning, offloading, skin care, and food.
- Basal cell cancer is common and stays local, squamous cell can spread, and melanoma is the deadliest because it spreads early.
- Use ABCDE, which is Asymmetry, Border, Color, Diameter >6 mm, and Evolving, to flag a lesion for a closer look.
Section 5Skin infections
Your skin is your body's largest organ and its first wall of defense. Two layers do the heavy lifting. The tough outer epidermis is waterproofed by a protein called keratin. The deeper dermis holds blood vessels, nerves, and hair follicles. On top of all this lives a healthy crowd of harmless bacteria and fungi, the normal skin flora. There is also an oily, slightly acidic film, the acid mantle, that keeps troublemakers in check. Infection happens when that barrier is breached. A cut, a scratch, cracked skin, a bug bite, or a weak immune system can do it. Then organisms slip past the wall and multiply faster than your defenses can clear them.
Bacterial infections: cellulitis, impetigo, and MRSA
Cellulitis is a deep infection of the dermis and the fat below it. It is usually caused by Streptococcus or Staphylococcus aureus. Bacteria enter through a break in the skin, and your immune system floods the area. That is exactly why you see the classic signs: redness, warmth, swelling, and pain. Those signs are not the bacteria. They are inflammation, with wide vessels bringing white blood cells and fluid. The border is often fuzzy and moving outward. The edge is often drawn with a pen and the time noted, so the team can see if it advances.
Impetigo is a surface infection of the epidermis, most common in young children. It makes oozing sores that dry into a signature honey-colored crust. It spreads very easily by touch, and scratching carries it further. MRSA stands for methicillin-resistant Staphylococcus aureus. It is not a different disease, it is a resistant strain. It shrugs off common penicillin-family antibiotics, because its penicillin-binding protein is altered. MRSA often looks like an angry, painful abscess or boil that patients swear was a "spider bite." It needs specific antibiotics, and an abscess must be drained.
Fungal infections: tinea and candida
Fungi love places that are warm, dark, and moist, which tells you exactly where to look. Tinea (dermatophyte infection) feeds on keratin in the dead outer skin. The fungus grows outward while the center clears. That makes a ring with a raised, scaly edge, and it is why we say ringworm. There is no worm involved. Tinea gets body-part names: tinea pedis (athlete's foot), tinea cruris (jock itch), and tinea capitis (scalp).
Candida is a yeast that normally lives on us quietly. It overgrows in skin folds, under the breasts, in the groin, and in diaper areas. It makes a beefy-red rash with satellite lesions, which are small separate spots near the edges. It thrives after antibiotics wipe out rival bacteria. It also thrives in patients with diabetes or a weak immune system. That is one reason high blood sugar and repeat yeast infections often travel together.
Viral infections: herpes simplex and herpes zoster
Herpes viruses share one signature trick. After the first infection they hide in nerve cells for life. Then they reactivate with stress, illness, sunlight, or a weak immune system. Herpes simplex virus (HSV) makes painful, grouped, fluid-filled vesicles. HSV-1 causes cold sores around the mouth, and HSV-2 causes genital sores.
Herpes zoster (shingles) is the chickenpox virus waking up. That virus, varicella-zoster, has lain dormant in a sensory nerve root (a dorsal root ganglion) since childhood. When it wakes, it travels down that single nerve. It erupts as a painful blistering rash in a dermatome, the strip of skin one nerve supplies. That is why shingles classically shows up as a stripe on one side of the body. The stripe stops short at the midline. Burning pain often comes before the rash, and the pain can linger for months as postherpetic neuralgia.
| Feature | Herpes simplex | Herpes zoster (shingles) |
|---|---|---|
| Virus | HSV-1 / HSV-2 | Varicella-zoster, woken up |
| Pattern | Grouped blisters, mouth or genitals | One dermatome, one side, stops at the midline |
| Comes back? | Yes, in the same place | Usually once, but the pain can last |
When skin infection turns dangerous: necrotizing fasciitis
Necrotizing fasciitis is sometimes called a "flesh-eating" infection. It is a surgical emergency. Fierce bacteria race along the fascia, the sheet beneath the skin and fat. They release toxins that kill tissue and clot off its blood supply. The telltale clue is pain out of proportion to what you see. The surface may look only mildly red while the patient is in agony. Later signs are fast spread, dusky or purple skin, and blisters. You may feel crepitus, a crackling from gas in the tissue, and the patient looks very sick. Treatment is urgent surgery to cut away dead tissue, plus IV antibiotics. Delay costs limbs and lives. Explore the infection types in the interactive figure below.
- Skin infection starts when the epidermal barrier is breached. Redness, warmth, and swelling are inflammation, not the microbe itself.
- Cellulitis is deep and spreading, so mark the border. Impetigo shows honey-colored crusts. MRSA is resistant staph, often a painful abscess.
- Fungi (tinea, candida) favor warm, moist areas. Candida overgrows after antibiotics and in diabetes.
- HSV and zoster hide in nerves and reactivate. Shingles follows a single dermatome and stops at the midline.
- Necrotizing fasciitis is a surgical emergency. Pain out of proportion to the exam is the warning sign.
Section 6Burns
Your skin is the largest organ you have, and it does a lot of quiet work you never think about. It holds fluid in and keeps germs out. It senses touch and heat, and it helps hold your body heat steady. A burn injures this barrier. Once enough of it is gone, the trouble reaches far beyond the skin itself. That is the single most important idea in burn care. A large burn is a whole-body emergency, not just a wound.
Burn depth: how deep did the injury go?
Skin has layers. The thin outer epidermis sits on top of the thicker dermis, which holds blood vessels, nerve endings, hair follicles, and sweat glands. Below that is fat under the skin, then muscle and bone. How deep a burn reaches sets how it looks, how much it hurts, and whether it can heal on its own.
| Feature | Superficial | Partial-thickness | Full-thickness |
|---|---|---|---|
| Layers involved | Epidermis only | Epidermis plus part of the dermis | All of the epidermis and dermis (may reach fat, muscle, bone) |
| Old name | First-degree | Second-degree | Third-degree |
| Appearance | Red, dry, no blisters | Red, moist, blisters, weeping | White, leathery, waxy, or charred, and dry |
| Pain | Painful | Very painful | Often painless in the deepest spots |
| Healing | Days, no scar | Weeks, may scar | Cannot heal alone, needs grafting |
The pain pattern surprises people. A superficial burn, such as a mild sunburn, hurts because the nerve endings are irritated but still alive. A full-thickness burn can be oddly painless in its center, because the sensory nerves there were destroyed. So a quiet, leathery, white patch is often worse than a screaming red blistered one. A deep full-thickness burn can also form eschar, a tight band of dead tissue that will not stretch. If it squeezes a limb or the chest, a surgeon may need to release it, in a procedure called an escharotomy.
Estimating burn size: the rule of nines
Depth tells you how bad the burn is. Size tells you how big the whole-body threat is. Clinicians estimate the total body surface area (TBSA) burned with the rule of nines. It splits the adult body into parts worth about 9% each, or multiples of 9. The head and neck are 9%. Each arm is 9%. The front of the torso is 18%, and the back is 18%. Each leg is 18%, and the genital area is 1%. For scattered small burns, the patient's own palm is roughly 1% TBSA. Children have larger heads for their size, so pediatric charts differ. TBSA matters because it drives the fluid math and the choice to send the patient to a burn center.
Why a big burn threatens the whole body
Once TBSA climbs past roughly 20-25%, the injury stops being local. Damaged tissue releases inflammatory mediators that make capillaries leaky everywhere. Plasma, protein, and fluid pour out of the bloodstream into the tissues. That causes massive third-spacing and edema. The result is burn shock, a form of hypovolemic shock. Blood volume drops even though total body water has not. Blood pressure falls, and organs are underperfused, so they do not get the blood they need. This is why we work the ABCs.
- Airway first. If someone was burned in a closed space, watch for inhalation injury. Clues include facial burns, singed nose hairs, soot in the mouth, a hoarse voice, and sooty (carbonaceous) sputum. Hot gases and swelling can close the airway fast. So the team often chooses early intubation, placing a breathing tube, before swelling makes it impossible.
- Breathing and circulation. With smoke exposure, suspect carbon monoxide poisoning and give high-flow oxygen. A pulse oximeter can read falsely normal, since it cannot tell oxygen from carbon monoxide.
- Fluid resuscitation. Large burns need aggressive IV fluids, usually lactated Ringer's. A formula such as the Parkland formula sets the starting rate. Then you titrate it, meaning you adjust it, to urine output, often about 0.5 mL/kg/hr in adults. Too little fluid deepens shock, and too much causes dangerous edema.
The delayed threat: infection
The burned skin barrier is gone. The burn wound is a warm surface rich in protein, which bacteria love. After the first day or two, infection and sepsis become the leading cause of death in major burns. That is why burn wounds get careful cleaning, topical antimicrobials (germ-killing creams), and strict aseptic technique. The immune system is also thrown off. Add the huge open surface, and these patients are very easy to infect.
- Depth runs from superficial (red, dry, painful) to partial-thickness (blistered, weeping, very painful) to full-thickness (white and leathery, often painless because the nerves are destroyed).
- The rule of nines estimates TBSA (head 9%, each arm 9%, front torso 18%, back 18%, each leg 18%, genitals 1%, palm about 1%). It drives fluid and transfer choices.
- Large burns cause leaky capillaries and third-spacing, which bring on hypovolemic burn shock even though total body water is unchanged.
- Priorities follow time. Airway first, for inhalation injury. Then fluid resuscitation with lactated Ringer's, titrated to urine output. Then prevention of infection and sepsis.
- A large burn is a whole-body emergency, not just a skin wound.
The chapter in one breath
- Fracture healing runs in order: hematoma, soft callus, hard callus, then remodeling. So pain, swelling, and deformity are the body walling off the break and rebuilding bone over weeks to months.
- Compartment syndrome is the fracture emergency you cannot miss. Pressure rises in a closed muscle compartment. You catch it EARLY by pain out of proportion to the injury and pain with passive stretch, with paresthesia as an early sensory sign. Pulselessness, pallor, paralysis, and poikilothermia (a cool limb) are LATE, grim signs that tissue is already dying. So even though the classic list is the 6 P's (pain, paresthesia, pallor, pulselessness, paralysis, poikilothermia), do not wait for the late P's. A pulse you can feel does not rule it out. It demands a fasciotomy before tissue dies.
- Fat embolism usually follows a long bone or pelvic fracture within 24 to 72 hours. Marrow fat lodges in the lungs and brain, so the classic picture is shortness of breath, confusion, and a petechial rash.
- Osteoporosis is silent low bone density, with bone resorption outpacing bone formation. So the first sign is often a fragility fracture of the hip, wrist, or a vertebra, rather than pain.
- Tell the arthritides apart. Osteoarthritis is wear-and-tear joint pain, often asymmetric (not matched side to side), and worse with use. Rheumatoid arthritis is symmetric autoimmune inflammation with long morning stiffness. Gout is monosodium urate crystals, causing a hot, red, intensely painful great-toe attack (podagra).
- Learn skin cancer by ABCDE (Asymmetry, Border, Color, Diameter >6 mm, Evolving). Melanoma is the deadliest because of early metastasis, meaning it spreads early, unlike the more common but rarely fatal basal and squamous cell carcinomas.
- Cellulitis is a deeper bacterial infection of the dermis and the fat below (often Staph or Strep). It is warm, red, swollen, and tender, with poorly defined borders, and it can turn systemic with fever.
- Estimate how much of the body burned with the rule of nines, and judge depth by tissue. Superficial burns redden and blanch. Partial-thickness burns blister and hurt intensely. Full-thickness burns are leathery, painless, and need grafting.
- For major burns the killer is hypovolemic (burn) shock from a massive capillary fluid leak. So fluid resuscitation (often the Parkland formula) comes first, along with watching the airway for inhalation injury.
ReferenceWords worth knowing
A quick list of the terms in this chapter. Skim it now, or come back any time a word trips you up.
- ABCDE rule
- A quick checklist for odd-looking skin spots. It prompts you to watch for Asymmetry, a ragged Border, uneven Color, a Diameter wider than about 6 mm, and any Evolving change in size, shape, or color over time.
- Callus
- The soft new woven bone and cartilage that forms a bridge around a healing fracture. The body later reshapes it into stronger, mature lamellar bone.
- Cellulitis
- A deeper bacterial skin infection, usually from Staphylococcus or Streptococcus. It spreads through the dermis and the tissue below, bringing warmth, redness, swelling, and tenderness with fuzzy edges.
- Compartment syndrome
- An emergency that can cost a limb. Swelling or bleeding inside a closed muscle compartment raises pressure high enough to cut off blood flow. The classic clue is pain out of proportion to the injury that gets worse with passive stretch.
- Fat embolism
- A complication seen most often after long bone or pelvic fractures. Fat globules from the marrow enter the blood and lodge in the lungs or brain. The usual result is shortness of breath, confusion, and a petechial rash.
- Fracture
- A break in the continuity of a bone. It ranges from a tiny hairline crack to a complete split, and it happens when force is greater than the bone can absorb.
- Gout
- An inflammatory arthritis caused by uric acid crystals settling in a joint, classically the big toe. It brings sudden severe pain, redness, warmth, and swelling.
- Herpes zoster
- Also called shingles. It is a painful blistering rash along a single dermatome, which breaks out when the sleeping varicella-zoster (chickenpox) virus wakes up in a nerve root.
- Melanoma
- The most dangerous skin cancer. It starts in melanocytes, the cells that make pigment, and it can spread (metastasize) early. It is often caught first by using the ABCDE rule on a changing mole.
- Osteoarthritis
- A wear-and-tear joint disease in which cartilage slowly breaks down. Pain and stiffness get worse with use and usually ease with rest.
- Osteoporosis
- Low bone mass with a weakened inner structure. Bones are left porous and fragile, which greatly raises the risk of fractures, above all in the hip, spine, and wrist.
- Partial-thickness burn
- A burn that damages the epidermis and part of the dermis. It usually looks red, moist, and blistered, and it stays painful because the sensory nerve endings are still alive.
- Pressure injury
- Damage to skin and the tissue under it, over a bony prominence, from sustained pressure that cuts off blood flow (ischemia). It often shows up in patients who cannot move, over the sacrum, heels, or hips.
- Psoriasis
- A long-lasting autoimmune skin disease in which skin cells turn over far too fast. They pile up into well-defined red plaques covered by silvery scales, often on the elbows, knees, and scalp.
- Rheumatoid arthritis
- A long-lasting autoimmune disease in which the body attacks the joint lining (synovium). It brings matched pain, swelling, and morning stiffness that usually gets better with movement.
- Rule of nines
- A fast way to estimate what percent of the body surface is burned. It splits the adult body into regions worth about 9% each, or multiples of nine, and it guides fluid resuscitation.
DrillFlashcards for this unit
These are the Week 14 cards. They are the same deck as the hub, pulled in here so you can review as soon as you finish reading. Tap a card to flip it, and hit Shuffle to mix them up. To grade yourself and track what you have mastered across the whole deck, open the full flashcards page.