Psychological Disorders & Therapy
About one in five adults will live with a mental disorder this year. So these conditions are not rare. They are some of the most common things people go through. This chapter starts with a hard question. What makes a thought, a feeling, or an action a disorder, and not just odd or a bit of a pain? Next we tour the main families. First come anxiety, OCD, and trauma. Then come the mood and psychotic disorders. Then we turn to the good news: the treatments that work. You will meet the talk therapies that go back to Freud, Rogers, and Beck. You will also meet the drugs and other body-based treatments that changed care for good. One idea runs under all of it, and it has strong support. Mind and body, thought and brain chemistry, are two views of one system.
By the end of this chapter you can
- Explain the four tests that set a disorder apart from normal ups and downs: dysfunction, distress, deviance, and danger.
- Say what the DSM is, what it does, and where labels fall short.
- Tell the main anxiety disorders, OCD, and PTSD apart. Say why the DSM now puts them in separate chapters.
- Compare major depressive disorder, bipolar disorder, and schizophrenia, and the main ideas about their causes.
- Compare four kinds of talk therapy: psychodynamic, humanistic, behavioral, and cognitive (CBT).
- Sum up the main kinds of psychiatric medication and what each one acts on.
- Explain why the therapeutic alliance, the bond with the therapist, helps in all kinds of therapy.
- Use the biopsychosocial model and the diathesis-stress model to see why disorders start.
Section 1Defining disorders & the DSM

What makes behavior "disordered"
Almost every sign of a mental disorder is something we all feel in small doses. We all feel nervous before a test. We feel low after a loss. Many of us knock on wood. So a feeling by itself does not draw the line between a quirk and an illness. The line comes from a set of judgments about the feeling.
Clinicians often teach these judgments as the four Ds. Dysfunction means it gets in the way of daily life, like work, friends, or taking care of yourself. Distress means it makes the person truly suffer. Deviance means it is far from what the culture expects. Danger means it puts the person or others at risk. No one D is enough by itself. Grief hurts, but it is healthy. A firefighter who runs into a burning house is "deviant," or unusual, but brave. So the Ds are weighed together, and always in context.
The most important D is dysfunction. Jerome Wakefield, a professor of social work and philosophy, put it in two words: harmful dysfunction. This is a way to think through what a disorder is. It is not a lab result. It says two things must both be true. First, some inner system fails at the job it evolved to do. Second, that failure does harm that the person or their society can see. Fear that keeps you away from a snake is doing its job. Fear that keeps you shut in your home for ten years is not. This view keeps us from calling plain difference an illness. Being single, unusual, or not popular is not a disorder, however odd a culture may find it.
The DSM and how diagnosis works
To talk with each other, clinicians need a shared dictionary. In the United States, that book is the Diagnostic and Statistical Manual of Mental Disorders, or DSM. The American Psychiatric Association puts it out. It is now in its fifth edition, text revision (DSM-5-TR, 2022). For each disorder, the DSM gives a checklist. It says how many signs, for how long, and how much harm to daily life. The World Health Organization keeps a matching system called the ICD. It is now in its eleventh edition (ICD-11), and it is used all over the world.
The DSM's great strength is reliability. That means two clinicians who see the same person will likely give the same label. They agree far more often now than they did in the 1970s. Its harder, open problem is validity. Validity asks if the labels match real, separate things in nature. Or do they just name sets of signs that often blur together?
Labels are strong, and that cuts both ways. A label can open the door to care and to insurance. It can bring relief by giving a name to pain. But labels can also stick. David Rosenhan ran a famous study in 1973, On Being Sane in Insane Places. Healthy people faked one sign to get into mental hospitals. They said the label "schizophrenia" then shaped how staff saw all they did. Even taking notes was written up as a sign of illness. Later, though, researchers found big problems in how the study was done and reported. So treat it as a warning story, not as solid proof.
The lesson still holds. A label names a condition a person has. It is not the whole of who they are. That is why careful writers say "a person with schizophrenia," not "a schizophrenic." Comorbidity means having two or more disorders at once. It is very common. That is one more sign that these labels are useful tools, not sharp lines found in nature.
| The four Ds | What it asks | Caution |
|---|---|---|
| Dysfunction | Does it get in the way of work, relationships, or self-care? | The most important criterion; still needs context |
| Distress | Does it cause the person real suffering? | Some states (for example, mania) can feel good to the person |
| Deviance | Does it differ sharply from cultural norms? | Norms vary; being different is not a disorder |
| Danger | Does it put the person or others at risk? | Dramatic but actually uncommon in most disorders; people with mental disorders are more often victims of violence than causes of it |
- The four Ds are dysfunction, distress, deviance, and danger. They are weighed together and in context. Dysfunction counts most.
- A disorder is a harmful dysfunction. Just being different is not a disorder.
- The DSM (now DSM-5-TR) gives clinicians shared rules for each label. The WHO's ICD is the world version.
- The DSM has strong reliability but its validity is still argued. Labels can help and hurt. Rosenhan's study warned of this, though the study itself is now in doubt.
Section 2Anxiety, OCD & trauma
Anxiety disorders
Fear and anxiety are close cousins, but psychologists keep them apart. Fear is the alarm that goes off when a threat is here right now. It is the jolt that gets you out of the road. Anxiety is fear about the future. It is worry about a threat that has not come and may never come. In small amounts, both help us. They become anxiety disorders when they are too big for the threat, last a long time, and get in the way of life. As a group, anxiety disorders are the most common mental disorders of all.
The group has several members. Generalized anxiety disorder is worry about many things that is hard to stop. It shows up most days for at least six months. Panic disorder brings sudden panic attacks. In an attack, the heart races and the chest feels tight. A sense of doom takes over. It feels so physical that many people think they are having a heart attack. Then they dread the next attack.
Some people with panic attacks start to avoid places where it would be hard to get out or get help. That pattern is called agoraphobia. In DSM-5 and DSM-5-TR, it is its own diagnosis, though it often shows up with panic disorder. Specific phobias are strong fears of one thing or one kind of place, such as heights, spiders, or needles. The fear is much bigger than the real danger. Social anxiety disorder is a strong, lasting fear of being judged by others.
Martin Seligman's idea of biological preparedness helps explain which things people fear. Phobias tend to form around snakes, heights, and the dark. Those were real dangers for our distant ancestors. Phobias rarely form around cars or wall plugs, even though those hurt far more people today.
OCD and trauma-related disorders
Older versions of the DSM put OCD and PTSD under "anxiety." DSM-5 moved each one to its own chapter. Both involve anxiety. But each one works in its own way.
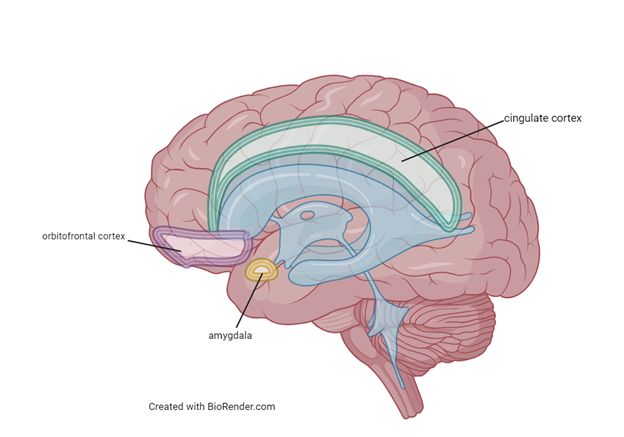
Obsessive-compulsive disorder (OCD) has two parts. Obsessions are unwanted thoughts, pictures, or urges that keep pushing into the mind. They might be fears of germs, of causing harm, or of things not being even. Compulsions are acts done over and over, like washing, checking, or counting. The person feels a strong pull to do them to calm the dread. The act brings a moment of relief. That relief rewards the whole cycle, so it gets tighter over time. Brain scans point to a loop that runs too hot. The loop links the orbitofrontal cortex, the striatum, and the thalamus.
Post-traumatic stress disorder (PTSD) can follow a brush with death, serious injury, or sexual violence. The event may have happened or only been threatened. Combat, assault, and disaster are examples. The signs fall into four groups and last more than a month. Intrusion means flashbacks and bad dreams that replay the event. Avoidance means staying away from reminders. Negative shifts in mood and thinking can mean guilt, numbness, or feeling cut off. Hyperarousal means being jumpy and always on watch for danger.
Here is a key point. Most people who live through trauma do not get PTSD. The diathesis-stress model helps explain who does. A diathesis is a built-in weak spot, from genes or from early life. A disorder starts when that weak spot meets a big enough stress.
| Disorder | DSM-5-TR chapter | Core feature |
|---|---|---|
| Generalized anxiety | Anxiety disorders | Long-lasting, hard-to-control worry about many things |
| Panic disorder | Anxiety disorders | Repeated panic attacks and fear of the next one |
| Specific phobia | Anxiety disorders | Intense fear, out of proportion, of a specific trigger |
| OCD | Obsessive-compulsive & related | Obsessions (unwanted thoughts) + compulsions (rituals) |
| PTSD | Trauma- & stressor-related | Intrusion, avoidance, mood change, and hyperarousal after trauma |
- Fear is about a threat that is here now. Anxiety looks ahead to one in the future. A disorder starts when the response is too big and gets in the way of life.
- Anxiety disorders include generalized anxiety, panic disorder, phobias, and social anxiety. They are the most common group.
- OCD pairs unwanted obsessions with compulsions that bring brief relief. PTSD follows trauma. Its signs are intrusion, avoidance, low mood, and hyperarousal.
- The diathesis-stress model explains why the same trauma harms one person and not another.
Section 3Mood & psychotic disorders
Depression and bipolar disorder
Everyone has bad days. Major depressive disorder is something else. The low mood lasts at least two weeks and will not lift. Or the person has anhedonia, which means they lose the joy they used to get from things. Other signs come too, for at least five in all. They include changes in sleep and hunger, feeling tired, feeling worthless, trouble focusing, and thoughts of death. Major depression is about twice as common in women as in men. It is one of the top causes of disability in the world.
Bipolar disorder adds the other pole. It brings times of mania. A manic episode lasts at least a week. The mood is far too high, or very irritable. Thoughts race. The person may feel grand and powerful, need little sleep, and spend or take risks in reckless ways. Bipolar I needs at least one full manic episode. Most people with bipolar I also have times of depression, but the label does not require them. Bipolar II pairs depression with hypomania, a milder high that lasts at least four days. Bipolar disorder is one of the most heritable mental disorders. That means genes play a big part.
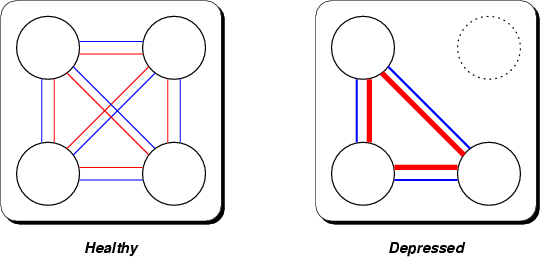
Why do mood disorders happen? No one answer is enough. That is the point of the biopsychosocial model. It looks at the body, the mind, and the social world all at once. On the body side, the classic monoamine hypothesis links depression to low levels of three brain chemicals: serotonin, norepinephrine, and dopamine. But the truth is more complex than "a chemical imbalance."
On the mind side, Aaron Beck described a negative cognitive triad. People with depression tend to hold dark beliefs about three things: themselves, the world, and the future. They read unclear events in ways that seem to prove those beliefs. Martin Seligman's idea of learned helplessness adds to the picture. It is the giving up that follows stress a person cannot control. So does Susan Nolen-Hoeksema's work on rumination, which means going over the same worries again and again. Depression carries a real risk of suicide. Any sign of hopelessness must be taken seriously. In the United States, anyone in crisis, or worried about someone, can call or text 988 at any hour. That reaches the Suicide and Crisis Lifeline.
Schizophrenia
Schizophrenia is a psychotic disorder. Psychosis means a break from the reality other people share. Schizophrenia often starts in the late teens or early twenties. Its positive symptoms are things that are added. They include hallucinations, most often hearing voices. They also include delusions, which are fixed false beliefs that a person keeps even when the facts say no. Mixed-up speech and behavior belong here too. Its negative symptoms are things taken away. They include a flat face and voice (often called flat affect), saying very little, and avolition, a loss of drive to do things.
One old myth needs fixing. Schizophrenia is not "split personality." The name means a split between thought and reality. It does not mean many selves. Having more than one identity is a different condition, called dissociative identity disorder.
Schizophrenia is best seen through the diathesis-stress lens. Genes matter a lot. If one identical twin has it, the other has about a 33 to 50% chance, depending on the study. But genes are not fate. That same number means at least half of these twin pairs are discordant. One twin has it and the other does not.
The dopamine hypothesis came from how drugs act. Drugs that block dopamine ease the positive symptoms. Drugs that boost dopamine, like amphetamines, can bring on psychosis. Some stresses raise the risk in people who are already vulnerable. These include problems before birth, an infection in the mother while pregnant, and heavy cannabis use in the teen years. They can tip a risk in the genes into a real illness.
| Disorder | Hallmark | Leading explanation |
|---|---|---|
| Major depression | ≥2 weeks of low mood or anhedonia, plus other symptoms | Monoamines, negative cognitive triad, learned helplessness |
| Bipolar disorder | Episodes of mania (bipolar I) or hypomania (bipolar II), usually with depression | Strongly genetic; disrupted mood regulation |
| Schizophrenia | Positive (hallucinations, delusions) and negative (flat affect) symptoms | Diathesis-stress; dopamine dysregulation |
- Major depression means at least 2 weeks of low mood or anhedonia, plus other signs. It is twice as common in women.
- Bipolar disorder adds times of mania (or hypomania in bipolar II). Genes play a big part.
- Schizophrenia has positive symptoms (hallucinations, delusions) and negative symptoms (flat affect, avolition). It is not "split personality."
- The biopsychosocial and diathesis-stress models work better than any one-cause story.
Section 4Psychotherapy
Insight therapies: psychodynamic and humanistic
Psychotherapy is treatment through talking, in a planned relationship with a trained helper. There are dozens of kinds. They sort into a few big schools. The oldest is psychodynamic therapy. It grew out of Sigmund Freud's psychoanalysis. Its main idea is that today's problems grow from hidden, unconscious conflicts. These often start in childhood. To heal, in this view, you need insight. That means bringing what is hidden into the light.
Freud had three main tools. In free association, the client says whatever comes to mind, with no filter. In dream analysis, client and therapist look for hidden meaning in dreams. The therapist also watches for transference. That is when the client aims feelings about key people in their life at the therapist. Classic psychoanalysis took years. Modern psychodynamic therapy is shorter and more focused. It keeps the core belief that knowing yourself heals.
The humanistic school, led by Carl Rogers, did not share Freud's dark view of human nature. Rogers's client-centered therapy, also called person-centered therapy, starts from a hopeful idea. People have a built-in drive to grow. A warm bond can set that drive free. The therapist gives three things. Unconditional positive regard means accepting the client with no judgment. Empathy means truly getting what the client feels inside. It often uses active listening, which means saying back what the client said in your own words. Genuineness, also called congruence, means the therapist is real and honest. Abraham Maslow's idea of self-actualization, or growing into your full self, was the school's guiding star. A psychodynamic therapist explains what things mean. A humanistic therapist mostly listens, and trusts the client to find the way.
Action therapies: behavioral and cognitive
Behavioral therapy takes a different view. A problem is a learned habit, so it can be unlearned. There is no need to dig up the past. Joseph Wolpe built on Ivan Pavlov's classical conditioning. He made systematic desensitization. First, the client learns to relax deeply. Then the client climbs a "fear ladder," from mild fears up to the worst one. At each step, the client pairs calm with the thing they fear. Calm takes the place of fear, and a phobia can fade. This is called counterconditioning. Exposure therapy uses the same idea more widely. Other methods use B. F. Skinner's operant conditioning. In token economies, people earn tokens for good habits and trade them for rewards. Over time, the rewards reshape behavior.
The main approach today is cognitive behavioral therapy (CBT). It joins the behavioral school with one big cognitive idea. Our thoughts, not the events, drive how we feel. Aaron Beck's cognitive therapy teaches people to catch their quick, automatic thoughts and test them. Many of these thoughts are thinking errors. One is catastrophizing, which means expecting the worst. Another is all-or-nothing thinking. A third is overgeneralizing, which means one bad event turns into "this always happens."
Albert Ellis's rational emotive behavior therapy (REBT) made the same point with his ABC model. A is the Activating event. C is the emotional Consequence, the feeling. A does not cause C by itself. B, our Beliefs about the event, does. Irrational beliefs bring painful feelings. CBT is short-term and builds skills. It gives homework to do between sessions. It has more proof behind it than any other talk therapy for anxiety and depression.
| Approach | Founder(s) | Core idea | Signature technique |
|---|---|---|---|
| Psychodynamic | Freud | Symptoms grow from unconscious conflict | Free association, dream & transference analysis |
| Humanistic | Rogers, Maslow | People grow when they are accepted and understood | Unconditional positive regard, active listening |
| Behavioral | Wolpe, Skinner | Disorders are learned and can be unlearned | Systematic desensitization, token economy |
| Cognitive (CBT) | Beck, Ellis | Thoughts, not events, drive feelings | Challenging thinking errors; the ABC model |
- Psychodynamic therapy (Freud) seeks insight into hidden conflict. Its tools are free association, dreams, and transference.
- Humanistic therapy (Rogers) heals with unconditional positive regard, empathy, and genuineness.
- Behavioral therapy treats problems as learned habits. It uses systematic desensitization, exposure, and token economies.
- CBT (Beck, Ellis) targets thinking errors. It has the most support of any talk therapy for anxiety and depression.
Section 5Biomedical therapy & the therapeutic relationship
Medications and other biomedical treatments
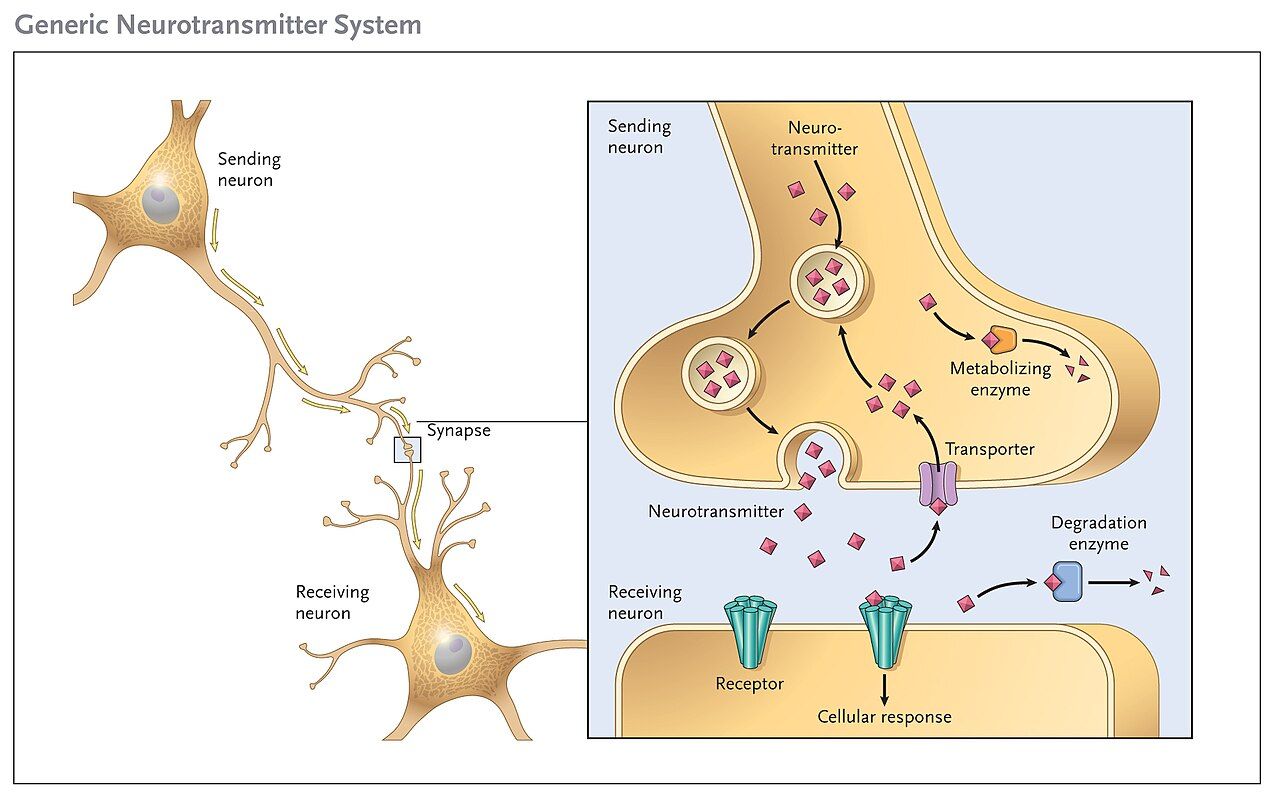
Biomedical therapy treats disorders by acting on the body. Most often it uses psychotropic medication, which means drugs that act on the mind. Almost all of them work at the synapse, the tiny gap between nerve cells. They change how brain chemicals are sent, picked up, or cleared away.
Antidepressants are the biggest group. The SSRIs (selective serotonin reuptake inhibitors) are one kind. Fluoxetine (Prozac) is an example. An SSRI stops nerve cells from soaking serotonin back up, so it stays in the synapse longer. SSRIs treat depression. They also treat most anxiety disorders and OCD. They often take a few weeks to fully work. Anti-anxiety drugs like the benzodiazepines calm the nerves fast. But the body can come to depend on them.
Antipsychotics ease hallucinations and delusions, mostly by blocking dopamine. The first ones, such as chlorpromazine and haloperidol, changed care. But they often caused problems with movement. One lasting problem is called tardive dyskinesia. Newer drugs are called "atypicals." Clozapine and risperidone are examples. They cause fewer movement problems. They cause more weight gain and raise the risk of diabetes. Clozapine helps many people who got no help from other antipsychotics. For bipolar disorder, the mood stabilizer lithium is still a mainstay, many years after it was found. It needs regular blood tests. The gap between a helpful dose and a harmful one is small.
Some severe depression does not get better with drugs or therapy. Other options exist. In electroconvulsive therapy (ECT), a brief current sets off a short seizure in the brain. Today the person is asleep under anesthesia, with drugs to relax the muscles. It is far gentler than its grim name suggests. It works very well for people with the most severe depression. Its most common side effect is some memory loss around the time of treatment. A newer, milder tool is transcranial magnetic stimulation (TMS). It uses magnetic pulses to wake up certain parts of the brain. It needs no seizure and no anesthesia. These tools are strong but blunt. That is why they come at the end of the line, not the front.
The therapeutic relationship
Here is one of the firmest findings in all of clinical psychology. The schools of therapy have very different ideas. Yet their results are far more alike than you would guess. Mary Lee Smith and Gene Glass ran a famous meta-analysis. That is a study that pools the results of many studies. The average person in therapy did better than about 80% of people with no treatment. But no one approach clearly beat the rest. This got the nickname the dodo bird verdict. It comes from a line in Alice in Wonderland: "everyone has won, and all must have prizes." The verdict is still argued. For some problems, some methods do work better. Exposure for phobias and OCD is one example.
So if the method explains less than we thought, what explains the results? A large share comes from the therapeutic alliance. That is the bond of trust, warmth, and shared goals between client and therapist. It is one of the best predictors of getting better in every kind of therapy. So Rogers was right to stress the relationship. That holds even for therapists who reject the rest of his theory.
Two last ideas follow. First, most clinicians are eclectic or integrative. They borrow whatever tool fits the client, instead of sticking to one school. Second, the best evidence often favors combined treatment. Medicine steadies the body while therapy rebuilds thoughts and habits. This is the biopsychosocial model from earlier in the chapter, put to work. Mind and body are not two patients. They are one, and the best care treats them together.
| Drug class | Example | Mainly treats | Acts on |
|---|---|---|---|
| SSRI antidepressant | Fluoxetine (Prozac) | Depression, anxiety, OCD | Serotonin reuptake |
| Anti-anxiety | Benzodiazepines | Short-term anxiety | GABA (calms neural firing) |
| Antipsychotic | Haloperidol; clozapine | Schizophrenia, psychosis | Dopamine (mainly) |
| Mood stabilizer | Lithium | Bipolar disorder | Several systems; steadies mood swings |
- Biomedical therapy acts on the body. Most psychotropic drugs work at the synapse.
- SSRIs treat depression, anxiety, and OCD. Antipsychotics block dopamine. Lithium steadies bipolar disorder.
- ECT and TMS can help severe depression that other care has not helped.
- The therapeutic alliance predicts results in all kinds of therapy. Combined and eclectic care often works best.
The chapter in one breath
- A behavior counts as a disorder when the four Ds are weighed together. They are dysfunction, distress, deviance, and danger. Dysfunction comes first.
- The DSM gives clinicians shared, reliable rules for each label. But labels have limits, and comorbidity is common.
- Anxiety disorders (generalized, panic, phobias, social) are the most common. OCD and PTSD now have their own DSM chapters.
- Major depression and bipolar disorder are mood disorders. Schizophrenia is a psychotic disorder with positive and negative symptoms. It is not "split personality."
- The diathesis-stress and biopsychosocial models say a disorder starts when a weak spot meets stress. Body, mind, and the world around us all play a part.
- Talk therapies come in four main kinds: psychodynamic (Freud), humanistic (Rogers), behavioral (Wolpe, Skinner), and cognitive/CBT (Beck, Ellis).
- Biomedical therapy works on the brain. It includes SSRIs, antipsychotics, lithium, and ECT. The therapeutic alliance predicts success in every kind of therapy.
- The best results often come from combined, eclectic care that treats mind and body as one.
ReferenceWords worth knowing
Here are the key terms from this chapter. Skim them now, or come back whenever a word trips you up.
- Anhedonia
- The loss of interest or pleasure in things a person used to enjoy. It is a core symptom of major depression.
- Antipsychotic
- A medication that reduces hallucinations and delusions, mainly by blocking dopamine.
- Bipolar disorder
- A mood disorder with episodes of mania (bipolar I) or hypomania (bipolar II), usually along with episodes of depression.
- Cognitive behavioral therapy (CBT)
- An action therapy that joins behavioral methods with fixing distorted thinking. It is the best-supported talk therapy for anxiety and depression.
- Comorbidity
- Having two or more disorders at the same time.
- Compulsion
- A repeated behavior or mental act that a person feels driven to do to ease the anxiety from an obsession.
- Delusion
- A fixed false belief held despite clear evidence against it. It is a positive symptom of schizophrenia.
- Diathesis-stress model
- The idea that a disorder develops when a built-in vulnerability (the diathesis) meets enough stress.
- DSM
- The Diagnostic and Statistical Manual of Mental Disorders, the standard U.S. system for classifying disorders. The current version is DSM-5-TR.
- Hallucination
- A sensory experience with nothing outside causing it, such as hearing voices. It is a positive symptom of schizophrenia.
- Humanistic therapy
- An insight therapy (Rogers) that helps people grow through unconditional positive regard, empathy, and genuineness.
- Major depressive disorder
- At least two weeks of low mood or anhedonia, plus other symptoms, that get in the way of daily life.
- Mania
- A period of unusually high or irritable mood, lasting at least a week, with racing thoughts, a grand sense of self, and less need for sleep.
- Obsession
- An unwanted thought, image, or urge that keeps coming back and causes strong distress.
- Obsessive-compulsive disorder (OCD)
- A disorder that pairs obsessions with the compulsions done to relieve them.
- Post-traumatic stress disorder (PTSD)
- A trauma-related disorder marked by intrusion, avoidance, negative changes in mood and thinking, and hyperarousal after a traumatic event.
- Psychoanalysis
- Freud's psychodynamic therapy. It seeks insight into unconscious conflict through free association, dream analysis, and transference.
- Schizophrenia
- A psychotic disorder with positive symptoms (hallucinations, delusions) and negative symptoms (flat affect, avolition).
- SSRI
- A selective serotonin reuptake inhibitor, such as fluoxetine. It raises serotonin in the synapse to treat depression, anxiety, and OCD.
- Systematic desensitization
- A behavioral method that pairs relaxation with a step-by-step fear hierarchy to unlearn a phobia.
- Therapeutic alliance
- The bond of trust and shared goals between client and therapist. It strongly predicts results in all therapies.
- Unconditional positive regard
- Rogers's stance of accepting and valuing a client without judgment, no matter what they say or do.