Cardiac Disorders: Dysrhythmias, Valves and Vascular Disease
Chapter 8 gave you the pump and its fuel supply. This chapter gives you the wiring, the doors and the plumbing. A dysrhythmia is an electrical problem that becomes a mechanical problem the instant it steals filling time or the atrial kick; a valve lesion is a mechanical problem that becomes an electrical problem the instant a stretched atrium fibrillates; and vascular disease is what happens when the conduit itself narrows, clots, dilates or tears. On a busy medical–surgical floor these three live together in the same patient: the eighty-two-year-old with aortic stenosis, new atrial fibrillation, a heparin drip and a cool, pulseless foot. Your job is not to memorise every strip in the book. It is to recognise the handful of rhythms that kill, to know whether the patient in front of you is stable or unstable, and to know which intervention comes first. Everything else in this chapter hangs off that skeleton.
By the end of this chapter you can
- Trace an impulse through the conduction system and relate each ECG waveform and interval to the mechanical event it produces, using normal values for the PR interval, QRS duration and QTc.
- Analyse a rhythm strip with a repeatable six-step method and identify sinus, atrial, junctional and ventricular rhythms plus the degrees of atrioventricular block.
- Distinguish a stable from an unstable patient and select the correct first intervention — vagal manoeuvre, drug, synchronised cardioversion, defibrillation or transcutaneous pacing.
- Apply the CHA2DS2-VASc score to atrial fibrillation, compare warfarin with the direct oral anticoagulants, and describe the anticoagulation rules that govern cardioversion.
- Explain the haemodynamics of aortic stenosis, mitral stenosis, and aortic and mitral regurgitation, and match each to its murmur, its assessment findings and its nursing cautions.
- Recognise infective endocarditis, obtain cultures in the correct sequence, and teach prophylaxis to a patient with a prosthetic valve.
- Differentiate peripheral arterial disease from chronic venous insufficiency by ulcer, pulse, positioning and ankle–brachial index, and identify the six P’s of acute limb ischaemia.
- Manage venous thromboembolism safely, including heparin and low-molecular-weight heparin monitoring, reversal agents and recognition of heparin-induced thrombocytopenia.
- Identify aortic aneurysm, aortic dissection and hypertensive emergency as time-critical events, and report each using SBAR.
Section 1Reading the Rhythm: Conduction, the Six-Step Strip and the Sinus Rhythms
The conduction system and what each waveform means
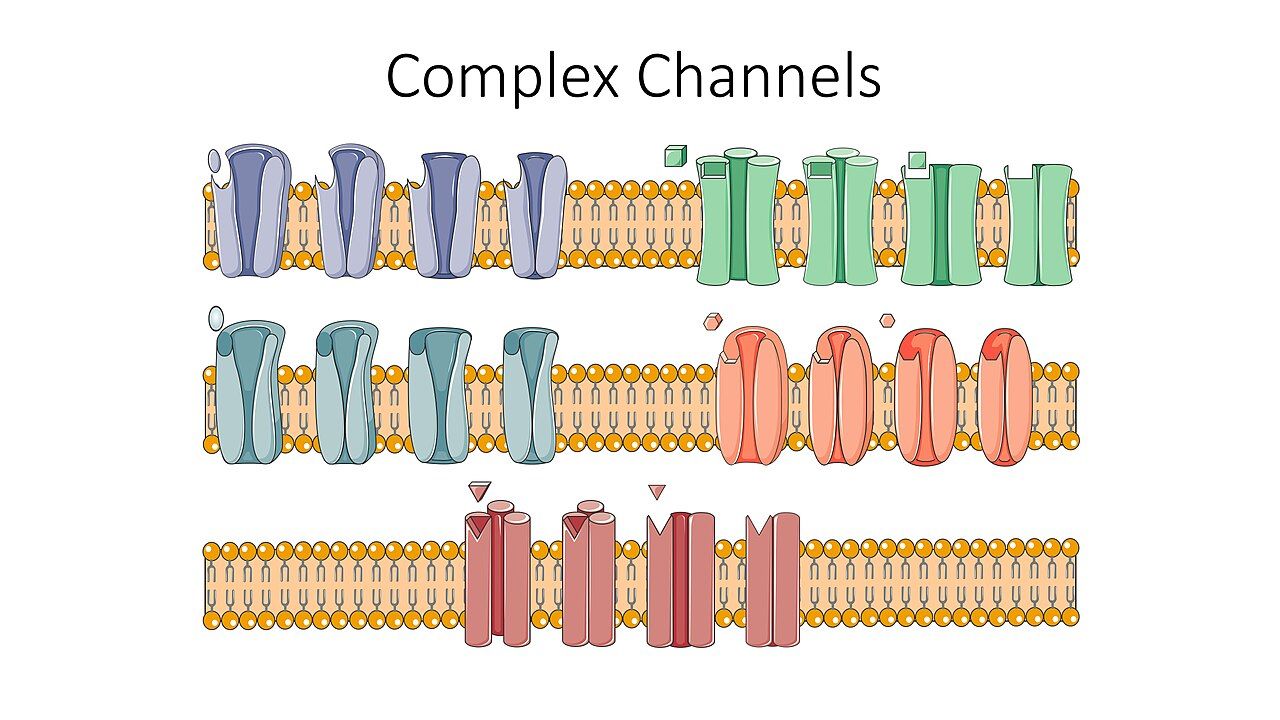
Cardiac muscle is unusual because it generates its own signal. Specialised pacemaker cells depolarise spontaneously, and the fastest one in the heart sets the pace. Normally that is the sinoatrial (SA) node in the high right atrium, firing at 60 to 100 times a minute. The impulse spreads across both atria, producing the P wave and the atrial contraction that tops off ventricular filling — the atrial kick, worth roughly 20 to 30 per cent of cardiac output in a healthy adult and considerably more in a stiff, hypertrophied or ischaemic ventricle. The signal then reaches the atrioventricular (AV) node, which deliberately delays it by about a tenth of a second so the atria can finish emptying before the ventricles squeeze. That delay is the flat part of the PR interval.
From the AV node the impulse races down the bundle of His, splits into right and left bundle branches and fans out through the Purkinje fibres, depolarising both ventricles almost simultaneously. That is the QRS complex, and it is narrow — 0.06 to 0.10 seconds — precisely because the specialised conduction tissue is fast. A wide QRS tells you the impulse took the slow route, muscle cell to muscle cell, which means it either started in the ventricle or met a blocked bundle branch on the way down. The ST segment is the quiet interval after the whole ventricle has depolarised and before repolarisation begins, and it should sit on the isoelectric line; the T wave is ventricular repolarisation, the electrical reset. Atrial repolarisation happens too, but it is buried inside the QRS and you never see it.
The system has redundancy. If the SA node fails, the AV junction takes over at 40 to 60 beats a minute, producing a narrow QRS with an absent, inverted or retrograde P wave — a junctional escape rhythm. If the junction fails too, the ventricle itself will fire at 20 to 40 beats a minute with a wide, bizarre QRS — an idioventricular rhythm. Escape rhythms are the heart’s last-resort generators. They are slow, they are unreliable, and they are never something to suppress with an antiarrhythmic; if you abolish the escape you are left with asystole.
Finally, remember that electricity is not perfusion. A monitor can show a textbook rhythm while the patient has no pulse at all — that is pulseless electrical activity. The first response to any alarming rhythm is always the same: look at your patient, touch your patient, check a central pulse and a blood pressure. Treat the person, not the screen.
| Feature | Normal value | What an abnormality suggests |
|---|---|---|
| Small box / large box | 0.04 s / 0.20 s | Five small boxes make one large box; thirty large boxes make six seconds |
| Rate (adult) | 60–100 beats/min | <60 bradycardia, >100 tachycardia; count QRS complexes in a 6-second strip and multiply by 10 |
| P wave | Upright, rounded, one per QRS | Absent or chaotic in atrial fibrillation; sawtooth in flutter; inverted in junctional rhythm |
| PR interval | 0.12–0.20 s | Prolonged in first-degree AV block; shortened with pre-excitation; variable in complete block |
| QRS duration | 0.06–0.10 s (up to 0.12 s) | Wide means ventricular origin, bundle branch block, paced beat or hyperkalaemia |
| QT / QTc | QTc <0.44 s men, <0.46 s women | QTc >0.50 s carries a high risk of torsades de pointes; hold the offending drug and call |
| ST segment | Isoelectric | Elevation suggests injury, depression suggests ischaemia or digoxin effect |
A systematic six-step strip analysis
Students who guess at strips get them wrong; students who follow the same six steps every single time get them right. Step one: rate. Count the QRS complexes in a six-second strip and multiply by ten, or for a regular rhythm divide 300 by the number of large boxes between two R waves. Step two: rhythm. March out the R-to-R intervals with calipers or the edge of a piece of paper. Are they regular, regularly irregular (a repeating pattern, as in Wenckebach) or irregularly irregular (no pattern at all, the signature of atrial fibrillation)? Step three: P waves. Is there one, is it upright, and does it look like every other P wave on the strip?
Step four: P-to-QRS relationship. Is there exactly one P for every QRS? More P waves than QRS complexes means beats are being dropped — a block. Step five: PR interval. Measure it and, just as importantly, ask whether it is constant. A PR that lengthens progressively before a dropped beat is Mobitz I; a PR that stays fixed and then drops a beat without warning is Mobitz II; a PR that varies randomly with no relationship at all is third-degree block. Step six: QRS duration. Narrow or wide? Narrow tells you the impulse came from above the ventricles, and that is reassuring even when the rate is fast. Wide and fast, in an adult with cardiac disease, is ventricular tachycardia until proven otherwise.
Two habits will save you. First, always run and mount a strip when the rhythm changes, label it with the date, time and the patient’s symptoms, and compare it to the previous one; a rhythm change with no symptoms is a different problem from a rhythm change with chest pain and a systolic of 78. Second, when telemetry alarms, verify at the bedside before you act. Loose electrodes, a patient brushing their teeth, and a shivering patient all produce artefact that looks alarming. Artefact has one giveaway: you can usually march the underlying QRS complexes straight through the noise.
Sinus rhythms, sinus arrest and the bradycardia response
Sinus bradycardia is a normal-looking strip at a rate below 60. In a conditioned athlete or a sleeping adult it is normal. It becomes a problem when it produces symptoms: dizziness, syncope, fatigue, hypotension, confusion, chest pain or heart failure. Common causes are vagal stimulation (suctioning, vomiting, straining at stool, carotid pressure), inferior wall myocardial infarction, hypothyroidism, raised intracranial pressure, hypothermia and drugs — beta blockers, non-dihydropyridine calcium channel blockers, digoxin, amiodarone and cholinesterase inhibitors. Always look at the medication administration record before you conclude the node is diseased.
For symptomatic bradycardia the sequence is: assess airway, breathing and circulation, give oxygen if the patient is hypoxaemic, obtain intravenous access, apply the monitor and get a twelve-lead. Atropine 1 mg intravenous push is the first drug, repeated every three to five minutes to a maximum total of 3 mg. If atropine fails, move to transcutaneous pacing or a chronotropic infusion — dopamine 5 to 20 micrograms per kilogram per minute or epinephrine 2 to 10 micrograms per minute. Two cautions matter: atropine is unlikely to work and should not delay pacing when the block is below the AV node (Mobitz II or third-degree block with a wide QRS), and transcutaneous pacing hurts, so the conscious patient needs analgesia and sedation while you confirm both electrical capture on the monitor and mechanical capture by palpating a pulse.
Sinus tachycardia is almost never the primary problem. It is a symptom. Fever, pain, anxiety, hypovolaemia, hypoxaemia, anaemia, sepsis, hyperthyroidism, alcohol withdrawal, caffeine, nicotine and stimulants all drive it, and so do beta agonists such as albuterol. Treat the cause, not the number. Slowing a compensatory tachycardia in a hypovolaemic patient removes the only thing keeping their cardiac output up. Sick sinus syndrome, common in older adults, is a diseased node that alternates between inappropriate bradycardia and bursts of atrial tachycardia — the tachy–brady syndrome — and it is a leading reason for permanent pacemaker implantation after age 70.
Electrolytes, drugs and the vulnerable QT interval
A remarkable number of dysrhythmias on a medical–surgical floor are metabolic, not cardiac, and they are the ones you can actually fix. Potassium 3.5 to 5.0 mEq/L is the number to watch. Hypokalaemia flattens the T wave, produces a U wave, provokes premature ventricular contractions and sets the stage for torsades de pointes; it is common in patients on loop diuretics, which is to say most patients with heart failure. Hyperkalaemia peaks the T waves, then widens the QRS, then flattens the P wave and finally produces a sine wave and arrest. Magnesium 1.3 to 2.1 mEq/L travels with potassium: you cannot correct a stubborn hypokalaemia until the magnesium is replaced. Two replacement rules are absolute. Potassium is never given by intravenous push or bolus — it is always diluted and infused on a pump, conventionally no faster than 10 mEq per hour on a general floor and only faster in a monitored setting through a central line, because a bolus stops the heart. And never add potassium to a hanging bag; use the premixed one. Ionised calcium 4.5 to 5.6 mg/dL shortens or lengthens the QT interval when it is high or low respectively.
The QT interval deserves its own paragraph because prolonging it is the most common way a well-meaning drug order kills a patient. Corrected QT above 500 milliseconds is the threshold at which most institutions require notification. The offenders you will actually hang are amiodarone, sotalol, procainamide, ibutilide, haloperidol, ondansetron, methadone, fluoroquinolones such as levofloxacin, macrolides such as azithromycin, and many antipsychotics and antidepressants. Two or three of these together, in a patient who is also hypokalaemic and hypomagnesaemic, is a recipe for polymorphic ventricular tachycardia. Before giving a QT-prolonging drug, look at the most recent QTc and the most recent potassium and magnesium. That is a nursing intervention, not a pharmacy one.
Finally, digoxin. Therapeutic serum level is 0.5 to 2.0 ng/mL, and in heart failure most clinicians now target 0.5 to 0.9 ng/mL. Hold the dose and notify the provider if the apical pulse is below 60 in an adult. Early toxicity is deceptively vague — anorexia, nausea, vomiting, fatigue, confusion — and the classic yellow-green or halo visual disturbance comes late. Any new dysrhythmia in a patient on digoxin should be treated as toxicity until the level and the potassium return, because hypokalaemia dramatically potentiates digoxin binding. The antidote is digoxin immune Fab.
Analyse every strip the same six ways and answer the stability question first, because the rhythm name matters far less than whether the rhythm is producing hypotension, altered mentation, ischaemic pain or acute heart failure.
Section 2Atrial Fibrillation, Flutter and the Supraventricular Tachycardias
Why atrial fibrillation matters: the lost kick and the quiet appendage
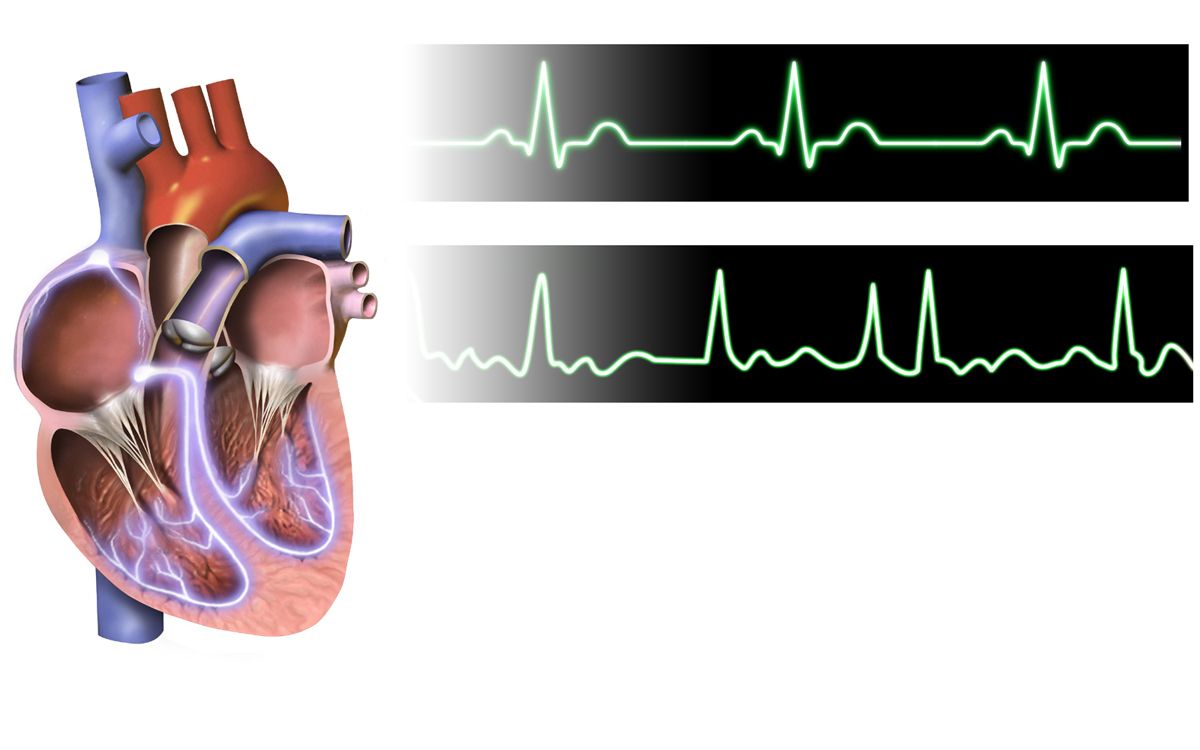
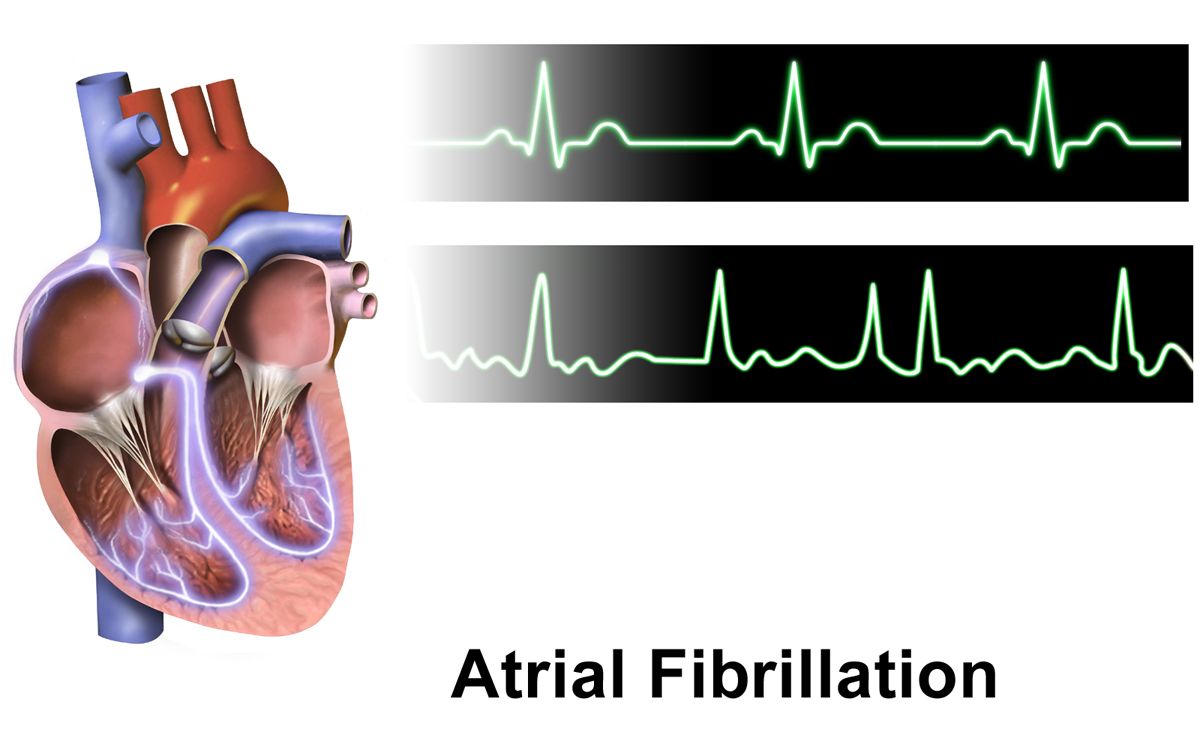
In atrial fibrillation the atria stop contracting and instead quiver at 350 to 600 impulses a minute. The AV node acts as a gatekeeper, letting through an unpredictable subset of those impulses, which is why the ventricular response is irregularly irregular — the single most reliable bedside finding. On the strip there are no organised P waves, only a wavy or flat fibrillatory baseline, and the QRS complexes are narrow unless there is a coexisting bundle branch block.
Two consequences follow, and every intervention in atrial fibrillation aims at one of them. First, the atrial kick is lost. In a young healthy heart that costs perhaps 20 per cent of cardiac output; in an older patient with a stiff, hypertrophied ventricle or aortic stenosis it can cost 30 to 40 per cent, and the drop is felt immediately as fatigue, dyspnoea, hypotension or frank pulmonary oedema. A rapid ventricular response makes it worse by shortening diastole, which is both the filling time for the ventricle and the perfusion time for the coronary arteries. This is why new-onset atrial fibrillation with a rate of 150 can precipitate angina in a patient whose coronary disease was previously silent.
Second, blood stagnates. The left atrial appendage is a blind pouch that, without coordinated contraction, becomes a thrombus factory. A clot that forms there and embolises travels to the brain, and this is why atrial fibrillation raises stroke risk roughly fivefold and why cardioembolic strokes tend to be large and disabling. Understanding this one anatomical fact makes the entire anticoagulation discussion make sense. It also explains the pulse deficit you may find: because many ventricular beats are too weak to open the aortic valve, the apical rate counted at the chest can exceed the radial rate counted at the wrist. Always take an apical pulse for a full minute in atrial fibrillation, and never rely on the automated blood pressure cuff’s heart rate.
Atrial fibrillation is provoked by hypertension, heart failure, valvular disease (especially mitral stenosis), coronary disease, hyperthyroidism, obstructive sleep apnoea, obesity, alcohol, sepsis, pulmonary embolism, electrolyte derangement and cardiac or thoracic surgery. Postoperative atrial fibrillation after cardiac surgery is so common — roughly a third of patients — that it is anticipated rather than surprising. Screening a new case means a twelve-lead ECG, an echocardiogram, thyroid studies, electrolytes including magnesium, a complete blood count and renal function.
Rate, rhythm and the cardioversion clock
For the unstable patient — hypotensive, ischaemic, confused, in pulmonary oedema because of the rhythm — the answer is immediate synchronised cardioversion, typically 120 to 200 joules biphasic, with sedation if time allows. For everyone else, the first goal is rate control, usually a target resting ventricular rate under about 110 in an asymptomatic patient or under 80 if symptoms persist. The workhorse agents are intravenous beta blockers (metoprolol 5 mg slow push, may repeat) and the non-dihydropyridine calcium channel blocker diltiazem (0.25 mg/kg over two minutes, then an infusion). Both drop blood pressure and slow conduction, so take an apical pulse and a blood pressure immediately before and after every dose; the usual hold parameters are a heart rate below 60 or a systolic pressure below 100, and if the order does not specify them, get them clarified before the first dose. Avoid diltiazem in a patient with reduced ejection fraction because of its negative inotropy. Digoxin is a second-line choice reserved for patients with heart failure or hypotension; it controls the rate at rest but poorly with activity. Amiodarone both slows the rate and may chemically convert the rhythm, which is exactly why it cannot be given casually.
That brings us to the rule students most often miss. If atrial fibrillation has lasted more than 48 hours, or the duration is unknown, the patient must not be converted — electrically or chemically — until either three weeks of therapeutic anticoagulation has been completed or a transoesophageal echocardiogram has excluded a left atrial thrombus. Converting a fibrillating atrium restores coordinated contraction and can fire an existing clot straight into the cerebral circulation. After any conversion, anticoagulation continues for at least four weeks, because the atrium is mechanically stunned and remains thrombogenic even though the rhythm on the monitor looks normal.
Atrial flutter is the organised cousin: a single re-entrant circuit, usually around the tricuspid annulus, producing a sawtooth flutter-wave baseline at an atrial rate of 250 to 350. When conduction is a fixed 2:1 you get a very regular ventricular rate near 150, which is the classic trap — a regular narrow tachycardia at exactly 150 should make you look hard for hidden flutter waves. Flutter carries the same embolic risk as fibrillation and the same anticoagulation rules, converts at lower energy (50 to 100 joules), and is often curable by catheter ablation of the cavotricuspid isthmus. Left atrial appendage occlusion devices offer an alternative for patients who cannot tolerate long-term anticoagulation.
Anticoagulation: scoring the risk and giving the drug safely
Stroke prevention is decided by the CHA2DS2-VASc score, not by whether the rhythm is paroxysmal, persistent or permanent. In general, a score of 2 or more in men and 3 or more in women warrants long-term oral anticoagulation. Bleeding risk is estimated separately (HAS-BLED and similar tools), but a high bleeding score is a prompt to correct modifiable risks — uncontrolled hypertension, alcohol, concurrent non-steroidal anti-inflammatory drugs — not an automatic reason to withhold anticoagulation. Aspirin alone is not adequate stroke prophylaxis in atrial fibrillation.
| Letter | Risk factor | Points |
|---|---|---|
| C | Congestive heart failure or left ventricular dysfunction | 1 |
| H | Hypertension | 1 |
| A2 | Age 75 years or older | 2 |
| D | Diabetes mellitus | 1 |
| S2 | Prior stroke, transient ischaemic attack or thromboembolism | 2 |
| V | Vascular disease (prior myocardial infarction, peripheral arterial disease, aortic plaque) | 1 |
| A | Age 65 to 74 years | 1 |
| Sc | Sex category female | 1 |
The direct oral anticoagulants — apixaban, rivaroxaban, edoxaban (factor Xa inhibitors) and dabigatran (a direct thrombin inhibitor) — are now first-line for non-valvular atrial fibrillation. They require no routine coagulation monitoring and have few food interactions, but they must be dose-adjusted for renal function and age, they have short half-lives so a single missed dose genuinely matters, and they are contraindicated in patients with mechanical heart valves or moderate-to-severe mitral stenosis, who still require warfarin. Warfarin is monitored by the international normalised ratio, target 2.0 to 3.0 in atrial fibrillation. Its antidote is vitamin K (with prothrombin complex concentrate for serious bleeding); idarucizumab reverses dabigatran and andexanet alfa reverses apixaban and rivaroxaban.
Teaching is where the nursing happens. Patients on warfarin need a consistent intake of vitamin K–rich foods rather than avoidance of them, no new over-the-counter medicine or herbal product without checking (ginkgo, ginseng, garlic, vitamin E and St John’s wort all interact), an electric razor and a soft toothbrush, and a medical alert identification. Every anticoagulated patient must be taught the bleeding report list: black or tarry stools, blood in urine or vomit, coughing blood, a nosebleed that will not stop after ten minutes of pressure, unusual bruising, and — the one they forget — a fall or any blow to the head, which requires evaluation even when they feel fine because of the risk of a delayed intracranial bleed.
Paroxysmal supraventricular tachycardia, vagal manoeuvres and adenosine
Paroxysmal supraventricular tachycardia is a re-entrant circuit, usually within or near the AV node, producing an abrupt-onset, abrupt-offset, perfectly regular narrow-complex tachycardia at 150 to 250 beats a minute. P waves are typically buried in the preceding T wave. Patients describe a sudden pounding in the chest or neck, lightheadedness, dyspnoea and anxiety; young, otherwise healthy people tolerate it for hours, while an older patient with coronary disease may become ischaemic within minutes.
For the stable patient, start with vagal manoeuvres: ask the patient to bear down as if having a bowel movement (Valsalva) for 10 to 15 seconds, or apply a cold stimulus to the face. Carotid sinus massage is a provider manoeuvre and is avoided in older adults and anyone with carotid bruits because of stroke risk. Have the monitor running and a strip recording; the transient AV block a vagal manoeuvre produces is diagnostic even when it does not convert the rhythm, because it unmasks flutter waves or fibrillation.
If vagal manoeuvres fail, the drug is adenosine 6 mg by rapid intravenous push over one to two seconds, immediately followed by a 20 mL normal saline flush with the arm elevated, using the port closest to the patient and preferably an antecubital or larger vein. If there is no conversion in one to two minutes, give 12 mg the same way. Adenosine has a half-life under 10 seconds, so a slow push simply does not work. Warn the patient in advance: they will feel flushing, chest pressure and a sense of impending doom, and the monitor will show a few seconds of asystole or bradycardia before sinus rhythm resumes. Adenosine is used cautiously or avoided in asthma because it can provoke bronchospasm, and its effect is blunted by caffeine and theophylline. If the patient is unstable at any point, skip all of this and go to synchronised cardioversion at 50 to 100 joules. Definitive long-term therapy for recurrent supraventricular tachycardia is catheter ablation, which is curative in the great majority of patients.
In atrial fibrillation the rate steals output and the stagnant atrium makes clot, so every intervention is either rate control, rhythm control or anticoagulation — and no one is converted after 48 hours of fibrillation without three weeks of anticoagulation or a clot-free transoesophageal echocardiogram.
Section 3Ventricular Dysrhythmias, Heart Block and Electrical Therapy
From premature ventricular contractions to ventricular tachycardia
A premature ventricular contraction is an early, wide, bizarre QRS with no preceding P wave, usually followed by a full compensatory pause. Because it fires before the ventricle has filled, it produces little or no stroke volume, which is why a patient with frequent premature ventricular contractions may have a pulse deficit and feel a “skipped beat” or a thud. Occasional premature ventricular contractions are common and benign in a structurally normal heart. They become concerning when they are frequent (more than about six a minute), multifocal (differently shaped, meaning multiple irritable sites), coupled (pairs), run in threes or more, or fall on the T wave of the preceding beat — the R-on-T phenomenon, which can trigger ventricular fibrillation because it lands in the vulnerable period of repolarisation.
The nursing response to new or increasing premature ventricular contractions is not a drug. It is a search for the cause: check oxygenation, check the potassium and magnesium, check for ischaemia with a twelve-lead, review the drug list for QT prolongers and stimulants, check for caffeine and nicotine, and look at any central line or pulmonary artery catheter, because a catheter tip irritating the right ventricle is a classic and immediately reversible cause. Assess whether the patient is symptomatic and whether they are perfusing.
Three or more consecutive ventricular beats is ventricular tachycardia — a run if it is brief and self-limiting, sustained if it lasts more than 30 seconds or causes haemodynamic collapse. Monomorphic ventricular tachycardia is regular and wide at 100 to 250 beats a minute with all complexes the same shape, and it usually arises from scar tissue after a myocardial infarction. A wide-complex tachycardia in an adult with known heart disease should be treated as ventricular tachycardia until proven otherwise; the mistake of calling it supraventricular tachycardia with aberrancy and giving a calcium channel blocker can be fatal. Assess for a pulse immediately, because the treatment path forks entirely on that finding. Stable ventricular tachycardia with a pulse is treated with intravenous amiodarone 150 mg over 10 minutes (alternatives include procainamide and sotalol); unstable monomorphic ventricular tachycardia with a pulse gets synchronised cardioversion; pulseless ventricular tachycardia is a cardiac arrest.
Torsades de pointes is polymorphic ventricular tachycardia in the setting of a prolonged QT interval, and it looks like the QRS complexes are twisting around the baseline. It is its own diagnosis because it has its own treatment: magnesium sulfate 1 to 2 g intravenously, plus removal of every QT-prolonging drug and correction of potassium and magnesium. It frequently self-terminates and just as frequently degenerates into ventricular fibrillation, so the patient stays on the monitor with the defibrillator at the bedside. Know in advance what to do if it does not self-terminate: because the QRS complexes are constantly changing shape, there is no consistent R wave for the machine to synchronise to, and pressing sync on unstable torsades commonly ends with the defibrillator refusing to discharge while the patient deteriorates. Unstable or pulseless polymorphic ventricular tachycardia is therefore treated as ventricular fibrillation — an immediate high-energy unsynchronised shock — while the magnesium, the drug review and the electrolyte correction continue.
The code: defibrillation, synchronised cardioversion and what not to shock
Ventricular fibrillation is chaotic, disorganised depolarisation with no coordinated contraction and therefore no cardiac output. The patient is pulseless, apnoeic and unresponsive within seconds. Along with pulseless ventricular tachycardia it is one of the two shockable rhythms, and survival falls by roughly 7 to 10 per cent for every minute that defibrillation is delayed. The response is to confirm unresponsiveness and pulselessness, call for help and the defibrillator, and begin high-quality compressions at 100 to 120 per minute, 2 to 2.4 inches deep, allowing full recoil and minimising interruptions, at a 30:2 ratio until an advanced airway is placed.
Defibrillation is unsynchronised: it delivers energy the instant the button is pressed, because in ventricular fibrillation there is no R wave to synchronise to. Use 120 to 200 joules biphasic per the manufacturer, or 360 joules monophasic. Resume compressions immediately after the shock without pausing to check a rhythm. Give epinephrine 1 mg intravenously or intraosseously every three to five minutes and, after the second or third shock, amiodarone 300 mg followed by 150 mg, or lidocaine 1 to 1.5 mg/kg. Throughout, work the reversible causes — hypovolaemia, hypoxia, hydrogen ion (acidosis), hypo- and hyperkalaemia, hypothermia, tension pneumothorax, tamponade, toxins, and thrombosis of the coronary or pulmonary circulation.
Synchronised cardioversion is different and the difference is examinable. The machine times the shock to the R wave so that it does not land on the T wave and induce ventricular fibrillation. It is used for unstable rhythms that still have a pulse: atrial fibrillation at 120 to 200 joules, atrial flutter and supraventricular tachycardia at 50 to 100 joules, and monomorphic ventricular tachycardia with a pulse at 100 joules. Every one of those rhythms is organised enough to give the machine an R wave; polymorphic ventricular tachycardia is not, so an unstable or pulseless polymorphic rhythm is defibrillated rather than cardioverted. Sedate the conscious patient. Press and hold the discharge buttons, because the machine waits for the next R wave. If the rhythm degenerates to ventricular fibrillation, turn the sync function off and defibrillate. Safety is the nurse’s job for both procedures: ensure everyone is clear including yourself, remove supplemental oxygen from the immediate area, verify no one is touching the bed, and never place a pad directly over an implanted device.
The two non-shockable rhythms are asystole and pulseless electrical activity. Shocking them does nothing and delays what does work: compressions, epinephrine and an aggressive hunt for the reversible cause. Asystole should be confirmed in a second lead and the leads and gain checked, because a disconnected electrode produces a flat line on a living patient.
The atrioventricular blocks and when atropine is the wrong drug
| Block | Strip signature | Significance and management |
|---|---|---|
| First degree | PR interval >0.20 s, constant, every P conducts | Usually benign; monitor, review AV nodal blocking drugs, no treatment if asymptomatic |
| Second degree, Mobitz I (Wenckebach) | PR lengthens progressively until a QRS is dropped, then the cycle repeats | Block is at the AV node; often transient (inferior myocardial infarction, digoxin, beta blockers); treat only if symptomatic — atropine works |
| Second degree, Mobitz II | PR constant, then a P wave suddenly conducts nothing; QRS often wide | Block is below the AV node and is unstable; expect progression to complete block; atropine usually ineffective; prepare for transcutaneous then permanent pacing |
| Third degree (complete) | P waves and QRS complexes entirely independent; atrial rate faster and regular, ventricular escape 20–60 and regular | Atrioventricular dissociation; hold AV nodal blockers, transcutaneous pacing and a chronotropic infusion, permanent pacemaker |
The two things students confuse are Mobitz I versus Mobitz II, and when atropine helps. Mobitz I lengthens the PR before it drops a beat; Mobitz II drops without warning. The mechanism explains everything else. Mobitz I is a fatiguing AV node, and the AV node is richly innervated by the vagus nerve, so blocking the vagus with atropine speeds it up. Mobitz II and complete block with a wide QRS sit in the His–Purkinje system, which has little vagal innervation, so atropine does nothing useful there — and by speeding the atrial rate it can actually worsen the ratio of conducted beats. For Mobitz II and third-degree block, the answer is pacing, and atropine must never delay it. Third-degree block is recognised by marching out the P waves at one regular rate and the QRS complexes at a different, slower regular rate, with no fixed relationship between them.
Pacemakers, implantable defibrillators and the nursing that surrounds them
A permanent pacemaker delivers an impulse when the heart’s own rate falls below a programmed threshold; the spike appears on the strip immediately before the captured complex. Three malfunctions are testable. Failure to capture is a pacer spike with no complex after it — the impulse fired but the myocardium did not respond, often because of lead displacement, a low output setting, or electrolyte or ischaemic change. Failure to sense is a spike that appears where it should not, marching into the patient’s own beats and risking an R-on-T event. Failure to pace is no spike at all when one is due, from battery depletion, a lead fracture or oversensing. All three are reported promptly.
An implantable cardioverter–defibrillator adds the ability to detect and terminate ventricular tachycardia or fibrillation with antitachycardia pacing or an internal shock. Teach the patient to sit or lie down when they feel a warning symptom, to keep a log of every shock, and the reporting rule: one shock with recovery means call the clinic; more than one shock in 24 hours, or a shock accompanied by chest pain, syncope or dyspnoea, means call 911. Household members should learn cardiopulmonary resuscitation; a bystander touching the patient during a discharge may feel a harmless tingle. Driving restrictions vary by state and by whether the device was placed for primary or secondary prevention, and this conversation must not be skipped.
Post-implantation care for either device: monitor the incision for bleeding, haematoma, redness or drainage; restrict the arm on the operative side from lifting above shoulder height and from lifting more than about 10 pounds for four to six weeks so the leads can fibrose into place; use a sling only as ordered and encourage gentle range of motion so the shoulder does not freeze; and watch for pneumothorax, which presents as new dyspnoea and diminished breath sounds after subclavian access. Long term, the patient carries the device identification card, avoids arc welding, large running motors and high-voltage fields, keeps a mobile phone at least six inches from the generator and uses the opposite ear, walks briskly through and never lingers in airport security arches, and asks whether their device is MRI-conditional before any scan.
Check for a pulse first: pulseless ventricular tachycardia and ventricular fibrillation get unsynchronised defibrillation and compressions, unstable organised rhythms with a pulse get synchronised cardioversion while unstable polymorphic ventricular tachycardia gets an unsynchronised shock because there is no R wave to track, and Mobitz II or complete heart block gets pacing rather than atropine.
Section 4Valvular Heart Disease and Infective Endocarditis
Stenosis versus regurgitation: the mechanical logic
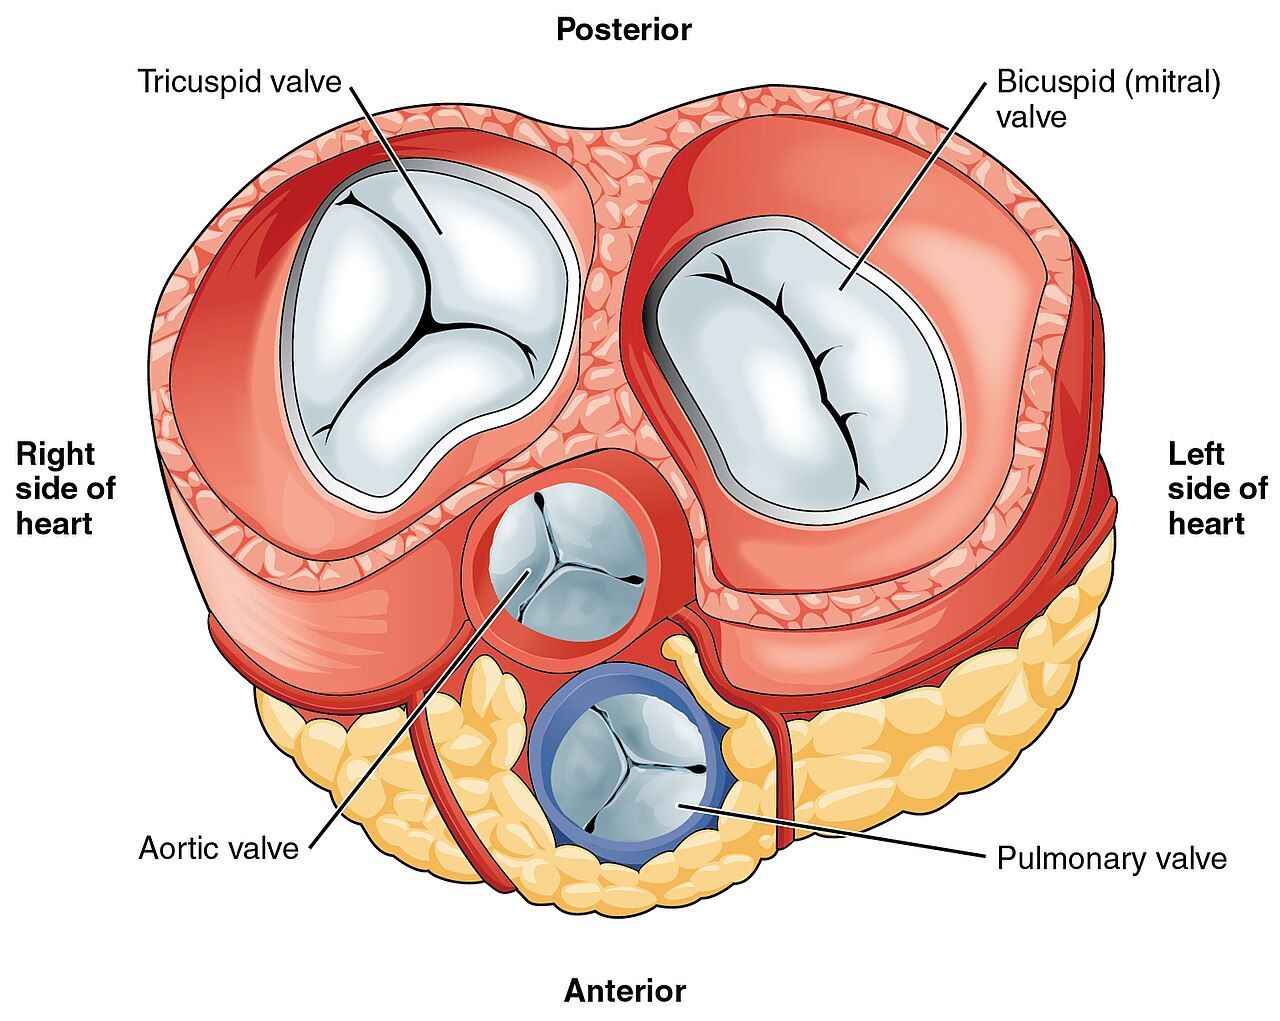
There are only two things a valve can do wrong. A stenotic valve will not open properly, so the chamber behind it must generate higher pressure to push blood through a smaller orifice; that chamber hypertrophies and pressure backs up behind it. A regurgitant (insufficient) valve will not close properly, so blood leaks backward with every beat; the receiving chamber has to handle its normal volume plus the regurgitant volume, so it dilates. Stenosis causes pressure overload and hypertrophy; regurgitation causes volume overload and dilation. Learn that sentence and you can reason out the findings of any valve lesion rather than memorising four separate lists.
Work out where the blood backs up and you have the symptoms. A mitral valve problem backs up into the left atrium and then into the pulmonary circulation, so the patient is dyspnoeic, orthopnoeic, has crackles and may cough pink or blood-tinged sputum. An aortic valve problem eventually backs up through the left ventricle into the left atrium and lungs as well, but its earlier symptoms are those of inadequate forward flow: exertional syncope, angina and fatigue. Tricuspid and pulmonic lesions back up into the systemic venous system, producing jugular venous distension, hepatomegaly, ascites and dependent oedema. A dilated left atrium, regardless of cause, stretches the atrial tissue and produces atrial fibrillation — which is how valve disease and Section 2 collide in the same patient.
Causes have shifted over time. Rheumatic heart disease, once the dominant cause worldwide and still important in immigrant and under-resourced populations, is now a smaller share in the United States, where degenerative calcific disease of the aortic valve in older adults, myxomatous degeneration of the mitral valve, congenital bicuspid aortic valve, infective endocarditis and dilation secondary to heart failure predominate. Transthoracic echocardiography is the diagnostic test of choice for all of them; it gives valve area, pressure gradient, ejection fraction and chamber size. Transoesophageal echocardiography is reserved for when better resolution is needed — vegetations, prosthetic valve dysfunction, left atrial thrombus. A B-type natriuretic peptide level (normal generally under 100 pg/mL) helps gauge how much the ventricle is straining.
The four lesions you must be able to describe
| Lesion | Murmur and signs | Key clinical points |
|---|---|---|
| Aortic stenosis | Harsh systolic crescendo–decrescendo at the second right intercostal space, radiating to the carotids; narrow pulse pressure; slow, weak carotid upstroke | Classic triad of syncope on exertion, angina and dyspnoea; severe when valve area is <1.0 cm² or mean gradient >40 mmHg; preload-dependent, so nitrates and aggressive diuresis can cause profound hypotension |
| Aortic regurgitation | Blowing decrescendo diastolic murmur at the left sternal border; wide pulse pressure; bounding water-hammer pulses; head bobbing | Volume-overloaded, dilated left ventricle; may be chronic and tolerated for years or acute (dissection, endocarditis) and catastrophic; afterload reduction helps forward flow |
| Mitral stenosis | Loud S1, opening snap, low-pitched diastolic rumble at the apex, best heard in the left lateral position | Usually rheumatic; left atrial hypertension causes dyspnoea, orthopnoea, haemoptysis and atrial fibrillation; severe when valve area is <1.5 cm²; requires warfarin, not a direct oral anticoagulant, if in atrial fibrillation |
| Mitral regurgitation | Holosystolic (blowing) murmur at the apex radiating to the axilla; S3 may be present | Left atrial and left ventricular volume overload; acute forms from papillary muscle rupture after myocardial infarction cause flash pulmonary oedema and are a surgical emergency |
| Mitral valve prolapse | Mid-systolic click, sometimes with a late systolic murmur | Very common and usually benign; palpitations, atypical chest pain, anxiety and fatigue; teach avoidance of caffeine and stimulants, adequate hydration, and a beta blocker if symptomatic |
Aortic stenosis earns extra attention because of what it forbids. The hypertrophied, non-compliant left ventricle depends on adequate preload and on the atrial kick to fill. Remove preload with a nitrate or a large dose of a loop diuretic and stroke volume falls off a cliff; the patient becomes hypotensive and may syncopise. Put the same patient into rapid atrial fibrillation and the loss of the atrial kick plus shortened filling time does the same thing. This is why the classic teaching is to be cautious with nitroglycerin in severe aortic stenosis, and why new atrial fibrillation in these patients is treated urgently. Whenever a nitrate is on the order set, screen for a phosphodiesterase-5 inhibitor as well — sildenafil or vardenafil within 24 hours, or tadalafil within 48 hours, makes any nitrate an absolute contraindication because the combination causes profound, refractory hypotension. Once symptoms appear, untreated severe aortic stenosis carries an average survival measured in a few years, which is why symptom onset is the trigger for valve replacement.
Nursing assessment for any valve patient is a fatigue and activity history — what could you do six months ago that you cannot do now? — plus auscultation at all four valve areas with both the diaphragm and the bell, palpation for a thrill, assessment for jugular venous distension, hepatomegaly, dependent oedema and crackles, daily weights, and an accurate apical–radial pulse. Management before surgery is largely medical: diuretics and sodium restriction for congestion, rate control and anticoagulation for atrial fibrillation, treatment of hypertension, and prompt treatment of anaemia, fever and infection, because anything that raises cardiac demand decompensates a fixed valve.
Repair, replacement and life with a prosthetic valve
Options range from valve repair — preferred for the mitral valve where feasible because it preserves the native apparatus and avoids anticoagulation — through percutaneous balloon valvuloplasty for selected mitral stenosis, to full replacement. Transcatheter aortic valve replacement delivers a bioprosthetic valve through the femoral artery without sternotomy, and postoperative nursing focuses on the vascular access site (bleeding, haematoma, retroperitoneal bleed presenting as flank or back pain and unexplained hypotension), distal pulses, renal function after contrast, stroke assessment, and new conduction disturbance — the new valve sits next to the conduction system, so a new left bundle branch block or complete heart block requiring a permanent pacemaker is a recognised complication.
Surgical replacement uses either a mechanical valve or a bioprosthetic (tissue) valve, and the trade-off is durability against anticoagulation. Mechanical valves last decades but require lifelong warfarin — international normalised ratio 2.0 to 3.0 for most mechanical aortic valves and 2.5 to 3.5 for mechanical mitral valves — and direct oral anticoagulants are contraindicated. Tissue valves generally last 10 to 20 years and need only a shorter course of anticoagulation followed by aspirin, but they degenerate and may require reoperation. Younger patients therefore usually receive mechanical valves and older patients tissue valves, though patient preference about bleeding risk and pregnancy plans weighs heavily.
After open valve surgery, nursing priorities are the ones common to cardiac surgery: haemodynamic monitoring, chest tube patency and output, pain control adequate to permit deep breathing, incentive spirometry with a splinting pillow, sternal precautions, early mobilisation, glycaemic control and rhythm surveillance for postoperative atrial fibrillation. Watch specifically for cardiac tamponade — a sudden drop or cessation of chest tube drainage followed by hypotension, jugular venous distension, muffled heart tones, narrowing pulse pressure and pulsus paradoxus. That is a rapid-response call, not a wait-and-see. Discharge teaching for a mechanical valve includes the expected soft clicking sound, bleeding precautions, strict international normalised ratio follow-up, antibiotic prophylaxis before dental work, and reporting fever, new dyspnoea, a changed valve sound or an embolic symptom immediately.
Infective endocarditis and rheumatic heart disease
Infective endocarditis is infection of the endocardium, usually of a valve, in which platelets and fibrin build a vegetation around colonising organisms. Two things follow: the vegetation destroys the valve, producing acute regurgitation and heart failure, and pieces break off and embolise. Left-sided vegetations embolise to the brain, spleen, kidneys and extremities; right-sided vegetations, common in people who inject drugs, embolise to the lungs and present as septic pulmonary emboli. Risk factors are prosthetic valves, prior endocarditis, congenital heart disease, injection drug use, indwelling vascular catheters, haemodialysis and immunosuppression. Staphylococcus aureus causes most acute, aggressive disease; viridans group streptococci cause the subacute form that follows dental procedures.
The presentation is fever plus a new or changed murmur, with fatigue, night sweats, weight loss, arthralgias and anorexia. The peripheral findings are classic and worth knowing by name: Osler nodes (painful, tender nodules on finger and toe pads — Osler is Ouch), Janeway lesions (painless flat haemorrhagic macules on palms and soles), splinter haemorrhages under the nails, Roth spots on the retina, petechiae on the conjunctivae and oral mucosa, and clubbing in long-standing disease. Diagnosis rests on the modified Duke criteria, combining blood cultures with echocardiographic evidence of vegetation. Obtain at least three sets of blood cultures from separate venipuncture sites before the first dose of antibiotic; giving antibiotics first can sterilise the cultures and leave the team treating blind for six weeks.
Treatment is four to six weeks of intravenous antibiotics targeted to the organism, frequently completed at home or in a skilled facility through a peripherally inserted central catheter. Nursing care is line care with meticulous sterile technique, monitoring temperature trends, tracking renal function and drug levels for vancomycin and aminoglycosides, daily assessment for new murmur or heart failure, and a focused neurological check every shift because embolic stroke is the feared complication. Surgery is indicated for heart failure from valve destruction, uncontrolled infection, prosthetic valve involvement or recurrent emboli. Prophylaxis is now restricted to the highest-risk patients — prosthetic valves or prosthetic material, prior endocarditis, certain congenital heart disease and cardiac transplant recipients with valvulopathy — who take amoxicillin 2 g orally 30 to 60 minutes before dental procedures involving gingival or periapical manipulation; cephalexin, azithromycin or doxycycline are used for penicillin allergy. Teach meticulous oral hygiene and regular dental care, because everyday gum disease produces more cumulative bacteraemia than any single procedure.
Acute rheumatic fever remains the reason that untreated streptococcal pharyngitis is not a trivial illness. Two to three weeks after group A streptococcal throat infection, antibodies cross-react with cardiac, joint, skin and neural tissue, producing carditis, migratory polyarthritis, chorea, erythema marginatum and subcutaneous nodules. The mitral valve is most often scarred, and the stenosis may not declare itself for twenty years. The nursing message is simple and preventive: culture the sore throat, and finish the entire antibiotic course.
Stenosis loads pressure and regurgitation loads volume, so predict the findings from the chamber behind the failing valve — and in aortic stenosis protect preload, because nitrates, brisk diuresis and new atrial fibrillation can all drop cardiac output abruptly.
Section 5Vascular Disease: Arteries, Veins, the Aorta and the Crisis
Peripheral arterial disease and acute limb ischaemia
Peripheral arterial disease is atherosclerosis of the limb arteries, most often the lower extremities. The pathophysiology is identical to coronary disease, so the risk factors are identical — smoking above all, then diabetes, hypertension, dyslipidaemia, age and chronic kidney disease — and the presence of peripheral arterial disease means that patient almost certainly has coronary and cerebrovascular disease too. The cardinal symptom is intermittent claudication: reproducible cramping, aching or fatigue in the calf, thigh or buttock brought on by a predictable amount of walking and relieved within a few minutes of rest. As disease progresses, pain appears at rest, characteristically in the forefoot and toes at night, and is relieved by hanging the leg over the side of the bed, because gravity assists a circulation that can no longer overcome supine pressures.
Assessment findings follow the mechanism. The limb is cool and pale, with thin, shiny, hairless skin, thickened nails, muscle atrophy, diminished or absent pedal pulses, prolonged capillary refill, pallor on elevation and dependent rubor. Ulcers, when they come, sit on the toes, the lateral malleolus or pressure points; they are round with sharply demarcated “punched-out” edges, pale or necrotic at the base, exquisitely painful and minimally exudative. The diagnostic bedside test is the ankle–brachial index, the ratio of ankle to brachial systolic pressure by Doppler.
| Ankle–brachial index | Interpretation |
|---|---|
| 1.00–1.40 | Normal |
| 0.91–0.99 | Borderline; consider exercise testing |
| 0.41–0.90 | Mild to moderate peripheral arterial disease; claudication typical |
| 0.40 or less | Severe disease; rest pain, ulceration, critical limb ischaemia |
| Greater than 1.40 | Non-compressible, calcified vessels — common in diabetes and chronic kidney disease; the value is unreliable, use toe pressures |
Management begins with risk-factor treatment, because the leg is the visible part of a systemic disease: complete tobacco cessation (the single highest-value intervention), a high-intensity statin, an antiplatelet agent such as aspirin 81 mg or clopidogrel 75 mg, blood pressure and glycaemic control. A supervised walking programme — walk to near-maximal claudication pain, rest, repeat, for 30 to 45 minutes three or more times a week — genuinely increases walking distance by promoting collateral vessels, and it is the intervention patients most need coaching to continue through the discomfort. Cilostazol, a phosphodiesterase III inhibitor, improves walking distance but is contraindicated in heart failure of any severity and takes weeks to work. Revascularisation, by angioplasty with stenting or by bypass grafting, is reserved for lifestyle-limiting claudication or critical limb ischaemia.
Positioning and foot care are where nursing decides outcomes. In arterial disease, keep the legs below heart level or neutral — never elevated — because elevation removes the gravitational assist. Keep the patient warm with socks and blankets, but never apply direct heat such as a heating pad or hot soak, because neuropathic skin will burn before the patient feels it. Avoid crossing the legs and avoid constricting clothing. Inspect the feet daily including between the toes with a mirror, wash with lukewarm water and mild soap, dry thoroughly, moisturise the skin but not between the toes, cut nails straight across or have a podiatrist do it, and never walk barefoot. Any new break in the skin is reported the same day. Acute arterial occlusion announces itself with the six P’s — pain, pallor, pulselessness, paraesthesia, poikilothermia (coolness) and paralysis — and it is a limb-threatening emergency with roughly six hours before irreversible tissue loss. Do not elevate, do not apply heat or cold, do not massage the limb: keep it dependent and protected, keep the patient nothing by mouth in anticipation of surgery, and call immediately for anticoagulation and revascularisation.
Venous thromboembolism and anticoagulation safety
Virchow’s triad explains every deep vein thrombosis you will ever see: venous stasis, endothelial injury and hypercoagulability. The hospitalised medical–surgical patient has all three — immobility, surgical or catheter-related vessel trauma, and the acute-phase hypercoagulable state of illness, malignancy, oestrogen therapy, pregnancy or inherited thrombophilia. Findings in the affected limb are unilateral oedema (measure and compare calf circumferences at a marked point), warmth, erythema, tenderness along the deep venous course and a dull ache. Homans sign is unreliable and is no longer recommended. Venous duplex ultrasonography is the diagnostic test; a D-dimer below about 500 ng/mL FEU is useful to exclude thrombosis in a low-probability patient but is non-specific and rises with surgery, infection, pregnancy, malignancy and age.
The feared complication is pulmonary embolism: sudden dyspnoea, pleuritic chest pain, tachypnoea, tachycardia, hypoxaemia, apprehension and, in massive embolism, hypotension and syncope. Any patient with a known or suspected deep vein thrombosis who becomes acutely short of breath is a rapid-response call. Prevention is a nursing responsibility on every shift: early and frequent ambulation, ankle pumps and leg exercises for the patient who cannot walk, adequate hydration, sequential compression devices worn as ordered, and pharmacologic prophylaxis such as enoxaparin 40 mg subcutaneously daily or heparin 5000 units subcutaneously two or three times a day unless contraindicated.
Treatment is anticoagulation, which does not dissolve the existing clot but stops its extension while the body lyses it. Options are a direct oral anticoagulant, low-molecular-weight heparin such as enoxaparin 1 mg/kg subcutaneously every 12 hours, or an unfractionated heparin infusion bridging to warfarin. Unfractionated heparin is monitored by activated partial thromboplastin time at 1.5 to 2.5 times control (commonly about 46 to 70 seconds) or by an anti-factor Xa level of 0.3 to 0.7 units/mL; its antidote is protamine sulfate. Low-molecular-weight heparin needs no routine monitoring except in renal impairment, obesity or pregnancy, where an anti-Xa level is used. Teach enoxaparin injection into the abdominal fat two inches from the umbilicus, alternating sides, without expelling the air bubble and without rubbing the site. Warfarin overlaps with heparin for at least five days and until the international normalised ratio has been therapeutic for 24 hours, because warfarin is transiently procoagulant at initiation.
Heparin-induced thrombocytopenia is the complication that must not be missed. An immune reaction to heparin–platelet factor 4 complexes causes the platelet count to fall by more than 50 per cent, typically five to ten days after exposure, and paradoxically causes thrombosis, not bleeding. Check a baseline platelet count and monitor it on every heparin patient. If it is suspected: stop all heparin, including flushes and heparin-bonded catheters, notify the provider, and anticipate a non-heparin anticoagulant such as argatroban, bivalirudin or fondaparinux. Do not transfuse platelets, and do not start warfarin until the platelet count has recovered. An inferior vena cava filter is reserved for patients in whom anticoagulation is contraindicated or has failed.
Chronic venous insufficiency and telling the two ulcers apart
Chronic venous insufficiency results from incompetent valves in the deep or perforating veins, often after a previous deep vein thrombosis, so blood refluxes and venous pressure stays high. Capillaries leak fluid, protein and red cells into the tissue; haemoglobin breakdown leaves the characteristic brown haemosiderin staining, and the skin becomes indurated, itchy and eczematous. The limb is warm, oedematous and heavy, worse at the end of the day and better after a night in bed. The ulcer that follows sits over the medial malleolus, is shallow with irregular sloping borders, has a beefy red granulating base, drains a good deal of fluid and is uncomfortable rather than agonising.
| Feature | Arterial ulcer | Venous ulcer |
|---|---|---|
| Location | Toes, heels, lateral malleolus, pressure points | Medial malleolus, gaiter area of the lower leg |
| Appearance | Round, punched-out, pale or black base | Shallow, irregular border, red granulating base |
| Drainage | Minimal | Moderate to heavy |
| Pain | Severe; worse with elevation and at night | Aching, heavy; better with elevation |
| Surrounding skin | Thin, shiny, hairless, cool, pallor on elevation | Warm, oedematous, brown haemosiderin staining, dermatitis |
| Pulses | Diminished or absent | Usually present (may be hard to palpate through oedema) |
| Positioning | Dependent — keep the leg down | Elevated above heart level several times a day |
Management of venous disease is compression, elevation and skin care. Graduated compression stockings of 20–30 or 30–40 mmHg are the mainstay, applied first thing in the morning before the leg has become oedematous, removed at night, and replaced every three to six months when they lose elasticity. Layered compression wraps such as an Unna boot are used for active ulcers. The critical safety check is that compression must not be applied to a limb with significant arterial insufficiency — confirm the ankle–brachial index first, because squeezing a leg that cannot get arterial blood in will cause necrosis. Teach elevation above heart level for 20 minutes several times daily, avoidance of prolonged standing or sitting with legs dependent, ankle pumping every hour, weight management, and daily moisturising of intact skin. Venous ulcers are slow; healing is measured in weeks to months, and adherence to compression is the single strongest predictor of whether they close and stay closed.
Aneurysm, dissection and hypertensive crisis
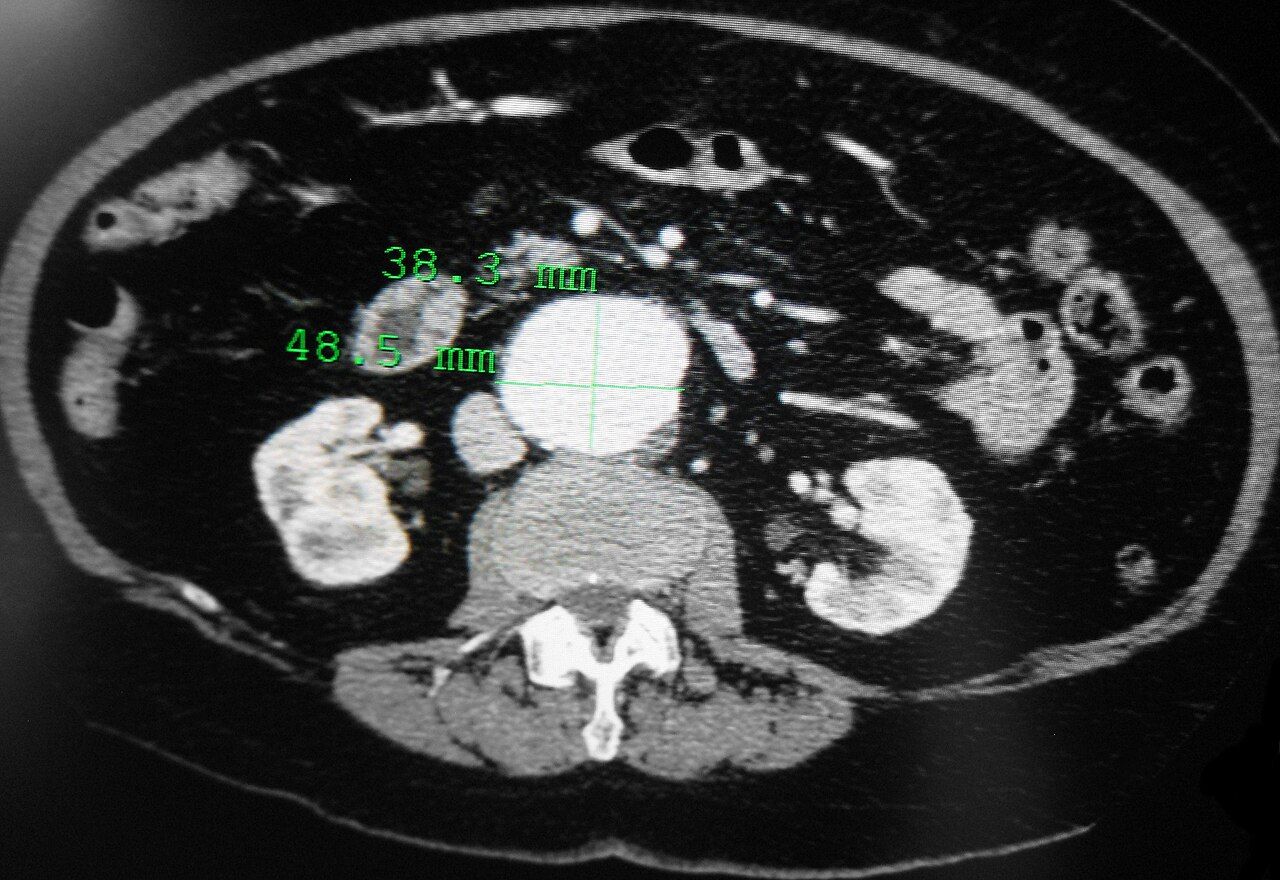
An abdominal aortic aneurysm is a permanent dilation to more than one and a half times normal diameter, driven by atherosclerosis, hypertension, smoking, male sex, age and connective tissue disorders such as Marfan syndrome. It is usually silent and found incidentally; when there are findings they are a pulsatile mass at or above the umbilicus, a bruit and vague abdominal or low back pain. Do not palpate deeply on a suspected or known aneurysm. Surveillance imaging is by ultrasound or computed tomography, and elective repair — open or endovascular — is generally offered at about 5.5 cm, or sooner for rapid expansion of more than 0.5 cm in six months, symptoms, or in some women at a smaller diameter. Medical management in the meantime is blood pressure control, statin therapy and absolute smoking cessation. Rupture presents as sudden severe, tearing abdominal, flank or back pain with hypotension, tachycardia and a pulsatile mass, and it is an immediate surgical emergency: large-bore access, type and crossmatch, nothing by mouth, and the operating room. After endovascular repair, monitor peripheral pulses and limb perfusion hourly at first, renal function (contrast plus possible graft coverage of renal arteries), the groin access sites, and any new back or abdominal pain, which may signal an endoleak.
Aortic dissection is a tear in the intima that allows blood to split the layers of the aortic wall. The pain is abrupt, maximal at onset, and described as tearing or ripping, classically radiating to the back between the scapulae. Look for a systolic blood pressure difference of more than 20 mmHg between arms, a pulse deficit, a new diastolic murmur of aortic regurgitation, and neurological deficit if the arch vessels are involved. Type A dissection involves the ascending aorta and is a surgical emergency; type B is descending and usually managed medically. The medical goal is to reduce the shearing force fast: heart rate below 60 and systolic pressure to roughly 100 to 120 mmHg within about 20 minutes. Give the intravenous beta blocker first — esmolol or labetalol — and only then add a vasodilator such as nicardipine or nitroprusside, because a vasodilator given alone produces reflex tachycardia that increases the force per beat and can extend the dissection. Pain control with opioids is not optional; catecholamine release from pain raises pressure.
Hypertensive emergency is a systolic pressure above 180 or a diastolic above 120 with evidence of acute target organ damage — encephalopathy, stroke, papilloedema, acute heart failure or pulmonary oedema, myocardial ischaemia, acute kidney injury, dissection or eclampsia. Without organ damage, the same numbers are hypertensive urgency, treated with oral agents and follow-up over 24 to 48 hours. In an emergency the patient is admitted to an intensive setting for continuous intra-arterial or frequent non-invasive pressure monitoring and a titratable intravenous infusion — nicardipine, clevidipine, labetalol, esmolol or nitroprusside (protect from light, and watch for cyanide and thiocyanate toxicity with prolonged high-dose use). Lower the mean arterial pressure by no more than about 25 per cent in the first hour, then toward 160/100 to 110 over the next two to six hours, and to normal over 24 to 48 hours; dropping it faster can infarct a brain, kidney or coronary bed that has autoregulated to the higher pressure. The exceptions are aortic dissection, which demands rapid lowering, and acute ischaemic stroke, where pressure is permitted to run high unless thrombolysis is planned.
Arterial disease means a limb that is cool, pulseless, painful with elevation and ulcerated over pressure points and is kept dependent; venous disease means a limb that is warm, oedematous, stained and ulcerated at the medial malleolus and is elevated and compressed — and confusing the two reverses the treatment.
The chapter in one breath
Cardiac rhythm is only ever important because of what it does to output and to clot. Analyse every strip the same six ways, then answer one question before any other: is this patient stable or unstable, and is the rhythm the reason? Unstable tachycardia with an organised rhythm gets synchronised cardioversion, unstable polymorphic ventricular tachycardia gets an unsynchronised shock because there is no consistent R wave to synchronise to, unstable bradycardia gets atropine and then pacing, and pulselessness gets compressions and, if the rhythm is ventricular fibrillation or pulseless ventricular tachycardia, unsynchronised defibrillation. Atrial fibrillation steals the atrial kick and grows thrombus in the left atrial appendage, which is why rate control, rhythm control and anticoagulation are the only three things you ever do about it, and why nobody is converted after 48 hours without three weeks of anticoagulation or a clean transoesophageal echocardiogram. Valve disease is mechanics: stenosis loads pressure and hypertrophies, regurgitation loads volume and dilates, and the symptoms appear wherever the blood backs up. Vascular disease is the conduit failing by narrowing, clotting, dilating or tearing — and the bedside difference between an arterial and a venous leg reverses the positioning, the compression and the plan. Everywhere in this chapter, assessment precedes intervention and airway, breathing and circulation precede everything.
Words worth knowing
| Term | What it means |
|---|---|
| Atrial kick | The 20 to 30 per cent of ventricular filling supplied by atrial contraction; lost in atrial fibrillation and sorely missed by a stiff ventricle |
| Irregularly irregular | An R-to-R pattern with no discernible repeating sequence; the bedside hallmark of atrial fibrillation |
| Pulse deficit | Apical rate exceeding radial rate, because some ventricular beats are too weak to generate a palpable peripheral pulse |
| CHA2DS2-VASc | Point score estimating stroke risk in atrial fibrillation and driving the decision to anticoagulate |
| Direct oral anticoagulant | Apixaban, rivaroxaban, edoxaban or dabigatran; no routine monitoring, renally dosed, not for mechanical valves or significant mitral stenosis |
| Synchronised cardioversion | A shock timed to the R wave, used for unstable tachydysrhythmias that still have a pulse and an organised, trackable QRS |
| Defibrillation | An unsynchronised shock delivered immediately, used for ventricular fibrillation, pulseless ventricular tachycardia and unstable polymorphic ventricular tachycardia, whose changing QRS cannot be synchronised to |
| R-on-T phenomenon | A premature ventricular beat landing on the T wave during repolarisation, capable of triggering ventricular fibrillation |
| Torsades de pointes | Polymorphic ventricular tachycardia arising from a prolonged QT interval; treated with intravenous magnesium sulfate, and with an unsynchronised shock rather than synchronised cardioversion if the patient becomes unstable or pulseless |
| Mobitz II | Second-degree block with a constant PR and intermittently dropped QRS; infranodal, unstable, and an indication for pacing rather than atropine |
| Atrioventricular dissociation | Independent atrial and ventricular activity; the defining feature of third-degree (complete) heart block |
| Failure to capture | A pacemaker spike not followed by a depolarisation, meaning the impulse fired but the myocardium did not respond |
| Stenosis / regurgitation | A valve that will not open (pressure overload, hypertrophy) versus one that will not close (volume overload, dilation) |
| Osler nodes / Janeway lesions | Painful nodules on finger and toe pads versus painless macules on palms and soles; peripheral findings of infective endocarditis |
| Modified Duke criteria | Diagnostic framework for infective endocarditis combining blood culture and echocardiographic findings |
| Intermittent claudication | Reproducible exertional limb pain relieved by rest; the cardinal symptom of peripheral arterial disease |
| Ankle–brachial index | Ankle-to-brachial systolic pressure ratio; 0.90 or less indicates peripheral arterial disease, above 1.40 indicates non-compressible calcified vessels |
| Virchow triad | Venous stasis, endothelial injury and hypercoagulability — the three conditions that produce venous thrombosis |
| Heparin-induced thrombocytopenia | Immune platelet drop of more than 50 per cent, typically days 5 to 10, that causes thrombosis; stop all heparin and use a non-heparin anticoagulant |
| Hypertensive emergency | Severe hypertension with acute target organ damage; lower the mean arterial pressure by no more than about 25 per cent in the first hour |