Paediatric Systemic and Chronic Conditions
A child is not a small adult, and nowhere is that truer than in the systemic and chronic conditions of childhood. A toddler carries a larger proportion of body water in the extracellular compartment, turns that water over faster, has immature renal concentrating ability, and can therefore lose a tenth of their body weight to a two-day gastroenteritis while an adult with the same illness merely feels unwell. A child compensates for shock with tachycardia and vasoconstriction and holds blood pressure nearly to the point of arrest, so hypotension in a child is a late and ominous finding. Every drug is weighed against kilograms, every fluid rate is calculated rather than ordered by habit, and every dose must still be checked against the maximum an adult would ever receive. This chapter moves system by system — gut, kidney and endocrine gland, blood and marrow, brain, bone and skin — and then returns to the two things that hold all of it together: the arithmetic, and the family.
By the end of this chapter you can
- State normal paediatric vital sign ranges by age band and calculate the age-specific threshold for hypotension, explaining why hypotension is a late sign of shock in children.
- Grade dehydration by percentage weight loss, select oral versus intravenous rehydration, and calculate an isotonic fluid bolus at 20 mL/kg.
- Calculate maintenance fluids using the 4-2-1 rule and verify the result against the Holliday-Segar daily method.
- Perform a weight-based safe-dose-range check, show the arithmetic, and compare the result with the maximum adult dose before administering.
- Prioritise nursing actions in diabetic ketoacidosis, vaso-occlusive crisis, acute chest syndrome, febrile neutropenia, status epilepticus and rising intracranial pressure, naming the first action in each.
- Differentiate nephrotic syndrome from acute glomerulonephritis and describe the monitoring that detects deterioration first.
- Recognise compartment syndrome, splenic sequestration and Hirschsprung enterocolitis as time-critical events and escalate using SBAR.
- Apply delegation boundaries in paediatrics, retaining assessment, teaching, evaluation and the unstable child within registered nurse practice.
- Partner with families in chronic illness using non-blaming, family-centred language and developmentally matched teaching.
Section 1Fluid Balance, Dehydration and the Gastrointestinal Tract

Why children destabilise faster
Water is distributed differently in a child. A newborn is roughly 75 to 80 percent water with about half of that in the extracellular compartment, compared with an adult who is around 60 percent water with only a third extracellular. Extracellular fluid is the fluid that is lost first in vomiting, diarrhoea, fever and burns, so the child has proportionally more of the vulnerable compartment and less of the protected intracellular reserve. Add a metabolic rate two to three times that of an adult, a body surface area to mass ratio that magnifies insensible loss, and renal tubules that cannot concentrate urine efficiently until around two years of age, and the picture is of an organism with a very small margin.
The compensation is cardiovascular and it is quiet. A child in early shock increases heart rate and clamps down peripherally. Stroke volume in an infant is relatively fixed, so cardiac output is almost entirely rate-dependent — which is why bradycardia in a sick infant is a pre-arrest rhythm, not a reassuring one. Blood pressure holds until roughly 25 to 30 percent of circulating volume is gone. The findings that appear before hypotension are the ones worth chasing: tachycardia at rest, capillary refill longer than two seconds, cool mottled extremities, weak peripheral pulses with a stronger central pulse, and a falling level of alertness or an unusual disinterest in the parent.
Urine output is the cheapest and most honest monitor available. Expect at least 2 mL/kg/h in an infant, 1 mL/kg/h in a child, and 0.5 to 1 mL/kg/h in an adolescent. Weigh nappies to measure rather than estimate: 1 gram of gained nappy weight equals 1 mL of urine. Weight itself is the single most sensitive index of acute fluid change, because 1 kg of acute weight loss equals 1 litre of fluid deficit. Weigh on the same scale, at the same time, in the same clothing or none, once daily — and in acute illness, twice.
| Age band | Heart rate (awake, per min) | Respiratory rate (per min) | Systolic BP (mmHg) | Hypotension if systolic below |
|---|---|---|---|---|
| Newborn (0–28 days) | 100–180 | 30–60 | 60–90 | 60 |
| Infant (1–12 months) | 100–160 | 30–53 | 70–100 | 70 |
| Toddler (1–2 years) | 90–150 | 22–37 | 80–110 | 70 + (2 × age in years) |
| Preschool (3–5 years) | 80–140 | 20–28 | 80–110 | 70 + (2 × age in years) |
| School age (6–11 years) | 70–120 | 18–25 | 90–120 | 70 + (2 × age in years) through age 10; below 90 from age 10 onward |
| Adolescent (12–18 years) | 60–100 | 12–20 | 100–130 | 90 |
Grading dehydration and rehydrating
Grade dehydration by percentage of body weight lost, using a recent pre-illness weight when one exists: percent deficit equals pre-illness weight minus current weight, divided by pre-illness weight, times 100. When no recent weight exists, grade clinically. Mild dehydration is under 5 percent, moderate is 5 to 10 percent, and severe is over 10 percent. In a 10 kg toddler, 10 percent is 1 kg — one litre — and that child looks profoundly unwell.
| Finding | Mild (under 5%) | Moderate (5–10%) | Severe (over 10%) |
|---|---|---|---|
| Mental state | Alert, thirsty | Irritable or listless | Lethargic, obtunded |
| Heart rate | Normal | Tachycardic | Marked tachycardia, weak pulses |
| Capillary refill | Under 2 s | 2–3 s | Over 3 s, mottled |
| Mucous membranes | Slightly dry | Dry | Parched, no tears |
| Anterior fontanelle (infant) | Flat | Slightly sunken | Markedly sunken |
| Urine output | Slightly reduced | Under 1 mL/kg/h | Minimal or anuric |
| First-line therapy | ORS 50 mL/kg over 4 h | ORS 100 mL/kg over 4 h | IV isotonic bolus 20 mL/kg |
Oral rehydration solution is the treatment for mild and moderate dehydration in a child who is alert and able to drink, including a child who is vomiting. The technique matters more than the volume ordered: 5 mL by syringe or spoon every one to two minutes, escalating as tolerated, gives roughly 150 to 300 mL in an hour. Replace ongoing losses with an extra 10 mL/kg for each diarrhoeal stool and about 2 mL/kg for each vomit. Continue breastfeeding or chestfeeding throughout, and reintroduce the usual diet within four to six hours — there is no evidence for prolonged clear-liquid diets, and early refeeding shortens illness. Plain water, fruit juice, sports drinks and carbonated drinks are the wrong osmolality and can worsen diarrhoea and drop sodium.
Severe dehydration is intravenous. The first action is to establish vascular access — peripheral intravenous, and if two attempts or 90 seconds fail in a decompensated child, intraosseous — and give an isotonic bolus of 0.9 percent sodium chloride or lactated Ringer solution at 20 mL/kg over 5 to 20 minutes. Reassess after every bolus: heart rate, perfusion, mental state, urine output. Repeat to a total of 40 to 60 mL/kg, and if perfusion has not improved by then, the problem is not simple hypovolaemia. Bolus volumes are reduced to 10 mL/kg in neonates, in diabetic ketoacidosis, in severe malnutrition and in known cardiac disease. Dextrose-containing and hypotonic fluids are never used for a resuscitation bolus.
Obstruction and the acute abdomen
Hypertrophic pyloric stenosis presents between two and eight weeks of age, most often in a firstborn male infant, with forceful non-bilious vomiting that becomes projectile, an infant who is ravenously hungry immediately afterwards, visible left-to-right peristaltic waves, and sometimes a firm olive-shaped mass in the right upper quadrant. Persistent loss of gastric hydrochloric acid produces the classic hypochloraemic, hypokalaemic metabolic alkalosis. The single most important teaching point is one of sequence: this is a medical emergency before it is a surgical one. The infant is kept nil by mouth with a nasogastric tube to low intermittent suction, and fluid and electrolyte derangement is corrected before pyloromyotomy, because operating on an alkalotic hypokalaemic infant invites post-operative apnoea. Feeds resume in small volumes four to six hours after surgery and some vomiting for the first day or two is expected.
Intussusception occurs when one segment of bowel telescopes into another, most often at the ileocaecal valve, in children between three months and three years with a peak around five to ten months. The child screams and draws the knees to the chest in sudden colicky episodes lasting a few minutes, then between episodes may appear entirely well or unusually lethargic. A sausage-shaped mass may be palpable in the right upper quadrant. Stool mixed with blood and mucus — the “currant jelly” stool — is a late finding and its absence proves nothing. Air or hydrostatic contrast enema under fluoroscopy is both diagnostic and therapeutic in most cases. After reduction, the passage of a normal brown stool suggests the bowel has reduced and must be reported to the provider immediately, because it changes the plan.
Appendicitis in a child begins as periumbilical pain that migrates to McBurney point in the right lower quadrant, with anorexia, low-grade fever, guarding and rebound tenderness. A sudden and complete relief of pain is not improvement — it is perforation, and it will be followed within hours by rigidity, rising fever and shock. Never apply heat to the abdomen and never give an enema or laxative for undiagnosed abdominal pain in a child. Hirschsprung disease presents with failure to pass meconium within 48 hours of birth, abdominal distension and ribbon-like foul-smelling stools; its emergency is enterocolitis — fever, explosive foul diarrhoea and a tense distended abdomen — which is life-threatening and demands immediate escalation.
Chronic conditions of the gut
Gastro-oesophageal reflux is physiological in most infants and resolves as the lower oesophageal sphincter matures by around 12 months. Management is conservative: smaller more frequent feeds, thorough burping, holding the infant upright for 20 to 30 minutes after feeds, and avoiding seat positions that flex the abdomen. Infants still sleep supine — reflux does not override safe-sleep guidance. Escalate the infant who is not gaining weight, who has haematemesis, apnoea, arching with feeds or recurrent respiratory illness, because that pattern is disease rather than physiology.
Cleft lip and cleft palate make feeding, not appearance, the first nursing priority. Use a wide-based or one-way-valve cleft bottle, hold the infant upright at 45 to 90 degrees, direct the nipple toward the intact side of the palate, and burp frequently because these infants swallow a great deal of air. Lip repair is usually undertaken around two to three months and palate repair by six to twelve months so that speech develops over a closed palate. After repair, protect the suture line absolutely: no straws, no pacifiers, no spoons or hard-tipped toys in the mouth, elbow immobilisers with scheduled removal one arm at a time for range of motion, and positioning supine or side-lying rather than prone after a lip repair.
Coeliac disease requires strict lifelong exclusion of gluten from wheat, barley and rye; rice, corn, quinoa and potato are safe, and oats are permitted provided they are certified gluten-free, since the problem with oats is contamination during growing and milling rather than gluten itself — a small minority who remain symptomatic on oats are reviewed individually. Untreated, it produces steatorrhoea, abdominal distension, wasted buttocks and growth faltering. The family needs label-reading skills, a plan for school meals and birthday parties, and the reassurance that a single exposure is a setback rather than a failure.
Grade a child’s dehydration by percentage weight lost, treat mild and moderate loss orally with 50 to 100 mL/kg of oral rehydration solution over four hours, and reserve the 20 mL/kg isotonic bolus for the child who is severely dehydrated or poorly perfused — remembering that hypotension in a child is a late sign, never an early one.
Section 2Renal, Genitourinary and Endocrine Conditions
Urinary tract infection and vesicoureteral reflux
An infant with a urinary tract infection rarely complains of dysuria. The presentation is systemic and vague: fever without an obvious source, irritability, poor feeding, vomiting, foul-smelling urine, poor weight gain, and in the neonate, jaundice or hypothermia. Any infant under three months with a fever of 38.0 °C or higher needs a full evaluation that includes urine. In toilet-trained children the picture becomes recognisable — urgency, frequency, dysuria, new daytime wetting, suprapubic or flank pain.
Specimen technique determines whether the result means anything. In a child who is not toilet trained, a culture must come from a catheterised or suprapubic specimen; bag specimens are contaminated so frequently that a positive culture cannot be interpreted, though a negative bag specimen is useful for ruling out. Treat with the prescribed antibiotic for the full course, push fluids, and teach front-to-back wiping, cotton underwear, avoidance of bubble baths, complete and unhurried voiding roughly every two to three hours, and treatment of constipation, which is one of the most under-recognised drivers of recurrent infection.
Vesicoureteral reflux, graded I through V, allows infected bladder urine to reach the kidney and scar it. Lower grades often resolve with growth on surveillance with or without prophylactic antibiotics; higher grades may need surgical reimplantation. The nursing message to families is that fever in a child with reflux is not a wait-and-see event.
Nephrotic syndrome and acute glomerulonephritis
These two look superficially similar — a swollen child with abnormal urine — and they are managed almost oppositely, so the distinction is worth holding clearly.
| Nephrotic syndrome (minimal change) | Acute post-streptococcal glomerulonephritis | |
|---|---|---|
| Typical age | 2–6 years | 5–12 years |
| Trigger | Often none identified; may follow viral illness | Group A streptococcal pharyngitis 1–2 weeks prior, or impetigo 3–6 weeks prior |
| Proteinuria | Massive (over 50 mg/kg/day; urine protein-to-creatinine ratio above 2) | Mild to moderate |
| Haematuria | Usually absent | Gross — tea- or cola-coloured urine |
| Blood pressure | Normal or low | Elevated — hypertension is the hallmark |
| Serum albumin | Low (under 2.5 g/dL) | Normal or mildly reduced |
| Oedema | Periorbital on waking, becoming generalised with ascites | Periorbital and mild peripheral |
| Key labs | Hyperlipidaemia, hypoalbuminaemia | Elevated antistreptolysin-O titre, low serum C3, raised urea and creatinine |
| Mainstay of therapy | Corticosteroids: prednisone 2 mg/kg/day, maximum 60 mg/day, 4–6 weeks then taper | Supportive: blood pressure control, sodium and fluid restriction; antibiotics if infection persists |
| Watch for | Infection, especially peritonitis; thrombosis; hypovolaemia during diuresis | Hypertensive encephalopathy, acute kidney injury, circulatory congestion |
For both, the daily weight taken at the same time on the same scale is the most informative single measurement on the chart — more sensitive than abdominal girth, more reliable than a visual impression of puffiness, and quicker to change than serum albumin. Strict intake and output, daily abdominal girth in nephrotic syndrome, urine dipstick for protein each morning, and blood pressure four-hourly in glomerulonephritis complete the picture. The corticosteroid-treated child is immunosuppressed: screen visitors, avoid crowds, delay live vaccines, and treat fever as urgent. Teach families that steroids cause hunger, mood swings, a rounded face and weight gain, that these are expected and reversible, and that the drug is never stopped abruptly.
Type 1 diabetes and diabetic ketoacidosis
Type 1 diabetes is autoimmune destruction of pancreatic beta cells, and in children it frequently announces itself as ketoacidosis. Diabetic ketoacidosis is defined by a blood glucose above 200 mg/dL (11.1 mmol/L), venous pH below 7.3 or serum bicarbonate below 15 mmol/L, and ketonaemia or ketonuria. The child is polyuric, polydipsic, losing weight, breathing deeply and rapidly in Kussmaul respirations with acetone on the breath, and vomiting with abdominal pain that is easily mistaken for gastroenteritis.
The order of treatment is the lesson. Fluids come first, insulin second. Give an isotonic bolus of 10 mL/kg over the first hour — deliberately gentler than the 20 mL/kg used in other forms of shock — and then begin a continuous regular insulin infusion at 0.05 to 0.1 units/kg/h one to two hours after fluids have started. No insulin bolus is given to a child in DKA. Serum potassium will appear normal or high while total body potassium is severely depleted, because acidosis drives potassium out of cells; as insulin drives it back in, potassium falls fast. Potassium is added to the infusion once the serum level is below 5.5 mmol/L and the child is passing urine. Dextrose is added when glucose falls to around 250 to 300 mg/dL so that the insulin infusion can continue to close the anion gap without producing hypoglycaemia; glucose should not fall faster than 50 to 100 mg/dL per hour.
Cerebral oedema is the complication that kills children in DKA, and it typically appears 4 to 12 hours into treatment, often just as the numbers are improving. The warning signs are headache, a rising blood pressure with a falling heart rate, recurrent vomiting, incontinence in a previously continent child, irritability, and any decline in level of consciousness. This is an immediate call to the provider and the rapid response team, with the head of bed elevated and hypertonic therapy prepared — mannitol 0.5 to 1 g/kg or 3 percent sodium chloride 3 to 5 mL/kg intravenously.
Day-to-day management is a family project. Rapid-acting insulin such as lispro or aspart begins working in 10 to 15 minutes, peaks at 1 to 2 hours and lasts 3 to 5 hours, so it is given with food in hand. Long-acting glargine or detemir has no pronounced peak and is never mixed in a syringe with another insulin; when regular and NPH are drawn together, draw clear before cloudy. Rotate injection sites within one anatomical region to keep absorption predictable. Hypoglycaemia below 70 mg/dL in a conscious child is treated with roughly 15 g of fast carbohydrate in an adolescent and 5 to 10 g in a young child — about 0.3 g/kg — then rechecked in 15 minutes and followed with protein and complex carbohydrate. For the unconscious child, give glucagon intramuscularly: 0.5 mg if under 25 kg and 1 mg if 25 kg or more, and turn the child on their side because glucagon commonly causes vomiting. The rule that families most often get wrong is the sick-day rule: insulin is never omitted during illness, even when the child is not eating, because illness raises counter-regulatory hormones and drives ketosis.
Congenital endocrine conditions
Congenital hypothyroidism is detected on the newborn blood-spot screen because the untreated infant looks deceptively easy — sleepy, quiet, constipated, jaundiced, a poor feeder with a large tongue and an open posterior fontanelle. Levothyroxine at approximately 10 to 15 mcg/kg/day must begin within the first two weeks of life to protect neurodevelopment. Teach the parent to crush the tablet and mix it with a small volume of breast milk, formula or water given by syringe, never in a full bottle that may not be finished, and to separate it from soy formula, iron and calcium, which impair absorption. Signs of over-replacement are tachycardia, irritability, sweating and poor weight gain.
Congenital adrenal hyperplasia, most commonly 21-hydroxylase deficiency, may present with atypical genitalia in a genetically female infant or, in the salt-wasting form, with a crisis in the second or third week of life: vomiting, dehydration, hyponatraemia, hyperkalaemia and shock. Lifelong hydrocortisone with fludrocortisone in salt-wasting disease is the treatment, and the vital family teaching is stress dosing — the dose is doubled or tripled during fever, vomiting or injury, and an emergency intramuscular hydrocortisone kit and medical identification travel with the child everywhere.
Nephrotic syndrome and glomerulonephritis are separated at the bedside by blood pressure and urine colour, and both are monitored best by the daily weight; in diabetic ketoacidosis the sequence is fluids before insulin, potassium before it falls, and cerebral oedema suspected the moment a treated child develops headache with bradycardia.
Section 3Blood, Cancer and Immune Conditions
Sickle cell disease
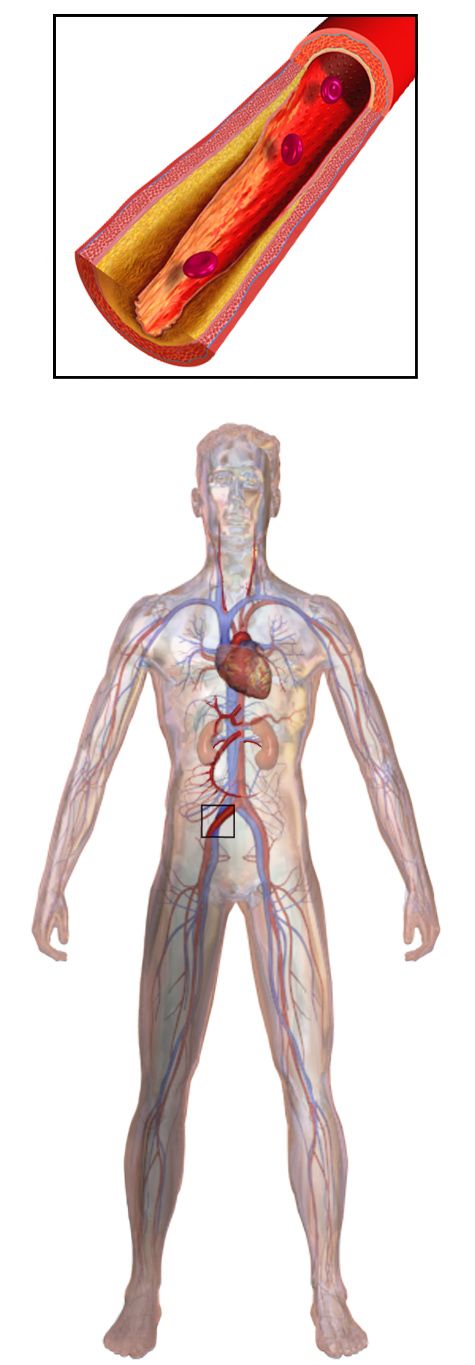
Sickle cell disease is autosomal recessive. A single substitution of valine for glutamic acid at position six of the beta-globin chain produces haemoglobin S, which polymerises when deoxygenated and deforms the red cell into a rigid crescent. Those cells obstruct microvasculature and are cleared early, giving the two halves of the disease: vaso-occlusion and chronic haemolytic anaemia. Symptoms do not appear until fetal haemoglobin declines, usually after four to six months, often first as dactylitis — painful swelling of the hands and feet.
| Event | Recognition | Priority nursing action |
|---|---|---|
| Vaso-occlusive (pain) crisis | Severe deep bone, joint, back or abdominal pain; low-grade fever | Analgesia on a schedule plus intravenous fluids at 1.5 times maintenance; warmth to the area; oxygen only if oxygen saturation is below 95 percent |
| Acute chest syndrome | New pulmonary infiltrate with fever, chest pain, cough, hypoxia, tachypnoea | Leading cause of death — escalate immediately; oxygen, antibiotics, analgesia that permits deep breathing, incentive spirometry every 2 h while awake, possible transfusion |
| Splenic sequestration | Rapidly enlarging spleen, sudden fall in haemoglobin, pallor, hypovolaemic shock; peak risk under 5 years | Life-threatening — volume resuscitation and urgent transfusion; teach caregivers to palpate the spleen daily at home |
| Aplastic crisis | Profound anaemia after parvovirus B19 infection with a low reticulocyte count | Transfusion support; isolate from pregnant staff and visitors |
| Overwhelming infection | Fever in a functionally asplenic child | Fever of 38.5 °C or higher is an emergency — blood culture and parenteral antibiotics without waiting for other results |
| Silent or overt stroke | Focal weakness, aphasia, seizure, declining school performance | Annual transcranial Doppler screening from age 2 to 16; chronic transfusion if velocities are elevated |
Prevention is where nursing changes the trajectory. Penicillin V prophylaxis begins by two months of age at 125 mg orally twice daily and increases to 250 mg twice daily from age three until at least age five. Pneumococcal, meningococcal, Haemophilus influenzae type b and annual influenza immunisation are non-negotiable. Hydroxyurea raises fetal haemoglobin and markedly reduces crises, acute chest syndrome and transfusion need; it requires regular full blood counts because it suppresses the marrow, and it is teratogenic, which matters for adolescents. Families avoid dehydration, extremes of cold, high altitude, unpressurised flight and exhaustion. Meperidine is avoided for sickle pain because its metabolite normeperidine accumulates and lowers the seizure threshold.
Bleeding disorders and iron deficiency
Haemophilia A is an X-linked recessive deficiency of factor VIII, so it is expressed almost entirely in males and carried by females. It presents with prolonged bleeding after circumcision, easy bruising once the child begins to cruise, and haemarthrosis — joint bleeding that a young child reports as stiffness, warmth and a refusal to move the limb before pain is ever described. Treatment is factor replacement, given prophylactically in moderate and severe disease and on demand for bleeds; desmopressin can be used for mild haemophilia A. For an acute bleed, rest, ice, compression and elevation are applied while factor is prepared. Aspirin and non-steroidal anti-inflammatory drugs are avoided, intramuscular injections and rectal temperatures are avoided, and contact sports are replaced with swimming and cycling. The rule that saves lives: after a head injury, the child receives factor first and imaging second — treatment is never delayed for a scan.
Immune thrombocytopenia typically follows a viral illness by one to three weeks and presents in a well-looking child with petechiae, purpura and epistaxis. Most cases resolve spontaneously. Nursing care is protective — soft toothbrush, no rectal temperatures, no intramuscular injections, no contact sports, pressure to venepuncture sites for at least five minutes — with the greatest concern being intracranial haemorrhage when platelets fall below about 20,000/mm³.
Iron deficiency anaemia is the commonest nutritional deficiency of childhood. Risk peaks at 9 to 24 months and again in adolescence. The usual drivers are whole cow milk before 12 months, more than about 700 mL of cow milk daily in a toddler which displaces iron-rich foods and irritates the gut mucosa, and prolonged exclusive breastfeeding without iron supplementation after six months. Oral iron is prescribed as 3 to 6 mg/kg/day of elemental iron in one to three divided doses, given between meals with a source of vitamin C, through a straw or with a syringe toward the back of the mouth to limit dental staining, and the family warned that stools will turn black and tarry. Iron is a leading cause of fatal poisoning in children under six, so the bottle is stored locked and out of reach and the number of tablets in the house is kept small.
Childhood leukaemia and febrile neutropenia
Acute lymphoblastic leukaemia is the most common childhood malignancy, peaking between two and five years. The presentation follows directly from marrow crowding: pallor and fatigue from anaemia, bruising, petechiae and epistaxis from thrombocytopenia, and fever and recurrent infection from neutropenia, with bone and joint pain, lymphadenopathy and hepatosplenomegaly. Diagnosis is by bone marrow aspiration. Treatment runs through induction, consolidation and intensification, and a maintenance phase, totalling roughly two to three years, with intrathecal chemotherapy for central nervous system prophylaxis because systemic drugs do not cross the blood-brain barrier reliably.
Febrile neutropenia is the paediatric oncology emergency. Calculate the absolute neutrophil count: total white cell count multiplied by the sum of the percentage of segmented neutrophils and bands, divided by 100. A white count of 1,200/mm³ with 20 percent segs and 5 percent bands gives 1,200 × 0.25 = 300/mm³, which is severe neutropenia. A single temperature of 38.3 °C or a temperature of 38.0 °C sustained for an hour in a child with an absolute neutrophil count below 500 requires blood cultures and the first dose of broad-spectrum intravenous antibiotics within 60 minutes. The neutropenic child cannot mount classic signs — there may be no purulence, no infiltrate on film, no redness — so fever alone is the signal. No rectal temperatures, no suppositories, no live vaccines, no fresh flowers or standing water in the room, and meticulous hand hygiene by everyone entering.
Tumour lysis syndrome occurs as cells are destroyed early in treatment: potassium, phosphate and uric acid rise while calcium falls, threatening arrhythmia and acute kidney injury. Prevention is aggressive hydration with allopurinol or rasburicase, with close monitoring of electrolytes and urine output. Anticipatory guidance for families covers hair loss, mucositis, nausea, changed taste, and the fact that a child on chemotherapy who develops chickenpox exposure needs to be reported the same day.
Allergy and anaphylaxis
Anaphylaxis is a clinical diagnosis: acute onset of skin or mucosal involvement with either respiratory compromise or hypotension, or two or more organ systems involved after a likely allergen, or hypotension alone after a known allergen. The first action is intramuscular epinephrine into the anterolateral thigh — 0.01 mg/kg of the 1 mg/mL concentration to a maximum of 0.3 mg in a child and 0.5 mg in an adolescent or adult — repeated every 5 to 15 minutes as needed. Autoinjectors are supplied at 0.1 mg for the smallest infants where available, 0.15 mg for children roughly 7.5 to 25 kg, and 0.3 mg at 25 kg and above. Antihistamines relieve the rash and itch only, and corticosteroids do neither quickly; neither treats anaphylaxis and neither prevents a biphasic reaction, so they are adjuncts given after epinephrine and never instead of it — giving them first only delays the drug that works. Lay the child flat with legs elevated unless breathing is easier sitting, and never allow a child to stand or walk after epinephrine because sudden upright posture during hypovolaemia has caused arrest.
In sickle cell disease treat the crisis with hydration, scheduled analgesia and oxygen only when hypoxic, and treat fever and a rapidly enlarging spleen as emergencies; in oncology, fever with an absolute neutrophil count below 500 means cultures and antibiotics within 60 minutes; in anaphylaxis, intramuscular epinephrine comes before every other drug.
Section 4Neurologic, Musculoskeletal and Integumentary Conditions
Seizures and status epilepticus
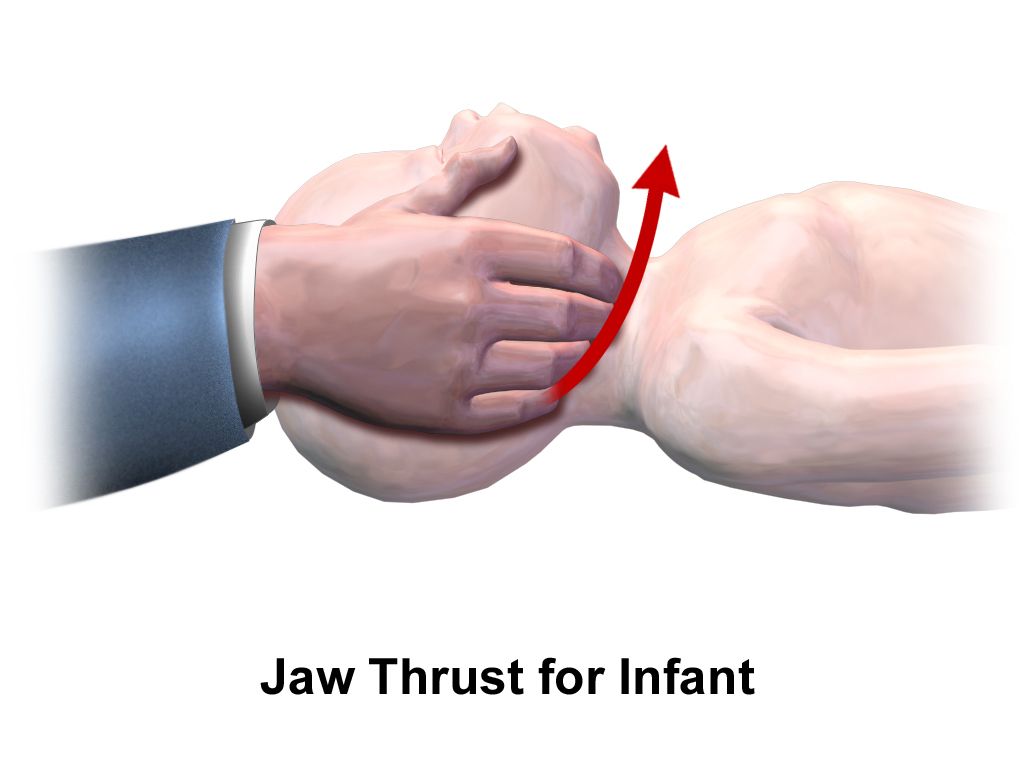
A simple febrile seizure occurs between six months and five years, is generalised, lasts under 15 minutes, and does not recur within 24 hours. It is frightening and usually benign. Nursing care during any seizure is the same: stay with the child, note the time, turn the child to the side, protect the head, loosen tight clothing, clear the surrounding area, and give oxygen if available. Nothing is ever put in the mouth, and the child is never restrained. Afterwards, document the onset, duration, movement pattern, eye deviation, incontinence, colour change and the length and character of the postictal period. Teach parents plainly that antipyretics reduce discomfort but have never been shown to prevent a recurrence, and that a child who has a febrile seizure is not thereby a child with epilepsy.
Status epilepticus is a seizure lasting five minutes or more, or repeated seizures without recovery of consciousness between them. Airway, oxygen, position, glucose check and timing come first, and then the drug ladder is followed on the clock.
| Time | Step | Drug and weight-based dose |
|---|---|---|
| 0–5 min | Stabilise | Airway positioning, oxygen, monitor, capillary glucose, intravenous access, note the time |
| 5–20 min | First-line benzodiazepine | Lorazepam 0.1 mg/kg IV, maximum 4 mg per dose; or midazolam 0.2 mg/kg IM, maximum 10 mg; or rectal diazepam 0.5 mg/kg (ages 2–5), 0.3 mg/kg (6–11), 0.2 mg/kg (12 and over), maximum 20 mg |
| 20–40 min | Second-line agent | Levetiracetam 60 mg/kg IV (maximum 4,500 mg); or fosphenytoin 20 mg phenytoin-equivalents/kg (maximum 1,500 mg PE); or valproate 40 mg/kg (maximum 3,000 mg) |
| Beyond 40 min | Refractory | Repeat second-line or begin anaesthetic infusion with intensive care involvement |
Anticipate respiratory depression after benzodiazepines and have bag-valve-mask and suction at the bedside before the drug is given. For a child on long-term anticonvulsants, teach that medication is never stopped abruptly, that adherence around illness and travel matters, and that helmets are worn for cycling and skating while unsupervised swimming and climbing at height are avoided.
Meningitis and rising intracranial pressure
Bacterial meningitis in a neonate is non-specific: temperature instability, poor feeding, lethargy, a weak or high-pitched cry, a bulging fontanelle and paradoxical irritability, meaning the infant cries more when picked up and comforted rather than less. Nuchal rigidity, the Kernig and Brudzinski signs, photophobia and severe headache belong to older children. Suspicion is enough to act. Droplet precautions begin immediately and continue for 24 hours after effective antibiotics start; blood cultures are drawn and antibiotics are given without waiting for lumbar puncture if the puncture will be delayed. Bacterial cerebrospinal fluid is cloudy with a high white count dominated by neutrophils, high protein and low glucose; viral fluid is clear with lymphocytes, normal glucose and mildly raised protein. Close household and childcare contacts of a child with meningococcal disease require chemoprophylaxis with rifampicin or ceftriaxone.
Rising intracranial pressure declares itself differently by age. In an infant expect a bulging tense fontanelle, separated sutures, an increasing head circumference, a high-pitched cry, irritability, poor feeding and the “setting sun” downward gaze. In an older child expect headache worst on waking, vomiting that may be effortless, diplopia, papilloedema, and a change in personality or school performance. The late signs are the Cushing triad — hypertension with a widening pulse pressure, bradycardia and irregular respiration — and by then herniation is imminent. Nursing management is to elevate the head of the bed about 30 degrees, keep the head midline and the neck unflexed, space nursing activities rather than clustering them so that pressure can return to baseline between interventions, keep the room quiet and dim, avoid suctioning, coughing, straining and hip flexion, and control fever and pain, all of which raise pressure.
A ventriculoperitoneal shunt fails in two ways: obstruction, which reproduces the signs of raised pressure, and infection, which presents with fever, redness along the tract, irritability and poor feeding within the first one to two months after placement. Post-operatively the child is usually positioned flat on the side opposite the valve to prevent too-rapid decompression, and head circumference is measured daily in infants.
Neural tube defects and cerebral palsy
Myelomeningocele is visible at birth as a sac over the spine containing meninges and neural tissue. Before surgical closure, usually within 24 to 72 hours, the infant is positioned prone or side-lying, the sac is covered with a sterile non-adherent dressing moistened with warm sterile normal saline and never allowed to dry, no nappy is placed over the sac, and the infant is handled with strict latex-free precautions from the first moment because these children develop latex allergy at very high rates with repeated exposure. Measure head circumference daily — hydrocephalus develops in the majority. Long-term care involves clean intermittent catheterisation, a bowel programme, and mobility support. Prevention belongs to the preconception period: 400 mcg of folic acid daily for all people who could become pregnant, and 4 mg daily for those with a previously affected pregnancy.
Cerebral palsy is a non-progressive disorder of movement and posture arising from an injury to the developing brain; the lesion does not worsen, though its musculoskeletal consequences do. Spastic forms predominate. Early clues include persistent primitive reflexes, hand preference before 12 months, scissoring of the legs, stiff or floppy tone, and delayed motor milestones. Nursing priorities are safety, communication and nutrition — these children aspirate readily, so upright positioning, thickened textures where indicated and unhurried feeding matter, and growth is monitored closely. Antispasmodics, botulinum toxin injection, intrathecal baclofen, orthoses and orthopaedic surgery all have a place. Speak to the child according to age, not according to motor ability; motor impairment is not intellectual impairment.
Bones, casts and skin
Children’s bones bend before they break, producing greenstick and buckle fractures, and their growth plates are weaker than the surrounding ligament, so a physeal injury occurs where an adult would sprain. Neurovascular assessment distal to any injury, cast or traction is the recurring nursing task: pain, pallor, pulselessness, paraesthesia and paralysis. The earliest and most reliable sign of compartment syndrome, however, is none of the classic five — it is pain out of proportion to the injury, unrelieved by opioids, and worsened by passive stretch of the digits. Report it immediately, loosen or bivalve the cast, and keep the limb at heart level rather than elevated, because elevation above the heart reduces arterial inflow to an already ischaemic compartment.
Some fractures are a safeguarding question. A fracture in a child who is not yet cruising or walking, posterior rib fractures, metaphyseal corner fractures, multiple fractures at different stages of healing, or an explanation that does not match the injury pattern all require escalation and documentation in objective, non-accusatory language. The same is true of a scald with a clean stocking-glove demarcation and no splash marks. The single most useful question is whether the injury fits the child’s developmental stage: an infant who cannot yet roll did not roll off the sofa, and a child too short to reach the tap did not run their own bath. Reporting is a mandatory legal duty triggered by reasonable suspicion, not by proof or certainty — the nurse reports and the investigating agency determines what happened, and no colleague, manager or provider can waive that duty. Keep the child safe, record the caregiver’s account verbatim and your own observations factually, and do not interrogate the family or announce the referral as an accusation.
Developmental dysplasia of the hip is screened with the Ortolani and Barlow manoeuvres in the first weeks of life, and later by asymmetric thigh and gluteal folds, limited hip abduction and a shortened femur on the affected side. The Pavlik harness is worn 23 hours a day for infants under about six months; parents are taught to check skin under the straps, dress the infant in a shirt and knee socks beneath the harness, and never to adjust the straps themselves. In adolescence, slipped capital femoral epiphysis presents in a heavier teenager as hip or referred knee pain with an outwardly rotated limb and limited internal rotation, and the immediate action is strict non-weight-bearing pending surgical fixation. Idiopathic scoliosis is screened with the Adams forward-bend test; bracing is typically considered for curves of 25 to 45 degrees in a growing child and surgical fusion above about 45 to 50 degrees, after which nursing care centres on log-rolling, neurovascular checks and effective analgesia.
Duchenne muscular dystrophy is X-linked, caused by absent dystrophin. Between three and five years the child shows a waddling gait, frequent falls, calf pseudohypertrophy and the Gowers sign of walking the hands up the thighs to rise. Creatine kinase is markedly elevated. Corticosteroids slow the decline; the eventual causes of death are cardiomyopathy and respiratory failure, so cardiac and pulmonary surveillance begin long before symptoms.
Atopic dermatitis is managed by soak-and-seal: a short lukewarm bath, a gentle pat dry, and emollient applied within three minutes, twice or more daily. Topical corticosteroid potency is matched to the site, with only the lowest potencies used on the face, neck and skin folds. Keep nails short, use cotton clothing, avoid fragranced products and overheating, and treat the itch, because scratching is what breaks skin and invites infection.
Treat a seizure lasting five minutes as status epilepticus and give a weight-based benzodiazepine with airway equipment ready; recognise the Cushing triad as a late sign of intracranial pressure rather than a first one; and remember that the earliest sign of compartment syndrome is pain out of proportion and on passive stretch, with the limb kept at heart level, not above it.
Section 5Weight-Based Safety and Living with Chronic Illness
The arithmetic that keeps a child safe
Every paediatric medication order is a calculation, and the nurse is the last person who can catch an error before it reaches the child. Three habits prevent most harm. First, the weight is measured in kilograms on admission and recorded in kilograms only — never pounds, never a weight reported by a parent from memory, never an estimate. Second, every dose is checked against the published safe dose range for that drug per kilogram per dose and per day. Third, every paediatric dose is compared with the maximum adult dose, because a large adolescent multiplied by a per-kilogram figure can easily exceed what any adult would receive.
| Scenario | Arithmetic | Decision |
|---|---|---|
| Amoxicillin 90 mg/kg/day divided every 12 h for an 18 kg child | 90 × 18 = 1,620 mg/day; 1,620 ÷ 2 = 810 mg per dose. Suspension is 400 mg/5 mL, so 810 ÷ 400 × 5 = 10.1 mL | Safe; measure 10.1 mL in an oral syringe |
| Ibuprofen ordered as 400 mg for a 22 kg child | 400 ÷ 22 = 18.2 mg/kg per dose; safe range is 5–10 mg/kg per dose | Hold and clarify — the order is roughly double the upper limit |
| Acetaminophen 15 mg/kg for a 72 kg adolescent | 15 × 72 = 1,080 mg | Exceeds the 1,000 mg maximum single adult dose — give 1,000 mg. The adult ceiling always wins |
| Morphine 0.1 mg/kg IV for a 12 kg toddler | 0.1 × 12 = 1.2 mg | Safe; high-alert drug — independent double check by a second nurse before administration |
| Epinephrine 0.01 mg/kg IM for an 18 kg child in anaphylaxis | 0.01 × 18 = 0.18 mg of the 1 mg/mL solution | Give 0.18 mL, or use the 0.15 mg autoinjector supplied for 7.5–25 kg |
Maintenance fluid volume is calculated by the Holliday-Segar method, expressed hourly as the 4-2-1 rule: 4 mL/kg/h for the first 10 kg of body weight, 2 mL/kg/h for the second 10 kg, and 1 mL/kg/h for each kilogram above 20. Worked for a 26 kg child: the first 10 kg gives 10 × 4 = 40 mL/h; the second 10 kg gives 10 × 2 = 20 mL/h; the remaining 6 kg gives 6 × 1 = 6 mL/h; total 66 mL/h. The daily equivalent confirms it — 100 mL/kg for the first 10 kg is 1,000 mL, 50 mL/kg for the second 10 kg is 500 mL, and 20 mL/kg for the last 6 kg is 120 mL, giving 1,620 mL per day, or 67.5 mL/h. Maintenance fluid for children beyond the neonatal period should be isotonic — 0.9 percent sodium chloride or lactated Ringer solution, usually with 5 percent dextrose — because hypotonic maintenance fluid has repeatedly caused hospital-acquired hyponatraemia and seizures. Potassium is added only once the child is passing urine. Maintenance is added to, not substituted for, deficit replacement and ongoing losses.
Cystic fibrosis as the model chronic condition
Cystic fibrosis is autosomal recessive, caused by mutations in the CFTR chloride channel gene on chromosome 7, producing abnormally viscous secretions in the airway, pancreas, biliary tree, intestine and reproductive tract. It may declare itself at birth as meconium ileus, or later as recurrent respiratory infection, steatorrhoea, growth faltering despite a large appetite, and a salty taste to the skin. Diagnosis is by newborn screening confirmed with a sweat chloride above 60 mmol/L on two occasions, and by genotyping.
Daily care runs on sequence. Airway clearance — chest physiotherapy, high-frequency chest wall oscillation vest, positive expiratory pressure devices, autogenic drainage — is performed before meals rather than after, to avoid vomiting, and bronchodilators precede it while dornase alfa and hypertonic saline are timed to the clearance session. Pancreatic enzyme replacement is taken with every meal and every fat-containing snack, within about 30 minutes of eating, at 500 to 2,500 lipase units/kg per meal and never exceeding 10,000 lipase units/kg/day, a ceiling set because higher doses have been associated with fibrosing colonopathy. Capsules may be opened onto a small amount of acidic soft food such as apple sauce and must not be crushed or chewed. The diet is high in calorie and protein at roughly 110 to 200 percent of the usual requirement, with fat-soluble vitamins A, D, E and K supplemented and additional salt provided in heat and during exercise. CFTR modulator therapy has transformed outcomes for eligible genotypes.
Pain, development and the family as partner
Children feel pain fully and report it differently, so the tool must match the child. Use the FLACC behavioural scale for infants and children up to about three years and for any non-verbal child; the Wong-Baker FACES or Oucher scale from roughly three to seven years; and a 0 to 10 numeric scale from about age eight. Believe the score. Chronic under-treatment of paediatric pain is well documented and it is a nursing failure, not a physiological curiosity. Combine pharmacological management with sucrose and non-nutritive sucking in infants, distraction, guided imagery, warmth, positioning, and above all parental presence.
Development shapes every explanation. A toddler fears separation and needs a parent present, brief warning and a comfort object. A preschooler thinks magically and may believe illness is a punishment, so say plainly that nothing they did or thought caused this. A school-age child wants to know how the body works and to have a job to do — holding the tape, counting to three. An adolescent needs privacy, confidentiality within legal limits, honest information about how treatment affects appearance and social life, and progressive ownership of their own regimen with continuing adult oversight. Perform painful procedures in a treatment room rather than the bed, so the bed remains safe.
Language is clinical care. Describe what is happening rather than assigning blame: an infant is “taking small volumes and tiring at the breast”, not “a difficult feeder”; a family is “managing three medicines across two households and missing evening doses”, not “non-compliant”. That reframing is not politeness — it points at the actual problem, which is usually a solvable one of access, understanding, schedule or cost. Use the family’s words for themselves, whether that is mother, birthing parent, dad, carer or grandparent, and treat the person who does the daily work of the illness as a member of the team.
Escalation and delegation
Escalate with SBAR so that the urgency is unmistakable. Situation: “This is Aisha, the nurse on 4 East, calling about Leo, 4 years old, weight 16 kg, one hour into insulin infusion for DKA.” Background: “He presented with a glucose of 620 mg/dL and pH 7.08, he has had 160 mL of normal saline as a 10 mL/kg bolus, and the insulin infusion is running at 0.1 units/kg/h.” Assessment: “In the last 20 minutes his heart rate has fallen from 148 to 82, blood pressure has risen from 96/58 to 124/78, he is complaining of headache and he has vomited twice. I believe he is developing cerebral oedema.” Recommendation: “I need you at the bedside now, I have raised the head of the bed, I am requesting an order for hypertonic saline or mannitol, and I have activated the rapid response team.”
| Task | Assistive personnel | Licensed practical or vocational nurse | Registered nurse only |
|---|---|---|---|
| Vital signs on a stable child | Yes, reports values to the RN | Yes | Interprets and acts on them |
| Daily weight, intake and output, nappy weighing | Yes | Yes | Evaluates the trend |
| Feeding a stable child, hygiene, positioning, ambulation | Yes | Yes | — |
| Oral rehydration by an established plan in a stable child | May offer fluid and record volume | Yes | Sets and revises the plan |
| Routine oral and intramuscular medication, stable gastrostomy feeds, tracheostomy care on a stable child | No | Yes, within scope and policy | Retains high-alert drugs, titrations and intravenous push |
| Initial and ongoing assessment, neurovascular checks, pain reassessment after intervention | No | Contributes data | Yes |
| Patient and family teaching and evaluation of learning | No | Reinforces established teaching | Yes |
| Any care of an unstable or deteriorating child | No | No | Yes |
Weigh the child in kilograms, calculate every dose per kilogram, verify it against the safe range and then against the maximum adult dose, run maintenance fluid by the 4-2-1 rule with isotonic solution, and keep assessment, teaching, evaluation and the unstable child within registered nurse practice.
The chapter in one breath
Children compensate brilliantly and then fail suddenly. Their larger extracellular water compartment and faster turnover make dehydration the common final pathway of ordinary illness, so grade it by percentage weight lost, rehydrate orally at 50 to 100 mL/kg over four hours when the child can drink, and reserve the 20 mL/kg isotonic bolus for severe loss — remembering that tachycardia, delayed capillary refill and altered alertness arrive long before hypotension, which in a child aged one to ten is anything below 70 plus twice the age in years. Across systems the pattern repeats: mechanism, then assessment, then management, then the complication that kills. Fluids before insulin in ketoacidosis, with cerebral oedema suspected when a treated child develops headache and bradycardia. Hydration, scheduled analgesia and hypoxia-triggered oxygen for sickle crisis, with acute chest syndrome and splenic sequestration as the emergencies. Cultures and antibiotics within 60 minutes for fever with a neutrophil count under 500. A benzodiazepine at five minutes for status epilepticus. Pain on passive stretch as the earliest sign of compartment syndrome. Holding it all together is arithmetic — kilograms, safe dose ranges, the maximum adult dose that always wins, and the 4-2-1 rule — and a family whose daily work with the illness makes them colleagues rather than visitors.
Words worth knowing
| Term | What it means |
|---|---|
| 4-2-1 rule | Hourly maintenance fluid calculation: 4 mL/kg/h for the first 10 kg, 2 mL/kg/h for the second 10 kg, 1 mL/kg/h for every kilogram beyond 20 kg. |
| Absolute neutrophil count | Total white cell count multiplied by the combined percentage of segmented neutrophils and bands, divided by 100; below 500/mm³ is severe neutropenia. |
| Acute chest syndrome | New pulmonary infiltrate with fever, chest pain and hypoxia in sickle cell disease; the leading cause of death and an immediate escalation. |
| Compartment syndrome | Rising pressure within a fascial compartment causing ischaemia; earliest sign is pain out of proportion and on passive stretch, and the limb is kept at heart level. |
| Currant jelly stool | Blood and mucus passed in intussusception; a late finding whose absence does not exclude the diagnosis. |
| Cushing triad | Hypertension with widened pulse pressure, bradycardia and irregular respiration — a late and ominous sign of raised intracranial pressure. |
| Diabetic ketoacidosis | Glucose above 200 mg/dL with pH below 7.3 or bicarbonate below 15 mmol/L plus ketosis; treated with fluids first, then an insulin infusion without a bolus. |
| FLACC scale | Behavioural pain tool scoring face, legs, activity, cry and consolability, used for infants, toddlers and non-verbal children. |
| Gowers sign | Walking the hands up the thighs to rise from the floor, indicating proximal muscle weakness as in Duchenne muscular dystrophy. |
| Haemarthrosis | Bleeding into a joint, the characteristic bleed of haemophilia, first reported by a young child as stiffness and refusal to move the limb. |
| Holliday-Segar method | Daily maintenance fluid calculation: 100 mL/kg for the first 10 kg, 50 mL/kg for the second 10 kg, 20 mL/kg thereafter. |
| Hypochloraemic metabolic alkalosis | The acid-base picture of pyloric stenosis, produced by loss of gastric hydrochloric acid; corrected before surgery. |
| Nephrotic syndrome | Massive proteinuria, hypoalbuminaemia, oedema and hyperlipidaemia; treated with corticosteroids and monitored by daily weight. |
| Oral rehydration solution | Glucose-electrolyte solution at physiological osmolality that treats mild and moderate dehydration, given in small frequent volumes even when the child is vomiting. |
| Paradoxical irritability | An infant who cries more, not less, when picked up and comforted — a meningeal sign in infancy. |
| Pavlik harness | Abduction device for developmental dysplasia of the hip in infants under about six months, worn 23 hours daily and adjusted only by the clinician. |
| Splenic sequestration | Sudden pooling of blood in the spleen in sickle cell disease with rapid anaemia and hypovolaemic shock; caregivers are taught to palpate the spleen. |
| Status epilepticus | A seizure lasting five minutes or longer, or repeated seizures without recovery, treated with a weight-based benzodiazepine on the clock. |
| Tumour lysis syndrome | Rapid cell breakdown producing high potassium, phosphate and uric acid with low calcium; prevented by hydration and urate-lowering therapy. |
| Vaso-occlusive crisis | Painful episode from microvascular obstruction by sickled cells, managed with hydration, scheduled analgesia and oxygen only when hypoxic. |