Health Assessment & Nursing Fundamentals
The Nurse, Professional Practice and Scope
In a few months you will walk into a room, put your hands on a stranger, and decide whether what you are seeing is normal. Everything that follows in this book — every technique, every number, every red flag — rests on a license that is granted by a state, defined by a statute, and revocable. This chapter is about that foundation. It explains what a nursing license actually authorizes, where the boundary of your scope sits and how to test whether an action falls inside it, what you may hand to an assistant and what never leaves you, and how the standards of practice, the Code of Ethics and the law of negligence converge at the bedside. It ends where every chapter in this book ends: with the findings that mean stop, escalate now, and the exact words — SBAR — you will use to escalate them.
By the end of this chapter you can
- Distinguish the legal authority and educational preparation of the CNA, LPN/LVN, RN and APRN, and explain what the NCLEX-RN and the Nurse Licensure Compact do.
- Locate your Nurse Practice Act and apply a three-question scope of practice test before performing any unfamiliar task.
- Apply the five rights of delegation and correctly sort tasks into what may go to UAP, what may go to an LPN/LVN, and what must stay with the RN.
- Name the six ANA Standards of Practice and the four elements of negligence, and describe the nurse’s specific role in informed consent and in restraint use.
- Perform and sequence the four assessment techniques — inspection, palpation, percussion, auscultation — and state the abdominal exception and why it exists.
- State adult vital-sign ranges to the exact number and adjust expected values for infants, children, pregnancy and older adults.
- Assess for cyanosis, jaundice, pallor and erythema in patients of any skin tone using oral mucosa, conjunctivae, sclerae and palms/soles.
- Rewrite a vague chart entry as a precise, defensible one, and correct a documentation error legally.
- Recognize adult and pediatric red flags that require escalation now, and deliver a complete SBAR report up the chain of command.
Section 1Becoming and Staying a Nurse
The credentials, and what each one legally means
Students use the word “nurse” loosely; the law does not. A certified nursing assistant (CNA) holds a certification, not a license, after roughly four to sixteen weeks of training. A CNA is authorized to provide personal care and to collect certain routine data. A licensed practical nurse or licensed vocational nurse (LPN/LVN) completes a twelve- to eighteen-month program and passes the NCLEX-PN. An LPN holds a license and a defined, narrower scope: in most states an LPN may administer most medications, perform sterile dressing changes and tracheostomy care, insert a urinary catheter, and gather data — but works under the direction of an RN or a provider and does not perform the initial comprehensive assessment or independently formulate the plan of care.
The registered nurse (RN) comes from one of three routes: a diploma program, an associate degree in nursing (ADN/ASN), or a bachelor of science in nursing (BSN). All three sit for the same examination, the NCLEX-RN, and all three receive the same license with the same legal scope. The degrees are not legally different; they are professionally different. The BSN adds community health, leadership, research literacy and statistics, and it is the entry point for graduate study and for Magnet-designated employers. An advanced practice registered nurse (APRN) — nurse practitioner, clinical nurse specialist, certified registered nurse anesthetist, or certified nurse-midwife — holds a graduate degree, national certification, and a second, separate state authorization that permits diagnosis and, in most states, prescribing.
| Credential | Preparation | Examination | What it authorizes |
|---|---|---|---|
| CNA / UAP / PCT | Weeks to a few months; state registry | State competency exam (certification, not licensure) | Hygiene, feeding, ambulation, positioning, intake and output, weights, and routine vital signs on stable patients — all delegated by an RN |
| LPN / LVN | 12–18 months, practical nursing program | NCLEX-PN | Data collection, most medication administration, sterile procedures, wound and ostomy care, reinforcement of teaching — under RN or provider direction |
| RN (ADN, diploma or BSN) | 2–4 years | NCLEX-RN | Comprehensive assessment, nursing diagnosis, planning, implementation, evaluation, patient teaching, delegation and supervision |
| APRN (NP, CNS, CRNA, CNM) | Master’s or doctoral degree plus national certification | NCLEX-RN plus certification exam | Advanced assessment, diagnosis, ordering and interpreting tests, and prescribing (scope varies by state: full, reduced or restricted practice) |
The Nurse Practice Act and your board of nursing
Every state and territory has a Nurse Practice Act (NPA) — an actual statute passed by that state’s legislature. The NPA defines who may call themselves a nurse, what nursing practice includes, the grounds for discipline, and it creates the board of nursing (BON), the agency that issues your license and can suspend or revoke it. The BON then writes administrative rules and advisory opinions that fill in the detail the statute leaves open. This is the single most important document in your professional life and most students never read it. Read yours before you start clinicals. It is free, it is online, and it is written in plain enough English.
The National Council of State Boards of Nursing (NCSBN) is the organization the boards jointly own; it develops the NCLEX and administers the Nurse Licensure Compact (NLC). A multistate license issued by a compact state lets you practice, physically or by telehealth, in every other compact state without a second license. It does not exempt you from the practice act of the state where the patient is located — the rule is that you practice under the law of the state where the patient is, not where you are sitting. Licenses are renewed on a state-set cycle, usually every two years, generally with continuing education and sometimes practice-hour requirements.
Discipline is real and it is public. The most common paths to a board action are diversion of controlled substances, practicing while impaired, falsification of documentation, patient abandonment (leaving an assignment without transferring care to a qualified person), boundary violations, and practicing outside scope. Most states also make you a mandatory reporter of suspected abuse or neglect of a child, an older adult, or a dependent adult — a duty that belongs to you personally and is not discharged by telling the charge nurse and letting it go.
What professional practice actually asks of you
Licensure is the floor. The profession expects more, and the framework most schools use is QSEN — Quality and Safety Education for Nurses — with six competencies: patient-centered care, teamwork and collaboration, evidence-based practice, quality improvement, safety, and informatics. These are not slogans. Patient-centered care means the plan is built around what the patient values, not around what is convenient for the unit. Evidence-based practice means that when you were taught something in 2018 and the evidence changed in 2024, you change. Informatics means you can find the answer in the chart and in the literature quickly, and that you understand the electronic record is a legal document and a data source, not a typing chore.
Professional practice also means accountability that does not transfer. You are accountable for the assessment you performed, the medication you pushed, the finding you did or did not report, and the task you delegated. “The provider ordered it” is not a defense if the order was clearly unsafe — a nurse who administers an obviously wrong dose shares liability with the prescriber. The correct action when an order looks wrong is to hold it, clarify it with the prescriber, and document the clarification.
Your authority to practice comes from a state statute, the Nurse Practice Act, enforced by a board of nursing — not from your employer, your degree or your job description.
Section 2Scope, Delegation and the Team
Three questions before you do anything unfamiliar
New nurses get into trouble not by doing something malicious but by doing something helpful that was not theirs to do. Before you perform a task you have not performed before, run three questions in order. One: is it within my state’s Nurse Practice Act and board rules? If the statute or the board says no, stop — nothing downstream can rescue it. Two: is it within my employer’s policy, and do I have an order or protocol if one is required? Facilities lawfully restrict practice below the statutory ceiling; a hospital may decide RNs do not push a given medication even where the state permits it. Three: am I personally competent — educated, trained, and validated — to do this safely right now? A yes to the first two and a no to the third still means you do not do it; you find someone who can and you arrange to be taught.
The most common scope traps in the first year are administering an IV push medication in a facility that does not credential RNs for it, titrating a drip without a protocol, taking a verbal order in a non-emergency situation when policy forbids it, performing a skill you watched but were never checked off on, and “just” suturing, casting, or adjusting a device because a provider asked and was busy. In every one of these, the safe answer is the same sentence: “I’m not checked off on that — I’ll get someone who is.” No one has ever been disciplined for saying it.
Who may do what
Two words get confused constantly. Assignment is transferring both the responsibility and the accountability for tasks that are already within the receiving person’s own scope and job description — a charge nurse assigning four patients to an RN. Delegation is transferring responsibility for performing a specific task to someone whose scope does not otherwise include it, while you keep the accountability. If a UAP takes a blood pressure you delegated and it is wrong, the number is your problem. Supervision is the ongoing monitoring that follows delegation; you cannot delegate and then disappear.
| Task | UAP / CNA | LPN / LVN | RN only |
|---|---|---|---|
| Vital signs on a stable patient | Yes (RN interprets) | Yes | — |
| Vital signs on an unstable or newly admitted patient | No | No if the patient is unstable; on a stable new admission an LPN may collect data under RN direction | Yes — RN performs and interprets |
| Bathing, feeding, oral care, positioning, ambulation of a stable patient | Yes | Yes | — |
| Intake and output, daily weight, specimen collection, point-of-care glucose (state-dependent) | Yes | Yes | — |
| Oral, subcutaneous and intramuscular medications | No | Yes (most states) | Yes |
| Sterile dressing change, tracheostomy care, urinary catheter insertion, enteral feeding | No | Yes | Yes |
| IV push medication, blood product administration, central line care, titrating drips | No | No (rare state exceptions) | Yes |
| Initial and ongoing assessment, nursing diagnosis, care planning | No | No — may collect data only | Yes |
| Patient and family teaching, discharge education | No | May reinforce teaching already given | Yes — initial teaching |
| Evaluation of the response to an intervention | No | No | Yes |
| Any care of an unstable or unpredictable patient | No | No | Yes |
The five rights of delegation
NCSBN and the ANA describe five checks, and they are worth memorizing because NCLEX tests them relentlessly. Right task — it is repetitive, predictable, low-risk, and does not require nursing judgment. Right circumstance — this patient is stable and the setting is appropriate; the same task on a different patient may not be delegable. Right person — this specific individual has the training and demonstrated competence, not merely the job title. Right direction and communication — you state the task, the patient, the expected method, the deadline, and exactly what to report back and when. Right supervision and evaluation — you follow up, you obtain the result, and you evaluate the outcome yourself.
Vague delegation is unsafe delegation. Compare “Can you get vitals on room 12?” with “Please take a manual blood pressure on Mr. Ruiz in 12 within the next ten minutes, sitting, left arm, and tell me the number right away if the systolic is under 100 or over 160.” The second sentence gives the task, the patient, the method, the timeframe and the reporting threshold. It takes eight seconds longer and it is the difference between delegation and hoping.
Four things never leave the RN, and this is the sentence to carry into the exam and into practice: assessment, nursing diagnosis and planning, teaching, and evaluation — plus anything at all involving an unstable patient. A UAP may gather a number; only the RN decides what that number means. If a UAP reports a blood pressure of 86/50, the delegated task was completed correctly and the clinical problem is entirely yours.
You may delegate a task but never the accountability for it, and assessment, teaching, evaluation and unstable patients never leave the registered nurse.
Section 3Standards, Ethics and the Law at the Bedside
The standards you will be measured against
When a case is reviewed, the question is not whether you meant well — it is whether you met the standard of care, defined as what a reasonably prudent nurse with similar preparation would have done in similar circumstances. That standard is built from the ANA Nursing: Scope and Standards of Practice, your state’s NPA, facility policy, manufacturer instructions, and current evidence. The six Standards of Practice map exactly onto the nursing process and are the spine of the next chapter: assessment, diagnosis, outcomes identification, planning, implementation and evaluation. Layered on top are the Standards of Professional Performance — ethics, advocacy, respectful and equitable practice, communication, collaboration, leadership, education, scholarly inquiry, quality of practice, professional practice evaluation, resource stewardship and environmental health.
Standards are not aspirational language. If a patient falls and the record shows no fall-risk screening was documented on admission, the deviation from the assessment standard is the case. This is why documentation is not clerical work: in a legal review, care that was not documented is treated as care that was not given.
Ethical principles and the Code of Ethics
The ANA Code of Ethics for Nurses is the profession’s non-negotiable statement of obligation. Its provisions establish that the nurse practices with compassion and respect for every person, that the nurse’s primary commitment is to the patient, that the nurse advocates for and protects the patient’s rights and safety, and that the nurse owes the same duties to self as to others — a provision that matters when you are asked to take a ninth patient or a third consecutive double shift.
| Principle | What it obligates | At the bedside |
|---|---|---|
| Autonomy | Respect the patient’s right to decide | A competent adult may refuse a medication you are certain they need; you document the refusal and notify the provider |
| Beneficence | Act for the patient’s good | Repositioning a patient at 0200 because pressure injuries form in hours |
| Nonmaleficence | Do no harm | Holding a beta blocker when the apical pulse is 48 and calling the prescriber |
| Justice | Distribute care fairly | The uninsured patient receives the same pain assessment and the same response as everyone else |
| Fidelity | Keep your promises | You said you would return in twenty minutes with the pain medication — you return in twenty minutes |
| Veracity | Tell the truth | You do not tell a patient “this won’t hurt” when it will; you do not chart what you did not do |
The legal floor: negligence, consent, privacy and restraints
Negligence is failing to act as a reasonably prudent person would; malpractice is professional negligence. A plaintiff must prove four elements, all of them: duty (you had a nurse–patient relationship), breach (you departed from the standard of care), causation (that breach caused the harm), and damages (real injury occurred). Missing one element ends the case. Also know the intentional torts, because they are quieter and easier to commit: assault (threatening unwanted contact — “hold still or I will hold you down”), battery (the contact itself, including performing a procedure a patient refused), false imprisonment (restraining or confining without order or emergency justification), defamation (libel in writing, slander in speech), and invasion of privacy.
Informed consent belongs to the person performing the procedure. The provider must explain the diagnosis, the nature and purpose of the procedure, the risks and benefits, the alternatives, and the consequences of refusing. The nurse’s role is narrow and specific: verify that the consent form is signed, that the signature is voluntary, and that the patient can describe in their own words what is about to happen — then witness the signature. If the patient says “they’re taking out my gallbladder, I think, or maybe part of my colon,” you stop, you do not have them sign, and you page the provider. Consent obtained after a sedating premedication is not valid consent.
HIPAA protects health information; the rule of practice is minimum necessary and need-to-know. The most frequent violations by students are elevator and hallway conversations, looking up a patient you are not assigned to, and photographing anything on a personal phone. Restraints are a last resort, never a response to short staffing, convenience or punishment, and are used only after less restrictive alternatives have been tried and documented. They require a provider order that is never written as needed (no PRN restraint orders) and that is time-limited: for violent or self-destructive behavior, up to 4 hours for an adult, 2 hours for ages 9–17, and 1 hour for children under 9, with a face-to-face evaluation of the patient by a physician or trained licensed independent practitioner within 1 hour of initiation. Use the least restrictive effective type, and monitor frequently with release, repositioning, range of motion, fluids, toileting, circulation and skin checks. Applying restraints without an order, outside an immediate emergency, is false imprisonment.
You are judged against the standard of care — what a reasonably prudent nurse would have done — and the record of what you assessed, reported and documented is the evidence of whether you met it.
Section 4The Core Skill: Assessing, Measuring, Documenting
The four techniques and the order they go in
Every regional examination in this textbook uses the same four techniques in the same order. Inspection comes first and is the most underused: you look, deliberately and with adequate light, comparing side to side, before you touch anything. Inspect for color, symmetry, contour, movement, lesions, drainage and effort. Most abnormal findings are visible before they are palpable. Palpation comes second. Use the finger pads for texture, pulses, moisture, tenderness and masses; the ulnar or palmar surface for vibration such as thrills and fremitus; and the dorsum of the hand for temperature, because it is more sensitive to heat. Light palpation depresses about 1 cm; deep palpation depresses about 4–5 cm and is used to identify organs and deep masses. Palpate tender areas last, and warm your hands.
Percussion comes third. Press the distal phalanx of the non-dominant middle finger firmly on the skin, keep the other fingers off the surface, and strike that phalanx sharply with the tip of the dominant middle finger using wrist motion only, withdrawing immediately. You are listening for whether the tissue underneath is air-filled, fluid-filled or solid: resonance over normal lung, hyperresonance over trapped air as in emphysema or pneumothorax, tympany over the gastric bubble and the intestines, dullness over the liver, a full bladder or consolidated lung, and flatness over bone and muscle. Auscultation comes fourth. Use the diaphragm pressed firmly for high-pitched sounds — breath sounds, bowel sounds, normal heart sounds S1 and S2 — and the bell held lightly for low-pitched sounds such as S3, S4, and bruits. Place the stethoscope on skin, never over a gown, and stop moving and talking while you listen.
There is one exception, and it is the abdomen. The abdominal sequence is inspect, auscultate, percuss, palpate. Auscultation is moved ahead of percussion and palpation because pressing on the abdomen mechanically stimulates or suppresses peristalsis and changes the bowel sounds you are about to grade. If you palpate first, the bowel sounds you then document are an artifact you created. Auscultate all four quadrants, beginning in the right lower quadrant near the ileocecal valve where sounds are usually most active; normal is 5–30 gurgles per minute, and before you may document absent bowel sounds you must listen for a full 5 minutes in that quadrant. Sequence errors like this one are exactly the kind of mistake that looks trivial on paper and produces a false finding in a real chart.
The numbers you must know cold
You cannot recognize abnormal until normal is automatic. These are adult values; commit them to memory now, because during a rapid response nobody will let you look them up.
| Measure | Expected adult value | Abnormal | What the abnormal finding suggests |
|---|---|---|---|
| Temperature (oral) | 36.5–37.5 °C (97.7–99.5 °F); mean 37.0 °C (98.6 °F) | Fever ≥ 38.0 °C (100.4 °F); hypothermia < 35.0 °C (95.0 °F) | Infection, inflammation, drug reaction; hypothermia in sepsis, exposure, hypothyroidism |
| Temperature by route | Rectal about 0.5 °C (0.9 °F) above oral; axillary about 0.5 °C below oral; tympanic and temporal approximate core | Route not documented | Comparing an axillary reading to a rectal one creates false trends — always chart the route |
| Pulse (apical or radial, full 60 s if irregular) | 60–100 beats/min, regular | Bradycardia < 60; tachycardia > 100; irregular rhythm; pulse deficit | Bradycardia: beta blockers, digoxin toxicity, heart block. Tachycardia: pain, fever, hypovolemia, hypoxia, anxiety |
| Respirations (count 30–60 s, unobserved) | 12–20 breaths/min, quiet, effortless, regular | < 12 or > 20; accessory muscle use; nasal flaring; retractions | Bradypnea: opioids, rising intracranial pressure. Tachypnea: hypoxia, acidosis, pain, anxiety, pulmonary embolism |
| Blood pressure | Less than 120/80 mm Hg; pulse pressure 30–40 mm Hg; mean arterial pressure at least 65 mm Hg (systolic plus twice diastolic, divided by three) | Elevated 120–129 / under 80; stage 1 130–139 or 80–89; stage 2 at or above 140 or 90; crisis above 180 and/or above 120; hypotension below 90 systolic | Cuff bladder width about 40% of arm circumference and length about 80%; a cuff too small or wrapped too loosely falsely raises the reading and one too large falsely lowers it. Feet flat, back supported, arm at heart level, no talking, five minutes seated. Hypotension with tachycardia suggests hypovolemia or sepsis |
| Orthostatic vitals | Minimal change on standing | Systolic drop ≥ 20 mm Hg or diastolic drop ≥ 10 mm Hg within 3 minutes of standing, or a rise in pulse ≥ 20 | Volume depletion, bleeding, antihypertensives, autonomic dysfunction — high fall risk |
| Oxygen saturation | 95–100% on room air | Below 95%; below 90% is hypoxemia (roughly PaO2 60 mm Hg) | In chronic CO2 retention the target is commonly 88–92% — verify the ordered target before titrating oxygen |
| Pain | Self-report on a 0–10 numeric scale, assessed with every vital-sign set (the older label “fifth vital sign” has been retired, because a score alone is not an order for an opioid) | Any score above the patient’s stated goal | Nonverbal patients require a behavioral tool such as FLACC or PAINAD — never assume no report means no pain |
| Urine output | At least 30 mL/hour, or 0.5 mL/kg/hour | Less than 30 mL/hour for 2 consecutive hours | Hypovolemia, hypoperfusion, acute kidney injury, obstruction |
Values shift across the lifespan, and the shift is largest at the extremes. Children run faster and breathe faster; older adults run cooler and stiffer. Memorize the direction of change even if you keep the table handy.
| Age | Heart rate (beats/min) | Respirations (breaths/min) | Blood pressure (mm Hg) |
|---|---|---|---|
| Newborn (0–1 month) | 100–160 | 30–60 | About 60–90 systolic |
| Infant (1–12 months) | 100–160 | 30–53 | 72–104 / 37–56 |
| Toddler (1–3 years) | 90–150 | 22–37 | 86–106 / 42–63 |
| Preschool (3–5 years) | 80–140 | 20–28 | 89–112 / 46–72 |
| School age (6–12 years) | 70–120 | 18–25 | 97–115 / 57–76 |
| Adolescent (13–18 years) | 60–100 | 12–20 | 110–131 / 64–83 |
| Adult | 60–100 | 12–20 | Less than 120/80 |
| Older adult (65 and above) | 60–100 (less rate reserve; blunted response to stress) | 12–20 (reduced chest wall compliance) | Rising systolic and widening pulse pressure; isolated systolic hypertension is common but not “normal aging” |
Three lifespan cautions save lives. First, in infants and children hypotension is a late and ominous sign — children compensate with tachycardia and vasoconstriction until they crash; for ages 1–10 years, hypotension is a systolic below 70 plus twice the age in years. Second, in older adults the febrile response is blunted: a temperature of 37.8 °C (100.0 °F), or a rise of 1.1 °C (2 °F) above that person’s own baseline, is a significant fever, and new confusion may be the only sign of infection. Third, in pregnancy heart rate rises 10–20 beats/min, blood volume rises 30–50%, and blood pressure falls slightly through the second trimester before returning to baseline by term; after about 20 weeks, lay the patient in a left lateral tilt rather than supine, because the gravid uterus compresses the inferior vena cava and drops cardiac output.
Seeing findings on every skin tone
Much of the classic physical-examination vocabulary was written for pale skin, and describing findings only as “redness” or “blueness” causes real, documented harm — pulse oximeters overestimate saturation in patients with darker skin, and stage 1 pressure injuries are missed at higher rates. The fix is technique, not vocabulary: assess the areas with the least melanin and the thinnest tissue, use natural or bright white light, compare with the patient’s own unaffected skin, and palpate as well as look.
| Finding | In lighter skin | In darker skin | Where to look and what to do |
|---|---|---|---|
| Cyanosis | Blue-gray lips, nail beds, skin | Ashen or dull gray mucous membranes; loss of the normal red undertone | Oral mucosa, tongue, conjunctivae, palms, soles, nail beds — and check the oxygen saturation and work of breathing rather than trusting color alone |
| Jaundice | Yellow skin and sclerae | Yellow-brown sclerae and hard palate; skin change may be inapparent | Sclera close to the iris (peripheral scleral fat can look normally yellow), hard palate, palms and soles |
| Pallor | Loss of pink; waxy or white | Ashen-gray or yellow-brown skin; dull appearance | Conjunctivae, oral mucosa, nail beds, palms — pale conjunctivae suggest anemia in any skin tone |
| Erythema / inflammation | Redness with warmth | Deeper, violaceous, purple or darker-than-surrounding hue; redness may be invisible | Palpate for warmth, firmness, bogginess, induration and tenderness; compare to the mirror-image site on the other side |
| Stage 1 pressure injury | Nonblanchable redness over a bony prominence | Color change may be subtle or absent | Temperature change, firm or boggy texture, and pain over the prominence are the reliable signs; document the technique used |
| Petechiae | Tiny red-purple nonblanching dots | Best seen on lighter-pigmented surfaces | Buccal mucosa, conjunctivae, abdomen, volar forearm |
Charting it so it holds up
Documentation is a clinical intervention and a legal record simultaneously. Chart what you observed and measured, not what you concluded without data; quote the patient in their own words; time everything; and never leave a blank space that another person could fill in. Chart after care, never before. Enter a late entry as a late entry with both the current time and the time the event occurred. In an electronic record, use the amendment function — the audit trail preserves the original anyway, and an attempt to conceal reads far worse in court than the error did.
| Vague entry | Precise entry | Why the difference matters |
|---|---|---|
| “Pt had a rough night. VS stable. Will monitor.” | “0300 — Patient awake, restless, repositioning frequently. Reports sharp RLQ pain 8/10 on 0–10 numeric scale, up from 4/10 at 2200. T 38.4 °C oral, HR 118 regular, RR 24 unlabored, BP 138/84 right arm sitting, SpO2 96% RA. Abdomen distended, hypoactive bowel sounds all four quadrants, guarding on light palpation RLQ. Provider Dr. Okoye paged 0305.” | “Stable” is a conclusion with no data behind it; the precise entry proves what was assessed, when, and that escalation occurred |
| “Patient is confused.” | “Patient oriented to person only; unable to state place, month or year. Was oriented x4 at 0800. Follows one-step commands. Pulls at IV line.” | Baseline plus specific deficit converts an impression into a trend a provider can act on |
| “Wound looks better.” | “Sacral wound 3.0 cm x 2.5 cm x 0.4 cm, pink granulation over 80% of the base, scant serosanguineous drainage, no odor, periwound skin intact and warm without induration.” | Measurements let the next nurse detect deterioration; “better” is not comparable to anything |
| “Refused meds. Uncooperative.” | “Patient declined metoprolol at 0900, stating ‘it makes me dizzy when I stand up.’ Education provided on purpose and on reporting dizziness. Dr. Okoye notified 0910; dose held per order.” | “Uncooperative” is a judgment and is potentially defamatory; the quote, the teaching and the notification are the defensible record |
Inspect, palpate, percuss, auscultate — abdomen excepted — then chart the measured finding rather than your impression, because in a review, care that was not documented is care that was not given.
Section 5Recognizing Trouble and Escalating It
Failure to rescue, and the findings that mean now
Failure to rescue is the term for a patient who deteriorates and dies not because the complication was unpredictable, but because the warning signs were recorded and not acted upon. Reviews of these events consistently find abnormal vital signs documented for six to eight hours before the arrest — most often a rising respiratory rate, which is the earliest and most ignored warning sign in adult medicine. The nurse is the surveillance system. Nobody else is in the room every hour.
| Red flag | Threshold | Why it matters | Act |
|---|---|---|---|
| Respiratory rate | Below 8 or above 28 breaths/min; new accessory muscle use, retractions, tripod position, or inability to speak in full sentences | Earliest marker of impending deterioration and of opioid oversedation | Stay with the patient, sit upright, apply oxygen, rapid response; if the cause is opioid oversedation, stimulate, support ventilation and give naloxone per protocol |
| Oxygen saturation | Below 90% on room air, or below the individually ordered target, or a new oxygen requirement | Hypoxemia; a new oxygen need is itself an escalation trigger | Apply oxygen, reassess, escalate |
| Heart rate | Below 40 or above 130 beats/min; new irregular rhythm | Perfusion failure, arrhythmia, drug toxicity | Full 60-second apical pulse, ECG per protocol, notify provider |
| Blood pressure | Systolic below 90 mm Hg, or a drop of 40 mm Hg from that patient’s baseline; mean arterial pressure below 65 | Organ hypoperfusion, shock, bleeding | Recheck manually on the opposite arm with a correctly sized cuff, lay the patient flat (left lateral tilt if pregnant beyond 20 weeks; keep the head raised if breathing is labored), escalate immediately |
| Temperature | Above 39.4 °C (103 °F) or below 35.0 °C (95.0 °F); in older adults, 37.8 °C (100 °F) or a 1.1 °C (2 °F) rise above baseline | Sepsis presents as hypothermia as often as fever in the frail | Sepsis screen, cultures and antibiotics per protocol |
| Level of consciousness | Any new confusion, agitation, lethargy or unresponsiveness | Altered mentation is a core sepsis and shock criterion and often the first sign in older adults | Check glucose, oxygen saturation; escalate |
| Neurologic deficit | Sudden facial droop, arm drift, slurred speech, vision loss, worst-ever headache | Stroke — treatment is time-dependent | Activate the stroke alert, establish the time last known well, check a glucose, and keep the patient nothing by mouth until a swallow screen is passed |
| Chest pain | New chest pain or pressure, with or without diaphoresis, nausea, or jaw or arm radiation | Acute coronary syndrome; women, older adults and people with diabetes present atypically | Stay, vital signs, 12-lead ECG per protocol, notify immediately |
| Urine output | Less than 30 mL/hour for 2 consecutive hours | Hypoperfusion or acute kidney injury | Assess volume status and bladder; notify provider |
| Pediatric | Grunting, nasal flaring, head bobbing, retractions, no wet diaper in 8 hours, inconsolability — and any hypotension | Children compensate until they do not; hypotension in a child is a pre-arrest sign | Escalate immediately; do not wait for a repeat set |
| Parent or patient concern | “Something is wrong,” “this isn’t like him” | A validated predictor of deterioration in its own right | Take it as a vital sign and reassess in person |
SBAR: the escalation script
SBAR — Situation, Background, Assessment, Recommendation — exists because unstructured calls fail. Before you dial, have the chart open, the most recent vital signs in front of you, the allergy list, the pertinent medications and the code status, and have laid eyes on the patient yourself within the last few minutes. Then say it in this order.
S — Situation. “Dr. Okoye, this is Priya Menon, RN, on 4 West. I’m calling about Mr. Daniel Ruiz in room 412, post-op day one from a right hemicolectomy. His respiratory rate has climbed to 28 and his oxygen saturation has dropped to 88% on room air.” B — Background. “He’s 68, with COPD and type 2 diabetes. He came back from the OR yesterday at 1400. He’s had 6 mg of morphine IV in the last four hours, last dose at 0230. He hasn’t been out of bed since surgery.” A — Assessment. “Right now he’s tachypneic and anxious, speaking in three-word sentences. Heart rate 122 sinus tach, blood pressure 98/56, temperature 37.9 °C. Breath sounds are diminished at both bases with no wheeze. His right calf is 3 cm larger than the left and tender. I’m concerned about a pulmonary embolism.” R — Recommendation. “I’ve placed him on 2 liters by nasal cannula and sat him upright. I’d like you to come see him now. Can I get orders for a stat CT pulmonary angiogram, a 12-lead ECG and an arterial blood gas? And what oxygen saturation target do you want, given his COPD?”
Notice four things about that call. It named the nurse and the unit; it gave the numbers rather than adjectives; it stated a concern out loud rather than hinting at one; and it closed with a specific, answerable request. Then document it: “0310 Dr. Okoye notified of RR 28, SpO2 88% RA, HR 122, BP 98/56, right calf tenderness. Verbal orders received for stat CTPA, ECG, ABG; SpO2 target 88–92%. Read back and verified. Provider to bedside.”
Advocacy, the chain of command and speaking up
Escalation does not stop at one phone call. If the provider does not respond, or responds in a way you believe is unsafe, you go up the chain of command: charge nurse, then nursing supervisor or manager, then the attending physician, then the medical director or administrator on call. Most facilities also have a rapid response team that any nurse may activate without a physician’s permission for a patient who is deteriorating but has not arrested, and many now extend that activation to patients and families. Calling a rapid response is never wrong; the near-miss you prevent is invisible, and the arrest you failed to prevent is not.
When you are ignored, use the two-challenge rule: state your concern clearly twice, and if it is still not acknowledged, take it to the next level of the chain. Structured phrases exist for this because in the moment people go quiet. The CUS script escalates the language deliberately: “I am Concerned. I am Uncomfortable. This is a Safety issue — I need us to stop.” That last sentence is the one to memorize, because the moments when you most need it are the moments when you will least want to say it.
Advocacy also runs in the ordinary direction: making sure the patient understands what they consented to, that pain is treated, that the discharge plan matches the home the person is actually going to, and that the frightened family gets an explanation. Two patient identifiers — full name and date of birth, never the room number — before every medication, specimen and procedure. Hand hygiene before and after every patient contact. These are not junior tasks you outgrow; they are the practice.
Deterioration is almost always visible in the vital signs hours before the arrest — recognize the red flag, escalate with SBAR, and keep escalating up the chain of command until someone acts.
The chapter in one breath
Nursing is a licensed practice defined by a state statute — the Nurse Practice Act — and enforced by a board of nursing, and the license, not the employer, sets the outer limit of what you may do. Before any unfamiliar task, test it against the practice act, then facility policy and orders, then your own validated competence; a no at any level means you stop and find someone qualified. You may delegate tasks that are predictable and low-risk to unlicensed personnel using the five rights of delegation, but you keep the accountability, and assessment, nursing diagnosis and planning, teaching, evaluation and any care of an unstable patient never leave the registered nurse. You will be judged against the standard of care, built from the ANA standards, the Code of Ethics and the law of negligence, and the record you write is the evidence. Physical examination proceeds by inspection, palpation, percussion and auscultation — except the abdomen, where auscultation moves ahead of percussion and palpation. Know adult vital-sign ranges exactly, adjust them for infants, children, pregnancy and older adults, and look for cyanosis, jaundice, pallor and erythema on mucosa, conjunctivae, sclerae and palms rather than trusting surface color. When a red flag appears, escalate with SBAR — and keep escalating.
Words worth knowing
| Term | What it means |
|---|---|
| Nurse Practice Act (NPA) | The state statute that defines nursing practice, sets licensure requirements and creates the board of nursing; it is the legal ceiling on your scope. |
| Board of nursing (BON) | The state agency that issues, renews, disciplines and revokes nursing licenses and writes the rules that interpret the NPA. |
| Nurse Licensure Compact (NLC) | An agreement letting a multistate license from one compact state authorize practice in the others; you follow the law of the state where the patient is located. |
| Scope of practice | The set of activities a licensee is legally permitted to perform, limited further by facility policy and by individual competence. |
| Standard of care | What a reasonably prudent nurse with similar preparation would do in similar circumstances; the yardstick in any negligence review. |
| Assignment | Transferring both responsibility and accountability for work already within the receiving person’s own scope and job description. |
| Delegation | Transferring responsibility for performing a specific task to another person while the delegating RN retains accountability for the outcome. |
| Five rights of delegation | Right task, right circumstance, right person, right direction and communication, right supervision and evaluation. |
| Unlicensed assistive personnel (UAP) | Certified nursing assistants, patient care technicians and similar staff who perform delegated, predictable, low-risk tasks for stable patients. |
| Negligence / malpractice | Failure to act as a reasonably prudent person would; malpractice is professional negligence, requiring duty, breach, causation and damages. |
| Battery | Unconsented physical contact, including performing a procedure a competent patient has refused. |
| Informed consent | The provider’s duty to explain diagnosis, procedure, risks, benefits, alternatives and consequences of refusal; the nurse verifies understanding and voluntariness and witnesses the signature. |
| Inspection, palpation, percussion, auscultation | The four physical-examination techniques, performed in that order — except on the abdomen. |
| Abdominal exception | Inspect, auscultate, percuss, palpate — auscultation precedes touch because palpation alters bowel sounds. |
| Orthostatic hypotension | A fall of at least 20 mm Hg systolic or 10 mm Hg diastolic within three minutes of standing; a marker of volume depletion and fall risk. |
| Mean arterial pressure (MAP) | Systolic plus twice the diastolic, divided by three; at least 65 mm Hg is generally required to perfuse organs. |
| Failure to rescue | Death or serious harm following a recognizable complication whose warning signs were documented but not acted upon. |
| SBAR | Situation, Background, Assessment, Recommendation — the standardized structure for escalating a concern or handing off a patient. |
| Rapid response team | A team any nurse may activate, without a physician’s permission, for a deteriorating patient who has not yet arrested. |
| Two-challenge rule / CUS | State a safety concern twice and escalate if unacknowledged, using the words “I am Concerned, I am Uncomfortable, this is a Safety issue.” |
Check yourself
THE NURSING PROCESS AND CLINICAL JUDGMENT
The nursing process is not a school exercise you outgrow after fundamentals — it is the thinking pattern that keeps a patient alive on a night shift when the physician is two floors away and something is quietly going wrong. Assessment, diagnosis, planning, implementation, evaluation: five steps that run as a loop, not a line, and that cycle again every time you touch a patient. Layered on top of that loop is clinical judgment — the ability to notice which of the forty things you observed actually matters, to decide what it means, to act on it, and to check whether your action worked. This chapter teaches the loop with the hands attached: the exact order in which you inspect, palpate, percuss and auscultate; the exact numbers that define normal; the exact words you write in the chart; and the exact moment you stop charting and pick up the phone.
By the end of this chapter you can
- Describe the five steps of the nursing process (ADPIE) and explain why it is cyclical rather than linear.
- Distinguish subjective from objective data and primary from secondary sources, and validate a questionable finding before acting on it.
- Perform the four examination techniques in correct order — inspection, palpation, percussion, auscultation — and state the abdominal exception and its rationale.
- State adult vital sign reference ranges to the exact number and describe how each changes across the lifespan and in pregnancy.
- Recognize cyanosis, jaundice, pallor and erythema in patients of every skin tone using oral mucosa, conjunctivae, sclerae, palms and soles.
- Cluster cues into a three-part PES nursing diagnosis and write a two-part risk diagnosis correctly.
- Write a SMART outcome and prioritize care using ABC, Maslow’s hierarchy and acute-before-chronic reasoning.
- Apply the Five Rights of Delegation and correctly separate tasks that may go to UAP or LPN/LVN from those that remain with the RN.
- Document a finding in precise, defensible language and escalate a deteriorating patient using SBAR.
Section 1Assessment — Collecting Data You Can Defend
Five steps, one loop
The nursing process is usually taught as an acronym — ADPIE: Assessment, Diagnosis, Planning, Implementation, Evaluation. That acronym is accurate but it hides the most important feature of the process, which is that it never stops. Evaluation feeds straight back into assessment. You reassess after every intervention, after every position change, after every dose of an analgesic or an antihypertensive, and at the beginning of every shift. A patient who was stable at 0700 is a different data set at 1100, and the plan you built at 0730 is a hypothesis, not a contract.
Assessment is the deliberate, systematic collection of data about a patient’s health status. It comes first for a reason that is not academic: every other step is corrupted by bad data. If you chart a respiratory rate of 18 because that is what the last nurse charted and you did not actually count, the diagnosis is wrong, the plan is wrong, the intervention is wrong, and the evaluation confirms a fiction. Counting respirations takes thirty to sixty seconds. Do it.
There are four kinds of assessment and you will use all four. The initial comprehensive assessment is performed on admission and establishes the baseline every later finding is measured against. The focused or problem-focused assessment targets one system or one complaint — a lung assessment on a patient with pneumonia, a neurovascular check distal to a new cast. The emergency assessment is the rapid primary survey (airway, breathing, circulation, disability, exposure) performed when a patient is decompensating, and it is intentionally incomplete because completeness costs time you do not have. The ongoing or time-lapsed assessment is the reassessment that detects change — and change, more than any single value, is what tells you a patient is in trouble.
Subjective, objective, primary, secondary
Subjective data is what the patient tells you: pain, nausea, dizziness, dyspnea, fear. These are symptoms, and they cannot be measured by you — only reported by the patient. Chart them in the patient’s own words inside quotation marks whenever the wording matters: the patient states, “It feels like someone is standing on my chest.” Objective data is what you observe, measure or elicit: a blood pressure of 88/52, crackles in the right lower lobe, a 3 cm reddened area over the sacrum that does not blanch, a respiratory rate of 28. These are signs. Both types are real data and neither outranks the other — but only objective data can be independently verified, so it carries the weight in documentation and escalation.
The primary source of data is always the patient, when the patient is able and willing to give it. Secondary sources include family members, the medical record, the previous shift’s nurse, laboratory and imaging results, and other members of the team. Secondary data is legitimate but must be flagged as such: the daughter reports the patient has been confused for two days is not the same statement as the patient is confused.
Validation is the step students skip. When subjective and objective data conflict — a patient rates pain at 9 out of 10 while sleeping comfortably with a heart rate of 62, or a monitor reads a heart rate of 148 while the radial pulse is 74 — you do not choose the more convenient number. You recheck. Take an apical pulse for a full minute. Take a manual blood pressure with a correctly sized cuff. Ask the patient again in different words. A finding that surprises you is either an artifact or an emergency, and the only way to tell is to repeat the measurement.
How the hands actually move
Physical examination has four techniques, performed in a fixed order: inspection, palpation, percussion, auscultation. The order exists because each technique disturbs what the next one measures. Inspection is done first because it is the only technique that does not touch the patient and therefore cannot change the findings. Then palpation, then percussion, then auscultation.
There is one exception and you must know it: the abdomen is examined in the order inspect, auscultate, percuss, palpate. Auscultation is moved to second position because pressing on the abdomen mechanically stimulates the bowel and alters bowel sounds — palpate first and you will hear sounds you created rather than sounds the patient had. Listen before you touch. Use the diaphragm of the stethoscope, warmed, and listen in all four quadrants; normal bowel sounds are 5 to 30 per minute and irregular. Before declaring bowel sounds absent you must listen for a full five minutes in each quadrant.
Inspection means looking with intent, in good light, with the area adequately exposed and compared side to side. Symmetry is the single most useful concept in physical assessment: one warm foot and one cool foot means far more than two cool feet. Palpation uses the fingertips for texture, pulsation and size, the palmar surface of the metacarpophalangeal joints for vibration such as fremitus and thrills, and the dorsum of the hand for temperature, because the dorsum is more sensitive to heat. Warm your hands, keep your nails short, and always perform light palpation (about 1 cm) before deep palpation (about 4 to 5 cm). Never deeply palpate a pulsatile abdominal mass, and never test for rebound tenderness casually — both can cause harm.
Percussion strikes the distal interphalangeal joint of the pleximeter finger with the tip of the plexor finger, using wrist motion only, striking twice and withdrawing immediately so the sound is not damped. The note tells you what is under your finger to a depth of roughly 5 to 7 cm. Auscultation uses the diaphragm pressed firmly for high-pitched sounds (breath sounds, bowel sounds, normal S1 and S2) and the bell placed lightly for low-pitched sounds (S3, S4, bruits, some murmurs). Place the stethoscope on skin, never over a gown, and listen for at least one full respiratory cycle at each site.
| Percussion note | Where it is normal | When it is abnormal, it suggests |
|---|---|---|
| Resonance (low-pitched, hollow) | Normal lung tissue | Expected finding over all lung fields |
| Hyperresonance (booming, lower pitch) | Not normal in an adult; normal in a child’s thin chest | Trapped air — emphysema, asthma exacerbation, pneumothorax |
| Tympany (drum-like, loud) | Gastric air bubble, air-filled intestine | Over the abdomen generally, gaseous distention or obstruction |
| Dullness (thud, medium pitch) | Liver, spleen, full bladder, heart border | Over lung — consolidation (pneumonia), pleural effusion, atelectasis, mass |
| Flatness (very dull, soft) | Muscle, bone, sternum, thigh | Over the chest — large pleural effusion |
The numbers you must know cold
Vital signs are the cheapest early-warning system in medicine and the most frequently rushed measurement in nursing. Measure them correctly. Blood pressure: patient seated quietly for five minutes, back supported, feet flat on the floor, legs uncrossed, arm supported at heart level, no talking, no caffeine or nicotine for 30 minutes. The cuff bladder should be about 40 percent of arm circumference in width and encircle 80 percent of the arm; a cuff that is too small produces a falsely high reading, and a cuff that is too large produces a falsely low one. Position the lower cuff edge 2.5 cm (1 inch) above the antecubital fossa. Count an apical pulse for a full 60 seconds in infants, children and any irregular rhythm.
| Adult vital sign | Expected range | Abnormal and what it suggests |
|---|---|---|
| Temperature (oral) | 36.5–37.5 °C (97.7–99.5 °F); mean 37.0 °C (98.6 °F) | ≥38.0 °C (100.4 °F) fever/infection; <35.0 °C (95.0 °F) hypothermia, sepsis in elderly, environmental exposure |
| Route offsets | Rectal and temporal about 0.5 °C higher than oral; axillary about 0.5 °C lower | Route mismatch across shifts creates false “fever” trends — chart the route every time |
| Pulse (apical or radial) | 60–100 beats/min, regular | >100 tachycardia (pain, fever, hypovolemia, hypoxia, anxiety); <60 bradycardia (beta-blockers, heart block, athletic heart) |
| Respirations | 12–20 breaths/min, unlabored, regular | >20 tachypnea (earliest sign of deterioration); <12 bradypnea (opioids, rising intracranial pressure) |
| Blood pressure | Normal <120/<80 mmHg; elevated 120–129/<80; stage 1 hypertension 130–139 or 80–89; stage 2 ≥140 or ≥90 | >180 and/or >120 hypertensive crisis; systolic <90 or MAP <65 hypoperfusion |
| Pulse pressure | 30–40 mmHg (systolic minus diastolic) | Narrowed <25 percent of systolic suggests low stroke volume/shock; widened suggests arterial stiffness or increased intracranial pressure |
| Oxygen saturation | 95–100 percent on room air | <90 percent hypoxemia requiring action; target 88–92 percent in chronic CO2 retainers |
| Pain | 0–10 numeric scale; patient’s report is the standard | Any new or abruptly worsened pain is a cue, not a comfort issue, until proven otherwise |
| Urine output | ≥0.5 mL/kg/hr; roughly ≥30 mL/hr in an average adult | Sustained output below this is an early marker of hypoperfusion or acute kidney injury |
| Age group | Heart rate (awake, resting) | Respirations | Typical systolic BP |
|---|---|---|---|
| Newborn (0–28 days) | 100–160/min | 30–60/min | 65–95 mmHg |
| Infant (1–12 months) | 90–160/min | 25–45/min | 70–100 mmHg |
| Toddler (1–3 years) | 80–140/min | 20–30/min | 80–110 mmHg |
| Preschool (3–5 years) | 80–120/min | 20–28/min | 80–110 mmHg |
| School age (6–12 years) | 70–110/min | 18–25/min | 85–120 mmHg |
| Adolescent (13–18 years) | 60–100/min | 12–20/min | 100–120 mmHg (from age 13, adult thresholds apply — normal is <120/<80) |
| Adult | 60–100/min | 12–20/min | <120 mmHg |
| Older adult (65+) | 60–100/min | 12–20/min | Systolic often higher from arterial stiffness; widened pulse pressure common |
Three lifespan facts change management immediately. First, in children aged 1 to 10 years, hypotension is defined as a systolic pressure below 70 plus twice the age in years — a 4-year-old with a systolic of 74 is already hypotensive, and because children compensate with tachycardia and vasoconstriction until they abruptly do not, hypotension in a child is a late and ominous sign. Second, any infant younger than 3 months with a rectal temperature of 38.0 °C (100.4 °F) or higher is a medical emergency and requires immediate evaluation. Third, older adults often have a lower baseline temperature (frequently 36.0–36.5 °C) and a blunted febrile response, so a temperature of 37.2 °C (99.0 °F), or a rise of 1.1 °C (2 °F) above that patient’s own baseline, may be the only temperature sign of serious infection. In older adults, new confusion is frequently the first sign of infection, before any fever appears at all.
Pregnancy shifts the baseline in predictable ways: circulating blood volume rises 30 to 50 percent, resting heart rate rises 10 to 20 beats per minute, and blood pressure falls in the second trimester before returning toward baseline near term. That physiologic drop means a “normal-looking” blood pressure in late pregnancy can represent a significant rise from that patient’s own first-trimester baseline — which is why a systolic of 140 or a diastolic of 90 after 20 weeks, especially with headache, visual changes or right upper quadrant pain, is escalated, not observed.
| Finding | In lighter skin | In darker skin — assess here instead |
|---|---|---|
| Cyanosis | Bluish tinge of lips, nail beds, skin | Oral mucosa, tongue, conjunctivae, palms and soles, nail beds; skin may appear ashen or gray rather than blue |
| Pallor | Loss of pink tone in face and nail beds | Conjunctivae, oral mucosa, palms; skin may look ashen, yellow-brown or dull rather than pale |
| Jaundice | Yellowing of skin and sclerae | Sclerae (avoid confusing with normal subconjunctival fat), hard palate and junction of hard and soft palate, palms and soles — examine in natural daylight |
| Erythema and inflammation | Redness, blanching then refilling | Color may appear violaceous, purple, deep brown or simply darker than surrounding skin; palpate for warmth, induration, edema, tightness and tenderness rather than relying on color |
| Stage 1 pressure injury | Non-blanchable erythema over a bony prominence | Color change may be invisible — compare with adjacent skin and assess for temperature difference (warm then cool), boggy or firm texture, edema and pain |
Assessment is inspect, palpate, percuss, auscultate — except the abdomen, which is inspect, auscultate, percuss, palpate, because palpating first changes the bowel sounds you are about to report.
Section 2Analysis and Nursing Diagnosis — Turning Cues Into a Problem
From cue to cluster
A cue is a single piece of relevant data: a heart rate of 118, a report of burning on urination, a urine output of 15 mL over two hours. Cues become meaningful when they are clustered — grouped with other cues that share a plausible physiologic explanation. Heart rate 118, temperature 38.4 °C, respiratory rate 24, systolic 96, new confusion in an 82-year-old with an indwelling catheter is not five separate problems. It is one pattern, and the pattern is sepsis until proven otherwise.
Analysis has three moves. First, separate relevant from irrelevant data — the patient’s chronic well-controlled hypothyroidism is not driving today’s picture. Second, identify which cues are expected for this patient’s condition and which are unexpected; the unexpected ones deserve your attention first, because expected findings rarely kill patients and unexpected ones frequently do. Third, compare against two standards: population norms (is this outside 12–20 breaths per minute?) and the patient’s own baseline (was this patient at 12 all week and is now at 22?). A value inside the normal range that has moved sharply from a personal baseline is still a red flag.
Nursing diagnosis versus medical diagnosis
A medical diagnosis names a disease — pneumonia, heart failure, type 2 diabetes mellitus. It is made by a licensed provider and it generally does not change over the hospitalization. A nursing diagnosis names the patient’s human response to that disease — impaired gas exchange, activity intolerance, risk for unstable blood glucose — and it belongs to the RN, is treated by independent nursing interventions, and changes as the patient changes, sometimes within a single shift. Two patients with identical pneumonia may carry entirely different nursing diagnoses: one is short of breath and frightened, the other is dehydrated and falling.
| Medical diagnosis | Nursing diagnosis | |
|---|---|---|
| Names | The disease or pathology | The patient’s response to the disease or life situation |
| Made by | Physician, NP, PA within their scope | Registered nurse — cannot be delegated |
| Duration | Usually persists through the illness | Changes as the patient responds; reviewed every shift |
| Example | Left-sided heart failure | Excess fluid volume; activity intolerance; anxiety |
| Treated by | Medical and surgical therapy, prescriptions | Independent nursing interventions plus collaborative measures |
Writing it: PES, and the risk exception
The standard actual (problem-focused) nursing diagnosis is written in PES format: Problem, Etiology, Signs and symptoms, joined by the phrases “related to” and “as evidenced by.” For example: Impaired gas exchange related to alveolar-capillary membrane changes as evidenced by SpO2 88 percent on room air, respiratory rate 28, crackles in bilateral lower lobes and restlessness. The problem is the NANDA-I label, the etiology is the cause you can actually do something about, and the evidence is the objective and subjective data you collected.
Two rules students break constantly. First, the etiology must never be a medical diagnosis, because you cannot independently treat pneumonia — write “related to retained secretions and alveolar inflammation,” not “related to pneumonia.” Second, a risk diagnosis has only two parts: the risk label and the risk factors. There is no “as evidenced by,” because if there were evidence the problem would already exist and would no longer be a risk. Write: Risk for falls as evidenced by — wrong. Write: Risk for falls related to postural hypotension, new zolpidem order and generalized weakness — correct.
Deciding which problem comes first
Once you have several diagnoses, you must rank them, because you cannot do everything at 0800. Use ABC first: an airway problem outranks a breathing problem, which outranks a circulation problem, which outranks everything else. Then Maslow: physiologic needs before safety, safety before love and belonging, and so on — but note that within physiologic needs, oxygenation is always the top priority. Then apply the practical rules: actual problems before risk problems of equal urgency; acute before chronic; unexpected findings before expected ones; and problems that will worsen without immediate action before those that will not.
| Cue cluster | Expected explanation | Unexpected — escalate |
|---|---|---|
| Post-operative day 1, HR 96, temp 37.8 °C, incisional pain 5/10 | Normal inflammatory response and post-op pain | Temp ≥38.0 °C with purulent drainage, wound dehiscence, or pain escalating despite analgesia |
| Heart failure patient, 2 kg weight gain in 2 days, bibasilar crackles | Fluid retention — expected exacerbation, notify provider same shift | Pink frothy sputum, orthopnea, SpO2 <90 percent, RR >28 — pulmonary edema, escalate now |
| Older adult, new confusion, no fever | Never assume this is expected | Confusion is a cue for hypoxemia, hypoglycemia, infection, stroke or medication effect — check glucose, SpO2 and neuro status immediately |
| Post-op leg pain, unilateral calf swelling, warmth | None — there is no benign version of this cluster | Possible deep vein thrombosis; do not massage the calf, keep the patient in bed and notify the provider |
A nursing diagnosis names the patient’s response, not the disease; actual problems are written in three parts with “as evidenced by,” while risk diagnoses have only two.
Section 3Planning — Outcomes, Priorities and the Limits of Your Scope
Outcomes must be measurable or they are wishes
An outcome statement describes what the patient will do or achieve, not what the nurse will do. “Encourage fluids” is an intervention, not an outcome. Outcomes should be SMART: specific, measurable, attainable, relevant and time-bound. Write them in the patient’s voice with an observable behavior and a deadline. If two nurses could disagree about whether the outcome was met, it was not written well enough.
| Vague outcome | SMART outcome |
|---|---|
| Patient will breathe better. | Patient will maintain SpO2 ≥94 percent on 2 L/min nasal cannula with respiratory rate 12–20 and no accessory muscle use through the end of shift. |
| Patient will have less pain. | Patient will report pain ≤3/10 within 45 minutes of analgesic administration and will ambulate 30 feet twice today. |
| Patient will understand insulin. | Patient will independently demonstrate correct insulin self-injection technique, including site rotation, on two consecutive occasions before discharge. |
| Patient will not fall. | Patient will remain free of falls throughout hospitalization and will use the call light for all transfers, verbalized and demonstrated by the end of shift. |
Choosing interventions
Interventions come in three types and the distinction is a scope-of-practice question, not a vocabulary quiz. Independent interventions are within the RN’s own license and require no order: repositioning every two hours, elevating the head of the bed, incentive spirometry coaching, therapeutic communication, oral care, teaching, and assessment itself. Dependent interventions require a provider order: medications, intravenous fluids, wound care protocols, activity orders, diet orders. Collaborative or interdependent interventions are carried out with other disciplines: physical therapy mobility plans, respiratory therapy nebulizer schedules, dietitian-designed feeding plans, pharmacy medication reconciliation.
Every intervention you select should have a stated rationale, because a rationale is what allows you to defend the choice later and to recognize when the intervention is no longer appropriate. “Elevate head of bed 30 to 45 degrees to reduce aspiration risk and improve diaphragmatic excursion” tells the next nurse why the position matters, which means it is more likely to survive the shift change.
Delegation and the boundary of your license
Delegation is transferring the authority to perform a selected nursing task in a selected situation to a competent individual, while the RN retains accountability for the outcome. That last clause is the whole point: you can delegate the task, never the responsibility. The Five Rights of Delegation are the right task, under the right circumstance, to the right person, with the right direction and communication, under the right supervision and evaluation.
The RN never delegates assessment, nursing diagnosis, planning, evaluation, teaching, or any clinical judgment, and never delegates care of an unstable or unpredictable patient. Those five words — assess, diagnose, plan, teach, evaluate — are the ones to memorize. Unlicensed assistive personnel may collect and report data such as a blood pressure reading, but they may not interpret it. If a UAP tells you the pressure is 84/50, the measurement was delegated and the meaning is yours.
| Role | May do | May not do |
|---|---|---|
| UAP / CNA / PCT | Vital signs on stable patients, intake and output, bathing and hygiene, oral care, feeding patients without dysphagia, ambulation and positioning, weights, specimen collection, stocking, reporting measured values to the RN | Assessment or interpretation, teaching, evaluating response to care, care of an unstable patient, medication administration, sterile procedures, judgment calls of any kind |
| LPN / LVN (varies by state) | Focused data collection, most oral and many parenteral medications, routine dressing changes, tracheostomy and ostomy care, urinary catheter insertion, tube feedings, reinforcing teaching the RN has already provided | Initial comprehensive admission assessment, creating or revising the plan of care, most IV push medications, blood product administration, care of the unstable patient, independent patient teaching |
| RN | All of the above plus comprehensive assessment, nursing diagnosis, planning, teaching, evaluation, triage, delegation and supervision | Medical diagnosis, prescribing, procedures outside the state Nurse Practice Act or facility policy |
When you delegate, communicate specifically. “Take vitals on 12” is a weak instruction. “Please take a full set of vital signs on room 12 within the next fifteen minutes, count the respirations for a full minute, and tell me immediately if the systolic is under 100 or the heart rate is over 110” gives the task, the timeframe, the method and the reporting parameters. Then follow up — supervision and evaluation are the fifth right, and skipping them is the most common delegation failure on real units.
You may delegate a task but never the accountability, and assessment, diagnosis, planning, teaching and evaluation — along with any unstable patient — stay with the RN.
Section 4Implementation and Evaluation — Doing It, Charting It, Re-checking It
Implementation is assessment too
Implementation is not simply executing the plan. Every intervention is bracketed by assessment: you reassess immediately before acting (is the plan still appropriate?), you monitor during the action, and you reassess after to evaluate the response. Before giving a scheduled metoprolol, you check the apical pulse and blood pressure. Before ambulating a post-operative patient, you check orthostatic vital signs, pain level and the surgical site. Before suctioning, you auscultate. The order is never “do the task, then look at the patient.”
Reassessment intervals are not arbitrary. After an intravenous analgesic, reassess pain within 15 to 30 minutes; after an oral analgesic, within 45 to 60 minutes. After an antihypertensive, recheck blood pressure at the drug’s expected peak. After oxygen titration, recheck SpO2 and work of breathing within 15 minutes. After a fall, perform a full head-to-toe assessment plus neurologic checks immediately and per protocol thereafter. Know these intervals for the drugs you give — an intervention without documented reassessment is legally indistinguishable from an intervention that failed.
How to chart it
Documentation must be timely, factual, complete, organized and objective. Chart what you observed and what you did, not what you concluded about the patient’s character. “Patient uncooperative” is an opinion; “Patient declined morning ambulation, stating ‘my chest hurts too much’; pain rated 7/10; RN notified provider at 0915” is a record. Never chart in advance, never chart for someone else, never delete an entry — correct an error by following facility policy for an addendum, with the reason and your initials. Late entries are labeled as late entries with the actual time of the event and the actual time of the entry.
| Vague entry (indefensible) | Precise entry (defensible) |
|---|---|
| Tolerated ambulation well. | 0930 Ambulated 50 feet in hallway with front-wheeled walker, one-person standby assist. Pre-ambulation HR 84, SpO2 97 percent on room air. Post-ambulation HR 112, RR 26, SpO2 90 percent on room air; reported dyspnea 4/10. Seated in chair; SpO2 95 percent after 3 minutes rest. Provider notified 0942. |
| Wound looks better. | 1400 Right lower leg wound 4.0 cm × 2.5 cm × 0.3 cm deep; wound bed 80 percent red granulation, 20 percent yellow slough; scant serosanguineous drainage; periwound intact without induration or warmth. Cleansed with normal saline, hydrocolloid applied. Patient rated pain 2/10 during care. |
| Confused this morning. | 0710 Alert, oriented to person only (baseline oriented × 4 per prior shift). Unable to state year or location. Follows one-step commands. Pupils 3 mm equal and reactive; grips equal; no facial droop; speech clear. Capillary glucose 96 mg/dL, temp 37.9 °C, SpO2 91 percent on room air. Rapid response called 0716. |
| Complains of pain, medicated. | 2210 Patient reports sharp right upper quadrant pain 8/10, worse with inspiration, onset 2145, no radiation. HR 104, BP 138/82, RR 22. Hydromorphone 0.5 mg IV given 2215 per order. 2235 pain 3/10, HR 88, RR 16, respirations unlabored, sedation scale 1. |
Evaluation closes the loop
Evaluation asks one question about each outcome: was it met, partially met, or not met? You answer with data, not impression — you compare the patient’s current status to the measurable outcome you wrote. Outcome: SpO2 ≥94 percent on 2 L by end of shift. Result: SpO2 92 percent on 3 L with respiratory rate 22. That is not met, and it obligates you to act.
When an outcome is not met, there are only four possible reasons and you should check them in order: the assessment data was incomplete or wrong; the nursing diagnosis or its etiology was wrong; the outcome was unrealistic or the timeframe too short; or the interventions were appropriate but were not actually implemented. Revising the plan is not an admission of failure — it is the process working. What is a failure is carrying an outcome forward unchanged for three shifts while the patient does not improve.
Every intervention is sandwiched between assessments, and an intervention with no documented reassessment is indistinguishable, in a chart and in court, from one that never worked.
Section 5Clinical Judgment — From Noticing to Escalating
Two models, one habit of mind
Clinical judgment is the observed outcome of critical thinking and decision making — the conclusion you reach about a patient’s needs and the decision to act, modify or withhold action. Tanner’s widely taught model describes four phases: noticing (perceiving that something is different), interpreting (making sense of it), responding (deciding and acting) and reflecting (evaluating in the moment and afterward). Experienced nurses notice faster not because they see more data but because they know which data matters.
The NCSBN Clinical Judgment Measurement Model, which structures Next Generation NCLEX items, breaks the same process into six testable steps: recognize cues (what matters most?), analyze cues (what could it mean?), prioritize hypotheses (what is most likely and most dangerous?), generate solutions (what can I do?), take action (what will I do, and how?) and evaluate outcomes (did it help?). Map those onto ADPIE and they overlap almost perfectly — the difference is that the judgment model makes the reasoning between assessment and action explicit instead of assuming it.
The reason this matters at the bedside has a name: failure to rescue. Patients who deteriorate in hospitals usually show abnormal vital signs for six to eight hours before an arrest, most often a rising respiratory rate. The deterioration is rarely missed because it was invisible. It is missed because it was recorded and not acted upon. Respiratory rate is the most sensitive and the most frequently falsified vital sign on the flowsheet. Count it.
Red flags — findings that require action now
| Finding | Threshold | What it suggests / do now |
|---|---|---|
| Airway compromise | Stridor, drooling, inability to speak, gurgling | Obstruction — call for help, position, suction, do not leave the patient |
| Respiratory rate | >28 or <8/min, or any new accessory muscle use | Impending respiratory failure — earliest reliable sign of deterioration; rapid response |
| Oxygen saturation | <90 percent (or <88 percent in known CO2 retainer) not corrected by intervention | Hypoxemia — apply oxygen, sit upright, escalate; do not chase the number alone |
| Systolic blood pressure | <90 mmHg or MAP <65 mmHg, or a drop ≥40 mmHg from baseline | Shock or hypoperfusion — assess mentation, skin, urine output; escalate |
| Heart rate | >130 or <40/min sustained, or any new irregular rhythm with symptoms | Arrhythmia, hypovolemia, hypoxia, sepsis — obtain ECG, escalate |
| Neurologic change | Any new confusion, new focal deficit, unequal pupils, GCS drop of 2 or more | Stroke, hypoglycemia, hypoxemia, rising intracranial pressure — check glucose and SpO2 immediately, note last known well, activate stroke protocol |
| Sepsis screen (qSOFA) | Any 2 of: RR ≥22, altered mentation, systolic ≤100 mmHg | High risk of sepsis — escalate for cultures, lactate and antibiotics within the sepsis bundle window |
| Urine output | <0.5 mL/kg/hr for 2 consecutive hours, or <30 mL/hr in an adult | Hypoperfusion or acute kidney injury — assess volume status, escalate |
| Chest pain | Any new chest pain, especially with diaphoresis, dyspnea or nausea | Acute coronary syndrome — vital signs, 12-lead ECG within 10 minutes, notify provider; women and people with diabetes often present atypically with fatigue, jaw or epigastric discomfort |
| Nurse concern | “Something is wrong” without a number to point to | A legitimate rapid response trigger at most facilities — call it |
SBAR — how the escalation actually sounds
SBAR (Situation, Background, Assessment, Recommendation) exists because nurses were trained to narrate and providers were trained to expect a headline. SBAR forces the headline first. Prepare before you dial: have the chart, the current vital signs, the relevant medications, allergies, code status and the most recent labs in front of you. State your name and unit, and say the patient’s name and room.
| Element | What goes here | Worked example |
|---|---|---|
| Situation | Who you are, who the patient is, and the problem in one sentence | “This is Maria Lopez, RN, on 4 West. I’m calling about Mr. Chen in room 412. He has become acutely short of breath in the last thirty minutes.” |
| Background | Admitting diagnosis, relevant history, pertinent treatments and timing | “He is a 68-year-old admitted two days ago for a right total knee arthroplasty. History of atrial fibrillation on apixaban, which was held pre-operatively and restarted this morning.” |
| Assessment | Your objective findings and your clinical impression — numbers, not adjectives | “Respiratory rate 30, heart rate 124 and irregular, blood pressure 96/58, SpO2 88 percent on room air, up to 92 percent on 4 L nasal cannula. Lungs clear, no chest pain, right calf is swollen and warm. He is anxious and speaking in three-word sentences. I am concerned about a pulmonary embolism.” |
| Recommendation | What you want, specifically, and by when | “I would like you to come see him now. In the meantime, may I have orders for a stat ECG, a CT pulmonary angiogram, and titration of oxygen to keep saturation above 92 percent?” |
Two habits complete the escalation. First, read back and verify every verbal or telephone order, then document the order, the time, the provider and the read-back. Second, use the chain of command if the response is inadequate: if the provider does not respond within the timeframe your patient’s condition allows, or gives an order you believe is unsafe, notify the charge nurse and then the nursing supervisor, and call the rapid response team — which any nurse may activate without an order. Document each escalation attempt with the time. Chart the call: “0246 Dr. Patel paged. 0254 No response, second page. 0301 Charge nurse notified, rapid response activated.”
Recognizing deterioration is only half the skill — the other half is transmitting it in SBAR, with numbers, a named concern and a specific request, and escalating up the chain until someone responds.
The chapter in one breath
The nursing process — assessment, diagnosis, planning, implementation, evaluation — is a loop you re-enter every time you touch a patient, and clinical judgment is the reasoning that runs inside it. Assessment demands technique before conclusions: inspect, palpate, percuss, auscultate, in that order, with the abdomen the single exception because palpation alters bowel sounds. It demands exact numbers — adult heart rate 60 to 100, respirations 12 to 20, blood pressure below 120 over 80, SpO2 95 to 100 percent, urine output at least 0.5 mL/kg/hr — and it demands knowing how those numbers shift in newborns, children, pregnancy and older adults, and how cyanosis, jaundice, pallor and erythema present in darker skin, where the oral mucosa, conjunctivae, sclerae, palms and soles carry the information the skin surface hides. Cues become clusters, clusters become a nursing diagnosis written in PES format, and diagnoses are ranked by airway, breathing and circulation before anything else. Plans become SMART outcomes and interventions delegated within the Five Rights — never assessment, diagnosis, planning, teaching, evaluation or an unstable patient. Then you document in measurements rather than adjectives, reassess to close the loop, and when the numbers cross a red-flag threshold, you stop charting and escalate in SBAR.
Words worth knowing
| Term | What it means |
|---|---|
| ADPIE | The five steps of the nursing process: assessment, diagnosis, planning, implementation, evaluation — cyclical, not linear. |
| Subjective data | Symptoms reported by the patient and not measurable by the nurse; charted in the patient’s own words when wording matters. |
| Objective data | Signs the nurse observes, measures or elicits and that another clinician could independently verify. |
| Primary source | The patient. All other sources — family, record, prior nurse, labs — are secondary and must be identified as such. |
| Validation | Rechecking data when subjective and objective findings conflict or when a value is unexpected, before acting on it. |
| Cue | A single relevant piece of data; cues become meaningful only when clustered into a physiologic pattern. |
| Inspection, palpation, percussion, auscultation | The four examination techniques in required order; the abdomen is examined inspect, auscultate, percuss, palpate. |
| Focused assessment | A targeted reassessment of one system or complaint, as opposed to the comprehensive admission assessment. |
| Nursing diagnosis | A clinical judgment about the patient’s response to a health problem; made by the RN and treated with nursing interventions. |
| PES format | Problem related to Etiology as evidenced by Signs and symptoms — the three-part structure of an actual nursing diagnosis. |
| Risk diagnosis | A two-part diagnosis naming a vulnerability and its risk factors; it has no “as evidenced by” because no evidence exists yet. |
| SMART outcome | Specific, measurable, attainable, relevant, time-bound goal written as patient behavior with a deadline. |
| Independent intervention | Nursing action within the RN’s own license requiring no order, such as repositioning, teaching or elevating the head of the bed. |
| Delegation | Transferring authority for a task while retaining accountability for the outcome; governed by the Five Rights of Delegation. |
| Five Rights of Delegation | Right task, right circumstance, right person, right direction and communication, right supervision and evaluation. |
| Clinical judgment | The conclusion reached about a patient’s needs and the decision to act, modify or withhold action — the observable product of critical thinking. |
| Clinical Judgment Measurement Model | NCSBN framework: recognize cues, analyze cues, prioritize hypotheses, generate solutions, take action, evaluate outcomes. |
| Failure to rescue | Death or serious harm following a recognizable but unacted-upon deterioration; usually preceded by hours of abnormal vital signs. |
| SBAR | Situation, Background, Assessment, Recommendation — the structured handoff and escalation format that puts the headline first. |
| Pulse pressure | Systolic minus diastolic pressure, normally 30 to 40 mmHg; narrowing suggests falling stroke volume. |
Check yourself
COMMUNICATION, DOCUMENTATION AND HANDOFF
Everything you find at the bedside is worthless if it dies in your head. The most common root cause of serious patient harm in hospitals is not a missed lab value or a dull stethoscope — it is a communication failure: a nurse who noticed something and said it too softly, a handoff that skipped the one detail that mattered, a chart entry so vague that the next nurse could not tell whether the patient was improving. This chapter teaches the three ways nursing assessment travels: to the patient (therapeutic communication), to the team (escalation, SBAR, closed-loop verification) and to the future (the legal health record and the handoff). You will learn exact phrasing — what to say, what to write, what to refuse to write — and the numeric thresholds that convert an observation into a phone call you make right now instead of at the end of the shift.
By the end of this chapter you can
- Apply therapeutic communication techniques and identify non-therapeutic responses that shut a patient down.
- Adapt communication for infants, children, pregnancy, older adults, limited English proficiency and low health literacy, using a qualified medical interpreter and teach-back.
- Escalate a deteriorating patient using SBAR, stating the specific vital-sign and symptom thresholds that require notification now.
- Perform closed-loop communication, including read-back of verbal orders and critical values, and invoke the two-challenge rule and chain of command.
- Write objective, timed, defensible documentation, and convert a vague entry into a precise one — including describing cyanosis, jaundice, pallor and erythema accurately across skin tones.
- Document a physical assessment in the sequence it was performed — inspection, palpation, percussion, auscultation — and state the abdominal exception.
- Correct an error, enter a late entry, avoid Do Not Use abbreviations and protect PHI under HIPAA.
- Conduct a standardized handoff (I-PASS or ISBAR) and a bedside shift report with the patient present.
- Delegate to UAP using the five rights of delegation, and state what may never be delegated: assessment, teaching, evaluation and the unstable patient.
Section 1Therapeutic Communication and the Nurse’s Presence
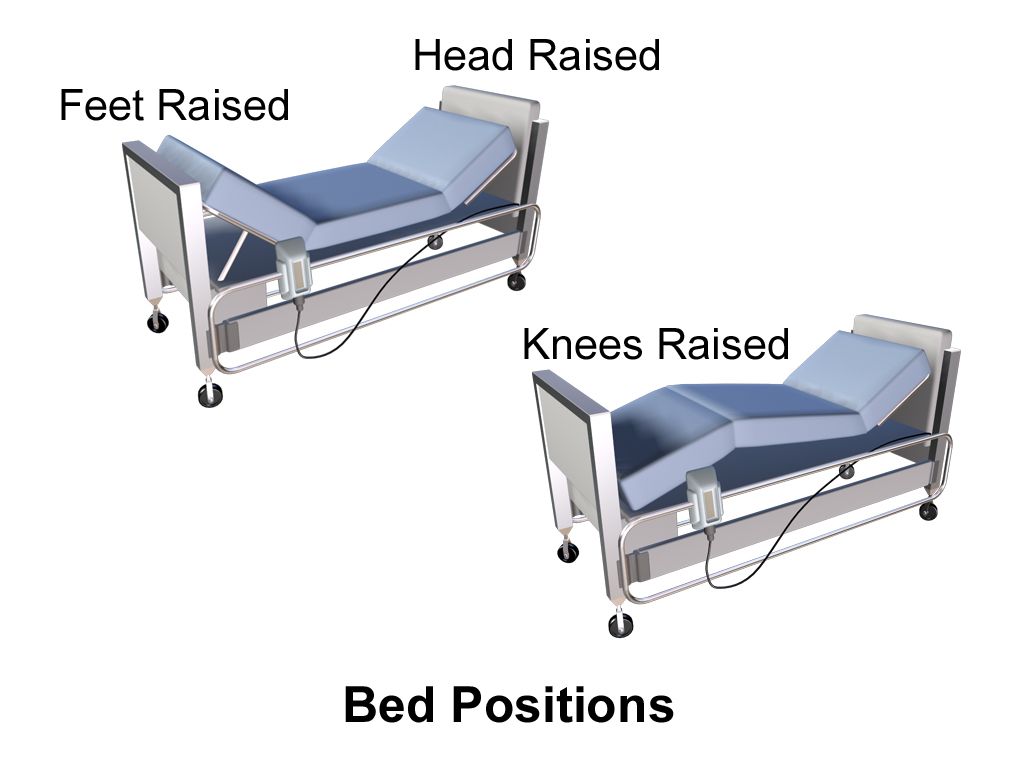
What makes communication therapeutic
Social conversation is symmetrical: two people trade stories and both leave satisfied. Therapeutic communication is deliberately asymmetrical. It is goal-directed, time-limited and centered entirely on the patient’s needs, not yours. You will not tell the patient about your own gallbladder surgery. You will not reassure them that everything will be fine, because you do not know that and saying it ends the conversation. What you will do is create enough safety that a frightened adult tells a stranger in scrubs that they have not taken their blood pressure medication in three months because it costs eighty dollars a month.
Hildegard Peplau described the nurse—patient relationship in three phases, and they hold up at the bedside. In the orientation phase you introduce yourself by name and role, state what you are going to do and how long it will take, and set the frame: “Good morning, Mr. Okonkwo, I’m Dana, I’m the registered nurse taking care of you until seven tonight. I’d like to spend about ten minutes going over how last night went and then listen to your heart and lungs.” In the working phase the actual assessment, teaching and problem-solving happen. In the termination phase you summarize, confirm understanding and say what happens next — including who is coming after you. Skipping orientation is the most common student error, and it is why patients answer their questions in monosyllables.
The techniques below are not scripts to memorize for an exam; they are the moves you will actually make forty times a shift. Practice them until they stop feeling artificial. The single highest-yield one is silence: after you ask a hard question, count to five in your head before you fill the space. Patients disclose in the gap.
| Technique | What it sounds like | Why it works |
|---|---|---|
| Open-ended question | “Tell me what the pain has been like since yesterday.” | Cannot be answered yes or no; yields the patient’s own story and words. |
| Silence | (pause 3–5 seconds, maintain attention) | Gives the patient room to organize a difficult thought. |
| Reflection | “You said you felt like a burden.” | Returns the feeling to the patient without judging it; invites elaboration. |
| Restating / paraphrasing | “So the shortness of breath only happens when you climb stairs.” | Confirms accuracy and shows you were listening. |
| Clarification | “I’m not sure I follow — when you say dizzy, do you mean the room spins or you feel faint?” | Separates vertigo from presyncope; the words patients use are imprecise. |
| Focusing | “Let’s stay with the chest pressure for a minute.” | Redirects a wandering history to the safety-critical thread. |
| Offering self | “I’ll sit with you for a few minutes.” | Presence without demanding conversation. |
| Making an observation | “You’ve been very quiet since your daughter left.” | Names non-verbal data gently; opens a door the patient can walk through or not. |
| Summarizing | “Here’s what I heard, tell me what I got wrong.” | Closes the encounter and lets the patient correct the record. |
| Non-therapeutic response | Example | What it actually does |
|---|---|---|
| False reassurance | “Don’t worry, everything will be fine.” | Dismisses fear and tells the patient not to bring it up again. |
| Why questions | “Why didn’t you take your insulin?” | Reads as accusation; produces defensiveness instead of the real barrier. Ask “What made it hard to take?” |
| Giving advice | “If I were you I’d have the surgery.” | Substitutes your values for theirs; undermines autonomy. |
| Changing the subject | Patient mentions dying; nurse asks about lunch. | Signals the topic is forbidden. |
| Approval / disapproval | “That was a good decision.” / “You shouldn’t feel that way.” | Makes the patient work for your approval and hide anything you might judge. |
| Defensiveness | “The night nurse is very experienced.” | Shuts down a complaint that may contain a safety report. |
| Stereotyped comfort | “Everything happens for a reason.” | Cliché substitutes for presence. |
Non-verbal communication, environment and body position
Patients decide within seconds whether you are actually available. Sit down. Studies of hospitalized patients consistently show that when the clinician sits, patients estimate the visit as longer than it was and report better communication — even when the actual seated time is shorter. Get your eyes at or below the level of the patient’s eyes. Standing over a supine adult is a power position and it feels like one. If there is no chair, crouch or sit on the edge of the recliner — not on the bed, which invades personal territory and is an infection-control problem.
The classic mnemonic is SOLER: Sit squarely facing the patient, Open posture (arms and legs uncrossed), Lean slightly forward, Eye contact appropriate to culture, Relaxed. Add the practical items SOLER leaves out: silence the television with permission, close the curtain and the door, lower the bed rail on the side you are sitting on while you are there and raise it again before you leave, and put your phone or workstation-on-wheels where it is not between you and the person. If you must type, narrate it — “I’m going to look at the screen for a second to check your last blood pressure, keep talking.”
Personal space matters and varies. Hall’s zones — intimate (0 to 18 inches), personal (18 inches to 4 feet), social (4 to 12 feet) — are a rough North American map, not a rule. Nursing work forces you into the intimate zone constantly, which is exactly why you announce each entry into it: “I’m going to listen to your back now, I’ll lift your gown from behind.” Direct eye contact is a sign of respect and attention in much of the United States and Western Europe, and can be read as confrontational or disrespectful in some East Asian, Indigenous American and traditional Middle Eastern contexts, particularly across gender or age differences. The safe practice is to offer eye contact and follow the patient’s lead rather than to enforce it.
Communicating across the lifespan, language and literacy
Infants and toddlers. Communication is with the caregiver and through the caregiver. Keep the child on the parent’s lap for as much of the exam as possible, save the invasive and distressing parts for last (ears and throat in a toddler always go last), and use the parent’s words for body parts. For preschoolers, expect magical and literal thinking: never say you are going to “take” their blood pressure or “take a little blood,” and never say a procedure will not hurt if it will. Offer real, narrow choices — “Which arm?” not “Can I check your blood pressure?” School-age children want mechanism and honesty; show them the equipment. Adolescents require time alone without the parent, an explicit statement of confidentiality and its legal limits, and a non-reactive face.
Pregnancy. Position matters after roughly 20 weeks: avoid prolonged supine positioning, which can cause aortocaval compression and supine hypotensive syndrome. Interview in a left-lateral tilt or seated. Ask about intimate partner violence privately, with no partner or family member in the room and never through a family interpreter — pregnancy is a period of elevated risk.
Older adults. Presbycusis is high-frequency hearing loss, so shouting (which raises pitch) makes comprehension worse. Lower your pitch, slow down, face the person so they can lip-read, reduce background noise, and confirm with teach-back. Never use elderspeak — “sweetie,” “honey,” “are we ready for our bath?” It is associated with resistance to care and with worse self-rated function. Allow extra processing time; older adults answer accurately, just more slowly. Ask about, and document, the patient’s preferred name.
Limited English proficiency. Use a qualified medical interpreter — in person, by video or by phone. This is a federal civil-rights requirement under Title VI, not a courtesy, and it is a patient-safety intervention: encounters without professional interpretation carry significantly more clinically consequential errors. Do not use family members, and never use a child, as an interpreter except in a life-threatening emergency while a qualified interpreter is being obtained. Speak to the patient, not the interpreter, in the first person and in short segments. Document the interpreter’s name or ID number and the modality used. For patients who are Deaf, ask their preference; American Sign Language is a distinct language and written English is often not equivalent.
Low health literacy. Roughly one in three US adults has difficulty with everyday health information, and it is invisible — people compensate skillfully. Use plain language (“high blood pressure” not “hypertension,” “water pill” not “diuretic”), limit teaching to three key points per encounter, and close with teach-back: “I want to be sure I explained this well. Tell me in your own words how you’ll take this new water pill at home.” Teach-back tests the teaching, not the patient, and you must say so.
Therapeutic communication is a clinical skill with a technique and a sequence — sit, orient yourself and your role, ask open-endedly, tolerate silence, and verify with teach-back — and its failures are as consequential as a missed vital sign.
Section 2Speaking Up: SBAR, Red Flags and Closed-Loop Communication
SBAR: the structure that makes you sound credible
SBAR — Situation, Background, Assessment, Recommendation — was adapted from nuclear submarine practice for exactly the problem nurses have: transferring urgent information to someone with more authority, over the phone, in under ninety seconds, without being dismissed. Many facilities use ISBAR, adding Introduction at the front, or ISBARR, adding Read-back at the end. Use whichever your employer uses, and use it every time, including when it feels like overkill. Structure is what lets the receiver find the important item.
The part students under-use is the R. New nurses frequently deliver a flawless S, B and A and then stop, leaving the provider to guess what is being asked. State what you want, out loud, even if you are not sure it is the right ask: “I’d like you to come see her now,” “I’m requesting an order for a stat 12-lead and troponin,” “I need a set of blood cultures and an order to start fluids.” If you are wrong, you have still made the request explicit and the conversation moves faster. Also state your time expectation and confirm the plan: “If she isn’t better in thirty minutes, I’ll call you back.”
| Element | What goes in it | Worked example (2 a.m. call) |
|---|---|---|
| Introduction | Your name, role, unit, patient name, room | “Dr. Reyes, this is Dana Whitfield, RN on 4 West. I’m calling about Ellen Marks, room 412.” |
| Situation | The problem, in one sentence, right now | “She’s become short of breath in the last twenty minutes and her oxygen saturation has dropped to 88 percent on 2 liters nasal cannula.” |
| Background | Admitting diagnosis, day of stay, relevant history, pertinent meds, code status | “She’s a 68-year-old admitted two days ago with a right hip fracture, post-op day 1 from ORIF. History of atrial fibrillation and CHF. She’s on apixaban, held pre-op. Full code.” |
| Assessment | Current vitals with numbers, your exam findings, your clinical impression | “Right now: heart rate 122 and irregular, blood pressure 98/56, respirations 28, temperature 37.1 Celsius, SpO₂ 88 percent on 2 liters, now 93 percent on a 6-liter mask. Lungs are clear bilaterally, no new edema, right calf is soft and non-tender. She’s anxious and diaphoretic. I’m concerned about a pulmonary embolism.” |
| Recommendation | What you want, and by when | “I’d like you to come evaluate her now. In the meantime I’m requesting orders for a stat CT pulmonary angiogram, ECG, troponin and BNP, and continuous pulse oximetry.” |
| Read-back | Repeat every order back and get confirmation | “Reading back: stat CTPA, 12-lead ECG, troponin and BNP now, continuous pulse ox, keep SpO₂ above 92 percent, and you’ll be here in ten minutes. Is that correct?” |
Red flags: the numbers that mean call now
You cannot escalate what you cannot recognize. Learn the adult normal ranges cold, then learn the thresholds that override everything you had planned for the next hour. Facilities vary slightly — know your unit’s parameters and your rapid response team criteria — but the values below are the common defaults, and a patient meeting any of them needs a provider or rapid response call, not a recheck at the end of your med pass.
| Parameter | Expected adult | Escalate NOW | What it suggests |
|---|---|---|---|
| Temperature (oral) | 36.5–37.5 °C (97.7–99.5 °F) | >38.0 °C (100.4 °F) or <36.0 °C (96.8 °F) | Infection; hypothermia is an ominous sepsis sign, especially in older adults |
| Heart rate | 60–100 beats/min | <40 or >130 beats/min; any new irregular rhythm with symptoms | Arrhythmia, hypovolemia, sepsis, pain, hypoxia |
| Respiratory rate | 12–20 breaths/min | <8 or >28 breaths/min | The earliest and most-ignored sign of deterioration; <8 suggests opioid toxicity |
| Blood pressure | <120/<80 mmHg (normal) | Systolic <90 mmHg, or a drop of >40 mmHg from the patient’s baseline; systolic >180 or diastolic >120 with symptoms | Shock; hypertensive emergency |
| SpO₂ | 95–100 percent on room air | <90 percent, or any new increase in oxygen requirement | PE, pneumonia, pulmonary edema, atelectasis, mucus plug |
| Level of consciousness | Alert and oriented to baseline | Any new confusion, agitation, unarousability, or a drop of 2 or more points on the Glasgow Coma Scale | Hypoxia, hypoglycemia, sepsis, stroke, bleed, drug effect |
| Urine output | At least 0.5 mL/kg/hr (about 30 mL/hr in an average adult) | <30 mL/hr for 2 consecutive hours | Hypovolemia, acute kidney injury, obstruction |
| Pain | At or below the patient’s goal | New severe pain, pain out of proportion to findings, chest pain, sudden severe headache | Ischemia, compartment syndrome, dissection, subarachnoid hemorrhage |
| Capillary glucose | 70–99 mg/dL fasting | <70 mg/dL (treat, then recheck in 15 min) or >400 mg/dL | Hypoglycemia is an emergency; treat before you call |
Ranges shift dramatically across the lifespan, and a “normal adult” heart rate in an infant is bradycardia. Memorize the pediatric bands well enough to know when a number is wrong for the age in front of you. Note that the wide neonatal band applies only through 28 days of life; from 1 month on, the upper limit is 180, so a rate of 195 in a 2-month-old is not a normal newborn rate but a finding that prompts evaluation for supraventricular tachycardia, pain, fever, hypovolemia or sepsis.
| Age | Heart rate (awake, beats/min) | Respiratory rate (breaths/min) | Systolic BP (approximate lower limit) |
|---|---|---|---|
| Neonate (birth to 28 days) | 100–205 | 30–60 | >60 mmHg |
| Infant (1 month to 1 year) | 100–180 | 30–53 | >70 mmHg |
| 1–2 years | 98–140 | 22–37 | >70 + (2 × age in years) |
| 3–5 years | 80–120 | 20–28 | >70 + (2 × age in years) |
| 6–11 years | 75–118 | 18–25 | >90 mmHg |
| 12–17 years | 60–100 | 12–20 | >90 mmHg |
| Pregnancy (2nd–3rd trimester) | Baseline rises 10–20 above pre-pregnancy | Unchanged rate; tidal volume rises | BP falls in 2nd trimester; ≥140/90 is abnormal and may signal preeclampsia |
| Older adult (65+) | 60–100 (blunted rise with stress) | 12–20 | Widened pulse pressure common; orthostatic drop common |
Closed-loop communication, read-back and the chain of command
Closed-loop communication (also called check-back) has three legs: the sender states the message, the receiver repeats it back in their own voice, and the sender confirms it was heard correctly. It is not optional for verbal or telephone orders and for critical laboratory values — it is a National Patient Safety Goal, and it is the practice that catches “fifteen” misheard as “fifty.” For medications, read back the drug name spelled out for sound-alikes, the dose with units, the route and the frequency: “Reading back: hydrALAZINE, h-y-d-r-a-l-a-z-i-n-e, 10 milligrams, IV push, one time now. Correct?”
A critical value is a laboratory result so far outside the expected range that it represents immediate risk — potassium below 2.5 or above 6.5 mmol/L, sodium below 120 or above 160 mmol/L, glucose below 50 or above 400 mg/dL, hemoglobin below 7 g/dL, platelets below 50,000/mm³, INR above 5, or a positive blood culture. When the lab calls one, you write it down, read it back, document the value, the name of the caller and the time, notify the provider, and document that notification with the time and the response. An undocumented notification is, legally, a notification that did not happen.
When you are worried and the person you called is not, you do not drop it. Use the graded assertiveness tools. CUS: “I am Concerned. I am Uncomfortable. This is a Safety issue.” Those words are recognized in most US hospitals as a formal stop signal. The two-challenge rule says that if you voice a concern twice and it is not acknowledged, you are obligated to escalate to the next level — charge nurse, rapid response team, nursing supervisor, attending physician, chief medical officer. You do not need permission to call a rapid response team, and in many facilities the patient or family can call one directly. Then document what you did, when, and to whom.
Escalation is a skill with defined numeric triggers, a defined structure (SBAR with an explicit recommendation), a defined verification step (read-back), and a defined path when you are not heard (CUS, the two-challenge rule, the chain of command).
Section 3Documentation: The Legal Record and How to Write It
What the chart is for, and the formats you will meet
The health record serves five purposes at once: it communicates with the team, it directs and evaluates care, it is the legal account of what happened, it drives reimbursement and coding, and it feeds quality and research data. The legal function is the one students underestimate. In a malpractice claim filed four years from now, the chart is the only witness that remembers. The standard the record is held to is simple and brutal: if it was not documented, it was not done — and the corollary, if it was documented but not done, that is fraud.
Six rules govern every entry regardless of format. Timely: chart as close to the event as possible, and never in advance — charting a medication before you give it is falsification even if you intend to give it in two minutes. Accurate and objective: record what you saw, heard, measured and did, not what you concluded about the patient’s character. Complete: include the assessment, the intervention, the patient’s response and any notification. Legible and permanent: black ink on paper, no pencil, no erasures, no white-out. Attributed: full signature with credentials, or your own EHR login — never share a password, never chart under another person’s login, and never let someone chart under yours. Chronological: use the facility’s clock convention, usually 24-hour time, and use late-entry format when you fall behind.
| Format | Structure | Where you will see it |
|---|---|---|
| Narrative | Chronological free-text paragraphs | Long-term care, home health, and the free-text box in any EHR |
| SOAP / SOAPIE | Subjective, Objective, Assessment, Plan (+ Implementation, Evaluation) | Problem-oriented records; providers and advanced practice |
| Focus / DAR | Focus (a concern, not necessarily a diagnosis), Data, Action, Response | Acute care nursing notes; the most nurse-friendly narrative format |
| PIE | Problem, Intervention, Evaluation | Units that chart from the nursing care plan |
| Charting by exception | Only deviations from a defined normal are narrated; normals are checked off | High-volume acute units. Efficient, but weak in litigation unless the “normal” standard is explicitly defined in policy. |
| Flowsheets / EHR structured fields | Discrete timed data: vitals, intake and output, pain, restraints, wounds | Everywhere. Most of your documentation volume lives here. |
How to actually chart it: vague versus precise
The difference between a defensible note and a worthless one is specificity. A vague note tells a reader nothing about trend, and trend is the whole point. Read the pairs below and notice that the precise version is not longer than the vague version by much — it is just made of measurements instead of adjectives.
| Vague — do not write this | Precise — write this |
|---|---|
| “Patient had a good night.” | “0300 Pt asleep, resp even and unlabored at 16/min, SpO₂ 97 percent on RA. Awakened for repositioning to left side; denies pain (0/10). Call light within reach, bed low and locked, 2 side rails up.” |
| “Tolerated ambulation well.” | “1420 Ambulated 60 feet in hallway with front-wheeled walker and 1-person standby assist. Pre-ambulation HR 84, BP 128/74, SpO₂ 96 percent RA; post HR 96, BP 124/70, SpO₂ 94 percent RA. Steady gait, no dyspnea or dizziness reported. Returned to chair.” |
| “Dressing changed, wound looks better.” | “1030 Sacral pressure injury, Stage 2, measures 3.5 cm × 2.0 cm × 0.2 cm. Partial-thickness loss with exposed dermis; wound bed pink, moist and viable, no slough, eschar or odor. Scant serous drainage on removed dressing. Periwound skin intact, no induration or warmth. Cleansed with normal saline, hydrocolloid applied, dated and initialed. Pt denies pain at site (0/10). Repositioned right side, heels offloaded on pillow.” |
| “Patient is uncooperative and difficult.” | “1015 Pt declined morning bath and 1000 metoprolol. States ‘That pill makes me feel like I am underwater.’ Educated on purpose of medication and risk of abrupt discontinuation; pt verbalized understanding and continued to decline. Dr. Alvarez notified at 1020, aware, no new orders. Pt remains alert, HR 88, BP 142/86.” |
| “Patient fell.” (unwitnessed) | “0215 Pt found sitting on floor at right side of bed on entering room in response to bed alarm. States ‘I was trying to get to the bathroom.’ No LOC reported by pt. Neuro check: alert, oriented ×4, PERRL, equal grip, no visible head injury. 3 cm superficial abrasion right elbow, no active bleeding. Denies neck, back or hip pain; no deformity, shortening or external rotation of either leg; full active ROM all extremities before moving. HR 92, BP 132/78, RR 18, SpO₂ 96 percent RA, glucose 118. Assisted to bed with 2-person assist using gait belt. Dr. Alvarez notified 0222; orders received for neuro checks q1h ×4. Family notified 0230.” |
| “Complained of chest pain, gave nitro.” | “0940 Pt reports substernal chest pressure 7/10, non-radiating, onset at rest 5 minutes ago, associated with nausea and diaphoresis. HR 104, BP 148/88, RR 22, SpO₂ 94 percent RA, afebrile. 12-lead ECG obtained 0942 and shown to Dr. Alvarez. Nitroglycerin 0.4 mg SL given 0944 per protocol. 0949 pain 3/10, BP 132/76. 0954 pain 0/10.” |
Chart what you assess in the order you assessed it, because the order is part of the technique. The standard sequence for every body region is inspection, palpation, percussion, auscultation. The abdomen is the exception: inspect, then auscultate, then percuss, then palpate — because percussing or palpating first mechanically stimulates the bowel and alters the bowel sounds you are about to report. Charting “abdomen soft, non-tender, bowel sounds present” when you palpated before you listened is documenting a finding you contaminated. A correct entry reads: “1100 Abdomen inspected: flat, symmetric, no distention, scars or visible pulsation. Bowel sounds active ×4 quadrants. Tympany throughout except dullness over liver. Soft, non-tender to light and deep palpation, no masses or guarding.”
Describing skin findings across skin tones. Pallor, cyanosis, jaundice and erythema are described in most textbooks as they appear in lightly pigmented skin, and students then miss them entirely in patients with darker skin. Do not chart “pink and well perfused” as a reflex on every patient. Assess and describe the sites where pigment interferes least — the oral mucosa, conjunctivae, sclerae, tongue, nail beds, palms and soles — and compare with the patient’s own uninvolved skin. Also palpate, because in darkly pigmented skin, erythema and early pressure injury are more reliably detected as warmth, induration, edema or a change in texture than as redness.
| Finding | Lightly pigmented skin | Darkly pigmented skin — where and how to look | Chart it as |
|---|---|---|---|
| Cyanosis | Blue-gray lips, nail beds, skin | Skin appears ashen or gray; check conjunctivae, oral mucosa, tongue, palms and soles for dusky gray-blue tone | “Oral mucosa and tongue dusky gray; nail beds gray-blue; SpO₂ 86 percent RA. Oxygen applied, HOB elevated, rapid response called 1412.” |
| Pallor | Loss of pink tone, white or waxy | Skin loses underlying red tones and appears yellow-brown or ashen; conjunctivae and palmar creases pale | “Conjunctivae pale, palmar creases pale, skin ashen compared with baseline.” |
| Jaundice | Yellow skin and sclerae | Check sclerae (avoid confusing with normal subconjunctival fat, which is yellow only peripherally), hard palate, palms and soles | “Sclerae icteric bilaterally; yellow discoloration of hard palate and palms.” |
| Erythema / inflammation | Redness, warmth | May appear purple, violaceous, darker than surrounding skin or not visibly discolored at all — palpate for warmth, firmness, edema, and ask about pain or itching | “Right calf warm and firm to touch, 2 cm larger circumference than left, darker and violaceous compared with surrounding skin, tender. Dr. Alvarez notified 1505 for possible DVT.” |
| Petechiae | Pinpoint red-purple spots | Best seen on the abdomen, buttocks, oral mucosa and conjunctivae | “Scattered non-blanching pinpoint purple macules on buccal mucosa and lower abdomen.” |
Errors, abbreviations, privacy and EHR-specific traps
Correcting an error on paper: draw a single line through the entry so the original remains readable, write “error” or “mistaken entry” above or beside it, add your initials, the date and the time, and then write the correct entry. Never obliterate, erase, use correction fluid or write over. In the EHR: use the built-in amendment or addendum function; the original stays in the audit trail forever regardless, so never attempt to hide anything. A late entry is labeled as such: “1900 Late entry for 1345 — ...” Backdating an entry to make it look contemporaneous is fraud.
The Joint Commission Do Not Use list applies to all orders and all handwritten and free-text documentation: do not write U or u (write “unit”), IU (write “international unit”), Q.D., QD, q.d., qd (write “daily”), Q.O.D., QOD (write “every other day”), a trailing zero (write 1 mg, never 1.0 mg), a missing leading zero (write 0.5 mg, never .5 mg), and MS, MSO₄, MgSO₄ (write “morphine sulfate” or “magnesium sulfate”). Each of these has killed people: 1.0 mg read as 10 mg is a tenfold overdose.
Privacy. Protected health information is anything that identifies the patient combined with health information. Under HIPAA you access only the records of patients in your care — not your neighbor’s, not a celebrity’s, not your own family member’s without authorization — and every access is logged and audited. Do not discuss patients in elevators, hallways or cafeterias. Do not photograph a patient, a wound or a monitor with a personal phone. Do not post anything on social media, including de-identified stories, room numbers or shift complaints; nurses lose licenses for this every year. Log out of the workstation every time you walk away.
Finally, two EHR-specific hazards. Copy-forward propagates yesterday’s assessment into today’s note, which means it propagates yesterday’s errors and makes the record legally indefensible; if you copy anything forward, you must read and edit every line. Wrong-patient charting happens when multiple charts are open; verify the name and date of birth on the banner before every entry. And keep the incident or variance report out of the medical record entirely — document the facts of what happened to the patient and the notification in the chart, complete the incident report separately as a quality-improvement document, and never write “incident report filed” in the nursing note, because doing so drags the report into discovery.
Documentation is objective, timed, attributed and specific enough to show a trend — measurements and quotations, never adjectives and conclusions — and it is written in the sequence the assessment was actually performed.
Section 4Handoff and Transitions of Care
Why handoffs fail, and the structures that fix them
A handoff is the transfer of responsibility and accountability for a patient from one clinician to another, along with the information required to act. It happens at shift change, at breaks, at transfer between units, at transport to and from procedures, and at discharge. It is the highest-risk moment in a hospital stay because responsibility can quietly land on nobody. Analyses of sentinel events repeatedly find handoff communication among the leading contributing factors, and the estimated cost of communication failure in US hospitals runs into the billions of dollars annually.
Handoffs fail for predictable reasons: information overload (a fifteen-minute recitation of the entire chart, with the critical item buried in minute eleven), omission of pending items (a culture that has not resulted, a scan that has not been read), interruptions, distraction, no opportunity to ask questions, and no explicit statement of who now owns the patient. The fixes are structural. Use a standardized format every time. Give the receiver protected, uninterrupted time. End with questions and an explicit transfer: “You have her.”
I-PASS is the best-validated structure; its implementation across pediatric residency programs was associated with a roughly 30 percent reduction in preventable adverse events without lengthening handoffs. Many nursing units use ISBAR instead, which is fine — consistency matters more than which acronym.
| I-PASS element | What you say | Example |
|---|---|---|
| Illness severity | Stable, “watcher,” or unstable — one word, said first | “Bed 12 is a watcher.” |
| Patient summary | Name, age, code status, diagnosis, day of stay, events of this shift | “Ellen Marks, 68, full code, POD 1 right hip ORIF. Desaturated to 88 percent at 0200, now on 4 liters, CTPA negative for PE, thought to be atelectasis.” |
| Action list | What must be done, by whom, and by when | “Incentive spirometer q1h while awake, out of bed to chair with PT at 1000, recheck CBC at 1200.” |
| Situation awareness and contingency planning | What might go wrong and exactly what to do if it does | “If her SpO₂ drops below 92 on 4 liters, get an ABG and call Dr. Reyes; she has a standing order for a chest x-ray.” |
| Synthesis by receiver | The receiving nurse reads back the plan and asks questions | “So: watcher, POD 1 hip, desat overnight, spirometer hourly, chair at 1000, CBC at noon, ABG and call if she drops below 92. Anything pending?” |
Bedside shift report: how it is actually done
Bedside shift report moves handoff from the nurses’ station into the room, with the patient and (with the patient’s permission) family present. It is associated with fewer falls during shift change, fewer call-light requests immediately after report, better patient experience scores and earlier catching of errors — because the patient is the only person in the building who was present for the entire admission. Run it like this:
1. Introduce. Both nurses enter together; the off-going nurse introduces the on-coming nurse by name and role. 2. Invite. Ask the patient’s permission for anyone else present to hear the report. 3. Report. Use your standard format, speak to the patient rather than across them, and avoid jargon — say “your kidney function test” rather than “creatinine trending up.” 4. Look. Do a joint visual check together: IV site and what is infusing at what rate, drains and output, oxygen and flow rate, dressings, drips and pumps, the last dose of pain medication, the fall-risk and skin-risk status, the safety items — bed low and locked, call light in reach, non-skid socks. 5. Involve. Ask the patient what their most important goal is for this shift. 6. Close. The on-coming nurse restates the plan, answers questions, and updates the whiteboard with their name and the goal.
Two judgment calls. First, sensitive information — a new cancer diagnosis the patient has not been told, HIV status, substance use, suspected abuse, a psychiatric history — is discussed outside the room or in general terms, then completed privately. Second, if the patient is asleep, you still enter, verify identity and the safety items visually, and keep voices low; you do not skip the room.
Transfers, procedures and discharge
Unit-to-unit transfer requires a nurse-to-nurse verbal report, not just a note. Include everything in I-PASS plus: isolation precautions and why, allergies, code status and any advance directive, lines and tubes with insertion dates, last medication doses (especially opioids, anticoagulants and antibiotics), pending results, and family contact and who has been notified of what. Send the belongings and the assistive devices — glasses, hearing aids, dentures, walker — and document what went with the patient. Procedure and OR handoffs add: NPO status and time, site marking, consent, last anticoagulant dose, and blood availability.
Discharge is a handoff to the patient, and it is where most preventable readmissions are born. Do not deliver it in the last ten minutes while the wheelchair waits. Start discharge teaching on admission. At discharge, cover in plain language: medications (what, why, when, what to stop — reconcile against the home list explicitly), follow-up appointments with date, time and address, activity and diet restrictions, wound or device care demonstrated back to you, and above all the warning signs that mean call the office or come back, written down and specific: a temperature above 38.0 °C (100.4 °F), redness spreading from the incision, calf pain or swelling, shortness of breath, chest pain, or an inability to keep fluids down. Then use teach-back on the two most dangerous items, and document that you did, including the patient’s response.
A handoff is complete only when it is standardized, includes contingency planning for what might go wrong, and ends with the receiver saying the plan back — and at the bedside, with the patient included as a source of truth.
Section 5Delegation, Difficult Conversations and Conflict
Delegating to UAP: what transfers and what never does
Delegation is the transfer of the authority to perform a selected task in a selected situation to a competent person, while the RN retains accountability for the outcome. That last clause is the one to burn in. You can delegate the task; you can never delegate the accountability, and you can never delegate the thinking steps of the nursing process — assessment, nursing diagnosis, planning, teaching and evaluation. Distinguish delegation from assignment, which is the routine transfer of activities that are already within the receiver’s own scope of practice.
The five rights of delegation are the checklist: the right task (delegable, repetitive, predictable, with a predictable outcome), under the right circumstance (a stable patient, appropriate setting, available resources), to the right person (verified competence for this task with this patient, not just a job title), with the right direction and communication (specific, measurable, with limits and a reporting threshold), and the right supervision and evaluation (you monitor, intervene as needed, evaluate the outcome and give feedback).
| May be delegated to UAP | Stays with the RN — never delegated |
|---|---|
| Vital signs on a stable patient | The initial and any ongoing assessment, and interpretation of any data |
| Bathing, oral care, perineal care, hygiene, bed-making | Nursing diagnosis and care planning |
| Assisting with feeding a patient without swallowing difficulty | Feeding a patient with dysphagia or aspiration risk |
| Ambulation, transfers and positioning of a stable patient | First ambulation after surgery or after epidural, or any unstable patient |
| Measuring and recording intake and output, weights | Evaluation of the patient’s response to any intervention |
| Blood-glucose fingersticks (where policy permits) | Patient and family teaching in any form |
| Specimen collection, applying non-sterile dressings (per policy) | Medication administration (except where state law permits certified medication aides) |
| Stocking, transporting, reporting observations | Any care of an unstable or unpredictable patient; anything requiring clinical judgment |
Delegate in a sentence with numbers and a threshold, then require a check-back. Weak: “Can you get vitals on 12?” Strong: “Marcus, please take a full set of vitals on Mrs. Marks in 412 within the next fifteen minutes, and come tell me right away if her heart rate is above 110, her systolic is below 100, or her oxygen saturation is below 92 percent. Write them in the flowsheet and let me know when they are in. Does that work with what else you have?” The final question is not politeness — it surfaces the fact that Marcus already has two showers and a transport, which is information you need before you count on those vitals. Licensed practical/vocational nurses have a broader scope than UAP that varies by state; they commonly administer many medications, perform sterile procedures and reinforce teaching, but the initial comprehensive assessment, the care plan, IV push medications in many states, and blood administration typically remain with the RN.
Hard conversations: anger, bad news, refusal
The angry patient or family member. Anger at the bedside is almost always fear, grief, pain or powerlessness in disguise. Do not match volume. Position yourself with a clear exit path behind you, keep your hands visible and open, lower your voice slightly, and use the sequence: acknowledge, apologize for the experience without admitting fault where none is established, ask, and act. “I can see you’re furious, and waiting four hours for pain medicine would make me furious too. I’m sorry that happened. Tell me what is most urgent right now and I’ll deal with that first.” Then actually do the thing and come back when you said you would. If the person becomes threatening, leave, get help and notify security; you are never obligated to remain in a room where you are unsafe, and workplace violence is a reportable event.
Bad news and hard questions. When a patient asks “Am I dying?”, the worst answers are false reassurance and deflection. Explore before you inform: “That’s a big question. What are you most worried about?” Diagnosis and prognosis disclosure belongs to the provider, but the conversation afterward belongs largely to you: silence, presence, permission to cry, and honest answers to the questions you can answer. Do not fill the silence.
Refusal of care. A competent adult may refuse anything, including care you believe is life-saving. Your obligations are to ensure the refusal is informed, to notify the provider, and to document. Document the specific care refused, the education provided, the consequences explained, the patient’s stated reason in their own words, the assessment of decision-making capacity, the provider notified with the time, and any alternative offered and accepted. For discharge against medical advice, document the risks explained, that the patient could state them back, whether they signed the AMA form, and that they were told they may return at any time — refusing to sign the form does not invalidate the departure and does not void insurance coverage, a common and harmful myth.
Conflict with the team, and speaking up in a hierarchy
Conflict on a unit is not a character flaw; it is structural, and unresolved conflict is a patient-safety hazard. The five classic modes are avoiding, accommodating, competing, compromising and collaborating. Collaborating produces the best long-term outcome and takes the most time; competing is appropriate only in an emergency when one person must direct. Most day-to-day disagreement is best handled with an I-statement and a specific request delivered privately: “When the 0800 medications were still in the drawer at 1000, I had to re-time the whole day and the patient missed a dose. I need us to check the drawer together at handoff.” Blame is “you never,” and it ends the conversation.
Disruptive or intimidating behavior — belittling, throwing, refusing to answer a page, public humiliation — is not something to absorb quietly. The Joint Commission considers such behavior a patient-safety issue precisely because it makes people stop speaking up. Document the facts objectively, report through your chain of command, and use CUS language in the moment. If you are a student or a new graduate, this is genuinely hard; use the words anyway, and remember that a rapid response call needs no one’s permission.
Finally, when an error occurs, communication is a duty rather than a choice. Assess and stabilize the patient first, notify the provider, follow the facility’s disclosure policy, complete the incident report, and document in the chart only the objective facts about the patient: what was given or done, the assessment, the notification with the time, the interventions and the response. Never chart speculation, never chart blame, and never chart that a report was filed.
You may delegate tasks but never assessment, teaching, evaluation or the unstable patient — and whether you are directing a UAP, defusing an angry family or challenging a physician, the message must be specific, measurable and closed with a check-back.
The chapter in one breath
Communication is the vehicle that carries assessment into action, and every leg of the trip has a technique. With the patient, sit down, orient yourself and your role, ask open-ended questions, tolerate silence, avoid false reassurance and “why” questions, use a qualified medical interpreter rather than a family member, and verify understanding with teach-back. With the team, use SBAR — and finish it with an explicit recommendation, because a report without an ask is not an escalation. Know the numbers that mean call now: respirations under 8 or over 28, systolic under 90, heart rate under 40 or over 130, SpO₂ under 90 percent, urine output under 30 mL/hr, any new confusion, and in an older adult a temperature over 37.8 °C or simply “not herself.” Close every loop: read back verbal orders and critical values, and if you are not heard, use CUS, the two-challenge rule and the chain of command. Document objectively, with measurements and quotations rather than adjectives, in the sequence the exam was performed — inspect, palpate, percuss, auscultate, except the abdomen, where auscultation comes second. Describe skin findings at the mucosa, conjunctivae, palms and soles so they are not missed in darker skin. Hand off with a standardized structure, contingency plans and a read-back at the bedside. Delegate tasks; keep assessment, teaching, evaluation and the unstable patient.
Words worth knowing
| Term | What it means |
|---|---|
| Therapeutic communication | Goal-directed, patient-centered interaction using deliberate techniques to build trust and gather accurate data. |
| Open-ended question | A question that cannot be answered yes or no, eliciting the patient’s own account (“Tell me about...”). |
| Non-therapeutic response | A reply that closes communication — false reassurance, advice-giving, “why” questions, changing the subject. |
| Teach-back | Asking the patient to restate instructions in their own words to verify the teaching, not to test the patient. |
| Qualified medical interpreter | A trained, credentialed interpreter provided by the facility; legally required for limited English proficiency, and never a family member or child. |
| SBAR / ISBAR | Situation, Background, Assessment, Recommendation (with Introduction) — the standard structure for urgent clinical communication. |
| Closed-loop communication | Sender states, receiver repeats back, sender confirms. Required for verbal orders and critical values. |
| Read-back | Verbatim repetition of a verbal or telephone order, including drug spelling, dose, route and frequency. |
| Critical value | A lab result representing immediate danger (for example K⁺ below 2.5 or above 6.5 mmol/L) that must be read back, documented and reported at once. |
| Early warning score (MEWS/NEWS) | A points system converting vital signs into a numeric deterioration risk that triggers a defined escalation response. |
| CUS / two-challenge rule | “Concerned, Uncomfortable, Safety issue”; if a concern is raised twice without acknowledgment, you must escalate up the chain of command. |
| Charting by exception | Documenting only deviations from a policy-defined normal; efficient but legally weak unless the normal standard is explicit. |
| Focus (DAR) charting | A note structured as Data, Action, Response around a focus such as pain, mobility or a patient concern. |
| Late entry | An entry made after the fact, labeled with both the current time and the time of the event; never backdated. |
| Do Not Use abbreviations | The prohibited list: U, IU, Q.D., Q.O.D., trailing zeros (1.0 mg), missing leading zeros (.5 mg), MS, MSO₄, MgSO₄. |
| PHI / HIPAA | Protected health information and the federal law governing it; access is limited to patients in your care and every access is audited. |
| Incident (variance) report | A separate quality-improvement document about an adverse event; never filed in or referenced within the medical record. |
| Handoff / I-PASS | Transfer of responsibility with the information to act; I-PASS = Illness severity, Patient summary, Action list, Situation awareness, Synthesis by receiver. |
| Bedside shift report | Handoff conducted in the room with the patient present, including a joint visual safety and equipment check. |
| Delegation and the five rights | Transferring a task while retaining accountability: right task, circumstance, person, direction/communication, and supervision/evaluation. |
Check yourself
SAFETY, ASEPSIS AND INFECTION PREVENTION
Nothing you do at the bedside matters if the patient is harmed by the care itself. Roughly one in every thirty-one hospitalized patients in the United States has a healthcare-associated infection on any given day, and falls, medication errors and misidentification remain among the most common preventable injuries in hospitals. This chapter is about the two habits that prevent most of that harm: a disciplined approach to physical safety, and an equally disciplined approach to breaking the chain of infection. You will learn to identify a patient correctly, screen for fall risk, use restraints only as a last resort and within legal limits, and respond to fire and to a sharps exposure. You will learn the five moments for hand hygiene, when alcohol is not enough, the exact order for donning and doffing personal protective equipment, the three tiers of transmission-based precautions with the diseases that belong to each, and the rules of a sterile field. Every rule here has a body attached to it.
By the end of this chapter you can
- Apply the elements of a culture of safety — two patient identifiers, time-out, rapid response activation and non-punitive event reporting — to a bedside scenario.
- Screen a patient for fall risk with a validated tool, implement targeted interventions, and document a fall with objective language.
- State the legal and monitoring requirements for restraints, including order limits, face-to-face evaluation timeframes and release intervals.
- Trace the six links of the chain of infection and name the specific nursing action that breaks each link.
- Assess a patient for local and systemic infection using inspection, palpation, percussion and auscultation in correct order, including the abdominal exception, and recognize how findings differ across the lifespan and across skin tones.
- Perform hand hygiene at each of the five moments, and identify the situations that require soap and water rather than alcohol-based hand rub.
- Don and doff personal protective equipment in the correct sequence and explain why each step is ordered as it is.
- Differentiate standard, contact, droplet and airborne precautions, name representative diseases for each tier, and set up the room and transport correctly.
- Distinguish medical asepsis from surgical asepsis, maintain a sterile field, apply the CLABSI, CAUTI, VAP and SSI prevention bundles, and delegate appropriately to unlicensed assistive personnel.
Section 1A Culture of Safety and the Patient Environment
Safety is a system, not a personality trait
Careful people still make errors. The nurse who has never been distracted, never been interrupted mid-task and never worked short-staffed does not exist. Modern patient safety science accepts that human error is inevitable and builds systems that catch it before it reaches the patient: barcode scanning, independent double checks on high-alert medications, standardized handoff, forcing functions that make the wrong move physically impossible. Your job is not to be flawless. Your job is to use the system as designed, every time, and to speak up when the system is failing.
The phrase just culture describes an organization that distinguishes among human error (a slip — console and fix the system), at-risk behavior (drifting from policy because the shortcut usually works — coach), and reckless behavior (conscious disregard of a substantial risk — discipline). This distinction matters to you as a student because it explains why reporting is safe. When you scan a wristband and the system flags the wrong drug, that is a near miss and it is worth reporting. Near misses are free lessons; the alternative is learning the same lesson from an injured patient.
An event report (incident report) is an internal quality document. Complete it for any fall, medication error, near miss, equipment failure or exposure. Two rules students get wrong constantly: first, you still chart the clinical facts of the event and your assessment in the medical record; second, you never write “incident report completed” or “error made” in the medical record. The chart describes what happened to the patient and what you did about it. The event report is the parallel document that feeds quality improvement, and referencing it in the chart can strip its protected status.
The same system gives you a way to summon help before a patient arrests. A rapid response team brings critical care expertise to the bedside for a patient who is deteriorating but has not yet coded, and in most hospitals any staff member — including a student — and often the patient or family may activate it without a practitioner’s order. Typical triggers are an acute change in heart rate to below 40 or above 130, respiratory rate below 8 or above 28, systolic pressure below 90 mm Hg, oxygen saturation below 90 percent despite supplemental oxygen, a new or prolonged seizure, acute chest pain, a sudden fall in level of consciousness or urine output, or simply that a staff member is worried about the patient. That last criterion is a real, written criterion and you are allowed to use it. Call early, do not wait for a returned page, and do not talk yourself out of it because the numbers are only almost at threshold. Failure to rescue — deterioration that was visible in the chart for hours before anyone acted — is one of the most studied preventable causes of hospital death, and the fix is almost always someone calling sooner.
Identifying the right patient, every single time
Wrong-patient events almost always trace back to a shortcut in identification. The Joint Commission’s first National Patient Safety Goal requires two patient identifiers before any medication, blood product, specimen collection, treatment or procedure. Acceptable identifiers are full name, date of birth and medical record number. A room number or bed location is never an identifier — patients move. Whenever the patient is able, use an open-ended question: “Please tell me your full name and date of birth,” not “Are you Mr. Alvarez?” A confused, sedated or hard-of-hearing patient will agree to almost any name.
Compare what the patient says with the wristband and with the order, and stop if any of the three disagree. For a patient who cannot state their name, verify the band against the record and, when policy allows, confirm with a family member or a second nurse. Blood administration adds a two-person verification of the unit, the blood type and the patient identifiers at the bedside. Before an invasive procedure, the team performs a time-out: everyone stops, and the team confirms correct patient, correct procedure, correct site and side (marked by the proceduralist), correct position, availability of implants and imaging, and antibiotic prophylaxis. Anyone in the room, including a student, may halt a time-out that does not match.
Falls: predict, prevent, and if it happens, document precisely
Falls are the most common adverse event reported in hospitals, and about a quarter of inpatient falls cause injury. Screening is done with a validated tool on admission, on transfer, after a change in condition, after a fall, and at least each shift per policy. The Morse Fall Scale scores history of falling, secondary diagnosis, ambulatory aid, intravenous therapy, gait and mental status; a score of 45 or higher is high risk (25 to 44 is moderate). The Hendrich II Fall Risk Model flags confusion, depression, altered elimination, dizziness, male sex, antiepileptics, benzodiazepines, and a timed get-up-and-go; a score of 5 or greater is high risk. Whichever tool your facility uses, the score is not the intervention. The score tells you to act.
Universal fall precautions apply to every patient: bed in the lowest position with wheels locked, call light and personal items within reach, adequate lighting, nonskid footwear, clear pathways, and orientation to the room. High-risk patients add purposeful hourly rounding using the four Ps — pain, potty, position, possessions — because most falls occur when a patient tries to get to the bathroom alone. Add a bed or chair alarm, a visual identifier per policy, a low bed with a floor mat, assistive devices in reach, and a toileting schedule. Review the medication list: benzodiazepines, opioids, antipsychotics, antihypertensives, diuretics, hypoglycemics and anticholinergics all raise risk, and four or more medications of any kind raises risk further. Check orthostatic vital signs in the patient who reports dizziness on standing: a drop of 20 mm Hg or more in systolic pressure, 10 mm Hg or more in diastolic pressure, or a rise in heart rate of 20 beats per minute or more within three minutes of standing is a positive result.
Raising all four side rails is a restraint, not a fall precaution. Two or three rails up for mobility and positioning is standard; four rails up on a bed confines the patient and, if they climb over, converts a two-foot fall into a four-foot fall onto the head. If a patient does fall, do not lift them first. Assess in place: level of consciousness, airway, breathing, circulation, pain, obvious deformity, head strike, and neurologic status. Take a full set of vital signs, and if the patient is anticoagulated or struck their head, escalate immediately for imaging and neurologic checks per protocol.
Restraints: the last option, with hard legal limits
A restraint is any manual method, physical device, material or equipment that immobilizes or reduces the ability of a patient to move freely, or any drug used as a restriction to manage behavior that is not standard treatment for the patient’s condition. Mittens tied to the bed are restraints; mittens alone usually are not. Four side rails up are a restraint. A tucked-in sheet the patient cannot get out of is a restraint. Under the Centers for Medicare and Medicaid Services Conditions of Participation, restraints require a practitioner’s order that is never written as PRN, must use the least restrictive effective method, and must be discontinued at the earliest possible time.
Always try alternatives first and document that you did: reorient the patient, move them closer to the nurses’ station, provide a sitter or family presence, treat pain, address hunger and toileting needs, reduce noise and lighting at night, offer a diversional activity or an activity apron, review deliriogenic medications, and camouflage lines under clothing or a stockinette. Delirium, not defiance, drives most of the pulling at tubes; treat the delirium.
| Requirement | Violent or self-destructive behavior | Non-violent, non-self-destructive (medical or surgical) |
|---|---|---|
| Typical indication | Imminent danger to self or others | Protecting a life-sustaining device the patient is pulling at, such as an endotracheal tube or central line |
| Order | Practitioner order required; never PRN | Practitioner order required; never PRN |
| Maximum order duration before renewal | 4 hours for adults 18 and older; 2 hours for ages 9–17; 1 hour for children under 9 | Renewed per hospital policy, and at least once each calendar day after in-person evaluation |
| Face-to-face evaluation | Within 1 hour of initiation by a physician or trained licensed practitioner | Not required within 1 hour; evaluation per policy |
| Total time before in-person re-evaluation | Orders may be renewed up to 24 hours total | Daily, ongoing |
| Monitoring | Continuous or per policy, commonly every 15 minutes | Commonly every 2 hours, per policy |
| Release and care | Release every 2 hours to assess and document skin integrity, circulation, sensation, range of motion; offer toileting, fluids, nutrition and repositioning | |
Technique matters. Tie limb restraints to the movable bed frame, never to a side rail — a rail that is lowered will wrench the limb. Use a quick-release knot that unties with a single pull, never a square knot or a bow that can jam. You should be able to slide two fingers between the restraint and the patient’s skin. Never place a patient in restraints in the prone position, and never restrain the arms above the head. Document the specific behavior that necessitated the restraint, the alternatives tried and their outcomes, the type and location of the device, the time applied, every assessment and release, the patient and family education provided, and the time of discontinuation. Restraint documentation is one of the most heavily surveyed records in the hospital.
Patient safety is a set of standardized, repeatable behaviors — two identifiers, time-out, fall screening with targeted intervention, restraints only as a last resort within legal limits — not a matter of individual carefulness.
Section 2Microbes, the Chain of Infection and Assessing the Infected Patient
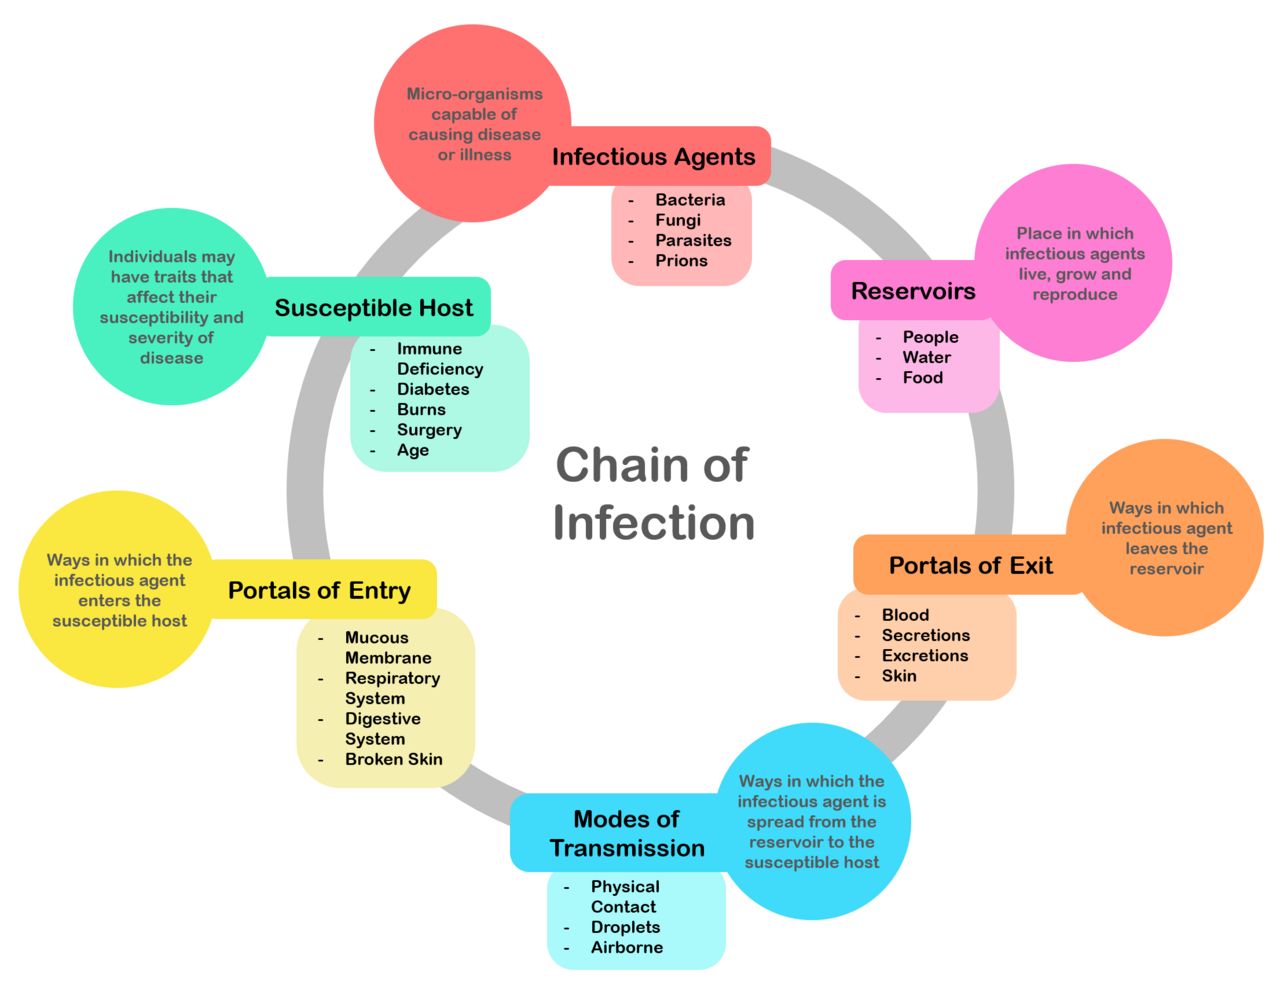
Six links, six chances to intervene
Infection requires an unbroken chain. An infectious agent (bacterium, virus, fungus, protozoan, prion) must live in a reservoir (a human, an animal, water, equipment, the environment), leave through a portal of exit (respiratory secretions, blood, stool, urine, wound drainage, skin), travel by a mode of transmission (contact — direct or indirect, droplet, airborne, vehicle such as contaminated food or fluid, or vector), enter a new host through a portal of entry (mucous membranes, broken skin, an intravenous catheter, a urinary catheter, the respiratory tract), and find a susceptible host. Remove any one link and there is no infection. Nurses spend their whole careers working links three, four and five.
| Link | Example | Nursing action that breaks it |
|---|---|---|
| Infectious agent | Clostridioides difficile, MRSA, influenza A, Candida auris | Antimicrobial stewardship, prompt culture before antibiotics, correct disinfectant selection |
| Reservoir | Infected wound, colonized nares, contaminated sink drain, standing water in a humidifier | Wound care, environmental cleaning, dating and changing tubing and solutions, no flowers or standing water in immunocompromised rooms |
| Portal of exit | Cough, diarrhea, wound drainage, blood on a sharp | Respiratory etiquette, contain drainage in an occlusive dressing, safe sharps handling, cover the source |
| Mode of transmission | Unwashed hands, a shared blood pressure cuff, aerosols | Hand hygiene, gloves and gown, dedicated or disinfected equipment, transmission-based precautions |
| Portal of entry | Central line hub, indwelling catheter, endotracheal tube, surgical incision | Aseptic technique, scrub the hub, closed drainage systems, remove devices as early as possible |
| Susceptible host | Older adult, neutropenic patient, diabetic patient, neonate | Vaccination, nutrition and glycemic control, mobility, skin integrity, early treatment of underlying disease |
Two words to keep straight: colonization means the organism is present and multiplying without tissue damage or host response — a patient may be colonized with MRSA in the nares for years. Infection means the organism is causing damage and the host is responding. A positive nasal swab in a patient with no symptoms is colonization and is not treated with antibiotics, although it may still trigger precautions because the patient can shed the organism. A healthcare-associated infection is one that was not present or incubating on admission, most commonly bloodstream, urinary, surgical site, pneumonia and C. difficile infections.
Assessing for infection at the bedside — the correct exam sequence
Physical assessment follows a fixed order: inspection, palpation, percussion, auscultation. Inspect first, because touching changes what you see (pressing on skin blanches it) and because looking costs nothing. Palpate second, using light palpation to about 1 cm before deep palpation to 4 to 5 cm, warm hands, short nails, and always palpating the tender area last so guarding does not contaminate the rest of the exam. Percuss third, listening for the resonance that tells you whether tissue underneath is air-filled, fluid-filled or solid. Auscultate fourth, with the diaphragm for high-pitched sounds and the bell for low-pitched sounds, on skin and never through a gown.
The abdomen is the exception, and it is the exception you will be asked about. For the abdomen the order is inspect, auscultate, percuss, palpate. Auscultation moves ahead of percussion and palpation because pressing on the abdomen mechanically stimulates or suppresses peristalsis and will give you falsely altered bowel sounds. Listen in all four quadrants, beginning in the right lower quadrant over the ileocecal valve, with the diaphragm, for 5 to 20 seconds per quadrant if sounds are present. Normal is 5 to 30 gurgles per minute. Before you may document absent bowel sounds you must listen for a full 5 minutes in a quadrant. This matters clinically in this chapter because the patient with suspected C. difficile colitis needs an abdominal exam, and a nurse who palpates first has destroyed the most useful piece of data they had.
For a wound or an intravenous site, inspect for the classic local signs — erythema, edema, warmth, pain, purulent drainage, loss of function — then palpate for warmth compared with the opposite limb, induration, fluctuance suggesting an abscess, and crepitus, which is an emergency. Measure the area of erythema in centimeters and mark its border with a skin pen and the time, so the next nurse can tell whether cellulitis is advancing. Note the drainage by amount, color and odor: serous (clear), sanguineous (bloody), serosanguineous (pink), or purulent (thick, opaque, yellow, green or brown).
Normal, abnormal and what the abnormal means
| Parameter | Expected adult finding | Abnormal finding | What it suggests |
|---|---|---|---|
| Temperature | 36.5–37.5 °C oral (97.7–99.5 °F); rectal about 0.5 °C higher, axillary about 0.5 °C lower | ≥ 38.0 °C (100.4 °F) = fever; < 36.0 °C (96.8 °F) = hypothermia | Fever: infection, inflammation, drug reaction. Hypothermia in an ill adult is an ominous sepsis sign, not reassurance |
| Heart rate | 60–100 beats/min, regular | > 100 (tachycardia), especially with fever or hypotension | Early compensation for sepsis, hypovolemia, pain, hypoxia |
| Respiratory rate | 12–20 breaths/min, unlabored | ≥ 22 breaths/min | The earliest and most ignored sign of deterioration; a qSOFA criterion |
| Blood pressure | Less than 120/80 mm Hg; MAP 70–100 mm Hg | Systolic ≤ 100 mm Hg, or a fall of more than 40 mm Hg from baseline; MAP < 65 mm Hg | Septic or other shock; organ perfusion is failing |
| Oxygen saturation | 95–100% on room air (target 88–92% in chronic carbon dioxide retention) | < 92%, or a new oxygen requirement | Pneumonia, atelectasis, pulmonary embolism, ARDS |
| Mentation | Alert and oriented to person, place, time and situation | New confusion, lethargy, agitation | In older adults, new delirium is often the first sign of infection, preceding fever |
| Urine output | At least 0.5 mL/kg/hour, roughly 30 mL/hour in an average adult | < 0.5 mL/kg/hour for 6 hours | Hypoperfusion, acute kidney injury from sepsis |
| White blood cell count | 4,500–11,000/mm³ | > 12,000, < 4,000, or more than 10% bands | Leukocytosis or leukopenia with a left shift indicates an active infectious process |
| Lactate | < 2 mmol/L | ≥ 2, and especially ≥ 4 mmol/L | Anaerobic metabolism from tissue hypoperfusion; drives sepsis resuscitation |
| Wound | Approximated edges, no drainage after 48–72 hours, a narrow margin of expected inflammation — pink on light skin, violaceous, deep brown or simply darker than surrounding skin on deeply pigmented skin | Purulent drainage, expanding erythema, induration, foul odor, dehiscence | Surgical site infection; crepitus or pain out of proportion suggests necrotizing infection — a surgical emergency |
Lifespan variation — the numbers actually change
Children are not small adults, and older adults are not simply slower adults. In a neonate under 28 days, a single rectal temperature of 38.0 °C (100.4 °F) or higher is a medical emergency requiring a full sepsis evaluation; do not give an antipyretic and reassess later. Neonates and young infants may present with hypothermia, poor feeding, lethargy, irritability, grunting or a bulging fontanelle rather than fever. In older adults, the febrile response is blunted: up to half of older adults with serious infection never mount a temperature above 38.0 °C. Long-term care criteria therefore define fever as a single oral temperature above 37.8 °C (100 °F), or repeated oral temperatures above 37.2 °C (99 °F), or an increase of more than 1.1 °C (2 °F) over that resident’s baseline. Suspect infection in the older adult who has become confused, stopped eating, started falling or lost function, even with a normal temperature.
| Age group | Heart rate awake (beats/min) | Respiratory rate (breaths/min) | Notes for infection assessment |
|---|---|---|---|
| Neonate (0–1 month) | 100–205 | 30–60 | Rectal 38.0 °C is an emergency; may be hypothermic instead |
| Infant (1 month–1 year) | 100–180 | 30–53 | Nasal flaring, grunting, retractions, poor feeding, fewer wet diapers |
| Toddler (1–2 years) | 98–140 | 22–37 | Febrile seizures peak between 6 months and 5 years |
| Preschool (3–5 years) | 80–120 | 20–28 | Hypotension is a very late sign; tachycardia is the warning |
| School age (6–11 years) | 75–118 | 18–25 | Compensates well, then decompensates suddenly |
| Adolescent (12–15 years) | 60–100 | 12–20 | Adult ranges; consider meningococcal disease with fever plus petechial rash |
| Pregnancy | Baseline rises 10–20 above pre-pregnancy | Rate near normal; tidal volume rises | Blood pressure falls in the second trimester, so “normal” pressure may mask shock; physiologic leukocytosis to about 15,000/mm³ is expected |
| Older adult (65+) | 60–100, may be blunted by beta blockers | 12–20; a rate above 20 is a strong red flag | Lower baseline temperature; delirium, falls and functional decline are often the presenting sign |
Escalating with SBAR
SBAR converts your worry into a clinical request the receiving provider can act on. Situation: who you are, who the patient is and what is wrong right now. Background: the relevant history in two or three sentences. Assessment: what you think is happening. Recommendation: what you want, stated out loud, with a timeframe. Nurses lose ground by stopping after Assessment. Ask for the thing.
Infection needs all six links of the chain intact; assess for it with inspection, palpation, percussion and auscultation — auscultating before percussion and palpation in the abdomen — and remember that the very young and the very old often show confusion, feeding changes or hypothermia instead of fever.
Section 3Hand Hygiene, Standard Precautions and PPE

The five moments, and the technique that makes them count
The World Health Organization’s Five Moments for Hand Hygiene are the framework you will be audited against: (1) before touching a patient, (2) before a clean or aseptic procedure, (3) after body-fluid exposure risk, (4) after touching a patient, and (5) after touching patient surroundings. Moments one and two protect the patient; moments three, four and five protect you and everyone else in the environment. Moment two is the one most often missed and the one with the shortest path to harm — the nurse who empties a drain and then adjusts an oxygen cannula without hand hygiene has just inoculated an airway. Beyond the five moments, perform hand hygiene before donning and after removing gloves (gloves leak and hands become contaminated during removal), before eating, after using the restroom, when moving from a contaminated body site to a clean body site on the same patient, and on entering and leaving any patient room.
Alcohol-based hand rub containing 60 to 95 percent alcohol is the preferred method for routine decontamination because it is faster, more effective against most organisms and less drying than soap. Apply the volume the manufacturer specifies — usually a full palmful — and rub over all surfaces for about 20 to 30 seconds until the hands are completely dry. Do not wave, blow or wipe them dry; the contact time is the mechanism. The surfaces people miss are the thumbs, the fingertips, the nail beds and the web spaces, so start there deliberately.
Soap and water is required, and alcohol is inadequate, in five situations: when hands are visibly soiled or contaminated with blood or body fluids; after caring for a patient with Clostridioides difficile; during outbreaks of norovirus; after known or suspected exposure to Bacillus anthracis; and before eating and after using the restroom. The reason is chemistry, not tradition: alcohol does not kill bacterial spores, and non-enveloped viruses such as norovirus are far less susceptible to it. Only the mechanical friction and rinsing of handwashing physically removes spores from the skin. To wash: wet hands with warm — not hot — water, apply soap, lather and rub all surfaces vigorously for at least 20 seconds, rinse with fingertips pointed downward so water runs from clean to dirty, dry thoroughly with a paper towel, and use that towel to turn off the faucet. The whole procedure takes 40 to 60 seconds.
Keep natural nail tips shorter than one-quarter inch (about 0.6 cm). Do not wear artificial nails, extenders, wraps or chipped polish when providing direct care to high-risk patients; artificial nails harbor gram-negative bacilli and yeast and have been traced to fatal neonatal intensive-care outbreaks. Rings increase the microbial load on the hands and interfere with glove fit. If your hands are cracked and dry, use the facility-approved lotion — damaged skin sheds far more organisms, and petroleum-based products degrade latex gloves.
Standard precautions apply to everyone, always
Standard precautions assume that the blood, all body fluids except sweat, non-intact skin and mucous membranes of every patient may be infectious, regardless of diagnosis or known status. You do not need a positive test to justify protecting yourself. The components are hand hygiene; personal protective equipment selected by anticipated exposure; respiratory hygiene and cough etiquette (tissues, a mask for the coughing patient, spatial separation of at least three feet in waiting areas); safe injection practices (one needle, one syringe, one time, and never re-enter a single-dose vial); safe handling of potentially contaminated equipment and linen; environmental cleaning; and sharps safety.
Sharps deserve their own discipline. Never recap a used needle; if recapping is unavoidable, use a one-handed scoop or a mechanical device. Activate the safety mechanism immediately, before your hand leaves the device. Dispose at the point of use into a puncture-resistant container and replace the container when it reaches the three-quarters full line. Never reach into a sharps container, never force an item in, and never place a used sharp on the bed, the tray or your pocket.
If you sustain a needlestick or a mucous membrane splash: wash the site immediately with soap and water, or flush eyes, nose or mouth with water or normal saline for 15 minutes. Do not squeeze the wound or apply bleach. Report to your supervisor and to employee health immediately — not at the end of the shift — so that source testing and post-exposure prophylaxis can begin. HIV post-exposure prophylaxis is most effective when started within hours and should be started no later than 72 hours after exposure. For perspective on why this urgency exists, the average risk of transmission from a percutaneous exposure to infected blood is roughly 0.3 percent for HIV, about 1.8 percent for hepatitis C, and up to 30 percent for hepatitis B in an unvaccinated worker — which is precisely why the hepatitis B vaccine series is required before clinical rotations.
PPE: the order is the safety feature
Personal protective equipment is chosen by what you expect to encounter, not by the label on the door. Gloves for contact with blood, body fluids, mucous membranes, non-intact skin or contaminated items. A fluid-resistant gown when clothing or arms may be soiled. A mask and eye protection — goggles or a full face shield, not personal eyeglasses — when splashing or spraying is possible, which includes suctioning, irrigating a wound, emptying drainage and caring for a patient with a productive cough. Gloves are single-use and single-patient: change them between tasks on the same patient when moving from a dirty site to a clean one, and never wash or re-use them.
| Step | DONNING — before entering | Why this order |
|---|---|---|
| 0 | Perform hand hygiene | Clean hands touch clean equipment |
| 1 | Gown — fully cover torso from neck to knees and arms to wrists, wrap around the back, tie at neck and waist | The largest garment goes on first so nothing must be lifted over it later |
| 2 | Mask or respirator — secure ties or elastic, fit the flexible band to the nose bridge, fit snug to face and below the chin; seal-check an N95 | Head straps must go on before eye protection so the straps are not disturbed |
| 3 | Goggles or face shield — place over face and eyes and adjust to fit | Sits over the mask, sealing the top edge |
| 4 | Gloves — extend to cover the wrist of the gown cuff | Last on, so gloves overlap the gown and nothing is exposed at the wrist |
| Step | DOFFING — at the doorway, inside the room | Why this order |
|---|---|---|
| 1 | Gloves — grasp the outside of one glove at the palm, peel it off into the gloved hand; slide the bare fingers under the second glove at the wrist and peel it off over the first. Discard. Perform hand hygiene. | Gloves are the most contaminated item; remove them first, glove-to-glove then skin-to-skin |
| 2 | Goggles or face shield — handle by the headband or earpieces only, lift away from the face, discard or place in the receptacle for reprocessing | The front is contaminated; the band behind the head is not |
| 3 | Gown — unfasten ties, pull away from neck and shoulders touching the inside only, turn it inside out, roll into a bundle and discard | Rolling contains the contaminated outer surface. Gown and gloves may be removed together in one motion if trained to do so |
| 4 | Mask or respirator — perform hand hygiene first if hands are contaminated, then grasp the bottom tie or elastic, then the top, lift away from the face without touching the front, and discard. For airborne precautions, remove the respirator only AFTER leaving the room and closing the door. | The front of the mask is contaminated; removing a respirator inside an airborne room exposes you to infectious aerosols |
| 5 | Perform hand hygiene immediately | Hands become contaminated during removal no matter how careful you are |
Two memory hooks will keep the sequences straight under pressure. Donning moves head-to-toe in size order and ends with gloves: gown, mask, goggles, gloves. Doffing removes the dirtiest item first and the mask last: gloves, goggles, gown, mask. Notice that the gown always comes off before the mask, that hand hygiene belongs between steps and at the end, and that the respirator is the only item ever removed outside the room. Some facilities teach a combined gown-and-glove removal in one motion, rolling the gown forward off the shoulders while the gloves are still on and peeling all of it inside out together; that variation is acceptable when you have been trained in it, and the order of everything else is unchanged.
Hand hygiene at the five moments — with soap and water for C. difficile, norovirus, anthrax and visibly soiled hands — plus standard precautions on every patient and PPE donned gown-mask-goggles-gloves and doffed gloves-goggles-gown-mask, prevents more infection than any other nursing action.
Section 4Transmission-Based Precautions
Three tiers, layered on top of standard precautions
Transmission-based precautions are added to — never substituted for — standard precautions when a patient is known or suspected to be infected or colonized with an organism that requires extra barriers. Start them on suspicion, before the laboratory confirms anything; waiting for a positive result is how measles gets into a waiting room. Some conditions need more than one tier: chickenpox and disseminated herpes zoster require airborne and contact precautions, and many respiratory viruses require droplet and contact.
| CONTACT | DROPLET | AIRBORNE | |
|---|---|---|---|
| How it spreads | Direct skin-to-skin, or indirect through contaminated hands, equipment and surfaces | Large respiratory particles that travel roughly 3 to 6 feet and fall; they do not remain suspended | Small particle nuclei 5 micrometers or less that remain suspended and travel on air currents |
| Representative diseases | MRSA, VRE, ESBL and CRE organisms, Candida auris, C. difficile, norovirus, RSV, rotavirus, scabies, lice, impetigo, draining abscess, hepatitis A in an incontinent patient | Influenza, pertussis, Neisseria meningitidis, Haemophilus influenzae type b, group A streptococcal pharyngitis (first 24 hours of therapy), mumps, rubella, diphtheria (pharyngeal), Mycoplasma pneumonia, adenovirus | Pulmonary or laryngeal tuberculosis, measles (rubeola), varicella (chickenpox), disseminated herpes zoster, smallpox; SARS-CoV-2 per current facility guidance |
| Room | Private room preferred; may cohort patients with the same organism | Private room preferred; if cohorting, keep beds at least 3 feet apart with the privacy curtain drawn. Door may remain open | Airborne infection isolation room: negative pressure, 6 air changes per hour in existing construction and 12 or more in new construction, exhausted outdoors or HEPA-filtered, door kept closed, pressure monitored daily |
| PPE on entry | Gown and gloves before entering, removed before exiting | Surgical mask on entry; add gown, gloves and eye protection per standard precautions and anticipated splash | Fit-tested N95 respirator or higher (PAPR), donned before entry and removed after exiting with the door closed |
| Patient transport | Limit to essential; cover infected areas with a clean dressing, use clean linen, notify the receiving department, staff wear clean PPE at the destination | Limit to essential; patient wears a surgical mask and follows respiratory etiquette; transporter does not need a mask if the patient is masked | Limit to essential; patient wears a surgical mask, never an N95, and skin lesions are covered. Schedule so the patient does not wait in common areas |
| Equipment | Dedicate stethoscope, blood pressure cuff and thermometer to the room; disinfect anything shared | Dedicate or disinfect per policy | Dedicate or disinfect per policy |
| Special notes | For C. difficile: soap and water hand hygiene, gown and gloves, and an EPA-registered sporicidal agent such as 1:10 sodium hypochlorite for the room | Nurse may need to be within 3 feet, so mask on entry regardless of intended distance | Assign immune staff to measles and varicella patients; unvaccinated staff should not enter. Measles particles remain infectious in the air for up to 2 hours after the patient leaves |
Room turnover, air clearance and the details that get missed
After an airborne-precautions patient leaves the room, the room must remain vacant until enough air exchanges have removed the suspended particles. At 12 air changes per hour, 99 percent removal takes about 23 minutes and 99.9 percent takes about 35 minutes; at 6 air changes per hour those figures are about 46 and 69 minutes. Environmental services should not enter before that interval elapses, and neither should you. Post the time the room was vacated so everyone is working from the same clock.
The opposite arrangement, a protective environment, is used for allogeneic hematopoietic stem cell transplant recipients: positive pressure relative to the corridor, 12 or more air changes per hour, HEPA filtration of incoming air, sealed room, and no dried or fresh flowers or potted plants because of Aspergillus. The confusion students carry into practice is the direction of airflow. Negative pressure keeps the organism in the room and protects everyone else. Positive pressure keeps organisms out of the room and protects the patient. A patient who is both immunocompromised and has tuberculosis requires an anteroom, and that is a facility engineering decision, not a bedside one.
A respirator only works if it seals. Fit testing is required annually and whenever facial features change, and a user seal check is required every single time you put one on: cover the respirator with both hands, inhale sharply and feel it collapse slightly toward the face, then exhale and feel for leakage around the edges and at the nose. Facial hair that crosses the seal makes an N95 ineffective, and a surgical mask is not a substitute for a respirator at any time. A patient in an airborne room wears a surgical mask during transport, never an N95, because a respirator has never been fit-tested to that patient’s face, it adds work of breathing to someone who is already ill, and if it carries an exhalation valve it vents unfiltered air and provides no source control at all. Keep the two purposes separate in your head: the patient’s surgical mask contains what they exhale, and your fit-tested respirator filters what you inhale.
Nursing care does not stop at the door. Patients in isolation receive fewer provider visits, report more depression and anxiety, and experience more non-infectious adverse events than comparable patients who are not isolated. Counter that deliberately. Explain to the patient and family, in plain language, what organism is involved, how it travels, why the gown and mask are worn, and what has to happen before precautions can end. Post visiting instructions and teach visitors the same PPE sequence you use. Enter the room for reasons other than tasks, cluster care so that you reduce the number of entries without reducing the amount of contact, and sit down when you are in there. Never let the sign on the door become a reason to stand in the hallway and talk loudly through the doorway.
Charting precautions and educating the patient
| Vague entry | Precise entry |
|---|---|
| “Isolation precautions in place. Family educated.” | “1400 — Contact plus droplet precautions initiated per order for suspected influenza A. Signage posted at door; gown, gloves, surgical mask and eye protection stocked in anteroom caddy. Stethoscope, cuff and thermometer dedicated to room 812. Patient and spouse taught rationale, hand hygiene technique with return demonstration by spouse, and the requirement for a mask during transport off the unit; both verbalized understanding and spouse correctly performed hand rub for 22 seconds. Patient placed in private room, door may remain open.” |
| “Diarrhea x several. Isolation started.” | “0930 — Five loose, watery, foul-smelling brown stools since 2300, Bristol type 7, approximately 900 mL total. Abdomen soft, mildly distended, hyperactive bowel sounds in all four quadrants on auscultation before palpation, diffuse tenderness without rebound or guarding. T 38.4 C oral, HR 104, BP 106/64. Contact precautions initiated for suspected C. difficile; stool specimen sent; soap-and-water hand hygiene posted at sink; sporicidal bleach wipes stocked. Provider notified.” |
Contact precautions require gown and gloves, droplet precautions require a surgical mask within the room, and airborne precautions require a fit-tested N95 plus a negative-pressure room with the door closed — and all three are layered on top of standard precautions and begun on suspicion, not on confirmation.
Section 5Asepsis, the Sterile Field and Device-Associated Infection
Medical asepsis versus surgical asepsis
Medical asepsis, or clean technique, reduces the number and transfer of pathogens. It includes hand hygiene, gloves, cleaning surfaces, separating clean from dirty, and not shaking linen. Surgical asepsis, or sterile technique, eliminates all microorganisms and spores from an object or area. It is required for entering a normally sterile body cavity or the bloodstream: inserting a urinary catheter, inserting or dressing a central line, performing a sterile dressing change on a fresh surgical wound, tracheostomy care in acute care, and any procedure entering the peritoneum or spinal canal. When you are unsure which applies, ask whether you are crossing into a sterile space. If yes, sterile technique.
Terminology also matters when you clean equipment. Cleaning physically removes soil and organic material and must precede everything else — disinfectants do not work through blood and feces. Disinfection destroys most pathogens on inanimate objects; high-level disinfection is used for semi-critical items that touch mucous membranes, such as endoscopes. Sterilization destroys all microorganisms including spores and is required for critical items that enter sterile tissue or the vascular system, such as surgical instruments and implants. Contact time on the label of a disinfectant wipe is not a suggestion; if the surface dries before the stated wet time, wipe again.
The rules of a sterile field
| Rule | How you apply it |
|---|---|
| Only sterile touches sterile | Any contact with a non-sterile item contaminates the field. If you are unsure whether something is sterile, it is not. |
| The outer 1 inch (2.5 cm) is not sterile | Place items toward the center. Anything that lands on the border is contaminated. |
| Keep the field in view and above waist level | Never turn your back on the field. Anything below waist or table level is contaminated, including your own hands when they drop. |
| Do not reach across the field | Add items from the side, holding the package 6 inches above and dropping the contents onto the center. Skin scales and lint fall. |
| Moisture contaminates — strikethrough | A wet drape wicks organisms from the surface underneath. Replace a soaked field. |
| Open the drape correctly | Open the flap farthest from you first, then the two sides, then the flap nearest you last, so you never reach over the sterile surface. |
| Pour without splashing | Hold the bottle with the label against your palm so a drip cannot run down and obscure it, discard the first small amount over a sink to cleanse the lip, then pour from 4 to 6 inches above the receptacle without reaching over the field. Once opened, the bottle’s rim is contaminated. |
| Control air movement and talking | Minimize movement, do not cough, sneeze or reach over the field, and keep doors closed. |
| Never leave the field unattended | An unwitnessed field is a contaminated field. Set up immediately before use. |
| Inspect the package first | Check the expiration date, the sterilization indicator, and the integrity of the seal. Torn, wet, punctured or previously opened means discard. |
To apply sterile gloves by the open method, peel the wrapper open on a clean dry surface above waist level without touching the inner surface, pick up the first glove by the folded cuff with your non-dominant hand touching only the inside, and pull it onto the dominant hand. Then slide the gloved fingers under the cuff of the second glove — touching only its outer surface — and pull it on. Adjust with both gloved hands, and keep your hands above your waist and in front of you from that moment until the procedure ends. If a glove tears, or you touch anything unsterile, stop, remove and start with a new pair. Nobody has ever been disciplined for re-gloving; patients have died from a nurse who kept going.
Device-associated infections and the bundles that prevent them
Most healthcare-associated infections in acute care attach to a device or an incision. Prevention is bundled, meaning that the elements are done together, every time, and audited; performing four of five elements does not deliver four-fifths of the benefit.
| Infection | Prevention bundle — the elements that matter | Nursing red flags |
|---|---|---|
| CLABSI central line-associated bloodstream infection | Hand hygiene; maximal sterile barrier precautions at insertion (cap, mask, sterile gown, sterile gloves, full-body drape); chlorhexidine-alcohol skin prep greater than 0.5%, scrubbed 30 seconds and allowed to dry completely; optimal site selection with subclavian preferred and femoral avoided in adults; daily review of line necessity with prompt removal; scrub the hub with alcohol for 10 to 15 seconds and let it dry before every access; transparent dressing changed every 7 days or gauze every 2 days, and immediately if damp, loose or soiled | Erythema, tenderness or drainage at the site; rigors or fever spike during or shortly after a flush; unexplained new bacteremia |
| CAUTI catheter-associated urinary tract infection | Insert only for accepted indications (acute retention or obstruction, accurate output in the critically ill, perioperative for selected surgeries, healing of open sacral or perineal wounds in incontinent patients, prolonged immobilization, comfort at end of life) — never for incontinence or staff convenience; aseptic insertion with sterile equipment; maintain a closed drainage system; keep the bag below the level of the bladder and off the floor at all times, including during transport; secure the catheter to prevent traction; keep tubing free of dependent loops; daily meatal care with soap and water only; no routine irrigation or catheter changes; daily review with removal at the earliest possible moment | New suprapubic or flank pain, fever, new delirium in an older adult, cloudy malodorous urine with symptoms. Do not culture asymptomatic patients |
| VAP / VAE ventilator-associated pneumonia or event | Head of bed elevated 30 to 45 degrees unless contraindicated; daily sedation interruption paired with a spontaneous breathing trial and daily assessment of readiness to extubate; oral care with toothbrushing at least twice daily; subglottic secretion drainage tubes for anticipated ventilation beyond 48 to 72 hours; maintain cuff pressure per policy; early mobility; venous thromboembolism prophylaxis per unit protocol | New or increased purulent secretions, new infiltrate, rising oxygen requirement or PEEP, fever |
| SSI surgical site infection | Antimicrobial prophylaxis within 60 minutes before incision (120 minutes for vancomycin or a fluoroquinolone) and discontinued appropriately; hair removed with clippers, never a razor, and only when necessary; preoperative chlorhexidine bathing; perioperative normothermia and glucose control below 180–200 mg/dL; sterile technique for the first dressing change, which the surgeon usually performs at 24 to 48 hours; hand hygiene before and after wound care | Purulent incisional drainage, expanding erythema, dehiscence, fever after postoperative day 3, pain that is increasing rather than decreasing |
Delegation and scope: who may do what
Delegation is the transfer of responsibility for performing a task to someone else while the registered nurse retains accountability for the outcome. Use the five rights of delegation: right task, right circumstance, right person, right direction and communication, and right supervision and evaluation. The permanent boundary is this — assessment, teaching, evaluation, nursing judgment and the care of an unstable patient never leave the RN. A task that seems routine on a stable patient may not be delegable on an unstable one, and the same task may be delegable at 0800 and not at 1600 because the patient changed.
| May be delegated to UAP (with direction and supervision) | Stays with the licensed nurse |
|---|---|
| Performing hand hygiene and wearing PPE correctly; stocking the isolation cart | Deciding which tier of precautions a patient requires, and when precautions may be discontinued |
| Measuring vital signs and intake and output on a stable patient and reporting the numbers | Interpreting those vital signs and deciding what they mean; taking vitals on an unstable or newly deteriorating patient |
| Bathing, oral care, perineal and meatal hygiene, repositioning, ambulating a stable patient | Skin, wound and neurologic assessment; the initial and any ongoing assessment |
| Emptying a urinary drainage bag, recording output, keeping the bag below the bladder | Inserting a urinary catheter (sterile procedure, per state and facility policy) and judging whether it can be removed |
| Applying nonskid socks, keeping the bed low and locked, keeping the call light in reach, answering call lights, sitting with a patient | Fall risk screening and scoring, and selecting the interventions; initiating restraints and performing the restraint assessments |
| Reinforcing previously taught information (“remember to use the hand rub”) | All patient and family teaching, including teaching about precautions, and evaluating whether the teaching worked |
| Routine environmental tidying and transporting specimens per policy | Any sterile dressing change, central line care, and all sterile technique |
When you delegate, be specific and close the loop: “Please take Mr. Ruiz’s vital signs now, before his 1000 medications, and tell me the number right away if the systolic is under 100 or the heart rate is over 110.” That single sentence contains the task, the timeframe, the parameters and the reporting requirement. “Go get vitals when you can” contains none of them. And a final piece of scope that students underestimate: you are permitted — obligated — to stop any team member, at any level, who is about to break sterile technique or skip hand hygiene. Say it plainly, say it kindly, say it out loud.
Surgical asepsis has non-negotiable rules — only sterile touches sterile, a one-inch contaminated border, nothing below the waist or out of sight, and doubt equals contamination — and the device bundles that prevent CLABSI, CAUTI, VAP and SSI work only when every element is performed every time by a nurse who never delegates assessment, teaching or evaluation.
The chapter in one breath
Safe care is built from repeatable behaviors rather than good intentions. Verify identity with two identifiers — never the room number — and stop the line at a time-out that does not match. Screen every patient for falls with a validated tool, apply universal precautions plus targeted interventions for high scorers, and if a fall occurs, assess in place and chart only what you saw, measured and quoted. Restraints are a last resort with hard legal limits: never PRN, four hours for a violent-behavior order in an adult, a face-to-face evaluation within one hour, release and skin assessment every two hours, quick-release knot to the bed frame. Infection needs six intact links; nurses break the chain most powerfully at transmission and portal of entry. Hand hygiene at all five moments, with soap and water for C. difficile, norovirus, anthrax and visibly soiled hands. Standard precautions on everyone. PPE on as gown, mask, goggles, gloves; off as gloves, goggles, gown, mask, with the respirator removed only after leaving the room. Contact means gown and gloves; droplet means a surgical mask; airborne means a fit-tested N95 and a closed negative-pressure room. Sterile means sterile, and doubt means contaminated. Escalate red flags immediately with SBAR, and ask for what you want.
Words worth knowing
| Term | What it means |
|---|---|
| Medical asepsis | Clean technique — practices that reduce the number and spread of pathogens, such as hand hygiene, gloves and surface disinfection. |
| Surgical asepsis | Sterile technique — practices that eliminate all microorganisms and spores, required whenever a sterile body cavity or the bloodstream is entered. |
| Chain of infection | The six sequential links — agent, reservoir, portal of exit, mode of transmission, portal of entry, susceptible host — all of which must be intact for infection to occur. |
| Colonization | The presence and multiplication of an organism without tissue damage or host response; not treated with antibiotics but may still require precautions. |
| Healthcare-associated infection (HAI) | An infection that was not present or incubating at the time of admission, acquired during the delivery of care. |
| Standard precautions | The baseline tier applied to every patient, treating blood, all body fluids except sweat, non-intact skin and mucous membranes as potentially infectious. |
| Transmission-based precautions | Contact, droplet and airborne measures added on top of standard precautions for known or suspected transmissible organisms. |
| Airborne infection isolation room (AIIR) | A negative-pressure room with 6 to 12 or more air changes per hour, air exhausted outdoors or HEPA-filtered, and the door kept closed. |
| Protective environment | A positive-pressure, HEPA-filtered room used for allogeneic stem cell transplant recipients; no fresh or dried flowers or plants. |
| Alcohol-based hand rub | A 60 to 95 percent alcohol preparation rubbed over all hand surfaces for 20 to 30 seconds until dry; ineffective against spores. |
| Five Moments for Hand Hygiene | Before patient contact, before a clean or aseptic procedure, after body-fluid exposure risk, after patient contact, after contact with patient surroundings. |
| Personal protective equipment (PPE) | Gown, mask or respirator, eye protection and gloves; donned gown-mask-goggles-gloves and doffed gloves-goggles-gown-mask. |
| N95 respirator | A filtering facepiece requiring annual fit testing and a user seal check with every use; required for airborne precautions and never worn by the patient. |
| Sterile field | A microorganism-free work area whose outer one inch is contaminated, which must remain in sight and above waist level and never be left unattended. |
| Strikethrough | Contamination of a sterile field by moisture wicking organisms upward from the non-sterile surface beneath it. |
| Restraint | Any device, method or drug used to restrict movement or behavior that is not standard treatment; requires a non-PRN order, monitoring and time-limited renewal. |
| Morse Fall Scale | A validated fall-risk instrument on which a score of 45 or higher indicates high risk. |
| qSOFA | A rapid bedside sepsis screen: respiratory rate 22/min or higher, altered mentation, systolic blood pressure 100 mm Hg or lower; two of three is a red flag. |
| Neutropenic fever | A single oral temperature of 38.3 °C (101 °F) or a sustained 38.0 °C with an absolute neutrophil count below 500/mm³; antibiotics are due within one hour. |
| SBAR | Situation, Background, Assessment, Recommendation — the structured format for escalating a concern and requesting specific action. |
Check yourself
Vital Signs
Vital signs are the only part of the assessment that produces a number every patient, every shift, in every setting — and because they are numbers, they are the first thing anyone deteriorating shows you. Hours before a patient looks septic, the respiratory rate has already climbed. Hours before a patient bleeds out visibly, the pulse pressure has already narrowed and the pulse has quickened. This chapter teaches you to produce numbers that can be trusted: the correct route, the correct cuff, the correct count, the correct position, the correct amount of time. It then teaches you to read them — against the exact adult ranges, against the lifespan variations that make a heart rate of 140 normal in an infant and an emergency in an adult, and against the patient’s own baseline, which almost always matters more than the textbook. It ends with the values that mean stop, call now, and the words you will use to call.
By the end of this chapter you can
- State adult ranges for temperature, pulse, respiration, blood pressure and SpO2 to the exact number, and adjust each for infants, children, pregnancy and older adults.
- Sequence the four assessment techniques — inspection, palpation, percussion, auscultation — and state the abdominal exception and why it exists.
- Select and perform the correct temperature route, and name the contraindications to oral and rectal measurement.
- Assess a pulse for rate, rhythm and amplitude, grade it on the 0 to 4+ scale, and measure an apical–radial pulse deficit with a second nurse.
- Recognize Kussmaul, Cheyne-Stokes and Biot respiratory patterns and state what each suggests.
- List the limitations of pulse oximetry — poor perfusion, nail polish, carbon monoxide, motion, anemia and skin pigmentation — and explain occult hypoxemia.
- Size a blood pressure cuff (bladder width about 40 percent of arm circumference) and explain why a cuff that is too small reads falsely high.
- Perform orthostatic vital signs correctly and state the numeric definition of a positive result.
- Rewrite a vague vital-sign entry as a precise, defensible one, and escalate abnormal values using SBAR.
Section 1Vital Signs as a System
What the numbers are actually telling you
The five traditional vital signs — temperature, pulse, respiration, blood pressure and oxygen saturation — are not five unrelated chores. They are five windows onto two questions: is this patient perfusing tissue with oxygenated blood, and is the body’s regulatory machinery still holding the line? Temperature reports the hypothalamic set point and the presence of inflammation. Pulse reports cardiac rate and, in its quality, stroke volume. Respiration reports both gas exchange and, quietly, metabolic acidosis. Blood pressure reports the driving force behind perfusion. Oxygen saturation reports how loaded the hemoglobin is. When one moves, ask what the others are doing, because compensation is a pattern, not a single value.
That pattern is why trend beats snapshot. A blood pressure of 104/62 is unremarkable in a small young adult and alarming in a patient whose baseline is 160/90, because the second patient has lost more than fifty points of driving pressure and may be perfusing a kidney at the edge of failure. Before you decide a number is normal, find the last three sets on the flowsheet. Deterioration almost never announces itself with one wildly abnormal value; it announces itself with three sets that each looked acceptable and that, lined up, point one direction.
Of the five, respiratory rate is the one students underweight and clinicians most often falsify. It is the earliest and most sensitive predictor of deterioration in adults, it rises before blood pressure falls, and it is the value most likely to be charted as 18 because 18 looks reasonable. Counting a real respiratory rate takes thirty to sixty seconds and can be the difference between recognizing early sepsis and finding it in shock four hours later.
The four techniques, and the one exception you must never forget
Every physical assessment in this book is built from four techniques performed in a fixed order: inspection, then palpation, then percussion, then auscultation. Inspection is deliberate looking — adequate light, exposed skin, comparison side to side. Palpation uses the fingerpads for texture, pulsation and tenderness, the ulnar surface of the hand for vibration, and the dorsum of the hand for temperature, because the back of the hand is the most temperature-sensitive surface you have. Percussion strikes the distal interphalangeal joint of the pleximeter finger with the tip of the plexor finger, using wrist motion only, to judge whether the tissue beneath is air-filled, fluid-filled or solid. Auscultation uses the diaphragm for high-pitched sounds (breath sounds, bowel sounds, S1 and S2) and the bell, held lightly, for low-pitched sounds (S3, S4, bruits, murmurs of mitral stenosis).
There is one exception, and it is asked on every examination and matters at every bedside. For the abdomen, the order is inspect, auscultate, percuss, palpate. Auscultation moves ahead of the hands because pressing on the abdomen mechanically stimulates or suppresses peristalsis and changes the bowel sounds you are about to listen for. Palpate first and you have contaminated your own data. Everywhere else on the body, palpation precedes auscultation; on the abdomen it follows it.
Vital signs sit inside these techniques rather than beside them. You inspect while you count respirations, you palpate to find a radial pulse and to estimate a systolic pressure before you inflate a cuff, and you auscultate for Korotkoff sounds and for an apical rate. Treating vital signs as data entry rather than as physical assessment is exactly how bad numbers get charted.
How often, and who may take them
Frequency is set by provider order, facility policy and patient condition, and the last of those overrides the first two upward but never downward. Common patterns: a full set on admission and at the start of every shift; every four hours on a general medical-surgical unit; postoperatively every fifteen minutes for four sets, every thirty minutes for two, every hour for four, then every four hours; every fifteen minutes during the first hour after a blood transfusion begins, with the nurse remaining with the patient for the first fifteen minutes; before and after any procedure, any transfer, any fall, any change in condition, and any patient complaint that could be cardiopulmonary. Certain medications carry their own vital-sign gate: an apical rate before digoxin (hold and notify if under 60 in an adult), a blood pressure before an antihypertensive, a respiratory rate and sedation level before an opioid dose.
Measuring routine vital signs on a stable, predictable patient may be delegated to unlicensed assistive personnel. Interpreting them may not. When you delegate, you must give the assistant the exact numbers to report back to you — not “let me know if anything looks off,” but “tell me immediately if the heart rate is above 110, the systolic is below 100, the respiratory rate is above 24, the temperature is above 38 °C, or the SpO2 is below 92 percent.” The registered nurse retains the baseline admission set, any set on an unstable patient, any set taken because the patient changed, and every act of judgment about what the numbers mean.
| Task | May go to UAP | Stays with the RN |
|---|---|---|
| Routine four-hourly vital signs, stable patient | Yes, with reporting parameters given | Interpretation and response |
| Admission baseline set | No | Yes — it anchors every later comparison |
| Vital signs on a patient who just became short of breath | No | Yes — patient is unstable |
| Vital signs before and during a blood transfusion | No | Yes |
| Apical pulse before digoxin | No — requires assessment and a hold decision | Yes |
| Orthostatic vital signs | No — interpretation and fall risk are nursing judgment | Yes |
| Teaching a patient to take a home blood pressure | No — teaching is never delegated | Yes |
The adult numbers, and how they move across the lifespan
Memorize the adult set as exact numbers, not as impressions. Then memorize the direction pediatric values move: as a child grows, heart rate and respiratory rate fall and blood pressure rises. A heart rate of 140 is expected in a two-month-old and is a rapid-response call in a forty-year-old. Pediatric numbers are given here in the ranges used by Pediatric Advanced Life Support; individual textbooks vary by a few beats, so follow your facility’s reference and, above all, the child’s own baseline.
| Adult vital sign | Expected value | Terms for abnormal |
|---|---|---|
| Temperature (oral) | 36.5–37.5 °C (97.7–99.5 °F); average 37.0 °C (98.6 °F) | Fever/pyrexia 38.0 °C (100.4 °F) or higher; hypothermia below 35.0 °C (95.0 °F) |
| Pulse | 60–100 beats/min, regular | Bradycardia under 60; tachycardia over 100 |
| Respiration | 12–20 breaths/min, quiet and unlabored | Bradypnea under 12; tachypnea over 20; apnea |
| Blood pressure | Under 120/80 mm Hg | Hypotension generally under 90/60; hypertension 130/80 or higher |
| SpO2 | 95–100 percent on room air | Hypoxemia under 90 percent (target 88–92 percent in chronic CO2 retention) |
| Pulse pressure | 30–40 mm Hg (systolic minus diastolic) | Narrowed under 25; widened over 60 |
| Mean arterial pressure | 70–100 mm Hg | Organ perfusion threatened below 65 |
| Age | Heart rate (beats/min) | Respirations (breaths/min) | Systolic BP (mm Hg) |
|---|---|---|---|
| Neonate, under 1 month | 100–205 awake, 90–160 asleep | 30–60 | 60–90 (hypotension below 60) |
| Infant, 1–12 months | 100–180 awake, 90–160 asleep | 30–53 | 72–104 (hypotension below 70) |
| Toddler, 1–2 years | 98–140 | 22–37 | 86–106 |
| Preschool, 3–5 years | 80–120 | 20–28 | 89–112 |
| School age, 6–11 years | 75–118 | 18–25 | 97–120 |
| Adolescent, 12–15 years | 60–100 | 12–20 | 110–131 |
| Adult | 60–100 | 12–20 | Under 120 |
For children over one year, the fifth-percentile (lowest acceptable) systolic pressure is 70 plus twice the age in years; below that value a child aged one to ten is hypotensive, and hypotension in a child is a late, ominous sign because children compensate with tachycardia until they cannot. In pregnancy, heart rate rises 10 to 20 beats per minute by the third trimester, blood pressure falls during the second trimester and returns to baseline near term, and tidal volume rises about 30 to 40 percent while the respiratory rate stays essentially unchanged. In older adults, arterial stiffening produces isolated systolic hypertension and a widened pulse pressure, the febrile response is blunted so that infection may present with confusion or a fall rather than a temperature, and baseline temperature runs lower — a rise of 1.1 °C (2 °F) above that patient’s own baseline is clinically significant even if the absolute number never reaches 38 °C.
Pain is measured with every vital-sign set and is often called the fifth vital sign, though strictly it is a self-reported symptom rather than a measured physiologic value. Use a 0-to-10 numeric rating scale for adults who can self-report, Wong-Baker FACES from about age three, FLACC for children two months to seven years, CRIES for neonates, PAINAD for advanced dementia and CPOT for intubated adults. Self-report is the gold standard and outranks your impression of how comfortable the patient looks. Pain assessment is developed fully in Chapter 7.
Vital signs are physical assessment expressed as numbers, and the trend across sets — not any single value — is what tells you a patient is deteriorating.
Section 2Temperature
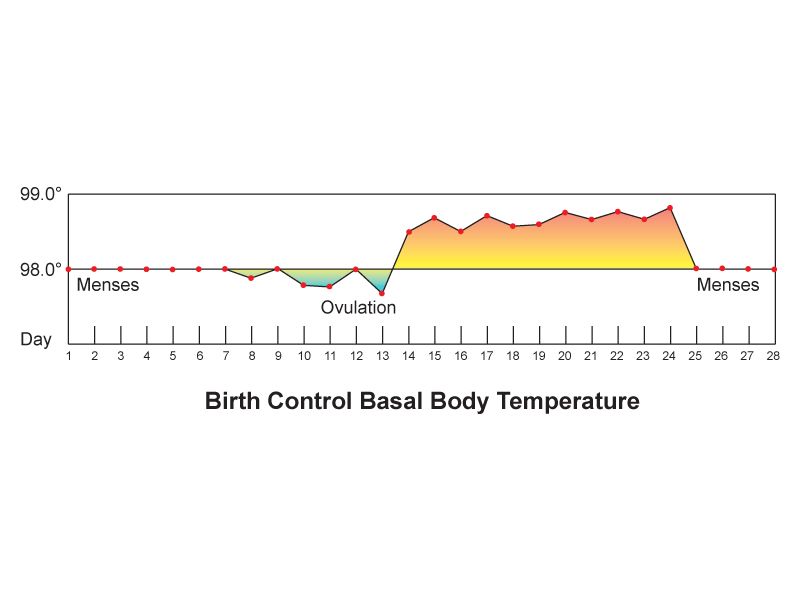
Thermoregulation and what counts as a fever
The hypothalamus holds core temperature near 37.0 °C (98.6 °F) by balancing heat production — basal metabolism, muscle activity, shivering, thyroid hormone and catecholamines — against heat loss through radiation, conduction, convection and evaporation. Fever is not a failure of that system. In fever, pyrogens raise the hypothalamic set point, and the body then works to reach the new, higher target: the patient vasoconstricts, feels cold, and shivers during the chill phase while the temperature climbs. At the plateau the patient is hot and vasodilated — on lighter skin this looks flushed, while on brown or black skin the change is easier to feel as warmth and to see in the conjunctivae and oral mucosa than to read as redness. When the set point resets downward, the patient diaphoreses and vasodilates in the defervescence phase. Recognizing these phases keeps you from piling blankets on a shivering patient whose temperature is already 39 °C.
Hyperthermia is different in mechanism and in danger. There the set point is normal but heat gain overwhelms heat loss — heat stroke, malignant hyperthermia, neuroleptic malignant syndrome, anticholinergic toxicity. Hyperthermia does not respond to antipyretics, because there is no raised set point to lower; it requires active cooling and removal of the cause. A temperature above 40 °C (104 °F) with altered mental status and hot dry skin is heat stroke until proven otherwise, and it is an emergency.
Normal temperature also varies predictably. It is lowest between 0400 and 0600 and highest between 1600 and 1800, swinging 0.5 to 1.0 °C across the day; it rises 0.3 to 0.6 °C after ovulation; it rises with exercise, heavy clothing and a hot environment. If you are comparing a morning temperature to an evening one, part of the difference is the clock. To convert, multiply degrees Celsius by 1.8 and add 32; to reverse, subtract 32 and divide by 1.8.
Choosing a route and performing it correctly
Routes are not interchangeable, and the conversions between them are approximations. Chart the route with the number, every time, and compare like with like across the shift.
| Route | Expected adult range | Technique | Avoid when |
|---|---|---|---|
| Oral | 36.5–37.5 °C (97.7–99.5 °F) | Probe in the posterior sublingual pocket, lips closed, mouth breathing avoided; wait 15–30 minutes after hot or cold intake, smoking or chewing gum | Confusion, seizure risk, inability to follow directions, oral surgery or trauma, children under about 4 years |
| Rectal | 0.5 °C (0.9 °F) higher than oral: 37.0–38.0 °C (98.6–100.4 °F) | Lubricated probe, side-lying, insert 3.5 cm (1.5 in) adult or 1.5–2.5 cm (0.5–1 in) infant, hold in place the entire time | Neutropenia, thrombocytopenia or anticoagulation, rectal or perineal surgery, diarrhea, imperforate anus, spinal cord injury with autonomic dysreflexia risk, cardiac patients (vagal stimulation) |
| Tympanic | Close to rectal; about 0.3–0.6 °C above oral | Pull pinna up and back in adults and children over 3, down and back under 3; aim at the tympanic membrane; use a clean cover | Otitis, ear drainage, impacted cerumen, ear surgery, hearing aid in place |
| Temporal artery | About 0.4 °C above oral | Slide across the forehead to the hairline, then behind the ear lobe if the forehead is diaphoretic | Diaphoresis, forehead scar or dressing, recent cold pack |
| Axillary | 0.5 °C (0.9 °F) lower than oral: 36.0–37.0 °C (96.8–98.6 °F) | Probe deep in a dry axilla, arm held firmly against the chest for the full dwell time | Any time accuracy matters — it is the least reliable route; use only when others are contraindicated |
For infants under three months, rectal temperature is the reference standard and the number that decision rules are built on. For most other patients an oral or temporal reading is enough, and the accuracy you gain from a rectal temperature rarely justifies the invasion. Core temperature from an esophageal, bladder or pulmonary artery probe is used in critical care and during therapeutic hypothermia; if such a probe is in place, it is the number the team will act on.
Fever across the lifespan, and what abnormal temperature means
| Finding | Suggests | Action |
|---|---|---|
| Rectal 38.0 °C (100.4 °F) or higher in an infant under 3 months | Possible serious bacterial infection; the infant cannot localize it | Emergency evaluation — notify the provider immediately, expect a full sepsis workup |
| Single oral temperature 38.3 °C (101 °F), or 38.0 °C sustained one hour, in a neutropenic patient | Neutropenic fever — may be the only sign of overwhelming infection | Medical emergency; cultures and antibiotics within one hour |
| New confusion, falls or hypothermia in an older adult | Infection with a blunted febrile response — sepsis may present without fever | Full vital-sign set, look for other sepsis criteria, notify provider |
| Temperature below 36.0 °C (96.8 °F) with tachycardia and tachypnea | Sepsis, environmental exposure, hypothyroidism, burns | Escalate — hypothermia counts toward sepsis criteria exactly as fever does |
| Above 41.0 °C (105.8 °F), hyperpyrexia | Heat stroke, malignant hyperthermia, CNS lesion | Active cooling now; antipyretics will not fix hyperthermia |
| Temperature spike within 30 minutes of starting a transfusion | Febrile or hemolytic transfusion reaction | Stop the transfusion, keep the line open with normal saline, notify provider and blood bank |
Two lifespan cautions deserve emphasis. Infants have a large surface-area-to-mass ratio, little insulating fat and no shivering thermogenesis at birth; they lose heat fast and become hypothermic rather than febrile when septic. Older adults may run a baseline temperature of 36.2 °C, so a “normal” 37.8 °C may already represent a 1.6-degree rise and a real infection. In both groups the absolute number lies more often than the change from baseline does.
Chart the route with the temperature, treat 38.0 °C (100.4 °F) as fever in adults, and remember that infants and older adults may be seriously infected with a normal or low temperature.
Section 3The Pulse
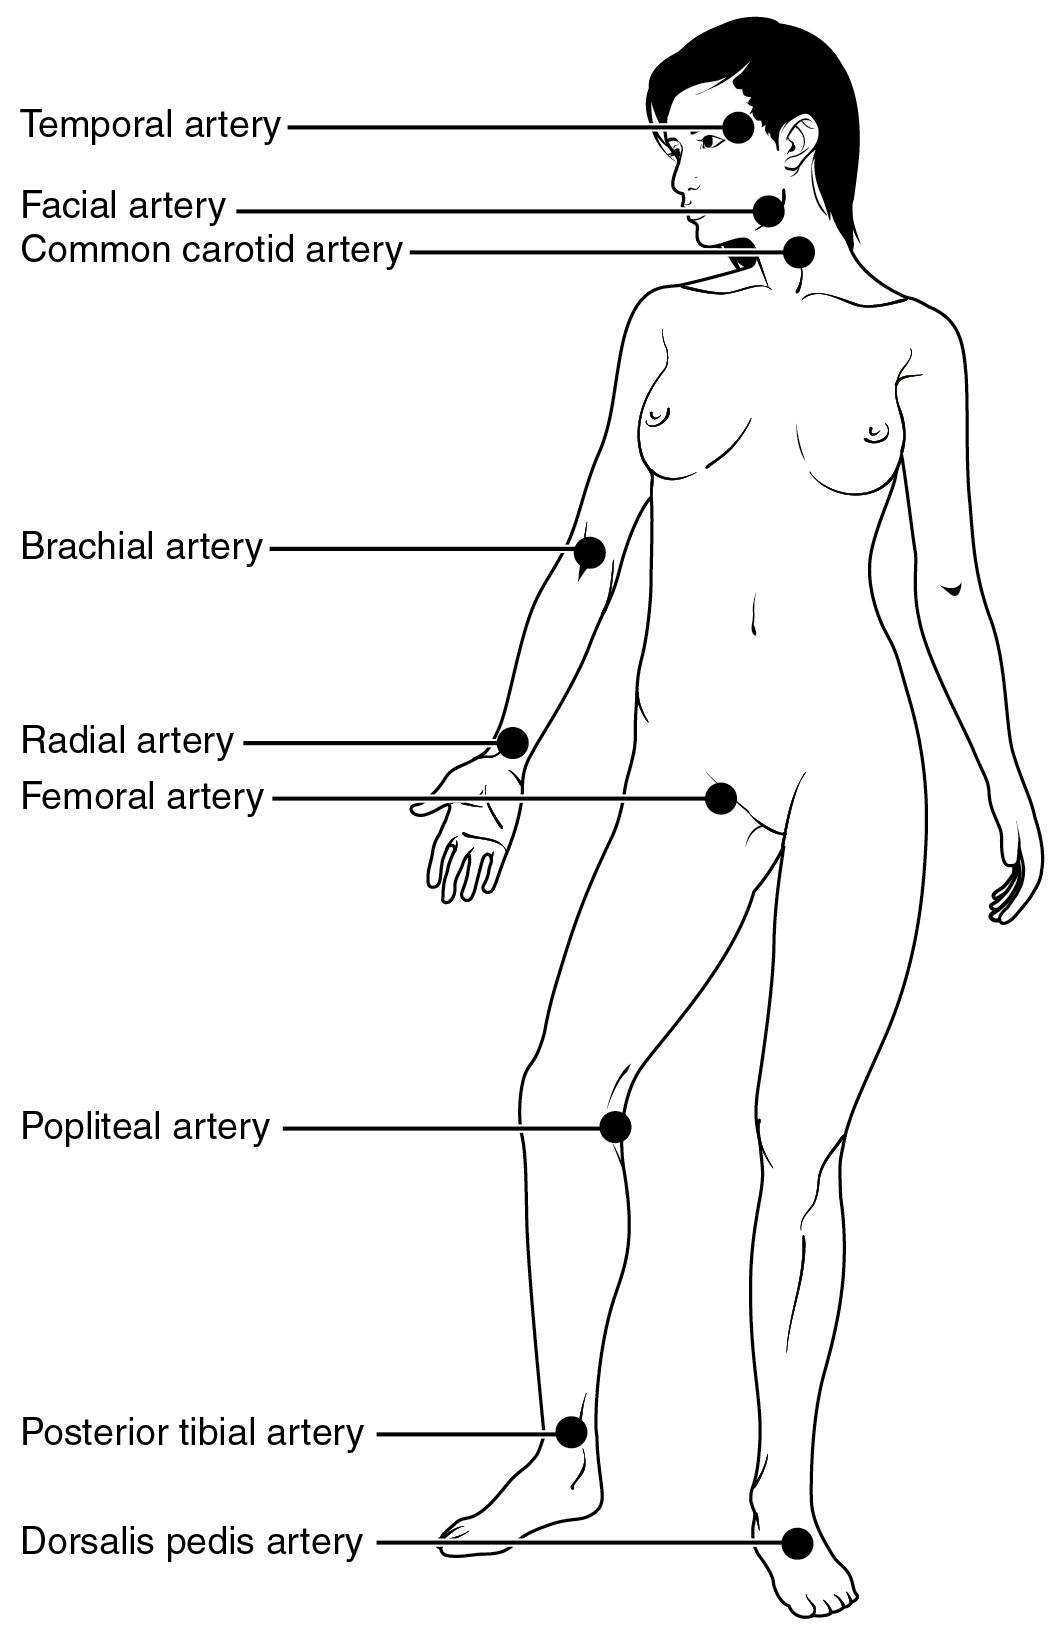
What you are feeling, and how to feel it
Each ventricular contraction ejects a stroke volume into an already-full aorta, and the pressure wave that travels down the arterial tree is what your fingers detect. That means the pulse carries information about rate, about the regularity of the electrical rhythm, and about the force of the contraction reaching the periphery. Palpate with the pads of your index and middle fingers, never the thumb, which has a pulse of its own that you will happily count as the patient’s.
Press gently. Heavy pressure occludes the vessel and erases the very finding you are grading. Count for 30 seconds and multiply by two if the rhythm is regular; count a full 60 seconds if the rhythm is irregular, if the rate is very fast or very slow, if the patient is an infant, or if you are taking an apical pulse. Doubling an irregular 30-second count is how a real rate of 96 becomes a charted 120.
| Site | Where | Used for |
|---|---|---|
| Temporal | Anterior to the ear, over the temporal bone | Children, when the radial is inaccessible |
| Carotid | Medial to the sternocleidomastoid, at the level of the cricoid | Shock and cardiac arrest — the last pulse to disappear. Palpate one side only, gently: bilateral or heavy pressure can trigger a vagal response and bradycardia |
| Brachial | Medial antecubital fossa, groove between biceps and triceps | Blood pressure auscultation; pulse check in infants |
| Radial | Thumb side of the flexor wrist surface | Routine adult pulse |
| Femoral | Below the inguinal ligament, midway between symphysis and anterior superior iliac spine | Shock; assessment after cardiac catheterization |
| Popliteal | Behind the knee, knee slightly flexed | Lower-extremity perfusion; thigh blood pressure |
| Posterior tibial | Behind and below the medial malleolus | Peripheral vascular assessment |
| Dorsalis pedis | Dorsum of the foot, lateral to the extensor hallucis longus tendon | Peripheral perfusion — congenitally absent in up to 10 percent of healthy people, so compare sides and mark the spot you found |
| Apical | Fifth intercostal space, left midclavicular line | Infants and children under 2, irregular rhythms, before digoxin, whenever the radial is unreliable |
Rate, rhythm and amplitude
Report all three. Rate is beats per minute against the expected 60 to 100 in adults, adjusted for age and for the patient’s own baseline — an endurance athlete at 48 and a patient on a beta-blocker at 56 are not necessarily abnormal, while 56 in a patient whose baseline is 88 is a change worth investigating. Rhythm is the spacing between beats: regular, regularly irregular (a repeating pattern, such as every third beat dropped), or irregularly irregular (no pattern at all, the classic finding of atrial fibrillation). Amplitude is the force of the wave, graded on a 0 to 4+ scale; some facilities use a 0 to 3+ scale, so know which one your chart uses before you document a number.
| Grade | What it feels like | Suggests |
|---|---|---|
| 0 | Absent — not palpable by hand; confirm with a Doppler before charting zero, and document whether the signal was present by Doppler only | Arterial occlusion, severe shock, compartment syndrome — a new absent pulse is an emergency |
| 1+ | Weak, thready, easily obliterated | Low stroke volume: hypovolemia, heart failure, peripheral arterial disease |
| 2+ | Normal, expected, not easily obliterated | Expected finding |
| 3+ | Full, increased | Hyperdynamic states: fever, anxiety, exercise, anemia, hyperthyroidism |
| 4+ | Bounding, cannot be obliterated | Aortic regurgitation, patent ductus arteriosus, severe hypertension, fluid overload |
Two special qualities are worth recognizing early. Pulsus paradoxus is an exaggerated fall in systolic pressure — more than 10 mm Hg — during inspiration; the peripheral pulse seems to fade with each breath in. It points toward cardiac tamponade, severe asthma or constrictive pericarditis and warrants immediate escalation. Pulsus alternans alternates strong and weak beats at a regular rhythm and suggests severe left ventricular dysfunction.
The apical pulse and the pulse deficit
The apical pulse is auscultated with the diaphragm at the point of maximal impulse — fifth intercostal space, left midclavicular line in an adult. Each “lub-dub” counts as one beat, and you count for a full minute. Take an apical rather than a radial pulse in any infant or child under two, in any patient with an irregular rhythm, before administering digoxin or another rate-controlling drug, and whenever the peripheral pulse is difficult to feel. In infants the point of maximal impulse sits higher and more lateral — third or fourth intercostal space, at or just lateral to the midclavicular line — because the heart lies more horizontally in the chest.
A pulse deficit is the difference between the apical rate and the radial rate. It exists because some ventricular contractions are too weak, or come too soon after the last one, to fill enough to generate a palpable peripheral wave. You hear them at the apex; the wrist never feels them. The classic causes are atrial fibrillation and frequent premature ventricular contractions, and the size of the deficit is a rough measure of how much of the heart’s work is being wasted.
Measure it properly. The reliable method uses two nurses and one watch: one auscultates the apex, one palpates the radial, both count simultaneously for a full 60 seconds beginning on an agreed signal. Subtract the radial from the apical; the apical is never lower. One nurse taking the two rates sequentially will produce a number, but not a trustworthy one, because the rhythm changes between counts. Document all three values, not just the difference: “Apical 118, irregularly irregular; radial 92; pulse deficit 26. Counted simultaneously for 1 minute with RN Alvarez.”
A pulse has a rate, a rhythm and an amplitude — count irregular rhythms apically for a full minute, and measure a pulse deficit with two nurses counting at the same time.
Section 4Respiration and Oxygen Saturation

Counting a breath without changing it
Breathing is the one vital sign under voluntary control, which means a patient who knows you are counting will breathe differently. Count without announcing it. The standard technique is to finish the radial pulse, keep your fingers on the wrist, and shift your eyes to the chest or abdomen — the patient believes you are still counting the pulse. One full cycle of rise and fall is one respiration. Count for 30 seconds and double if the pattern is regular; count a full 60 seconds if it is irregular, if the rate is abnormal, or if the patient is an infant.
Infants breathe diaphragmatically, so watch the abdomen rather than the chest, and expect an irregular pattern with brief pauses — periodic breathing is normal in newborns, but a pause longer than 20 seconds, or any pause accompanied by bradycardia or cyanosis — judged at the tongue, oral mucosa and conjunctivae rather than by skin color, which is unreliable on brown and black infants — is apnea and is not normal. In older adults, reduced chest wall compliance and lower vital capacity mean a slightly higher resting rate, but a rate above 24 is abnormal at any adult age.
Adult expected values: 12 to 20 breaths per minute, quiet, effortless, with symmetric chest expansion and an inspiration-to-expiration ratio of roughly 1 to 2. Anything that changes that ratio — prolonged expiration in obstructive disease, for example — is a finding even when the rate is normal.
Depth, effort and pattern
Rate alone is half the assessment. Look at depth (shallow, normal or deep), effort (accessory muscle use, nasal flaring, intercostal or subcostal retractions, tripod positioning, pursed-lip breathing, ability to speak in full sentences) and pattern. Retractions and nasal flaring in a child mean respiratory distress regardless of what the number says, and a child who becomes quiet and sleepy after a period of retractions may be tiring toward respiratory failure, not improving.
| Pattern | Description | Suggests |
|---|---|---|
| Eupnea | 12–20/min, regular, unlabored | Expected finding |
| Tachypnea | Over 20/min, often shallow | Fever, pain, anxiety, hypoxemia, pulmonary embolism, early sepsis |
| Bradypnea | Under 12/min, regular | Opioids and sedatives, raised intracranial pressure, severe metabolic alkalosis |
| Kussmaul | Deep, rapid, labored and regular | Metabolic acidosis, classically diabetic ketoacidosis — the lungs blowing off CO2 to compensate |
| Cheyne-Stokes | Crescendo then decrescendo depth, followed by 10–20 seconds of apnea, repeating | Heart failure, raised intracranial pressure, end of life; can be normal in infants and in sleeping older adults |
| Biot (ataxic) | Irregular breaths of varying depth interrupted by irregular apnea | Brainstem injury, meningitis — ominous |
| Apneustic | Prolonged gasping inspiration with a short, insufficient expiration | Pontine lesion |
| Agonal | Slow, irregular gasps | Peri-arrest — treat as no effective breathing and start resuscitation |
Pulse oximetry: what it measures and what it misses
A pulse oximeter shines red and infrared light through a pulsating vascular bed and calculates the percentage of hemoglobin binding sites occupied by oxygen, reported as SpO2. Expected value on room air is 95 to 100 percent. Because of the shape of the oxyhemoglobin dissociation curve, an SpO2 of 90 percent corresponds to a PaO2 of about 60 mm Hg, and below that point the curve falls steeply — small further drops in saturation represent large drops in dissolved oxygen. That is why 90 percent is a threshold rather than a gentle slope. In patients with chronic carbon dioxide retention, a target of 88 to 92 percent is deliberate, not an oversight.
Place the probe on a warm, well-perfused digit with the light source and detector facing each other, and confirm that the displayed pulse rate matches the pulse you palpate and that the waveform or signal-strength indicator looks convincing. A saturation reading attached to a heart rate that does not match the patient is not data.
| Limitation | Effect on the reading | What to do |
|---|---|---|
| Poor perfusion — hypotension, shock, hypothermia, vasopressors, peripheral arterial disease | Low or absent, unreliable signal | Warm the hand, move to earlobe or forehead sensor, correlate with palpated pulse, obtain an arterial blood gas |
| Motion, shivering, tremor | Erratic, artifactually low | Reposition, steady the digit, use a forehead or ear probe |
| Dark nail polish (blue, green, black), artificial nails | Falsely low or no reading | Remove polish, rotate the probe 90 degrees on the digit, or use another site |
| Carbon monoxide poisoning | Falsely normal or high — carboxyhemoglobin is read as oxyhemoglobin | Never trust the SpO2 in a fire or exhaust exposure; obtain co-oximetry and treat clinically |
| Methemoglobinemia (benzocaine, dapsone, nitrates) | Reads near 85 percent regardless of true saturation | Co-oximetry; the classic clue is chocolate-brown blood with a normal PaO2 |
| Severe anemia | Normal percentage, inadequate oxygen content | SpO2 does not measure how much hemoglobin exists — correlate with hemoglobin and clinical status |
| Intravenous dyes (methylene blue, indocyanine green) | Transiently falsely low | Recheck after the dye clears |
| Ambient light, venous congestion, a blood pressure cuff on the same arm | Falsely low or unstable | Shield the probe, use the opposite arm from the cuff |
| Darker skin pigmentation | May overestimate true arterial saturation — occult hypoxemia is measurably more common in patients with darker skin | Do not use a reassuring SpO2 to override work of breathing, mental status or dyspnea; obtain an arterial blood gas when the picture does not fit |
That last row is a patient-safety issue, not a footnote. Occult hypoxemia — a true arterial saturation below 88 percent while the oximeter reads 92 to 96 percent — occurs several times more often in patients with darker skin. Combine that with the fact that cyanosis is harder to appreciate on darkly pigmented skin, and the two tools most likely to catch hypoxemia can fail together in the same patient. Assess the oral mucosa, tongue, conjunctivae, palms and soles, where cyanosis appears as a gray or ashen dullness; count the respiratory rate; listen to whether the patient can finish a sentence; and escalate on the clinical picture even when the number looks acceptable.
Respiratory rate is the earliest sign of deterioration and must be counted, not estimated; pulse oximetry reports saturation only, and it can read falsely reassuring in carbon monoxide exposure, poor perfusion and darker-pigmented skin.
Section 5Blood Pressure, and Knowing When to Call
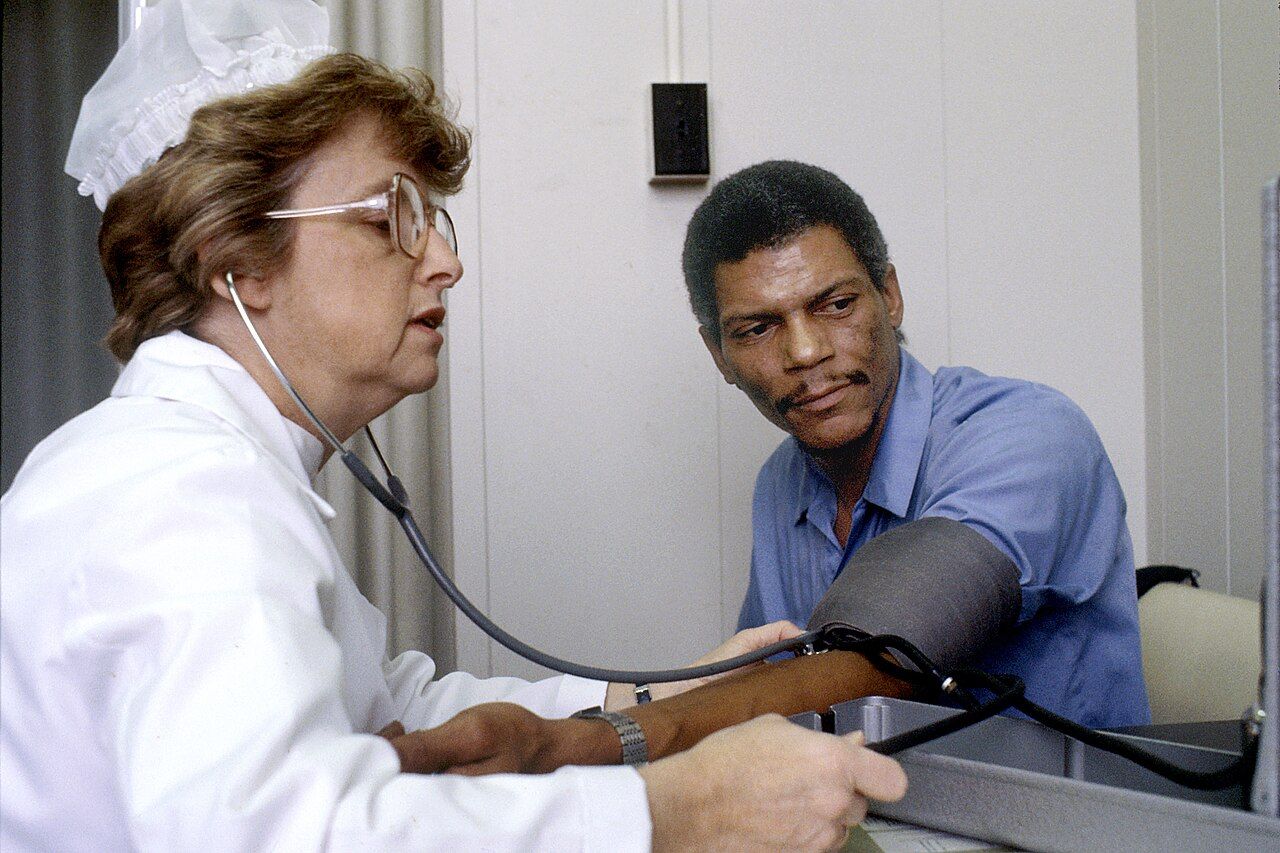
The technique that makes the number trustworthy
Blood pressure is the force the blood exerts against the arterial walls: the systolic peak during ventricular ejection and the diastolic trough during ventricular relaxation. It is determined by cardiac output and systemic vascular resistance, so it falls with hypovolemia, vasodilation and pump failure, and rises with volume overload, vasoconstriction and increased stroke volume. It is also the vital sign most easily corrupted by technique, and a corrupted blood pressure changes medication decisions.
Start with the cuff. The inflatable bladder width should be about 40 percent of the arm circumference at the midpoint of the upper arm, and the bladder length should encircle about 80 percent of the arm. A cuff that is too small requires more pressure to compress the artery and therefore reads falsely high — this is the single most common cause of a spurious hypertension diagnosis, and it happens constantly on patients with large arms. A cuff that is too large reads falsely low. Measure the arm or use the range printed on the cuff; do not eyeball it. If no cuff fits the upper arm, use a correctly sized cuff on the forearm with the radial artery auscultated, and document that you did.
Then prepare the patient. Five minutes of quiet rest, seated, back supported, feet flat on the floor, legs uncrossed, bladder empty, no caffeine or nicotine or exercise in the preceding 30 minutes, and no talking during the measurement — by the patient or by you. Bare the arm; a cuff over a sleeve reads falsely high. Support the arm at heart level, roughly the mid-sternum or fourth intercostal space. An arm hanging below heart level reads falsely high; an arm held above it reads falsely low. Avoid an arm with an arteriovenous fistula or graft, an intravenous infusion or PICC line, lymphedema or axillary node dissection, a cast, injury or paralysis. On first assessment measure both arms and use the higher; a persistent difference greater than 10 to 15 mm Hg between arms is abnormal, and a large acute difference raises the question of aortic dissection.
Now the measurement itself. Palpate the radial pulse and inflate until it disappears, note that number, and deflate fully; wait 30 to 60 seconds. Place the diaphragm (or bell) lightly over the brachial artery in the antecubital fossa, not under the cuff edge. Inflate to 20 to 30 mm Hg above the palpated systolic estimate. Deflate at 2 to 3 mm Hg per second — faster deflation systematically underestimates systolic and overestimates diastolic. The palpation step is not optional: it protects you from the auscultatory gap, a silent interval between the first and second Korotkoff phases seen in some patients with hypertension, which can make you record a systolic pressure 20 to 40 mm Hg too low if you inflated only until sounds vanished.
| Korotkoff phase | Sound | Meaning |
|---|---|---|
| Phase I | First clear tapping | Systolic pressure |
| Phase II | Swishing or blowing murmur | Where the auscultatory gap may appear |
| Phase III | Crisper, more intense tapping | Turbulent flow continues |
| Phase IV | Abrupt muffling | Recorded as diastolic only when sounds continue to zero — document all three numbers, for example 130/72/0 |
| Phase V | Disappearance of sound | Diastolic pressure in adults, in pregnancy and, per current pediatric guidance, in children |
| Error | Effect on the reading |
|---|---|
| Cuff too narrow or too short for the arm | Falsely high |
| Cuff too wide or too long | Falsely low |
| Cuff applied over clothing, or loosely | Falsely high |
| Arm below heart level | Falsely high (about 2 mm Hg per 2.5 cm of drop) |
| Arm above heart level or unsupported | Falsely low or falsely high with isometric effort |
| Legs crossed at the knee | Systolic higher by 2 to 8 mm Hg |
| Back unsupported, feet dangling | Diastolic higher by up to 6 mm Hg |
| Full bladder; talking during measurement; recent caffeine or nicotine | Higher by roughly 10 mm Hg each |
| Deflating faster than 3 mm Hg per second | Systolic falsely low, diastolic falsely high |
| Rechecking immediately without deflating fully and waiting | Venous congestion raises diastolic |
Automated oscillometric devices calculate systolic and diastolic values from the measured mean arterial pressure. They are accurate on stable patients with regular rhythms and unreliable in atrial fibrillation, tremor, shivering, severe hypotension and extremes of arm size. Any automated reading that would change management — especially a very low one — should be confirmed manually before you act on it.
Reading the number: categories, MAP, pulse pressure and orthostatics
| Category (adult, ACC/AHA) | Systolic | Combined by | Diastolic |
|---|---|---|---|
| Normal | Under 120 | and | Under 80 |
| Elevated | 120–129 | and | Under 80 |
| Hypertension stage 1 | 130–139 | or | 80–89 |
| Hypertension stage 2 | 140 or higher | or | 90 or higher |
| Hypertensive crisis | Higher than 180 | and/or | Higher than 120 |
A hypertensive crisis divides on symptoms. Hypertensive urgency is a pressure above 180/120 without evidence of target-organ damage: recheck after five minutes of rest, notify the provider, expect oral therapy and close follow-up. Hypertensive emergency is the same pressure with chest pain, dyspnea, neurologic change, visual change, severe headache, back pain or new oliguria, and it requires immediate intravenous therapy with the mean arterial pressure lowered by no more than about 25 percent in the first hour — dropping it faster can infarct the brain, heart or kidney.
Two derived numbers earn their place at the bedside. Mean arterial pressure approximates the average perfusion pressure across the cardiac cycle and is calculated as the diastolic plus one third of the pulse pressure; normal is 70 to 100 mm Hg, and a MAP below 65 is generally taken as the point at which organ perfusion is threatened. Pulse pressure is systolic minus diastolic, normally 30 to 40 mm Hg. A narrowing pulse pressure — below about 25 mm Hg, or less than 25 percent of the systolic — suggests falling stroke volume from hypovolemia, cardiac tamponade or heart failure, and it often narrows before the systolic pressure falls. A widening pulse pressure suggests arterial stiffening, aortic regurgitation, thyrotoxicosis or, in a head-injured patient, rising intracranial pressure. Cushing triad — rising systolic with a widening pulse pressure, bradycardia and irregular respirations — is a late and emergent sign of brain herniation.
Orthostatic vital signs test whether the patient can maintain pressure against gravity. Perform them when a patient reports dizziness on standing, has fallen, is on antihypertensives or diuretics, is suspected of bleeding or dehydration, or is starting to mobilize after prolonged bed rest. Technique: have the patient lie supine for at least five minutes, then measure blood pressure and heart rate. Assist the patient to sitting, wait one minute, repeat. Assist to standing, and measure at one minute and again at three minutes. Keep a chair behind the patient and a gait belt on; stop immediately and return the patient to bed if symptoms appear. The test is positive when, within three minutes of standing, the systolic falls by 20 mm Hg or more or the diastolic falls by 10 mm Hg or more. A heart-rate rise of 20 beats per minute or more supports volume depletion; a patient who drops pressure without raising the heart rate may have autonomic failure or be beta-blocked. Symptoms — lightheadedness, greying vision, near-syncope — are part of the result and belong in the note.
Charting it so it counts
A vital-sign entry has to let a nurse who has never met the patient reconstruct exactly what you measured, how, and what you did about it. That means values with units, the route or site, the position, the oxygen delivery, the comparison to the prior set, and the action taken. Compare these two entries describing the same patient.
| Vague and indefensible | Precise and defensible |
|---|---|
| “VS stable. Pt appears comfortable. Will continue to monitor.” | “1400 T 38.4 °C (101.1 °F) oral; HR 118 apical, regular; RR 26, unlabored, no accessory muscle use; BP 96/54 right arm, adult regular cuff, seated, arm supported; SpO2 92 percent on room air; pain 3/10 at right flank. Compared with 1000 set (T 37.2, HR 88, RR 18, BP 124/72, SpO2 97 percent RA): febrile, tachycardic, tachypneic, systolic down 28; more confused than at 1000. Meets 3 of 3 qSOFA criteria (RR 26, systolic 96, altered mentation). Provider notified 1408 via SBAR; blood cultures and lactate ordered.” |
| “BP low, held med.” | “0745 BP 88/52 left arm, seated, manual, confirmed after 5 min rest; HR 62. Scheduled metoprolol 25 mg PO held per parameters (hold for SBP under 100). Dr. Nwosu notified 0752, order received to hold and recheck in 1 hour. Patient asymptomatic, denies dizziness, ambulated to bathroom with standby assist.” |
| “Orthostatics positive.” | “Orthostatic VS: supine after 5 min BP 128/78, HR 72; sitting 1 min BP 118/74, HR 84; standing 1 min BP 102/66, HR 96; standing 3 min BP 98/62, HR 104. Patient reported lightheadedness at 3 min standing, no syncope, returned to bed with two-person assist. Positive orthostatic hypotension (SBP drop 30, HR rise 32). Fall precautions in place, provider notified 1120.” |
Chart in the moment, not at the end of the shift; chart what you measured rather than what you concluded (“BP 96/54” rather than “BP soft”); never chart a value you did not personally obtain without naming who did; and never chart in advance. If a value is refused or cannot be obtained, say so and say why: “Rectal temperature declined by patient; temporal 37.9 °C obtained instead.”
Red flags and the SBAR call
Some numbers do not wait for the next scheduled set. Learn these as thresholds that trigger a call, and remember that any acute change from a patient’s own baseline can outrank an absolute value.
| Red flag | Why it matters | Escalation |
|---|---|---|
| Adult respiratory rate under 10 or over 24 — and under 8 or over 30 is critical at any adult age | Earliest marker of deterioration; opioid-induced respiratory depression | Call now; for opioid depression assess sedation, stimulate, oxygen, prepare naloxone |
| SpO2 under 90 percent on room air, or falling despite added oxygen | PaO2 already near 60 mm Hg and on the steep part of the curve | Oxygen, sit upright, reassess airway, call now |
| Systolic under 90, MAP under 65, or a fall of 40 mm Hg from baseline | Perfusion failure — shock of any cause | Rapid response; large-bore access, position supine, prepare fluids |
| Heart rate under 40 or over 130 in an adult | Rate itself now compromises output | Call now; obtain a 12-lead ECG |
| Temperature 38.3 °C or higher, or below 36.0 °C, with tachycardia and tachypnea | Sepsis criteria — hypothermia counts | Sepsis protocol; cultures and lactate before antibiotics |
| Rectal 38.0 °C or higher in an infant under 3 months | Cannot localize infection | Immediate provider notification |
| New confusion, agitation or decreased level of consciousness | Often the first sign of hypoxia or sepsis, and part of qSOFA | Full vital-sign set, glucose, call now |
| Above 180/120 with chest pain, neurologic change, dyspnea or visual change | Hypertensive emergency | Immediate call; expect IV therapy and monitored setting |
| 140/90 or higher after 20 weeks of pregnancy, especially with headache, visual change or epigastric pain | Preeclampsia; 160/110 is severe-range and time-critical | Immediate obstetric notification |
| New absent peripheral pulse with a cold, painful limb that is pale or ashen-grey compared with the other side — compare limbs and check nail beds, palms and soles, since pallor is not reliably visible on darker skin | Acute arterial occlusion or compartment syndrome | Emergency — do not elevate the limb, call immediately |
Escalate in SBAR, and have the chart and the last two sets of vital signs in front of you before you dial. A worked example for the febrile patient above:
S — Situation: “Dr. Nwosu, this is Priya Raman, RN, on 4 West. I’m calling about Mr. Delgado in room 412, a 68-year-old man admitted yesterday with pyelonephritis. His vital signs have changed significantly in the last four hours and I’m concerned he is becoming septic.”
B — Background: “He was admitted at 0900 yesterday, is on IV ceftriaxone, has a history of type 2 diabetes and benign prostatic hyperplasia. At 1000 today he was 37.2 degrees, heart rate 88, respirations 18, blood pressure 124/72, saturation 97 percent on room air.”
A — Assessment: “Right now he is 38.4 oral, heart rate 118 and regular, respirations 26, blood pressure 96/54, saturation 92 percent on room air, and he is more confused than this morning. His mean arterial pressure is 68. He meets all three qSOFA criteria — respiratory rate 26, systolic 96 and altered mentation — and that systolic is down 28 points from this morning. I think he is septic and starting to decompensate.”
R — Recommendation: “I would like you to come and see him now. I am requesting the sepsis order set: blood cultures times two, a lactate, a CBC and chemistry, and a 30 mL/kg crystalloid bolus. I have started oxygen at 2 liters and placed a second large-bore IV. Would you like me to activate the rapid response team while you are on your way? And how often would you like vital signs — I plan on every 15 minutes.”
Then close the loop. Read the orders back, document the time of the call and the response, and if the patient continues to deteriorate or the provider does not respond, move up the chain of command — charge nurse, rapid response team, nursing supervisor. A rapid response team may be activated by any nurse without a provider’s permission, and in most facilities by the patient or family as well.
A blood pressure is only as good as the cuff, the position and the deflation rate — and once you have a trustworthy abnormal number, the job is not charting it but escalating it, in SBAR, now.
The chapter in one breath
Vital signs are physical assessment converted into numbers, and they earn their name because they are the earliest, cheapest and most sensitive warning that a patient is failing. Adults sit at 36.5 to 37.5 °C orally, 60 to 100 beats per minute, 12 to 20 breaths per minute, under 120/80 mm Hg, and 95 to 100 percent saturation; children run faster and lower-pressured, and older adults run cooler with wider pulse pressures. Technique determines whether those numbers mean anything: chart the temperature route, count an irregular pulse apically for a full minute, measure a pulse deficit with two nurses at once, count respirations without telling the patient, and remember that a cuff too small reads falsely high while a hurried deflation drags the systolic down. Pulse oximetry reports saturation only, and it lies in carbon monoxide poisoning, poor perfusion and — importantly — more often in patients with darker skin, so assess mucosa, conjunctivae and work of breathing rather than trusting the display. Interpret every value against the previous set and against that patient’s baseline, delegate measurement on stable patients but never interpretation, document values rather than conclusions, and escalate red flags immediately in SBAR.
Words worth knowing
| Term | What it means |
|---|---|
| Apical pulse | Heart rate auscultated at the point of maximal impulse, fifth intercostal space at the left midclavicular line, counted for a full minute. |
| Auscultatory gap | A silent interval between Korotkoff phases I and II that causes a falsely low systolic reading unless the cuff is first inflated above a palpated estimate. |
| Bradycardia / tachycardia | Adult heart rate under 60 / over 100 beats per minute. |
| Cheyne-Stokes respiration | Cyclical crescendo-decrescendo breathing alternating with apnea; seen in heart failure, raised intracranial pressure and dying. |
| Core temperature | Temperature of the deep tissues, approximated by rectal, tympanic, esophageal, bladder or pulmonary artery measurement. |
| Defervescence | The phase in which the hypothalamic set point falls and the patient diaphoreses and vasodilates as the fever breaks. |
| Eupnea | Normal, quiet, unlabored breathing at 12 to 20 breaths per minute in an adult. |
| Hypertensive emergency | Blood pressure above 180/120 mm Hg with evidence of target-organ damage; requires immediate intravenous treatment. |
| Korotkoff sounds | The five phases of sound heard as a cuff deflates; phase I is systolic, phase V is diastolic. |
| Kussmaul respirations | Deep, rapid, labored breathing compensating for metabolic acidosis, classically diabetic ketoacidosis. |
| Mean arterial pressure (MAP) | Average perfusion pressure, diastolic plus one third of the pulse pressure; normal 70 to 100 mm Hg, with 65 the usual perfusion threshold. |
| Occult hypoxemia | True arterial saturation below 88 percent while pulse oximetry reads 92 percent or higher; more frequent in patients with darker skin pigmentation. |
| Orthostatic hypotension | A fall of 20 mm Hg systolic or 10 mm Hg diastolic within three minutes of standing from supine. |
| Pulse deficit | Apical rate minus radial rate, measured simultaneously by two nurses for one minute; reflects contractions too weak to generate a peripheral wave. |
| Pulse pressure | Systolic minus diastolic pressure; normally 30 to 40 mm Hg, narrowing with falling stroke volume. |
| Pulsus paradoxus | An inspiratory fall in systolic pressure greater than 10 mm Hg; suggests tamponade or severe asthma. |
| Pyrexia | Fever — an adult temperature of 38.0 °C (100.4 °F) or higher, produced by a raised hypothalamic set point. |
| SpO2 | Peripheral oxygen saturation, the percentage of hemoglobin binding sites occupied by oxygen as estimated by pulse oximetry. |
| Thermoregulation | Hypothalamic balancing of heat production against heat loss through radiation, conduction, convection and evaporation. |
| qSOFA | Quick bedside sepsis screen: respiratory rate 22 or higher, systolic 100 mm Hg or lower, altered mentation; two of three indicates high risk. |
Check yourself
THE HEALTH HISTORY AND THE THERAPEUTIC INTERVIEW
Almost everything you will ever know about a patient arrives first as words. Before you lay a stethoscope on a chest or press a fingertip into an abdomen, the patient tells you where it hurts, when it started, what they took for it, and what they are afraid it means — and study after study finds that the history alone points to the correct diagnosis in the large majority of cases. The interview is therefore not the polite preamble to the “real” assessment; it is assessment, and it is a skill with technique, sequence, and error modes exactly like auscultation has. This chapter teaches you how to prepare the room and yourself, how to open with a question that produces information instead of a yes, how to analyze a symptom with OLDCARTS or PQRSTU, how to move through a review of systems without turning it into an interrogation, how to adapt for a toddler, a teenager, an interpreter, or an eighty-eight-year-old with hearing aids in the drawer — and how to recognize the sentence in the middle of a history that means you stop asking questions and escalate.
By the end of this chapter you can
- Prepare the environment, protect privacy under HIPAA, and position yourself for a therapeutic interview at eye level and appropriate interpersonal distance.
- Describe the orientation, working, and termination phases of the nurse’s interview and state the purpose of each.
- Apply at least ten therapeutic communication techniques and identify nontherapeutic responses such as false reassurance, leading questions, and “why” questions.
- Collect a complete health history, including biographic data, source and reliability, reason for seeking care, history of present illness, past health history, medication reconciliation, allergies with reactions, family history, and functional assessment.
- Analyze any symptom using OLDCARTS or PQRSTU and elicit pertinent negatives in a focused review of systems.
- Distinguish subjective from objective data and state the physical-examination sequence — inspection, palpation, percussion, auscultation — including the abdominal exception.
- Modify the interview for infants, children, adolescents (HEEADSSS), pregnancy, older adults, limited English proficiency, hearing loss, and aphasia.
- Chart a history in precise, quotable, defensible language and escalate red-flag findings using SBAR.
- Differentiate what may be delegated to unlicensed assistive personnel from what remains the registered nurse’s responsibility.
Section 1Before You Speak: Preparing for the Interview
Preparing yourself and the room
The interview begins before you enter the room. Review what is already known — the chart, the admission note, the handoff you just received, the medication list, the last set of vital signs, the reason the patient is here. This is the preinteraction phase, and it exists so that you do not spend the patient’s energy asking for data that is already documented. A patient who has told four people in six hours that her mother died of breast cancer will not enjoy telling a fifth. Reviewing first also lets you enter with a hypothesis: if the handoff said “new onset atrial fibrillation,” you already know you will be asking about palpitations, alcohol, thyroid disease, and anticoagulation.
Then prepare the physical space, because environment is technique. Close the door or draw the curtain fully — a curtain that is half open is not privacy, it is theater. Silence or mute the television. Adjust the lighting so the patient can see your face, and position yourself so a light source is not behind you, which turns you into a silhouette. Set the room to a comfortable temperature and offer a blanket; a shivering, half-covered patient is thinking about their body, not your questions. If the patient uses glasses, hearing aids, or dentures, put them in before you begin. Removing the barriers to communication takes ninety seconds and improves the quality of every answer that follows.
Finally, prepare your own attention. Put the phone away or turn it face down. Decide before you start how much time you actually have and tell the patient the truth about it: “I have about fifteen minutes right now, and I want to use it on what matters most to you.” A bounded, honest interview earns more trust than an open-ended one you visibly abandon halfway through. If the patient is in significant pain, nauseated, or urgently needs the bathroom, address that first. Maslow applies to interviewing too — nobody gives a good family history while they need a bedpan.
The phases of the interview
The orientation phase (also called the introduction) is short and it is where credibility is established. Knock, wait, enter. Address the patient by their preferred name and title — ask, do not assume, and never default to “honey,” “sweetie,” or “buddy.” Introduce yourself with name and role: “Good morning, Mr. Alvarez. I’m Dana Whitfield, I’m the registered nurse caring for you until seven tonight.” State the purpose and the plan: “I’d like to ask you some questions about your health so we can plan your care, and then I’ll do a physical assessment.” Ask permission and confirm identity using two identifiers per your facility policy — typically full name and date of birth, checked against the armband, never the room number.
The working phase is the body of the interview: data collection, symptom analysis, and validation. It moves from open to focused. You begin broad (“Tell me what brought you in”), let the patient talk without interruption, then narrow into specific closed questions to fill the gaps (“Has the pain ever woken you from sleep?”). Beginners reverse this order and start firing closed questions, which produces a checklist of yes and no answers and misses the story. Resist the urge. Research on clinician behavior consistently finds that patients are interrupted within roughly eleven to twenty-three seconds of beginning to speak; if you simply stay quiet for sixty to ninety seconds, most patients will hand you the history unprompted.
The termination phase closes the loop. Summarize what you heard in your own words and ask the patient to correct you: “So the pressure in your chest started Tuesday, comes on when you climb stairs, goes away when you rest, and this morning it lasted longer than usual. Did I get that right?” This is not a courtesy — it is error checking, and it routinely catches misunderstandings. Then ask the highest-yield question in all of nursing: “Is there anything else you think I should know?” Tell the patient what happens next and when you will be back. Never end an interview by walking out mid-sentence; if you must leave, name it and give a return time.
Presence, positioning, and the therapeutic use of self
Sit down. A nurse who sits is perceived as having spent substantially more time in the room than a nurse who stands for the identical duration, and the patient discloses more. Sit at the patient’s eye level or slightly below — standing over a supine adult in a bed reproduces a power imbalance that suppresses disclosure. Keep an interpersonal distance of roughly four to five feet, about twice arm’s length, for the conversational portion; that is close enough for warmth and far enough that the patient does not feel cornered. Move into personal and intimate space only for the physical examination, and announce it first: “I’m going to listen to your lungs now, so I’ll be standing close behind you.”
Keep your posture open — uncrossed arms, hands visible, leaning slightly forward, feet toward the patient. Avoid barriers: do not conduct the interview from behind a computer workstation with your back to the bed. If you must chart during the conversation, angle the screen so the patient can see it, and tell them what you are doing: “I’m typing what you said so I get it right.” Eye contact should be comfortable and intermittent, not fixed staring; the culturally appropriate amount varies widely, and in some communities sustained direct eye contact from a younger person to an elder, or across genders, is read as disrespect rather than attentiveness. Follow the patient’s lead.
Therapeutic use of self means deliberately deploying your own presence — voice, pace, face, silence — as an instrument. Speak slightly slower and lower than feels natural. Match your affect roughly to the patient’s: brisk cheerfulness delivered to a frightened person reads as dismissal. Watch your own nonverbals, because patients read them ruthlessly; a nurse who winces at a wound teaches the patient that the wound is disgusting. And protect confidentiality actively, not passively. Under the HIPAA Privacy Rule you must apply reasonable safeguards to limit incidental disclosures, which in practice means you do not take a sexual history through a curtain in a semi-private room. (The separate minimum-necessary standard is about how much information you disclose to any given recipient, not about who can overhear you.) Ask visitors to step out for the sensitive portion — “I ask everyone’s family to step out for a few minutes so I can ask some private questions” — which normalizes the request and, crucially, does not tip off a controlling partner that this patient specifically is being screened.
Privacy, positioning, and an uninterrupted first ninety seconds are not manners — they are the technique that determines how much true data the interview yields.
Section 2Therapeutic Communication: What Opens a Patient Up and What Shuts Them Down
Techniques that open the conversation
Therapeutic communication is a set of named, teachable moves. Open-ended questions invite narrative and cannot be answered with one word: “Tell me about the pain,” “What has your breathing been like at home?” Start here for every new problem. Closed or direct questions pin down specifics and are appropriate later or in an emergency: “Are you allergic to any medication?” “What time did it start?” In a rapid response, closed questions dominate, and that is correct — technique follows acuity.
Silence is the most underused technique in nursing. After a hard question, wait at least three to five seconds. The pause feels enormous to you and normal to the patient, and it is where disclosures live. General leads (“Go on,” “Mm-hm,” “And then?”) keep a narrative moving without steering it. Restating and paraphrasing feed back content so the patient can confirm or correct: “So you stopped the water pill on your own two weeks ago.” Reflection feeds back feeling rather than content: “You sound frightened.” Clarification repairs vagueness — “When you say dizzy, do you mean the room spins, or you feel like you might pass out?” That single clarification separates vertigo from presyncope and changes the entire workup.
Focusing narrows a scattered account (“Let’s stay with the chest pressure for a moment”). Empathy statements name and legitimize the emotion without claiming to share it: “That sounds exhausting,” not “I know exactly how you feel.” Offering self supplies presence without promises: “I’ll sit with you for a few minutes.” Validation confirms that a concern is reasonable. Summarizing ends a segment and checks accuracy. Finally, gentle confrontation surfaces a discrepancy without accusation: “You’re telling me the pain is a two out of ten, and I notice you’re guarding your belly and sweating. Help me understand.”
Responses that close it down
Nontherapeutic responses are usually well-intended, which is exactly why they are hard to unlearn. False reassurance (“Don’t worry, everything will be fine”) ends the conversation and cannot be honored; you do not know that it will be fine. Giving advice substitutes your judgment for the patient’s and blocks problem solving; offer information instead. “Why” questions read as accusation — “Why did you stop taking your insulin?” puts the patient on trial, while “What made it hard to keep taking the insulin?” produces the real answer, which is often that a vial costs more than the electric bill.
Leading and biased questions supply the answer you expect (“You don’t drink much, do you?”) and reliably generate false negatives. Stacked questions — three at once — get one answer and you will not know which. Medical jargon produces polite nodding: patients routinely misinterpret “NPO,” “void,” “hypertension,” and “negative results.” Changing the subject, defensive responses, stereotyped comments (“Everything happens for a reason”), false agreement, and interrupting all communicate the same message: your story is not welcome here. Watch also for distancing language (“the gallbladder in 12B”) and elderspeak — the sing-song, over-loud, diminutive register used with older adults, which is associated with resistance to care and loss of dignity.
| Nontherapeutic response | What the patient hears | Say this instead |
|---|---|---|
| “Don’t worry, you’ll be fine.” | Stop telling me how scared you are. | “It sounds like you’re worried about the surgery. Tell me what worries you most.” |
| “Why didn’t you come in sooner?” | You caused this. | “What made it hard to get here earlier?” |
| “You don’t smoke, right?” | The right answer is no. | “Tell me about your tobacco or vaping use, past and present.” |
| “If I were you, I’d take the surgery.” | Your decision is not yours. | “What questions do you still have about each option?” |
| “I know exactly how you feel.” | This is about you now. | “I can’t know what this is like for you. Tell me.” |
| “Everyone here is very competent.” | Do not complain. | “Tell me what happened last night that concerned you.” |
| Stacked: “Any chest pain, shortness of breath, or swelling?” | Pick one to answer. | Ask them one at a time and pause after each. |
Hard conversations: anger, tears, silence, and sensitive topics
An angry patient is usually a frightened or powerless one. Do not match the volume. Keep your voice low and slow, maintain a safe exit path, acknowledge the feeling without conceding facts you do not know (“You’re angry that no one told you about the delay. That’s fair — let me find out what happened”), and set a clear behavioral limit if needed (“I want to help you and I need you to stop shouting so I can hear you”). If you feel unsafe, leave and get help; personal safety precedes data collection, always.
A crying patient does not need to be fixed. Stop talking, offer tissues, stay, and wait. “Take your time” is a complete intervention. Do not rush to the next question and do not leave the room to escape the discomfort. With an anxious patient, shorten sentences, ask one thing at a time, and orient frequently. With a withdrawn or depressed patient, expect long latency — count to five before rephrasing, and use simple open questions with generous pauses.
Sensitive topics — sexual health, substance use, intimate partner violence, incontinence, finances, spiritual distress — require three things: privacy, normalization, and a matter-of-fact tone. Normalize with a preamble: “I ask every patient these questions.” Ask permission: “Is it all right if I ask about your sexual health?” Use the patient’s own words back to them. Ask about behavior, not identity (“Do you have sex with men, women, or both?”), and ask about the specific act rather than assuming from a stated orientation. Keep your face neutral. If a patient declines, document the decline and revisit later — a refusal today is not a refusal forever.
When the barrier is language, hearing, vision, or cognition
For patients with limited English proficiency, use a qualified medical interpreter — in person, by video, or by phone. This is a legal obligation for facilities receiving federal funds under Title VI of the Civil Rights Act and Section 1557 of the Affordable Care Act, and it is a safety issue: ad hoc interpreters produce clinically significant errors at several times the rate of trained ones. Do not use family members, and never use a child. Speak to the patient, not the interpreter; use first person (“Where does it hurt?” not “Ask him where it hurts”); use short segments; allow extra time. Document the interpreter’s name or ID number and the modality used. A bilingual nurse must be formally qualified by the facility before interpreting.
For hearing loss, first check that hearing aids are in and working. Face the patient in good light, do not cover your mouth, lower your pitch rather than raising your volume (high frequencies are lost first in presbycusis), rephrase rather than simply repeating louder, and reduce background noise. Do not rely on lip reading — only a minority of English speech sounds are visible on the lips. For patients who are Deaf and use American Sign Language, ASL is a distinct language and a qualified ASL interpreter is required; writing notes is not an equivalent substitute. For vision loss, announce yourself on entering and before touching, describe what you are doing, and orient the patient to the room and call light.
For aphasia, distinguish the two patterns, because the nursing approach differs. In expressive (Broca) aphasia comprehension is relatively intact but output is effortful — give time, allow gestures, use yes/no or pointing questions, and never finish sentences unless the patient asks you to. In receptive (Wernicke) aphasia speech is fluent but the content is off and comprehension is impaired — use short concrete phrases, gestures, pictures, and demonstration. For dementia or delirium, interview in a calm environment, ask one simple question at a time, avoid open-ended abstraction, use closed questions, and obtain collateral history from a caregiver — while still directing questions to the patient first. Document the source and your judgment of reliability.
Open-ended questions, silence, clarification, and summarizing produce data; false reassurance, advice, “why” questions, and jargon destroy it.
Section 3The Complete Health History, Component by Component
Biographic data, source, reliability, and the reason for seeking care
Biographic data anchors the record: full legal name, date of birth, age, sex assigned at birth and gender identity, pronouns, address and phone, occupation (present and past), preferred language, marital or partnership status, emergency contact, and insurance or payer if your facility collects it. Occupation is not administrative trivia — a forty-year history of grain dust, asbestos, or solvent exposure explains a chest film, and a night-shift schedule explains a hemoglobin A1c.
Source of history and reliability come next. Record who provided the information: the patient, a parent, a spouse, a group-home staff member, a prior record, or emergency medical services. A primary source is the patient; anything else is a secondary source. Then state whether the account seems reliable, and why. Reliability is not an insult — it is a flag for whoever reads your note next.
The reason for seeking care — historically called the chief complaint, increasingly called the chief concern — is a brief statement, ideally in the patient’s own quoted words, plus a duration. Write “‘My heart’s been flip-flopping since Saturday’ — 3 days,” not “atrial fibrillation.” The patient’s words are data; your diagnostic label is inference, and inference belongs later. Recording a label instead of the words is one of the most common and most consequential documentation errors students make, because it quietly closes the differential before anyone has examined the patient.
History of present illness, past health history, medications, and allergies
The history of present illness (HPI) is the chronological, detailed story of the current problem from the last time the patient felt well to now. It is built by symptom analysis, which Section 4 covers in full. It should include what the patient has already tried, what happened when they tried it, and their own theory of what is wrong — that last item takes ten seconds and frequently reveals the actual reason they came in (“My brother had the exact same thing and it was his heart”).
Past health history covers childhood illnesses; chronic conditions with dates of diagnosis; hospitalizations and surgeries with dates and facilities; injuries and accidents; blood transfusions; immunization status (including influenza, COVID-19, tetanus/Tdap, pneumococcal, shingles, and HPV as age-appropriate); most recent screening tests and examinations; and, for patients who can become pregnant, an obstetric history. Obstetric history is commonly recorded as GTPAL — Gravida (total pregnancies), Term births (37 weeks 0 days or later), Preterm births (20 weeks 0 days through 36 weeks 6 days), Abortions or losses before 20 weeks, and Living children.
Medication reconciliation is a required, high-risk task. Ask the patient to name every prescription, over-the-counter product, vitamin, herbal supplement, inhaler, eye drop, patch, injectable, and “as needed” medication — and ask about each category explicitly, because patients almost never volunteer eye drops, topicals, or supplements when asked “what medications do you take?” For each, capture drug, dose, route, frequency, indication, and when the last dose was actually taken, which is often not what the label says. Ask about sharing or borrowing medications, and ask about cost as a barrier without judgment. The best practice is to have the patient or family bring in the actual bottles.
Allergies require the reaction, not just the name. “Allergic to penicillin” is nearly useless; “Penicillin — hives and lip swelling within 1 hour, age 22, required epinephrine” is actionable, and “Penicillin — upset stomach as a child” describes an intolerance, not an allergy. That distinction changes antibiotic choice and patient outcomes. Ask separately about food, latex, contrast media, tape and adhesives, and environmental allergens. Document severity and the date of the reaction.
| Component | What you actually ask | Why it changes care |
|---|---|---|
| Reason for seeking care | “What brought you in today?” (record verbatim + duration) | Frames the entire encounter; the patient’s words prevent premature diagnostic closure |
| HPI | “Start from the last time you felt completely well.” | Chronology distinguishes acute from acute-on-chronic |
| Past health history | “What conditions do you see a doctor for? Any surgeries?” | Comorbidity drives risk, monitoring, and drug choice |
| Medications | “Walk me through everything you take, including drops, patches, and supplements.” | Prevents omission errors, duplication, and interactions |
| Allergies | “What happens when you take it? How soon? What was done?” | Separates true allergy from intolerance; guides emergency drugs |
| Family history | “Are your parents living? What conditions run in the family?” | Sets screening age and genetic risk |
| Functional assessment | “Walk me through a typical day at home.” | Determines discharge safety, equipment, and home services |
Family history and the genogram
Family history looks for heritable and familial risk across at least three generations — the patient, siblings and children, parents, and grandparents. Ask about age and cause of death for deceased relatives and current age and health for living ones. Screen specifically for cardiovascular disease and early sudden cardiac death, hypertension, stroke, diabetes, cancers (with the organ and the age at diagnosis), kidney disease, seizure disorders, mental illness and suicide, substance use disorder, tuberculosis, and known genetic conditions such as sickle cell disease, cystic fibrosis, or hemophilia.
Age at diagnosis is the part students skip and the part that matters most. A father with a myocardial infarction at 78 is unremarkable; a father with a myocardial infarction at 44 is a premature-family-history risk factor that changes lipid management. Breast cancer in a grandmother at 80 is different from breast cancer in a sister at 35, which may prompt genetic counseling. Bilateral, multiple-primary, or male breast cancer, and clusters of breast with ovarian or pancreatic cancer, raise concern for inherited susceptibility.
A genogram is the drawn version of this: squares for males, circles for females, a diamond when sex is unknown, a slash through the symbol for deceased with the age and cause noted, horizontal lines for partnerships, vertical lines for offspring, and the patient marked with an arrow. It compresses three generations into an image you can read in five seconds and is far more useful at a glance than a paragraph. Also ask about family environment and shared exposures — household smoking, water source, occupational exposures, and who the patient can actually call at two in the morning.
Functional assessment and perception of health
Functional assessment asks what the patient can do, not what is wrong with them, and it is what determines whether discharge is safe. Assess activities of daily living (ADLs) — bathing, dressing, toileting, transferring, continence, and feeding — and instrumental activities of daily living (IADLs) — managing medications, managing money, shopping, cooking, housekeeping, laundry, using the telephone, and transportation. Ask about assistive devices, who helps and how often, and what has changed in the last six months. A patient who could climb their porch steps in March and cannot in June has a story worth chasing.
Extend into the domains that predict outcomes: nutrition (a 24-hour dietary recall, appetite change, unintentional weight loss, food access, chewing and swallowing, dentition); elimination patterns; sleep and rest (hours, insomnia, snoring, witnessed apnea, daytime somnolence); activity and exercise; substance use including tobacco, vaping, alcohol, cannabis, and other drugs, quantified honestly (“How many days a week do you have a drink? On those days, how many?”); sexual health; occupational and environmental hazards; coping and stress; social supports; spiritual and cultural practices that affect care; and advance directives and health care proxy.
Screen for social drivers of health deliberately, because they are more predictive of readmission than most laboratory values: housing stability, food security, transportation, utilities, interpersonal safety, literacy, and ability to afford medications. Ask plainly — “In the last twelve months, did you worry that your food would run out before you got money to buy more?” Close the history with the patient’s perception of health: “How would you describe your health? What do you think is going on? What are you hoping we can do?” Self-rated health is a startlingly strong predictor of outcomes, and the answer tells you exactly where to aim your teaching.
A complete history is not a form to fill in but a structure to think in — and its highest-risk components are medication reconciliation, allergy reactions, and functional status.
Section 4Symptom Analysis, the Review of Systems, and the Bridge to the Physical Exam
Analyzing a symptom: OLDCARTS and PQRSTU
Every symptom — pain, cough, dizziness, nausea, a rash, palpitations, fatigue — gets the same systematic dissection. Two mnemonics dominate. OLDCARTS: Onset (when did it start, sudden or gradual, what were you doing), Location (point to it with one finger), Duration (how long does an episode last, is it constant or intermittent), Characteristics (in your words — sharp, crushing, burning, tearing), Aggravating and associated factors (what makes it worse; what else happens with it), Relieving factors and radiation (what helps; does it travel), Timing and treatment (pattern across the day; what have you already taken), Severity (0 to 10, and what it stops you from doing).
PQRSTU covers the same ground with a different handle: Provocative and palliative, Quality, Region and radiation, Severity, Timing, and Understanding — the patient’s own interpretation and the impact on daily life. Use whichever your program teaches; use it every single time, including at three in the morning, because completeness is what makes the pattern visible. The character of chest pain distinguishes pleuritic from ischemic; the radiation of flank pain to the groin suggests a ureteral stone; a sudden “thunderclap” onset of the worst headache of a person’s life is a subarachnoid hemorrhage until proven otherwise.
Two additions elevate a student history to a professional one. First, always ask what makes it better or worse in behavioral terms — not just “does anything help” but “does leaning forward help, does eating make it worse, does it wake you at night.” Second, always capture pertinent negatives: the symptoms you deliberately asked about and the patient denies. “Denies fever, cough, hemoptysis, leg swelling, or recent travel” in a patient with chest pain proves you thought about pneumonia and pulmonary embolism. Absent findings, documented, are evidence of clinical reasoning.
The review of systems
The review of systems (ROS) is a head-to-toe screen of subjective symptoms, by body system, to catch problems the patient did not think to mention. It is entirely questions — nothing you observe belongs here. Move in a fixed order so you do not skip a system: general, integumentary, head and neck, eyes, ears, nose and sinuses, mouth and throat, respiratory, cardiovascular, peripheral vascular, gastrointestinal, genitourinary, sexual and reproductive, musculoskeletal, neurologic, hematologic, endocrine, and psychiatric.
Use plain language. Ask “Any trouble swallowing?” not “Any dysphagia?” Ask “Do you ever leak urine when you cough or laugh?” rather than “Any stress incontinence?” A complete ROS is appropriate for a comprehensive admission history; for a focused or emergency assessment, review the system involved plus the systems immediately adjacent to it. Whichever you do, document which it was — “Focused ROS, cardiopulmonary” is honest; implying a complete ROS you did not perform is a documentation integrity problem.
Certain ROS answers are not merely positive — they are stop-signs. Learn them as a set, because they arrive in the middle of an otherwise routine conversation and your job is to recognize them in real time.
| System | Expected / reassuring answer | Concerning answer | What it may indicate |
|---|---|---|---|
| General | Weight stable, usual energy, no fevers | Unintentional loss of 4.5 kg (10 lb) or 5 percent of body weight in 6 months; drenching night sweats | Malignancy, tuberculosis, HIV, hyperthyroidism, heart failure |
| Cardiovascular | No chest pain; can climb two flights without stopping | Substernal pressure with exertion, radiating to jaw or left arm, with diaphoresis and nausea | Acute coronary syndrome — escalate immediately |
| Respiratory | No cough, no dyspnea, sleeps on one pillow | Sudden dyspnea with pleuritic pain and calf swelling; or coughing blood | Pulmonary embolism — escalate immediately; malignancy; tuberculosis |
| Neurologic | No headaches beyond occasional tension type | “Worst headache of my life,” sudden onset; new one-sided weakness, facial droop, slurred speech | Subarachnoid hemorrhage; stroke — activate the stroke alert and establish the last-known-well time |
| Gastrointestinal | Regular bowel pattern, no melena | Vomiting blood, black tarry stools, or new severe abdominal pain with rigidity | Upper GI bleed; perforation or peritonitis |
| Genitourinary | Voids without pain, no hematuria | Flank pain with fever and chills; no urine output in 12 hours | Pyelonephritis or urosepsis; obstruction or acute kidney injury |
| Psychiatric | Mood stable, sleeps adequately, no thoughts of self-harm | “Sometimes I think everyone would be better off without me,” with a plan or means | Active suicidal ideation — do not leave the patient alone; escalate now |
| Obstetric (pregnancy) | Fetal movement as expected; no bleeding | Severe headache with visual changes and right-upper-quadrant pain after 20 weeks | Preeclampsia with severe features — urgent evaluation |
Subjective, objective, and the handoff to the physical examination
Subjective data is what the patient (or a proxy) reports — symptoms, feelings, perceptions, history. It cannot be observed by anyone else and is documented as reported: “Pt reports…”, “Pt states…”, “Pt denies…”, or in direct quotation. Objective data is what you observe, measure, or elicit — vital signs, a wound’s dimensions, lung sounds, a laboratory value, an observed limp. Nausea is subjective; emesis of 200 mL of coffee-ground fluid is objective. Pain is uniquely both: the reported score is subjective and is charted as the patient states it, while guarding, grimacing, tachycardia, and diaphoresis are objective corroboration. You never override a reported pain score with your own impression.
When the history is complete, you move to the physical examination, and the sequence there is fixed: inspection, palpation, percussion, auscultation. Inspect first because touching changes what you will see and because looking costs nothing. Palpate second, light before deep, warm hands, painful areas last. Percuss third to assess density and organ borders. Auscultate fourth. Work in an organized head-to-toe order, compare side to side for symmetry, and expose only the region being examined.
There is exactly one region where this order changes, and you must know it cold. For the abdomen, the sequence is inspect, auscultate, percuss, palpate. Auscultation moves ahead of percussion and palpation because manipulating the abdominal wall alters bowel motility and therefore falsifies the bowel sounds you are about to grade. Listen before you touch, in all four quadrants, before percussing or palpating anything. Examine any area the patient identifies as painful last, and stop deep palpation entirely if there is rigidity, rebound, or a known or suspected abdominal aortic aneurysm.
| Region | Sequence | Rationale |
|---|---|---|
| All regions except the abdomen | Inspection → Palpation → Percussion → Auscultation | Least invasive first; touch is not yet distorting anything you will measure |
| Abdomen | Inspection → Auscultation → Percussion → Palpation | Percussing or palpating first alters bowel motility and falsely changes bowel sounds |
| Painful or suspicious areas | Examined last, within whichever sequence applies | Preserves cooperation and prevents guarding from contaminating the rest of the exam |
The history also tells you what to expect from the vital signs and how hard to worry when they deviate. Know the adult numbers exactly, and know how they shift across the lifespan, because “a heart rate of 130” is a red flag in an adult that demands an immediate search for a cause, and is unremarkable in a well six-month-old.
| Age group | Heart rate, awake (beats/min) | Respirations (breaths/min) | Blood pressure (mm Hg) |
|---|---|---|---|
| Newborn (0–28 days) | 100–205 | 30–60 | Systolic 67–84 |
| Infant (1–12 months) | 100–180 | 30–53 | Systolic 72–104 |
| Toddler (1–2 years) | 98–140 | 22–37 | Systolic 86–106 |
| Preschool (3–5 years) | 80–120 | 20–28 | Systolic 89–112 |
| School age (6–11 years) | 75–118 | 18–25 | Systolic 97–115 |
| Adolescent (12–15 years) | 60–100 | 12–20 | Systolic 110–131 |
| Adult | 60–100 | 12–20 | Normal <120/<80; elevated 120–129/<80; stage 1 130–139/80–89; stage 2 ≥140/≥90 |
| Older adult (65+) | 60–100 | 12–20 | Systolic stiffening common; isolated systolic hypertension frequent |
Adult oral temperature normally runs 36.5–37.5 °C (97.7–99.5 °F); rectal readings average about 0.5 °C higher and axillary about 0.5 °C lower. Fever in an adult is generally defined at 38.0 °C (100.4 °F) or above. Older adults run a lower baseline, often 35.8–36.6 °C, and may mount no fever at all with serious infection — a single oral temperature of 37.8 °C (100 °F), repeated readings above 37.2 °C (99 °F), or a rise of 1.1 °C (2 °F) over that patient’s own baseline should be treated as fever. Oxygen saturation is 95–100 percent on room air for most adults; patients with chronic carbon-dioxide retention are often targeted to 88–92 percent, so know the ordered target before you adjust anything. Be aware that pulse oximeters can overestimate true arterial saturation in patients with darker skin pigmentation, producing occult hypoxemia — a normal-looking reading in a patient who is genuinely hypoxic. Never let the number override the patient: work of breathing, respiratory rate, mental status, and the patient’s own report of breathlessness come first, and a reading that does not match the patient warrants a repeat on a different site and escalation.
Analyze every symptom the same way every time, document the pertinent negatives, and remember that the exam sequence is inspect–palpate–percuss–auscultate everywhere except the abdomen, where auscultation comes second.
Section 5Lifespan, Culture, Risk Screening, Charting, and Escalation
Adapting across the lifespan
For infants, the history comes entirely from the caregiver and includes prenatal, birth, and neonatal history — gestational age, complications, delivery mode, birth weight, newborn screening, feeding method and volumes, wet diapers per day, sleep position, and developmental milestones. Perform the least invasive parts of any assessment while the infant is calm and in the caregiver’s arms.
Toddlers and preschoolers think concretely and magically; they may believe illness is punishment. Get to eye level, use short words, allow a security object, and offer limited real choices (“left arm or right arm?” — never “may I?” for something that is not optional). Avoid frightening literalisms: “take your blood pressure” and “shot” and “put you to sleep” are heard exactly as spoken. School-age children can give substantial history themselves and want a mechanical explanation; ask them first, then verify with the caregiver.
Adolescents must be given time alone with the clinician. Explain confidentiality and its legal limits up front — you will keep what they say private except where there is risk of harm to themselves or others, or abuse. Use the HEEADSSS framework: Home, Education and employment, Eating, Activities, Drugs, Sexuality, Suicide and depression, and Safety, moving from least to most sensitive. In pregnancy, add GTPAL, prenatal care, fetal movement, and the preeclampsia symptom set. For older adults, allow more time, ask about function and falls, review polypharmacy and who fills the pillbox, screen for cognition and mood, and ask about caregiver strain and elder mistreatment — privately. Do not shout; do not use elderspeak; do not assume confusion until you have ruled out hearing loss, delirium, pain, and hypoxia.
Cultural humility, and findings across skin tones
Cultural humility is a posture, not a body of memorized facts: you assume you do not know this patient’s beliefs and you ask. Useful questions include “What do you think caused this?”, “What do you call it?”, “What have you already tried, including home or traditional remedies?”, and “Who in your family helps make health decisions?” Ask about fasting, dietary law, modesty and same-gender caregiver preferences, and practices around touch, blood products, and end of life. Never generalize from an ethnic label to an individual’s beliefs.
Skin tone changes how findings appear, and describing every abnormality as “redness” is both inaccurate and a documented source of missed pressure injuries and missed hypoxia in patients with darker skin. Assess in natural or bright white light, compare with the patient’s own baseline and adjacent skin, and always use the mucous membranes and palms as a check.
| Finding | In lightly pigmented skin | In darker pigmented skin | Where to look instead |
|---|---|---|---|
| Cyanosis | Blue-gray lips, nail beds, skin | Skin appears ashen, gray, or dull; blue may not be visible at all | Oral mucosa, tongue, conjunctivae, palms and soles, nail beds |
| Pallor | Loss of pink tone; skin appears white | Yellow-brown or ashen-gray cast; loss of underlying red tones | Conjunctivae, oral mucosa, palms, nail beds |
| Jaundice | Yellow skin and sclerae | Sclerae may show normal carotene deposits near the outer edge — check near the iris | Sclerae adjacent to the iris, hard palate, palms and soles |
| Erythema / inflammation | Bright red, blanchable | Deep red, purple, violaceous, or simply darker than surrounding skin | Palpate for warmth, induration, edema, and tenderness; compare to the opposite side |
| Early pressure injury | Nonblanchable erythema | Color change may be subtle; blanch response unreliable | Skin temperature difference, boggy or firm texture, patient-reported pain |
| Petechiae | Tiny red-purple nonblanching dots | Difficult to see on the skin surface | Buccal mucosa, conjunctivae, abdomen, palms and soles |
Screening for risk, and the red flags that stop the interview
Several validated screens belong in the history. The PHQ-2 asks about depressed mood and anhedonia over two weeks; a score of 3 or more is positive and should be followed by the PHQ-9. Any positive response to item 9 of the PHQ-9, or any spontaneous statement about wanting to die, triggers a direct suicide risk assessment — ask plainly (“Are you having thoughts of killing yourself?”), then ask about plan, means, timeline, and intent. Asking does not plant the idea; the evidence is clear on this. AUDIT-C screens alcohol use (positive at 4 or more for men, 3 or more for women); the CAGE questionnaire is positive at 2 or more. Screen for intimate partner violence privately, with the partner out of the room, using a brief tool such as HITS, and know your state’s mandatory reporting law for children, dependent adults, and elders.
Some statements end the data-collection phase immediately. Recognize them and act: chest pressure with diaphoresis, dyspnea, or radiation to the jaw or arm; sudden severe headache described as the worst of the patient’s life; new facial droop, one-sided weakness, or speech change (get the last-known-well time before anything else); airway symptoms after a new medication — lip or tongue swelling, throat tightness, stridor, hives; hematemesis, melena, or syncope; suicidal or homicidal ideation with plan or means; disclosure of abuse with immediate danger; and any patient who says they feel a sense of impending doom — which is a genuine clinical sign, not an anxiety symptom, until you have proven otherwise. One tier below these, but still requiring that you notify the provider before the shift moves on rather than charting it and continuing, is a missed dose of insulin, anticoagulant, antiepileptic, or antirejection medication.
Charting the history and escalating with SBAR
Documentation of a history has four requirements: it is timely, objective in tone, specific in measurement, and attributed to a source. Quote the patient for the reason for seeking care and for anything clinically or legally significant. Use “reports,” “states,” and “denies” rather than “complains of,” which reads as judgment. Never chart opinion about character (“drug seeking,” “uncooperative,” “poor historian”); chart the behavior you observed instead. Never chart care before it is given, never chart for another person, and correct errors according to policy — single line, initial, date, addendum — never by erasing or deleting.
| Vague entry | Precise entry | Why the difference matters |
|---|---|---|
| “Pt c/o chest pain. Will monitor.” | “0918 — Pt reports substernal chest pressure that began at 0850 while walking to the bathroom, described as ‘like a belt tightening,’ 7/10, radiating to left jaw, with diaphoresis and nausea, not relieved by rest x 25 min. Denies prior similar episodes, fever, cough, or leg swelling. VS 148/92, HR 104 regular, RR 24, T 36.8 °C oral, SpO2 94 percent room air. Rapid response activated 0920.” | Timed, quantified, quoted, includes pertinent negatives and the action taken |
| “Allergic to penicillin.” | “Penicillin — hives and lip swelling within 1 hr of dose, approx. age 22, treated in ED with epinephrine. Tolerates cephalexin per pt.” | Distinguishes true allergy from intolerance and guides antibiotic selection |
| “Poor historian.” | “History obtained from daughter at bedside. Pt oriented to person only; unable to state current medications or date. Considered limited reliability.” | Replaces a judgment with an observation plus an explicit source and reliability statement |
| “Drinks socially.” | “Reports 4–5 beers on each of 5 evenings per week x 10 yrs; last drink 0700 today. AUDIT-C 7.” | Quantified use predicts withdrawal risk and triggers a CIWA protocol |
| “Pt seems depressed.” | “PHQ-2 score 4. On PHQ-9, pt endorsed item 9: ‘I’ve thought it would be easier if I didn’t wake up.’ Denies plan or means. Provider notified 1410; 1:1 observation initiated.” | Documents the screen, the exact words, the risk assessment, and the safety intervention |
When you escalate, use SBAR, and have the chart, the last vital signs, and the medication list in front of you before you dial. Situation: “This is Dana Whitfield, RN, on 4 East calling about Mr. Alvarez in room 412. He has new chest pressure that started 30 minutes ago.” Background: “He’s a 62-year-old admitted yesterday for cellulitis, with a history of type 2 diabetes, hypertension, and a father who died of a myocardial infarction at 51. He’s on metformin and lisinopril, no anticoagulation.” Assessment: “Blood pressure 148/92, heart rate 104 and regular, respirations 24, oxygen saturation 94 percent on room air, temperature 36.8. He’s diaphoretic and describes 7 out of 10 pressure radiating to his jaw. I think this is cardiac.” Recommendation: “I’d like a 12-lead ECG now, cardiac markers, and an order for aspirin. Can you come see him, or should I activate rapid response?” Then read back any orders you receive, and document the call with the time, the person notified, and the response.
Delegation and scope
Interviewing is a professional nursing act. The registered nurse performs the initial and ongoing assessment, analyzes the data, formulates nursing diagnoses, teaches, evaluates responses to interventions, and manages unstable patients. None of that may be delegated. In particular, the health history, the interpretation of a symptom, the suicide risk assessment, patient education, and any judgment about reliability or acuity stay with the RN. Delegation follows the five rights — right task, right circumstance, right person, right direction and communication, right supervision and evaluation — and the RN who delegates retains accountability for the outcome.
Unlicensed assistive personnel may perform standardized, predictable tasks on stable patients: obtaining and recording routine vital signs, height and weight, intake and output, capillary blood glucose where policy allows, bathing, feeding, ambulating, and positioning. UAP may — and should — report what a patient told them, and you should ask them what they noticed; their observations are valuable raw data that you then interpret. What UAP may not do is collect the history, decide what a symptom means, teach the patient, evaluate the effect of an intervention, or take vital signs on an unstable patient whose readings will drive an immediate decision. Give explicit parameters when you delegate: “Please take Mr. Alvarez’s vital signs now and tell me right away if his heart rate is over 110, his systolic is under 100, or his oxygen saturation is under 92.” A licensed practical or vocational nurse can gather focused data and reinforce teaching within state scope, but the comprehensive assessment and the care plan remain the RN’s.
Adapt the interview to development, culture, and skin tone; screen deliberately for mood, safety, and substance use; chart in quoted, timed, quantified language; and escalate red flags with SBAR rather than finishing the form.
The chapter in one breath
The health history is assessment, not preamble, and it is the single richest source of clinical data you will ever have. It begins before you enter the room — reviewing the chart, closing the curtain, restoring glasses and hearing aids, sitting down at eye level about two arm-lengths away. It proceeds through orientation, working, and termination phases, opening with an unhurried question and holding your silence long enough for the patient to actually answer. Therapeutic technique — open-ended questions, silence, clarification, reflection, summarizing — produces data; false reassurance, advice, “why” questions, leading questions, and jargon destroy it. The complete history runs from biographic data and source reliability through the reason for seeking care in the patient’s own words, the history of present illness dissected by OLDCARTS or PQRSTU, past health history, a medication reconciliation that includes drops and supplements, allergies documented with their reactions, three generations of family history with ages at diagnosis, functional status, and social drivers of health. The review of systems screens subjective symptoms head to toe; documented pertinent negatives prove you reasoned. Then the physical begins — inspect, palpate, percuss, auscultate everywhere except the abdomen, where you auscultate before you touch. Adapt for infants, adolescents, pregnancy, elders, interpreters, and every skin tone. And when a red flag arrives mid-sentence, stop, assess, stay, and escalate with SBAR.
Words worth knowing
| Term | What it means |
|---|---|
| Subjective data | What the patient or a proxy reports — symptoms, feelings, history; charted as “reports,” “states,” “denies,” or in direct quotation. |
| Objective data | What the nurse observes, measures, or elicits — vital signs, wound dimensions, breath sounds, laboratory values. |
| Reason for seeking care | The brief statement, ideally quoted verbatim with a duration, of why the patient came; also called the chief concern or chief complaint. |
| History of present illness (HPI) | The detailed chronological account of the current problem, from the last time the patient felt well until now. |
| OLDCARTS | Onset, Location, Duration, Characteristics, Aggravating and associated factors, Relieving factors and radiation, Timing and treatment, Severity — a symptom-analysis framework. |
| PQRSTU | Provocative/palliative, Quality, Region/radiation, Severity, Timing, Understanding — an alternative symptom-analysis framework. |
| Pertinent negative | A symptom specifically asked about and denied; documenting it demonstrates that the differential was considered. |
| Review of systems (ROS) | A head-to-toe screen of subjective symptoms by body system; contains no examination findings. |
| Primary vs. secondary source | The patient is the primary source; family, caregivers, prior records, and EMS reports are secondary sources and must be identified in the chart. |
| Medication reconciliation | Systematic verification of every prescription, over-the-counter product, supplement, patch, drop, and inhaler with dose, route, frequency, and time of last actual dose. |
| Allergy vs. intolerance | An allergy is an immune-mediated reaction (hives, angioedema, anaphylaxis); an intolerance is an adverse but non-immune effect such as nausea. Both are documented, with the reaction described. |
| GTPAL | Gravida, Term births, Preterm births, Abortions/losses before 20 weeks, Living children — shorthand for obstetric history. |
| Genogram | A drawn family tree of at least three generations using squares, circles, and connecting lines to display heritable risk at a glance. |
| ADLs and IADLs | Basic self-care tasks (bathing, dressing, toileting, transferring, continence, feeding) and higher-order tasks (medications, money, shopping, cooking, transportation, telephone). |
| HEEADSSS | Home, Education/employment, Eating, Activities, Drugs, Sexuality, Suicide/depression, Safety — the confidential adolescent psychosocial interview. |
| Cultural humility | An ongoing stance of self-examination and inquiry in which the nurse asks about the individual’s beliefs rather than assuming them from group membership. |
| Elderspeak | Slow, loud, sing-song, diminutive speech directed at older adults; associated with reduced dignity and increased resistance to care. |
| Aphasia (expressive vs. receptive) | Expressive (Broca) — comprehension intact, output effortful; receptive (Wernicke) — speech fluent but content and comprehension impaired. |
| SBAR | Situation, Background, Assessment, Recommendation — the structured format for escalating a concern and making a specific request. |
| Five rights of delegation | Right task, right circumstance, right person, right direction and communication, right supervision and evaluation. |
Check yourself
General Survey, Pain and Mental Status
Before you place a stethoscope on anyone, you have already collected data. The way a patient sits, whether they finish a sentence without stopping for air, whether they are groomed, whether they meet your eye, whether they shift and wince when they move — all of it is assessment, and all of it is chartable. This chapter teaches the three assessments that frame every other examination in this book: the general survey, the systematic first impression; the pain assessment, which is a symptom only the patient can define and which nurses have historically undertreated; and the mental status assessment, where a change of a single point is often the earliest sign that a patient is deteriorating. You will also learn the four physical examination techniques — inspection, palpation, percussion, auscultation — and the one body region where that order deliberately changes. Get these right and the rest of the head-to-toe becomes a confirmation of what you already suspected.
By the end of this chapter you can
- Perform a structured general survey across the four domains of physical appearance, body structure, mobility and behavior, and state at least six findings that warrant escalation.
- Demonstrate inspection, palpation, percussion and auscultation in correct sequence, and explain the abdominal exception in which auscultation precedes percussion and palpation.
- Measure height and weight accurately, calculate and interpret body mass index (BMI), and identify clinically significant unintentional weight loss.
- Conduct a complete pain assessment using PQRSTU or OLDCARTES, and select the correct pain scale for a patient by age, developmental stage and ability to self-report.
- Distinguish nociceptive (somatic and visceral) from neuropathic pain and match assessment language to each.
- Apply the Pasero Opioid-Induced Sedation Scale (POSS) and explain why sedation is monitored before respiratory rate falls.
- Assess level of consciousness with AVPU, RASS and the Glasgow Coma Scale (GCS), and score all three components of the GCS accurately.
- Differentiate delirium, dementia and depression, and screen for delirium using the Confusion Assessment Method (CAM).
- Document a general survey, pain and mental status assessment in precise, defensible language, escalate using SBAR, and apply the rules of delegation to unlicensed assistive personnel.
Section 1The General Survey and the Four Techniques
What the general survey is, and the four domains you scan
The general survey is a deliberate, structured first impression. It is not “eyeballing” the patient. It is a scan that you perform the same way on every patient so that when something is different, you notice it. It begins the moment the patient is in your field of view — in the doorway, in the hallway, in the waiting room — and it continues while you introduce yourself, wash your hands and take vital signs. Experienced nurses do this in under a minute and can tell you, before the monitor is attached, roughly how sick the person is. That skill is not intuition. It is a checklist run so many times that it has become automatic, and you build it by running the checklist consciously until it is.
Scan four domains, always in the same order. Physical appearance: apparent age compared with stated age, level of consciousness, skin color and condition, facial expression and symmetry, hygiene and grooming, dress appropriate to the setting and the weather, and any odor (ketones, alcohol, urine, infected wound, poor hygiene). Body structure: height and build, apparent nutritional state, symmetry of the body, posture, and any obvious deformity, amputation, edema or muscle wasting. Mobility: gait, use of assistive devices, range of motion, how the patient moves from chair to bed, and any involuntary movement such as tremor, tic or restlessness. Behavior: eye contact, facial expression, mood and affect, speech (rate, volume, clarity, articulation), and the relationship between the patient and anyone accompanying them.
Two survey findings deserve special naming because they carry so much weight. Tripod positioning — the patient sitting leaning forward with arms braced on knees or a bedside table — means the patient is recruiting accessory muscles to breathe and should never be laid flat “so you can examine them.” And the number of words a patient can say between breaths is a bedside respiratory measurement you can chart: full sentences, three-to-four-word phrases, or single words. A patient who was speaking in full sentences at 0800 and is speaking in three-word phrases at 1200 has deteriorated, even if the recorded respiratory rate has not changed.
The four techniques, and the order that changes
Every physical examination in this book is built from four techniques, performed in this sequence: inspection, palpation, percussion, auscultation. The logic is that each technique is progressively more disruptive, so the least invasive information is gathered while the body is still undisturbed. There is one deliberate exception. For the abdomen, the sequence is inspect, auscultate, percuss, palpate. Percussing and palpating the abdomen mechanically stimulates the bowel and alters bowel sounds, so listening must happen before you touch. Say that exception out loud until it is reflex, because it is one of the most commonly missed items on both exams and clinical checkoffs — and a nurse who palpates first and then reports “hyperactive bowel sounds” has reported an artifact they created.
Inspection is purposeful looking. Provide adequate light — natural daylight is best, especially for assessing color in darker skin tones — expose only the area being examined, keep the room warm, and compare the side you are examining with its opposite. Inspect before you touch, and give it real time; most nurses under-inspect. Colour findings must be judged where pigment cannot hide them, in every patient and not only in patients with dark skin: look at the oral mucosa and tongue, the palpebral conjunctivae, the lips and nail beds, and the palms and soles. Cyanosis is not reliably “blue” — in richly pigmented skin it shows as grey, ashen or dull darkening, and it is confirmed at the tongue, oral mucosa and conjunctivae rather than at the fingertips. Pallor appears as ash-grey or yellow-brown skin with pale conjunctivae, pale palms and pale mucous membranes. Jaundice is judged at the sclera next to the iris, the hard palate, and the palms and soles, remembering that harmless subconjunctival fat can look yellow in darkly pigmented patients. Erythema and inflammation are frequently invisible in dark skin, so palpate for warmth, induration, tightness and tenderness and compare with the opposite side instead of looking for redness — relying on redness alone is exactly how early pressure injury and cellulitis are missed in patients with dark skin. Palpation uses different parts of the hand for different jobs: finger pads for texture, moisture, pulsation, masses and edema; the dorsum (back) of the hand for temperature, because it is thinner and more sensitive to heat; the ulnar surface and base of the fingers for vibration such as tactile fremitus and thrills. Light palpation depresses the tissue about 1 to 2 cm; deep palpation depresses about 4 to 5 cm and is done with one hand or with two hands stacked. Warm your hands, keep nails short, start light, and palpate tender or painful areas last.
Percussion produces sound that tells you what lies beneath. Hyperextend the middle finger of your non-dominant hand (the pleximeter), press its distal joint firmly against the skin, and keep your other fingers off the surface so they do not damp the vibration. Strike the pleximeter at the distal interphalangeal joint with the tip of your dominant middle finger (the plexor), using a quick, sharp motion from the wrist, two taps, then withdraw immediately. Learn five tones: tympany (drumlike, over the gastric bubble and intestine), resonance (hollow, over normal lung), hyperresonance (booming, over hyperinflated lung as in emphysema or pneumothorax), dullness (thudlike, over liver, spleen, a full bladder or consolidated lung), and flatness (very dull, over muscle and bone). Auscultation uses the diaphragm for high-pitched sounds (breath sounds, bowel sounds, normal S1 and S2) pressed firmly against skin, and the bell for low-pitched sounds (extra heart sounds S3 and S4, the murmur of mitral stenosis, bruits) rested lightly, because pressing the bell hard turns it into a diaphragm. Never auscultate through clothing, and clean the stethoscope with alcohol before and after every patient.
Height, weight, BMI and the numbers that matter
Measure, do not ask. Reported heights and weights are consistently wrong, and in a patient receiving weight-based medications such as heparin, vancomycin or chemotherapy, a guessed weight is a medication error waiting to happen. Weigh adults on the same scale, at the same time of day, in similar clothing, and record in kilograms because that is the unit drug calculations use. For daily weights — the single most sensitive measure of fluid status in heart failure and renal disease — weigh before breakfast, after voiding, in the same gown. A gain of 1 kg corresponds to roughly 1 litre of retained fluid; a gain of more than 1 kg (about 2 lb) in 24 hours or 2.3 kg (about 5 lb) in a week is a reportable finding in a heart failure patient.
Body mass index (BMI) is weight in kilograms divided by height in metres squared. Adult categories: underweight below 18.5; healthy weight 18.5 to 24.9; overweight 25.0 to 29.9; obesity class I 30.0 to 34.9, class II 35.0 to 39.9, class III 40.0 and above. BMI is a screening number, not a diagnosis: it does not distinguish muscle from fat, and it misclassifies very muscular patients, patients with large amounts of ascites or edema, and older adults who have lost lean mass. Pair it with waist circumference, measured at the top of the iliac crest at the end of a normal exhalation; greater than 102 cm (40 in) in men and greater than 88 cm (35 in) in non-pregnant women indicates increased cardiometabolic risk. Unintentional weight loss is significant at greater than 5 percent of body weight in one month or greater than 10 percent in six months, and it should trigger a nutrition referral and a search for cause.
Measurement changes across the lifespan. Infants and children under 24 months are measured as recumbent length on a length board with two people, weighed nude on an infant scale in kilograms, and have head circumference measured at the widest point (just above the eyebrows and around the occipital prominence) at every well visit through 24 to 36 months. All three are plotted on growth charts; a single point means little, but a child who crosses two major percentile lines downward is a concern. In children aged 2 to 20, BMI is interpreted as a percentile for age and sex: underweight below the 5th, healthy 5th to 84th, overweight 85th to 94th, obesity at or above the 95th. In pregnancy, recommended total weight gain depends on pre-pregnancy BMI: 12.5 to 18 kg (28 to 40 lb) if underweight, 11.5 to 16 kg (25 to 35 lb) if healthy weight, 7 to 11.5 kg (15 to 25 lb) if overweight, and 5 to 9 kg (11 to 20 lb) if obese. Older adults lose roughly 1 cm of height per decade after age 40 from disc compression and vertebral change, so a measured height noticeably below the patient’s historic height may reflect osteoporotic vertebral compression fractures rather than measurement error.
| Domain | Expected finding | Abnormal finding | What it may suggest |
|---|---|---|---|
| Apparent age | Appears stated age | Appears older than stated age | Chronic illness, malnutrition, substance use, chronic pain, severe stress |
| Consciousness | Alert, oriented ×4, responds appropriately | Drowsy, agitated, not oriented, slow to respond | Hypoxia, hypoglycemia, delirium, stroke, sedation, sepsis |
| Skin color | Even tone, no pallor of conjunctivae or palms | Central cyanosis, jaundice, marked pallor, flushing | Hypoxemia, liver or hemolytic disease, anemia or shock, fever |
| Breathing | Quiet, effortless, speaks full sentences | Tripod posture, accessory muscle use, nasal flaring, 3-word phrases | Asthma or COPD exacerbation, heart failure, pneumonia, PE |
| Body structure | Symmetric, proportional, nourished | Temporal and interosseous wasting, cachexia, obvious asymmetry | Malnutrition, malignancy, prior stroke, muscular dystrophy |
| Posture | Erect and relaxed, sits comfortably | Guarding, knees drawn up, rigid stillness, restless writhing | Peritonitis (still), renal or biliary colic (cannot lie still) |
| Gait | Smooth, coordinated, arms swing, steady base | Shuffling, wide-based, antalgic (limping), unsteady | Parkinson disease, cerebellar disorder, pain, high fall risk |
| Movement | Voluntary, purposeful, no tremor | Tremor, tics, picking at bedding, unilateral weakness | Parkinson disease, delirium, hepatic encephalopathy, stroke |
| Grooming | Clean, dress appropriate to weather | Unkempt, malodorous, layered clothing in warm room | Depression, dementia, homelessness, hypothyroidism, self-neglect |
| Speech | Clear, moderate pace and volume, fluent | Slurred, aphasic, pressured, very slow, hoarse | Stroke, intoxication, mania, depression, laryngeal disease |
| Affect and eye contact | Appropriate to content, culturally congruent | Flat, labile, avoids gaze, fearful glances at companion | Depression, psychosis, delirium, possible abuse or coercion |
| Odor | None remarkable | Fruity/acetone, ammonia, foul wound odor, alcohol | Diabetic ketoacidosis, uremia, infected wound, intoxication |
The general survey is a structured scan of appearance, body structure, mobility and behavior performed before you touch the patient, and the exam techniques that follow run inspection, palpation, percussion, auscultation — except the abdomen, which is inspected, auscultated, percussed, then palpated.
Section 2Pain: the Symptom Only the Patient Can Define
The ethical baseline and why pain is measured, not judged
Margo McCaffery’s working definition remains the standard of nursing practice: pain is whatever the experiencing person says it is, existing whenever they say it does. That sentence is not sentiment, it is a rule of practice. Pain is a subjective symptom with no laboratory value and no imaging study that confirms it. Your job is to measure it — consistently, with a validated tool, in the patient’s own words — and to act on the measurement. Your job is not to decide whether the number is deserved. Documented undertreatment of pain in Black and Hispanic patients, in women, in older adults, in patients with substance use disorders and in patients who cannot speak English is one of the best-established disparities in health care. It happens through exactly the mechanism you are guarding against: a clinician substitutes their own judgment for the patient’s report.
Two clinical facts protect patients from that error. First, vital signs do not confirm or refute pain. Acute pain often raises heart rate, blood pressure and respiratory rate and can cause diaphoresis and pupil dilation, but those responses adapt within hours to days. A patient with chronic pain or long-standing severe pain frequently has entirely normal vital signs. Never chart “pain rated 8 out of 10 but vital signs stable, appears comfortable” as if the second half undermines the first. Second, behavior is not a lie detector. Patients smile, joke, watch television and sleep through severe pain; sleep is a coping behavior and an exhausted patient may sleep at a pain score of 8. Chart what you observe alongside what the patient reports, without editorializing.
Use a professional interpreter for any patient with limited English proficiency — never a family member, never a child — and remember that pain expression is culturally patterned. Some patients are raised to bear pain silently and view complaint as weakness; others express pain loudly as a normal signal for help. Neither pattern tells you anything about the intensity of the pain. Ask, in the patient’s language, what word they use for pain: hurt, ache, sore, pressure, discomfort, burning, tight. Patients frequently deny “pain” and then agree readily to “pressure” or “soreness.”
PQRSTU and OLDCARTES: the actual questions
Two mnemonics organize the full symptom analysis, and either is acceptable. PQRSTU: Provocation and palliation — “What brings it on? What makes it better? What makes it worse?” Quality — “Describe the pain in your own words” (ask open-ended first; only offer descriptors such as burning, stabbing, aching, cramping if the patient cannot generate any). Region and radiation — “Point to it with one finger. Does it travel anywhere?” Severity — a number on a validated scale, both now and at its worst and best in the last 24 hours. Timing — onset, duration, frequency, constant or intermittent, and what the patient was doing when it started. Understanding and effect on you — “What do you think is causing it? What can you not do because of it? What is an acceptable level of pain for you?”
OLDCARTES covers the same ground in a different order: Onset, Location, Duration, Character, Aggravating factors, Relieving factors, Treatments tried, Effect on daily life, Severity. The two elements students most often skip are also the two that most change the plan of care: treatments already tried (including what worked at home, over-the-counter drugs, heat, ice, position, cannabis, herbal preparations and prayer) and the patient’s functional goal. “Zero out of ten” is rarely a realistic postoperative goal; “a 3, so I can get up and walk to the bathroom” is a goal you can actually work toward and evaluate against, and it is what belongs in the care plan.
Ask about pain at more than one moment. A patient at rest may report 2 out of 10 and then report 8 out of 10 on standing; incident pain, or pain with movement, is what actually determines whether the patient will ambulate, cough, deep-breathe and avoid pneumonia and venous thromboembolism. Chart both: “3/10 at rest, 8/10 with ambulation.” Also screen for the effect of pain on sleep, appetite, mood, concentration and relationships, because unrelieved pain drives delirium, depression and functional decline, and because those effects justify escalating the plan when a number alone does not persuade a prescriber.
Choosing the right pain scale
Self-report is always the gold standard, so the first question is whether the patient can self-report. If yes, choose a self-report tool matched to development, literacy and language. If no — a preverbal infant, an intubated critically ill adult, a patient with advanced dementia, a patient with a profound intellectual disability — you must use a validated observational tool, and you must not record “denies pain” for a patient who cannot answer. In that situation the sequence is: attempt self-report; look for an obvious cause of pain (surgery, fracture, wound care, positioning, a full bladder); observe behavior with a validated scale; ask a family member or regular caregiver what this person looks like when they hurt; and, when there is a plausible cause, consider an analgesic trial with reassessment of behavior.
| Tool | Who it is for | Range | How to read it |
|---|---|---|---|
| Numeric Rating Scale (NRS) 0–10 | Adults and children roughly 8 years and older who can self-report | 0–10 | 0 none; 1–3 mild; 4–6 moderate; 7–10 severe |
| Wong-Baker FACES | Children 3 years and older; adults with limited literacy or language | 0–10 in steps of 2 | Patient picks the face that matches how they feel, not how they look |
| Faces Pain Scale – Revised (FPS-R) | Children roughly 4–12 years | 0–10 | Six neutral faces, no tears or smiles; less biased toward mood |
| Verbal Descriptor Scale | Older adults, mild cognitive impairment, low numeracy | None → mild → moderate → severe → worst possible | Chart the exact word used, not a number you converted it into |
| Visual Analog Scale (VAS) | Adults and adolescents, research and clinic settings | 100 mm line | Patient marks the line; measure in millimetres from the left anchor |
| FLACC | Nonverbal children roughly 2 months to 7 years; nonverbal adults | 0–10 | Face, Legs, Activity, Cry, Consolability; each scored 0–2 |
| NIPS / CRIES | Neonates (CRIES for postoperative neonates from about 32 weeks) | NIPS 0–7; CRIES 0–10 | Physiologic plus behavioral items; neonates do feel and remember pain |
| CPOT | Critically ill adults unable to self-report, intubated or not | 0–8 | Greater than 2 indicates significant pain requiring intervention |
| Behavioral Pain Scale (BPS) | Intubated, sedated ICU adults | 3–12 | Greater than 5 indicates unacceptable pain |
| PAINAD | Advanced dementia, nonverbal older adults | 0–10 | Breathing, vocalization, facial expression, body language, consolability |
Types of pain, reassessment and opioid safety
Classify pain by mechanism, because the words the patient uses point to the treatment. Nociceptive somatic pain arises from skin, muscle, bone and joint; it is well localized and described as aching, throbbing, sharp or gnawing — a fracture, a surgical incision, a pressure injury. Nociceptive visceral pain arises from organs; it is poorly localized, deep, squeezing, cramping or pressure-like, often with nausea and diaphoresis, and it refers to predictable places — diaphragmatic irritation to the shoulder tip, cardiac ischemia to the jaw, left arm, or between the shoulder blades, biliary colic to the right scapula, renal colic from flank to groin. Neuropathic pain arises from damaged nerve tissue; it is burning, shooting, electric, stabbing, or accompanied by numbness, tingling and hypersensitivity to light touch, and it responds poorly to opioids and better to agents such as gabapentin, pregabalin and duloxetine. When a patient says “it feels like electricity” or “the sheet hurts my feet,” those exact words belong in your note because they change the prescription.
Also classify by duration. Acute pain has an identifiable cause, is expected to resolve as tissue heals, and is protective. Chronic (persistent) pain continues beyond expected healing, commonly defined as more than 3 months, is no longer protective, and reshapes sleep, mood and function. Breakthrough pain is a transient flare above otherwise controlled baseline pain and requires a short-acting rescue dose, not a change in the long-acting regimen. Cancer pain and end-of-life pain often combine all of these. And know that pain unrelieved by the ordered regimen is itself a finding to escalate — not a reason to wait for the next scheduled dose.
Reassess after every intervention. The general standard, which your facility policy will specify precisely: reassess roughly 15 to 30 minutes after an intravenous analgesic, 30 to 60 minutes after intramuscular or subcutaneous, and about 60 minutes after an oral dose. An intervention that is not reassessed is not documented care. Reassessment includes the pain score, the patient’s function (did they get up, cough, sleep), and a sedation and respiratory check for any opioid.
The single most important opioid safety concept is this: sedation precedes respiratory depression. By the time the respiratory rate falls, the patient has already been over-sedated for some time. Monitor sedation with a validated tool, most commonly the Pasero Opioid-Induced Sedation Scale (POSS): S — sleep, easy to arouse (acceptable); 1 — awake and alert (acceptable); 2 — slightly drowsy, easily aroused (acceptable, continue to monitor); 3 — frequently drowsy, arousable but drifts off to sleep during conversation (unacceptable: hold or reduce the opioid dose, typically by 25 to 50 percent per order, monitor sedation and respiratory status closely, add supplemental oxygen only per protocol, notify the prescriber); 4 — somnolent, minimal or no response to verbal or physical stimulation (unacceptable and an emergency: stop the opioid, stay with the patient, call for help and rapid response, prepare naloxone, support airway and breathing). Do not confuse POSS with the Richmond Agitation-Sedation Scale (RASS), which measures sedation and agitation for a different purpose in critical care.
Pain is measured with a validated tool matched to the patient’s ability to self-report, reassessed after every intervention, and never dismissed because vital signs are normal or the patient looks comfortable — and in any patient on opioids, rising sedation is the earliest warning, before the respiratory rate ever falls.
Section 3Mental Status and Level of Consciousness
Level of consciousness: AVPU, RASS and the Glasgow Coma Scale
Level of consciousness (LOC) is the most sensitive single indicator of neurologic change, and it is the finding that most often deteriorates first when a patient is becoming hypoxic, septic, hypoglycemic or bleeding into the head. Describe it behaviorally, not with a label. “Lethargic” means different things to different nurses; “opens eyes to loud voice, answers name correctly, falls back asleep within 10 seconds” means the same thing to everyone. The traditional descriptive ladder runs alert, lethargic (drowsy but rousable to voice), obtunded (rousable with difficulty, limited responses), stuporous (rousable only with vigorous or painful stimulus), and comatose (no rousable response). Use those words if your unit does, but always add the behavior.
AVPU is the fast field screen: Alert, responds to Voice, responds to Pain (a central stimulus — trapezius pinch, supraorbital ridge pressure or, where your facility permits it, mandibular pressure — applied only when needed and for no more than about 10 seconds; fingertip pressure on the nail bed is a peripheral stimulus — it is the standard opening stimulus for eye opening and limb response on the GCS, but because a limb can pull away by spinal reflex it cannot establish localization or, by itself, the P of AVPU, so escalate to a central stimulus before you call a patient unresponsive; the sternal rub is no longer recommended, because it bruises and abrades the skin without adding information), Unresponsive. It is quick and coarse, and it belongs in a rapid response or a first look, not in an ongoing neurologic flowsheet. RASS, the Richmond Agitation-Sedation Scale, runs from +4 (combative, violent) through 0 (alert and calm) to −5 (unarousable, no response to voice or physical stimulation); most sedated critical care patients are targeted at 0 to −2. RASS is also the level-of-consciousness input for delirium screening.
The Glasgow Coma Scale scores three independent responses and reports them separately as well as summed — document “E3 V4 M5 = GCS 12,” because the components carry information that the total hides. Always score the best response obtained, and score the best side for motor. Interpretation: 13 to 15 mild, 9 to 12 moderate, 8 or less severe brain injury — and a GCS of 8 or less is the classic threshold at which the airway is considered unprotected and intubation is anticipated (“less than 8, intubate”). The lowest possible score is 3, not 0. If a component cannot be tested — an intubated patient has no testable verbal response, a swollen orbit no testable eye opening — record it as not testable rather than guessing a 1. A drop of 2 or more points is an emergency, and so is any new asymmetry between sides.
| Component | Score | Response | How you test it |
|---|---|---|---|
| Eye opening | 4 | Spontaneous | Eyes already open on approach, before you speak |
| 3 | To sound | Opens eyes when you speak or call the name | |
| 2 | To pressure | Opens eyes to fingertip pressure on the nail bed or trapezius pinch | |
| 1 | None | No eye opening to any stimulus | |
| Verbal response | 5 | Oriented | States name, place and current month or year correctly |
| 4 | Confused | Converses in sentences but content is wrong or disoriented | |
| 3 | Words | Random or exclamatory words, no conversational exchange | |
| 2 | Sounds | Moans, groans, unintelligible sound only | |
| 1 | None | No sound at all | |
| Motor response | 6 | Obeys commands | “Squeeze my hand and let go” or “hold up two fingers” (avoid grasp reflex) |
| 5 | Localizes | Brings hand above clavicle toward a central painful stimulus | |
| 4 | Normal flexion (withdrawal) | Rapid pulling away from the stimulus, elbow flexes normally | |
| 3 | Abnormal flexion (decorticate) | Slow flexion of arms to the chest, wrists flexed, legs extended | |
| 2 | Extension (decerebrate) | Arms straight and internally rotated, wrists pronated — worse than 3 | |
| 1 | None | No motor response to pressure (exclude spinal injury and paralytics) |
Pair LOC with pupils. Normal adult pupils are round, equal and roughly 3 to 5 mm in ambient room light (2 to 6 mm is the usual range — larger in young patients and in a darkened room, smaller in older adults), and briskly reactive to light both directly and consensually — charted as PERRLA. New unequal pupils (anisocoria greater than 1 mm), a sluggish or fixed pupil, or a unilaterally “blown” dilated pupil suggests third cranial nerve compression from rising intracranial pressure and is an emergency. Pinpoint pupils suggest opioid effect or a pontine lesion. The Cushing triad — rising systolic pressure with widening pulse pressure, bradycardia and irregular respirations — is a late sign of increased intracranial pressure; if you wait for it, you have waited far too long.
The components of the mental status examination
Beyond consciousness, the mental status examination has a fixed set of components, and most of them are collected simply by conducting the health history attentively. Appearance and behavior: grooming, hygiene, dress, posture, motor activity, eye contact, cooperation. Speech: rate, volume, fluency, articulation, spontaneity — note dysarthria (slurred, a motor problem) versus aphasia (a language problem: expressive, receptive or global). Mood and affect: mood is the sustained emotional state the patient reports in their own words (“How have your spirits been?”); affect is the emotional expression you observe moment to moment. Describe affect as full, constricted, blunted, flat or labile, and state whether it is congruent with the content of what is being said.
Thought process is how thinking is organized: logical and goal-directed is expected; abnormalities include circumstantial (eventually arrives at the point after excessive detail), tangential (never arrives), flight of ideas, loose associations, perseveration (repeating the same response), neologisms and word salad. Thought content is what the patient is thinking: delusions, obsessions, phobias, and — asked directly of every patient in whom it is a possibility — thoughts of harming self or others. Perception: illusions (a misinterpreted real stimulus) and hallucinations (a perception without a stimulus). Auditory hallucinations are most characteristic of primary psychiatric illness; visual and tactile hallucinations point toward delirium, alcohol or sedative withdrawal, or a drug effect and require a medical work-up, not a psychiatric label. Insight and judgment: does the patient understand they are ill, and can they reason through a realistic problem such as “What would you do if you ran out of your blood pressure medication on a Sunday?”
Cognition is tested actively. Orientation ×4 is person, place, time and situation; ask it conversationally rather than as an interrogation (“Just to make sure I have things right — can you tell me your full name, where we are, what month it is, and what brought you in?”). Orientation is lost in a predictable order: time first, then place, then situation, and person last. Attention is the hallmark of delirium and is tested with digit span (5 to 7 digits forward is normal for an adult), reciting the months of the year backward, spelling “WORLD” backward, or serial sevens. Memory: immediate (register three unrelated words and repeat them at once), recent (recall the same three words after 3 to 5 minutes of distraction), and remote (verifiable historical detail). Language: naming, repetition, comprehension, reading, writing. Higher function: similarities (“how are an apple and an orange alike?”) and simple calculation. Avoid proverb interpretation as a stand-alone test; it is heavily influenced by culture, language and education.
Cognitive screening tools and how to use them honestly
Screening tools give you a number to compare over time, but they are not diagnoses and they perform badly when misapplied. The Mini-Cog is the most practical bedside screen: register three unrelated words, have the patient draw a clock face with all the numbers and set the hands to a specified time such as ten past eleven, then ask for the three words. Recall scores 0 to 3 (one point per word); a normal clock scores 2 and an abnormal clock scores 0, for a total of 0 to 5. A total of less than 3 — that is, 0, 1 or 2 — is a positive screen and warrants full evaluation; 3, 4 or 5 is a negative screen but does not rule out milder impairment. It takes about 3 minutes and is relatively resistant to education and language effects.
The Mini-Mental State Examination (MMSE) scores 0 to 30 across orientation, registration, attention, recall, language and construction; a score below 24 suggests cognitive impairment, though the cut point must be adjusted for education. The Montreal Cognitive Assessment (MoCA) also scores 0 to 30, is more sensitive to mild cognitive impairment and executive dysfunction, defines 26 or above as normal, and adds one point for patients with 12 or fewer years of formal education. Both require training and, in the case of the MMSE and MoCA, permission or certification depending on the version and setting.
Use these tools honestly. A patient who cannot hear you, cannot see the paper, has no glasses, is in severe pain, has just received an opioid, is being tested at 0300, or is being tested in their second language will score poorly for reasons that have nothing to do with cognition. Correct the sensory and comfort barriers first — glasses on, hearing aids in and switched on, lights up, pain treated, an interpreter present — then screen. And never chart a screening score as a diagnosis: “Mini-Cog 2 of 5” is a finding; “patient has dementia” is a medical diagnosis you do not make.
Level of consciousness is the earliest and most sensitive neurologic indicator: describe it behaviorally, score it consistently with AVPU, RASS or the three separate GCS components, and treat a two-point GCS drop, new pupil asymmetry or any new inattention as an emergency rather than a nursing observation.
Section 4Delirium, Dementia and Depression
Telling the three apart
Confusion is not a diagnosis; it is a symptom with three common explanations that are treated completely differently. Delirium is an acute, fluctuating disturbance of attention and awareness caused by a medical problem — it is a medical emergency and it is usually reversible. Dementia (major neurocognitive disorder) is a slow, progressive loss of cognitive function that is not reversible. Depression can mimic dementia so closely that it was historically called pseudodementia, and it is treatable. The single question that separates them is: what was this person like two weeks ago? Delirium is defined by acute change from baseline, which means you must find the baseline — from family, from the group home staff, from the long-term care nurse, from the prior admission’s notes. A patient who has been oriented only to person for six years is at their baseline. A patient who was balancing a checkbook last Tuesday and cannot say the month today is delirious until proven otherwise.
| Feature | Delirium | Dementia | Depression |
|---|---|---|---|
| Onset | Hours to days, identifiable | Months to years, insidious | Weeks to months |
| Course over 24 hours | Fluctuates; typically worse at night | Stable through the day; slow decline over years | Fairly stable; often worse in the morning |
| Attention | Impaired — the hallmark feature | Normal until late stages | Distractible but able to attend if engaged |
| Level of consciousness | Altered (hyperalert or drowsy) | Normal until late stages | Normal |
| Speech and thinking | Disorganized, rambling, incoherent | Word-finding difficulty, impoverished content | Slow, sparse, delayed responses |
| Typical answer to a question | Wrong, irrelevant or incoherent | Near-miss answer or confabulation | “I don’t know” with little effort |
| Memory | Recent and immediate impaired | Recent lost first, remote preserved longer | Patchy; complains of memory loss more than testing shows |
| Perception | Illusions and visual hallucinations common | Usually absent until late | Usually absent (may occur in severe depression) |
| Psychomotor activity | Hyperactive, hypoactive or mixed | Normal early | Slowed, or agitated |
| Insight | Fluctuating, often absent | Poor and worsening | Present — the patient is distressed by the deficit |
| Reversibility | Usually reversible if the cause is treated | Not reversible | Treatable |
| Nursing priority | Find and treat the cause NOW; keep safe | Support function, routine, caregiver | Screen for suicide risk; ensure safety and referral |
Screening for delirium and preventing it
Delirium affects a very large share of hospitalized older adults, is independently associated with prolonged stay, functional decline, new nursing home placement and death, and is missed most of the time. It is missed because the hypoactive subtype — quiet, withdrawn, drowsy, slow, not making trouble — is the most common and carries the worst prognosis, while nurses are trained by experience to notice the hyperactive patient who is pulling at lines. A quiet patient who is not their usual self is the one to worry about.
The Confusion Assessment Method (CAM) is the standard bedside screen and requires four features. Delirium is present when you have Feature 1 AND Feature 2, plus either Feature 3 OR Feature 4. Feature 1: acute onset or fluctuating course — is there evidence of an acute change from baseline, and does the behavior come and go? Feature 2: inattention — does the patient have difficulty focusing, become easily distracted, lose track of what is being said? Feature 3: disorganized thinking — rambling, illogical, unpredictable switching of subject. Feature 4: altered level of consciousness — anything other than alert (vigilant, lethargic, stuporous, comatose). The ICU version (CAM-ICU) uses RASS and a picture and letter task so that intubated patients can be screened without speaking. Screen at least once a shift in any at-risk patient and any time the family says “that is not how she normally is.”
When a screen is positive, look for the cause with a memory aid such as PINCH ME: Pain, Infection (urinary tract infection and pneumonia are the classics), Nutrition, Constipation and urinary retention, Hydration, Medication (benzodiazepines, anticholinergics including diphenhydramine, opioids, steroids, and abrupt withdrawal of alcohol or benzodiazepines), Environment (sensory deprivation, sleep disruption, ICU, restraints). Check a glucose and an oxygen saturation immediately — hypoglycemia and hypoxia are fast, common and correctable. Prevention is largely nursing work: get glasses and hearing aids on the patient, reorient with a visible clock and calendar, keep familiar objects and family present, mobilize early, protect sleep by clustering care and dimming lights, maintain hydration and bowel function, treat pain adequately, avoid deliriogenic drugs, and use physical restraints only as a genuine last resort because they increase agitation, injury and delirium duration.
Depression, mood and suicide risk
Screen for depression routinely, because it is common, treatable and frequently masked by physical complaints. The PHQ-2 asks about the last two weeks: little interest or pleasure in doing things, and feeling down, depressed or hopeless, each scored 0 (not at all) to 3 (nearly every day). A total of 3 or more is a positive screen and should be followed by the PHQ-9, where a score of 10 or more indicates at least moderate depression. In older adults the Geriatric Depression Scale (GDS-15) is better tolerated, and a score of 5 or more suggests depression. Note that in older adults depression more often presents as somatic complaints, memory complaints, irritability or withdrawal than as reported sadness.
Question 9 of the PHQ-9 asks about thoughts of being better off dead or of self-harm, and any positive answer requires immediate action, not a note for the next shift. Ask about suicide directly and plainly: “Are you having thoughts of killing yourself?” Asking does not plant the idea and does not increase risk — that is a myth, and the evidence contradicts it. If the answer is yes, use a structured tool such as the Columbia Suicide Severity Rating Scale (C-SSRS) to assess ideation, intent, plan, means and prior attempts. Do not leave the patient alone, remove means from the environment, initiate your facility’s suicide precautions, and notify the provider and rapid response or behavioral health team immediately. Never promise confidentiality about safety information, and never make a “no-harm contract” a substitute for supervision and a real safety plan. In the United States, patients and families can reach the Suicide and Crisis Lifeline by calling or texting 988.
Warning signs that raise concern include hopelessness, giving away possessions, putting affairs in order, a sudden unexplained calm after a period of severe depression, increased substance use, withdrawal from others, and access to firearms or a stockpile of medication. Risk is elevated in older men, in patients with a prior attempt, in those with serious or painful medical illness, in those recently discharged from psychiatric care and in those who are socially isolated. Document exactly what you asked and exactly what the patient answered, in quotation marks.
Acute, fluctuating confusion with inattention is delirium — a medical emergency with a findable cause — not dementia and not “just sundowning”; the quiet hypoactive patient is the one most often missed and most likely to die, and any positive suicide screen requires action in that moment — do not leave the patient alone, remove means, start suicide precautions and notify the provider immediately.
Section 5Documenting, Escalating and Delegating
How to chart what you found
Charting rules that apply to everything in this chapter: write objectively, quantify with numbers and named scales, quote the patient when the exact words matter, timestamp every entry, and chart what you did about the finding and what happened next. Avoid conclusions you did not test (“drug-seeking,” “non-compliant,” “appears fine”), avoid words that mean different things to different readers (“lethargic,” “good,” “tolerated well”), and never chart an assessment you did not personally perform. If a finding is abnormal and you notified someone, document the name, the time, what you reported and what was ordered.
| Assessment | Vague entry (do not write this) | Precise entry (write this) |
|---|---|---|
| General survey | “Pt looks weak and older than his age. Poor appetite.” | “0730 Adult male, appears older than stated age of 68. Sitting upright in tripod position at bedside, using accessory neck muscles, speaks in 3- to 4-word phrases. Grooming unkempt, clothing soiled. Temporal wasting noted. Ht 178 cm, Wt 71.2 kg (79.0 kg six weeks ago, 9.9 percent loss), BMI 22.5. Oral mucosa and palpebral conjunctivae pink, no pallor; no grey or ashen discoloration of tongue or nail beds. VS T 37.1 °C oral, HR 104, RR 26, BP 138/84, SpO2 89 percent on room air. Head of bed elevated, oxygen 2 L/min nasal cannula started per protocol, SpO2 94 percent at 0736. Dr. Nunez notified 0738 via SBAR.” |
| Pain | “C/o pain. Medicated. Tolerated well.” | “1410 Pt reports pain in right lower quadrant, points with one finger to McBurney point, rates 8/10 on 0–10 NRS, describes as ‘sharp, like a knife,’ onset 3 hours ago, constant, worse with movement and coughing, no radiation, not relieved by repositioning. Guarding, lies with knees flexed, grimaces on movement. HR 108, BP 146/88. Morphine 2 mg IV given per order. Provider notified 1415. 1440 Pain 3/10, resting quietly, POSS 2, RR 16, SpO2 96 percent RA.” |
| Mental status | “Pt confused this afternoon. Reoriented.” | “1500 Acute change from 0800 baseline (was oriented ×4). Now oriented to person and place only; states the year is 1998 and cannot say why she is in the hospital. Unable to recite months backward, stops after ‘December, November.’ Attention drifts mid-sentence; speech rambling. Reports seeing ‘children at the window.’ CAM positive (acute onset with fluctuation, inattention, disorganized thinking). RASS 0. Daughter at bedside states ‘this is not like her at all.’ T 38.1 °C oral, HR 110, BP 102/58, RR 24, SpO2 92 percent RA, glucose 96 mg/dL. Bed low and locked, chair alarm on, glasses and hearing aid in place, sitter requested. Dr. Nunez notified 1510.” |
Red flags: escalate now
Escalate immediately — call the provider, activate rapid response, or both — for any of the following. Any acute change in level of consciousness or mental status from the patient’s baseline, including new inattention. A GCS drop of 2 or more points, or GCS 8 or less. New pupil asymmetry, a fixed or sluggish pupil, or new unilateral weakness or facial droop. Stroke signs screened with BE-FAST — Balance loss, Eyes (vision change), Face droop, Arm drift, Speech change, Time to call — and always establish and report the last known well time, because thrombolysis and thrombectomy windows depend on it. Sudden severe headache described as the worst of the patient’s life. New chest pain, or pain described as crushing, tearing or ripping. Pain that is severe, unrelieved by the ordered regimen, or disproportionate to the physical findings — this is the classic pattern of compartment syndrome and of mesenteric ischemia. A rigid, board-like abdomen with rebound tenderness. POSS 3 or 4 in a patient receiving opioids, or a respiratory rate below 8 to 10 with sedation. Any suicidal or homicidal ideation. Cushing triad. And any patient whose family says clearly that this is not how the patient normally is.
One more escalation trigger deserves emphasis because it is entirely nursing-driven: the patient just does not look right. Deterioration frequently announces itself as a change in the general survey — a patient who was chatty is now quiet, a patient who was sitting up is now slumped, a patient whose color was good is now gray. That impression is legitimate clinical data. Convert it into specifics (respiratory rate, SpO2, work of breathing, mental status, capillary refill, urine output), then escalate.
Escalating with SBAR
SBAR gives your report a shape the receiving clinician expects, and it forces you to end with a request instead of a description. S — Situation: who you are, who the patient is, and the one-sentence problem. B — Background: the relevant history in three or four sentences, not the whole chart. A — Assessment: your vital signs, your findings, and your clinical impression — nurses are permitted and expected to say what they think is happening. R — Recommendation: what you want, stated explicitly, with a timeframe. Write the numbers down before you call and have the chart, the medication record and the last set of vitals in front of you.
A worked example. S: “Dr. Nunez, this is Amara Boyd, RN, on 4 West. I am calling about Mrs. Ellen Rowe in room 412. She has had an acute change in mental status in the last four hours.” B: “She is 81, admitted two days ago with a right hip fracture, surgery yesterday morning, history of hypertension and hypothyroidism. She has a urinary catheter placed preoperatively and she is on scheduled oxycodone. At 0800 she was alert and oriented ×4 and joking with her daughter.” A: “Right now her CAM is positive — acute onset with fluctuation, inattention, and disorganized thinking. She is oriented to person and place only, thinks the year is 1998, and reports seeing children at the window. Her temperature is 38.1 orally, heart rate 110, blood pressure 102 over 58, respirations 24, oxygen saturation 92 percent on room air, glucose 96. Her urine is cloudy and strong smelling. I think she has a urinary tract infection with delirium, and I am concerned about early sepsis.” R: “I would like you to come assess her within the next 15 minutes. I am requesting orders for blood cultures before antibiotics, a urinalysis with culture, a lactate and CBC, and an order for intravenous fluids. I would also like to discuss holding her oxycodone and switching to a scheduled non-opioid, and removing the catheter if she no longer needs it. Do you want me to activate rapid response while you are on your way?”
Delegation, supervision and scope
The rule that governs everything in this section: the registered nurse may delegate a task, but never the nursing process. Assessment, analysis and nursing diagnosis, planning, patient and family teaching, evaluation of outcomes, and any care of an unstable or unpredictable patient remain with the RN. Unlicensed assistive personnel (UAP) may collect and report data; only the RN interprets it. Apply the five rights of delegation every time: the right task, under the right circumstances, to the right person, with the right direction and communication, and with the right supervision and evaluation. And remember that delegating does not transfer accountability — you remain accountable for the outcome and for verifying that the task was done.
| May be delegated to UAP | Stays with the RN (or LPN/LVN per state scope) |
|---|---|
| Measuring and recording height, weight and routine vital signs on a stable patient | Interpreting vital signs and deciding what they mean; all vital signs on an unstable patient or immediately after a change |
| Reporting the number a patient states when asked about pain | Performing the pain assessment, choosing and scoring a pain scale, evaluating response to analgesia |
| Repositioning, ambulating a stable patient, applying heat or cold per order, providing a quiet environment | Deciding that a patient may ambulate, teaching relaxation and non-pharmacologic techniques, administering analgesics |
| Reorienting a confused patient, using familiar objects, providing 1:1 safety observation as assigned | Performing CAM, GCS, RASS, POSS, Mini-Cog or a suicide risk screen and acting on the result |
| Reporting what was observed — “she pulled at her IV,” “he did not eat lunch,” “she said 7 out of 10” | Documenting the assessment, drawing the conclusion, notifying the provider, changing the plan of care |
| Assisting with ADLs, hygiene, intake and output measurement, catheter care per policy | Initial and change-of-condition assessments, admission assessment, discharge teaching, evaluation of any outcome |
Give direction that is specific and includes the report-back threshold, because “let me know if anything changes” is not a delegation instruction. Say instead: “Please take Mr. Alvarez’s vital signs at 1000 and 1400 and tell me right away if his heart rate is over 110, his respiratory rate is over 24, his systolic is under 100, or his oxygen saturation is under 92 percent. Also tell me immediately if he seems more sleepy than he was this morning, even if the numbers look fine.” Then verify. The UAP who tells you a patient “seems more sleepy” has just handed you the earliest sign of opioid-induced sedation, and your job is to go look.
Charting turns an assessment into defensible, communicable data — specific, timed, quoted, numbered and paired with the action you took — and when a finding is a red flag you escalate with SBAR, ending with an explicit request, because assessment, teaching, evaluation and unstable patients can never be delegated away.
The chapter in one breath
Assessment begins before you touch anyone. The general survey scans four domains — physical appearance, body structure, mobility and behavior — and gives you a rapid, structured impression of how sick a patient is; height, weight, BMI and waist circumference turn that impression into numbers, and unintentional loss of more than 5 percent of body weight in a month is a finding, not a coincidence. The examination techniques that follow run inspection, palpation, percussion, auscultation, with the abdomen deliberately reversed to inspect, auscultate, percuss, palpate because touching first changes what you hear. Pain is a subjective symptom you measure rather than judge: analyze it with PQRSTU or OLDCARTES, score it with a tool matched to the patient’s ability to self-report, reassess after every intervention, and watch sedation with POSS because sedation always precedes respiratory depression. Mental status is where deterioration shows up first — describe consciousness behaviorally, score the three GCS components separately, and treat new inattention as delirium, a medical emergency with a findable cause, until proven otherwise. Then chart it precisely, escalate red flags with SBAR ending in an explicit request, and keep assessment, teaching, evaluation and unstable patients with the RN.
Words worth knowing
| Term | What it means |
|---|---|
| General survey | The structured first impression of a patient across physical appearance, body structure, mobility and behavior, begun before any touch. |
| Tripod position | Sitting leaning forward with arms braced on knees or a table to recruit accessory muscles; a visible sign of respiratory distress. |
| Body mass index (BMI) | Weight in kilograms divided by height in metres squared; a screening measure of weight for height, not a diagnosis of body composition. |
| Percussion tones | Tympany, resonance, hyperresonance, dullness and flatness — the sounds produced by striking over air, lung, hyperinflated lung, solid organ and bone. |
| Abdominal exception | The abdomen is examined inspect, auscultate, percuss, palpate, because percussion and palpation alter bowel sounds. |
| PQRSTU | Provocation and palliation, Quality, Region and radiation, Severity, Timing, Understanding and effect on you — a full symptom analysis. |
| Nociceptive pain | Pain from tissue injury: somatic pain is well localized and aching or sharp; visceral pain is deep, poorly localized, cramping and often referred. |
| Neuropathic pain | Pain from nerve damage, described as burning, shooting, electric or numb and tingling; responds poorly to opioids. |
| Breakthrough pain | A transient flare of pain above an otherwise controlled baseline, treated with a short-acting rescue dose. |
| FLACC / CPOT / PAINAD | Observational pain scales for patients who cannot self-report: young children, critically ill adults and people with advanced dementia. |
| POSS | Pasero Opioid-Induced Sedation Scale; S and 1–2 acceptable, 3 requires dose reduction and close monitoring, 4 is an emergency. |
| Level of consciousness (LOC) | Degree of alertness and responsiveness; the most sensitive early indicator of neurologic deterioration. |
| Glasgow Coma Scale (GCS) | Eye (1–4), verbal (1–5) and motor (1–6) response scores totalling 3 to 15; 8 or less indicates severe injury and an unprotected airway. |
| Decorticate vs decerebrate | Abnormal flexion toward the core (GCS motor 3) versus abnormal extension with pronation (GCS motor 2); extension is the worse finding. |
| Orientation ×4 | Awareness of person, place, time and situation; lost in the order time, place, situation, with person retained longest. |
| Affect vs mood | Affect is the emotional expression you observe moment to moment; mood is the sustained emotional state the patient reports. |
| Delirium | Acute, fluctuating disturbance of attention and awareness from a medical cause; a reversible emergency, most often missed in its hypoactive form. |
| Confusion Assessment Method (CAM) | Delirium screen requiring acute or fluctuating onset AND inattention, plus either disorganized thinking OR altered level of consciousness. |
| Cushing triad | Rising systolic pressure with widening pulse pressure, bradycardia and irregular respirations — a late sign of increased intracranial pressure. |
| SBAR | Situation, Background, Assessment, Recommendation — the structured escalation format that must end with an explicit request. |
Check yourself
Assessing Skin, Hair and Nails
The integument is the only organ you can examine in full without a single piece of technology, and it is the organ most likely to tell you something before the monitor does. Skin reports perfusion, oxygenation, hydration, hepatic function, nutrition, immune status, medication reactions and — bluntly — the quality of the nursing care a patient has received. A pressure injury is one of the few adverse events that is almost always preventable and almost always attributable, which is why regulators count them. This chapter teaches you to look with intent rather than glance: how to set up the room and the light, how to move through inspection and palpation in a fixed order so you never skip the heel or the sacrum or the skin under the oxygen tubing, how to name a lesion by its primary morphology and size, how to recognize pallor, cyanosis, jaundice and erythema in every skin tone rather than only in pale skin, how to stage a pressure injury without reverse–staging it, how to chart what you saw in words a wound nurse can act on, and when to stop charting and escalate by SBAR right now.
By the end of this chapter you can
- Describe the layers and appendages of the integumentary system and explain what each structure allows you to infer at the bedside.
- Perform a systematic skin, hair and nail examination using inspection and palpation in sequence, and state where this differs from the standard inspection, palpation, percussion, auscultation order and why the abdomen is the exception.
- Assess skin turgor, temperature, moisture, texture, capillary refill and edema, and report exact values and grades rather than adjectives.
- Differentiate primary from secondary lesions by morphology and size in centimeters, and describe configuration, distribution and blanching.
- Identify pallor, cyanosis, jaundice and erythema across the full range of skin tones by examining oral mucosa, conjunctivae, palms, soles and sclerae, and by palpating for warmth and induration.
- Recognize expected variations in newborns, children, pregnancy and older adults, including acrocyanosis, milia, striae gravidarum and senile purpura.
- Stage a pressure injury from Stage 1 through Stage 4, unstageable and deep tissue pressure injury, distinguish it from moisture–associated skin damage, and apply the Braden Scale.
- Document a skin or wound finding in precise, measurable, reproducible language and contrast it with a vague entry.
- Name the integumentary red flags that require escalation within minutes, deliver that escalation using SBAR, and state which skin–related tasks may be delegated to UAP and which may not.
Section 1The Skin as an Organ You Can Actually See
Three layers, and what each one tells you
The epidermis is avascular, thin as tissue paper over the eyelid and thick as a callus over the sole, and it turns over roughly every 28 days. Because it has no blood supply of its own, it is nourished by diffusion from the dermis below — which is exactly why a patient with poor perfusion gets shiny, fragile, slow–healing skin. The basal layer holds melanocytes. Every person has approximately the same number of melanocytes; what differs across skin tones is how much melanin those cells produce and how it is packaged. This single fact matters enormously at the bedside: it means a patient with deeply pigmented skin has the same underlying physiology of pallor, cyanosis and erythema as a patient with pale skin, but the visual signal is filtered through pigment. You do not change the assessment. You change where you look.
The dermis is the working layer: collagen and elastin for tensile strength and recoil, capillary loops for the color you see through the epidermis, sensory nerve endings for touch, pressure, temperature and pain, and the sebaceous and sweat glands. When you assess turgor you are testing dermal elastin and interstitial fluid. When you see erythema you are seeing dilated dermal capillaries. When a Stage 2 pressure injury shows a pink, moist, shiny wound bed, you are looking directly at exposed dermis — and because the dermis holds the nerve endings, that wound hurts. A wound that has destroyed the dermis entirely, on the other hand, may be strangely painless, which is a warning sign rather than a reassurance.
The subcutaneous layer (hypodermis) is adipose and connective tissue. It insulates, cushions bony prominences and stores energy. This is why the cachectic patient, the frail older adult and the critically ill patient who has lost 12 kg in three weeks are at extreme pressure–injury risk: the padding over the sacrum, ischial tuberosities, greater trochanters, heels and occiput is simply gone. When you can see visible adipose in a wound bed, you are looking at a full–thickness injury — at minimum a Stage 3.
The appendages: hair, nails and glands
Hair follicles, nails, eccrine sweat glands, apocrine glands and sebaceous glands are all epidermal derivatives, which is why systemic illness marks all of them at once. Eccrine glands are distributed nearly everywhere and are your thermoregulatory workhorse; diaphoresis in a patient who is not hot is a sympathetic surge and deserves a set of vital signs, not a towel. Apocrine glands sit in the axillae and groin, become active at puberty and produce body odor when bacteria act on their secretions. Sebaceous glands produce sebum, which keeps the stratum corneum pliable; they decline with age, which is one reason older adults develop xerosis (dry, scaling, itchy skin) and why moisturizing is a nursing intervention rather than a courtesy.
Nails are keratinized plates growing from the nail matrix under the proximal fold. Fingernails grow about 0.1 mm per day — roughly 3 mm per month, so a full fingernail replaces itself in about six months. Toenails grow at about a third of that rate and take 12 to 18 months. That growth rate is clinically useful: if you see a transverse groove (a Beau line) 6 mm from the cuticle, the systemic insult that arrested nail growth happened roughly two months ago. Hair likewise grows in cycles, and a diffuse shed two to three months after a major stressor — childbirth, sepsis, surgery, severe illness — is telogen effluvium, not disease.
Functions, and the assessment question each one implies
Teaching the functions of skin as a memorized list wastes them. Each function is really an assessment question. Barrier: is the skin intact, and where is it not? Thermoregulation: is this patient hot, cold, diaphoretic, mottled? Sensation: can this patient feel the pressure of their own heel on the mattress, or has neuropathy, spinal cord injury, sedation or an epidural taken that protective feedback away? Vitamin D synthesis, immune surveillance via Langerhans cells, fluid and electrolyte conservation, excretion, and identity — the face and hands a patient recognizes as their own. That last one is not sentimental. Disfiguring skin disease and visible wounds carry real psychological weight, and a patient who will not look at their own stoma or their own burn is telling you something you must document and address.
| Structure | What it does | What its failure looks like at the bedside |
|---|---|---|
| Epidermis / stratum corneum | Barrier to microbes, chemicals, water loss | Maceration, skin tears, fissures, portal of entry for infection |
| Melanocytes (basal layer) | Melanin production, UV protection | Hyper– or hypopigmentation after inflammation; melanoma |
| Dermal capillary loops | Perfusion, color, thermoregulation | Pallor, cyanosis, mottling, prolonged capillary refill |
| Collagen and elastin | Strength and recoil | Tenting (poor turgor), striae, senile purpura, fragile tearing skin |
| Dermal nerve endings | Touch, pressure, temperature, pain | Unfelt pressure, unnoticed burns, painless diabetic foot ulcer |
| Subcutaneous adipose | Cushion over bony prominences, insulation | Rapid pressure injury in cachexia; visible fat in a Stage 3 wound |
| Eccrine glands | Thermoregulatory sweat | Diaphoresis with shock, pain, hypoglycemia; anhidrosis with heat stroke |
| Sebaceous glands | Sebum, skin pliability | Xerosis, pruritus, cracking — especially in older adults |
| Nail matrix | Continuous nail plate growth | Beau lines, splinter hemorrhages, clubbing, koilonychia |
Melanocyte number is essentially the same in all humans; melanin output is what varies. So the physiology of cyanosis is identical in every patient — only the viewing window changes. When pigment obscures the skin surface, move to the conjunctivae, oral mucosa, tongue, palms and soles, and compare the patient to their own baseline rather than to a photograph in a textbook.
Baseline variation across the lifespan
Nothing in skin assessment makes sense until you know what is normal for the age in front of you. A newborn is covered in vernix caseosa and fine lanugo, has pinpoint white milia across the nose and chin, and commonly develops erythema toxicum neonatorum — blotchy erythematous macules with tiny central papules appearing at 24 to 72 hours and resolving on its own. Acrocyanosis (blue hands and feet with a pink trunk and pink mucous membranes) is expected in the first 24 to 48 hours of life. Central cyanosis — blue lips, tongue and oral mucosa — is never normal at any age. Congenital dermal melanocytosis, the blue–gray patches over the sacrum and buttocks seen most often in infants with darker skin tones, is a benign finding that must be documented on admission with location and size so it is never mistaken for bruising.
Older adults lose dermal thickness, elastin, subcutaneous fat, sebum and capillary density. Expect thin, dry, wrinkled, cool skin; solar lentigines (liver spots); seborrheic keratoses (the greasy, stuck–on brown plaques); cherry angiomas; and senile purpura — flat, dark purple patches on the forearms and dorsal hands from fragile vessels and thin dermis, which is not evidence of abuse by itself. Turgor is unreliable over the hand in an older adult; test over the sternum or below the clavicle instead. In pregnancy expect melasma, linea nigra, striae gravidarum, spider angiomas and palmar erythema, all driven by estrogen and increased cutaneous blood flow.
| Group | Expected findings | Do not mistake for |
|---|---|---|
| Newborn / neonate | Vernix, lanugo, milia, erythema toxicum, acrocyanosis first 24–48 h, congenital dermal melanocytosis, physiologic jaundice appearing after 24 h | Infection, bruising, abuse; jaundice in the first 24 h is pathologic — escalate |
| Infant / toddler | Diaper dermatitis, cradle cap, congenital dermal melanocytosis fading, high surface–area–to–mass ratio | Bruising or abuse — congenital dermal melanocytosis is flat, blue–gray and present from birth, and the term “mongolian spot” is obsolete. Dehydration — test turgor on the abdomen or inner thigh, not the hand |
| Child / adolescent | Acne, increased sebum and apocrine activity, tinea, traction alopecia from tight styles | Tinea capitis mistaken for dandruff; traction alopecia mistaken for a normal hairline. Patterned bruising, or any bruising in a non–ambulatory infant, is a mandated–reporter concern |
| Pregnancy | Melasma, linea nigra, striae gravidarum, spider angiomas, palmar erythema, increased sweating | Severe generalized pruritus of palms and soles with no rash suggests intrahepatic cholestasis — report same day |
| Older adult | Xerosis, thinning, decreased turgor, solar lentigines, seborrheic keratoses, senile purpura, nails that are thickened, longitudinally ridged and brittle with a dull yellow–gray hue but a plate that is still adherent and a clean subungual space, reduced axillary and pubic hair | Dehydration (use sternum), abuse (senile purpura is flat and on extensor forearms). Do not make the reverse error either — thick, yellow–brown, crumbling nails with debris beneath the plate are onychomycosis, not aging, so inspect for crumbling and subungual debris before calling a discolored toenail normal, especially in diabetes or peripheral arterial disease |
Skin is a whole organ with predictable structure, so every visible finding — color, turgor, temperature, texture, a wound bed — maps back to a specific layer or appendage, and knowing the layer tells you how deep the problem goes.
Section 2Technique: How the Examination Is Actually Performed
The order of techniques, and the one exception you must memorize
The standard sequence of physical examination is inspection, palpation, percussion, auscultation — least invasive to most, so that each technique does not corrupt the one after it. For the integument only the first two apply: you inspect, then you palpate. There is nothing to percuss and nothing to auscultate on skin, with the narrow exception of listening over a vascular lesion or graft for a bruit. Learn the four–step order anyway, because it governs every other regional examination in this book.
The exception is the abdomen, and it is the single most tested sequence variation in nursing school: inspect, auscultate, percuss, palpate. Auscultation moves to second position because percussing and palpating the abdomen mechanically stimulates the bowel and alters the frequency and character of bowel sounds. If you palpate first, whatever you hear afterward is an artifact of your own hands. Every other region — skin, thorax, heart, extremities — keeps inspection, palpation, percussion, auscultation.
Two more sequencing rules matter for skin. First, inspect and palpate region by region as you undrape, rather than exposing the whole patient at once; this preserves dignity and warmth and reduces the chance you skip a region. Second, always compare side to side. Symmetry is your control group. A warm, red, swollen left calf means far more when you have just palpated a cool, normal right calf thirty seconds earlier.
Setting up: light, warmth, gloves, ruler
Poor lighting is the most common reason a skin finding is missed. Use natural daylight if you can, or a strong daylight–balanced overhead light plus a penlight; fluorescent light adds a green cast that masks jaundice, and the amber glow of a night light will hide early erythema entirely. Use tangential lighting — shine the penlight across the surface at a low angle — to raise the shadow of a lesion that is flat under direct light and to reveal the subtle contour of a healing wound. Warm the room; a cold patient will be pale, mottled and vasoconstricted, and you will misread perfusion. Perform hand hygiene, wear gloves for any contact with non–intact skin, mucous membrane or drainage, and change gloves and repeat hand hygiene between a wound and clean skin, and between one wound and the next.
Carry a flexible centimeter ruler, not an inch ruler and not your own estimate. “Dime–sized” and “golf–ball–sized” are not measurements and cannot be trended. Carry a penlight, a magnifier if available, and know that a transparent glass slide or clear plastic pressed on a red lesion (diascopy) will tell you whether it blanches — a two–second maneuver that separates a benign erythema from a hemorrhagic rash.
A repeatable head–to–toe route
Use the same route every time so that omission becomes impossible. Scalp and behind the ears, then face, then neck and the skin folds under the chin, then anterior trunk including under the breasts and in the axillae, then arms and hands with the palms and interdigital webs, then abdomen and the panniculus folds, then perineum and the gluteal cleft, then legs, then feet including between every toe and the plantar surfaces, then log–roll and inspect the entire posterior surface: occiput, scapulae, spine, sacrum, ischial tuberosities and heels. Then inspect under and around every device — oxygen tubing over the ears and nares, the nasogastric tube against the nostril, pulse oximeter probes, the collar of a cervical brace, compression sleeves, casts, ID bands, the tubing coiled under the patient’s thigh. Device–related pressure injuries are common and they conform to the shape of the device.
On palpation you are gathering five things: temperature, moisture, texture, turgor and mobility, plus tenderness and any masses. Use the dorsum of your hand for temperature because it is more thermally sensitive than the palm, and compare bilaterally. Test turgor by gently pinching a fold of skin — over the sternum or beneath the clavicle in adults and especially in older adults, over the abdomen or inner thigh in infants. Expected: the fold returns immediately, in under 2 seconds. Tenting that persists 3 seconds or more suggests volume depletion, though it is unreliable in isolation in older adults, so pair it with mucous membranes, urine output, orthostatic vital signs and daily weight. Assess capillary refill by pressing the nail bed or a fingertip pulp for 5 seconds and releasing; expected refill is under 2 seconds in adults and children.
| What you palpate | Expected (normal) | Abnormal | What abnormal suggests |
|---|---|---|---|
| Temperature (dorsum of hand, bilateral) | Warm, equal side to side | Generalized cool; unilateral cool; localized hot | Shock or hypothermia; arterial occlusion in that limb; cellulitis, abscess or inflammation |
| Moisture | Dry with minimal dampness in folds | Diaphoresis; drenching sweats; very dry and flaking | Pain, fever, hypoglycemia, MI, sympathetic surge; dehydration, hypothyroidism, xerosis |
| Texture | Smooth, soft, even | Rough, thickened; velvety hyperpigmented axillae; paper–thin | Hypothyroidism; acanthosis nigricans and insulin resistance; steroid use, aging |
| Turgor (sternum in adults) | Recoils immediately, under 2 s | Tenting 3 s or more | Volume depletion; unreliable alone in older adults |
| Capillary refill | Under 2 s | Over 3 s with cool, mottled skin | Poor perfusion, hypovolemia, shock, arterial compromise |
| Mobility and edema | Skin lifts and returns; no pitting | Pitting graded 1+ to 4+; non–pitting brawny edema | Heart failure, hypoalbuminemia, venous insufficiency, DVT; lymphedema |
Edema, and the numbers that frame every skin finding
Grade pitting edema by pressing your thumb firmly over a bony prominence — the tibia, the medial malleolus, the dorsum of the foot, or the sacrum in a bedbound patient — for 5 seconds and then observing the indentation. The conventional scale is 1+ = about 2 mm, barely detectable, rebounds immediately; 2+ = about 4 mm, rebounds in a few seconds; 3+ = about 6 mm, deep pit, the limb looks swollen, rebound may take 10 to 30 seconds; 4+ = about 8 mm, very deep pit, gross swelling, indentation lasts more than 30 seconds. Record the grade, the depth, the location and how far up the limb it extends: “3+ pitting edema bilateral lower extremities to mid–calf” is usable data.
Skin findings are interpreted against vital signs, so know the real numbers. In a healthy adult: oral temperature 36.5 to 37.5 °C (97.7 to 99.5 °F) with an average near 37 °C (98.6 °F); pulse 60 to 100 beats per minute; respirations 12 to 20 per minute; blood pressure less than 120/80 mm Hg as normal; oxygen saturation 95 to 100 percent on room air. A hot, red, tender leg with a temperature of 38.6 °C, a heart rate of 118 and a systolic of 88 is not a dermatology consult — it is sepsis until proven otherwise.
| Age group | Heart rate (bpm) | Respirations (per min) | Typical systolic BP (mm Hg) |
|---|---|---|---|
| Newborn (0–1 month) | 100–160 | 30–60 | 60–90 |
| Infant (1–12 months) | 100–150 | 25–40 | 70–100 |
| Toddler (1–3 years) | 90–140 | 20–35 | 80–110 |
| Preschool (3–5 years) | 80–120 | 20–30 | 85–110 |
| School–age (6–12 years) | 70–110 | 18–25 | 90–120 |
| Adolescent (13–18 years) | 60–100 | 12–20 | 100–120 |
| Adult | 60–100 | 12–20 | Less than 120 (with diastolic less than 80) |
| Older adult (65+) | 60–100 | 12–20 | Often higher; widened pulse pressure common |
Two lifespan cautions. Infants and young children lose heat fast because of a high body–surface–area–to–mass ratio and thin subcutaneous fat, so uncover them briefly and re–cover them. Older adults run a lower baseline temperature and blunt the febrile response, so a reading of 37.8 °C (100 °F), or a rise of 1.1 °C (2 °F) above that person’s own baseline, can represent significant infection — a cellulitis in an 84–year–old may present as new confusion and a temperature of 37.6 °C rather than a spiking fever.
If you learn only one sequencing fact this year, learn this one: every region is inspect, palpate, percuss, auscultate — except the abdomen, which is inspect, auscultate, percuss, palpate, because palpating first stimulates the bowel and changes the very sounds you are about to listen for.
A skin examination is only as good as its setup and its route: strong tangential light, a warm room, gloves, a centimeter ruler, a fixed head–to–toe path that includes the posterior surface, between the toes and under every device, and bilateral comparison at every step.
Section 3Color, Lesions and Vascular Findings — Normal Beside Abnormal
Reading color in every skin tone
The traditional description of cyanosis as “bluish skin” and pallor as “white skin” was written for one narrow band of complexions, and students who learn it that way miss hypoxia in patients with deeply pigmented skin. Fix this by changing your viewing windows, not your standards. For cyanosis, examine the oral mucosa, tongue, lips, conjunctivae, nail beds, palms and soles; in darker skin tones cyanosis appears ashen, gray or dusky rather than blue, and the tongue and buccal mucosa are the most reliable sites because they are minimally pigmented in almost everyone. Never wait for cyanosis to diagnose hypoxia; it requires roughly 5 g/dL of deoxygenated hemoglobin, which means a severely anemic patient can be dangerously hypoxic and never turn blue at all.
For pallor, examine the conjunctivae, oral mucosa, nail beds and palmar creases. In brown skin, pallor may look yellow–brown; in black skin, ashen or gray; the underlying skin loses its normal red undertone. For jaundice, examine the sclerae (near the limbus, avoiding the peripheral fat pad, which can look yellow normally in darker–skinned patients), the hard palate under bright light, the sublingual area, and the palms and soles. For erythema, do not rely on redness at all in deeply pigmented skin: it presents as a deeper violet, purple, maroon or eggplant hue and is often invisible under artificial light. Instead palpate — compare the area to the same site on the opposite side for increased warmth, induration, firmness, boggy softness, edema and tenderness, and ask the patient whether that spot itches, burns or hurts. Warmth and induration in a patient reporting pain over a bony prominence is a Stage 1 pressure injury or early cellulitis whether or not you can see red.
| Finding | Light skin tones | Medium to deeply pigmented skin tones | Best sites to examine |
|---|---|---|---|
| Pallor | Pale, whitish, loss of pink | Ashen gray or yellow–brown; loss of red undertone | Conjunctivae, oral mucosa, nail beds, palmar creases |
| Cyanosis | Bluish lips, nail beds, skin | Ashen, gray, dusky; skin looks “dulled” | Tongue, buccal mucosa, lips, conjunctivae, palms, soles, nail beds |
| Jaundice | Yellow skin and sclerae | Yellow sclerae near the limbus; hard palate; yellow palms and soles | Sclerae, hard palate, sublingual, palms, soles |
| Erythema / inflammation | Red, blanching with pressure | Deep purple, violet, maroon, eggplant; often not visible | Palpate for warmth, induration, edema, tenderness; compare bilaterally in natural light |
| Petechiae / purpura | Red–purple, non–blanching | Look at buccal mucosa and conjunctivae, where they are visible | Oral mucosa, conjunctivae, palms, soles |
Naming the lesion: primary, secondary, size
A primary lesion arises on previously normal skin. A secondary lesion results from a change in a primary lesion — scratching, infection, healing or time. Naming the morphology and giving a measurement in centimeters is what turns your note into data. “Rash on chest” is useless. “Multiple erythematous, blanchable macules 2 to 4 mm, coalescing into patches up to 6 cm, distributed over anterior chest and both upper arms, sparing palms and soles, no mucosal involvement” lets a provider act from the hallway.
| Primary lesion | Definition and size | Common example |
|---|---|---|
| Macule | Flat, circumscribed color change, less than 1 cm | Freckle, petechia, measles rash |
| Patch | Flat color change, greater than 1 cm | Vitiligo, melasma, congenital dermal melanocytosis |
| Papule | Raised, solid, less than 1 cm | Wart, elevated nevus, acne papule |
| Plaque | Raised, flat–topped, greater than 1 cm | Psoriasis |
| Nodule | Raised, solid, deeper, 1 to 2 cm | Lipoma, rheumatoid nodule |
| Tumor | Raised, solid, greater than 2 cm | Large lipoma, neoplasm |
| Vesicle | Fluid–filled, clear, less than 1 cm | Herpes simplex, varicella, early shingles |
| Bulla | Fluid–filled, greater than 1 cm | Second–degree burn blister, bullous pemphigoid |
| Pustule | Pus–filled, any size | Impetigo, folliculitis, acne pustule |
| Wheal | Raised, edematous, transient, irregular border | Urticaria (hives), mosquito bite, allergic reaction |
| Cyst | Encapsulated, fluid or semisolid, in dermis or subcutis | Epidermoid cyst |
| Secondary lesion | What it is | Nursing significance |
|---|---|---|
| Scale | Flakes of shed stratum corneum | Psoriasis, eczema, xerosis; treat dryness |
| Crust | Dried serum, blood or pus | Honey–colored crust suggests impetigo — contagious |
| Erosion | Loss of epidermis only; moist, heals without scar | Ruptured vesicle; corresponds to a Stage 2 pressure injury depth |
| Ulcer | Loss of epidermis and dermis or deeper; scars | Pressure, arterial, venous or diabetic; measure and stage |
| Fissure | Linear crack through epidermis into dermis | Portal of entry for infection; common at heels and between toes |
| Excoriation | Self–inflicted scratch or abrasion | Confirms pruritus; risk of secondary infection |
| Lichenification | Thickened skin with exaggerated skin lines | Chronic rubbing, chronic eczema |
| Atrophy | Thinning, translucent, paper–like | Topical or systemic steroids, aging; skin–tear risk |
| Scar / keloid | Fibrous replacement; keloid extends beyond wound borders | Keloids are more common in patients with darker skin tones — counsel before elective procedures |
Configuration, distribution and blanching
Three modifiers finish the description. Configuration: annular (ring), linear, grouped or herpetiform, target/iris, serpiginous, confluent. Distribution: localized, generalized, symmetric, dermatomal, sun–exposed, intertriginous, acral (hands and feet). Distribution is diagnostic on its own — a painful vesicular eruption in a band on one side of the trunk that stops abruptly at the midline is herpes zoster, following a single dermatome; a symmetric rash on palms and soles carries an entirely different differential than the same rash on the trunk.
Blanching is the fastest and highest–yield maneuver in the entire skin examination. Press a red area with your fingertip or a clear slide for 3 seconds and release. If it whitens and refills, the redness is intravascular — blood inside dilated vessels — and the causes are inflammation, fever, flushing, drug eruption, reactive hyperemia. If it does not blanch, blood has leaked out of the vessels into the tissue, and the differential turns serious: petechiae, purpura, thrombocytopenia, vasculitis, meningococcemia, disseminated intravascular coagulation. Non–blanching erythema over a bony prominence in skin that is still intact is, by definition, a Stage 1 pressure injury — but if that non–blanchable area is deep red, maroon or purple, or is a blood–filled blister, call it a deep tissue pressure injury instead, because it is deeper and can deteriorate within hours.
| Vascular finding | Size | Blanches? | Suggests |
|---|---|---|---|
| Erythema | Variable | Yes | Inflammation, infection, fever, reactive hyperemia |
| Petechiae | Less than 3 mm | No | Thrombocytopenia, sepsis, vasculitis, straining — with fever, an emergency |
| Purpura | 3 mm to 1 cm | No | Vasculitis, coagulopathy, DIC, meningococcemia |
| Ecchymosis | Greater than 1 cm | No | Trauma, anticoagulation, fragile vessels; patterned shapes raise abuse concern |
| Hematoma | Variable, raised | No | Collected blood; measure and mark the border, trend it |
| Spider angioma | Under 2 cm with radiating legs | Yes, from the center | Normal in pregnancy; multiple ones suggest liver disease |
| Cherry angioma | 1 to 5 mm, bright red papule | Partially | Benign, increases with age |
The lesion you must not walk past: ABCDE
Nurses see more undressed skin than any other clinician, which makes you the most likely person to find a melanoma. Screen every pigmented lesion with ABCDE: Asymmetry (one half unlike the other), Border irregular, notched or blurred, Color varied within a single lesion — brown, black, red, white, blue, Diameter greater than 6 mm (about a pencil eraser), Evolving — changing in size, shape, color, elevation, or newly itching, bleeding or crusting. Add the ugly duckling rule: the mole that looks unlike all the patient’s other moles deserves attention even if it passes ABCDE. Evolution is the most important letter; a patient who says “that one has changed” is reporting a red flag.
Skin cancer is not a light–skin–only disease, and the reason patients with darker skin tones have worse melanoma survival is later detection. The most common melanoma subtype in Black patients is acral lentiginous melanoma, which appears on the palms, soles, and under the nails — sites that get skipped by clinicians who inspect only sun–exposed skin. So examine the soles and the interdigital spaces on every patient, and take a new dark longitudinal band in a nail, especially one that widens or spreads pigment onto the surrounding nail fold, as a finding to report rather than a cosmetic curiosity.
Press the red. Blanching erythema is blood inside vessels; non–blanching erythema is blood outside them. That single 3–second maneuver separates reactive hyperemia from a Stage 1 pressure injury, and a viral exanthem from meningococcemia. In deeply pigmented skin, where you cannot judge color reliably, substitute palpation: warmth, induration, boggy or firm texture, and patient–reported pain.
Describe every skin finding with four elements — morphology, size in centimeters, configuration and distribution — then test blanching, and adapt the viewing window to the patient’s skin tone rather than lowering the standard of the assessment.
Section 4Hair, Scalp and Nails
Hair and scalp
Inspect and palpate hair for distribution, quantity, texture, color and the condition of the scalp beneath it — separate the hair in several places rather than looking at the surface, and always inspect behind the ears and at the nape, where lice, seborrheic scale and device pressure hide. Expect terminal hair on the scalp, axillae and pubic area after puberty and fine vellus hair elsewhere. Expect gradual thinning, graying and reduced axillary and pubic hair in older adults.
Patterns matter more than amount. Alopecia areata produces sharply defined round bald patches with smooth underlying scalp. Traction alopecia thins the frontal and temporal hairline and follows tight braids, weaves, extensions or a ponytail worn the same way for years; it is reversible early and permanent late, which makes it a genuine teaching opportunity rather than a cosmetic aside. Telogen effluvium is a diffuse shed 2 to 3 months after childbirth, surgery, severe illness or major weight loss and regrows. Tinea capitis gives scaly patches with broken–off hairs and is contagious. Hirsutism — coarse terminal hair in a male pattern on a female patient’s face, chest or abdomen — warrants reporting for endocrine evaluation.
One hair finding is a vascular emergency in slow motion: loss of hair over the lower legs, ankles and toes together with shiny, thin, cool, pale skin and thickened nails is classic peripheral arterial disease. Pair that with dependent rubor, pallor on elevation, diminished pulses and painful, punched–out ulcers on the toes or lateral malleolus, and you have a limb at risk. Contrast it with venous insufficiency: warm limb, brown hemosiderin staining, edema, and a shallow, weepy, irregular ulcer at the medial malleolus. The two are managed in opposite directions — compression helps venous disease and can destroy an arterial limb — so the distinction is not academic.
Nails: angle, surface, color, and the bed beneath
Inspect nail shape, contour, surface, thickness, color and the surrounding folds, and palpate the nail plate for firmness and adherence to the bed. The normal nail base angle (Lovibond angle) is approximately 160 degrees; the nail is firmly adherent, smooth, and the bed is pink with capillary refill under 2 seconds. In clubbing the angle flattens and then exceeds 180 degrees, the nail base becomes spongy or floating, and the fingertip bulbs. Use the Schamroth window test: have the patient place the dorsal surfaces of two matching fingernails together. Normally a small diamond–shaped window of light appears between them; in clubbing the window disappears. Clubbing develops over months and points to chronic hypoxemia or shunting — cystic fibrosis, congenital cyanotic heart disease, bronchiectasis, interstitial lung disease, lung cancer, cirrhosis, inflammatory bowel disease.
| Expected finding | Abnormal finding | What it suggests |
|---|---|---|
| Nail base angle about 160 degrees; Schamroth window present | Angle over 180 degrees, spongy base, no window (clubbing) | Chronic hypoxia, cardiopulmonary disease, cirrhosis, IBD |
| Smooth, evenly convex plate | Concave, spoon–shaped (koilonychia) | Iron–deficiency anemia, hemochromatosis |
| Uniform surface without grooves | Transverse depressions (Beau lines) | Systemic insult that arrested nail growth — date it at about 3 mm per month |
| Pink bed, refill under 2 s | Pale or cyanotic bed; refill over 3 s | Anemia, hypoxia, hypovolemia, poor perfusion |
| Clear bed without streaks | Red–brown longitudinal splinter hemorrhages | Usually trauma; with fever and a murmur, suspect infective endocarditis |
| Plate adherent to bed | Distal separation (onycholysis) | Trauma, psoriasis, thyroid disease, fungal infection |
| Nail folds intact, non–tender | Red, swollen, tender, possibly purulent fold (paronychia) | Bacterial or candidal infection — common in diabetes and frequent hand–wetting |
| Thin, translucent plate | Thick, yellow, crumbling, debris beneath (onychomycosis) | Fungal infection; very common in older adults and diabetes |
| Even color | Proximal white with distal brown band (Terry nails); proximal white, distal red–brown (half–and–half nails) | Cirrhosis and hypoalbuminemia; chronic kidney disease |
| Longitudinal pigment bands may be normal in darker skin tones | New, single, widening dark band; pigment spreading onto the nail fold (Hutchinson sign) | Possible subungual melanoma — report for evaluation |
Infestations and the findings that change the room
Pediculosis capitis (head lice) shows as intense itching with tiny gray–white nits cemented to hair shafts, most densely behind the ears and at the nape; nits found within about 6 mm (a quarter inch) of the scalp indicate active infestation, while nits far out on the shaft are usually old. Scabies presents as relentless itching that is worst at night with thin, wavy burrows in the finger webs, flexor wrists, axillae, waistband area, and genitals; in infants it involves the palms, soles and scalp. Both findings change nursing practice immediately: initiate contact precautions per facility policy, bag linens, notify the provider and infection prevention, and treat the itching as real distress rather than a complaint. Neither is a marker of poor hygiene, and telling the patient so plainly is part of care.
Ask before you assess the nails and hair: nail polish, gel or acrylic hides cyanosis, splinter hemorrhages, onycholysis and melanonychia, and it can interfere with a pulse oximeter reading. Remove polish from at least one finger on admission, or clip the oximeter probe sideways across the finger or use the earlobe. And never assume a hair or nail practice is neglect — ask how the patient normally cares for their hair, and document the plan they agree to.
Hair and nails are slow–motion recorders of systemic health — clubbing means months of hypoxia, Beau lines date a past insult by about 3 mm per month, and hairless shiny legs with thick nails point to arterial disease long before the limb becomes an emergency.
Section 5Skin Integrity, Documentation, Red Flags and Scope
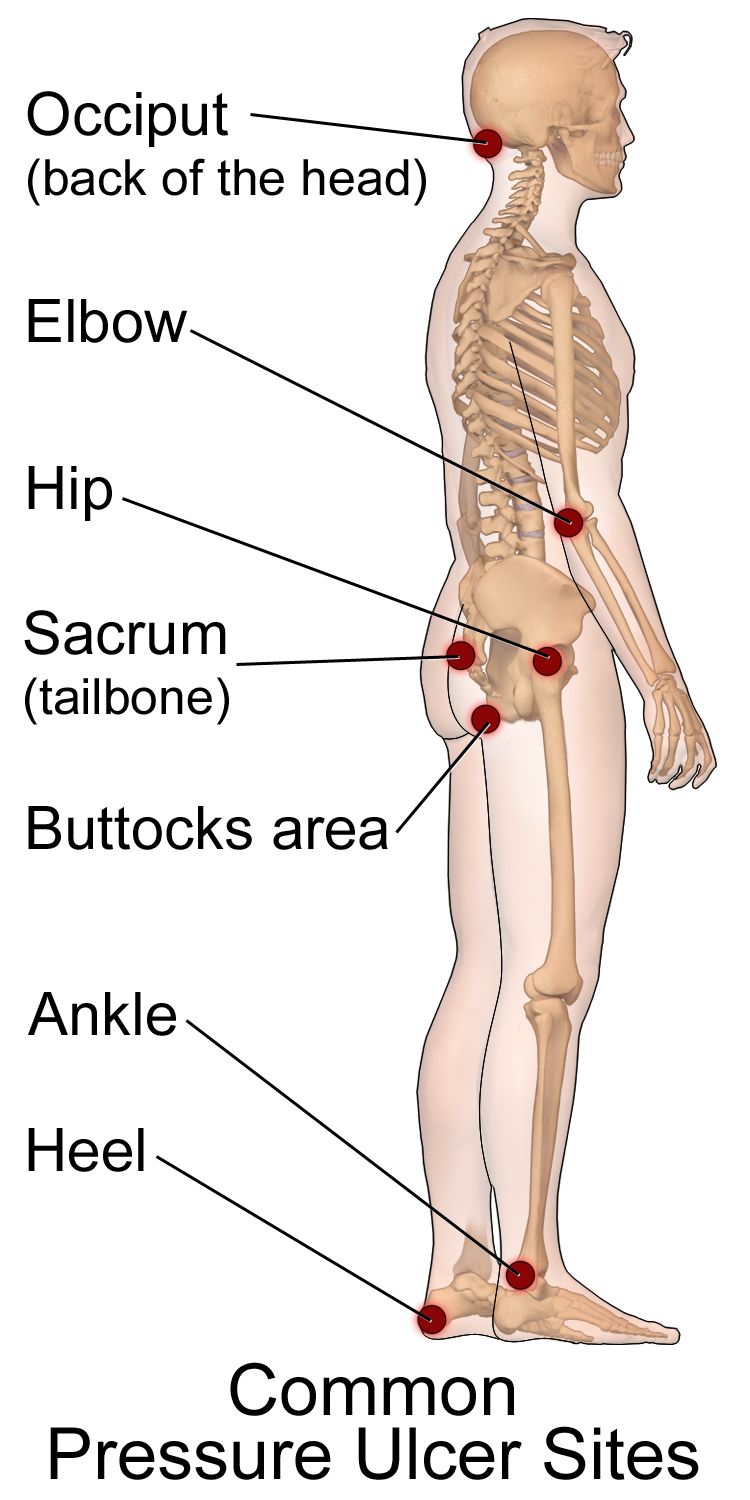
Risk, prevention and the Braden Scale
Pressure injuries develop where soft tissue is compressed between bone and a surface long enough to occlude capillary flow, and they are accelerated by shear, friction, moisture, poor nutrition and impaired sensation. Assess risk on admission, at every shift change or per facility policy, and with any change in condition, using the Braden Scale. It scores six subscales — sensory perception, moisture, activity, mobility, nutrition, and friction and shear — for a total of 6 to 23, where a lower score means higher risk. Conventional cutoffs: 19 to 23 no risk, 15 to 18 mild, 13 to 14 moderate, 10 to 12 high, 9 or below very high. A score of 18 or less should trigger a prevention bundle, and many facilities use a higher threshold for older adults and patients with darker skin tones because visual detection of early injury is less reliable.
The prevention bundle is nursing work, not an order set: reposition a bedbound patient at least every 2 hours and a chair–bound patient every 1 hour (or teach small shifts every 15 minutes if they can); use a 30–degree lateral tilt rather than direct side–lying on the trochanter; keep the head of bed at 30 degrees or less unless contraindicated, because higher elevation drives shear at the sacrum; float the heels off the bed entirely with a pillow under the calves or a heel offloading boot; use lift sheets and never drag; keep skin clean and dry with a barrier product for incontinence; optimize protein and calorie intake and involve dietitian services; and do not massage over bony prominences or reddened areas — massage over compromised tissue increases damage.
Staging — and the errors that get students in trouble
| Stage | Defining feature | Presentation in darker skin tones |
|---|---|---|
| Stage 1 | Intact skin with localized non–blanchable erythema | May not appear red at all — look for an area whose hue simply differs from the surrounding skin, and palpate for warmth, coolness, firmness, bogginess and pain. A persistent deep purple or maroon hue points to a deep tissue pressure injury rather than Stage 1 |
| Stage 2 | Partial–thickness loss with exposed dermis; pink or red, moist, shiny; may be an intact or ruptured serum–filled blister. No slough, eschar, granulation or visible adipose | Wound bed color may be less pink; periwound may look violaceous |
| Stage 3 | Full–thickness loss; adipose (fat) visible; granulation tissue and rolled edges (epibole) may be present; slough or eschar may be present but does not obscure the depth; no fascia, muscle, tendon or bone visible; undermining and tunneling may occur | Same depth criteria; assess periwound by palpation |
| Stage 4 | Full–thickness loss with exposed or directly palpable fascia, muscle, tendon, ligament, cartilage or bone; undermining and tunneling common; osteomyelitis risk | Same depth criteria |
| Unstageable | Full–thickness loss in which the base is obscured by slough or eschar; stage cannot be determined until enough is removed to see the base | Same |
| Deep tissue pressure injury (DTPI) | Intact or non–intact skin with localized, persistent non–blanchable deep red, maroon or purple discoloration, or a blood–filled blister, or epidermal separation revealing a dark wound bed | Discoloration is harder to see — palpation for a boggy, firm or temperature–different area is essential; may deteriorate rapidly |
Four rules save you. First, do not reverse–stage. A healing Stage 4 does not become a Stage 2; it is a “healing Stage 4” forever, because lost muscle and fat are replaced by scar, not by the original tissue. Second, do not stage a wound that is not a pressure injury. Staging language belongs only to pressure injuries; skin tears, surgical wounds, venous ulcers, arterial ulcers, diabetic foot ulcers and burns are described by depth and characteristics instead. Third, do not remove stable eschar on a heel. Dry, adherent, intact eschar on an ischemic heel without erythema, fluctuance, drainage or odor is a biological cover; leave it, offload the heel and report. If it becomes soft, boggy, draining or surrounded by erythema, escalate. Fourth, distinguish pressure injury from moisture–associated skin damage.
| Pressure injury | Incontinence–associated dermatitis (a form of MASD) | |
|---|---|---|
| Location | Over a bony prominence or under a device | Perineum, perianal, gluteal cleft, groin, inner thighs, skin folds — over soft tissue |
| Edges | Distinct, defined | Diffuse, irregular, poorly defined |
| Depth | May be full–thickness | Partial–thickness only; erythema, maceration, denudement |
| Cause | Pressure, shear | Prolonged moisture, urine, stool, sweat, wound exudate |
| Intervention | Offload, reposition, support surface | Cleanse, protect with barrier, manage incontinence, toileting schedule |
How to chart it
Documentation is a clinical intervention. It is how the next nurse detects deterioration, how the wound team plans, and how the record demonstrates that an injury was present on admission rather than acquired on your unit. Chart what you observed and measured, not what you concluded. Wounds are measured in centimeters as length × width × depth, with length head–to–toe and width side–to–side, and undermining or tunneling described by depth in centimeters and by clock position with 12 o’clock toward the patient’s head.
| Vague entry (do not write this) | Precise entry (write this) |
|---|---|
| “Skin okay.” | “Skin warm, dry, intact, appropriate for patient’s tone; turgor recoils immediately over sternum; no lesions, rashes or edema noted head to toe including posterior surface, heels and between toes; no redness under O2 tubing or SCD sleeves.” |
| “Bedsore on bottom, looks worse.” | “Sacrum: full–thickness open wound 4.2 cm (L) × 3.0 cm (W) × 0.8 cm (D), subcutaneous adipose visible, no exposed bone, tendon or muscle. Wound bed 70 percent red granulation, 30 percent adherent yellow slough. Undermining 1.5 cm at 3 o’clock. Moderate serosanguineous exudate, no odor. Periwound induration and warmth extending 1 cm, edges attached. Patient rates pain 6/10 with dressing change. Stage 3 pressure injury, unchanged in stage, increased in size from 3.5 × 2.6 cm on 07/28. Wound care RN notified 1410.” |
| “Rash on arms.” | “Multiple raised, erythematous, blanchable wheals 1 to 4 cm with irregular borders over bilateral forearms and anterior trunk, onset approximately 30 min after first dose of IV cefazolin. Patient reports itching 8/10. No lip or tongue swelling, no stridor, no wheeze, no dyspnea. Lungs clear. VS 37.2 °C, HR 96, RR 18, BP 128/76, SpO2 98 percent RA. Rapid response criteria reviewed; provider notified 0915.” |
| “Leg red and warm, will monitor.” | “Right lower leg: area of warmth, induration and deep violet discoloration extending from ankle to mid–calf, border marked with skin marker at 2200, 14 cm at widest point; 3 cm larger than the border marked at 1800. Tenderness rated 9/10, described as out of proportion to appearance. Two tense bullae over lateral calf. T 38.9 °C, HR 124, RR 26, BP 92/54, SpO2 94 percent RA. Rapid response called 2205.” |
Mark the border of a spreading erythema with a skin marker and write the time next to it. It costs ten seconds, it converts “seems bigger” into measurable data, and it is often the single piece of evidence that persuades a provider to come to the bedside now.
Red flags and the SBAR that follows
Some skin findings buy you hours. These do not.
| Red flag finding | Suspect | Act |
|---|---|---|
| Non–blanching petechial or purpuric rash with fever, headache, neck stiffness or altered mental status | Meningococcemia, DIC, sepsis | Rapid response NOW; droplet precautions; do not wait for the next round |
| Pain far out of proportion to appearance, rapidly advancing erythema, crepitus, dusky skin, bullae, systemic toxicity | Necrotizing soft–tissue infection | Rapid response NOW; surgical emergency; mark border, keep NPO |
| Urticaria with lip or tongue swelling, stridor, wheeze, hypotension | Anaphylaxis | Stop the infusion, call for help, epinephrine per protocol, airway, oxygen, IV fluids |
| Painful, dusky, blistering rash with mouth, eye or genital mucosal involvement; skin sloughs with lateral pressure (Nikolsky sign) | Stevens–Johnson syndrome / toxic epidermal necrolysis | Stop the suspected drug, escalate immediately; burn–center level care |
| Central cyanosis of lips, tongue or oral mucosa at any age | Hypoxemia, shunt, methemoglobinemia | Oxygen, airway assessment, SpO2, rapid response |
| Cold, pale, pulseless, painful, paresthetic, paralyzed limb (the six Ps) | Acute arterial occlusion | Emergency; do not elevate, do not apply compression, call now |
| Newborn jaundice within the first 24 hours of life | Pathologic hyperbilirubinemia, hemolysis | Notify provider immediately; bilirubin level |
| New deep tissue pressure injury or unstageable wound | Ongoing pressure damage | Offload immediately, notify provider and wound team, photograph per policy |
| Patterned bruising, burns with clear margins, injuries inconsistent with history, bruising in a non–ambulatory infant | Abuse or neglect | Ensure safety, document objectively with measurements, report as a mandated reporter |
Escalate with SBAR, which turns anxiety into a plan. Situation: “Dr. Ellis, this is Marcus Reed, RN, on 4 West. I’m calling about Mr. Alvarez in 412 — I’m concerned he has a rapidly spreading soft–tissue infection of the right leg.” Background: “He’s a 62–year–old admitted two days ago for cellulitis after a lawn–mower laceration, on IV vancomycin, with type 2 diabetes and an A1c of 9.4.” Assessment: “At 1800 the erythema was marked at the ankle. It’s now 3 cm past that mark, the skin is dusky with two tense bullae, I feel crepitus over the lateral calf, and his pain is 9 out of 10 and out of proportion to what I see. Temperature 38.9, heart rate 124, respirations 26, blood pressure 92/54 down from 132/78, SpO2 94 percent on room air.” Recommendation: “I need you to see him now. I’ve activated rapid response, held his diet, and I’m requesting surgical consult, blood cultures and fluid resuscitation orders.” Notice the recommendation is specific. “Something is wrong” is not an SBAR.
Delegation and scope
The five rights of delegation — right task, right circumstance, right person, right direction and communication, right supervision and evaluation — apply constantly in skin care, because so much skin work happens during hygiene, which is frequently delegated. The line is simple and absolute: assessment, interpretation, staging, teaching, evaluation and the care of an unstable patient stay with the RN. Unlicensed assistive personnel may observe and report what they see; they may never assess what it means. Delegating a task never delegates accountability, and the RN must give explicit direction about what to report and when.
| May be delegated to UAP | Stays with the RN (or LPN/LVN per state scope) |
|---|---|
| Bathing, perineal care, applying prescribed moisturizer or barrier cream to intact skin | The head–to–toe skin assessment itself and its interpretation |
| Turning and repositioning on a set schedule; floating heels; applying prescribed offloading boots | Braden scoring, pressure–injury staging, wound bed assessment and measurement |
| Reporting observations — “there is redness on his tailbone,” “the skin under the oxygen tubing looks sore” | Deciding what that redness means and what the plan of care becomes |
| Keeping linens dry and wrinkle–free; managing incontinence care | Patient and family teaching about prevention, nutrition and skin self–examination |
| Measuring and recording intake and output, weights, and routine vital signs on a stable patient | Any care of an unstable patient, first assessments, and evaluation of whether interventions worked |
| Assisting with ambulation and range of motion as directed | Sterile dressing changes and wound irrigation (per facility policy and state scope; never UAP) |
The bath is the assessment. The single highest–yield habit in skin care is to be present during hygiene — that is when the sacrum, the gluteal cleft, the heels, the skin folds and the areas under devices are actually visible. If you delegate the bath and never look, you have delegated your assessment, and you cannot.
Prevention, correct staging, precise measurable charting, immediate SBAR escalation for the findings that kill, and a hard line between what a UAP may observe and what only an RN may assess — those five behaviors are what make skin care nursing rather than housekeeping.
The chapter in one breath
Skin, hair and nails are examined by inspection and palpation, in that order, under strong tangential light in a warm room, along a fixed head–to–toe route that includes the posterior surface, between the toes, the skin folds and under every device — and you learn the full inspect, palpate, percuss, auscultate sequence here because every region follows it except the abdomen, where auscultation moves second so palpation does not alter bowel sounds. Palpate for temperature with the dorsum of your hand, moisture, texture, turgor (sternum in adults, immediate recoil, tenting at 3 seconds or more), capillary refill under 2 seconds, and pitting edema graded 1+ through 4+. Name lesions by morphology and size in centimeters, add configuration and distribution, and press the redness: blanching means blood inside vessels, non–blanching means blood outside them. Assess color across skin tones at the conjunctivae, oral mucosa, sclerae, palms and soles, and substitute palpation for color when pigment obscures erythema. Know the Braden Scale, the four pressure–injury stages plus unstageable and deep tissue injury, and never reverse–stage. Chart measurements, not impressions. Escalate purpura with fever, pain out of proportion, mucosal sloughing, central cyanosis and a pulseless limb with a specific SBAR recommendation. UAP observe and report; RNs assess.
Words worth knowing
| Term | What it means |
|---|---|
| Integument | The skin and its appendages — hair, nails, and sebaceous, eccrine and apocrine glands; the body’s largest organ. |
| Turgor | Skin elasticity, tested by pinching a fold over the sternum in adults; immediate recoil is expected, tenting of 3 seconds or more suggests volume depletion. |
| Capillary refill | Time for color to return to a compressed nail bed or fingertip; expected under 2 seconds in adults and children. |
| Blanching | Whitening of erythema under pressure, indicating blood is still inside dilated vessels; non–blanching means blood has leaked into tissue. |
| Cyanosis | Dusky, gray or blue discoloration from deoxygenated hemoglobin; central cyanosis of lips, tongue and mucosa is never normal. |
| Acrocyanosis | Blue hands and feet with a pink trunk and pink mucosa, expected in a newborn during the first 24 to 48 hours. |
| Jaundice | Yellow discoloration from bilirubin; best seen in the sclerae near the limbus, the hard palate, and the palms and soles. |
| Macule / papule | A flat color change under 1 cm / a raised solid lesion under 1 cm; the two most commonly confused primary lesions. |
| Vesicle / bulla | A fluid–filled lesion under 1 cm / over 1 cm. |
| Wheal | A transient, raised, edematous lesion with an irregular border — a hive. |
| Petechiae / purpura / ecchymosis | Non–blanching hemorrhage into skin: under 3 mm / 3 mm to 1 cm / over 1 cm. |
| Nikolsky sign | Sloughing of the epidermis with gentle lateral pressure; a hallmark of Stevens–Johnson syndrome and toxic epidermal necrolysis. |
| ABCDE | Melanoma screening: Asymmetry, Border irregularity, Color variation, Diameter over 6 mm, Evolving. |
| Clubbing | Loss of the normal 160–degree nail base angle to more than 180 degrees with a spongy nail base; indicates chronic hypoxia. |
| Beau lines | Transverse grooves in the nail from a systemic insult that halted nail growth; dated at roughly 3 mm per month of fingernail growth. |
| Koilonychia | Spoon–shaped, concave nails classically associated with iron–deficiency anemia. |
| Braden Scale | Pressure–injury risk tool scoring six subscales for a total of 6 to 23; lower is higher risk, and 18 or less triggers prevention. |
| Deep tissue pressure injury | Persistent non–blanchable deep red, maroon or purple discoloration, or a blood–filled blister, over intact or non–intact skin. |
| Unstageable | A full–thickness pressure injury whose base is obscured by slough or eschar, so depth and stage cannot yet be determined. |
| SBAR | Situation, Background, Assessment, Recommendation — the structured format for escalating a finding, ending in a specific request. |
Check yourself
Assessing Head, Neck, Eyes, Ears, Nose and Throat
Everything above the clavicles is crowded, and that is exactly why it matters. In a space the size of your two fists sit the airway, four of the great sensory organs, ten lymph node chains, the thyroid, the carotids and eleven of the twelve cranial nerves. A student who learns this region as a list of parts will chart “HEENT within normal limits” and move on. A nurse who learns it as a system will notice that the uvula has shifted to the left, that one pupil is a millimetre larger than it was two hours ago, that the node above the clavicle is hard and will not move, or that a patient who was hoarse this morning is now making noise on inspiration. Those four findings are, in order, a peritonsillar abscess, a herniating brain, a probable malignancy and an airway that is closing. This chapter teaches the technique first — hands, light, sequence — then the findings, then the numbers, then the words you write and the escalation you call.
By the end of this chapter you can
- Perform a systematic head, neck and HEENT examination in the correct order — inspection, palpation, percussion, auscultation — and state the one region where that order changes.
- Palpate the ten cervical lymph node chains and distinguish a reactive node from a node that suggests malignancy, including the supraclavicular (Virchow) node.
- Examine the thyroid by anterior and posterior approach, auscultate for a thyroid bruit, and confirm the trachea is midline.
- Measure distance and near visual acuity, test visual fields by confrontation, assess the six cardinal fields of gaze, and document PERRLA accurately with pupil size in millimetres.
- Perform otoscopy with correct pinna traction for age, identify the normal tympanic membrane landmarks, and interpret the whispered voice, Weber and Rinne tests.
- Inspect the nose, sinuses, oral mucosa, tongue and pharynx, grade tonsils 1+ through 4+, and identify leukoplakia and oral candidiasis.
- State expected vital-sign values for adults and across the lifespan, and describe how HEENT findings differ in infants, children, pregnancy and older adults.
- Assess cyanosis, jaundice, pallor and erythema in patients of every skin tone using oral mucosa, conjunctivae, sclera and palms and soles.
- Recognize HEENT red flags that require escalation now, communicate them using SBAR, and correctly delegate — or refuse to delegate — tasks to unlicensed assistive personnel.
Section 1The Head, Face and Neck
The order of the exam, and the one place it changes
Physical assessment has a fixed order: inspection, palpation, percussion, auscultation. You look before you touch, you touch before you tap, and you tap before you listen. The reason is not tradition. Looking costs nothing and biases nothing; touching a tender area first makes the patient guard, tense and stop cooperating; and percussion sets tissue moving in ways that can change what you hear afterward. In the head and neck you will use inspection and palpation constantly, percussion almost never, and auscultation in exactly two places — over the carotid arteries and over an enlarged thyroid.
There is one region of the body where this order is deliberately broken. The abdomen is the exception: inspect, then AUSCULTATE, then percuss, then palpate. Bowel sounds are produced by peristalsis, and pressing on the abdomen mechanically stimulates or suppresses that peristalsis. If you palpate first, the bowel sounds you then auscultate are sounds you created, not sounds the patient had. Memorize the exception now, because it is the single most commonly missed sequencing item on licensure examinations and the single most commonly botched sequence at the bedside. Everywhere else — head, neck, thorax, extremities — the standard order holds.
Before you touch the patient, set the stage. Perform hand hygiene, introduce yourself, use two identifiers, explain what you are about to do, and position the patient sitting upright with their head at your eye level. Sitting matters: it lets you compare both sides of the face and neck simultaneously, and symmetry is the single most powerful assessment tool you have in this region. Almost every abnormality above the clavicles announces itself first as an asymmetry.
Skull, face and the temporomandibular joint
Inspect the skull for size, shape and symmetry. The expected finding is normocephalic and atraumatic — a rounded, symmetric skull with no depressions, bossing or lesions, and no evidence of injury. Then palpate the entire scalp with the pads of your fingers in small circles, front to back, feeling for tenderness, masses, depressions and step-offs in the bone. Part the hair to look at the scalp itself; you are checking for lesions, scaling, lice and, in an older adult who has fallen, a boggy hematoma hidden under thick hair. Palpate the temporal arteries just anterior to each ear: they should be smooth, non-tender and equally pulsatile.
Inspect the face at rest and in motion. At rest, look at the palpebral fissures, nasolabial folds and mouth corners for symmetry. Then test the muscles of facial expression, which is cranial nerve VII (facial): ask the patient to raise their eyebrows, close their eyes tightly while you try to open them, smile, show their teeth and puff out their cheeks. A drooping mouth corner with an intact forehead points to a central lesion such as a stroke; a droop that includes the forehead on the same side points to a peripheral seventh nerve palsy such as Bell palsy. That distinction — forehead spared or not — changes the entire escalation pathway, and you can make it in eight seconds. While you are there, test cranial nerve V (trigeminal): palpate the masseter and temporalis muscles while the patient clenches, and check light touch sensation on the forehead, cheek and jaw bilaterally.
Palpate the temporomandibular joint by placing your index fingertips just anterior to the tragus of each ear and asking the patient to open and close the mouth slowly. You should feel a smooth, symmetric glide. The mouth should open 3 to 6 cm between the incisors, roughly the width of three of the patient’s own fingers held vertically. Audible clicking is common and by itself not alarming. Crepitus, pain, locking, or an opening of less than 3 cm is abnormal. An inability to open the mouth at all — trismus — in a patient with a sore throat is not a dental problem; it is a deep neck space infection until proven otherwise, and it belongs in Section 4 and in your escalation list.
Lymph nodes: the ten chains and what a bad node feels like
Palpate the cervical nodes using the pads of your index and middle fingers, both hands at once, moving the skin over the underlying tissue in gentle circles. Use light pressure — heavy pressure pushes a small node out of your way and you will miss it. Work in a fixed order every time so you never skip a chain: preauricular (in front of the ear), posterior auricular (over the mastoid), occipital (base of the skull), tonsillar (angle of the mandible), submandibular (halfway between the angle and the tip of the jaw), submental (behind the tip of the chin, one hand), superficial cervical (over the sternocleidomastoid), deep cervical chain (under the sternocleidomastoid — hook your fingers around the muscle and ask the patient to tilt the head toward the side you are examining to relax it), posterior cervical (along the anterior edge of the trapezius) and supraclavicular (in the hollow above the clavicle; ask the patient to shrug and then relax, and have them take a deep breath and hold it to bring a deep node up under your finger).
Most healthy adults have no palpable nodes at all, and many have a few small nodes that are less than 1 cm, soft, mobile, discrete and non-tender. When you find a node, describe six things: location, size in centimetres, shape, consistency, mobility and tenderness. Those six words separate a viral pharyngitis from a lymphoma. The pattern that reassures is tender, warm, soft, mobile and bilateral — that is inflammation, and it usually has an obvious source such as a throat, ear or scalp infection. The pattern that worries is hard, fixed, matted, painless and unilateral — that is how malignancy presents, and painlessness is a feature, not a reassurance.
Two rules override everything else. First, a palpable supraclavicular node is abnormal at any size, in any patient, at any age. The left supraclavicular node — the Virchow node — drains the thoracic duct and can be the first sign of a gastric, pancreatic, esophageal or pulmonary malignancy. Second, size is not the only trigger for referral. Any node that is hard, fixed, matted or painless needs a provider evaluation at any size; so does any node that has been enlarging for more than two to four weeks without an infectious explanation, any node larger than 1 cm that does not settle as the infection settles, and any node larger than 2 cm regardless of how it feels. Do not wait for a suspicious node to reach 2 cm before you report it.
| Finding | Expected | Abnormal | What the abnormal suggests |
|---|---|---|---|
| Skull | Normocephalic, atraumatic, no tenderness | Depression, step-off, boggy area, focal tenderness | Fracture, hematoma; in an older adult, an unwitnessed fall |
| Temporal artery | Smooth, non-tender, equal pulses | Thickened, nodular, tender artery in a patient over 50 | Giant cell arteritis — vision-threatening, urgent |
| Face (CN VII) | Symmetric at rest and with movement | Droop with forehead SPARED | Central lesion — suspect stroke, activate stroke pathway |
| Face (CN VII) | Symmetric at rest and with movement | Droop INCLUDING forehead, one side | Peripheral CN VII palsy (Bell palsy); eye needs protection |
| TMJ | Smooth glide, opens 3–6 cm, painless | Crepitus, pain, locking, opening <3 cm | TMJ disorder; trismus with sore throat suggests abscess |
| Cervical nodes | Non-palpable, or <1 cm, soft, mobile, non-tender | Tender, warm, mobile, bilateral | Reactive — infection somewhere in the drainage field |
| Cervical nodes | Non-palpable, or <1 cm, soft, mobile, non-tender | Hard, fixed, matted, painless, unilateral — at ANY size | Malignancy until proven otherwise |
| Supraclavicular node | Never palpable | Any palpable node | Thoracic or abdominal malignancy; always significant |
| Neck ROM | Flexion 45°, extension 55°, lateral bend 40°, rotation 70° | Nuchal rigidity, pain on passive flexion | Meningeal irritation — with fever and headache, emergency |
Thyroid, trachea and carotids
Confirm the trachea is midline before anything else. Place your index finger in the suprasternal notch and slip it gently to each side of the trachea; the space between the trachea and the sternocleidomastoid should be equal on both sides. A deviated trachea is never a minor finding. Air or fluid under pressure pushes the trachea away from the affected side — that is tension pneumothorax and large pleural effusion. Loss of lung volume pulls the trachea toward the affected side — that is atelectasis, fibrosis and pneumonectomy. A patient who is short of breath with a trachea deviated away from the side with absent breath sounds is a rapid-response call, not a documentation entry.
Now the thyroid. The isthmus lies across the second and third tracheal rings, with a lobe curving back on either side. Inspect first: with the patient’s neck slightly extended, hand them a cup of water and watch them swallow. Thyroid tissue rises with the swallow; lymph nodes and most other neck masses do not. That single manoeuvre — watch it move with the swallow — is the most useful thing you will do at the neck. For the posterior approach, stand behind the seated patient, place the fingers of both hands on the neck with your index fingers just below the cricoid cartilage, ask the patient to flex the neck slightly forward and tilt it toward the side you are palpating (this relaxes the sternocleidomastoid), displace the trachea gently toward that side with the opposite hand, and ask for a sip of water. For the anterior approach, stand in front, use the same displacement and swallow, and palpate with your thumbs. Use whichever you can do reliably; consistency beats elegance.
A normal thyroid is often not palpable at all. When it is, the lobes feel smooth, firm, non-tender and roughly the size of the distal phalanx of the patient’s thumb. Enlargement is a goiter. If you feel any enlargement, place the bell of your stethoscope over each lobe and ask the patient to hold their breath. A soft blowing swishing sound is a thyroid bruit, and it means increased vascularity — classically hyperthyroidism and Graves disease. Palpate gently; vigorous manipulation of a hyperactive gland is avoided. Finally, auscultate each carotid with the bell while the patient holds their breath, listening for a bruit. Never palpate both carotid arteries at the same time and never massage the carotid sinus; you can drop the heart rate and the cerebral perfusion of the patient in front of you.
Assess the head and neck by inspection then palpation, comparing both sides at once, and treat a deviated trachea, a hard fixed node or any palpable supraclavicular node as findings that leave the room with you.
Section 2Assessing the Eyes
Visual acuity and visual fields
Visual acuity is the vital sign of the eye, and like any vital sign it is measured, not estimated. Use a Snellen chart at 20 feet (6 metres) in good light. Test each eye separately with the other eye covered by an occluder or the patient’s palm — never by their fingers, because patients peek — then test both eyes together. If the patient wears glasses or contacts for distance, leave them on and chart the result as corrected. Record the smallest line the patient reads correctly, plus the number of letters missed on that line: 20/30 − 1 means they read the 20/30 line and missed one letter. The numerator is your testing distance; the denominator is the distance at which a person with normal vision could read that line. So 20/20 is expected adult acuity, and 20/40 means your patient must stand at 20 feet to see what a normal eye sees at 40 feet. Legal blindness in the United States is 20/200 or worse in the better eye with best correction. If a patient cannot read the largest letter, move them closer and record the distance; if they still cannot, test counting fingers, then hand motion, then light perception, in that order.
Test near vision with a handheld Jaeger card held at 14 inches (35 cm); normal is J1 or 14/14. Difficulty with near vision beginning in the forties is presbyopia, a normal age-related stiffening of the lens, and it is the reason your fifty-year-old patient holds the discharge instructions at arm’s length. That is a teaching moment about large-print materials, not a pathology.
Screen peripheral vision by confrontation. Sit facing the patient at eye level about 60 cm (2 feet) away. Cover your right eye and have them cover their left, so you and the patient are looking directly at one another with the opposite eyes. Keep your eyes locked, then bring a wiggling finger in from the far periphery in each of four quadrants, midway between you and the patient, and ask them to say “now” the moment they see it. Because you are the control, you should see the finger at the same instant. Normal fields extend approximately 50° superiorly, 60° nasally, 70° inferiorly and 90° temporally. A quadrant the patient consistently misses is a field cut and needs a provider — and it also needs a safety plan, because a patient with a left field cut will walk into the left side of the doorway and will not see the food on the left half of the tray.
The external eye, the pupils and extraocular movement
Inspect the eyebrows, lids and lashes for symmetry, ptosis, edema, lesions and lid margin inflammation. The upper lid normally covers the top 1 to 2 mm of the iris; the sclera should not be visible above the iris. Inspect the conjunctivae by having the patient look up while you pull the lower lid down: the palpebral conjunctiva should be pink and moist, and the bulbar conjunctiva clear with fine visible vessels. Sclera should be white. In patients with darker skin, small tan or brown melanin deposits are commonly seen in the sclera near the limbus and are a normal variant — do not mistake them for jaundice. When you are screening for jaundice, look at the sclera immediately adjacent to the iris, at the hard palate and under the tongue; the peripheral sclera can carry a yellowish tint from fat and carotene in perfectly healthy people.
Assess the cornea by shining a penlight obliquely across it; it should be smooth, clear and glossy, with no cloudiness or abrasion. A thin greyish-white ring around the outer iris in an adult over 60 is arcus senilis and is a normal aging finding; the same ring in a patient under 40 warrants a lipid evaluation. Test the corneal light reflex by shining a penlight at the bridge of the nose from about 30 cm: the reflection should land on exactly the same spot of each cornea. Asymmetry means the eyes are not aligned.
Pupils are round, equal and, in normal room light, 3 to 5 mm in diameter (the full normal range is roughly 2 to 6 mm depending on light and age). Chart the actual millimetre size using the gauge printed on your penlight or pupil card — “pupils equal” is not data. Darken the room, bring the light in from the side, and check four things: direct constriction of the lit eye, consensual constriction of the other eye, then accommodation and convergence as the patient shifts gaze from a distant object to your finger 10 cm from their nose. That is PERRLA: pupils equal, round, reactive to light and accommodation. About one in five people has a benign difference of up to 1 mm between pupils that is stable over time — physiologic anisocoria. What is never benign is a new difference, especially a unilateral dilated pupil that reacts sluggishly or not at all in a patient with a declining level of consciousness. That is third nerve compression from an expanding intracranial mass, and it is a call to the rapid response team while you are still standing at the bedside.
Assess extraocular movement through the six cardinal fields of gaze, which test cranial nerves III, IV and VI together. Hold your finger about 30 cm away, ask the patient to hold their head still and follow with their eyes only, and move slowly through an H pattern — lateral, up-and-lateral, down-and-lateral on each side. Both eyes should move together, smoothly and fully, with parallel alignment. A few beats of nystagmus at extreme lateral gaze are normal; sustained nystagmus in any other position is not.
| Pupil finding | Description | Most likely cause | Nursing action |
|---|---|---|---|
| Expected | 3–5 mm, equal, brisk direct and consensual response | Normal | Chart size in mm and reactivity |
| Pinpoint (1–2 mm), bilateral | Constricted, may be minimally reactive | Opioid effect; pontine hemorrhage | Assess respirations and sedation; opioid effect needs naloxone consideration and provider notification |
| Unilateral dilated, fixed | One pupil >6 mm, non-reactive, with decreasing level of consciousness | CN III compression — uncal herniation | EMERGENCY. Rapid response now; do not wait for the next round |
| Bilateral fixed and dilated | Both >6 mm, no reaction | Severe hypoxic or anoxic brain injury; anticholinergics; late herniation | EMERGENCY; assess airway, breathing, circulation and call |
| Mid-dilated, fixed, oval; painful red eye | Hard globe, halos around lights, nausea and vomiting | Acute angle-closure glaucoma | EMERGENCY ophthalmology referral; vision is lost in hours |
| Stable unequal pupils, both reactive | Difference up to 1 mm, unchanged over time, patient alert | Physiologic anisocoria | Document the baseline so the next nurse does not panic |
The internal eye, the red reflex and eye emergencies
The funduscopic examination is performed by advanced practice providers in most settings, but you need to understand it because you will assist with it, position for it and read the results. Darken the room. Hold the ophthalmoscope in your right hand, use your right eye, and examine the patient’s right eye; then switch everything for the left. Start about 25 cm away and 15° lateral to the patient’s line of sight, find the orange glow of the red reflex, then follow it in to within 3 to 5 cm. The optic disc is creamy yellow-orange with sharp margins and a cup that occupies no more than about half of the disc diameter. Arterioles are lighter and narrower than venules, in roughly a 2:3 ratio. The macula lies about two disc diameters temporal to the disc. Blurred disc margins — papilledema — indicate raised intracranial pressure.
The red reflex is the finding nurses genuinely own, because it is checked at every newborn and well-child assessment. It should be present, equal and symmetric in both eyes. A white reflex — leukocoria — is an urgent referral: retinoblastoma, congenital cataract and retinopathy of prematurity all present this way, and retinoblastoma is a childhood cancer where time to treatment determines whether the child keeps the eye and the life. If a parent shows you a phone photo in which one of their baby’s eyes glows white while the other glows red, you escalate that photo.
Three ocular situations demand action before assessment. A chemical splash is irrigated immediately — do not stop to test acuity, do not look for the bottle first. Remove contact lenses, hold the lids open and irrigate with normal saline or lactated Ringer solution for at least 15 to 20 minutes, or until the conjunctival pH is 7.0 to 7.4, directing flow from the inner to the outer canthus so you do not wash the chemical into the other eye. Alkali burns penetrate deeper and irrigate longer than acid. Never attempt to neutralize a chemical with another chemical. An impaled foreign body is never removed at the bedside: stabilize it, shield both eyes to stop conjugate movement, keep the patient still and call. And sudden painless loss of vision in one eye — a curtain coming down, a shower of floaters, a shade closing — is a retinal artery occlusion or a retinal detachment and is a same-hour emergency.
Visual acuity is measured with a chart and charted as a fraction, pupils are charted in millimetres, and a new unilateral fixed dilated pupil, a white red reflex, a chemical splash or sudden painless vision loss are all escalations rather than assessments.
Section 3Assessing the Ears and Hearing
The external ear: inspection and the two-second diagnosis
Inspect both auricles for size, shape, symmetry, position and skin condition. The top of the auricle should meet an imaginary line drawn from the outer canthus of the eye to the occiput, and the auricle should sit within 10° of vertical. Low-set or rotated ears in an infant are associated with congenital renal and chromosomal anomalies and are reported, not just noted. Inspect the external canal opening for discharge, redness, swelling and cerumen. Note the colour and character of any discharge: purulent drainage suggests infection, and clear or blood-tinged watery drainage after head trauma is cerebrospinal fluid until proven otherwise.
Then palpate. Move the auricle up and down, press the tragus inward, and press over the mastoid process. This takes two seconds and does real diagnostic work. Pain when you move the pinna or press the tragus points to otitis externa, an infection of the canal. Ear pain with no tenderness on external manipulation points to otitis media, behind the drum. And tenderness, redness or swelling over the mastoid, especially with an auricle that is pushed forward and outward, is mastoiditis — a complication that can extend intracranially and needs urgent evaluation.
Otoscopy: how to hold it, what you should see
Choose the largest speculum that will fit the canal comfortably; a speculum that is too small gives you a keyhole view and is more likely to touch the sensitive canal wall. Hold the otoscope like a pencil, upside down, braced against the patient’s head with the ulnar side of your hand, so that if the patient moves suddenly your hand moves with them and the speculum does not lacerate the canal. Straighten the canal by pulling the auricle: up and back for adults and children 3 years and older, down and back for infants and children under 3, because their canal points upward. Insert slowly, downward and forward, about 1 to 1.5 cm in an adult, watching your path the whole way in.
The normal tympanic membrane is pearly grey, translucent, intact and slightly concave. You should identify the cone of light — the triangular light reflex that points anteroinferiorly, at roughly 5 o’clock in the right ear and 7 o’clock in the left — along with the umbo, the handle of the malleus and the short process. On pneumatic insufflation the membrane moves. Cerumen is normal and protective and does not need removal unless it blocks the view or the hearing; when irrigation is ordered, it is contraindicated if there is any suspicion of perforation, tympanostomy tubes, current infection or a history of ear surgery.
In children, the ear examination and the throat examination are performed last, after everything that requires cooperation, because both are intrusive and both end cooperation. Infants and toddlers have shorter, wider, more horizontally oriented eustachian tubes, which is why otitis media peaks between 6 and 24 months and why a bottle-propped supine feeding raises the risk.
| Tympanic membrane appearance | Interpretation | Typical accompanying findings |
|---|---|---|
| Pearly grey, translucent, cone of light intact, mobile | Expected | Hearing intact, no pain |
| Red, bulging, landmarks obscured, immobile | Acute otitis media | Fever, ear pain, recent upper respiratory infection, irritable infant pulling at ear |
| Amber or yellow, air-fluid level or bubbles visible | Otitis media with effusion (serous) | Muffled hearing, popping, usually afebrile |
| Retracted, landmarks unusually prominent | Eustachian tube dysfunction, negative middle-ear pressure | Fullness, mild hearing loss |
| Dense chalky white patches | Tympanosclerosis — old scarring | Usually asymptomatic; history of repeated infections or tubes |
| Visible dark perforation or purulent drainage in canal | Perforated tympanic membrane | Sudden relief of pain, drainage; NO irrigation, NO drops without an order |
| Blood behind an intact drum (hemotympanum) | Basilar skull fracture until proven otherwise | Head trauma, Battle sign, raccoon eyes — escalate now |
Testing hearing: whisper, Weber and Rinne
Start with the simplest and most sensitive screen: the whispered voice test. Stand about an arm’s length (roughly 60 cm) behind and to the side of the patient so they cannot read your lips. Occlude the non-tested ear by pressing and gently rubbing the tragus. Exhale fully — this ensures you are truly whispering — then whisper a combination of three numbers and letters, such as “4–K–2.” A patient with normal hearing repeats all three correctly. If they miss any, repeat with a different set; failing to repeat at least three of six items is a failed screen. Test each ear separately.
Tuning fork tests separate conductive loss (a problem in the outer or middle ear — cerumen, effusion, perforation, otosclerosis) from sensorineural loss (a problem in the cochlea or eighth nerve — aging, noise exposure, ototoxic drugs). Use a 512 Hz fork. For the Weber test, strike the fork, place the base on the midline of the top of the skull or the mid-forehead, and ask where the sound is heard. Normal is equal in both ears with no lateralization. Sound that lateralizes to the bad ear means conductive loss in that ear (blocking room noise makes bone conduction seem louder there). Sound that lateralizes to the good ear means sensorineural loss in the other ear.
For the Rinne test, place the vibrating fork on the mastoid process, ask the patient to say when the sound disappears, then immediately move the still-vibrating tines about 2 cm in front of the ear canal. Normally, air conduction is better than bone conduction by about a 2:1 time ratio, so the patient hears the fork again in front of the ear — charted as AC > BC, positive Rinne. When bone conduction is equal to or better than air conduction, the Rinne is negative and there is conductive loss on that side. Nurses do not diagnose from these tests; nurses use them to decide how urgently to route a patient and to communicate a precise finding.
Two hearing changes need speed. Sudden sensorineural hearing loss — hearing that disappears in one ear over hours to a day or two, often with the patient describing fullness and tinnitus — is an emergency, not a wait-and-see. Outcomes are best when corticosteroids begin as early as possible — ideally within about 72 hours — and treatment is still offered up to two weeks from onset, so a patient who calls the clinic reporting that one ear stopped working overnight is triaged as urgent, and a patient who reports it five days later is still worked in today rather than dismissed as too late. And any patient on an ototoxic medication — aminoglycosides, high-dose loop diuretics, cisplatin, high-dose salicylates, vancomycin — who reports new tinnitus, hearing loss or vertigo needs the medication reported and levels reviewed before the next dose.
Pull the pinna up and back over age 3 and down and back under age 3, expect a pearly grey drum with a cone of light at 5 and 7 o’clock, and treat sudden one-sided hearing loss, mastoid tenderness and post-traumatic ear drainage as urgent rather than routine.
Section 4Nose, Sinuses, Mouth and Throat
Nose and sinuses
Inspect the external nose for symmetry, deformity and lesions. Test patency one side at a time: occlude one naris, ask the patient to close their mouth and sniff, then repeat on the other side. Then use an otoscope with a wide short speculum, or a nasal speculum with a penlight, tilting the patient’s head back slightly. You should see a midline septum, pink moist mucosa, and the inferior and middle turbinates as smooth reddish-pink ridges on the lateral wall. Do not confuse a turbinate with a polyp; polyps are pale, grey, glistening and mobile, and they do not hurt when touched.
Abnormal nasal findings are unusually informative. Pale, boggy, bluish-grey turbinates with clear watery discharge indicate allergic rhinitis. Bright red swollen mucosa suggests infection. A perforated septum raises questions about intranasal cocaine use, chronic topical decongestant use or trauma. Unilateral foul-smelling purulent discharge in a toddler is a nasal foreign body until someone looks. And clear watery drainage from one nostril after head trauma may be cerebrospinal fluid — do not pack it, do not insert a nasogastric tube, and report it immediately.
Only the frontal and maxillary sinuses are accessible. Palpate the frontal sinuses by pressing up under the bony brow ridges, never directly on the eyes, and the maxillary sinuses by pressing up under the cheekbones. Expected finding: no tenderness. Sinuses may also be transilluminated in a darkened room, but this is a low-yield technique in practice. The ethmoid and sphenoid sinuses cannot be examined at the bedside. Cranial nerve I (olfactory) is tested only when there is a reason — head trauma, suspected neurologic disease, new anosmia — by occluding one nostril and asking the patient to identify a familiar non-irritating odour such as coffee or vanilla with their eyes closed.
For epistaxis, sit the patient upright and leaning forward — never tilted back, which sends blood into the airway and the stomach and causes vomiting. Pinch the soft compressible part of the nose just below the nasal bones firmly and continuously for 10 to 15 minutes without releasing to check. Apply ice to the bridge. Bleeding that continues beyond 20 to 30 minutes of correct pressure, occurs in a patient on anticoagulants, or is accompanied by hemodynamic change requires provider evaluation.
Mouth, tongue and the oral cancer check
Put on gloves. Inspect the lips for colour, moisture, cracking and lesions. Then use a tongue blade and a good light to inspect the buccal mucosa, gums, teeth, hard and soft palate, tongue and floor of the mouth. Expected findings: mucosa pink, smooth and moist; gums pink with tight margins and no bleeding; teeth intact with no obvious caries; palate intact; tongue midline, pink, with a papillated dorsal surface and a smooth ventral surface. The parotid (Stensen) duct opens on the buccal mucosa opposite the second upper molar; the submandibular (Wharton) ducts open on either side of the frenulum under the tongue.
Now do the part students skip. Wrap the tip of the tongue in a gauze square, pull it gently forward and to each side, and inspect the lateral borders and the floor of the mouth, then palpate the floor of the mouth bimanually. Those two areas are where oral cancers most commonly begin, and they are the two areas that a quick “say ahh” never shows you. A thick white patch that does not scrape off is leukoplakia, a precancerous lesion requiring biopsy, and it is strongly associated with tobacco, smokeless tobacco and alcohol. By contrast, white curd-like plaques that do scrape off, leaving a red raw base that may bleed, are oral candidiasis. It is common in infants but it is never a normal finding: report it, expect an antifungal order such as nystatin, and assess feeding, bottle and pacifier hygiene and maternal nipple candidiasis. Distinguish it from milk residue, which wipes away without leaving a raw base, and treat thrush that persists or recurs beyond infancy as a reason to ask about immune status. In an adult it demands a question about inhaled corticosteroids without rinsing, recent antibiotics, diabetes or immunosuppression. Any oral ulcer or lesion present for more than two weeks is referred.
Several normal variants are commonly mistaken for pathology, and most of them are more frequent in patients with darker skin. Leukoedema is a filmy greyish-white translucent appearance of the buccal mucosa that disappears when the mucosa is stretched. Physiologic melanin pigmentation produces brown or blue-grey patches on the gingiva, buccal mucosa or tongue, present for years and asymptomatic. Torus palatinus is a hard bony midline ridge on the hard palate. Fordyce granules are small yellow-white sebaceous spots on the buccal mucosa. None require action; all require that you not chart them as lesions. What does require action is new pigmentation, a pigmented lesion that is changing, or a lesion that bleeds.
Pharynx, tonsils and the airway you are protecting
Depress the middle third of the tongue with a blade — pressing too far back triggers gagging — and ask the patient to say “ahh.” Inspect the tonsils, anterior and posterior pillars, uvula and posterior pharyngeal wall. Expected: mucosa pink and moist, tonsils without exudate, uvula midline, soft palate rising symmetrically and the uvula staying midline as it rises. That rise tests cranial nerves IX and X; a uvula that deviates to one side on phonation indicates weakness on the opposite side. Then ask the patient to stick out their tongue: it should protrude midline, which tests cranial nerve XII. Deviation of the protruded tongue points toward the side of the lesion.
Grade the tonsils on a standard scale, because “big tonsils” means nothing to the next clinician. 1+ tonsils are just visible beyond the pillars. 2+ extend halfway to the uvula. 3+ touch the uvula. 4+ touch each other in the midline — so-called kissing tonsils. Note colour, symmetry and exudate separately from size. In a sore throat, the findings that raise the probability of group A streptococcus are the Centor criteria: fever above 38°C, tonsillar exudate, tender anterior cervical adenopathy and the absence of cough. Cough, hoarseness, coryza and conjunctivitis point toward a virus. Nurses do not prescribe from this — but nurses do decide who gets seen this afternoon and who gets fluids and a follow-up call.
The throat exam has one absolute stop rule. If a patient — particularly a child — presents with sudden high fever, severe sore throat, drooling, muffled “hot potato” voice, refusal to lie down, sitting forward in a tripod position, and any stridor, do not put a tongue blade in that mouth. Do not lie them down. Do not draw blood or start an IV. Do not agitate the child. This picture is epiglottitis or another airway-threatening infection, and instrumenting the pharynx can precipitate complete obstruction. Keep the patient upright and calm, ideally in the parent’s arms, give oxygen in the least disturbing way possible, and get the airway team — anaesthesia and ENT — to the bedside immediately. The same restraint applies to a patient with a rapidly swelling tongue or lips from angioedema, and to a patient with severe unilateral throat pain, trismus and a uvula pushed to the opposite side, which is a peritonsillar abscess.
| Region | Expected finding | Abnormal finding | What it suggests |
|---|---|---|---|
| Nasal mucosa | Pink, moist; septum midline; both nares patent | Pale, boggy, bluish-grey turbinates | Allergic rhinitis |
| Nasal drainage | Scant clear mucus | Unilateral foul purulent drainage in a child | Nasal foreign body |
| Nasal drainage | Scant clear mucus | Clear watery drainage after head trauma | CSF leak — no packing, no NG tube, escalate |
| Lips and oral mucosa | Pink, moist, intact | Dry, sticky mucosa; tongue furrowed | Dehydration (the most reliable site in any skin tone) |
| Buccal mucosa | Pink and moist; leukoedema and melanin pigment are normal variants | White plaques that scrape off, red base beneath | Candidiasis — ask about steroids, antibiotics, immunosuppression |
| Tongue and floor of mouth | Midline, pink, no lesions | White patch that will NOT scrape off | Leukoplakia — precancerous, needs biopsy |
| Gums | Pink, tight margins, no bleeding | Overgrown gingiva covering tooth surfaces | Drug-induced gingival hyperplasia — phenytoin, calcium channel blockers, cyclosporine |
| Uvula and soft palate | Midline; palate rises symmetrically with “ahh” | Uvula deviated, trismus, unilateral swelling | Peritonsillar abscess — urgent |
| Tonsils | 1+ to 2+, pink, no exudate | 3+ to 4+ with exudate, fever, tender anterior nodes, no cough | Probable streptococcal pharyngitis — needs testing |
| Voice and breathing | Clear voice, quiet breathing | Stridor, drooling, tripod posture, muffled voice | AIRWAY EMERGENCY — no tongue blade, call the airway team |
Inspect the lateral tongue and floor of the mouth deliberately, grade tonsils 1+ to 4+, confirm the uvula is midline and rises symmetrically, and never introduce a tongue blade into the mouth of a drooling, stridorous, tripoding patient.
Section 5Numbers, Variation, Charting, Red Flags and Delegation
The numbers, across the lifespan
HEENT complaints rarely stand alone. A sore throat with a respiratory rate of 16 is a clinic visit; the same sore throat with a respiratory rate of 34 and a heart rate of 128 is a different problem entirely. You cannot make that distinction without knowing expected values cold, and expected values change dramatically with age. Adult resting norms are a temperature of 36.5–37.5°C (97.7–99.5°F), heart rate 60–100 beats per minute, respiratory rate 12–20 breaths per minute, blood pressure less than 120/80 mmHg, and oxygen saturation 95–100% on room air. Pain is assessed and documented alongside them.
| Age group | Heart rate (awake, beats/min) | Respiratory rate (breaths/min) | HEENT-relevant note |
|---|---|---|---|
| Newborn (0–1 month) | 100–205 | 30–60 | Obligate nose breather; any rectal temp ≥38.0°C (100.4°F) is an emergency workup |
| Infant (1–12 months) | 100–180 | 30–53 | Anterior fontanel open; otitis media risk peaks 6–24 months |
| Toddler (1–2 years) | 98–140 | 22–37 | Pull pinna DOWN and back until age 3; foreign bodies in nose and ear common |
| Preschool (3–5 years) | 80–120 | 20–28 | Tonsils are proportionally large through childhood, peaking about age 6–10 |
| School age (6–11 years) | 75–118 | 18–25 | Snellen chart usable; vision and hearing screening standard |
| Adolescent (12–15 years) | 60–100 | 12–20 | Screen noise exposure and vaping; adult technique applies |
| Adult | 60–100 | 12–20 | Visual acuity 20/20; presbyopia begins in the forties |
A few structural numbers belong with these. Newborn head circumference is 32–38 cm, measured over the widest point just above the eyebrows and pinnae, and is tracked routinely to about 24–36 months. The anterior fontanel is 2.5–4 cm at its widest and closes between 12 and 18 months; the posterior fontanel is 0.5–1 cm and closes by 1 to 2 months. Assess a fontanel with the infant calm and upright: a bulging, tense fontanel at rest suggests increased intracranial pressure, and a sunken fontanel suggests dehydration. Transient bulging while crying is normal.
Variation across skin tone and life stage
Colour changes are described in most textbooks as if every patient were pale. That is a patient-safety problem, because cyanosis, jaundice, pallor and erythema are all harder to see in richly pigmented skin and are all routinely missed. The solution is to move your assessment to sites where pigmentation is minimal and vascularity is high — and almost all of those sites are in this chapter’s territory.
| Finding | Where to look in ALL skin tones | What you see in lighter skin | What you see in darker skin |
|---|---|---|---|
| Central cyanosis | Lips, tongue, oral mucosa, conjunctivae, nail beds | Blue-grey lips and tongue | Ashen or grey lips and tongue; mucosa loses its normal pink undertone |
| Pallor / anemia | Palpebral conjunctiva, oral mucosa, palms, soles, nail beds | Skin appears white or waxy | Skin looks ashen or yellow-brown; conjunctiva and mucosa look pale rather than pink |
| Jaundice | Sclera adjacent to the iris, hard palate, under the tongue, palms and soles | Yellow skin and sclera | Yellow best seen in hard palate and sclera near the limbus; peripheral scleral yellow and small brown scleral deposits are normal variants |
| Erythema / inflammation | Compare bilaterally; PALPATE for warmth, induration and tautness | Redness readily visible | Redness may be invisible; rely on warmth, swelling, tightness and the patient’s report |
| Dehydration | Oral mucous membranes, tongue furrowing, tear production, fontanel in infants | Dry lips and mucosa | Identical — oral mucosa is skin-tone independent and is the reliable site |
Life stage changes the exam as much as skin tone does. In pregnancy, estrogen-driven mucosal edema causes nasal congestion and epistaxis, and the gums become hyperemic and bleed easily; the thyroid may enlarge modestly. What is never normal in pregnancy is new blurred vision, scotomata or photophobia with headache after 20 weeks — that combination with a blood pressure of 140/90 mmHg or higher is preeclampsia, and 160/110 mmHg or higher is severe-range and requires immediate escalation. In older adults, expect presbyopia, presbycusis, arcus senilis, decreased tear and saliva production (often worsened by anticholinergic medications), thinner drier nasal mucosa, reduced smell and taste, and drooping upper lids. Expect them — but do not dismiss them. Xerostomia causes caries, poor denture fit, altered nutrition and impaired swallowing, and it is very often a medication side effect that can be reduced.
Charting it: vague versus precise
Documentation is not paperwork; it is the instrument by which your assessment reaches the next nurse and the provider at 3 a.m. The test of a good HEENT entry is simple: could a colleague who has never seen this patient reconstruct exactly what you found and detect a change tomorrow? Objective findings, measured values, laterality and negatives that matter — those are what make an entry usable.
| Vague — do not write this | Precise — write this |
|---|---|
| “HEENT within normal limits.” | “Head normocephalic, atraumatic. Face symmetric at rest and with movement. Neck supple, full active ROM, trachea midline. Thyroid non-palpable, no bruit. Cervical nodes non-palpable bilaterally.” |
| “Swollen gland in neck.” | “Right anterior cervical node 1.5 × 1.0 cm, firm, mobile, tender, warm; overlying skin intact. Left anterior cervical chain non-palpable. No supraclavicular nodes.” |
| “Pupils equal and reactive.” | “Pupils 4 mm bilaterally, equal, round, brisk direct and consensual response to light; accommodation intact. EOMs intact through six cardinal fields, no nystagmus.” |
| “Vision blurry.” | “Pt reports blurred vision OS × 2 hours, painless, no floaters. Corrected acuity 20/25 OD, 20/70 OS, 20/30 OU by Snellen at 20 ft. Visual fields full to confrontation OD; misses lower temporal quadrant OS.” |
| “Sore throat, tonsils big.” | “Oral mucosa pink and moist. Tonsils 3+ bilaterally with white exudate; uvula midline, soft palate rises symmetrically. No trismus, no drooling, voice clear. Temp 38.6°C oral; tender anterior cervical nodes bilaterally; no cough reported.” |
| “Ear looks infected.” | “Right TM erythematous and bulging, landmarks and cone of light obscured; canal without drainage. Left TM pearly grey, cone of light at 7 o’clock, intact. Tenderness with right tragal pressure absent; no mastoid tenderness. Whispered voice 3/3 left, 1/3 right.” |
Red flags, SBAR and who may do what
Some findings are charted. Some findings are called. Learning which is which is the difference between a nurse who documents an event and a nurse who prevents one. The following list is not exhaustive, but every item on it means you stop what you are doing and escalate.
| Red flag | Why it is urgent | Immediate nursing action |
|---|---|---|
| Stridor, drooling, tripod posture, muffled voice | Impending airway obstruction | No tongue blade, no supine position, keep calm and upright, oxygen, call airway team NOW |
| New unilateral dilated non-reactive pupil with declining LOC | Uncal herniation compressing CN III | Rapid response, elevate head of bed 30°, prepare for imaging, neuro checks |
| Tracheal deviation with dyspnea and absent breath sounds | Tension pneumothorax | Rapid response, high-flow oxygen, prepare for needle decompression |
| Sudden painless vision loss, curtain, shower of floaters | Retinal artery occlusion or detachment | Same-hour ophthalmology; keep patient still, nothing by mouth pending decision |
| Severe eye pain, halos, hard globe, mid-dilated fixed pupil, vomiting | Acute angle-closure glaucoma | Emergency ophthalmology; do not instill dilating drops |
| Chemical splash to the eye | Ongoing corneal destruction, worst with alkali | Irrigate immediately 15–20 min BEFORE acuity testing; remove contacts |
| Headache with fever, photophobia and nuchal rigidity | Meningitis | Isolation precautions, provider now, prepare for lumbar puncture and antibiotics |
| New temporal artery tenderness, jaw claudication, vision change, age over 50 | Giant cell arteritis — irreversible blindness within days | Urgent provider notification, ESR/CRP, steroids are time-critical |
| Expanding neck swelling or hoarseness after thyroid or carotid surgery | Hematoma compressing the airway | Rapid response, sit upright, oxygen, stay with patient, emergency airway equipment at bedside |
| Sudden one-sided hearing loss over hours | Sudden sensorineural hearing loss; steroids work best started early (ideally <72 h) and are still offered up to 2 weeks | Urgent ENT/audiology referral, do not schedule routinely |
| Clear rhinorrhea or otorrhea after head trauma, with Battle sign or raccoon eyes | Basilar skull fracture with CSF leak | No nasal packing, no NG tube (orogastric only), head of bed elevated, provider now |
| Rectal temperature ≥38.0°C (100.4°F) in an infant under 3 months | Serious bacterial infection risk | Immediate provider notification and full sepsis evaluation |
Escalate with SBAR, because a structured report gets a decision and an unstructured one gets questions. Here is a HEENT escalation written out in full, the way you would actually say it into the phone:
| SBAR | What you say |
|---|---|
| S — Situation | “This is Dana Reyes, RN, on 4 West. I’m calling about Mr. Alvarez in 412. He has new swelling of the anterior neck and his voice has changed in the last 30 minutes. I’m concerned about his airway.” |
| B — Background | “He is a 62-year-old man, post-operative day zero from a total thyroidectomy at 0900. He was stable through recovery. He is on enoxaparin prophylaxis.” |
| A — Assessment | “At 1615 his anterior neck is visibly fuller than at 1545 and the dressing is taut. He is hoarse and reports throat tightness. Respirations 26 and slightly noisy on inspiration, heart rate 112, blood pressure 148/86, SpO2 93% on room air, temperature 37.1°C. He is anxious and sitting forward. Trachea appears midline. This looks like an expanding neck hematoma.” |
| R — Recommendation | “I need you to come to the bedside now. I have him upright, oxygen at 4 L by nasal cannula, an emergency airway tray and a suture removal set at the bedside, and I’ve called anaesthesia. Do you want the wound opened at the bedside if he deteriorates, and may I make him nothing by mouth?” |
Finally, delegation. The rule is a rule of scope, not of workload. The nursing assessment, the interpretation of findings, patient teaching, evaluation of outcomes, and the care of any unstable or unpredictable patient stay with the registered nurse and cannot be delegated. Unlicensed assistive personnel may perform tasks that are routine, standardized and have a predictable outcome on a stable patient, and they may — and must — report what they observe. Delegating well means being specific: not “keep an eye on him,” but “tell me right away if his voice changes, if he starts drooling, or if he says his throat feels tight.”
| May be delegated to UAP | RN only (never delegated) |
|---|---|
| Positioning the patient upright, adjusting lighting, gathering the otoscope, penlight and Snellen chart | Performing and interpreting the HEENT assessment, including acuity, pupils, nodes and otoscopy findings |
| Cleaning and disinfecting reusable equipment; disposing of specula | Deciding what a finding means and whether it requires escalation |
| Measuring and recording vital signs on a STABLE patient | Assessing vital signs on an unstable patient, or interpreting any trend |
| Assisting with oral care, denture care and hygiene | Assessing oral mucosa, swallow safety and aspiration risk |
| Applying a warm compress or an ice pack per an existing order | Eye irrigation for a chemical splash; instilling any medication |
| Escorting, transporting and assisting a patient with a visual field deficit | Teaching the patient about the deficit and creating the safety plan |
| Reporting observations: “his eye is red,” “she said her ear hurts,” “his voice sounds different” | Acting on those observations and documenting the assessment |
Know the expected numbers for every age, assess colour changes at the mucous membranes and conjunctivae rather than the skin, chart measured values with laterality, escalate red flags using SBAR, and keep assessment, interpretation, teaching and unstable patients in your own hands.
The chapter in one breath
The head and neck are examined by inspection then palpation, comparing both sides simultaneously, with percussion essentially unused and auscultation reserved for the carotids and an enlarged thyroid — and with the standing reminder that the abdomen is the one region where the order becomes inspect, auscultate, percuss, palpate. Ten cervical node chains are palpated in a fixed order; tender, mobile, bilateral nodes suggest infection while hard, fixed, painless, unilateral nodes suggest malignancy, and any supraclavicular node is abnormal. The thyroid rises with a swallow, and a goiter is auscultated with the bell for a bruit. The trachea is midline. Eyes are measured, not guessed: Snellen at 20 feet, Jaeger at 14 inches, confrontation fields, pupils in millimetres, six cardinal fields of gaze, and the red reflex in every infant. Ears require correct pinna traction — up and back over 3, down and back under 3 — a pearly grey drum with the cone of light at 5 and 7 o’clock, and whisper, Weber and Rinne to separate conductive from sensorineural loss. The mouth demands inspection of the lateral tongue and floor, tonsil grading 1+ to 4+, and a midline uvula that rises symmetrically. Findings are charted with numbers and laterality, red flags are escalated with SBAR, and assessment, teaching, evaluation and unstable patients never leave the RN.
Words worth knowing
| Term | What it means |
|---|---|
| Normocephalic, atraumatic | Standard charting phrase for a skull of normal size and shape with no evidence of injury. |
| Lymphadenopathy | Enlarged lymph nodes; described by location, size in centimetres, shape, consistency, mobility and tenderness. |
| Virchow node | An enlarged left supraclavicular node draining the thoracic duct; a classic sign of abdominal or thoracic malignancy. |
| Goiter | Any visible or palpable enlargement of the thyroid gland. |
| Thyroid bruit | A soft blowing sound heard with the bell over an enlarged, hypervascular thyroid; suggests hyperthyroidism. |
| Trismus | Inability to open the mouth fully because of muscle spasm; with a sore throat it suggests a deep space or peritonsillar abscess. |
| Snellen chart | Distance visual acuity chart read at 20 feet (6 m); results charted as a fraction such as 20/40. |
| Presbyopia | Age-related loss of near focusing ability beginning in the forties as the lens stiffens. |
| PERRLA | Pupils Equal, Round, Reactive to Light and Accommodation — always charted with actual pupil size in millimetres. |
| Consensual response | Constriction of the opposite pupil when light is shone into one eye. |
| Anisocoria | Unequal pupil size; up to about 1 mm and stable is physiologic, but a new difference is an emergency. |
| Red reflex | The orange-red glow seen through the ophthalmoscope; absence or a white reflex (leukocoria) in an infant is an urgent referral. |
| Papilledema | Swelling of the optic disc with blurred margins, indicating raised intracranial pressure. |
| Arcus senilis | Greyish-white ring at the corneal periphery; normal after 60, needs lipid evaluation under 40. |
| Cone of light | Triangular light reflex on the tympanic membrane at 5 o’clock on the right and 7 o’clock on the left. |
| Weber test | Tuning fork on the midline skull; lateralizes to the bad ear in conductive loss and to the good ear in sensorineural loss. |
| Rinne test | Compares air to bone conduction; normal is AC greater than BC in about a 2:1 ratio. |
| Presbycusis | Age-related high-frequency sensorineural hearing loss; speak lower and slower rather than louder. |
| Leukoplakia | A thick white oral patch that does NOT scrape off; precancerous and requiring biopsy. |
| Leukoedema | Filmy greyish-white buccal mucosa that disappears on stretching; a normal variant, more common in darker-skinned patients. |
Check yourself
Assessing the Thorax and Lungs
The chest is the one region where a nurse can detect a patient deteriorating before any monitor announces it. Respiratory rate is the earliest vital sign to change in sepsis, in hemorrhage, in opioid oversedation and in heart failure — and it is the vital sign most often invented rather than counted. This chapter teaches the thoracic exam the way it is actually performed at the bedside: the bony landmarks you find with your fingertips, the lobes lying underneath them, and then the four steps in their fixed order — inspection, palpation, percussion, auscultation. You will learn what resonance sounds like against dullness, why bronchial breath sounds in the periphery mean consolidation, why a wheeze that disappears is worse than a wheeze that does not, and how to write a lung note precise enough that the next nurse can tell whether the patient improved. Every finding here has an escalation threshold attached, because a chest exam that ends in your head instead of in an SBAR call helps no one.
By the end of this chapter you can
- Locate the suprasternal notch, sternal angle (angle of Louis), vertebra prominens, costal angle and the standard thoracic reference lines, and name the lobe lying beneath any point you touch.
- Perform the thoracic exam in the correct order — inspection, palpation, percussion, auscultation — and explain why the abdomen is the single exception to that sequence.
- Count and describe respiratory rate, depth and pattern, and state the expected ranges for the newborn, infant, toddler, preschooler, school-age child, adolescent, adult and older adult.
- Assess chest expansion and tactile fremitus, and interpret increased and decreased fremitus.
- Distinguish the five percussion tones and measure diaphragmatic excursion (expected 3–5 cm).
- Differentiate vesicular, bronchovesicular and bronchial breath sounds and identify crackles, wheezes, rhonchi, stridor and pleural friction rub.
- Elicit and interpret bronchophony, egophony and whispered pectoriloquy.
- Recognize respiratory red flags requiring immediate escalation and communicate them using SBAR.
- Document a lung assessment in precise, defensible language and apply the five rights of delegation to respiratory tasks.
Section 1Landmarks, Lobes and the Respiratory Baseline
Reference lines and the bony landmarks you can find in the dark
A lung finding without a location is nearly useless. “Crackles in the chest” tells the next nurse nothing; “fine end-inspiratory crackles, bilateral posterior bases, below the level of the scapular tips” tells them exactly where to listen at 0300 to see whether the patient got better. Naming a location requires two coordinates: a horizontal one from the ribs and intercostal spaces, and a vertical one from a reference line. Learn to find both by touch, because you will often be assessing in a dim room with a patient who does not want to sit forward.
Start at the suprasternal notch, the hollow at the top of the sternum. Walk your fingers down about 5 cm until you feel a firm ridge — the sternal angle, or angle of Louis, where the manubrium meets the body of the sternum. The second rib articulates here, so the space just below your finger is the second intercostal space. From that single landmark you can count every rib on the anterior chest. Count in the intercostal spaces, not on the ribs, and remember that the costal cartilages of ribs eight through ten fuse rather than attach to the sternum, so anterior counting becomes unreliable below about the seventh rib. The sternal angle also marks the level where the trachea bifurcates into the right and left mainstem bronchi (roughly T4 to T5) — useful, because that is exactly where normal breath sounds are loudest and most tubular.
Posteriorly, ask the patient to flex the neck forward and find the vertebra prominens, the prominent spinous process of C7. Below it lies T1. The inferior angle of the scapula sits at approximately the seventh rib or seventh intercostal space and is the practical marker for “the bases.” The vertical reference lines are: midsternal, midclavicular and anterior axillary anteriorly; anterior, mid- and posterior axillary laterally; and vertebral (midspinal) and scapular posteriorly. The costal angle, formed where the two costal margins meet at the xiphoid, is normally less than 90 degrees and widens in chronic air trapping.
What lies beneath: lobes, fissures and lung borders
The right lung has three lobes, the left has two plus the lingula, which is the left lung’s anatomic answer to the right middle lobe. The clinically important fact is where those lobes sit relative to the skin. The oblique (major) fissures run from about the T3 spinous process posteriorly, around the chest, to the sixth rib at the midclavicular line. Everything you auscultate on the posterior chest below the scapular tips is lower lobe. The right horizontal (minor) fissure runs from the fourth rib at the sternum to the fifth rib at the midaxillary line, so the right middle lobe is heard on the anterior and right lateral chest only — never on the back. This is why nurses who auscultate only the posterior chest miss right middle lobe pneumonia and aspiration, and why the lateral chest wall at the midaxillary line is a mandatory part of the exam, not an optional one.
The lung apices extend 2 to 4 cm above the inner third of the clavicles, so a finding “above the clavicle” is still lung. The lower borders sit at roughly the sixth rib at the midclavicular line, the eighth rib at the midaxillary line, and the level of T10 posteriorly, descending to about T12 on deep inspiration. Below those borders you are percussing liver on the right and stomach or spleen on the left, which is why a dull note at the right base near the sixth rib is normal liver and not consolidation.
The respiratory baseline and the order of the exam
Count respirations for a full 30 seconds and multiply by two when the pattern is regular, and for a full 60 seconds when it is irregular, when the patient is an infant, or when the rate is at either extreme. Count without announcing it — keep your fingers on the radial pulse and watch or feel the chest, because a patient who knows you are counting breathes differently. Document rate, depth (shallow, normal, deep) and rhythm (regular, irregular), plus effort and oxygen saturation with the delivery device and flow rate. “RR 18” alone is an incomplete vital sign.
| Age group | Expected respiratory rate (breaths/min) | Bedside notes |
|---|---|---|
| Newborn (birth to 1 month) | 30–60 | Irregular periodic breathing with pauses under 20 seconds is normal; a pause of 20 seconds or more, or any pause with color or heart-rate change, is apnea |
| Infant (1–12 months) | 30–53 | Nose breathers in the early months; a blocked nose alone can cause distress |
| Toddler (1–2 years) | 22–37 | Breathing remains abdominal/diaphragmatic |
| Preschooler (3–5 years) | 20–28 | Thoracic breathing emerges around age 6 to 7 |
| School-age (6–11 years) | 18–25 | Chest wall still thin; sounds transmit widely |
| Adolescent (12–18 years) | 12–20 | Adult pattern established |
| Adult | 12–20 | Over 20 is tachypnea; under 12 is bradypnea; both are reportable trends |
| Older adult | 12–20 | May sit at the upper end; a sustained rate over 24 in an older adult is a sepsis and pneumonia screen, not normal aging |
| Pregnancy (any trimester) | 12–20 (usually unchanged) | Tidal volume rises 30% to 40%; rate itself should not rise much — tachypnea in pregnancy is abnormal |
Oxygen saturation by pulse oximetry is normally 95% to 100% on room air. A saturation of 90% corresponds roughly to a PaO2 of 60 mmHg — the shoulder of the oxyhemoglobin dissociation curve, below which small further drops in saturation mean large drops in PaO2. For most patients with chronic carbon dioxide retention the prescribed target is 88% to 92%, because excess oxygen worsens ventilation-perfusion matching and can blunt ventilatory drive; titrate only within the ordered range. That target is never a reason to withhold oxygen — a patient who is acutely and severely hypoxemic is given oxygen first, and the target range is re-established once they are safe. Always chart saturation with its context: “SpO2 94% on 2 L/min nasal cannula” means something entirely different from “SpO2 94% on room air.”
The thoracic exam runs inspection, palpation, percussion, auscultation — in that order, every time. The abdomen is the one exception: there you inspect, then auscultate, then percuss, then palpate, because pressing on the abdomen first changes bowel sounds and can produce falsely absent or hyperactive findings. Learn the exception as an exception so you never carry it into the chest.
Every chest finding needs a rib level and a reference line, because a location-free finding cannot be compared to the next nurse’s assessment.
Section 2Inspection and Palpation of the Thorax
Inspection: what the first ten seconds tell you
Inspection begins before you touch anything, and often before you speak. Expose the chest with the patient sitting upright, gown open, room warm and light good. Stand back far enough to see the whole thorax and watch a full minute of breathing. Note position first: a patient sitting bolt upright, leaning forward on their elbows, is in the tripod position and is recruiting every accessory muscle they have. Note speech: a patient who can speak only three or four words between breaths is in significant distress regardless of the number on the pulse oximeter.
Look at shape. The normal adult chest is wider than it is deep; the anteroposterior to transverse diameter ratio is about 1:2 (ranging to 5:7). In a barrel chest the ratio approaches 1:1, the ribs run horizontally rather than sloping down at roughly 45 degrees, and the costal angle exceeds 90 degrees — the configuration of chronic air trapping in emphysema and long-standing asthma, and an expected finding in infants under about two years and in some older adults with kyphosis. An increased anteroposterior diameter is a chronic finding, so it never explains a new symptom — do not let it talk you out of an acute change. Note also pectus excavatum (a sunken sternum), pectus carinatum (a protruding sternum), kyphosis, scoliosis and any surgical scars or chest tube sites.
Look at effort. Normal quiet breathing is almost invisible: the chest rises symmetrically, the accessory muscles are silent, and the ratio of inspiration to expiration is about 1:2. Abnormal effort shows as retractions (skin sucking in above the clavicles, between the ribs, or below the xiphoid), nasal flaring, grunting (an infant generating their own positive end-expiratory pressure — always ominous), head bobbing in an infant, use of the sternocleidomastoid, scalene and trapezius muscles, and pursed-lip breathing. Watch for paradoxical movement, where a segment of chest wall moves inward on inspiration — flail chest after trauma. Finally, look at the fingers: the normal nail-bed angle is about 160 degrees, and clubbing (angle 180 degrees or more, with a spongy nail bed) signals months to years of hypoxemia, not an acute event.
Breathing patterns worth naming
| Pattern | What it looks like | What it suggests |
|---|---|---|
| Eupnea | 12–20/min in an adult, regular, effortless, I:E about 1:2 | Expected |
| Tachypnea | Over 20/min, usually shallow | Fever, pain, anxiety, hypoxemia, sepsis, metabolic acidosis, pulmonary embolism |
| Bradypnea | Under 12/min, regular | Opioids and sedatives, increased intracranial pressure, hypothyroidism — check sedation level |
| Hyperpnea | Normal or increased rate with increased depth | Exercise, anxiety, early metabolic acidosis |
| Kussmaul respirations | Deep, labored, fast and regular | Severe metabolic acidosis, classically diabetic ketoacidosis — the body blowing off CO2 |
| Cheyne-Stokes | Crescendo–decrescendo depth alternating with apneic pauses of 15–60 seconds | Heart failure, uremia, brain injury, end of life; can be normal in infants and in adults at high altitude during sleep |
| Biot (ataxic) | Irregular breaths of variable depth with abrupt apneic pauses | Medullary damage, severe brain injury — escalate |
| Apnea | Cessation of breathing; 20 seconds or more in an infant | Always an emergency in any age group when sustained |
| Orthopnea | Dyspnea lying flat, relieved by sitting up; chart as pillows required | Heart failure, COPD, large effusion; document as “two-pillow orthopnea” |
Palpation: tenderness, expansion, fremitus and crepitus
Palpate with warm hands and a stated purpose. First, palpate for tenderness, masses and lesions with the finger pads over the anterior, lateral and posterior chest wall, and note whether pain is reproducible with pressure — reproducible chest wall tenderness suggests a musculoskeletal or costochondral source, but it never rules out a cardiac or pulmonary cause on its own. Confirm the trachea is midline by placing an index finger in the suprasternal notch and slipping it gently to each side to compare the spaces between the trachea and the sternocleidomastoid. Deviation is a late and dangerous sign.
Next assess chest expansion. Standing behind the seated patient, place your thumbs along the spine at about the level of the tenth rib with your palms lightly on the posterolateral chest, and slide medially just enough to raise a small skin fold between your thumbs. Ask for a deep breath. Your thumbs should move apart symmetrically, separating about 3 to 5 cm. Asymmetry is the finding that matters: the side that lags is the abnormal side — think pneumothorax, pleural effusion, lobar pneumonia, atelectasis, splinting from rib fracture, or post-operative guarding.
Then assess tactile fremitus, the palpable vibration of the voice transmitted through lung tissue. Use the ball of the palm or the ulnar surface of one hand, move in a side-to-side ladder pattern, and ask the patient to repeat “ninety-nine” or “one-one-one” in a low voice each time you move. Fremitus is normally strongest near the large airways — the second intercostal spaces anteriorly and between the scapulae posteriorly — and fades toward the bases. Compare sides, not absolute intensity. Solid, consolidated lung conducts sound better, so fremitus increases in pneumonia. Air, fluid or fat between your hand and the lung conducts it worse, so fremitus decreases in pneumothorax, pleural effusion, emphysema, bronchial obstruction and simply in a thick chest wall or a very muscular back.
Finally, feel for crepitus — subcutaneous emphysema. It feels like fine bubble wrap or crackling tissue paper under the skin, usually over the upper chest, neck or around a chest tube insertion site. It means air has escaped into the subcutaneous tissue and demands immediate assessment for pneumothorax, a disconnected or malpositioned chest tube, or airway injury. Mark the borders with a skin pen, note the time, and escalate.
| Palpation finding | Expected | Abnormal and what it suggests |
|---|---|---|
| Trachea | Midline in the suprasternal notch | Deviated toward the lesion: atelectasis, pneumonectomy, fibrosis. Deviated away: tension pneumothorax, large pleural effusion, large mass — emergency |
| Chest expansion | Symmetric, thumbs separate 3–5 cm | Unilateral lag: pneumothorax, effusion, consolidation, splinting. Globally reduced: COPD, kyphosis, neuromuscular weakness, obesity |
| Tactile fremitus | Symmetric, strongest near large airways, fading at bases | Increased: consolidation (pneumonia). Decreased or absent: pneumothorax, effusion, emphysema, obstructed bronchus, thick chest wall |
| Chest wall | Non-tender, no masses, no crepitus | Point tenderness over a rib after trauma suggests fracture; crepitus suggests subcutaneous air |
Compare side to side, never top to bottom. Every step of the chest exam is a symmetry test — you are asking “is the right the same as the left at this level?” A finding that is identical on both sides is far more likely to be that patient’s normal; a finding on one side only is the one that earns a phone call.
Inspection and palpation localize the problem before you ever hear it: the side that lags, the side with different fremitus and the side the trachea points away from are all telling you where to listen hardest.
Section 3Percussion and Diaphragmatic Excursion
How to percuss so the note means something
Percussion is the step students skip and experienced nurses use to answer one question quickly: is there air where there should be air? Sound produced by tapping the chest wall penetrates only about 5 to 7 cm, so percussion assesses the outer lung, not deep structures — a small central lesion will be silent to your fingers.
Use indirect percussion. Hyperextend the middle finger of your non-dominant hand — the pleximeter — and press its distal interphalangeal joint firmly into an intercostal space, keeping the rest of that hand off the chest wall so it does not damp the vibration. With the dominant hand, flex the wrist (not the elbow or shoulder) and strike the pleximeter’s DIP joint sharply with the tip of your middle finger — the plexor — using a quick, bouncing motion. Deliver two taps, then withdraw immediately; a finger left in place absorbs the sound you are trying to hear. Keep your fingernail short, or you will hurt both of you.
Percuss over intercostal spaces only. Bone gives a dull, useless note, so avoid the sternum, ribs, scapulae and vertebrae. Work in the same side-to-side ladder as the rest of the exam: right apex, left apex, right second interspace, left second interspace, and downward, comparing each pair before moving on. Anteriorly, percuss from above the clavicles to the sixth rib. Posteriorly, ask the patient to cross their arms in front to swing the scapulae laterally, then percuss from C7 down to T10, staying medial to the scapular borders and finishing along the lateral chest.
The five percussion tones
| Tone | Quality and pitch | Normally heard over | Abnormal when it appears over lung, and what it suggests |
|---|---|---|---|
| Flatness | Very soft, high-pitched, short | Muscle, bone, thigh | Massive pleural effusion; a large solid tumor |
| Dullness | Soft to moderate, medium pitch, thudding | Liver, heart, full bladder | Consolidation (pneumonia), atelectasis, pleural effusion, hemothorax, mass |
| Resonance | Loud, low-pitched, hollow, long | Normal air-filled lung | This is the expected finding across both lung fields |
| Hyperresonance | Very loud, very low, booming, longer | Not normal in an adult; normal in a young child’s thin chest | Emphysema, acute asthma with air trapping, pneumothorax |
| Tympany | Loud, high-pitched, drum-like, musical | Gastric air bubble, air-filled bowel | Large pneumothorax; tension pneumothorax |
Two normal findings trip up beginners. Dullness at the right base at about the fifth to sixth intercostal space anteriorly is liver, and tympany in the left lower anterior chest is the gastric air bubble — neither is pathology. Cardiac dullness is expected from the third to fifth interspaces left of the sternum. Anything else that is dull where it should be resonant deserves a careful auscultation of that exact spot.
Diaphragmatic excursion
Diaphragmatic excursion measures how far the diaphragm travels between full expiration and full inspiration, and it is the cleanest bedside test of ventilatory mechanics available without equipment. With the patient sitting and leaning slightly forward, ask them to exhale fully and hold. Percuss down the posterior chest along the scapular line until resonance changes to dullness, and mark that spot. Let them breathe, then ask them to inhale deeply and hold. Percuss down again until the note changes, and mark the second spot. The distance between the two marks is the excursion, and it is measured on both sides.
Expected excursion in a healthy adult is 3 to 5 cm, and up to 7 to 8 cm in a tall, well-conditioned adult. The right side may sit slightly higher than the left because of the liver. Reduced excursion appears in emphysema (a flattened, already-depressed diaphragm), atelectasis, pleural effusion, severe obesity, ascites, late pregnancy, phrenic nerve injury and simple splinting from pain. Asymmetry — one side moving well and the other barely at all — is the more alarming pattern and points to unilateral disease or a paralyzed hemidiaphragm.
Percussion is a comparison, not a measurement. You are not trying to name the note in isolation — you are asking whether this interspace sounds like its partner on the other side. Percuss the patient’s own thigh once to remind your ear what flat sounds like, then let the two lungs argue with each other.
Resonance is the expected lung note; dullness means something solid or fluid replaced the air, hyperresonance and tympany mean there is too much air — and diaphragmatic excursion under 3 cm tells you the patient cannot move air even when they try.
Section 4Auscultation and Voice-Transmitted Sounds
Technique and sequence
Use the diaphragm of the stethoscope, pressed firmly enough to leave a light ring on the skin, and always on bare skin — auscultating through a gown produces rustling artifact that beginners confuse with crackles. Ask the patient to sit upright and breathe slowly and a little more deeply than usual through an open mouth. Nose breathing adds turbulence; mouth breathing gives clean sounds. Listen to at least one full inspiration and expiration at every site, and stop and let the patient rest if they become dizzy or lightheaded from hyperventilating.
Move in the same side-to-side ladder used for percussion: apices first, then downward, comparing each pair before descending. Posteriorly, listen at approximately eight to ten paired sites from above the scapulae down to the level of T10, staying medial to the scapular borders. Then listen laterally at the midaxillary lines from the axilla to the seventh or eighth rib — this is where the right middle lobe and the lingula live. Then listen anteriorly from above the clavicles down to the sixth rib, moving the breast tissue aside rather than listening through it. If a patient cannot sit up, listen posteriorly with them rolled to each side and document their position, because gravity changes findings.
Describe what you hear along four axes: location, timing in the respiratory cycle (inspiratory, expiratory or both, early or late), quality, and whether it clears with coughing. A crackle that clears after two deep breaths and a cough is atelectatic and usually resolves with mobilization and incentive spirometry; a crackle that persists is not.
Normal breath sounds
| Sound | Pitch and intensity | Inspiration : expiration | Where it is normal | Meaning if heard elsewhere |
|---|---|---|---|---|
| Vesicular | Soft, low-pitched, breezy | Inspiration longer, roughly 3:1, no pause | Most of the peripheral lung fields | Vesicular sounds heard over the trachea would be abnormally diminished |
| Bronchovesicular | Moderate pitch and intensity | Inspiration equals expiration | First and second interspaces anteriorly; between the scapulae posteriorly | In the periphery of an adult, suggests early consolidation. Normal throughout the chest in infants and young children |
| Bronchial (tubular) | Loud, high-pitched, hollow | Expiration longer than inspiration, with a brief pause between | Over the trachea and manubrium only | Over peripheral lung, strongly suggests consolidation — solid lung transmits large-airway sound outward |
| Diminished or absent | Faint or silent | — | Never normal over ventilated lung | Pneumothorax, large effusion, severe emphysema, obstructed bronchus, atelectasis, shallow breathing, obesity — and, in an asthmatic, a silent chest means impending respiratory arrest |
Adventitious sounds
| Sound | Description and timing | Clears with cough? | Common causes |
|---|---|---|---|
| Fine crackles (rales) | Discontinuous, brief, high-pitched popping; end-inspiratory; like rolling hair between your fingers or opening Velcro | Atelectatic crackles do; others do not | Pulmonary edema, pneumonia, interstitial fibrosis, atelectasis, early heart failure |
| Coarse crackles | Louder, lower-pitched, wet, bubbling; early inspiratory and often expiratory | May partially clear | Secretions in larger airways: pneumonia, bronchitis, pulmonary edema, poor cough |
| Wheezes (sibilant) | Continuous, musical, high-pitched; predominantly expiratory, may be inspiratory when severe | No | Bronchospasm: asthma, COPD, bronchiolitis, anaphylaxis, heart failure (“cardiac asthma”); a fixed unilateral wheeze suggests foreign body or tumor |
| Rhonchi (sonorous wheezes) | Continuous, low-pitched, snoring or gurgling; expiratory more than inspiratory | Often yes — this is the distinguishing feature | Secretions or mucus in large airways: bronchitis, pneumonia, cystic fibrosis |
| Stridor | Loud, high-pitched, harsh crowing; inspiratory; audible without a stethoscope, loudest over the neck | No | Upper-airway obstruction: croup, epiglottitis, foreign body, anaphylaxis, post-extubation edema, laryngospasm — a true emergency, call for help before you finish the exam |
| Pleural friction rub | Coarse, grating, creaking like leather; both inspiration and expiration; localized, usually anterolateral and painful | No | Pleuritis, pleural inflammation, pulmonary infarct, pneumonia extending to the pleura |
Two distinctions carry the most clinical weight. First, rhonchi versus crackles: ask the patient to cough and listen again. Sounds that clear were secretions sitting in an airway; sounds that persist reflect fluid or disease in the tissue. Second, wheeze versus stridor: a wheeze is expiratory and comes from the lower airways; stridor is inspiratory, comes from obstruction of the extrathoracic upper airway — anywhere above the thoracic inlet, whether supraglottic (epiglottitis), glottic (laryngospasm, vocal cord edema) or subglottic (croup, post-extubation edema) — and buys the patient minutes rather than hours. Confusing them delays an airway response.
Voice-transmitted sounds
When percussion is dull and breath sounds are bronchial where they should be vesicular, three quick maneuvers confirm consolidation. Perform each with the stethoscope diaphragm over the suspicious area, comparing to the same spot on the opposite side.
Bronchophony: ask the patient to say “ninety-nine” repeatedly. Normally the words are muffled and indistinct. Over consolidated lung they become louder and clearer. Egophony: ask the patient to say a long “eeee.” Normally you hear a muffled “eeee.” Over consolidation it converts to a nasal “aaaa” — the classic E-to-A change, also heard just above the fluid level of a pleural effusion where lung is compressed. Whispered pectoriloquy: ask the patient to whisper “one-two-three” or “ninety-nine.” Normally the whisper is faint and unintelligible. Over consolidation the whispered words come through crisply, as if the patient were speaking directly into your stethoscope. All three are increased in consolidation and decreased or absent over a pneumothorax or a large effusion, for the same reason fremitus behaves that way: solids conduct sound, air and fluid do not.
Whispered pectoriloquy is the most sensitive of the three voice tests — if you can clearly understand a whisper through the chest wall, the lung underneath is consolidated until proven otherwise. Pair it with the percussion note: dull plus bronchial breath sounds plus increased fremitus plus positive egophony is a pneumonia until imaging says otherwise, and it is worth a call.
Bronchial breath sounds heard in the lung periphery, with increased fremitus, dullness and a positive E-to-A change, describe consolidated lung — and a chest that has gone silent in a wheezing patient is worse than one that is still wheezing.
Section 5Red Flags, Lifespan Variation, Documentation and Escalation
Findings that mean escalate now
The earliest sign of hypoxia is not cyanosis. It is restlessness, anxiety, agitation or new confusion, because the brain is the first organ to complain. A patient who was oriented at 0800 and is now pulling at their lines at 1000 is hypoxic until you prove otherwise. Cyanosis is a late sign requiring roughly 5 g/dL of deoxygenated hemoglobin, which means a profoundly anemic patient may never become visibly cyanotic despite dangerous hypoxemia.
| Red flag | Why it is urgent | Immediate nursing action |
|---|---|---|
| Stridor at any age | Upper-airway obstruction; the airway can close in minutes | Do not leave the patient; call for rapid response, keep them calm and upright, prepare airway equipment and epinephrine if anaphylaxis is suspected |
| Silent chest in a wheezing asthmatic | Airflow has dropped below the level that generates sound — impending respiratory arrest | Rapid response now; do not reassure the family that the wheezing “got better” |
| SpO2 under 90% on room air, or a drop of 4% or more from the patient’s baseline, not corrected by repositioning and prescribed oxygen | PaO2 is on the steep part of the dissociation curve | Sit upright, apply ordered oxygen, recheck probe placement and waveform, reassess, escalate |
| Adult RR over 28–30/min sustained, or under 8–10/min | Tachypnea is the earliest sepsis marker; bradypnea signals oversedation or rising intracranial pressure | Full set of vitals and mental status; for bradypnea check sedation scale and last opioid dose, hold further doses, have naloxone available per protocol |
| Infant RR over 60/min, grunting, head bobbing, or apnea 20 seconds or more | Infants decompensate quickly and fatigue fast | Escalate immediately; do not wait for a repeat set |
| Tracheal deviation with absent breath sounds, hyperresonance and hypotension | Tension pneumothorax — obstructive shock | Emergency; call rapid response, high-flow oxygen, prepare for needle decompression |
| New subcutaneous crepitus over the chest or neck | Air is dissecting into soft tissue from an airway or pleural leak | Mark and time the borders, assess for pneumothorax, notify the provider |
| Sudden pleuritic chest pain with dyspnea and tachycardia, often with a clear lung exam | Pulmonary embolism — the exam is frequently unimpressive | Oxygen, vitals, do not ambulate, escalate urgently |
| Frank hemoptysis, or pink frothy sputum | Bleeding into the airway; pink frothy sputum indicates flash pulmonary edema | Upright position, oxygen, suction available, escalate |
| Speaking in three-word sentences, tripod position, accessory muscle use | Work of breathing has exceeded reserve; fatigue precedes arrest | Stay with the patient, escalate before the numbers change |
Lifespan and skin-tone variation
Infants and children. The infant chest is round, with an anteroposterior to transverse ratio near 1:1 until about age two, so a “barrel chest” in a toddler is normal. Infants breathe primarily with the diaphragm, so watch the abdomen rise; thoracic breathing establishes around age six or seven. Count for a full 60 seconds, ideally while the infant is quiet or asleep. The chest wall is thin and sounds transmit widely, so bronchovesicular sounds throughout the lung fields are normal in children and would be abnormal in an adult. Retractions, nasal flaring, grunting and head bobbing form the visual distress score you should chart every time. Infants in the early months breathe preferentially through the nose, so nasal congestion alone can cause real distress.
Pregnancy. The enlarging uterus elevates the diaphragm by up to 4 cm, the transverse chest diameter increases about 2 cm and the costal angle widens. Tidal volume rises 30% to 40% under progesterone, so minute ventilation increases while the respiratory rate stays essentially normal. Physiologic dyspnea affects most pregnant patients and is typically mild, gradual and present at rest but not worsening. Sudden dyspnea, tachypnea, chest pain or hypoxemia in pregnancy is never physiologic — pregnancy is a hypercoagulable state and pulmonary embolism is a leading cause of maternal death.
Older adults. Costal cartilage calcifies, kyphosis increases the anteroposterior diameter, respiratory muscles weaken and elastic recoil falls, so chest expansion and diaphragmatic excursion decrease. Cough strength and ciliary clearance decline, which is why immobility so quickly produces atelectasis and pneumonia. Fine crackles at the bases that clear after several deep breaths and a cough are usually atelectatic, not heart failure. Critically, older adults often do not mount a fever or a productive cough with pneumonia — new confusion, a fall, anorexia or simply a rising respiratory rate may be the only presentation. Take a respiratory rate over 24 in an older adult seriously.
Skin tone. Cyanosis, pallor and erythema are unreliable when assessed only on the outer skin of patients with richly pigmented skin. Assess oral mucosa, the tongue, the conjunctivae, the palms and soles and the nail beds in natural or full-spectrum light. Central cyanosis appears as a gray or ashen cast to the lips, tongue and oral mucosa rather than a blue tint. Pallor may present as ashen, gray or yellow-brown rather than white. Erythema is often easier to feel than to see — compare warmth and induration to the opposite side. Be aware also that pulse oximetry systematically overestimates arterial saturation in patients with darker skin pigmentation, producing occult hypoxemia; when the number looks acceptable but the patient is working hard, believe the work of breathing and request an arterial or venous blood gas.
Charting the lung exam
Document what you observed and measured, not what you concluded. Include location, timing, quality, response to cough, position of the patient, oxygen device and flow, saturation, and the patient’s own words in quotation marks. Compare the two entries below.
| Vague and indefensible | Precise and useful |
|---|---|
| “Lungs clear. Patient resting.” | “0800. Resp 18, unlabored, regular; SpO2 97% on room air. Chest symmetric, AP:transverse approx 1:2, no accessory muscle use or retractions. Expansion symmetric. Resonant throughout. Vesicular breath sounds all fields anteriorly, laterally and posteriorly; no adventitious sounds. Trachea midline.” |
| “Crackles heard. Nurse aware.” | “1420. Fine end-inspiratory crackles bilateral posterior bases below the scapular tips, unchanged after cough and two deep breaths. Resp 26 and shallow, SpO2 91% on room air, rising to 95% on 2 L/min nasal cannula. Patient states ‘I feel like I cannot get a full breath.’ Two-pillow orthopnea, new since admission. HOB elevated 45 degrees. Provider notified 1425 — see SBAR note.” |
| “Patient short of breath, given oxygen.” | “2210. Speaking in three-to-four word sentences, tripod position at the bedside, SCM and intercostal accessory use, expiratory wheezes throughout all fields, no stridor. Resp 32, HR 118, SpO2 88% on room air. Oxygen applied at 2 L/min per standing order, SpO2 92%. Rapid response activated 2212.” |
Chart the negatives that matter. “No stridor, no retractions, trachea midline, no accessory muscle use” is not filler — it is the record that proves you looked, and it gives the next shift a true baseline to compare against. A note that says only “lungs clear” cannot show that a patient changed.
Delegation, scope and the SBAR call
Apply the five rights of delegation: right task, right circumstance, right person, right direction and communication, right supervision and evaluation. The registered nurse may delegate data collection tasks on a stable patient but never delegates assessment, interpretation, teaching, evaluation, or any aspect of care for an unstable or deteriorating patient.
| May be delegated to UAP (stable patient, facility policy permitting) | Stays with the RN — never delegated |
|---|---|
| Counting and reporting respiratory rate | Auscultating and interpreting breath sounds |
| Obtaining a pulse oximetry reading and reporting the number | Interpreting a saturation trend and deciding what it means |
| Positioning the patient upright or in semi-Fowler | Titrating oxygen or changing a delivery device |
| Reminding and encouraging a patient to use an incentive spirometer already taught by the RN | Teaching incentive spirometry, pursed-lip breathing or huff coughing for the first time |
| Ambulating a stable patient per the plan of care | Evaluating the response to a nebulizer treatment or to ambulation |
| Reporting observations such as “he sounds noisy” or “she is breathing fast” | Any care of a patient with new dyspnea, stridor, falling saturation or altered mental status |
When a red flag appears, escalate with SBAR. Have the chart, the last two sets of vitals and the medication list in front of you before you dial. A worked example: Situation — “This is Marcus Ellis, RN, on 4 West. I am calling about Mrs. Alvarez in room 412, a 74-year-old two days post right hip arthroplasty. She has new shortness of breath and her oxygen saturation has fallen to 88% on room air.” Background — “She has a history of heart failure and COPD, home oxygen 2 L at night. She has been on bed rest since surgery and has not ambulated today. Baseline saturation on admission was 95% on room air.” Assessment — “Respirations 30 and shallow, heart rate 118, blood pressure 104 over 62, temperature 37.9 Celsius. She is using accessory muscles and speaking in short phrases. Fine crackles at both bases that do not clear with cough, decreased breath sounds at the right base, dullness to percussion there. No stridor, trachea midline. She is more confused than this morning. I have her upright and on 2 L nasal cannula under the standing hypoxia protocol, which brought her to 92%.” Recommendation — “I think she needs to be seen now. I am requesting a chest x-ray, arterial blood gas and an oxygen order, and I would like to know whether you want a rapid response called. Can you come to the bedside?” Then close the loop: repeat the orders back, document the time of the call and the response, and reassess.
Restlessness and a rising respiratory rate precede a falling saturation — escalate on the trend and the work of breathing, using SBAR, before the numbers force your hand.
The chapter in one breath
The thoracic exam is a symmetry test performed in a fixed order: inspection, palpation, percussion, auscultation — with the abdomen standing alone as the exception where auscultation moves ahead of percussion and palpation. Find the sternal angle and the vertebra prominens first, because every finding you report needs a rib level and a reference line, and remember that the posterior chest below the scapular tips is lower lobe while the right middle lobe and lingula are heard only anteriorly and laterally. Count respirations for a full minute when anything is irregular, and hold the numbers in your head: 12 to 20 in an adult, 30 to 60 in a newborn, and a target saturation of 95% to 100% on room air, or 88% to 92% in the patient who retains carbon dioxide. Expect symmetric expansion of 3 to 5 cm, symmetric fremitus, resonance throughout, diaphragmatic excursion of 3 to 5 cm and vesicular breath sounds in the periphery. Consolidation announces itself as dullness, increased fremitus, bronchial breath sounds and a positive E-to-A change. Restlessness, not cyanosis, is the first sign of hypoxia; stridor and a silent chest are emergencies. Chart what you measured, delegate only data collection on stable patients, and escalate with SBAR.
Words worth knowing
| Term | What it means |
|---|---|
| Adventitious sounds | Added sounds superimposed on breath sounds — crackles, wheezes, rhonchi, stridor and friction rubs; never normal. |
| Angle of Louis (sternal angle) | The ridge where the manubrium meets the sternal body, level with the second rib; the starting point for counting ribs and the level of the tracheal bifurcation. |
| Atelectasis | Collapse of alveoli, common after surgery and immobility; produces dullness, decreased breath sounds and crackles that may clear with deep breathing. |
| Barrel chest | Anteroposterior to transverse diameter approaching 1:1 with horizontal ribs and a costal angle over 90 degrees; normal in infants, abnormal in adults. |
| Bronchial breath sounds | Loud, high-pitched, hollow sounds with expiration longer than inspiration; normal over the trachea, a sign of consolidation anywhere else. |
| Bronchophony | Increased clarity of spoken “ninety-nine” heard through consolidated lung. |
| Crackles (rales) | Discontinuous popping sounds from fluid or the sudden opening of collapsed small airways; fine and end-inspiratory, or coarse and wet. |
| Crepitus (subcutaneous emphysema) | A crackling, bubble-wrap sensation under the skin from air in the subcutaneous tissue; always reportable. |
| Diaphragmatic excursion | The distance the diaphragm descends between full expiration and full inspiration, percussed on the posterior chest; expected 3 to 5 cm. |
| Egophony | The E-to-A change: a spoken “eeee” heard as a nasal “aaaa” over consolidated or compressed lung. |
| Fremitus, tactile | Palpable vibration of the voice through the chest wall; increased over consolidation, decreased over air or fluid. |
| Hyperresonance | An abnormally loud, low, booming percussion note over an adult chest, indicating trapped air — emphysema, asthma or pneumothorax. |
| Kussmaul respirations | Deep, rapid, labored and regular breathing that blows off carbon dioxide in severe metabolic acidosis such as diabetic ketoacidosis. |
| Orthopnea | Breathlessness while lying flat, relieved by sitting up; quantified by the number of pillows required. |
| Pleural friction rub | A grating, leathery sound heard on both inspiration and expiration that does not clear with cough, from inflamed pleural surfaces. |
| Resonance | The loud, low-pitched, hollow percussion note of normal air-filled lung. |
| Retractions | Visible inward pulling of soft tissue above the clavicles, between the ribs or below the xiphoid during inspiration; a sign of increased work of breathing. |
| Stridor | A harsh, high-pitched inspiratory crowing audible without a stethoscope, indicating upper-airway obstruction; an emergency at any age. |
| Vesicular breath sounds | Soft, low-pitched sounds with inspiration longer than expiration; the normal finding over peripheral lung fields. |
| Whispered pectoriloquy | Whispered words heard distinctly through the chest wall, the most sensitive voice sign of consolidation. |
Check yourself
Assessing the Heart and Peripheral Vascular System
Cardiovascular disease is the leading cause of death in this country, and the nurse at the bedside is the person most likely to notice it turning. This chapter teaches the cardiac and peripheral vascular exam the way it is actually performed: where the valve areas sit on the chest wall, how to find the apical impulse with your fingertips, how to tell a jugular pulsation from a carotid one, when to use the bell and when the diaphragm, and how to grade a pulse, an edema and a murmur so the next nurse can tell whether the patient improved. You will learn the four-step order — inspection, palpation, percussion, auscultation — and the single exception to it. You will learn the real numbers: heart rate and blood pressure across the lifespan, capillary refill, ankle-brachial index, the size and location of a normal apical impulse. And you will learn which findings do not wait for morning rounds, because a cold pulseless foot and a new S3 in a patient gaining weight are both clocks that have already started.
By the end of this chapter you can
- Trace blood through the chambers and valves of the heart and relate systole and diastole to the production of S1 and S2.
- Locate the aortic, pulmonic, Erb’s point, tricuspid and mitral (apical) auscultatory areas and perform the precordial exam in the correct order — inspection, palpation, percussion, auscultation — naming the abdomen as the one exception.
- Assess the point of maximal impulse, thrills and heaves, and measure jugular venous pressure, distinguishing a jugular from a carotid pulsation.
- State expected heart rate and blood pressure values for the newborn, infant, toddler, preschooler, school-age child, adolescent, adult, pregnant patient and older adult.
- Differentiate normal S1 and S2 from physiologic splitting, S3, S4, murmurs, an opening snap and a pericardial friction rub, and grade a murmur on the six-point scale.
- Grade peripheral pulses and pitting edema, measure capillary refill and interpret the ankle-brachial index.
- Contrast arterial and venous insufficiency and recognize the six Ps of acute arterial occlusion and the signs of deep vein thrombosis.
- Recognize cardiovascular red flags requiring immediate escalation and communicate them using SBAR.
- Document a cardiovascular assessment in precise, defensible language and apply the five rights of delegation to cardiac and vascular tasks.
Section 1The Pump, the Cycle and the Cardiac Baseline
Chambers, valves and the direction of flow
The heart sits in the mediastinum behind the sternum, roughly two thirds of it to the left of the midline, with its broad base up under the second intercostal spaces and its pointed apex down and to the left at about the fifth intercostal space. That orientation is upside down from how students first picture it, and it matters: the valves closest to the base are the ones you hear best at the top of the chest, and the apex — the tip of the left ventricle — is what taps your fingers low on the left chest wall.
Deoxygenated blood returns from the body through the superior and inferior vena cava into the right atrium, crosses the tricuspid valve into the right ventricle, and is pumped through the pulmonic valve into the pulmonary artery and on to the lungs. Oxygenated blood returns through the four pulmonary veins into the left atrium, crosses the mitral valve into the left ventricle, and is ejected through the aortic valve into the aorta. The tricuspid and mitral valves are the atrioventricular valves; the pulmonic and aortic are the semilunar valves. The left ventricle does the systemic work and is therefore the thickest chamber, which is why it is the chamber you can feel and the chamber that hypertrophies under a lifetime of high blood pressure.
The heart is wrapped in the pericardium, a two-layered sac with a thin film of fluid between the layers. When those layers inflame they scrape against each other and produce a friction rub; when fluid accumulates rapidly between them the ventricles cannot fill, which is cardiac tamponade. The coronary arteries branch off the aorta immediately above the aortic valve and fill during diastole, not systole, which is why a very fast heart rate — by shortening diastole — worsens myocardial ischemia even when nothing else changes.
The cardiac cycle and what makes the sounds
Systole is ventricular contraction and ejection; diastole is ventricular relaxation and filling. Diastole is normally the longer of the two at rest, occupying roughly two thirds of the cycle. The heart sounds are not made by valves opening — opening is silent — but by the abrupt deceleration of blood and the vibration of structures when valves close.
S1, the “lub,” is closure of the mitral and tricuspid valves and marks the beginning of systole. It is lower pitched, slightly longer, and loudest at the apex. S2, the “dub,” is closure of the aortic and pulmonic valves and marks the end of systole. It is higher pitched, shorter, and loudest at the base. The interval between S1 and S2 is systole; the longer interval between S2 and the next S1 is diastole. If you cannot tell which sound is which — and at a rate over about 120 you often cannot — palpate the carotid pulse while you listen: the carotid upstroke coincides with S1.
Two more facts turn this into usable clinical information. First, S2 normally splits during inspiration, because negative intrathoracic pressure increases venous return to the right heart, prolongs right ventricular ejection and delays pulmonic closure behind aortic closure. Physiologic splitting is heard best at the second left intercostal space, appears on inspiration and vanishes on expiration, and is a normal finding, most obvious in children and thin young adults. Splitting that persists through expiration, or that widens on expiration, is not normal. Second, the atria contribute a final “atrial kick” of about 20 to 30 percent of ventricular filling at the very end of diastole. When the atria fibrillate, that kick disappears — which is why patients who go into atrial fibrillation often drop their blood pressure, and why an S4, which is generated by atrial contraction, can never exist in atrial fibrillation.
Precordial landmarks and the auscultatory areas
The five listening areas are not directly over their valves. They are the spots on the chest wall where blood flow carries each valve’s sound most clearly, so you must learn them as surface locations, counted from the sternal angle (angle of Louis) exactly as you learned to count ribs in the chest exam.
| Area | Surface location | Sound heard best here |
|---|---|---|
| Aortic | Second intercostal space, right sternal border | S2 louder than S1; aortic stenosis, aortic sclerosis |
| Pulmonic | Second intercostal space, left sternal border | S2 louder than S1; physiologic splitting of S2 is assessed here |
| Erb’s point | Third intercostal space, left sternal border | S1 and S2 roughly equal; aortic regurgitation, many murmurs are audible here |
| Tricuspid | Fourth to fifth intercostal space, left sternal border | S1 louder than S2; tricuspid regurgitation, right-sided S3 and S4 |
| Mitral (apical, PMI) | Fifth intercostal space, left midclavicular line | S1 louder than S2; mitral murmurs, S3 and S4 (use the bell) |
A common mnemonic runs All People Enjoy Time Magazine — aortic, pulmonic, Erb’s, tricuspid, mitral — and it tracks the standard base-to-apex sequence. Move in that order or its reverse, but move in an order and use the same one every time. Do not skip from spot to spot; slide the stethoscope in small steps so you do not miss a murmur that lives between two named areas.
The cardiac baseline: rate, rhythm and pressure
The apical pulse is auscultated at the mitral area with the diaphragm and counted for a full 60 seconds whenever the rhythm is irregular, whenever the patient is an infant or young child, and before administering any medication with a heart-rate parameter. Digoxin is the classic example: hold the dose and notify the provider if the apical rate is under 60 in an adult, under 70 in a child or under 90 in an infant, and always follow the parameters actually written in the order.
A pulse deficit is the difference between the apical rate and the radial rate counted over the same minute. It is measured by two clinicians counting simultaneously, or by counting apical then radial back to back if only one nurse is available, and it means that some ventricular contractions are too weak to generate a peripheral pulse. A deficit is common in atrial fibrillation and with frequent premature ventricular contractions, and it is always the apical rate — never the radial — that is the true heart rate.
| Age group | Expected heart rate (beats/min) | Expected blood pressure (mmHg) | Bedside notes |
|---|---|---|---|
| Newborn (birth to 1 month) | 100–205 awake; 90–160 asleep | Roughly 60–90 systolic | Hypotension if systolic is under 60; brachial or apical pulse only — never assess a carotid in an infant |
| Infant (1–12 months) | 100–180 awake; 90–160 asleep | Roughly 87–105 / 53–66 | Hypotension if systolic is under 70; bradycardia in an infant is usually hypoxia until proven otherwise |
| Toddler (1–2 years) | 98–140 | Roughly 95–105 / 53–66 | Hypotension if systolic is under 70 plus twice the age in years |
| Preschooler (3–5 years) | 80–120 | Roughly 95–110 / 56–70 | Innocent systolic murmurs are common and change with position |
| School-age (6–11 years) | 75–118 | Roughly 97–112 / 57–71 | Pediatric blood pressure norms depend on height percentile as well as age |
| Adolescent (12–18 years) | 60–100 | Roughly 112–128 / 66–80 | Hypotension if systolic is under 90 from age 10 upward |
| Adult | 60–100 | Under 120 and under 80 is normal | Elevated 120–129 and under 80; stage 1 hypertension 130–139 or 80–89; stage 2 at 140 or higher, or 90 or higher |
| Pregnancy | Baseline plus 10–20 (resting 70–90 is typical) | Diastolic falls 10–15 mmHg in the second trimester, returns to baseline by term | 140/90 or higher after 20 weeks is never normal; 160/110 or higher is a severe-range emergency |
| Older adult | 60–100; maximum rate and rate response are blunted | Same targets, but isolated systolic hypertension and a widened pulse pressure are common | May not mount a tachycardia in shock, especially on a beta blocker |
Pulse pressure is systolic minus diastolic and is normally about 30 to 40 mmHg, up to roughly 50. A narrow pulse pressure suggests reduced stroke volume — hypovolemia, heart failure, aortic stenosis, tamponade. A wide pulse pressure suggests stiff arteries in an older adult, or aortic regurgitation, thyrotoxicosis, anemia or fever. Cuff technique changes the number: the bladder width should be about 40 percent of the arm circumference and the bladder length about 80 percent, the arm must be supported at heart level, and the patient should sit quietly for five minutes with the back supported, feet flat on the floor, legs uncrossed, and should not talk during the measurement. An unsupported back raises the diastolic reading and crossed legs raise the systolic reading. A cuff that is too small or too loose reads falsely high; an arm held below heart level reads falsely high; an arm held above heart level reads falsely low.
Orthostatic vital signs are a cardiovascular test, not a courtesy. Measure blood pressure and heart rate after the patient has been supine at least five minutes, then repeat sitting and again standing at one minute and at three minutes. Orthostatic hypotension is a drop of 20 mmHg or more in systolic pressure, or 10 mmHg or more in diastolic pressure, within three minutes of standing; a compensatory rise in heart rate of 20 beats per minute or more is corroborating. Stay with the patient. If they become dizzy or pale, sit them down and abandon the test — you have your answer.
Every heart sound needs a location and a timing before it means anything. “Murmur heard” is not an assessment. “Grade II/VI systolic murmur at the second right intercostal space radiating to the carotids” is an assessment, and it points at one valve. Train yourself to answer three questions about any sound before you chart it: where is it loudest, is it in systole or diastole, and where does it go.
S1 opens systole and is loudest at the apex, S2 closes systole and is loudest at the base — and every murmur you will ever describe is located relative to those two sounds.
Section 2Inspecting and Palpating the Precordium and Neck Vessels
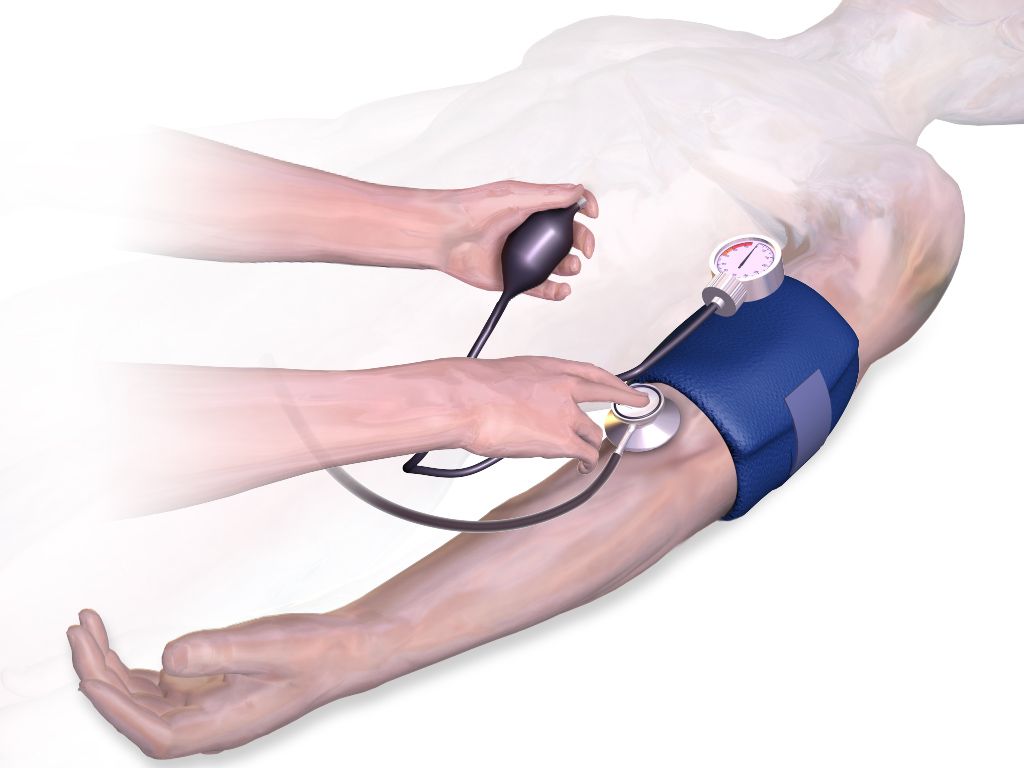
Setting up, and the order of the exam
The cardiovascular exam follows the same fixed sequence as the rest of the body: inspection, palpation, percussion, auscultation. The abdomen is the single exception — there you inspect, then auscultate, then percuss, then palpate, because pressing on the abdomen first alters bowel motility and produces falsely absent or falsely hyperactive bowel sounds. Nothing about the heart uses that modified order.
Position matters more here than anywhere else in the physical exam. Begin with the patient supine with the head of the bed at 30 to 45 degrees, chest exposed, room warm, and stand on the patient’s right side if you can. You will use two more positions later: the left lateral decubitus position, which rolls the apex of the heart toward the chest wall and brings out low-pitched apical sounds such as S3, S4 and the rumble of mitral stenosis; and sitting upright and leaning forward, which brings the base of the heart forward and brings out the soft early-diastolic murmur of aortic regurgitation and a pericardial friction rub. Tell the patient what you are doing and drape a female patient so that only the area being examined is uncovered; when breast tissue overlies the apex, ask the patient to lift the breast or displace it upward yourself with the back of your hand.
Inspection and palpation of the precordium
Inspect with tangential light across the chest so that movement casts a shadow. Look for the apical impulse, which is visible in roughly half of adults and in most thin patients and children, and for any other pulsation, lift or retraction. Note the chest wall itself: pectus excavatum can displace the heart, a median sternotomy scar tells you about prior surgery, and a firm rectangular bulge below the left clavicle is a pacemaker or defibrillator generator, which should be documented along with the site’s appearance.
Now palpate. Use the finger pads for pulsations and the ball of the hand at the base of the fingers for the low-frequency buzzing of a thrill. Palpate systematically at the apex, the left lower sternal border, the left and right second intercostal spaces and the epigastrium. The point of maximal impulse, or PMI, is the apical impulse and normally sits at the fifth intercostal space at or just medial to the left midclavicular line. It is small — about 1 to 2 cm across, no more than the size of a quarter, roughly one interspace — it is a brief gentle tap occupying the first half of systole, and it is easiest to feel with the patient rolled to the left side or in full expiration. If you cannot find it, that alone is not abnormal: obesity, a muscular chest wall, emphysema and large breasts all conceal it.
| Palpation finding | Expected | Abnormal and what it suggests |
|---|---|---|
| PMI location | Fifth intercostal space, at or just medial to the left midclavicular line | Displaced laterally and downward: left ventricular dilation from heart failure or volume overload. Displaced laterally without enlargement: pregnancy, ascites, large pleural effusion, tension pneumothorax pushing the mediastinum |
| PMI size | 1–2 cm, confined to one interspace | Diffuse, over 3 cm or spanning two interspaces: ventricular dilation |
| PMI quality and duration | Brief, gentle tap in early systole | Sustained through systole and forceful: left ventricular hypertrophy from hypertension or aortic stenosis. Hyperdynamic and brief: fever, anemia, anxiety, hyperthyroidism |
| Thrill | None | A palpable, purring, cat-like vibration over a valve area; means turbulent flow and automatically makes any murmur at least grade IV/VI |
| Heave or lift | None | A sustained forceful thrust that lifts your hand. At the left lower sternal border, right ventricular hypertrophy (pulmonary hypertension, COPD, pulmonary embolism). At the apex, left ventricular hypertrophy |
| Epigastric pulsation | Slight, or none; may be normal in thin patients | A wide, forceful, expansile pulsation may indicate an abdominal aortic aneurysm — do not palpate deeply, and report it |
Percussion of the heart is the third step in the sequence, and honesty is owed to students here: it is now rarely performed and has largely been replaced by chest radiography and echocardiography, because percussing the left cardiac border is imprecise and unreliable. It is still taught, and if you perform it you percuss from resonance in the left anterior axillary line medially toward the sternum at the third, fourth and fifth interspaces, listening for the change to dullness, which normally occurs at or medial to the midclavicular line. Cardiac dullness extending well past the midclavicular line suggests cardiac enlargement. Chart what you did and did not perform; do not chart a percussion you skipped.
The neck vessels: carotids and jugular venous pressure
The carotid arteries and internal jugular veins are the two windows onto the heart that sit outside the chest. Assess the carotid arteries one at a time, never both simultaneously — simultaneous compression can reduce cerebral perfusion, and pressure over the carotid sinus can trigger a reflex bradycardia or even asystole in a susceptible patient. Palpate low in the neck, medial to the sternocleidomastoid, below the level of the thyroid cartilage, using light pressure. The normal carotid upstroke is brisk, smooth and symmetric, graded 2+, and it coincides with S1. A weak, slow-rising and delayed upstroke suggests aortic stenosis; a bounding upstroke suggests aortic regurgitation, fever, anemia or hyperthyroidism.
Auscultate the carotids before you palpate them in any patient over about 50, or with known atherosclerosis, hypertension, diabetes, or a history of stroke or transient ischemic attack. Place the bell lightly over each carotid at the angle of the jaw, at the midcervical level and at the base of the neck, and ask the patient to hold their breath briefly so tracheal sounds do not mask what you are listening for. A bruit is a blowing, swishing sound of turbulent flow and requires reporting. Be aware that a bruit does not reliably indicate the degree of stenosis: a tightly narrowed artery may be silent because so little blood is moving through it.
Jugular venous pressure is a direct bedside estimate of right atrial filling pressure and volume status, and it is one of the most useful skills in this chapter. Position the patient at 30 to 45 degrees, turn the head slightly away from the side you are examining, and use tangential lighting. Look for the flickering pulsation of the internal jugular between the two heads of the sternocleidomastoid. Identify the highest point at which the pulsation is visible, then measure the vertical distance in centimeters from that point up from the horizontal plane of the sternal angle. Normal is 3 cm or less above the sternal angle; because the sternal angle sits about 5 cm above the right atrium in any position, that corresponds to a central venous pressure of roughly 8 cm of water or less. A jugular pulsation visible with the patient sitting fully upright at 90 degrees is markedly elevated.
| Feature | Internal jugular vein | Carotid artery |
|---|---|---|
| Palpable? | No — the pulsation is visible only | Yes — a definite palpable thrust |
| Waveform | Undulating, soft, two peaks per cardiac cycle | A single brisk outward stroke per cycle |
| Effect of position | Level falls as the patient sits up, rises as they lie flat | Unchanged by position |
| Effect of light pressure at the base of the neck | Obliterated easily | Not obliterated |
| Effect of respiration | Level normally falls with inspiration | No change |
Elevated jugular venous pressure, commonly charted as jugular venous distention, means the right side of the heart cannot handle its returning volume: right-sided heart failure, fluid overload, tricuspid regurgitation, pulmonary hypertension, cardiac tamponade, constrictive pericarditis or tension pneumothorax. Flat neck veins in a patient lying supine suggest the opposite — hypovolemia. Hepatojugular reflux refines the finding: with the patient at 30 to 45 degrees and breathing normally through an open mouth, press firmly over the right upper quadrant for 10 to 15 seconds. A sustained rise in jugular pressure of more than 3 cm that persists throughout the pressure suggests the right ventricle cannot accommodate additional volume. Stop if the patient reports pain.
If you can feel it, it is the carotid. If you can only see it, it is the jugular. That single rule prevents the most common error on the neck exam, and it also prevents the most dangerous one: pressing on both carotids at once while trying to compare them.
An apical impulse that has moved laterally and become diffuse, a heave at the sternal border, or jugular pulsation more than 3 cm above the sternal angle tell you the heart is failing before any sound does.
Section 3Auscultating the Heart: Normal Sounds, Extra Sounds and Murmurs
Technique: bell, diaphragm, position and sequence
Auscultate on bare skin in a quiet room. Clothing and gowns generate rustling that beginners mistake for murmurs and rubs. Warm the endpiece. Then use both sides of the stethoscope deliberately, because they filter different frequencies: the diaphragm, pressed firmly enough to leave a light ring, transmits high-pitched sounds — S1, S2, most murmurs, and friction rubs. The bell, applied lightly enough that it barely dimples the skin, transmits low-pitched sounds — S3, S4 and the diastolic rumble of mitral stenosis. Pressing the bell firmly stretches the skin beneath it into a diaphragm and eliminates exactly the sounds you were trying to hear, which is why so many students never hear an S3.
Go through all five areas with the diaphragm first, then repeat all five with the bell. At every site, listen for one thing at a time rather than trying to hear everything at once. Identify S1, then S2, then the systolic interval between them, then diastole, and only then listen for extra sounds. Note the rate and the rhythm: regular, regularly irregular (a repeating pattern, as in bigeminy or second-degree block) or irregularly irregular (no pattern at all, the hallmark of atrial fibrillation).
Finally, use the two special positions. Roll the patient into the left lateral decubitus position and listen at the apex with the bell — this is where S3, S4 and mitral stenosis appear. Then sit the patient up, ask them to lean forward and exhale fully and hold, and listen along the left sternal border and at the base with the diaphragm — this is where aortic regurgitation and a pericardial friction rub appear. Skipping these two maneuvers is why soft diastolic murmurs get missed on the unit and found in the cath lab.
S1, S2 and normal variation
At the apex, S1 is louder than S2; at the base, S2 is louder than S1. Both should be crisp. Muffled or distant heart sounds occur with obesity, emphysema, a thick chest wall, and — urgently — with pericardial effusion and cardiac tamponade, where muffled sounds join hypotension and jugular distention to form Beck’s triad. An accentuated S1 occurs with tachycardia, fever, anemia, exercise and mitral stenosis; a diminished S1 occurs with first-degree heart block and with mitral regurgitation. Variable S1 intensity from beat to beat is a clue to atrial fibrillation or complete heart block, because the relationship between atrial and ventricular contraction keeps changing.
Physiologic splitting of S2, described earlier, is normal when it appears on inspiration and disappears on expiration at the pulmonic area. Persistent splitting through both phases, fixed splitting that never varies with respiration (classically atrial septal defect) and paradoxical splitting that appears on expiration and disappears on inspiration (left bundle branch block, severe aortic stenosis) are all abnormal and reportable. A nurse is not expected to name the lesion; a nurse is expected to notice that the second sound is doing something it should not and to describe it accurately.
S3, S4, and the other extra sounds
| Sound | Timing and how it sounds | How to hear it | What it means |
|---|---|---|---|
| S3 (ventricular gallop) | Early diastole, just after S2; low-pitched and dull. Cadence of “Ken-tuc-KY,” the stressed syllable being the extra sound | Bell, lightly, at the apex, patient in left lateral decubitus | Rapid ventricular filling into a volume-overloaded ventricle. Normal in children, in healthy adults up to roughly age 35 to 40, and in pregnancy. After age 40 it is heart failure or volume overload until proven otherwise, and it is often the earliest sign of decompensation |
| S4 (atrial gallop) | Late diastole, just before S1; low-pitched. Cadence of “TEN-nes-see,” the stressed syllable again being the extra sound | Bell, lightly, at the apex, patient in left lateral decubitus | The atrium contracting against a stiff, non-compliant ventricle: hypertension, left ventricular hypertrophy, aortic stenosis, coronary disease, acute myocardial infarction. Common and often benign in older adults. Impossible in atrial fibrillation, because there is no organized atrial contraction |
| Summation gallop | S3 and S4 merging into one loud extra sound at fast rates | Bell at the apex | Tachycardia plus significant ventricular dysfunction — an ominous combination |
| Opening snap | Early diastole, shortly after S2; sharp and high-pitched | Diaphragm, apex to left sternal border | A stenotic mitral valve snapping open; usually followed by the diastolic rumble of mitral stenosis |
| Ejection click | Early systole, just after S1; sharp | Diaphragm, base | A stiffened aortic or pulmonic valve or a dilated great vessel |
| Midsystolic click | Mid to late systole; sharp and clicking, often followed by a late systolic murmur | Diaphragm, apex | Mitral valve prolapse |
| Pericardial friction rub | Scratchy, scraping, leathery; up to three components across the cycle | Diaphragm, left lower sternal border, patient sitting, leaning forward, breath held after exhalation | Pericarditis, including post-myocardial-infarction and uremic pericarditis. Unlike a pleural rub, a pericardial rub persists when the breath is held — that is how you tell them apart |
Learn the two gallops by their rhythm, not by their pitch, because a low-pitched sound is hard for a beginner to isolate but a three-beat cadence is not. If the extra beat falls after the “dub” you have S3; if it falls before the “lub” you have S4. Say the mnemonics aloud in your head while you listen. And note the age rule carefully in both directions: an S3 in a 22-year-old athlete or a pregnant patient at 32 weeks may be entirely physiologic, and an S3 in a 68-year-old who has gained four pounds since yesterday is a phone call.
Murmurs: grading them and describing them
A murmur is the sound of turbulent flow — blood forced through a narrowed valve, leaking backward through an incompetent one, moving through an abnormal opening, or simply moving fast through a normal heart. Intensity is graded on the six-point Levine scale, and the grade is always written as a fraction so the reader knows which scale you used: II/VI, not “grade 2.”
| Grade | What it takes to hear it |
|---|---|
| I/VI | Very faint; heard only after listening carefully for several beats, and not in all positions |
| II/VI | Quiet but heard immediately on placing the stethoscope |
| III/VI | Moderately loud, easily heard; no thrill |
| IV/VI | Loud, with a palpable thrill |
| V/VI | Very loud with a thrill; audible with the stethoscope only partly touching the chest |
| VI/VI | Audible with the stethoscope lifted just off the chest wall |
Grade IV and above always includes a thrill, so palpation and auscultation cross-check each other: if you graded a murmur IV/VI you should be able to feel it, and if you can feel it, it is at least IV/VI. Beyond intensity, describe six more attributes: timing (systolic or diastolic, and where within the phase), location of maximum intensity, radiation, pitch (high, medium, low), quality (blowing, harsh, rumbling, musical) and what changes it (position, respiration, exercise). A single clinical rule is worth memorizing: most systolic murmurs may be benign, but a diastolic murmur is never innocent and always requires evaluation.
| Murmur | Timing and quality | Loudest at | Radiates to | Associated findings |
|---|---|---|---|---|
| Aortic stenosis | Midsystolic, crescendo-decrescendo, harsh | Second right intercostal space | The carotids | Slow-rising weak carotid upstroke, narrow pulse pressure, sustained PMI; exertional syncope, angina and dyspnea are the classic triad |
| Mitral regurgitation | Holosystolic (pansystolic), blowing, high-pitched | Apex | The left axilla | Often an S3; may follow papillary muscle rupture after myocardial infarction |
| Tricuspid regurgitation | Holosystolic, blowing | Left lower sternal border | Right sternal border | Louder on inspiration; jugular distention, peripheral edema, pulsatile liver |
| Mitral valve prolapse | Midsystolic click then late systolic murmur | Apex | Little | Often in young, thin patients; frequently benign |
| Aortic regurgitation | Early diastolic, decrescendo, soft and blowing, high-pitched | Third to fourth left intercostal space | Toward the apex | Best heard — and often only heard — with the patient sitting, leaning forward and holding exhalation, but a soft early-diastolic murmur may still be audible in the routine position and is never dismissed; wide pulse pressure, bounding pulses |
| Mitral stenosis | Mid to late diastolic low rumble after an opening snap | Apex, a small area | Little | Requires the bell and the left lateral decubitus position; associated with atrial fibrillation |
| Innocent or physiologic murmur | Early to midsystolic, soft, grade I–II/VI, musical or vibratory | Left sternal border or pulmonic area | None | Changes markedly with position, disappears on sitting or standing; no thrill, normal S1 and S2, no symptoms. Common in children, fever, anemia, pregnancy, hyperthyroidism |
A murmur you can hear with the diaphragm pressed hard but that vanishes when you switch to a light bell was probably high-pitched all along; a sound that appears only under a light bell and vanishes under pressure is a genuine low-frequency gallop. Practice the switch on a patient known to have an S3 — once your ear has heard one real one, you will find them for the rest of your career.
New murmur plus new symptoms is a different animal from a chronic murmur charted on admission. A new holosystolic murmur at the apex in a patient two days after a myocardial infarction, especially with sudden dyspnea, can be papillary muscle rupture. Do not put it in the note for the day shift to notice — call.
Use the diaphragm firmly for high-pitched sounds and the bell lightly for S3, S4 and mitral stenosis, listen in the left lateral and forward-leaning positions every time, and remember that a diastolic murmur is never innocent.
Section 4The Peripheral Vascular Exam
Arteries: pulses, perfusion and the numbers that go with them
Palpate each pulse with the pads of two or three fingers — never the thumb, which has its own pulse strong enough to fool you — using light pressure that you increase only until you feel the maximum impulse. Assess rate, rhythm, amplitude, contour and symmetry, and always compare the two sides. The sites are temporal, carotid, brachial, radial, ulnar, femoral, popliteal, dorsalis pedis and posterior tibial. In infants, use the brachial pulse for the pulse check, not the carotid, and use the femoral to screen for coarctation of the aorta: a femoral pulse that is weaker than the brachial, or delayed behind it, is a classic sign.
| Grade | Description | Interpretation |
|---|---|---|
| 0 | Absent — no pulse palpable at the site | Occlusion; an emergency if new. Confirm with a Doppler and chart the two findings separately: not palpable but present by Doppler, or absent by Doppler |
| 1+ | Diminished, weak, thready; fades under light pressure | Reduced perfusion: peripheral arterial disease, low cardiac output, hypovolemia |
| 2+ | Normal: brisk, expected, easily palpated | Expected finding |
| 3+ | Increased, full | Hyperdynamic states: fever, anxiety, anemia, exercise, hyperthyroidism |
| 4+ | Bounding; cannot be obliterated by pressure | Aortic regurgitation, severe hypertension, fluid overload |
Facilities differ: some use a 0 to 3+ scale in which 3+ means bounding. Chart with the scale your facility uses and state it, and describe rather than rely on the number alone. When a pulse is not palpable, obtain a Doppler ultrasound probe and document explicitly: “right dorsalis pedis not palpable, present by Doppler” is a materially different finding from “absent by Doppler.” Mark the location of a Doppler-only pulse with a skin pen so the next nurse finds the same spot.
Two anatomic facts prevent unnecessary alarm and unnecessary reassurance. The dorsalis pedis pulse is congenitally absent or anatomically variant in roughly 2 to 10 percent of healthy people, so an isolated absent dorsalis pedis with a strong posterior tibial and warm pink foot is usually benign. The posterior tibial is rarely absent in healthy adults, and both pedal pulses absent in the same foot is abnormal until proven otherwise.
Capillary refill is assessed by compressing a nail bed until it blanches, holding for about five seconds, releasing and counting until color returns, with the hand or foot held at the level of the heart. Normal is under 2 seconds in children and adults; up to 3 seconds is generally accepted in neonates and in a cold room. Prolonged refill suggests poor perfusion, shock, hypothermia or peripheral arterial disease, and it is a soft sign in older adults with chronically thickened nails. The ankle-brachial index (ABI) is the systolic pressure at the ankle divided by the higher of the two brachial systolic pressures, measured with a Doppler: 1.00 to 1.40 is normal, 0.91 to 0.99 is borderline, 0.90 or less indicates peripheral arterial disease, under 0.40 indicates severe disease with a risk of critical limb ischemia, and a value above 1.40 means the vessels are calcified and non-compressible — a falsely reassuring high number seen in long-standing diabetes and renal disease.
The modified Allen test checks ulnar collateral flow before radial artery puncture or cannulation. Have the patient make a tight fist while you occlude both the radial and ulnar arteries, then have them open the hand, which will look pale. Release the ulnar artery only and watch. Color should return to the entire palm within about 5 to 7 seconds; return taking longer than 15 seconds is abnormal and the radial artery on that side should not be used.
Veins, edema and the two kinds of insufficiency
Inspect the legs with the patient both lying and standing. Note varicosities, which are dilated tortuous superficial veins made obvious by standing; note color, hair distribution, nail thickness, temperature compared side to side using the back of your hand, and any ulceration with its exact location, size in centimeters, border and wound-bed appearance. Measure calf circumference at a marked, reproducible point — conventionally 10 cm below the tibial tuberosity — and record the measurement so the next nurse measures the same place. A difference of more than 3 cm between the calves is one of the criteria used in deep vein thrombosis scoring.
Assess pitting edema by pressing firmly with your thumb for at least five seconds over a bony prominence — the dorsum of the foot, behind the medial malleolus, or over the tibia — then removing your thumb and observing the depth and rebound. In a patient on bed rest, also press over the sacrum, because dependent edema follows gravity and will collect there rather than in the feet.
| Grade | Depth of pit | Rebound |
|---|---|---|
| 1+ | About 2 mm; barely perceptible | Immediate |
| 2+ | About 4 mm | About 10 to 15 seconds |
| 3+ | About 6 mm; the extremity looks visibly swollen | More than 1 minute |
| 4+ | About 8 mm; the extremity is grossly distorted | Roughly 2 to 5 minutes |
Edema-grading scales vary between textbooks and facilities, which makes the number alone a weak communication tool. Strengthen it by charting depth in millimeters, the anatomic level to which the edema extends, whether it pits, whether it is unilateral or bilateral, and the rebound time. Non-pitting edema that feels firm or woody is a different problem — lymphedema, chronic venous change or myxedema — and should be described as such rather than forced onto a pitting scale. Daily weight is the most sensitive fluid measure you have: measure at the same time each morning, after voiding, in the same clothing, on the same scale. Each kilogram of gain represents roughly a liter of retained fluid, so a gain of about 1 kilogram, or 2 pounds, in 24 hours or about 2.3 kilograms, 5 pounds, in a week is a reportable threshold in heart failure.
| Feature | Arterial insufficiency | Venous insufficiency |
|---|---|---|
| Pain | Intermittent claudication: cramping calf pain with a predictable amount of walking, relieved by rest. Rest pain is worse when the leg is elevated and relieved by hanging the leg down | Dull ache, heaviness, worse with prolonged standing, relieved by elevation |
| Pulses | Diminished or absent | Present, though hard to feel through swelling |
| Skin color (in richly pigmented skin, judge these on the sole, the nail beds and against the opposite limb, and weigh temperature, pulses and capillary refill more heavily than color) | Pallor on elevation, dependent rubor (dusky red when the leg hangs down; may read as deepened brown or gray rather than red) | Brown hemosiderin staining around the ankles, stasis dermatitis; on darker skin the staining may be barely distinguishable from surrounding tone, so palpate for the firm, thickened texture |
| Temperature | Cool to cold | Warm |
| Skin and nails | Thin, shiny, taut, hairless; thick brittle nails | Thickened, sometimes weeping; hair usually present |
| Edema | Minimal or absent | Present, often marked; improves overnight |
| Ulcer location | Toes, heels, lateral malleolus, over pressure points | Medial malleolus, gaiter area |
| Ulcer appearance and pain | Punched-out, well-defined edges, pale or necrotic base; very painful | Irregular edges, ruddy granulation base, exudate; mildly painful |
| Capillary refill | Prolonged, over 3 seconds | Usually normal |
| Key nursing implication | Never elevate an ischemic leg and never apply compression without an ABI and an order | Elevate above heart level; compression therapy is the mainstay once arterial disease is excluded |
The vascular emergencies
Acute arterial occlusion is memorized as the six Ps: Pain (sudden and severe), Pallor, Pulselessness, Paresthesia, Paralysis and Poikilothermia (the limb takes on room temperature, feeling cold). Pain and pulselessness come first; paresthesia and paralysis are late and signal nerve and muscle death. Pallor is the least reliable of the six in richly pigmented skin — compare the sole, palm and nail beds against the opposite limb, and weigh sudden pain, absent pulses, coolness and numbness far more heavily than color. The limb is generally salvageable for only about six hours, so this is a call-now finding, not an end-of-shift note. The same six Ps drive neurovascular checks after orthopedic surgery, casting or trauma, where they also warn of compartment syndrome — in which the earliest and most reliable sign is pain out of proportion to the injury and pain on passive stretch of the muscle, appearing well before any pulse disappears. A cast that feels tight and a patient asking for more analgesia than the injury explains is an emergency assessment, not a medication question.
Deep vein thrombosis presents as unilateral calf or thigh swelling, warmth, erythema or a dusky discoloration, tenderness along the deep venous course, and sometimes a low-grade fever. Measure and compare calf circumferences and document both numbers. Do not perform Homans sign. Dorsiflexing the foot to elicit calf pain has poor sensitivity and poor specificity, is positive in many patients without thrombosis and negative in many with it, and offers no benefit that justifies manipulating a possibly clotted limb. Assess instead for the constellation of findings, escalate for imaging, and watch for the complication that actually kills: sudden dyspnea, pleuritic chest pain, tachycardia and hypoxemia signaling pulmonary embolism.
Elevation is the fork in the road. Elevating a venous leg drains it and relieves the ache; elevating an arterial leg removes what little gravity-assisted perfusion the foot had and can turn ischemia into necrosis. Before you prop a swollen leg on pillows or apply a compression stocking, ask one question: are the pulses there and is the foot warm?
Compare limb to limb and grade what you feel: a cool, pale, pulseless, painful extremity is an arterial emergency with a six-hour clock, while a warm, swollen, brown-stained ankle with palpable pulses is chronic venous disease.
Section 5Red Flags, Lifespan Variation, Documentation and Escalation
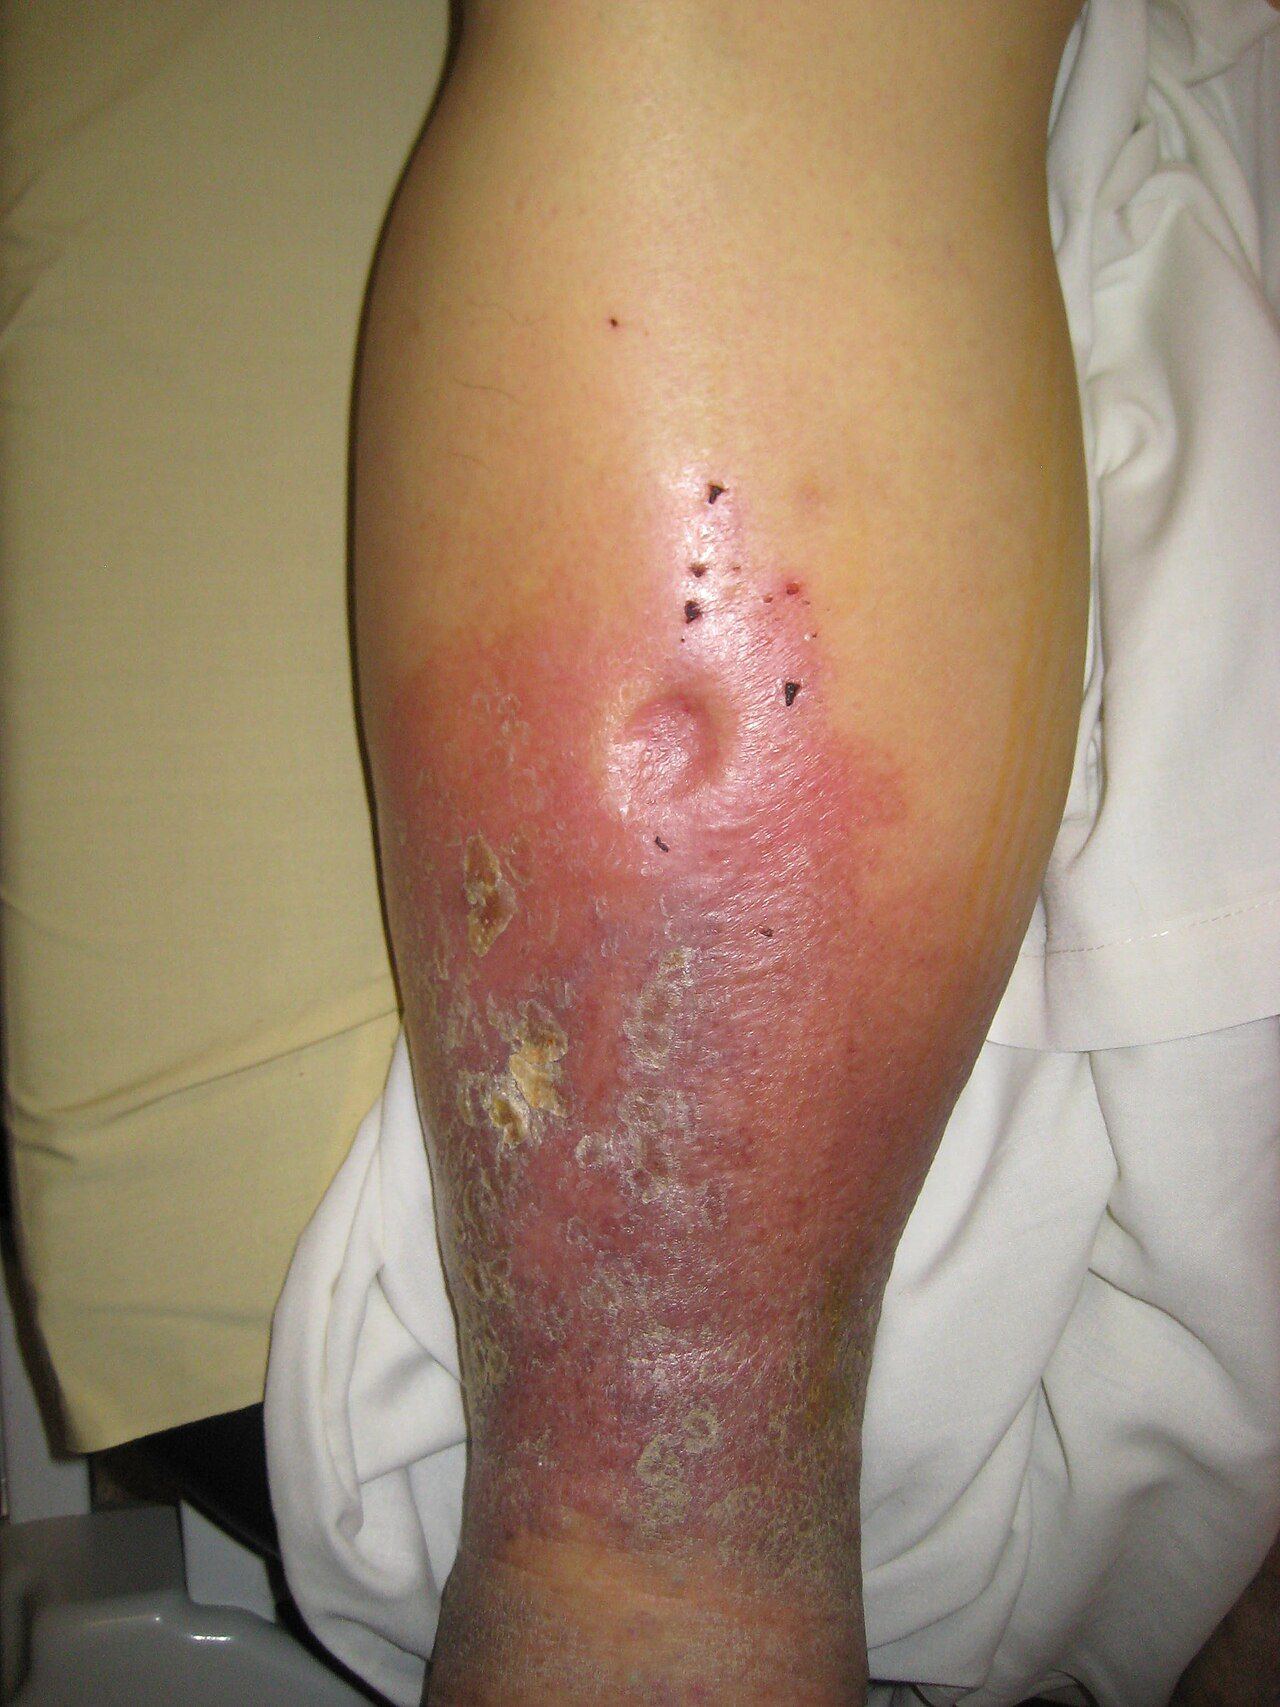
Findings that mean escalate now
Chest pain is assessed with a structured tool — OPQRST: onset, provocation and palliation, quality, region and radiation, severity on a 0 to 10 scale, and timing. But do not let the absence of classic chest pain reassure you. Women, older adults and people with diabetes frequently present with no chest pain at all: unexplained fatigue, dyspnea, nausea, indigestion, diaphoresis, back, jaw or shoulder discomfort, or simply new confusion may be the entire presentation of an acute coronary syndrome. Diabetic neuropathy blunts the pain signal, and a silent infarction is still an infarction.
| Red flag | Why it is urgent | Immediate nursing action |
|---|---|---|
| New or worsening chest pain, pressure or heaviness, especially with diaphoresis, nausea or dyspnea | Acute coronary syndrome; myocardium dies by the minute | Stay with the patient, vital signs, oxygen if saturation is under the ordered target, obtain a 12-lead ECG within 10 minutes, notify the provider, follow the chest-pain protocol for nitroglycerin and aspirin |
| New irregularly irregular rhythm, or a new pulse deficit | New atrial fibrillation with loss of atrial kick and stroke risk | Apical rate for a full minute, blood pressure, mental status and neurologic check, ECG, notify |
| Heart rate under 50 with symptoms, or over 150 | Cardiac output falls at both extremes — too few beats per minute when the rate is slow, and too little diastolic filling time when it is fast | Full vital signs, ECG, assess perfusion and level of consciousness, notify urgently. Before any rate-slowing drug, check the ordered parameters, which usually specify a minimum blood pressure as well as a minimum heart rate; hold the dose and notify if the patient falls outside them |
| Beck’s triad: hypotension, jugular venous distention, muffled heart sounds | Cardiac tamponade — obstructive shock | Emergency. Rapid response, oxygen, large-bore access, prepare for pericardiocentesis |
| New S3 in a patient over 40, plus weight gain, orthopnea or new crackles | Decompensating heart failure — S3 often precedes the crackles | Daily weight, intake and output, upright positioning, oxygen per order, notify before the patient needs intubation |
| Cool, pale, pulseless, painful extremity (six Ps) | Acute arterial occlusion — roughly six hours to save the limb | Do not elevate, do not apply heat or cold, do not massage the limb; keep it at or slightly below heart level, mark pulse sites, keep the patient nothing by mouth pending possible revascularization, notify vascular surgery immediately |
| Pain out of proportion after a cast, fracture or vascular procedure, worse on passive stretch | Compartment syndrome; pulses are preserved until very late | Do not elevate above heart level, do not bivalve a cast on your own authority, notify surgery urgently |
| New unilateral leg swelling, warmth and pain, then sudden dyspnea or pleuritic chest pain | Deep vein thrombosis progressing to pulmonary embolism | Do not massage the calf, oxygen, vital signs, escalate urgently. Hold ambulation only until the patient is evaluated and anticoagulation is started — prolonged bed rest is outdated and once treatment begins early ambulation is safe and encouraged |
| Systolic drop of 20 mmHg or diastolic drop of 10 mmHg on standing, with symptoms | Orthostatic hypotension — a fall and syncope risk | Return the patient to bed, initiate fall precautions, review antihypertensives and diuretics, notify |
| Blood pressure 180/120 or higher with headache, visual change, chest pain, dyspnea or neurologic change | Hypertensive emergency with end-organ damage | Repeat in the other arm, neurologic check, notify immediately — this is not a “recheck in an hour” number |
| Blood pressure 140/90 or higher after 20 weeks of pregnancy, especially with headache, epigastric pain or visual change | Preeclampsia; 160/110 or higher is severe range | Repeat after 15 minutes with correct cuff size, assess reflexes and proteinuria per protocol, notify obstetrics immediately |
| Bleeding or expanding hematoma at a femoral sheath or catheterization site | Arterial bleeding can be rapid and concealed retroperitoneally | Hold direct pressure above the puncture site, keep the leg straight, vital signs, call for help without leaving the patient |
Lifespan and skin-tone variation
Infants and children. The apical impulse sits higher and more laterally the younger the child: in an infant and toddler it is at the fourth intercostal space slightly lateral to the midclavicular line, from about age four to six it is at the fourth space at the midclavicular line, and by roughly age seven it has descended to the adult position at the fifth space at or just medial to the midclavicular line. Sinus arrhythmia — heart rate accelerating with inspiration and slowing with expiration — is a normal, healthy finding in children and young adults. Count apically for a full minute. Innocent murmurs are extremely common in childhood; the reassuring features are grade I to II, systolic only, no radiation, marked change with position, and a completely well child with normal growth. The alarming pediatric findings are a diastolic murmur, a murmur with a thrill, cyanosis — which in a darker-skinned infant will show as a gray or ashen tongue, oral mucosa and nail beds rather than a blue tint, so look in the mouth and not only at the skin — poor feeding, diaphoresis with feeds, failure to thrive, hepatomegaly and weak or delayed femoral pulses. Remember that in infants bradycardia is a hypoxia sign, and that in children hypotension is a very late sign of shock — prolonged capillary refill, cool mottled extremities, weak peripheral pulses and tachycardia come first.
Pregnancy. Blood volume rises 30 to 50 percent, cardiac output rises 30 to 50 percent, resting heart rate rises 10 to 20 beats per minute, and systemic vascular resistance falls so that diastolic pressure drops 10 to 15 mmHg in the second trimester before returning to baseline near term. The heart is displaced upward and to the left, so the apical impulse shifts up and laterally. A soft systolic ejection murmur and an S3 are found in most pregnancies and are physiologic. A diastolic murmur is not. From about 20 weeks, position the patient in a left lateral tilt rather than flat supine, because the gravid uterus compresses the inferior vena cava and can drop cardiac output sharply — supine hypotensive syndrome. Dependent edema of the feet and ankles is expected; sudden facial or hand edema with headache or visual change is preeclampsia until proven otherwise.
Older adults. Arteries stiffen, so systolic pressure and pulse pressure rise and isolated systolic hypertension is common. Ventricular compliance falls, so an S4 is a frequent and often benign finding while an S3 remains ominous. A soft systolic murmur from aortic sclerosis is very common. Baroreceptor reflexes blunt, making orthostatic hypotension and falls more likely, especially with diuretics, antihypertensives and after prolonged bed rest. Maximum heart rate and the ability to mount a tachycardia both decline, and a beta blocker will mask the tachycardia of hemorrhage or sepsis entirely — so a “normal” heart rate of 78 in a septic older adult on metoprolol is not reassurance. Peripheral pulses become harder to palpate as vessels calcify, and the presenting sign of a myocardial infarction may be confusion, a fall, weakness or dyspnea rather than pain.
Skin tone. Color changes central to cardiovascular assessment are unreliable when judged only on the outer skin of patients with richly pigmented skin. Assess the oral mucosa, tongue, lips, conjunctivae, palms, soles and nail beds, in natural or full-spectrum light. Central cyanosis appears as a gray or ashen cast to the lips, tongue and oral mucosa rather than a blue tint, and requires roughly 5 g/dL of deoxygenated hemoglobin — so it is a late sign in anyone and may never appear in a profoundly anemic patient. Pallor may present as ashen, gray or yellow-brown rather than white; check the conjunctivae and palmar creases. Erythema, as in cellulitis or phlebitis, may appear violaceous, deep brown or simply darker than surrounding skin, and is often easier to feel than to see — compare warmth, induration and tenderness against the opposite limb, and outline the border with a skin pen and time it so progression is measurable. Dependent rubor and hemosiderin staining are likewise subtler; rely on temperature, pulses, capillary refill and the pattern of hair loss. Finally, remember that pulse oximetry systematically overestimates arterial saturation in patients with darker skin pigmentation, producing occult hypoxemia; when the number looks acceptable but the patient looks unwell, believe the patient.
Charting the cardiovascular exam
Chart what you measured and observed, not what you concluded. Include rate and rhythm with the method used, the location and character of the apical impulse, the sounds at each area, the murmur description with its grade as a fraction, pulses with their grade and whether Doppler was needed, edema with depth and level, capillary refill, temperature and color of the extremities, jugular venous pressure with the head-of-bed angle, and the patient’s own words in quotation marks.
| Vague and indefensible | Precise and useful |
|---|---|
| “Heart sounds normal. Pulses present.” | “0800. Apical rate 76, regular, counted 60 seconds; radial 76, no pulse deficit. BP 118/72 right arm, sitting, adult cuff. S1 and S2 crisp at all five areas, no S3, no S4, no murmur, no rub. PMI at fifth ICS, left MCL, approximately 2 cm, non-sustained. No heaves or thrills. JVP 2 cm above sternal angle at 45 degrees. Radial, dorsalis pedis and posterior tibial pulses 2+ and equal bilaterally. Extremities warm and dry, capillary refill under 2 seconds, no edema.” |
| “Legs swollen. Elevated.” | “1500. Bilateral pitting edema of both lower legs, 4 mm pits with rebound at approximately 12 seconds, extending to mid-calf; right calf 39 cm, left calf 38.5 cm at 10 cm below the tibial tuberosity. Both feet warm, dorsalis pedis and posterior tibial 2+ bilaterally, capillary refill under 2 seconds. Weight 84.2 kg, up 1.4 kg from 0600 yesterday. New S3 at apex, bell, left lateral position. JVP 5 cm above sternal angle at 45 degrees. Patient states ‘I had to sleep on three pillows last night, I usually use one.’ Legs elevated, provider notified 1508 — see SBAR note.” |
| “Foot looks bad. Will monitor.” | “2140. Right foot pale and cool to mid-calf compared with warm left foot. Right dorsalis pedis and posterior tibial not palpable and not audible by Doppler; left 2+ both sites. Capillary refill right great toe over 5 seconds. Patient reports sudden severe right foot pain rated 9/10 starting at 2120 and new numbness of the toes. Right foot kept level, no heat or cold applied. Rapid response activated 2142, vascular surgery notified.” |
Chart the negatives that matter. “No murmur, no rub, no gallop, no jugular distention, no edema, pulses 2+ and equal” is not filler — it is the record that proves you looked, and it is the baseline that lets the next nurse prove the patient changed. A note reading only “heart sounds normal” cannot show anything.
Delegation, scope and the SBAR call
Apply the five rights of delegation: right task, right circumstance, right person, right direction and communication, right supervision and evaluation. The registered nurse may delegate routine data collection on a stable patient, but never delegates assessment, interpretation, teaching, evaluation, or any aspect of care for an unstable or deteriorating patient. Delegating the task never transfers accountability for the outcome.
| May be delegated to UAP (stable patient, facility policy permitting) | Stays with the RN — never delegated |
|---|---|
| Measuring blood pressure with an automated cuff and reporting the number | Interpreting a blood pressure trend and deciding whether to hold an antihypertensive |
| Counting and reporting a radial pulse | Auscultating an apical pulse, identifying a rhythm, and measuring a pulse deficit |
| Applying antiembolism stockings or sequential compression devices already ordered and sized | Deciding whether compression is safe — that requires an arterial assessment |
| Obtaining a daily weight and recording intake and output | Interpreting a 1.4 kg overnight weight gain and its implication for heart failure |
| Repositioning, elevating legs per the established plan of care, ambulating a stable patient | Doppler pulse assessment, neurovascular checks, capillary refill interpretation |
| Reporting observations such as “his legs look more swollen” or “she felt dizzy standing up” | Teaching about sodium restriction, daily weights or anticoagulants; care of any patient with chest pain, new dysrhythmia or a compromised limb |
When a red flag appears, escalate with SBAR. Have the chart, the last two sets of vital signs, the medication list and the most recent laboratory values in front of you before you dial. A worked example: Situation — “This is Priya Raman, RN, on 6 East. I am calling about Mr. Whitfield in room 618, a 71-year-old admitted two days ago with a heart failure exacerbation. He has new orthopnea and his weight is up 1.4 kilograms since yesterday morning.” Background — “He has a history of ischemic cardiomyopathy with an ejection fraction of 30 percent, hypertension and chronic kidney disease. He is on furosemide 40 milligrams IV twice daily, metoprolol and lisinopril. Admission weight was 82.8 kilograms; this morning he is 84.2. Baseline blood pressure has been running around 118 over 70.” Assessment — “Apical rate 104 and regular, blood pressure 102 over 64, respirations 26, SpO2 91 percent on room air rising to 95 percent on 2 liters nasal cannula. He now has an S3 at the apex that was not there yesterday, jugular venous pressure 5 centimeters above the sternal angle at 45 degrees, bilateral pitting edema to mid-calf at 4 millimeters, and fine crackles at both bases that do not clear with cough. He needed three pillows last night instead of one. Urine output has been 20 milliliters an hour for the last four hours. Pedal pulses are 2 plus and both feet are warm.” Recommendation — “I think he is decompensating and I would like him seen now. I am requesting an additional diuretic dose, a basic metabolic panel and BNP, a chest x-ray, and an order for oxygen to keep his saturation above 92 percent. Do you want strict intake and output and a repeat weight this evening? Can you come to the bedside?” Then close the loop: read the orders back, document the time of the call and the response, and reassess after the intervention.
A new S3, a rising weight, a new irregular rhythm or a limb that has lost its pulse are all escalation events — assess, measure, and call with SBAR rather than waiting for the next scheduled round.
The chapter in one breath
The cardiovascular exam follows the same fixed order as the rest of the body — inspection, palpation, percussion, auscultation — with the abdomen standing alone as the exception where auscultation moves ahead of percussion and palpation. Count ribs from the sternal angle to find the aortic, pulmonic, Erb’s point, tricuspid and mitral areas, and remember that S1 closes the AV valves and opens systole at the apex while S2 closes the semilunar valves and ends systole at the base. Hold the real numbers: adult heart rate 60 to 100 and blood pressure under 120 over 80, newborn heart rate 100 to 205, an apical impulse 1 to 2 cm at the fifth intercostal space and left midclavicular line, jugular pulsation no more than 3 cm above the sternal angle at 30 to 45 degrees, capillary refill under 2 seconds, pulses 2+ and symmetric, and an ankle-brachial index of 1.00 to 1.40. Use the diaphragm firmly for high-pitched sounds and the bell lightly at the apex in the left lateral position for S3 and S4, and never dismiss a diastolic murmur. In the limbs, cool and pulseless and painful means arterial and never elevate; warm and swollen and brown-stained means venous and elevate. Chart what you measured, delegate only routine data collection on stable patients, and escalate with SBAR.
Words worth knowing
| Term | What it means |
|---|---|
| Ankle-brachial index (ABI) | Ankle systolic pressure divided by the higher brachial systolic pressure; 1.00 to 1.40 is normal, 0.90 or less indicates peripheral arterial disease, and above 1.40 indicates non-compressible calcified vessels. |
| Beck’s triad | Hypotension, jugular venous distention and muffled heart sounds — the classic combination of cardiac tamponade. |
| Bruit | A blowing or swishing sound of turbulent arterial flow, heard with the bell over a carotid, femoral, renal or aortic vessel; always reported. |
| Capillary refill | Time for color to return to a compressed nail bed held at heart level; normally under 2 seconds in adults and children, up to 3 seconds in neonates. |
| Claudication | Reproducible cramping muscle pain brought on by a predictable amount of walking and relieved by rest; the hallmark symptom of peripheral arterial disease. |
| Dependent rubor | Dusky red discoloration of a foot when it hangs down, with pallor on elevation; a sign of chronic arterial insufficiency. |
| Erb’s point | The third intercostal space at the left sternal border, where S1 and S2 are roughly equal and many murmurs are audible. |
| Hepatojugular reflux | A sustained rise in jugular venous pressure of more than 3 cm during 10 to 15 seconds of firm right upper quadrant pressure, suggesting the right ventricle cannot accept more volume. |
| Jugular venous pressure (JVP) | The vertical height of the internal jugular pulsation above the sternal angle with the head of the bed at 30 to 45 degrees; normally 3 cm or less. |
| Levine scale | The six-point murmur intensity scale, written as a fraction; grade IV/VI and above always includes a palpable thrill. |
| Point of maximal impulse (PMI) | The apical impulse, normally 1 to 2 cm at the fifth intercostal space at or just medial to the left midclavicular line; displaced laterally and downward in left ventricular dilation. |
| Pulse deficit | The difference between the apical and radial rates counted over the same minute; indicates contractions too weak to perfuse the periphery, as in atrial fibrillation. |
| Pulse pressure | Systolic minus diastolic pressure, normally about 30 to 40 mmHg; narrow with low stroke volume, wide with stiff arteries or aortic regurgitation. |
| S1 | Closure of the mitral and tricuspid valves; the beginning of systole, loudest at the apex. |
| S2 | Closure of the aortic and pulmonic valves; the end of systole, loudest at the base, normally split on inspiration. |
| S3 (ventricular gallop) | A low-pitched early diastolic sound heard with the bell at the apex; physiologic under about age 40 and in pregnancy, a sign of volume overload and heart failure after that. |
| S4 (atrial gallop) | A low-pitched late diastolic sound from atrial contraction against a stiff ventricle; impossible in atrial fibrillation. |
| Six Ps | Pain, pallor, pulselessness, paresthesia, paralysis and poikilothermia — the signs of acute arterial occlusion, with roughly a six-hour window to save the limb. |
| Thrill | A palpable purring vibration over a valve area from turbulent flow; its presence makes a murmur at least grade IV/VI. |
| Heave (lift) | A sustained forceful precordial thrust that lifts the palpating hand; suggests ventricular hypertrophy. |
Check yourself
ASSESSING THE ABDOMEN, NUTRITION AND ELIMINATION
The abdomen is the one region where the four-step examination sequence you have used all semester changes: you inspect, then auscultate, then percuss, then palpate — because pressing on the belly first stirs the bowel and gives you sounds that were never really there. That single reordering is the signature of this chapter, and it is also a promise about how everything else here works: the abdomen does not announce itself the way a lung field or a pulse does. It hides a ruptured appendix behind a low-grade fever, a two-liter bladder behind restlessness, and a slow gastrointestinal bleed behind one dark stool nobody looked at. Nutrition and elimination belong in the same chapter because they are the abdomen’s inputs and outputs: what a patient can safely swallow, what their body did with it, and what came back out. You will learn the sequence, the numbers, the words to chart, and the findings that mean you pick up the phone now.
By the end of this chapter you can
- Map the four quadrants and nine regions of the abdomen and name the organs that lie beneath each.
- Perform the abdominal examination in the correct order — inspection, auscultation, percussion, palpation — and explain why auscultation moves ahead of percussion and palpation here and nowhere else.
- Distinguish expected from abnormal findings for contour, bowel sounds, bruits, percussion tones, liver span and palpation, and state what each abnormal finding suggests.
- Demonstrate focused maneuvers — Murphy sign, McBurney point, Rovsing sign, psoas, obturator, shifting dullness and fluid wave — and name the situations in which deep palpation is contraindicated.
- Screen nutritional status using BMI, waist circumference, percentage of unintentional weight loss, intake history and laboratory data, and explain why albumin is an inflammation marker rather than a nutrition marker.
- Carry out aspiration and enteral-feeding safety measures, including dysphagia screening, head-of-bed elevation and correct verification of feeding-tube placement.
- Assess bowel and urinary elimination using the Bristol Stool Form Scale, intake and output, daily weight, bladder scanning and post-void residual volumes, with age-appropriate values.
- Describe how abdominal, nutritional and elimination findings differ in infants, children, pregnancy and older adults, and how jaundice, pallor, cyanosis and erythema present across the full range of skin tones.
- Recognize the abdominal red flags that require immediate escalation, communicate them using SBAR, and distinguish tasks that may be delegated to UAP from those that remain with the registered nurse.
Section 1Mapping the Abdomen and Setting Up the Exam
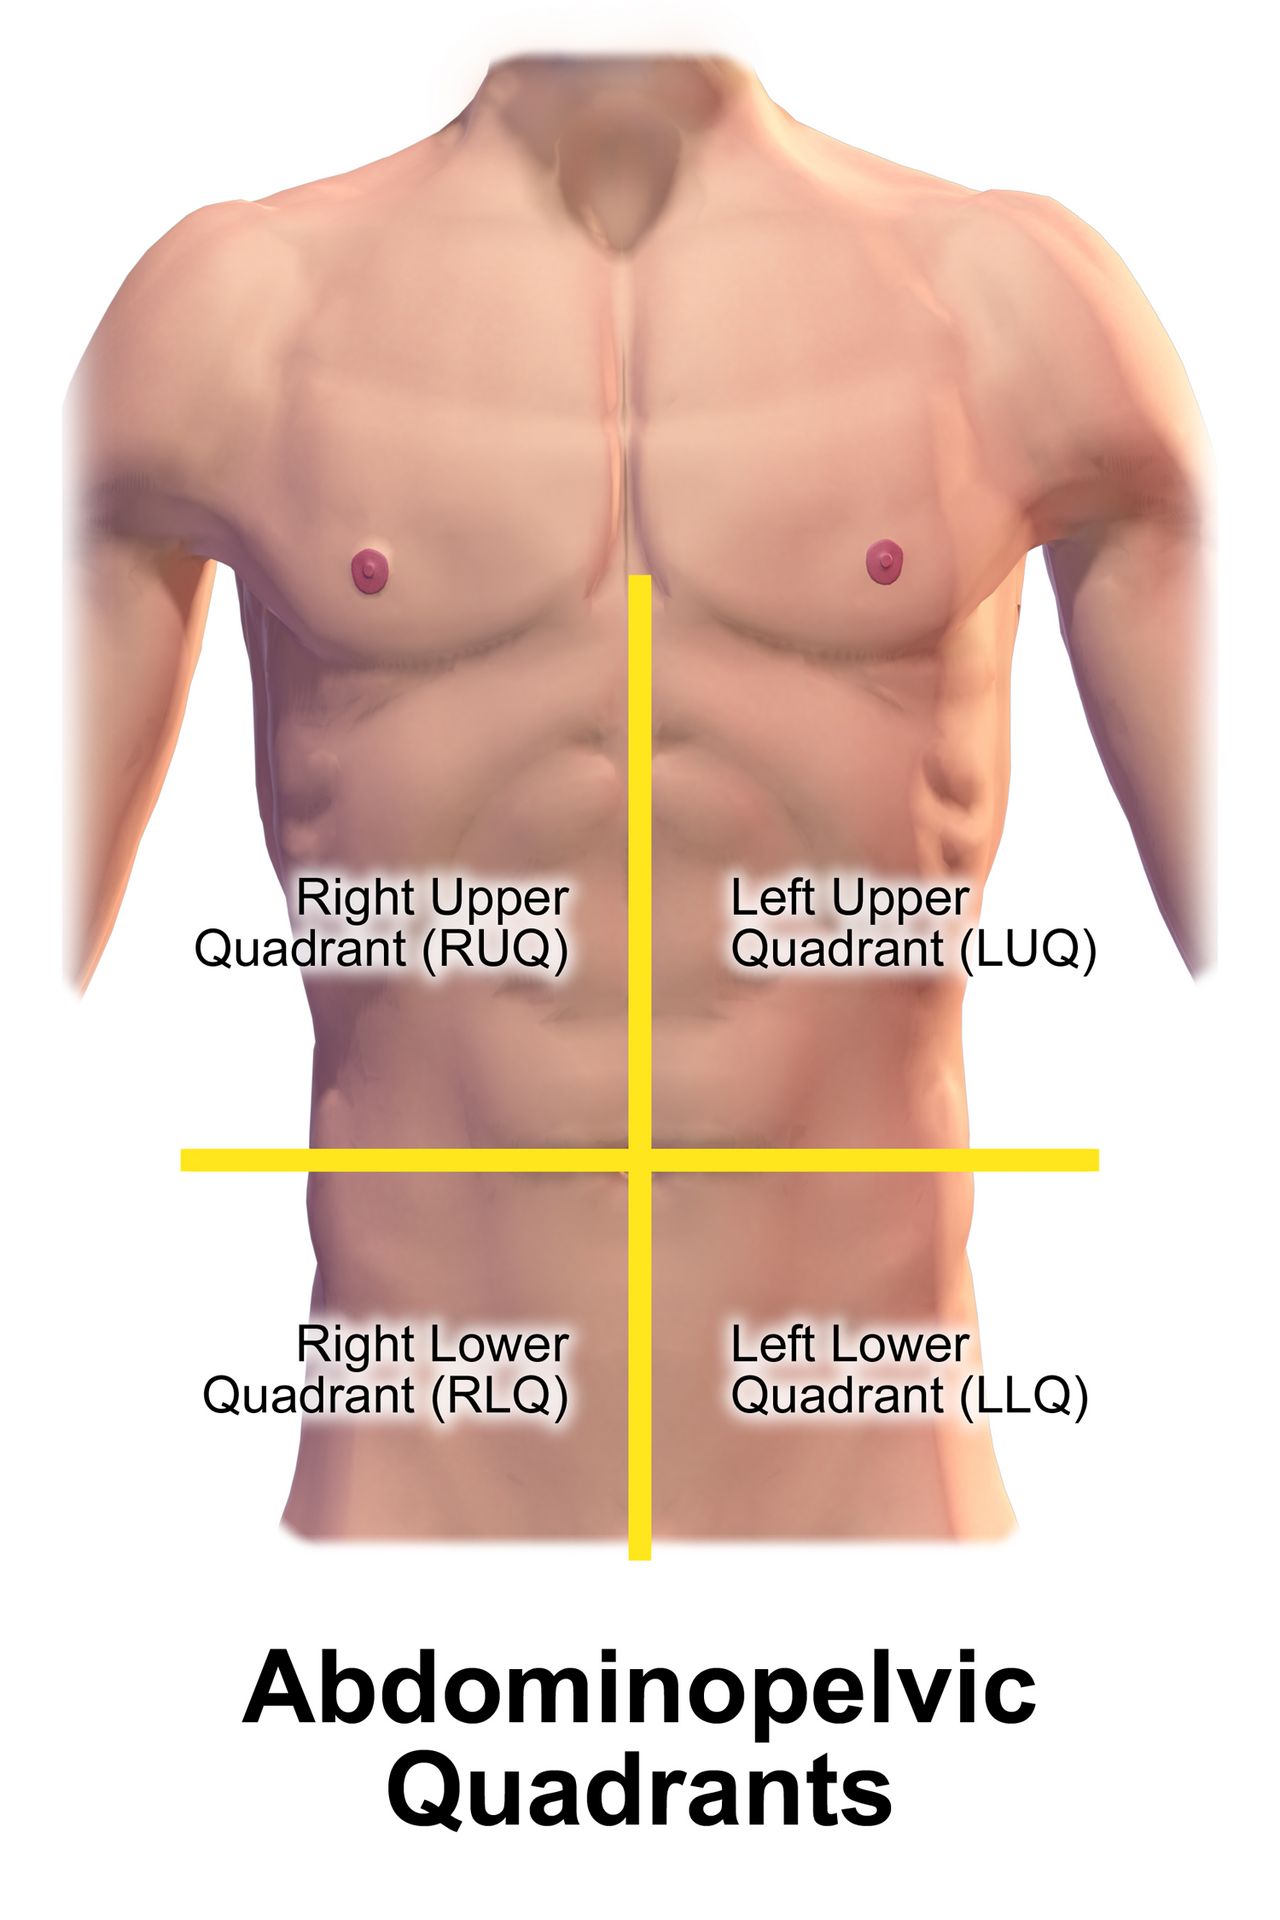
Quadrants, regions and what lives beneath
Draw two imaginary lines through the umbilicus — one vertical from the xiphoid process to the symphysis pubis, one horizontal — and you have the four quadrants that nurses use for charting and for handoff. This is the map you will speak in. When you tell a provider “tenderness in the right lower quadrant, guarding present,” you have said something anatomically specific in five words. When you say “the patient’s stomach hurts,” you have said nothing at all. The nine-region map (epigastric, umbilical, hypogastric or suprapubic down the midline; right and left hypochondriac, lumbar and inguinal on the sides) is more precise and appears in medical documentation and imaging reports, so you must be able to read it even if you chart in quadrants.
Underneath the surface, the organs are not evenly distributed, and knowing which structure sits where is what turns a location into a hypothesis. Right upper quadrant pain in a patient after a fatty meal points toward the gallbladder. Left upper quadrant pain after a bicycle-handlebar injury points toward the spleen. Midline suprapubic fullness in a patient who has not voided in eight hours points toward a distended bladder, not constipation. Pain also refers: gallbladder disease refers to the right scapula, splenic irritation to the left shoulder (Kehr sign), pancreatic pain straight through to the back, and ureteral colic from the flank down into the groin.
Two structures deserve a standing caution. The abdominal aorta runs just left of midline in the epigastric region; in an average-size adult it should measure less than 3 cm across and should pulsate forward, not sideways. A wide, expansile, laterally pulsating mass is a suspected abdominal aortic aneurysm, and you do not palpate deeply over it — you stop, take vital signs, and escalate. The other is any known or suspected abdominal mass in a child, particularly a Wilms tumor, which is never palpated repeatedly because of the theoretical risk of seeding tumor cells. Post a sign at the bedside if that diagnosis is under evaluation.
| Quadrant | Major structures beneath | Findings that commonly localize here |
|---|---|---|
| Right upper (RUQ) | Liver, gallbladder, duodenum, head of pancreas, right kidney and adrenal, hepatic flexure of colon | Cholecystitis (positive Murphy sign), hepatitis, hepatomegaly, duodenal ulcer, right lower lobe pneumonia referring down |
| Left upper (LUQ) | Stomach, spleen, left lobe of liver, body and tail of pancreas, left kidney and adrenal, splenic flexure | Splenomegaly or splenic rupture, gastritis, pancreatitis, gastric ulcer |
| Right lower (RLQ) | Cecum, appendix, right ovary and tube, right ureter, right spermatic cord | Appendicitis, ovarian cyst or torsion, ectopic pregnancy, ureteral stone, Crohn disease of the terminal ileum |
| Left lower (LLQ) | Sigmoid colon, descending colon, left ovary and tube, left ureter | Diverticulitis, constipation, ovarian pathology, ureteral stone |
| Midline | Abdominal aorta, bladder, uterus (when enlarged), umbilicus | Aortic aneurysm, urinary retention, pregnancy, umbilical hernia |
Positioning, exposure and the order that protects your findings
Set the room up before you touch anyone. Ask the patient to empty the bladder first — a full bladder is uncomfortable, distorts the suprapubic exam and makes a percussion finding you will then have to explain away. Position the patient supine with a small pillow under the head and another under slightly flexed knees; this relaxes the abdominal wall. Arms go at the sides or folded across the chest, never behind the head, which tightens the rectus muscles and manufactures rigidity you will misread as guarding. Drape so the abdomen is exposed from the xiphoid to the symphysis pubis while the chest and groin stay covered. Warm your hands and your stethoscope diaphragm, keep your fingernails short, and use a low light angled across the abdomen so contour and peristaltic waves cast shadows.
Now the sequence, and this is the paragraph to memorize. Everywhere else in the body you inspect, palpate, percuss and auscultate. In the abdomen you inspect, auscultate, percuss and palpate. The reason is mechanical: percussion and palpation stimulate the bowel and change its motility, so sounds heard afterward tell you about your own hands rather than about the patient. Auscultating before you press preserves the baseline. Two further ordering rules follow from patient comfort: examine the painful quadrant last, and if you perform a test for rebound tenderness, perform it at the very end, because it hurts and it will make everything after it uninterpretable.
Ask the patient to point with one finger to where it hurts before you begin. Watch the face, not the hand, during palpation — a patient who has been told to be brave will wince before they will complain. Talk the whole way through: “I am going to press lightly here, tell me the moment it is uncomfortable.” If the patient tenses, distract with conversation or ask them to breathe out slowly through the mouth; voluntary guarding relaxes with distraction, while involuntary guarding from peritoneal irritation does not. That distinction is one of the most clinically useful things in this chapter.
The focused history that steers the exam
The abdominal history is where most of the diagnostic yield lives, and it is nursing work, not something you wait for the provider to do. Use a structured symptom analysis — OLDCARTS (onset, location, duration, characteristics, aggravating factors, relieving factors, timing, severity) or PQRSTU — and then add the abdomen-specific questions: appetite and any change in it, nausea or vomiting and what the vomitus looked like, last oral intake, last bowel movement and its form and color, flatus (a patient who is passing gas is far less likely to be obstructed), urinary frequency, urgency, burning and stream, weight change over the last one, three and six months, alcohol intake, NSAID and anticoagulant use, and abdominal surgeries. In anyone of childbearing potential, ask the date of the last menstrual period and the possibility of pregnancy — a ruptured ectopic pregnancy presents as lower abdominal pain and can kill within hours.
Characterize the pain itself, because the quality maps onto the anatomy. Visceral pain arises from a hollow organ stretching or contracting; it is dull, crampy, poorly localized and often midline, and the patient moves around trying to find a comfortable position. Parietal (somatic) pain arises when the parietal peritoneum is inflamed; it is sharp, well localized, worse with movement or coughing, and the patient lies very still with knees drawn up. A patient who has gone from restless crampy midline pain to lying rigidly still with sharply localized pain has told you the process has reached the peritoneum. Referred pain is felt at a distance from its source and travels a predictable route.
Pain that is dramatically out of proportion to what you find on examination is its own alarm. A patient in atrial fibrillation who reports severe, unrelenting periumbilical pain while the abdomen feels soft and nearly normal may have acute mesenteric ischemia, and the soft abdomen is falsely reassuring. Trust the mismatch, not the palpation.
In the abdomen and only in the abdomen, auscultation comes before percussion and palpation, the painful area is examined last, and the history — pain quality, last bowel movement, last oral intake, pregnancy possibility — tells you what to look for before your hands ever touch the patient.
Section 2Inspection and Auscultation
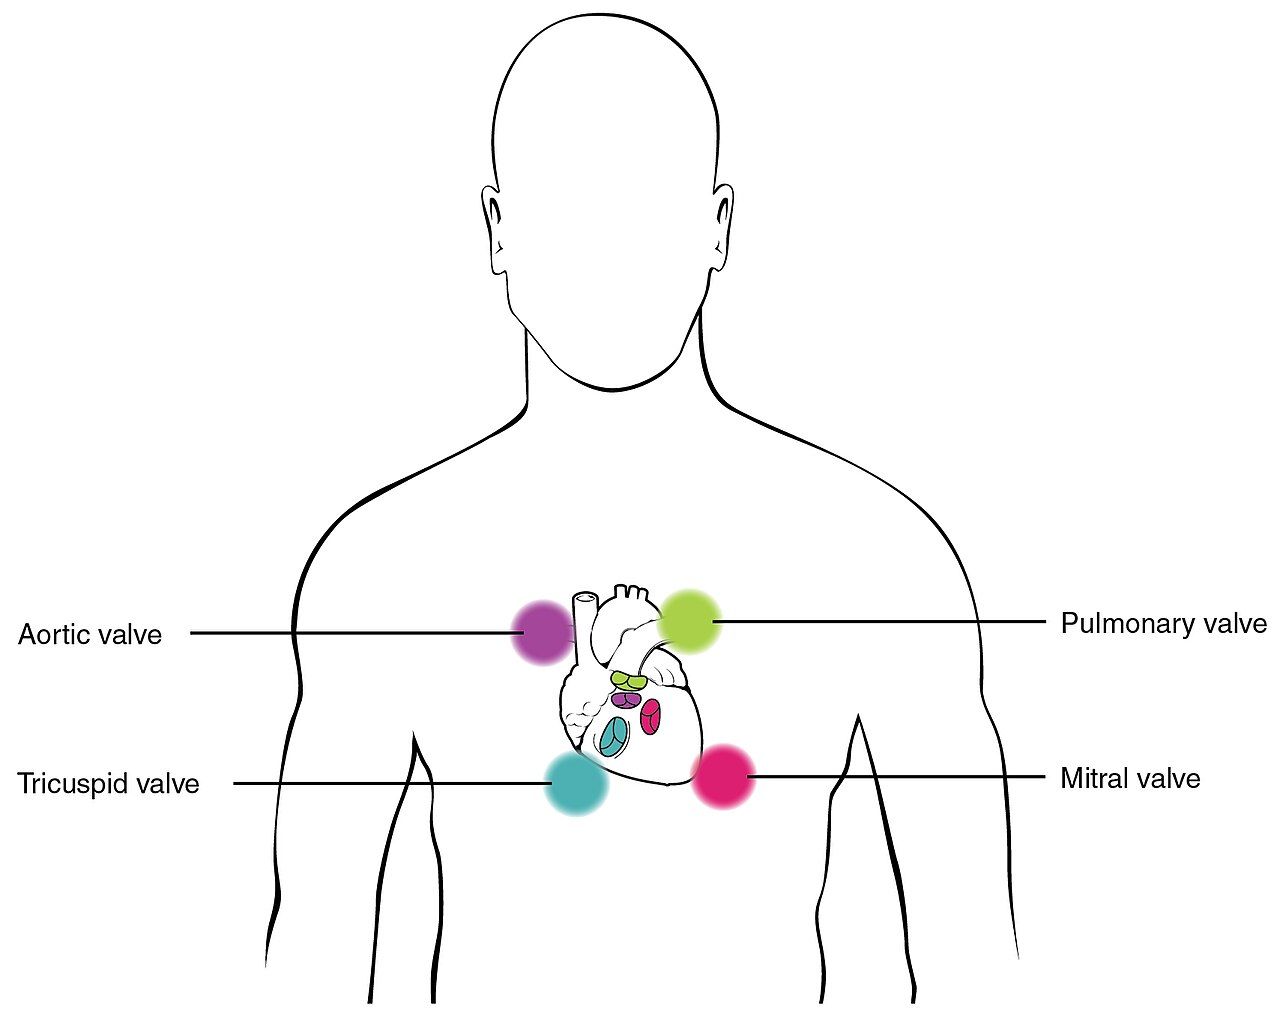
Inspection: contour, symmetry, skin and movement
Stand at the patient’s right side and then squat so your eyes are level with the abdomen; a flat contour and a distended one look identical from above and completely different from the side. Describe contour as flat, rounded, scaphoid (sunken, seen in significant weight loss and in dehydration) or protuberant. Then look for symmetry across the midline, because an asymmetric bulge is a mass, a hernia, an enlarged organ or a loop of obstructed bowel until proven otherwise. Ask the patient to lift the head off the pillow: a bulge that becomes more prominent is in the abdominal wall (hernia, diastasis recti), while one that disappears is intra-abdominal.
Inspect the skin systematically. Note scars and map them — every previous abdominal operation is a risk factor for adhesive small-bowel obstruction, and a scar is often the only history a nonverbal patient can give you. Striae that are silvery white are old and expected after pregnancy or weight change; striae that are wide, purple and accompanied by central obesity and a rounded face suggest hypercortisolism. Dilated, tortuous veins radiating from the umbilicus (caput medusae) and spider angiomas suggest portal hypertension. Periumbilical bruising (Cullen sign) and flank bruising (Grey Turner sign) are late signs of retroperitoneal or intraperitoneal bleeding, classically severe hemorrhagic pancreatitis, and they are always an escalation. In deeply pigmented skin neither reads as the textbook blue-purple bruise: look for an area that is darker, duller or violet compared with the surrounding skin and with the same site on the opposite side, use good direct light, and palpate for the tenderness, warmth and induration that go with it.
Watch for movement. Normal respiratory movement is smooth; men breathe more abdominally, women more thoracically. Visible peristaltic waves crossing the abdomen are abnormal in an adult and suggest intestinal obstruction — the bowel is straining against a blockage. In an infant, a wave crossing left to right with projectile, non-bilious vomiting and a firm olive-shaped mass in the right upper quadrant suggests hypertrophic pyloric stenosis. A visible pulsation in the epigastrium may be normal in a thin patient, but a wide, forceful, side-to-side pulsation is not.
| Inspection finding | Expected | Abnormal | What the abnormal suggests |
|---|---|---|---|
| Contour | Flat or rounded, symmetric | Distended, taut, asymmetric bulge, scaphoid | Ascites, obstruction, obesity, mass, organomegaly; scaphoid with severe malnutrition or dehydration |
| Umbilicus | Midline, inverted, no drainage | Everted, displaced, bulging, drainage | Everted with ascites or umbilical hernia; drainage with infection or fistula |
| Skin | Uniform with the patient’s skin tone, silvery striae, healed scars | Purple striae, caput medusae, Cullen or Grey Turner sign, spider angiomas, jaundice | Hypercortisolism, portal hypertension, retroperitoneal bleeding, hepatic disease |
| Movement | Smooth respiratory rise and fall; no visible peristalsis | Visible peristaltic waves; limited movement with splinting | Bowel obstruction, pyloric stenosis in an infant; peritonitis when the patient will not move the abdomen |
| Pulsation | Faint epigastric pulsation in a thin adult | Wide, expansile, laterally pulsating epigastric mass | Abdominal aortic aneurysm — stop, do not palpate deeply, escalate |
Bowel sounds: how long to listen and what to call it
Use the diaphragm of the stethoscope, warmed, and press lightly. Begin in the right lower quadrant, where the ileocecal valve reliably produces sound, then move clockwise: RLQ, RUQ, LUQ, LLQ. For a routine assessment, listen 15 to 30 seconds in each quadrant. Normal bowel sounds are high-pitched, irregular gurgles occurring roughly 5 to 30 times per minute; you should not try to count each one, because they run together. Chart them as present and active in all four quadrants. If you hear nothing in a quadrant, you must listen in that one spot for a full 5 minutes before you may document sounds as absent. “Absent bowel sounds” charted after ten seconds of listening is not an assessment; it is a guess that may prompt a nasogastric tube the patient does not need.
Hypoactive sounds are soft and infrequent (fewer than about 5 per minute). They are expected in the immediate postoperative period and with general anesthesia, opioids, immobility and hypokalemia; they also occur with paralytic ileus and with peritonitis, which are not benign, so never read them apart from the rest of the assessment. Hyperactive sounds are loud, rushing, high-pitched and frequent; you hear them with gastroenteritis, diarrhea, laxatives, gastrointestinal bleeding (blood in the gut is a cathartic) and in early mechanical obstruction. The clinically dangerous pattern is loud, high-pitched, tinkling or rushing sounds proximal to a blockage in a patient with distension and vomiting, which later fade to silence as the bowel fatigues. Hyperactive-then-absent in a distended, vomiting patient is a surgical emergency, not an improvement.
Two sounds are not bowel sounds and are worth naming. Borborygmi are the prolonged, loud, hyperperistaltic rumbles a patient will call “stomach growling” and are usually benign. A succussion splash — a sloshing you elicit by rocking the patient gently at the hips several hours after eating — suggests retained gastric contents from gastric outlet obstruction or gastroparesis.
Vascular sounds and friction rubs
Switch to the bell and listen for vascular sounds, which are lower pitched. A bruit is a blowing, swishing sound of turbulent arterial flow. Listen over the aorta in the epigastrium just left of midline, over each renal artery about 2 to 3 cm above the umbilicus and 2 to 3 cm lateral to it, over the iliac arteries partway between the umbilicus and the inguinal ligament, and over the femoral arteries in the groin. A bruit over the aorta with a widened pulsatile mass supports an aneurysm; a renal artery bruit in a patient with poorly controlled hypertension raises renovascular disease. A venous hum, a soft continuous humming near the umbilicus, suggests increased collateral circulation from portal hypertension. A friction rub — a grating sound over the liver or spleen that varies with respiration — suggests inflammation of the organ’s peritoneal surface, as with a tumor, abscess or infarct, and is rare and always significant.
Auscultation also has a role after abdominal surgery beyond bowel sounds: listen over a new ostomy or drain site if the patient reports a change, and always inspect a dressing and incision line during the same encounter. In pregnancy, fetal heart tones are auscultated with a Doppler over the lower abdomen, expected at 110 to 160 beats per minute; that is a different examination but shares the same real estate.
Auscultate with the diaphragm in all four quadrants starting at the right lower quadrant, use 5 full minutes in one spot before ever charting bowel sounds as absent, then switch to the bell for bruits over the aorta, renal, iliac and femoral arteries.
Section 3Percussion, Palpation and Focused Maneuvers
Percussion: mapping air, fluid and solid organs
Percussion tells you what is under your fingers before you press. Percuss lightly in all four quadrants in the same clockwise pattern. The dominant note over a normal abdomen is tympany, a hollow drum-like note produced by gas in the stomach and intestines. Scattered dullness is expected over the liver, over a full bladder, over a full colon and over the spleen. Generalized dullness where you expect tympany means something has replaced the gas: fluid, stool, a mass or a gravid uterus. Generalized hyperresonance across a distended abdomen suggests gaseous distension from obstruction or ileus.
Measure the liver span in the right midclavicular line. Start well below the umbilicus over tympany and percuss upward until the note changes to dullness; that is the lower border, normally at or just below the right costal margin. Then start in the midclavicular line over lung resonance, around the fourth intercostal space, and percuss downward until dullness begins; that is the upper border, normally in the fifth to seventh intercostal space. Mark both with a skin pencil and measure. The expected adult span at the midclavicular line is 6 to 12 cm; at the midsternal line it is 4 to 8 cm. Spans are larger in tall people and in men and smaller in short people and in women. A span greater than 12 cm is hepatomegaly. Beware two traps: a liver pushed down by chronic obstructive pulmonary disease has a normal span but a palpable edge, and dullness from a right pleural effusion falsely enlarges the span from above.
For the spleen, percuss the lowest left interspace in the anterior axillary line, which is normally tympanitic. Ask the patient to take a deep breath and percuss again; if the note changes to dullness on inspiration, that is a positive Castell sign suggesting splenomegaly. Dullness in Traube space (bounded by the sixth rib, the left midaxillary line and the left costal margin) suggests the same. For the bladder, percuss downward from the umbilicus toward the symphysis pubis; a dull note above the symphysis in a patient who has not voided suggests urinary retention, and a bladder holding roughly 300 mL or more becomes percussible. Confirm with a bladder scanner rather than guessing. For ascites, use shifting dullness: percuss the flanks with the patient supine and mark the fluid level, roll the patient to one side, wait 30 seconds and percuss again; dullness that shifts toward the dependent side is positive. A fluid wave requires an assistant or the patient’s own hand pressed edgewise along the midline while you tap one flank and feel for the impulse on the other; it is specific but insensitive and generally requires a large volume. Physical examination reliably detects ascites at roughly 1500 mL, while ultrasound detects about 100 mL — another reason to measure abdominal girth serially at a marked spot on the skin at the umbilicus, at the same time of day, with the patient supine.
Light and deep palpation
Palpate last, and palpate in two passes. For light palpation, keep the fingers together, hand flat, and depress about 1 to 2 cm with a gentle rotary motion in all four quadrants. Light palpation is a screen for tenderness, surface masses, muscle tone and skin temperature. It is also how you build trust: if you hurt the patient here, the deep pass will be worthless because they will guard. For deep palpation, use the palmar surfaces of the fingers and depress about 4 to 6 cm (some texts teach 5 to 8 cm), using the other hand on top for reinforcement in a large or obese abdomen. Deep palpation delineates organs and masses. Any mass gets described in six terms: location, size in centimeters, shape, consistency, mobility and tenderness.
Do not perform deep palpation when there is a pulsatile epigastric mass or known aortic aneurysm, a suspected abdominal tumor in a child, a transplanted kidney, polycystic kidneys, a recent abdominal surgical site, or an obvious surgical abdomen with rigidity — in that last case you have your answer and further pressing only causes pain. Assess the liver edge by placing your left hand under the right posterior flank at the eleventh and twelfth ribs, pressing upward, and placing your right hand below the right costal margin; ask the patient to inhale deeply and feel for the edge descending against your fingertips. A normal adult liver edge is often not palpable; when felt it is smooth, firm and nontender. A nodular, hard or tender edge is abnormal. The spleen is normally not palpable in an adult; a palpable spleen is enlarged roughly threefold, and you palpate it gently because an enlarged spleen can rupture.
Interpretation of tenderness comes down to one distinction. Voluntary guarding is bilateral, improves with distraction and warm hands, and disappears on expiration. Involuntary guarding — true rigidity — is constant, unaffected by distraction, and is a sign of peritoneal inflammation. A board-like abdomen with rebound tenderness, absent bowel sounds and a patient who will not move is peritonitis until proven otherwise, and it is an emergency.
Focused maneuvers and lifespan variation
| Maneuver | How it is performed | Positive finding | Suggests |
|---|---|---|---|
| Murphy sign | Hook fingers under the right costal margin at the midclavicular line, ask for a deep breath | Patient stops inspiration abruptly from pain | Acute cholecystitis |
| McBurney point tenderness | Palpate one-third of the distance from the right anterior superior iliac spine toward the umbilicus | Sharp localized tenderness | Appendicitis |
| Rovsing sign | Palpate deeply in the left lower quadrant | Pain referred to the right lower quadrant | Appendicitis (peritoneal irritation) |
| Psoas sign | Patient lies on the left side; passively extend the right hip, or have the patient raise the right leg against your hand | Right lower quadrant pain | Retrocecal appendicitis, psoas abscess |
| Obturator sign | Flex the right hip and knee to 90 degrees, then internally rotate the hip | Right lower quadrant or hypogastric pain | Pelvic appendicitis |
| Costovertebral angle (CVA) tenderness | Place one palm over the CVA and strike it with the ulnar surface of the other fist | Sharp flank pain, not just thud | Pyelonephritis, renal calculus |
| Shifting dullness / fluid wave | Percuss flanks supine then in lateral position; or tap one flank and feel the opposite | Dullness shifts to dependent side; impulse transmitted | Ascites |
| Blumberg (rebound) | Press deep and slow, release quickly — perform last | Pain worse on release | Peritoneal irritation |
Infants and children. The infant and toddler abdomen is normally round and protuberant both supine and standing; by the preschool and school-age years the potbelly persists on standing but the abdomen flattens when the child lies supine. A liver edge palpable 1 to 2 cm below the right costal margin is expected in infancy, as is a soft, easily reducible umbilical hernia, which is common in infants of African descent and usually closes without intervention by 2 years of age. Diastasis recti — a midline separation of the rectus muscles — is a benign finding that resolves with growth. Bowel sounds in a newborn occur roughly every 10 to 30 seconds. Flex the child’s knees, use a warm hand, and let a toddler sit on the caregiver’s lap or place your hand over the child’s own hand for the first pass.
Pregnancy. The gravid uterus becomes an abdominal organ at about 12 weeks; fundal height in centimeters approximates gestational age in weeks between roughly 20 and 36 weeks. Progesterone slows gastrointestinal motility, so bowel sounds are diminished and constipation and pyrosis are common. Because the enlarging uterus displaces the appendix upward and laterally, appendicitis in the third trimester may present with right upper quadrant rather than right lower quadrant pain — do not dismiss it. Position a pregnant patient with a wedge under the right hip after about 20 weeks to prevent supine hypotensive syndrome.
Older adults. The abdominal wall is thinner and more lax, so organs are easier to palpate and a mass or aneurysm may be more evident. Salivary flow, esophageal motility and peristalsis decline, and constipation is common but never normal. The most important lesson is presentation: an older adult with peritonitis may have no rigidity, no rebound, and only a low-grade fever, because the abdominal musculature is weaker and the inflammatory response is blunted. New confusion, anorexia, a single fall or tachycardia may be the only sign of an acute abdomen, and an older adult on corticosteroids or with diabetes may be even more silent.
Percuss for tympany, liver span (6 to 12 cm at the midclavicular line) and shifting dullness, then palpate light (1 to 2 cm) before deep (4 to 6 cm) with the painful quadrant last — and never deep-palpate a pulsatile mass, a child’s suspected tumor or a rigid, board-like abdomen.
Section 4Nutritional Assessment and Feeding Safety
Screening, anthropometrics and the numbers that matter
Nutrition screening is a nursing responsibility and, in accredited hospitals, must be completed within 24 hours of admission. A screen is brief and identifies risk; a full nutritional assessment by a registered dietitian follows for anyone who screens positive. Validated tools include the Malnutrition Screening Tool (MST), the Malnutrition Universal Screening Tool (MUST) and, for adults over 65, the Mini Nutritional Assessment Short Form (MNA-SF). All of them ask two things you can ask without any tool at all: Have you lost weight recently without trying? and Have you been eating poorly because of a decreased appetite?
Measure rather than estimate. Height is measured standing without shoes; in a patient who cannot stand, use knee height or recumbent length. Weight is measured with the same scale, at the same time of day, in the same amount of clothing, after voiding. Body mass index is weight in kilograms divided by height in meters squared. It is a screening number, not a diagnosis: it does not distinguish muscle from fat, it underestimates adiposity in older adults who have lost lean mass, and it overestimates risk in muscular athletes. Waist circumference is measured at the level of the iliac crest at the end of a normal expiration, and it adds information BMI cannot, because central adiposity carries the metabolic risk.
Unintentional weight loss is the single most useful bedside nutrition indicator, and it must be calculated, not eyeballed. Percentage of weight change equals usual body weight minus current weight, divided by usual body weight, times 100. In the hospital, remember that a rapid weight change is fluid, not tissue: 1 kg equals approximately 1 L of fluid, and a 2 kg overnight gain in a patient with heart failure is 2 L of retained fluid, not new fat. Also assess intake directly — a 24-hour recall, a 3-day food record, calorie counts, and the percentage of each meal actually eaten. Chart “consumed 25 percent of lunch, refused meat, drank 240 mL milk,” not “poor appetite.”
| Measure | Expected / reference value | Concerning value | What it suggests |
|---|---|---|---|
| BMI (adult) | 18.5–24.9 kg/m² | Under 18.5 underweight; 25.0–29.9 overweight; 30.0–34.9 obesity class I; 35.0–39.9 class II; 40 or above class III | Under-nutrition risk at the low end; cardiometabolic risk at the high end. In adults over 65 a BMI of 23–30 is often the healthier target. |
| Waist circumference | Below 102 cm (40 in) men; below 88 cm (35 in) women | At or above those values | Central adiposity, metabolic syndrome, cardiovascular risk |
| Unintentional weight loss | Stable weight | Over 5 percent in 1 month; over 7.5 percent in 3 months; over 10 percent in 6 months | Significant malnutrition risk; triggers dietitian referral |
| Protein requirement | 0.8 g/kg/day for a healthy adult | Intake below need with wounds, sepsis, burns (needs rise to 1.2–2.0 g/kg/day) | Negative nitrogen balance, impaired wound healing |
| Fluid requirement | Roughly 30 mL/kg/day in a healthy adult | Intake well below need, or restricted intake plus diuretics | Dehydration, constipation, acute kidney injury |
| Fiber | 25 g/day women, 38 g/day men (about 14 g per 1000 kcal) | Chronically low | Constipation, poor glycemic and lipid control |
Physical findings and laboratory data
Malnutrition writes itself on the body, and much of it appears in regions covered by earlier chapters: temporal wasting and hollow cheeks, prominent clavicles and scapulae, loss of subcutaneous fat over the ribs and the orbits, thin dull hair that pulls out easily, spoon-shaped nails (koilonychia) with iron deficiency, angular cheilitis and glossitis with B-vitamin deficiency, poor wound healing, and bilateral dependent edema that is nutrition-related only after cardiac, hepatic and renal causes are excluded. Formal diagnosis of malnutrition uses clinical criteria — insufficient energy intake, weight loss, loss of muscle mass, loss of subcutaneous fat, fluid accumulation and reduced grip strength — not a single laboratory value.
That last point is the one students most often get wrong. Serum albumin (3.5–5.0 g/dL) and prealbumin (15–36 mg/dL) are negative acute-phase reactants. They fall with inflammation, infection, surgery, liver disease and fluid overload regardless of what the patient has eaten, and albumin’s half-life of roughly 20 days makes it useless for tracking short-term nutritional change. A low albumin in a septic patient tells you the patient is inflamed, not that the patient is starving, and a normal albumin does not rule malnutrition out. Use them as severity-of-illness markers, and use intake, weight trend and physical findings for nutrition. Other values worth carrying: hemoglobin 14–18 g/dL in men and 12–16 g/dL in women; hematocrit 42–52 percent and 37–47 percent respectively; sodium 135–145 mEq/L; potassium 3.5–5.0 mEq/L; BUN 10–20 mg/dL; creatinine 0.6–1.2 mg/dL; fasting glucose 70–99 mg/dL.
Watch for refeeding syndrome in anyone who has eaten little for five or more days, in chronic alcohol use, anorexia nervosa or prolonged NPO status. When feeding restarts, insulin drives phosphate, potassium and magnesium into cells and serum levels crash within 12 to 72 hours, producing arrhythmias, respiratory failure and death. Nursing actions are concrete: advance calories slowly per order, obtain baseline and daily phosphorus, potassium and magnesium, monitor cardiac rhythm and daily weights, and report a falling phosphate immediately.
Swallowing, aspiration and enteral feeding
Before any patient with a new stroke, a new neurologic deficit, a recent extubation or a new complaint of choking receives anything by mouth — including water and medications — they need a swallow screen. Keep the patient NPO until the screen is passed. Signs of dysphagia include coughing or throat-clearing during or after swallowing, a wet or gurgly voice afterward, drooling, pocketing food in the cheek, multiple swallows for one bolus, prolonged mealtimes and unexplained weight loss or recurrent pneumonia. Silent aspiration produces none of these signs, which is why a passed bedside screen does not rule out aspiration. Patients who fail a screen — and high-risk patients who pass but go on to show unexplained weight loss, recurrent pneumonia or a wet voice — need a formal speech-language pathology evaluation, which may include an instrumental study such as a videofluoroscopic swallow study or fibreoptic endoscopic evaluation of swallowing (FEES).
Aspiration precautions are nursing work and they are specific: sit the patient fully upright at 90 degrees for meals and keep the head of bed elevated at least 30 to 45 degrees for 30 to 60 minutes afterward; chin-tuck when swallowing if instructed; small bites and single sips; no straws unless approved; alternate solids and liquids; provide oral care at least twice a day, since oral bacteria carried into the lung are what turn aspiration into pneumonia; and never rush or talk to a patient with a mouthful of food. Suction should be available at the bedside for high-risk patients.
For enteral feeding, verification of tube placement is a patient-safety issue with a right answer and a wrong one. An abdominal radiograph is the standard for confirming initial placement of a blind-inserted feeding tube, and nothing may be instilled until it is read. After that, verify at least every 4 hours and before each intermittent feed or medication by combining methods: measure and document the external tube length against the marked exit site, check gastric aspirate pH (a pH of 5.0 or less supports gastric placement, though acid-suppressing medications raise it), and inspect the aspirate. Do not use the auscultatory (air-bolus) method — it is unreliable and has been abandoned. Keep the head of bed at 30 to 45 degrees during continuous feeding unless contraindicated, flush with 30 mL of water before and after medications and every 4 hours during continuous feeds, and give each medication separately in liquid form when possible. Current guidance is that gastric residual volumes should not be checked routinely, and when they are, feeding is generally not held for volumes below 500 mL in the absence of other signs of intolerance — follow your facility protocol, and always report vomiting, new distension or a rise in residual with abdominal pain.
Screen every patient for malnutrition within 24 hours using weight trend and appetite, calculate percentage weight loss rather than estimating it, treat albumin and prealbumin as inflammation markers rather than nutrition markers, and confirm every new feeding tube by radiograph — never by auscultating an air bolus.
Section 5Elimination, Red Flags and Escalation
Bowel elimination, stool characteristics and ostomies
Normal adult bowel frequency ranges widely — from three stools a day to three stools a week — so what matters is the change from the patient’s own baseline. Assess frequency, form, color, odor, effort and continence, plus laxative and opioid use, fluid and fiber intake and mobility. Use the Bristol Stool Form Scale to describe form: type 1 is separate hard lumps, type 2 is lumpy and sausage-shaped, type 3 is sausage-shaped with surface cracks, type 4 is smooth and soft like a sausage or snake (the ideal), type 5 is soft blobs with clear edges, type 6 is fluffy pieces with ragged edges, and type 7 is entirely liquid with no solid pieces. Types 1 and 2 indicate constipation; types 6 and 7 indicate diarrhea. Charting “Bristol type 7 x 4 in 6 hours” means something to the next nurse; “loose stool” does not.
Color and content carry diagnostic weight. Brown is expected. Melena — black, tarry, sticky and foul — means digested blood from an upper gastrointestinal source and is an escalation; black stool from iron or bismuth is dry and not tarry, and you ask before you assume. Hematochezia, bright red blood, points lower. Clay-colored or acholic stool suggests biliary obstruction, especially with dark urine and jaundice. Steatorrhea — greasy, floating, foul stool — suggests fat malabsorption. Currant-jelly stool in an infant with intermittent severe crying and drawn-up legs suggests intussusception and is an emergency. Anyone with new diarrhea and recent antibiotics needs evaluation for Clostridioides difficile: place on contact precautions, wash your hands with soap and water because alcohol-based rub does not kill spores, use a sporicidal (bleach) cleaner for equipment, and do not send a formed specimen.
Assess an ostomy at every shift and at every pouch change. A healthy stoma is beefy red or pink, moist, and slightly raised (budded), and the peristomal skin is intact and matches the patient’s surrounding skin tone. A stoma that is pale, dusky, purple or black is ischemic and must be reported immediately; one that is dry, sunken (retracted) or bleeding beyond a small amount at the mucosa also warrants a call to the wound-ostomy nurse. Bleeding when you clean the surface lightly is common because the stoma is vascular mucosa. Output differs by site: an ileostomy drains continuously with liquid to pasty effluent, typically 500 to 1000 mL per day once it has adapted, and carries a real risk of dehydration and electrolyte loss — sustained output above roughly 1200 mL per day is high-output and must be reported. A descending or sigmoid colostomy produces formed stool on a more predictable schedule. Empty the pouch when it is one-third to one-half full, and expect no stool and no flatus from a new ostomy for the first 24 to 48 hours after surgery; beyond that, report it.
Urinary elimination, retention and fluid balance
Normal urine is pale yellow to amber, clear, with a faint aromatic odor. Expected adult output with normal intake is roughly 1200 to 1500 mL in 24 hours. The number to protect is the hourly minimum: at least 0.5 mL/kg/hour in an adult, which for a 70 kg patient is about 35 mL/hour, or the familiar bedside floor of 30 mL/hour. Children require about 1 mL/kg/hour and infants about 2 mL/kg/hour. Oliguria is under 400 mL in 24 hours or under 0.5 mL/kg/hour sustained for 6 hours; anuria is under 100 mL in 24 hours. Falling urine output is one of the earliest signs of hypoperfusion and one of the first things you report.
Adult bladder capacity is roughly 400 to 600 mL, with the first urge at about 150 to 300 mL. When a patient cannot void, do not reach for a catheter first — scan first. A bladder scanner measures the volume noninvasively; a post-void residual under 50 mL is normal, 50 to 100 mL is borderline and may be acceptable in an older adult, over 100 mL on repeated measurement indicates incomplete emptying, and over 200 mL with discomfort or over 300 to 400 mL is significant retention that is reported and usually catheterized per protocol. Nursing measures come first when the patient is stable: privacy, upright position, running water, warm perineal water, ambulation, and reviewing the medication list for anticholinergics and opioids. Every indwelling catheter is a CAUTI risk — keep the drainage bag below the level of the bladder and off the floor, maintain a closed system, secure the tubing to prevent traction, perform routine perineal care with soap and water, and ask daily whether the catheter can come out. The best CAUTI prevention is removal.
Intake and output requires the same discipline as vital signs. Count everything: oral fluids, ice chips at half their volume, intravenous fluids and flushes, tube feeds and water flushes, urine, emesis, liquid stool, ostomy effluent, drains and measurable wound drainage. Weigh diapers, incontinence pads and dressings when accuracy matters — 1 g equals 1 mL. Pair the I and O record with a daily weight taken at the same time on the same scale, because the weight is the more reliable number. Report a positive or negative balance that does not match the clinical picture rather than simply recording it.
| Parameter | Expected | Abnormal | Suggests |
|---|---|---|---|
| Urine color and clarity | Pale yellow to amber, clear | Dark amber, cloudy, foul, pink or red, tea-colored, orange | Concentration or dehydration; infection; hematuria; myoglobinuria or hepatic disease; phenazopyridine or rifampin |
| Adult hourly output | 0.5 mL/kg/hour or more | Under 0.5 mL/kg/hour for 6 hours | Hypovolemia, hypoperfusion, acute kidney injury, obstruction |
| Post-void residual | Under 50 mL | Over 100 mL repeated; over 300 mL | Incomplete emptying, urinary retention, neurogenic bladder, benign prostatic hyperplasia |
| Stool form | Bristol type 3 or 4 | Type 1–2, or type 6–7 | Constipation with dehydration, opioids, immobility; diarrhea with infection, tube feeds, medication |
| Stool color | Brown | Black tarry, bright red, clay colored, greasy floating | Upper GI bleed, lower GI bleed, biliary obstruction, fat malabsorption |
| Stoma | Beefy red or pink, moist, budded | Pale, dusky, purple, black, retracted | Ischemia or necrosis — report immediately |
Red flags, vital signs, SBAR and delegation
Abdominal emergencies are frequently missed because they present quietly. Escalate now, without waiting for rounds, for any of the following: a rigid, board-like abdomen with involuntary guarding; sudden severe pain, especially if it woke the patient; a distended abdomen with vomiting and absent bowel sounds; a pulsatile epigastric mass, or abdominal or back pain with hypotension; hematemesis or coffee-ground emesis; melena or frank rectal bleeding; Cullen or Grey Turner sign; a dusky or black stoma; wound dehiscence or evisceration; no urine output for 6 to 8 hours or a bladder scan over 400 mL with pain; pain out of proportion to examination findings; and any acute abdominal complaint accompanied by fever, tachycardia and hypotension. If evisceration occurs, do not push the tissue back — cover it with sterile gauze moistened with sterile normal saline, place the patient in low Fowler position with knees flexed, keep them NPO, take vital signs and call the surgical team immediately.
Vital signs frame every one of those findings, and the thresholds shift by age. Compare against the patient’s own baseline first, then against the table.
| Age group | Heart rate (beats/min) | Respiratory rate (breaths/min) | Systolic BP (mmHg) |
|---|---|---|---|
| Newborn (0–1 month) | 100–180 | 30–60 | 60–90 |
| Infant (1–12 months) | 100–160 | 30–53 | 70–100 |
| Toddler (1–3 years) | 90–150 | 22–37 | 80–110 |
| Preschool (3–5 years) | 80–140 | 20–28 | 80–110 |
| School age (6–11 years) | 70–120 | 18–25 | 85–120 |
| Adolescent (12–18 years) | 60–100 | 12–20 | 100–130 |
| Adult | 60–100 | 12–20 | Below 120 systolic and below 80 diastolic is normal; keep mean arterial pressure at 65 or above |
| Older adult | 60–100 | 12–20 | Wider pulse pressure common; a temperature of 37.2 °C (99 °F) may represent fever because baseline temperature is lower and the febrile response is blunted |
Adult oral temperature is 36.5 to 37.5 °C (97.7 to 99.5 °F) and oxygen saturation is 95 to 100 percent on room air. In an acute abdomen, the pattern to fear is a rising heart rate with a narrowing pulse pressure and falling urine output — compensated shock — often before the blood pressure ever drops.
Findings across skin tones require deliberate technique, because the classic color descriptions were written for lightly pigmented skin. Assess jaundice in the sclera near the limbus in good natural light, and confirm on the hard palate, the palms and the soles; carotenemia from a diet high in carrots or squash yellows the palms and soles but spares the sclera. Assess pallor in the conjunctivae, the oral mucosa, the palms, the soles and the nail beds; in richly pigmented skin, pallor may appear as ashen, gray or yellow-brown rather than white. Assess cyanosis in the lips, tongue, oral mucosa, conjunctivae, nail beds, palms and soles; in dark skin it may look gray, ashen or blue-black rather than blue. Assess erythema with your hands as much as your eyes — compare the site to the contralateral side and to surrounding skin, and palpate for warmth, induration, tightness and tenderness, because inflammation in deeply pigmented skin often appears violet, deep brown or simply darker rather than red. This is exactly how early peristomal irritation and early pressure injury get missed.
When you escalate, use SBAR and have the data in hand before you dial. Situation: “This is Maria Ortiz, RN, on 4 West calling about Mr. Daniel Okafor in 412, a 68-year-old man, postoperative day 2 from an open sigmoid colectomy. His abdomen has become rigid and he has new severe pain.” Background: “He has hypertension and type 2 diabetes. He passed no flatus today, had one episode of coffee-ground emesis at 1500, and has had 20 mL of urine over the last 2 hours.” Assessment: “Temperature 38.6 °C, heart rate 122, blood pressure 92/68 down from 138/78, respirations 26, oxygen saturation 94 percent on room air. Abdomen is distended and board-like with involuntary guarding, no bowel sounds in any quadrant after 5 minutes of listening. I think he has peritonitis.” Recommendation: “I need you to come see him now. May I place him NPO, insert a nasogastric tube to low intermittent suction, obtain a stat lactate, CBC and basic metabolic panel, and start a normal saline bolus?” Then read the orders back, document the call with the time, and if you do not get a response, use the chain of command or the rapid response team.
Finally, scope. Unlicensed assistive personnel may measure and record intake and output, weigh patients, obtain and record vital signs on stable patients, assist a stable patient with eating when no dysphagia risk exists, provide perineal and catheter hygiene, empty an established ostomy pouch and drainage bags and record the amounts, collect routine urine and stool specimens, assist with toileting and ambulation, and apply incontinence products. The registered nurse may not delegate assessment (inspection, auscultation, percussion and palpation of the abdomen; interpreting a bladder scan and deciding to catheterize; the initial and ongoing assessment of a stoma), the swallow screen and the first oral intake after it, insertion or verification of a nasogastric or feeding tube, initiation of enteral feeding, evaluation of whether an intervention worked, patient and family teaching, and any care of an unstable patient. The rule that will carry you: assessment, teaching, evaluation, judgment and unstable patients stay with the RN. When you delegate, give the specific task, the expected outcome, the limits, and what to report back and when — “Please empty and measure Mr. Okafor’s ileostomy pouch every 2 hours and tell me immediately if the output is over 200 mL in an hour or if it turns dark.”
A rigid abdomen, absent bowel sounds with vomiting and distension, coffee-ground emesis, melena, a dusky stoma, a pulsatile mass or urine output under 0.5 mL/kg/hour are escalations right now — communicated in SBAR with vital signs, and never handed off to unlicensed personnel, because assessment, teaching, evaluation and unstable patients stay with the RN.
The chapter in one breath
The abdomen is examined in a sequence that exists nowhere else in the body: inspect, auscultate, percuss, palpate — because pressing first changes the bowel sounds you are about to record. Set the patient up supine with knees flexed and bladder empty, examine the painful quadrant last, and save any rebound test for the very end. Map findings to the four quadrants so your language survives handoff. Auscultate with the diaphragm starting in the right lower quadrant, expect 5 to 30 irregular gurgles a minute, and listen a full 5 minutes before charting sounds as absent; then switch to the bell for bruits. Percuss for tympany, a liver span of 6 to 12 cm at the midclavicular line, and shifting dullness. Palpate light at 1 to 2 cm before deep at 4 to 6 cm, and never deep-palpate a pulsatile mass or a rigid abdomen. Nutrition rests on weight trend, intake, BMI and physical findings — not on albumin. Elimination rests on Bristol type, stool color, urine output of at least 0.5 mL/kg/hour and post-void residual. And the whole chapter ends where nursing always ends: recognize the red flag, hand the story over in SBAR, and keep assessment, teaching, evaluation and unstable patients with the RN.
Words worth knowing
| Term | What it means |
|---|---|
| Ascites | Accumulation of free fluid in the peritoneal cavity; detected clinically by shifting dullness or a fluid wave, usually only above about 1500 mL. |
| Borborygmi | Loud, prolonged, hyperperistaltic gurgling audible without a stethoscope; usually benign. |
| Bristol Stool Form Scale | Seven-type classification of stool form, from type 1 (separate hard lumps) to type 7 (entirely liquid); types 3 and 4 are ideal. |
| Bruit | Blowing or swishing sound of turbulent arterial flow, heard with the bell over the aorta, renal, iliac or femoral arteries. |
| Caput medusae | Dilated tortuous veins radiating from the umbilicus, a sign of portal hypertension. |
| Cullen sign / Grey Turner sign | Periumbilical bruising and flank bruising respectively, indicating retroperitoneal or intraperitoneal bleeding. |
| Guarding, voluntary vs involuntary | Voluntary guarding is anticipatory muscle tensing that relaxes with distraction; involuntary guarding (rigidity) persists and signals peritoneal inflammation. |
| Hematochezia / melena | Bright red rectal bleeding from a lower gastrointestinal source; black, tarry, foul stool from digested blood in an upper source. |
| Liver span | Vertical distance between the upper and lower borders of hepatic dullness at the right midclavicular line; 6 to 12 cm in an adult. |
| Murphy sign | Abrupt cessation of inspiration when the examiner presses beneath the right costal margin; suggests acute cholecystitis. |
| McBurney point | Point one-third of the way from the right anterior superior iliac spine to the umbilicus; classic site of appendiceal tenderness. |
| Oliguria / anuria | Urine output under 400 mL in 24 hours or under 0.5 mL/kg/hour for 6 hours; anuria is under 100 mL in 24 hours. |
| Post-void residual (PVR) | Volume remaining in the bladder immediately after voiding; under 50 mL is normal, over 100 mL repeated indicates incomplete emptying. |
| Prealbumin / albumin | Serum proteins (15–36 mg/dL and 3.5–5.0 g/dL) that fall with inflammation; markers of illness severity, not of nutritional intake. |
| Refeeding syndrome | Dangerous drop in phosphate, potassium and magnesium when nutrition restarts after prolonged starvation; monitor labs and cardiac rhythm. |
| Rovsing sign | Pain referred to the right lower quadrant when the left lower quadrant is palpated; supports appendicitis. |
| Scaphoid abdomen | Sunken, concave abdominal contour seen with marked weight loss or dehydration. |
| Stoma | Surgically created opening of bowel or ureter onto the abdominal wall; expected to be beefy red or pink, moist and budded. |
| Tympany | Loud, drum-like percussion note over gas-filled bowel; the dominant note of a normal abdomen. |
| Visceral vs parietal pain | Visceral pain is dull, crampy and poorly localized from a stretched hollow organ; parietal pain is sharp, well localized and worse with movement, from peritoneal inflammation. |
Check yourself
Assessing the Musculoskeletal and Neurologic Systems
These two systems are assessed together because they fail together. A patient who cannot lift an arm may have a torn rotator cuff, a compressed nerve root, or an infarct in the contralateral motor cortex — and the exam that tells those apart is the same exam, performed in order, compared side to side, and repeated over time. This chapter teaches the actual hands: how to inspect a joint, grade a muscle from 0 to 5, take a Glasgow Coma Scale score that another nurse can reproduce, elicit a patellar reflex and grade it 0 to 4+, and run a neurovascular check on a casted limb in any skin tone. It also teaches the findings that end the exam and start a phone call — pain out of proportion under a cast, a new pronator drift, a widening pulse pressure with a falling heart rate — and exactly how to hand those off in SBAR.
By the end of this chapter you can
- Perform a screening musculoskeletal exam in the correct order — inspection, palpation, range of motion, strength — and state why the abdomen is the one region where the classic four-step sequence is reordered.
- Grade muscle strength on the 0–5 scale and deep tendon reflexes on the 0–4+ scale, and document both so another clinician gets the same number.
- Measure and describe joint range of motion in degrees for the cervical spine, shoulder, elbow, hip, knee and ankle, and distinguish active from passive ROM.
- Assess gait, balance and fall risk using the Timed Up and Go, the 4-stage balance test and orthostatic vital signs, using exact cutoffs.
- Determine level of consciousness with AVPU and the Glasgow Coma Scale, and screen cognition and delirium with Mini-Cog and the CAM.
- Test cranial nerves I–XII, motor and cerebellar function, the sensory system and reflexes, and interpret findings as upper versus lower motor neuron.
- Describe expected variations across the lifespan — infant primitive reflexes, fontanels, pregnancy, the older adult — and assess pallor, cyanosis and erythema accurately in dark skin tones.
- Recognize the red flags that require escalation now — compartment syndrome, cauda equina syndrome, autonomic dysreflexia, stroke by BE-FAST, rising intracranial pressure — and escalate using SBAR.
- Apply delegation rules: what a UAP may do with a mobility-impaired or neurologically changing patient and what stays with the RN.
Section 1The Musculoskeletal Exam — Structure, Sequence and Strength
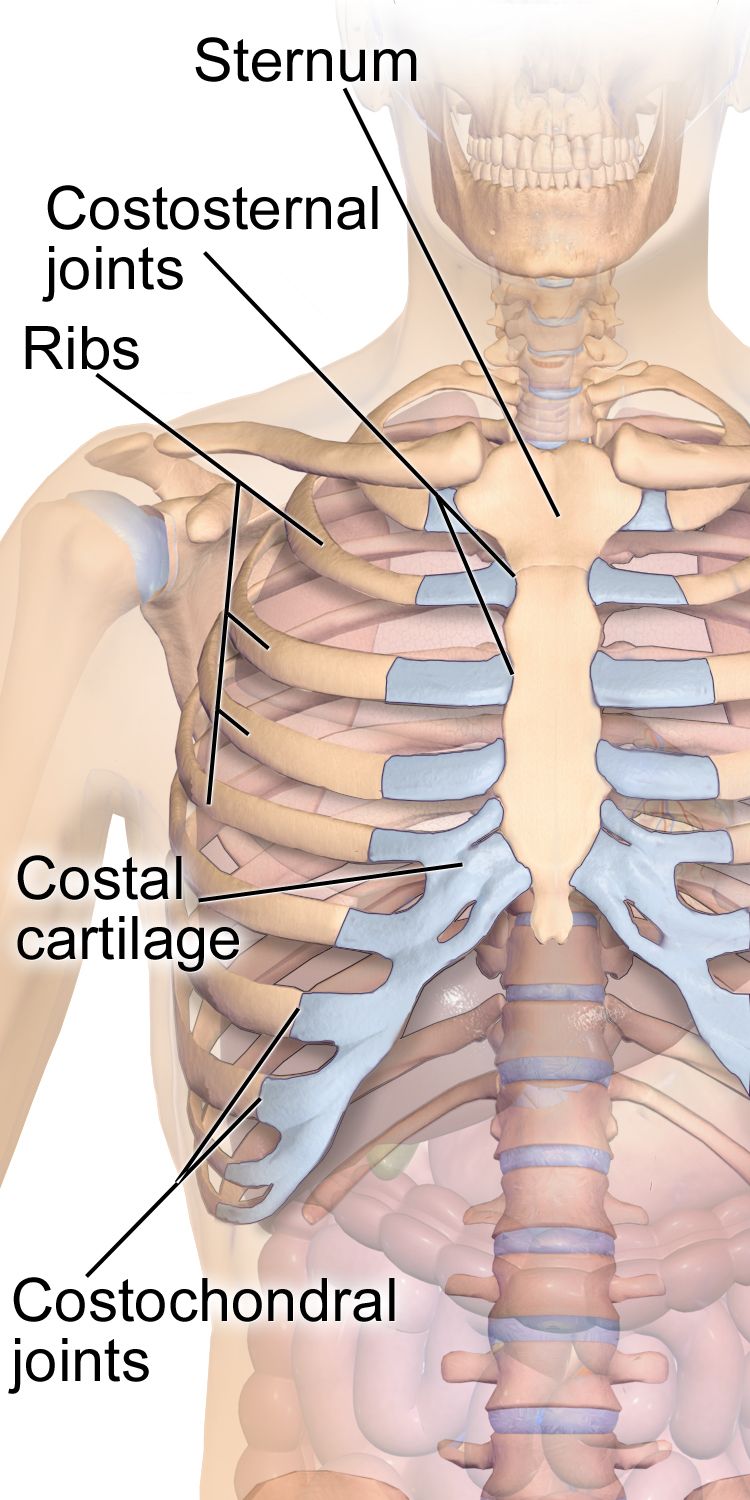
What you are actually assessing
The musculoskeletal system is 206 bones, roughly 640 skeletal muscles, and the joints, tendons, ligaments, bursae and cartilage that connect them. At the bedside you are almost never assessing all of it. You are doing one of two exams. The screening exam is what you perform on admission and at the start of a shift on a stable patient: observe posture and gait, watch the patient move in and out of bed and reach overhead, look at the hands, and check symmetry. It takes about ninety seconds and it is enough to catch asymmetry, guarding, deformity and functional loss. The focused exam is what you perform when the screening exam, the history or the diagnosis points somewhere: a fall with hip pain, a new cast, a shoulder that will not abduct, a complaint of numb fingers at night.
Two habits make the musculoskeletal exam reliable. First, always compare side to side. The patient’s own opposite limb is the only control group you have, and it is a very good one. A knee that measures three centimeters larger in circumference than its partner is an objective finding; “knee looks swollen” is an opinion. Second, examine the joint above and the joint below the painful one. Hip pathology refers pain to the knee, cervical pathology refers pain to the shoulder and hand, and a patient who points at one place is not always pointing at the problem.
Position matters more than students expect. Expose the joint fully — you cannot assess what is under a gown or a blanket — while draping everything you are not examining. Ask about pain before you touch, and examine the non-painful side first so the patient learns what your hands feel like on tissue that does not hurt. Never force a joint through a range the patient cannot reach voluntarily; passive range of motion is performed slowly, to the point of resistance or the report of pain, and then you stop.
The sequence — and the one region that breaks it
The classic physical assessment sequence is inspection, palpation, percussion, auscultation, and it is used in that order in every body region except the abdomen. In the abdomen the order becomes inspection, auscultation, percussion, palpation, because percussing and palpating first stimulates the bowel and alters the bowel sounds you were about to listen for — you would be auscultating a gut you already provoked. Nowhere else does that problem exist, so nowhere else is the order changed.
Applied to a joint, the four steps look like this. Inspection: with the patient upright and the joint exposed, compare size, contour, alignment and symmetry with the opposite side; look for swelling, redness, muscle wasting, deformity and the way the patient holds the part at rest. Palpation: using the pads of the fingers and the back of your hand for temperature, palpate the joint line, the bony landmarks, the tendon insertions and the surrounding muscle for warmth, effusion, tenderness, nodules and crepitus — a palpable or audible grating with movement. Percussion: in the musculoskeletal and neurologic exam, percussion is done with the reflex hammer over tendons (Section 4) and, in specific situations, over the spinous processes to reproduce focal bony tenderness. Auscultation: limited but real — auscultate the carotids for a bruit before any vigorous neck range of motion in an older adult, and listen over a joint replacement or a suspected arteriovenous malformation if there is a clinical reason.
Then two steps that belong specifically to the musculoskeletal exam are added after palpation: range of motion (active first, then passive if active is limited) and muscle strength against resistance. Active before passive is not arbitrary. Active ROM tells you what the patient can do — a functional answer. If active ROM is full, you do not need passive ROM. If active ROM is limited but passive ROM is full, the joint moves and the problem is muscle, nerve, pain or effort. If both are limited, the problem is in the joint itself: contracture, effusion, mechanical block, ankylosis.
Grading with numbers, not adjectives
Muscle strength is graded 0 to 5 against gravity and resistance, and every nurse in the building uses the same scale. Test the muscle group in isolation, stabilize the joint above it, and apply resistance through the mid-range while the patient holds. Grade each side separately: “5/5 right, 4/5 left” is information; “strength good” is not. Range of motion is recorded in degrees, from a defined zero (anatomic position) to the end of movement. You do not need a goniometer for a screening exam, but you do need to know what full looks like so you can say “knee flexion approximately 90 degrees, limited by pain” instead of “knee doesn’t bend all the way.”
| Grade | What the patient does | Common shorthand |
|---|---|---|
| 5 | Full ROM against gravity and full resistance | Normal (5/5) |
| 4 | Full ROM against gravity and some resistance | Good (4/5) |
| 3 | Full ROM against gravity only — no resistance tolerated | Fair (3/5) |
| 2 | Full ROM only with gravity eliminated (limb supported sideways) | Poor (2/5) |
| 1 | Palpable or visible flicker of contraction, no joint movement | Trace (1/5) |
| 0 | No detectable contraction | Zero (0/5) — paralysis |
| Joint and motion | Expected adult range | What limitation may mean |
|---|---|---|
| Cervical flexion / extension | 45° / 55° | Muscle spasm, arthritis; rigidity plus fever suggests meningeal irritation |
| Cervical rotation / lateral bending | 70° each side / 40° each side | Degenerative disc disease, torticollis |
| Shoulder flexion and abduction | 180° | Painful arc 60–120° suggests rotator cuff impingement |
| Elbow flexion / extension | 150–160° / to 0° | Effusion, contracture, heterotopic ossification |
| Wrist flexion / extension | 80–90° / 70° | Carpal tunnel syndrome, rheumatoid synovitis |
| Hip flexion (knee flexed / knee straight) | 120° / 90° | Osteoarthritis, effusion, flexion contracture |
| Knee flexion | 130–150° | Effusion, meniscal tear, post-arthroplasty stiffness |
| Ankle dorsiflexion / plantar flexion | 20° / 45° | Achilles pathology, cast immobilization, foot drop |
| Lumbar flexion / extension | 75–90° / 30° | Disc disease, spasm, ankylosing spondylitis |
How to chart it
Musculoskeletal documentation fails in a predictable way: it is written as a conclusion instead of an observation. “Musculoskeletal within normal limits” is unfalsifiable, unhelpful in court, and useless to the nurse who follows you and needs to know whether the left grip changed. Write what you did, what you measured, and on which side.
| Vague entry | Precise entry a nurse can act on |
|---|---|
| “MSK WNL. Moves all extremities.” | “Moves all four extremities to command. Strength 5/5 bilateral grips, 5/5 bilateral plantar flexion and dorsiflexion. No joint swelling, deformity or tenderness. Gait steady with single-point cane, no assist required.” |
| “Right knee swollen and sore.” | “Right knee warm to touch compared to left, circumference 42 cm right vs 38.5 cm left at mid-patella. Positive bulge sign. Active flexion 85° limited by pain rated 6/10; passive flexion 95°. Ambulates 10 feet with walker, antalgic gait favoring right. Left knee unremarkable.” |
| “Weak on the left.” | “Left grip 3/5, right grip 5/5. Left elbow flexion 4/5, right 5/5. Left leg 4/5 hip flexion, 5/5 elsewhere. New compared to 0800 assessment (all 5/5). Provider notified 1412.” |
Inspect, palpate, percuss, auscultate in every region except the abdomen — and in the musculoskeletal exam add active range of motion, then passive, then graded strength, always comparing left to right.
Section 2Region by Region — Spine, Limbs, Gait and the Neurovascular Check
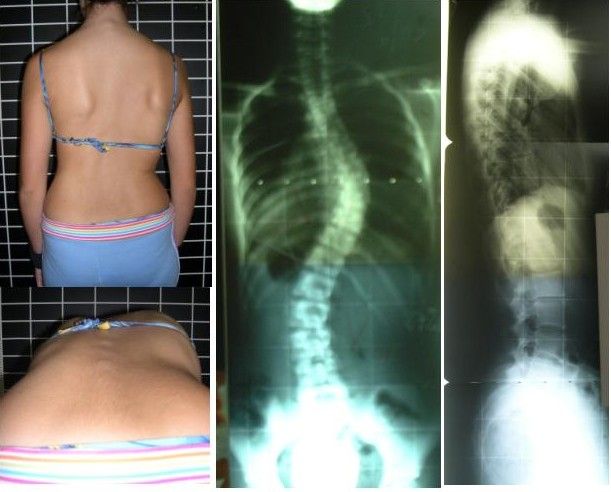
Spine and posture
Inspect the spine with the patient standing and undressed to the underwear, from behind and from the side. From behind, the spinous processes should form a straight vertical line; the shoulders, scapulae and iliac crests should be level; the gluteal fold should be symmetric. From the side, expect the normal curves: cervical concave, thoracic convex, lumbar concave. Kyphosis is an exaggerated thoracic convexity, lordosis an exaggerated lumbar concavity, scoliosis a lateral curvature with vertebral rotation. Palpate down the spinous processes and the paravertebral muscles for tenderness and spasm.
Screen for scoliosis with the Adams forward bend test: the patient stands with feet together and bends forward at the waist with knees straight and arms hanging. You look tangentially across the back for a unilateral rib hump or lumbar prominence, which reveals the vertebral rotation that a standing exam hides. Adolescent idiopathic scoliosis is screened around ages 10 and 12 in girls and 13 or 14 in boys, because curves progress during the growth spurt. Test lumbar range of motion — flexion 75–90°, extension 30°, lateral bending 35° each way, rotation 30° each way — stabilizing the pelvis so the motion comes from the spine.
For radicular low back pain, the straight leg raise is the test to know. The patient lies supine; you raise the extended leg by the heel with the knee straight. Reproduction of the patient’s shooting pain below the knee between 30 and 70 degrees of elevation is a positive test suggesting lumbar nerve root irritation (usually L5 or S1). Hamstring tightness or posterior thigh pulling is not a positive test. Pain reproduced in the affected leg when you raise the opposite leg (crossed straight leg raise) is less sensitive but much more specific for disc herniation.
Upper extremity
At the shoulder, inspect for the squared-off contour of a dislocation and for deltoid wasting. Palpate the sternoclavicular and acromioclavicular joints, the bicipital groove and the subacromial space. Screen ROM with three commands that cover everything: “raise both arms straight overhead” (flexion and abduction to 180°), “touch the back of your neck” (external rotation and abduction), “touch the middle of your back” (internal rotation and adduction). Pain only between 60 and 120 degrees of abduction — a painful arc — suggests subacromial impingement. In the drop arm test, you passively abduct the arm to 90 degrees and ask the patient to lower it slowly; if the arm drops abruptly, suspect a rotator cuff tear.
At the elbow, palpate the olecranon and the epicondyles; tenderness over the lateral epicondyle with resisted wrist extension suggests lateral epicondylitis. At the wrist and hand, inspect for the ulnar deviation and swan-neck or boutonniere deformities of rheumatoid arthritis, the hard Heberden nodes at the distal interphalangeal joints and Bouchard nodes at the proximal interphalangeal joints of osteoarthritis, and thenar wasting. For suspected carpal tunnel syndrome, Phalen test holds the wrists in full flexion back to back for 60 seconds and is positive if numbness or tingling develops in the thumb, index, middle and radial half of the ring finger; Tinel sign taps lightly over the median nerve at the volar wrist and is positive if the same tingling shoots into those digits.
Lower extremity and gait
At the hip, inspect stance and leg length, palpate the greater trochanter for bursal tenderness, and test flexion, internal rotation (40°) and external rotation (45°) — internal rotation is usually lost first in hip osteoarthritis. The Trendelenburg sign is positive when the patient stands on one leg and the opposite hip drops, indicating weakness of the gluteus medius on the weight-bearing side. At the knee, inspect for effusion and quadriceps atrophy, palpate the joint line, and use the bulge sign for a small effusion: milk fluid upward from the medial side, then stroke down the lateral side and watch for a fluid wave to appear medially. Larger effusions are detected by ballottement of the patella. Ligament and meniscal testing — anterior drawer and Lachman for the anterior cruciate ligament, McMurray for the meniscus — is generally performed by the provider, but you should recognize the names in the chart.
Then watch the patient walk, because gait integrates everything. Observe a full walking cycle from the front, side and back for stride length, arm swing, foot clearance, base width and symmetry. Named abnormal gaits carry diagnoses: antalgic (short time in stance on the painful side), steppage (high knee lift to clear a dropped foot — peroneal nerve or L5), shuffling with reduced arm swing (parkinsonian), wide-based and unsteady (cerebellar ataxia), scissoring (spastic diplegia), and the stiff circumducted swing of a hemiparetic gait after stroke.
Fall risk deserves exact numbers. In the Timed Up and Go (TUG), the patient rises from a standard armchair, walks 10 feet (3 meters), turns, walks back and sits down, wearing usual footwear and using their usual assistive device. 12 seconds or more indicates increased fall risk (CDC STEADI). The 4-Stage Balance Test asks for feet together, semi-tandem, full tandem and single-leg stance, 10 seconds each; inability to hold full tandem for 10 seconds is a fall-risk finding. Orthostatic vital signs are positive when, within 3 minutes of standing, systolic BP falls 20 mmHg or more, diastolic BP falls 10 mmHg or more, or heart rate rises 20 beats/min or more. Measure supine after 5 minutes rest, then sitting, then standing — and stay with the patient the whole time.
The neurovascular check — and skin tone
Any patient with a fracture, cast, splint, traction, surgical extremity, circumferential dressing or vascular procedure gets scheduled neurovascular checks distal to the injury, compared to the opposite limb. The elements are colour, temperature, capillary refill, pulses, sensation, movement, pain and edema — often charted as CMS (circulation, motion, sensation). Expected: warm, colour matching the other limb, capillary refill under 2 seconds (longer than 2 seconds is abnormal, and 3 seconds or more is clearly delayed), palpable distal pulse equal to the other side, intact light touch and two-point sensation, active wiggle of fingers or toes, and pain that is controlled by the ordered analgesia. Frequency is typically every hour for the first 24 hours after casting or surgery, then every 4 hours, or per facility protocol — and immediately with any patient complaint.
Colour findings must be assessed correctly in every skin tone, because “pink” is a description of light skin, not a physiologic standard. In darker skin, pallor appears as ashen or grey rather than white; cyanosis appears as grey, dusky or blue-black. The reliable sites in every patient are the oral mucosa and tongue, the conjunctivae, the palms and soles, and the nail beds. Jaundice is best seen in the sclera (against the hard palate and palms if the sclera is equivocal), and in darker skin the sclera may have normal yellowish fat deposits near the periphery — look near the cornea. Erythema and early inflammation may be invisible in darker skin, so assess by palpation: compare the area to surrounding skin for warmth, induration, edema, tautness and tenderness, and use natural or full-spectrum light rather than fluorescent. Ask the patient what their normal skin colour looks like.
| Neurovascular element | Expected finding | Abnormal finding and what it suggests |
|---|---|---|
| Colour | Matches the contralateral limb; oral mucosa, conjunctivae, palms/soles and nail beds unchanged from this patient’s own baseline — never judged against “pink” | Newly pale, ashen or grey against the other limb → arterial compromise; dusky, grey or blue-black at mucosa, conjunctivae or nail beds → venous congestion or hypoxia |
| Temperature | Warm, equal to opposite limb (back of hand) | Cool distal to injury → arterial insufficiency or tight cast |
| Capillary refill | Under 2 seconds | Longer than 2 seconds, and certainly 3 or more → poor perfusion (also cold environment, shock) |
| Pulses | Palpable, 2+ and equal bilaterally | Diminished or absent → late, ominous sign of compartment syndrome or arterial injury |
| Sensation | Intact light touch, no numbness or tingling | Paresthesia, numbness → nerve compression — an early compartment sign |
| Movement | Wiggles digits actively and fully | Weak or absent movement → late nerve or muscle ischemia |
| Pain | Relieved by ordered analgesia and elevation | Pain out of proportion, unrelieved, worse with passive stretch of the digits → compartment syndrome until proven otherwise |
Regional musculoskeletal assessment is comparison plus function — measure the joint in degrees, watch the patient walk, and on any immobilized limb run a scheduled neurovascular check whose colour findings you assess at the mucosa, conjunctivae, palms and nail beds rather than by expecting “pink.”
Section 3The Neurologic Exam Begins — Consciousness, Cognition and Cranial Nerves
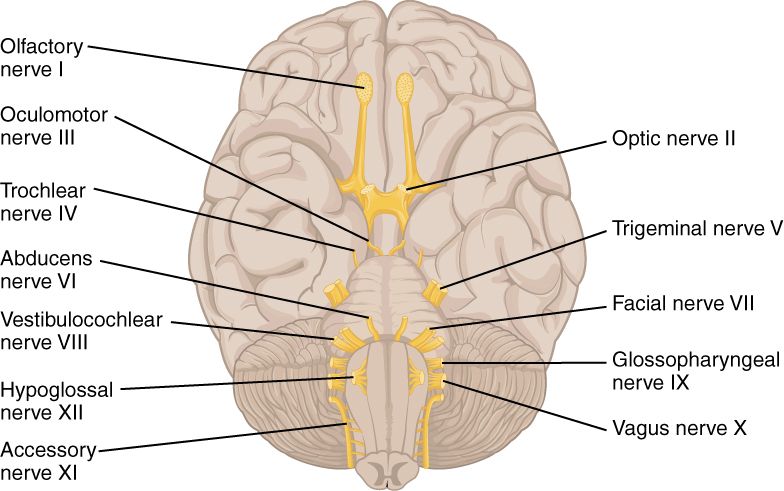
Level of consciousness first, always
Level of consciousness is the single most sensitive indicator of neurologic change, and it is assessed before anything else, because the rest of the exam depends on it. Consciousness has two parts: arousal (are they awake?) and awareness (do they know what is going on?). Start with the least invasive stimulus and escalate only as needed — voice at normal volume, then loud voice, then touch, then a central painful stimulus such as a trapezius squeeze or supraorbital pressure. Sternal rub is also a central stimulus, but it is no longer recommended as a routine tool because repeated rubbing bruises the skin. What you must not do is substitute a peripheral stimulus — nail-bed or nail-fold pressure — for a central one when you are scoring the motor response, because a limb can withdraw on a spinal reflex arc with no brain involvement at all.
AVPU is the fast screen: Alert, responds to Voice, responds to Pain, Unresponsive. The Glasgow Coma Scale is the standardized score, from 3 (worst possible) to 15 (fully intact), built from three components. Score the best response in each category, score each side’s best motor response but chart the best overall, and record the components, not just the total: a GCS of 9 made of E2 V2 M5 is a very different patient from E4 V1 M4, and “GCS 9” alone hides that. A GCS of 8 or less generally indicates an inability to protect the airway and prompts consideration of intubation. A drop of 2 or more points in the total, or any drop in the motor score, is an urgent change.
| Eye opening (E) | Verbal response (V) | Best motor response (M) |
|---|---|---|
| 4 — Spontaneous | 5 — Oriented | 6 — Obeys commands |
| 3 — To sound / speech | 4 — Confused conversation | 5 — Localizes to pressure |
| 2 — To pressure | 3 — Inappropriate words | 4 — Normal flexion / withdraws |
| 1 — None | 2 — Incomprehensible sounds | 3 — Abnormal flexion (decorticate) |
| NT — Not testable (swelling) | 1 — None · NT if intubated (chart “T”) | 2 — Extension (decerebrate) · 1 — None |
In the infant and preverbal child, the pediatric GCS substitutes developmentally appropriate responses: verbal 5 is coos and babbles, 4 irritable cries, 3 cries to pain, 2 moans to pain, 1 none; motor 6 becomes spontaneous purposeful movement and 5 becomes withdraws to touch. In critical care, sedation depth is scored separately with the RASS, from +4 (combative) through 0 (alert and calm) to −5 (unarousable) — a sedated patient’s low GCS may be pharmacologic, and you must know which.
Orientation, cognition and the delirium screen
“Alert and oriented ×4” means oriented to person, place, time and situation. Ask, do not assume: name, where we are right now, the month and year, and why they came to the hospital. Orientation is lost in a rough order — time first, then place, then situation, then person — so a patient who does not know the year but knows everything else is early, and a patient who does not know their own name is either profoundly impaired or not organically confused at all.
Screen cognition with the Mini-Cog: three unrelated words to remember, a clock-drawing task (“draw a clock face with all the numbers, then set the hands to ten past eleven”), then recall of the three words. Score 0–5 (one point per recalled word, two points for a normal clock); a total of 2 or less is a positive screen for cognitive impairment, while 3, 4 or 5 is a negative screen. The MMSE is scored out of 30 with less than 24 suggesting impairment; the MoCA is scored out of 30 with 26 or above considered normal and is more sensitive to mild impairment. None of these diagnoses dementia — they trigger further evaluation.
Delirium is the finding students miss most, because a quietly hypoactive delirious patient looks like a cooperative one. Use the Confusion Assessment Method (CAM): delirium is present when there is (1) acute onset or fluctuating course AND (2) inattention, PLUS either (3) disorganized thinking OR (4) altered level of consciousness. Test inattention concretely — months of the year backward from December, or digit span. Delirium is acute, fluctuating and usually reversible; dementia is chronic, progressive and stable hour to hour; depression can mimic both with poor effort and “I don’t know” answers. Also separate aphasia (a language disorder — expressive/Broca with effortful, halting, telegraphic speech and preserved comprehension; receptive/Wernicke with fluent but nonsensical speech and impaired comprehension) from dysarthria (a motor articulation problem with intact language). An aphasic patient may be fully oriented and unable to show you.
Cranial nerves I–XII
Test them in numerical order so you never skip one. On a routine medical-surgical patient the screening version takes two minutes: pupils, extraocular movements, facial symmetry, hearing to conversation, swallow, shoulder shrug and tongue protrusion. A focused exam — new neurologic complaint, suspected stroke, head injury, cranial surgery — tests all twelve.
| Nerve | How you test it | Expected | Abnormal suggests |
|---|---|---|---|
| I Olfactory | Eyes closed, one nostril at a time, familiar non-irritating scent (coffee) | Identifies scent both sides | Anosmia — frontal lesion, basilar skull fracture, viral |
| II Optic | Visual acuity (Snellen), gross visual fields by confrontation | 20/20 corrected; full fields | Hemianopsia — stroke, tumor, optic pathway lesion |
| III, IV, VI Oculomotor, Trochlear, Abducens | Six cardinal directions of gaze; pupil size, shape, direct and consensual reaction, accommodation | Conjugate gaze; pupils 2–5 mm, round, equal, briskly reactive (PERRLA) | Unilateral fixed dilated pupil → CN III compression / herniation — emergency; pinpoint <2 mm → opioids or pontine lesion |
| V Trigeminal | Light touch to forehead, cheek, jaw bilaterally; clench teeth and palpate masseters; corneal reflex (wisp) if indicated | Symmetric sensation; strong equal masseters | Unilateral numbness, weak jaw — brainstem lesion, trigeminal neuralgia |
| VII Facial | Raise eyebrows, close eyes tightly, smile, show teeth, puff cheeks; taste anterior two-thirds of tongue | Symmetric movement | Forehead spared → central lesion (stroke); whole side including forehead → peripheral (Bell palsy) |
| VIII Vestibulocochlear | Whispered word at 1–2 feet; Weber and Rinne with a 512 Hz tuning fork; balance | Hears whisper both sides; Weber midline; air conduction longer than bone (AC > BC) | Conductive vs sensorineural loss; vertigo, nystagmus |
| IX, X Glossopharyngeal, Vagus | Say “ahh” and watch the uvula and palate; voice quality; gag reflex if indicated | Palate rises symmetrically, uvula midline, clear voice | Uvula deviates away from the weak side; hoarseness, wet voice → aspiration risk |
| XI Spinal accessory | Shrug shoulders against resistance; turn head against resistance | Strong, symmetric 5/5 | Weak trapezius/sternocleidomastoid — nerve injury, neck surgery |
| XII Hypoglossal | Protrude tongue; move side to side; say “light, tight, dynamite” | Tongue midline, clear articulation | Tongue deviates toward the weak side; slurred lingual sounds |
Lifespan variation in the neurologic exam
Normal is age-dependent, and calling a normal infant finding pathologic (or missing a retained reflex) is a real error. In the newborn, the posterior fontanel closes by 2–3 months and the anterior fontanel by 12–18 months; a bulging tense fontanel in a quiet upright infant suggests raised intracranial pressure, a sunken one suggests dehydration. Primitive reflexes appear and then must disappear: Moro (startle) fades by 3–6 months, palmar grasp by 3–4 months, rooting by 3–4 months, tonic neck by 4–6 months, plantar grasp by 8–12 months. An upgoing great toe on plantar stimulation (Babinski response) is normal until roughly 12–24 months and abnormal after that. Persistence of a primitive reflex past its window, or asymmetry of any of them, is a referral.
In toddlers and children, bowed legs (genu varum) are expected until about age 2–3 and knock-knees (genu valgum) between about 2 and 7 years, peaking around 3–4 — both usually self-correct. In infancy screen the hips for developmental dysplasia with the Ortolani and Barlow maneuvers up to about 3 months, and after that with asymmetric thigh folds, limited hip abduction and a positive Galeazzi sign (unequal knee heights with hips and knees flexed).
In pregnancy, relaxin and progesterone loosen the pelvic ligaments and the center of gravity shifts forward, producing lumbar lordosis, low back pain, a wide-based waddling gait and increased fall risk; carpal tunnel symptoms are common from fluid retention. In the older adult, expect a loss of about 1 cm of height per decade after age 40, mild kyphosis, reduced muscle mass (sarcopenia), slower reaction time, smaller and more sluggishly reactive pupils, diminished vibratory sense in the feet, and ankle jerks that may be symmetrically diminished or absent — that last finding is common and, when bilateral and isolated, not necessarily pathologic. What is never normal at any age: new asymmetry, new confusion, and a new focal deficit.
Assess level of consciousness before anything else, chart the GCS in components rather than a bare total, screen every acute mental status change as delirium until proven otherwise, and interpret every neurologic finding against the patient’s age.
Section 4Motor, Cerebellar, Sensory and Reflex Testing
The motor exam — bulk, tone, strength and drift
Assess motor function in four steps. Bulk: inspect and compare muscle mass bilaterally; measure limb circumference at a fixed landmark if you suspect atrophy. Tone: with the patient relaxed, move each limb passively through range and feel the resistance. Expect mild, even resistance. Flaccidity is absent tone (a lower motor neuron finding); spasticity is velocity-dependent resistance that gives way suddenly (clasp-knife, an upper motor neuron finding); rigidity is resistance throughout the range, either lead-pipe or ratcheting cogwheel rigidity of parkinsonism. Strength: graded 0–5 as in Section 1, tested group by group and compared side to side. Involuntary movement: note tremor at rest (parkinsonian) versus tremor that worsens as the hand approaches a target (intention tremor, cerebellar), plus fasciculations, tics and myoclonus.
The most useful single motor screen on a hospital unit is pronator drift. The patient extends both arms forward, palms up, eyes closed, for 20–30 seconds. Downward drift with pronation of one forearm indicates a corticospinal tract lesion on the opposite side of the brain, and it appears when formal strength testing still measures 5/5. It costs thirty seconds and it catches early strokes. Test the legs in the same spirit: heel slides, or holding both legs elevated off the bed and watching for one to sink.
| Feature | Upper motor neuron lesion (brain, spinal cord) | Lower motor neuron lesion (anterior horn, root, peripheral nerve) |
|---|---|---|
| Tone | Increased — spasticity | Decreased — flaccidity |
| Reflexes | Hyperactive (3+ to 4+), clonus possible | Diminished or absent (0 to 1+) |
| Plantar response | Upgoing great toe — positive Babinski | Downgoing (flexor) or absent |
| Muscle bulk | Normal early; disuse atrophy late | Marked atrophy |
| Fasciculations | Absent | Present |
| Pattern of weakness | Whole limb or one side of the body | Follows a specific nerve or root distribution |
Cerebellar function, balance and coordination
The cerebellum coordinates; it does not generate power. So cerebellar testing asks for accuracy and rhythm, not force. Rapid alternating movements: the patient pats the thigh alternating palm and back of hand as fast as possible, or taps thumb to each finger in sequence. Slow, clumsy, irregular performance is dysdiadochokinesia. Finger-to-nose: the patient alternates touching their nose and your fingertip while you move it; overshooting the target is dysmetria. Heel-to-shin: supine, the patient runs one heel down the opposite shin from knee to ankle; wavering off the line is a cerebellar finding. Gait and tandem walk: ask for heel-to-toe walking along a straight line.
The Romberg test is frequently misdescribed. The patient stands with feet together and arms at the sides, eyes open for about 20 seconds, then eyes closed for about 20 seconds. It is positive when the patient is steady with eyes open but sways markedly or loses balance with eyes closed — and that pattern means proprioceptive (dorsal column) or vestibular dysfunction, not cerebellar disease. A patient who is unsteady even with the eyes open has a cerebellar problem. Stand close enough to catch the patient every single time; a fall during a Romberg test is a preventable injury and it belongs to you.
The sensory exam
Sensory testing requires an alert, cooperative patient with eyes closed, and it is done by comparing symmetric areas side to side and distal to proximal. Do not tell the patient where you are touching. Screen a routine patient at the shoulders, forearms, hands, thighs, lower legs and feet; test in detail only where symptoms, a dermatome or a known lesion sends you. Ask “does this feel the same on both sides?” rather than “can you feel this?”
Primary sensations: light touch with a cotton wisp; pain with the sharp and dull ends of a broken tongue blade or a disposable neuro pin (never a reused sharp); temperature only if pain sensation is abnormal; vibration with a 128 Hz tuning fork placed on a bony prominence such as the great toe interphalangeal joint or the medial malleolus — ask when the buzzing stops; proprioception by moving the patient’s great toe or finger up or down while holding it by the sides and asking which way it moved. Vibration and proprioception travel in the dorsal columns and are the first to go in diabetic peripheral neuropathy and vitamin B12 deficiency, which is why an annual monofilament and vibration check is standard diabetic foot care.
Cortical (discriminative) sensations are tested only when primary sensation is intact, because they require an intact parietal cortex to interpret normal input: stereognosis (identify a coin or key placed in the hand), graphesthesia (identify a number traced on the palm), two-point discrimination, and extinction (touch both sides simultaneously; failing to report one side despite intact single-side sensation suggests a contralateral parietal lesion and often accompanies neglect after a right-hemisphere stroke). Translate the patient’s numb area into a root using the dermatome map: C6 thumb, C7 middle finger, C8 little finger, T4 nipple line, T10 umbilicus, L4 medial malleolus, L5 dorsum of the foot and great toe, S1 lateral foot and heel, S2–S4 perianal saddle.
Reflexes — the percussion half of the neuro exam
Deep tendon reflexes are elicited by striking a tendon with the flat or pointed end of a reflex hammer, using a loose wrist and letting the hammer fall by its own weight. The limb must be relaxed and the tendon slightly stretched; position, not force, is what makes a reflex appear. If a reflex seems absent, use reinforcement before you chart a zero: have the patient clench the teeth or interlock the fingers and pull apart (the Jendrassik maneuver) at the instant you strike. Grade each reflex, compare bilaterally, and remember that asymmetry is more meaningful than the absolute grade.
| Grade | Response | Interpretation |
|---|---|---|
| 0 | No response | Absent — lower motor neuron lesion, peripheral neuropathy, spinal shock |
| 1+ | Diminished, present only with reinforcement | Hypoactive — may be normal in some older adults if symmetric |
| 2+ | Brisk, expected response | Normal |
| 3+ | Brisker than average, no clonus | May be normal in an anxious patient; upper motor neuron lesion if asymmetric |
| 4+ | Hyperactive with sustained clonus | Always abnormal — upper motor neuron lesion; in pregnancy, think preeclampsia |
| Reflex | Where you strike | Nerve roots | Expected response |
|---|---|---|---|
| Biceps | Your thumb over the biceps tendon in the antecubital fossa | C5–C6 | Elbow flexion |
| Brachioradialis | Radius, about 1–2 inches above the wrist | C5–C6 | Forearm supination and elbow flexion |
| Triceps | Triceps tendon just above the olecranon, arm hanging | C6–C7 (mainly C7) | Elbow extension |
| Patellar | Patellar tendon below the patella, knee flexed and dangling | L2–L4 (mainly L4) | Knee extension |
| Achilles | Achilles tendon with the foot slightly dorsiflexed | S1–S2 (mainly S1) | Plantar flexion |
| Plantar (superficial) | Stroke the lateral sole from heel to ball, then across the metatarsal heads | L5–S1 | Toe flexion in adults; upgoing toe with fanning is abnormal after about 2 years of age |
Test for clonus whenever reflexes are 3+ or 4+: support the knee in slight flexion and briskly dorsiflex the ankle, holding the stretch. Rhythmic beats of plantar flexion follow; a few unsustained beats can be normal, but sustained clonus is an upper motor neuron finding and, in a pregnant patient with hypertension and headache, a warning of impending eclampsia. Chart reflexes concretely: “DTRs 2+ and symmetric at biceps, triceps, patellar and Achilles. Plantar reflexes downgoing bilaterally. No clonus.”
Motor, cerebellar, sensory and reflex testing sort a deficit into upper versus lower motor neuron, and the pattern — spastic with 4+ reflexes and an upgoing toe, versus flaccid with absent reflexes and fasciculations — tells you where the lesion lives.
Section 5Red Flags, Serial Checks and Escalation
Musculoskeletal emergencies
Acute compartment syndrome is the one every orthopedic patient is at risk for and the one students must be able to recognize without being told. Pressure rises inside a closed fascial compartment — from fracture bleeding, crush injury, a tight cast or a circumferential dressing — until it exceeds capillary perfusion pressure and the muscle and nerve inside begin to die. Irreversible damage can occur within 4 to 8 hours. The classic six P’s are pain, paresthesia, pallor, pulselessness, paralysis and poikilothermia, but they are not equally useful: the earliest and most reliable signs are pain out of proportion to the injury, pain that increases with passive stretch of the digits, and paresthesia. Pallor, pulselessness and paralysis are late — a palpable pulse does not rule out compartment syndrome. Nursing actions: stop, do not elevate the limb above heart level (that reduces arterial inflow — keep it at heart level), do not apply ice, loosen or ask for the cast to be bivalved or the dressing split, hold nothing back on reporting, and escalate immediately. Definitive care is fasciotomy; diagnostic compartment pressure above 30 mmHg or a delta pressure under 30 mmHg is the surgical threshold.
Other musculoskeletal red flags: fat embolism syndrome, typically 24–72 hours after a long bone or pelvic fracture, presenting as hypoxemia with new dyspnea, acute confusion, and a petechial rash across the chest, axillae and conjunctivae; cauda equina syndrome — saddle anesthesia, new urinary retention or incontinence, bilateral leg weakness and bowel dysfunction — a surgical emergency; suspected deep vein thrombosis with new unilateral calf swelling, warmth and pain (do not rely on Homans sign, which is neither sensitive nor specific); and a hip fracture presenting as a shortened, externally rotated leg in a patient who cannot bear weight after a fall.
Neurologic emergencies
For suspected stroke, use BE-FAST: Balance loss, Eyes (sudden vision change), Face droop, Arm drift, Speech difficulty, Time — establish and document the last known well time, which is the time the patient was last seen at neurologic baseline, not the time symptoms were discovered. Activate the stroke alert, keep the patient NPO until a swallow screen is passed, obtain a point-of-care glucose (hypoglycemia is the great stroke mimic), and get the patient to non-contrast CT. Standard targets are door-to-CT within 25 minutes and door-to-needle for thrombolysis within 60 minutes; IV thrombolysis is generally considered within 4.5 hours of last known well, and mechanical thrombectomy in selected patients up to 24 hours. Deficit severity is scored with the NIHSS, 0 to 42.
Rising intracranial pressure announces itself in level of consciousness first — restlessness, then confusion, then a falling GCS — followed by headache, vomiting, and pupillary changes (a sluggish then fixed, dilated pupil on the side of the lesion from third nerve compression). Cushing triad — rising systolic blood pressure with a widening pulse pressure, bradycardia, and irregular or slowed respirations — is a late sign of impending herniation, not an early warning. Normal pulse pressure is 30–40 mmHg; a pressure of 180/60 in a head-injured patient with a heart rate of 48 is an emergency call, not a documentation entry. Decorticate posturing (flexion toward the core) is bad; decerebrate posturing (extension) is worse; progression from one to the other is deterioration.
Autonomic dysreflexia occurs in patients with spinal cord injury at or above T6: a noxious stimulus below the level of injury triggers sudden severe hypertension (systolic often 20–40 mmHg above the patient’s baseline, sometimes far higher), a pounding headache, bradycardia, flushing and sweating above the lesion with pallor and cool skin below, nasal congestion and anxiety. Act in this order: sit the patient upright and lower the legs, loosen constrictive clothing and abdominal binders, then find and remove the trigger — a distended bladder or kinked catheter is the cause in the large majority, then fecal impaction, then skin pressure — while checking blood pressure every 2–5 minutes and calling for help. Untreated it causes stroke, seizure and death.
| Parameter | Adult expected | Across the lifespan |
|---|---|---|
| Heart rate | 60–100 beats/min | Newborn 100–180; infant 100–160; toddler 90–140; preschool 80–120; school-age 75–118; adolescent 60–100 |
| Respiratory rate | 12–20 breaths/min | Newborn 30–60; infant 30–53; toddler 22–37; preschool 20–28; school-age 18–25; adolescent 12–20 |
| Blood pressure | Less than 120/80 mmHg; pulse pressure 30–40 | Pediatric BP is percentile-based by age, sex and height; older adults commonly have wider pulse pressures from arterial stiffening |
| Temperature | 36.5–37.5 °C (97.7–99.5 °F) oral | Older adults run lower and may not mount a fever with infection; infants lose heat quickly |
| SpO2 | 95–100% on room air | Chronic lung disease targets are often 88–92% per order |
| Pupils | 2–5 mm, equal, round, briskly reactive | Smaller and more sluggish in older adults; up to 1 mm anisocoria may be physiologic if longstanding and reactive |
| GCS | 15 | Pediatric GCS uses age-appropriate verbal and motor responses |
Serial checks, charting and SBAR
Neurologic checks are ordered at a frequency (every 15 minutes, hourly, every 4 hours) because trend is the finding. Perform them the same way every time, at the same depth, using the same stimulus — otherwise the “change” you detect is your technique. A complete neuro check includes level of consciousness and orientation, GCS components, pupils (size in millimeters and reactivity, both eyes), motor strength in all four extremities, sensation, speech quality and vital signs.
| Vague entry | Precise entry a nurse can act on |
|---|---|
| “Neuro checks WNL. Pupils equal.” | “Alert and oriented ×4. GCS 15 (E4 V5 M6). Pupils 3 mm bilaterally, round, brisk to light, consensual intact. Strength 5/5 all four extremities, no pronator drift. Sensation intact to light touch all extremities. Speech clear, no aphasia or dysarthria. BP 128/74, HR 76, RR 16.” |
| “Patient more sleepy this shift, will monitor.” | “1400: GCS 11 (E3 V3 M5), down from 15 at 1200. Right pupil 5 mm sluggish, left 3 mm brisk. Left arm drift with 3/5 grip, right 5/5. BP 176/62 (pulse pressure 114, was 128/78), HR 52, RR 10 and irregular. Rapid response activated 1403, provider notified 1404.” |
| “Complains of cast pain, medicated.” | “2210: Right forearm pain 9/10, unrelieved 45 min after oxycodone 5 mg, described as deep and burning, markedly worse with passive finger extension. Fingers cool and dusky compared to left, cap refill 4 sec (left 2 sec), numbness in index and middle fingers, radial pulse palpable. Cast intact and snug. Limb kept at heart level, not elevated. Provider paged 2212.” |
When you escalate, use SBAR so the person on the other end of the phone gets what they need in fifteen seconds. Compartment syndrome example: S — “This is Jordan Ellis, RN, on 4 West. I’m calling about Mr. Alvarez in 412, post-op day one right radius ORIF with a long-arm cast. I am concerned about acute compartment syndrome.” B — “He fell yesterday, had a closed distal radius fracture repaired at 1500, has had a well-controlled pain score of 3 to 4 all evening.” A — “Since 2130 his pain is 9 out of 10, unrelieved by oxycodone, and severely worse with passive extension of his fingers. He has new numbness in the index and middle fingers, cap refill 4 seconds on the right versus 2 on the left, fingers cool and dusky. Radial pulse is still present. I have kept the arm at heart level and removed nothing.” R — “I need you to evaluate him now for compartment syndrome and give me an order to bivalve or remove the cast. Can you come to the bedside, or should I activate the rapid response team?”
Stroke example: S — “Room 216, Mrs. Chen, new left-sided weakness and slurred speech, I am calling a stroke alert.” B — “72-year-old admitted for pneumonia, atrial fibrillation, on apixaban, baseline oriented ×4 and independent.” A — “Last known well 1830 when I gave her medications. At 1905 she has left facial droop with forehead sparing, left arm drift with 2/5 grip, left leg 4/5, dysarthric speech, BE-FAST positive. Glucose 112. BP 168/88, HR 96 irregular. NPO, head of bed 30 degrees, IV patent.” R — “I need stat CT and the stroke team at the bedside now; please confirm the code stroke activation.”
Delegation and scope
The Five Rights of Delegation are right task, right circumstance, right person, right direction and communication, right supervision and evaluation. The rule that never bends: the RN may delegate a task, never the nursing process. Assessment, interpretation, teaching, evaluation, clinical judgment and any patient who is unstable or changing stay with the RN. A UAP may collect data and report it; only the RN may decide what it means.
| May be delegated to UAP | Stays with the RN (or LPN/LVN per state scope) |
|---|---|
| Ambulating a stable patient with a specified device and level of assistance | The initial and any ongoing musculoskeletal or neurologic assessment, including the first ambulation after a change in status |
| Performing taught passive or active-assist range of motion on a stable patient | Determining that range of motion is safe, and interpreting new pain or resistance during it |
| Applying an ordered immobilizer, splint or compression device that is already fitted | Neurovascular checks distal to a fracture, cast or surgical site — and the decision that a limb is compromised |
| Repositioning, transferring with a lift, applying a gait belt, sitting with a fall-risk patient | Fall-risk assessment and the plan of care that follows it; teaching the patient and family |
| Measuring and reporting vital signs and pulse oximetry on a stable patient | Neuro checks and GCS scoring, orthostatic vital signs on a symptomatic patient, and any vital sign on an unstable patient |
| Reporting exactly what was observed — “he could not lift his left arm during his bath” | Deciding what that observation means, escalating it, and documenting the assessment |
Pain out of proportion under a cast, a new focal deficit, a falling GCS with a widening pulse pressure, saddle anesthesia with retention, and severe hypertension with headache in a T6-or-above spinal cord injury are all escalations now — delivered in SBAR, by the RN, with a specific request attached.
The chapter in one breath
The musculoskeletal and neurologic exams are built the same way: inspect, palpate, percuss and auscultate — the sequence used in every region except the abdomen, where auscultation moves ahead of percussion and palpation so the bowel is heard before it is provoked — then, for joints, add active range of motion, passive range of motion and strength graded 0 to 5, always compared left to right. Range of motion is charted in degrees; effusion, warmth and crepitus are found with your hands; gait and the Timed Up and Go (12 seconds or more equals fall risk) tell you whether any of it works. On the neurologic side, level of consciousness comes first, scored as a GCS documented in its components, followed by orientation, delirium screening with the CAM, cranial nerves I to XII, motor tone and pronator drift, cerebellar coordination, sensation mapped to dermatomes, and reflexes graded 0 to 4+ with 2+ expected. The patterns then sort themselves into upper versus lower motor neuron. Findings only matter if they are trended and charted concretely and, when they are red flags — compartment syndrome, cauda equina, autonomic dysreflexia, stroke, rising intracranial pressure — escalated immediately in SBAR by the RN, who may delegate the task but never the assessment.
Words worth knowing
| Term | What it means |
|---|---|
| Active range of motion | Movement the patient produces themselves; tests joint, muscle, nerve and willingness together. |
| Passive range of motion | Movement you produce for a relaxed patient; isolates the joint itself. |
| Crepitus | Palpable or audible grating within a joint or under the skin during movement. |
| Bulge sign | Bedside maneuver that reveals a small knee effusion by milking fluid from one side of the patella to the other. |
| Antalgic gait | A limp in which the patient shortens time spent bearing weight on the painful limb. |
| Trendelenburg sign | Pelvic drop on the unsupported side during single-leg stance, indicating gluteus medius weakness on the standing side. |
| Timed Up and Go (TUG) | Rise, walk 10 feet, turn, return, sit; 12 seconds or more indicates increased fall risk. |
| Neurovascular check | Serial assessment distal to an injury or cast — colour, temperature, capillary refill, pulses, sensation, movement, pain and edema. |
| Compartment syndrome | Rising pressure inside a closed fascial space causing ischemia; earliest signs are pain out of proportion, pain on passive stretch and paresthesia. |
| Glasgow Coma Scale (GCS) | Standardized score of eye, verbal and motor response, 3 to 15; 8 or less signals inability to protect the airway. |
| Pronator drift | Downward drift and pronation of one outstretched arm with eyes closed — a sensitive sign of a contralateral corticospinal lesion. |
| Dysmetria | Overshooting or undershooting a target on finger-to-nose testing; a cerebellar sign. |
| Romberg test | Standing with feet together, eyes open then closed; increased sway with eyes closed indicates proprioceptive or vestibular dysfunction. |
| Babinski response | Great toe dorsiflexion with fanning on plantar stimulation; normal until about 2 years of age, an upper motor neuron sign after that. |
| Clonus | Rhythmic involuntary beats of plantar flexion after brisk dorsiflexion; sustained clonus is always abnormal. |
| Dermatome | The skin region supplied by a single spinal nerve root, used to localize sensory loss. |
| Aphasia | Loss of language — expressive (halting, effortful) or receptive (fluent but meaningless) — distinct from dysarthria, which is slurred articulation. |
| Cushing triad | Rising systolic pressure with widening pulse pressure, bradycardia and irregular respirations; a late sign of rising intracranial pressure. |
| Autonomic dysreflexia | Severe hypertension with headache and flushing above the lesion in spinal cord injury at or above T6, triggered by a noxious stimulus below it. |
| Cauda equina syndrome | Saddle anesthesia, urinary retention or incontinence and bilateral leg weakness from compression of the lumbosacral nerve roots; a surgical emergency. |
Check yourself
Hygiene, Mobility, Skin Integrity and Core Skills
This is the chapter where assessment stops being something you look at and becomes something you do with your hands. Bathing a patient is the most complete skin survey anyone will perform that shift. Turning a patient is a pressure-injury intervention, a lung-expansion intervention and a circulation check at the same time. Walking a patient down the hall is a gait exam, an orthostatic screen and a fall-risk test rolled into one. The skills in this chapter — hygiene, positioning, safe patient handling, fall and restraint management, pressure-injury prevention and staging, medication administration and elimination care — are the ones that fill your first shifts, and they are also the ones most likely to harm someone if performed carelessly. A wrong water temperature, an unclamped drainage bag, a restraint tied to a side rail, a missed heel: each is a small technical error with a body attached to it. Learn the sequence, learn the numbers, and learn what you must never hand off.
By the end of this chapter you can
- Perform a bed bath, oral care, perineal care and foot care using correct clean-to-dirty sequence, and use the bath as a head-to-toe skin assessment.
- Describe the systemic complications of immobility and apply range-of-motion, positioning and progressive-mobility interventions to prevent them.
- Apply safe patient handling principles, including the 35-pound manual lift limit, gait-belt use and selection of the correct mechanical lift.
- Screen fall risk with the Morse Fall Scale and the Timed Up and Go, and carry out a correct post-fall response.
- State the legal definition of a restraint, the order and monitoring timeframes for violent and non-violent restraint, and safe application technique.
- Score the Braden Scale and stage a pressure injury as Stage 1 through 4, unstageable or deep tissue pressure injury, including in darkly pigmented skin.
- Administer medication using the rights of medication administration and the three checks, with two patient identifiers.
- Provide urinary and bowel elimination care, including CAUTI prevention, and perform abdominal assessment in the correct sequence.
- Distinguish what may be delegated to UAP from what must stay with the RN, and escalate a red-flag finding using SBAR.
Section 1Hygiene: The Most Thorough Assessment You Will Do All Shift
The bath is an assessment, not a chore
New nurses often think of the bath as the task you do before the real nursing starts. It is the other way around. During a complete bed bath you will see and touch the scalp, both ears, the neck, both axillae, the entire back, the sacrum, the perineum, the gluteal folds, both heels and the web spaces between every toe. There is no other routine activity that inspects those surfaces. Pressure injuries, incontinence-associated dermatitis, a heel that has turned boggy, a new rash under a breast, an untrimmed nail digging into a neighboring toe, a hearing aid that has been in for three days — all of it surfaces during the bath and nowhere else.
Work in an order and keep it the same every time so nothing gets skipped. Gather supplies first so you never leave the bedside. Raise the bed to your hip height and lower the side rail on your working side. Provide privacy, close the door, and keep the patient covered with a bath blanket, exposing only the region being washed — this preserves dignity and prevents chilling, which matters enormously in older adults. Water should be about 110–115°F (43–46°C); test it with a thermometer or the inner surface of your wrist, and use the cooler end of that range for anyone with diabetes, peripheral neuropathy, spinal cord injury or thin fragile skin who cannot reliably feel a burn. Change the water when it cools or becomes soapy.
The sequence is always clean to dirty. Eyes first, with no soap: use a separate corner of the washcloth for each eye and wipe from the inner canthus outward, so you never drag debris toward the tear duct. Then face, neck, arms with the far arm first, chest, abdomen, legs with the far leg first, back, and perineum last. Wash, rinse and dry each region completely before moving on — moisture trapped in the skin folds of the groin, under the breasts and in the pannus is where fungal rashes and moisture-associated skin damage begin. Pat dry; do not rub fragile skin. Apply moisturizer to dry areas, but never massage over a reddened bony prominence — friction over an already-injured microcirculation makes the injury worse.
Oral care, dentures and the patient who cannot protect an airway
Oral care is the hygiene task most often skipped and the one with the clearest link to hard outcomes. Dental plaque is colonized within days by respiratory pathogens, and micro-aspiration of that plaque is a principal route to hospital-acquired and ventilator-associated pneumonia. The evidence-based core is simple and unglamorous: brush the teeth with a soft toothbrush and fluoride toothpaste at least twice a day, including in intubated and comatose patients. Foam swabs alone do not remove plaque; they moisten. Routine chlorhexidine rinses, once standard in ventilator bundles, are no longer recommended for most non-cardiac-surgical patients — follow your facility protocol, but do not let a rinse substitute for a brush.
For the unconscious or dysphagic patient, positioning is the safety step. Place the patient in a side-lying position with the head turned toward you, or elevate the head of the bed and turn the head to the side, and keep suction on and within reach before you start. Use only a small amount of fluid, suction as you go, and never place your fingers between the teeth of a patient who may bite. Document the amount of secretions removed and the condition of the mucosa: pale, dry, cracked lips and a furrowed tongue point to dehydration; white plaques that scrape off point to candidiasis; spontaneous gingival bleeding raises the question of thrombocytopenia or anticoagulation.
Dentures are prostheses and are handled like them. Line the sink with a washcloth or fill it with water before you begin so a dropped denture does not shatter, and clean with cool or tepid water — hot water warps acrylic. Store dentures in a labeled, lidded container with water or denture solution, never wrapped in a tissue on the overbed table, which is how they end up in the laundry. Assess the underlying gums each time the dentures are out; a denture that has become loose after weight loss abrades the mucosa and causes ulcers that the patient will not mention.
Perineal care, foot care and shaving
Perineal care prevents infection and protects skin that is bathed in urine and stool. For a female patient, separate the labia and clean from the pubis toward the rectum in single downward strokes, using a clean section of the cloth for each stroke, and never returning upward — front to back, every time, because the female urethra is short — only about 4 cm long — and its meatus sits just centimeters from the anus. For a male patient, clean the tip of the penis in a circular motion beginning at the meatus and working outward. If the patient is uncircumcised, retract the foreskin, clean, and then replace the foreskin before you leave the bedside; a foreskin left retracted can swell and become entrapped, which is paraphimosis and a urologic emergency. Clean the scrotum and the perineum last.
Foot care is where a routine hygiene task becomes a limb-saving one. Inspect the soles, the heels and every web space, and ask the patient to look too or use a mirror at home. In patients with diabetes or peripheral arterial disease, do not soak the feet, do not use hot water, do not apply lotion between the toes, and do not cut the toenails — file straight across if permitted, and refer nail trimming to a podiatrist or an advanced clinician per policy. A single nick in a neuropathic, poorly perfused foot can become the ulcer that ends in amputation. For shaving, use an electric razor for any patient on anticoagulants, with thrombocytopenia, or with a bleeding disorder.
| What you find during hygiene | Expected | Abnormal — and what it suggests |
|---|---|---|
| Sacral skin after turning | Redness that blanches and resolves within 30 minutes of pressure relief | Non-blanchable erythema over the sacrum: Stage 1 pressure injury; purple or maroon discoloration: deep tissue pressure injury |
| Skin folds (groin, under breasts, pannus) | Dry, intact, same color as surrounding skin | Moist, macerated, bright red with satellite lesions: intertrigo or candidiasis, not pressure |
| Oral mucosa | Pink, moist, intact; tongue midline and moist | Dry and furrowed: dehydration. White adherent plaques: candidiasis. Bleeding gums: low platelets or anticoagulation |
| Heels | Skin intact, no tenderness, warm and equal to the other heel | Boggy, cooler, or a purple patch: developing deep tissue injury under an intact surface |
| Feet in diabetes | Warm, hair present, pulses palpable, no lesions | Cool, hairless, thin shiny skin, a painless ulcer over a pressure point: arterial disease with neuropathy — escalate |
| Perianal skin in an incontinent patient | Intact, dry between episodes | Diffuse red, weepy, poorly demarcated rash on the buttocks: incontinence-associated dermatitis, not a pressure injury |
How to chart it. Vague: “Bath given, skin ok.” Precise: “0930 Complete bed bath with assist of 1. Skin assessed head to toe. 2 cm area of non-blanchable erythema over left ischial tuberosity, intact, no induration, patient reports tenderness 3/10 with palpation. All other surfaces intact. Repositioned to right 30-degree lateral, heels floated on pillow, offloading schedule initiated q2h. Braden rescored 14. Wound care consult requested via order entry.”
Hygiene is the only routine activity that inspects and touches every square inch of the patient, so treat the bath as a scheduled full-body assessment that you own even when someone else does the washing.
Section 2Mobility, Positioning and Safe Patient Handling
What immobility does, system by system
Bed rest is a treatment with a dose-dependent toxicity, and the toxicity begins on day one. Skeletal muscle strength falls roughly 1 to 1.5 percent per day of strict bed rest, so a week of immobility can cost close to ten percent of a patient’s strength; bone demineralizes at about one percent per week; plantar flexion contracture — foot drop — can become fixed within a week or two without positioning and range of motion. In the lungs, supine positioning plus shallow breathing collapses dependent alveoli and pools secretions, producing atelectasis first and pneumonia after. In the vasculature, venous stasis joins endothelial injury and hypercoagulability to complete Virchow’s triad, and venous thromboembolism follows.
Autonomic reflexes deteriorate as well, which is why a patient who was fine three days ago becomes lightheaded the first time you stand them up. Orthostatic hypotension is a fall in systolic pressure of at least 20 mmHg or in diastolic pressure of at least 10 mmHg within three minutes of standing. Measure it deliberately: blood pressure and pulse supine after five minutes of rest, then again at one minute and three minutes after standing. A pulse rise of more than 20 beats per minute with the pressure drop points toward volume depletion rather than pure autonomic failure. Elsewhere, gut motility slows and constipation follows, urine stagnates in a flat renal pelvis and predisposes to stasis, infection and calculi, and unrelieved interface pressure begins the pressure-injury cascade covered in Section 4.
The intervention is not rest — it is progressive mobility, started early and escalated by protocol: passive range of motion, to active-assist, to dangling at the edge of the bed, to standing, to chair, to ambulation. Get the patient out of bed for meals. Ambulate at least three times a day if the plan allows. Use incentive spirometry ten times an hour while awake, apply sequential compression devices when ordered, and reposition on a schedule. Do not use the Homans sign to screen for deep vein thrombosis; it is neither sensitive nor specific, and squeezing a calf that contains a clot is not a clever idea.
Positioning, range of motion and the dangle
Positions have names because those names carry angles, and the angles carry consequences. Know them cold, because a provider order will say “semi-Fowler” and expect you to produce it.
| Position | Description | Used for — and the caution |
|---|---|---|
| Supine | Flat on the back, head of bed 0° | Spinal alignment, post-procedure. Highest sacral and heel pressure — float heels |
| Semi-Fowler | Head of bed 30–45° | Aspiration prevention, tube feeding, respiratory ease; 30° is the ceiling for pressure-injury prevention unless clinically required |
| Fowler / High Fowler | 45–60° / 60–90° | Dyspnea, meals, suctioning; above 30° shear on the sacrum rises sharply |
| 30° lateral side-lying | Rolled a third of the way over with pillows behind the back | The preferred turn. Avoid true 90° side-lying, which loads the greater trochanter directly |
| Sims | Left side-lying, lower arm behind, upper knee flexed | Enemas, suppositories, rectal exam, unconscious patient drainage |
| Prone | Face down, head turned | Refractory hypoxemia (proning); guard eyes, breasts, genitals, and pad the face |
| Trendelenburg | Whole bed tilted head-down | Rarely indicated; raises intracranial pressure and worsens ventilation — do not use routinely for hypotension |
Range of motion keeps joints from becoming the reason a recovered patient cannot go home. Perform passive range of motion when the patient cannot move a limb, active-assist when they can partially, and active when they can. Support the joint above and below, move slowly and smoothly through the available arc, repeat each movement three to five times, two or three times daily, and stop at the point of resistance or pain — never force a joint. Build it into the bath so it actually happens. Prevent foot drop with a foot board, high-top shoes or a splint per order, and prevent hip external rotation with a trochanter roll.
Before any patient stands for the first time in days, dangle. Raise the head of the bed, pivot the patient to sitting at the edge with feet flat on the floor, and let them sit for one to five minutes while you take a pulse and ask about dizziness. Apply nonskid footwear and the gait belt while they sit. If they report lightheadedness, blur or nausea, or the pulse jumps, lay them back down and recheck orthostatic vital signs. The dangle costs sixty seconds; the fall it prevents costs a hip.
Transfers, gait belts and mechanical lifts
Manual patient lifting is the leading cause of career-ending back injury in nursing, and the arithmetic is not close. The recommended maximum weight a single caregiver should manually lift, under ideal conditions, is 35 pounds (about 16 kg). Almost no adult patient weighs 35 pounds. That means the correct answer to “how do I move this patient” is usually equipment plus a second person, not better body mechanics. Choose by weight-bearing ability: a patient who can bear no weight or who is uncooperative requires a full-body mechanical lift with two staff; a patient who can bear partial weight, is cooperative and has upper-body strength may use a sit-to-stand lift; a patient who can bear full weight and follow directions may transfer with a gait belt and stand-by assist. Friction-reducing slide sheets and air-assisted lateral transfer devices are for bed-to-stretcher moves.
Body mechanics still matter for the moves that remain. Raise the bed to hip height while working and lower it to its lowest position when you leave. Stand with feet shoulder-width apart, one foot slightly ahead, for a wide base. Bend at the hips and knees, not the waist. Keep the load close to your center of gravity. Pivot with your feet — never twist your spine. Push or slide rather than lift. Face the direction of movement, count out loud so everyone moves together, and name one person as the leader.
Apply a gait belt over clothing, snug around the waist with room for two fingers underneath, buckle to the front or side. Do not use a gait belt over an abdominal incision, colostomy, feeding tube, chest tube, recent abdominal aortic aneurysm repair, or a pregnant abdomen — use an alternate device or a lift. When ambulating, stand on the patient’s weaker side, slightly behind, with one hand grasping the belt underhand at the back and the other near the shoulder. If the patient begins to fall, do not try to hold them upright. Pull them toward your body, ease them down along your leg to the floor while protecting the head, call for help, and assess before you move them.
| Device or maneuver | The rule |
|---|---|
| Cane | Held on the strong (unaffected) side. Handle at hip/greater trochanter level, elbow flexed about 15–30°. Advance cane and weak leg together, then the strong leg |
| Walker | Advance the walker 6–12 inches, step in with the weak leg, then the strong leg. All four points on the floor before stepping. Do not use a standard walker on stairs |
| Crutches | Weight on the hands, never the axillae — axillary pressure causes brachial plexus palsy. Two to three finger widths between axilla and crutch pad |
| Stairs | Up with the good leg first; down with the bad leg and the crutches or cane first |
| Wheelchair transfer | Chair on the patient’s strong side at a 45° angle, brakes locked, footrests up and out of the way, patient’s feet flat, pivot on the strong leg |
Immobility injures every organ system within days, so mobilize early and by protocol — and when you move a patient, let equipment carry the load, because 35 pounds is the honest limit of what one nurse should lift.
Section 3Falls, Restraints and the Least-Restrictive Envelope
Screening fall risk with real numbers
Falls are the most common adverse event in hospitals, and roughly a third of inpatient falls cause injury. Screening is done on admission, at every transfer of care, after any change in condition, after a fall, and at least each shift in most facilities. The Morse Fall Scale is the most widely used inpatient tool and scores six items: history of falling in the past three months (25 points), a secondary medical diagnosis (15), ambulatory aid — none, bed rest or nurse-assisted 0, crutches, cane or walker 15, holding onto furniture 30 — an intravenous line or saline lock (20), gait — normal, bed rest or wheelchair 0, weak 10, impaired 20 — and mental status, where a patient oriented to their own ability scores 0 and one who overestimates or forgets limitations scores 15. The total runs 0 to 125. The published cut-offs are 0–24 no risk, 25–44 low to moderate risk and 45 or higher high risk, though facilities calibrate their own thresholds. The Hendrich II tool is the other common instrument, with a score of 5 or more indicating high risk.
Two performance tests add information a paper score cannot. In the Timed Up and Go, the patient rises from a standard armchair, walks 10 feet (3 meters), turns, walks back and sits down; 12 seconds or longer indicates increased fall risk. The 30-second chair stand and the 4-stage balance test round out the CDC screening battery. Do not forget the medication review, which is often the highest-yield intervention: benzodiazepines, opioids, antipsychotics, antihypertensives, diuretics, hypoglycemics, anticholinergics and sedative-hypnotics all raise risk, and risk climbs steeply with four or more medications.
Note that the score is not the plan. A Morse score of 50 tells you the patient is high risk; it does not tell you whether the reason is orthostasis, an untreated urinary urgency, poor lighting, a new opioid or an unfamiliar walker. Interventions must match the mechanism.
The prevention bundle and the post-fall response
The bundle is unglamorous and it works. Bed in the lowest position and locked. Call light, phone, water and glasses within reach and demonstrated, not just placed. Nonskid footwear whenever out of bed. Adequate lighting, night light on, clutter and cords cleared, spills wiped immediately. Purposeful hourly rounding using the four Ps — pain, potty, position and possessions — because the most common fall is a patient trying to reach a bathroom alone. Toileting on a schedule for anyone with urgency, delirium or diuretics. Bed and chair alarms per policy, high-risk identifiers on the door and wristband, and a room near the nurses’ station for the highest-risk patients. Note that alarms alone have not been shown to reduce falls; they are a supplement to rounding, not a replacement.
If a patient does fall, the sequence protects them from a second injury. Do not move the patient first. Stay with them, call for help, and assess in place: level of consciousness, ability to move all extremities, pain, obvious deformity, head strike, and whether the fall was witnessed. Take a full set of vital signs including orthostatics when safe, check a blood glucose if the mechanism is unclear, and perform neurologic checks — especially in a patient on an anticoagulant, where a head strike is a potential intracranial bleed regardless of how well they look right now. Only after injury has been evaluated do you move them, with a lift and adequate staff. Notify the provider and the family, and initiate the frequency of neuro and vital sign checks that policy specifies.
How to chart it. Vague: “Patient found on floor. Incident report filed. Provider notified.” Precise: “0215 Unwitnessed fall. Patient found sitting on floor at right side of bed, bed in low position, call light on bed rail, nonskid socks on. Patient states ‘I was going to the bathroom.’ Alert and oriented x3, denies head strike, denies LOC. No deformity; ROM intact all extremities; reports 4/10 right hip pain with movement. VS 138/76, HR 92, RR 18, T 36.8 C, SpO2 96 percent RA, CBG 104. Neuro checks initiated q15 min x 4. Assisted to bed with 2 staff and full-body lift. Dr. Okonkwo notified 0222 via SBAR; hip and pelvis x-ray ordered. Morse rescored 55; bed alarm activated, scheduled toileting q2h initiated. Daughter notified 0240.” Note what is absent: an incident report is a quality document and is never referenced in the medical record.
Restraints: the legal definition, the order rules, the monitoring
A restraint is any manual method, physical or mechanical device, material or equipment that immobilizes or reduces the ability of a patient to move the arms, legs, body or head freely, or any drug used to manage behavior or restrict freedom of movement that is not a standard treatment for the patient’s condition. That definition catches things students do not expect: all four side rails raised is a restraint; a tucked-in sheet that prevents a patient from getting up is a restraint; a chair with a locking tray is a restraint. Two half rails raised so a patient can reposition themselves is not. A restraint is always the last resort after less restrictive alternatives have been tried and documented — sitter, family presence, orientation, toileting, pain relief, hearing aids and glasses, activity, lighting, reducing tethers, moving the patient nearer the station.
Restraints require an order from a physician or authorized licensed independent practitioner. PRN or standing restraint orders are prohibited. In an emergency a nurse may initiate restraint to protect the patient or others, but an order must be obtained immediately after, and a face-to-face evaluation must occur within one hour for violent or self-destructive restraint. The time limits differ by indication and by age.
| Element | Non-violent / non-self-destructive (medical-surgical) | Violent / self-destructive (behavioral) |
|---|---|---|
| Typical indication | Protecting a medical device — endotracheal tube, central line, surgical drain — in a confused patient | Imminent risk of harm to self or others |
| Order duration | Renewed per hospital policy, at minimum each calendar day after in-person re-evaluation | Adults 18 and older: 4 hours. Ages 9–17: 2 hours. Under 9 years: 1 hour. Renewable to a maximum of 24 hours, then a new in-person evaluation |
| Face-to-face evaluation | Per policy | Within 1 hour of initiation by a physician, LIP or trained RN |
| Monitoring | Assess at least every 2 hours: circulation, sensation, skin, range of motion, position, hydration, nutrition, toileting | Continuous monitoring; documented assessment at least every 15 minutes per policy |
| Release | Release, reposition, provide ROM and toileting at least every 2 hours | Release at the earliest possible moment; discontinue as soon as behavior criteria are met, without waiting for the order to expire |
Application technique is a safety skill. Use the least restrictive device that works. Pad bony prominences. Apply so that two fingers slide easily between the restraint and the skin. Secure with a quick-release knot — never a square knot — and tie to the movable bed frame, never to a side rail, because a rail that is lowered will torque or crush the limb. Keep the call light in the patient’s hand. Never leave a restrained patient alone in a room with the door closed unless continuous observation is in place. Document the behavior that necessitated restraint in objective, observable terms, the alternatives attempted and their failure, the order, the type and location of device, the release and reassessment times, and the criteria for discontinuation.
Screen fall risk with a validated score but treat the mechanism, assess a fallen patient before moving them, and treat restraint as a time-limited, ordered, continuously reassessed last resort — never a convenience.
Section 4Skin Integrity: The Braden Scale and Pressure Injury Staging
Assessing skin: the technique, and getting it right in every skin tone
Skin assessment follows the same order as every other regional exam — inspection first, then palpation — with adequate light and the surface fully exposed. Inspect for color, symmetry, moisture, lesions and hair distribution; then palpate for temperature with the dorsum of your hand, for texture, for turgor (over the sternum or forehead in older adults, since the back of the hand tents with age regardless of hydration), for edema (press over a bony prominence for at least five seconds), and for induration or bogginess. Systematically inspect every pressure point: occiput, ears, scapulae, elbows, spine, sacrum, coccyx, ischial tuberosities, greater trochanters, knees, malleoli and heels — plus every site touching a medical device, because oxygen tubing, cervical collars, endotracheal tube holders, pulse oximetry probes, casts and compression devices produce medical-device-related pressure injuries in the shape of the device.
The most consequential equity failure in this chapter is missing early pressure injury in patients with darker skin, who are demonstrably more likely to present at Stage 3 or 4 because Stage 1 was never seen. Non-blanchable erythema is described as red, but in darkly pigmented skin early pressure damage more often appears as an area that is simply darker-than-surrounding — gray, ashen or deeper in tone — and blanching may not be observable at all. Read the colour carefully, because it decides the stage rather than merely the detection: intact skin that is darker, gray or ashen than the surrounding tissue, with a change in temperature, firmness, sensation or pain, is a Stage 1; persistent purple, maroon or deep red discoloration over intact skin is not a Stage 1 but a deep tissue pressure injury, which carries a faster, more urgent escalation. So do not rely on color alone. Use temperature (compare the site with the mirror-image site on the other side using the back of your hand — early injury is often warmer, later injury cooler), consistency (boggy, mushy or firm compared with surrounding tissue), pain reported at the site, and moisture changes. Use natural or bright white light rather than yellow overhead light. Assess a patient’s general color changes where pigment is thin: cyanosis and pallor at the oral mucosa, conjunctivae, palms and soles and nail beds; jaundice at the sclera, hard palate and palms; erythema by warmth and tightness as much as by redness.
Lifespan matters too. Infants have a thin stratum corneum, a proportionally large occiput that becomes the number-one pressure site, and near-total device-related injury risk from probes and tubing. Children from about 21 days to 8 years of age should be scored with the Braden Q scale rather than the adult Braden. In pregnancy, positioning is left lateral tilt to avoid aortocaval compression, and edema and striae are expected. Older adults lose dermal thickness, subcutaneous fat over the trochanters and sacrum, elastin and sebum, so skin tears from tape and shear become a distinct injury category, and turgor is unreliable. Assess older skin gently, use silicone or paper tape, and lift rather than drag every single time.
The Braden Scale: what the number actually means
The Braden Scale for Predicting Pressure Sore Risk is scored on admission, then per policy — commonly every 24 hours on medical-surgical units, every shift in critical care — and again with any change in condition. It has six subscales. Five of them — sensory perception, moisture, activity, mobility and nutrition — score 1 to 4, and friction and shear scores 1 to 3. The total therefore ranges from 6 to 23, and here the counterintuitive part: a lower score means higher risk.
| Subscale | Range | What a low score is telling you |
|---|---|---|
| Sensory perception | 1–4 | The patient cannot feel or report discomfort — sedation, neuropathy, spinal cord injury, dementia |
| Moisture | 1–4 | Skin is constantly damp from incontinence, diaphoresis or wound drainage |
| Activity | 1–4 | Bedfast or chairfast |
| Mobility | 1–4 | Cannot make even slight changes in body or extremity position without help |
| Nutrition | 1–4 | Poor intake, NPO status, low albumin/prealbumin, unintentional weight loss |
| Friction and shear | 1–3 | Slides down in bed, requires maximum assist to move, spasticity or agitation |
| Total 19–23 no risk · 15–18 mild risk · 13–14 moderate risk · 10–12 high risk · 9 or below very high risk | ||
Two habits separate a nurse who uses Braden from a nurse who documents Braden. First, read the subscales, not just the total, because each low subscale names its own intervention: moisture of 1 means a barrier cream and a containment plan, nutrition of 2 means a dietitian consult, friction and shear of 1 means a slide sheet and a 30-degree head-of-bed limit. Second, remember the tool is a screen, not a verdict. A patient with a Braden of 20 who is going to the operating room for eight hours on a hard table, or who has a cast, or who is on vasopressors, is at real risk that the score does not capture. Clinical judgment overrides the number upward, never downward.
Staging: the deepest visible tissue defines the stage
Staging describes anatomy, not severity of appearance. Look at the deepest tissue you can actually see or palpate in the wound bed. If you cannot see the base, you cannot stage it.
| Stage | Defining features | Do not confuse it with |
|---|---|---|
| Stage 1 | Intact skin with localized non-blanchable erythema. In darker skin the area may not look red — look for skin that is darker, gray or ashen than the surrounding tissue; may be preceded by change in temperature, firmness, sensation or pain. Colour changes do not include purple or maroon | Blanchable reactive hyperemia, which resolves within about 30 minutes of offloading — and deep tissue pressure injury, because purple, maroon or deep red over intact skin is a DTPI, never a Stage 1 |
| Stage 2 | Partial-thickness loss with exposed dermis. Wound bed viable, pink or red, moist; may be an intact or ruptured serum-filled blister. No adipose, granulation tissue, slough or eschar | Incontinence-associated dermatitis, skin tears, tape injury, burns, abrasions — none of these are staged |
| Stage 3 | Full-thickness loss; adipose (fat) is visible. Granulation tissue and rolled edges (epibole) common; slough or eschar may be present but the base is visible. Undermining and tunneling may occur. Fascia, muscle, tendon, ligament, cartilage and bone are not exposed | Stage 4 — the discriminator is whether deeper structures are exposed or palpable |
| Stage 4 | Full-thickness skin and tissue loss with exposed or directly palpable fascia, muscle, tendon, ligament, cartilage or bone. Epibole, undermining, tunneling often present | Osteomyelitis is a complication, not a separate stage — escalate |
| Unstageable | Full-thickness loss in which the base is obscured by slough or eschar. Once debrided it will prove to be Stage 3 or 4 | Stable, dry, adherent eschar on a heel or an ischemic limb with no erythema, fluctuance or drainage is the body’s biologic cover — do not soften or remove it |
| Deep tissue pressure injury | Persistent non-blanchable deep red, maroon or purple discoloration of intact or non-intact skin, or epidermal separation revealing a dark wound bed or blood-filled blister. Pain and temperature change often precede the color change | A bruise. DTPI is not assigned a number; it may resolve or may deteriorate to Stage 3 or 4 within days |
Two additional categories exist. A medical-device-related pressure injury is staged with the same system and takes the shape of the device. A mucosal membrane pressure injury — from an endotracheal tube, a nasogastric tube, an indwelling catheter — cannot be staged, because mucosa has no keratinized epidermis or dermis to compare. Finally, pressure injuries do not reverse-stage. A healing Stage 4 that has filled with granulation tissue is documented as a “healing Stage 4 pressure injury,” never as a Stage 2, because the lost muscle and fat are replaced by scar, not by the original tissue.
Prevention that actually works
Reposition patients in bed at least every two hours and patients in a chair at least every hour — chair sitting concentrates enormous pressure on the ischial tuberosities, so teach capable patients to shift weight every 15 minutes. Turn to 30-degree lateral, not 90 degrees over the trochanter, and keep the head of bed at or below 30 degrees unless a clinical reason requires more, because higher elevation slides the skeleton down inside the skin and shears the sacral capillaries. Float the heels completely off the mattress on a pillow placed lengthwise under the calves with the knees slightly flexed; heels have almost no subcutaneous padding and are the second most common site after the sacrum. Use a pressure-redistributing surface for at-risk patients. Never use ring or donut cushions — they create a circle of ischemia around the very tissue you are protecting.
Manage moisture and nutrition as aggressively as pressure. Cleanse after each incontinence episode with a pH-balanced cleanser rather than soap, apply a barrier cream or film, and consider a containment strategy — but note that an indwelling catheter is not a pressure-injury intervention and trades one hospital-acquired infection for another. Involve a dietitian early; adequate protein and calories are the substrate for every repair. Use lift sheets and slide boards to eliminate dragging, keep linens dry and wrinkle-free, and inspect at every turn. And do not massage over bony prominences or reddened areas.
How to chart it. Vague: “Bedsore on bottom, dressing changed.” Precise: “1400 Sacral pressure injury, Stage 3, 3.5 cm x 2.8 cm x 0.6 cm deep, 100 percent red granulation, no slough, no undermining or tunneling detected with sterile probe. Moderate serosanguineous drainage, no odor. Periwound intact, no erythema, no induration. Patient reports 3/10 pain at dressing change, premedicated at 1330. Hydrocolloid applied per order. Braden 11 (sensory 2, moisture 1, activity 1, mobility 2, nutrition 3, friction/shear 2). Turn schedule q2h, heels floated, 30-degree lateral, HOB at 25 degrees. Dietitian consult in place.”
Score the Braden subscales as an intervention list rather than a number, stage by the deepest visible tissue, and never let redness be your only clue — in darker skin, temperature, firmness and pain are what find a Stage 1 before it becomes a Stage 4.
Section 5Core Skills: Medications, Elimination, Delegation and Escalation
The rights of medication administration and the three checks
Medication administration is a series of deliberate verifications, and skipping any one of them is how a fatal error happens quietly. The classic five rights are right patient, right drug, right dose, right route, right time. Contemporary practice adds right documentation, right reason (indication), right response (evaluation), right to refuse and right education. The rights are a framework, not a system — they tell you what to verify, while barcode scanning, independent double checks and pharmacy review are what make verification reliable.
Verify the drug against the medication administration record three times: when you take it from the storage or dispensing unit, when you prepare it and compare with the record, and again at the bedside immediately before giving it. Identify the patient with two identifiers — full name and date of birth, or name and medical record number. A room number is never an identifier. Scanning the wristband does not replace asking the patient to state their name and date of birth. Never give a medication you did not personally prepare, never leave medications at the bedside, and never chart a medication before it has been swallowed or infused.
A handful of specific rules prevent a disproportionate share of harm. High-alert medications — insulin, heparin and other anticoagulants, opioids, concentrated electrolytes, chemotherapy, neuromuscular blockers — require an independent double check by a second nurse per policy. Time-critical scheduled medications must be given within 30 minutes before or after the scheduled time; non-time-critical medications typically allow one to two hours per policy. Do not crush enteric-coated or extended-release tablets or open most capsules; check a “do not crush” list. For medications given by enteral tube, verify tube placement, elevate the head of bed at least 30 degrees, give each medication separately, and flush with 15–30 mL of water before, between and after. Avoid dangerous abbreviations: write “unit” not U, “daily” not QD, “every other day” not QOD, always use a leading zero (0.5 mg, never .5 mg) and never a trailing zero (5 mg, never 5.0 mg), because a misread decimal is a tenfold error. If a patient questions a medication — “that pill is usually pink” — stop and verify. The patient is often right.
If an error occurs, the order is fixed: assess the patient first, take vital signs, notify the provider, follow orders for monitoring or reversal, document the facts objectively in the chart, and complete the occurrence report separately.
Urinary elimination, catheters and CAUTI prevention
Know the numbers. A healthy adult produces about 1,200–1,500 mL of urine per day; the acceptable floor is 0.5 mL/kg per hour, and urine output of less than 30 mL per hour for two consecutive hours in an adult is a reportable finding. Oliguria is less than 400 mL in 24 hours and anuria less than 100 mL in 24 hours. Adult bladder capacity is roughly 300–600 mL, with the first urge felt around 150–300 mL. A bladder scan post-void residual above 100 mL deserves attention, and above about 200 mL is abnormal and usually triggers a straight catheterization protocol. Urine should be clear to amber; cloudy, malodorous, or dark tea-colored urine, or any frank blood, is abnormal.
An indwelling catheter is the single most modifiable cause of a hospital-acquired infection, so the first CAUTI intervention is to not place one. Legitimate indications are narrow: acute urinary retention or obstruction, accurate measurement in critically ill patients, selected perioperative needs, healing of Stage 3, 4 or unstageable perineal wounds in an incontinent patient, prolonged immobilization for trauma, and comfort at end of life. Incontinence alone, staff convenience and routine intake and output are not indications. If one is placed, insert with sterile technique: in a female patient, insert 5–7.5 cm (2–3 inches) until urine returns, then advance another 2.5–5 cm before inflating; in a male patient, hold the penis at a 90-degree angle and insert 17–22.5 cm (7–9 inches) until urine returns, then advance to the bifurcation. Inflate the balloon with the volume of sterile water printed on the balloon port, never with saline or air.
Maintenance is where infections are actually prevented. Keep the collection system closed and never disconnect it for convenience. Keep the bag below the level of the bladder at all times, including during transfers, and never on the floor. Keep the tubing free of dependent loops and kinks. Secure the catheter to the thigh or lower abdomen to prevent traction on the urethra. Perform routine meatal care with soap and water — antiseptics are not recommended and irritate the mucosa. Empty the bag with a patient-dedicated container before it is two-thirds full. Obtain specimens from the sampling port after disinfecting it, never from the drainage bag. And review the necessity every single day, because the strongest predictor of infection is the number of catheter-days.
Bowel elimination, ostomy care and the abdominal sequence
Before you give an enema, insert a rectal suppository, or evaluate constipation, assess the abdomen — and here the general exam sequence changes. Everywhere else in the body the order is inspection, palpation, percussion, auscultation. For the abdomen the order is inspection, auscultation, percussion, palpation, because percussing or palpating first mechanically stimulates the bowel and alters the bowel sounds you are about to count. Inspect contour, symmetry, distention, scars, stoma and visible peristalsis. Auscultate all four quadrants with the diaphragm, starting in the right lower quadrant near the ileocecal valve; normal sounds are irregular gurgles 5 to 30 times a minute, and you must listen a full five minutes in one quadrant before you may document absent bowel sounds. Then percuss for tympany over gas and dullness over organs or masses, and palpate lightly (about 1 cm) before deeply (4–5 cm), tender areas last. High-pitched tinkling or rushes with cramping suggests early obstruction; silence with a rigid, board-like abdomen suggests peritonitis and is a call-now finding.
Normal stool frequency ranges from three times a day to three times a week, and the Bristol Stool Form Scale is how you describe it: types 1 and 2 (hard lumps, lumpy sausage) indicate constipation, types 3 and 4 (cracked sausage, smooth snake) are normal, and types 5 through 7 (soft blobs, mushy, liquid) trend toward diarrhea. Watch for the classic trap: a patient who has had no formed stool for days and now has continuous small liquid leakage is not having diarrhea — that is likely fecal impaction with overflow, and giving an antidiarrheal will make it dangerous. Digital removal of an impaction requires an order and carries a real risk of vagal stimulation with bradycardia; stop immediately if the pulse drops or the patient becomes lightheaded.
For a cleansing enema, place the patient in the left Sims position with the right knee flexed, which follows the natural curve of the sigmoid colon. Solution should be about 105–110°F (40.5–43°C) — hot solution burns mucosa, cold solution causes cramping. Adult volume is typically 750–1,000 mL. Lubricate and insert the tube 7.5–10 cm (3–4 inches) in an adult, 5–7.5 cm in a child and 2.5–3.75 cm in an infant, aiming toward the umbilicus, and never force against resistance. Hang the bag about 30–45 cm (12–18 inches) above the anus and instill slowly; if the patient cramps, lower the bag and pause, do not stop and pull out. Ask the patient to retain the solution 5–15 minutes. Repeated tap-water enemas can cause water intoxication and hyponatremia, particularly in children and older adults, and hypertonic phosphate enemas can cause dangerous hyperphosphatemia in renal impairment.
Assess an ostomy every time you change the pouch. A healthy stoma is beefy red or pink, moist and budded slightly above skin level, and it is insensate, so slight bleeding with cleansing is expected. A pale stoma suggests anemia; a dusky, purple, brown or black stoma means ischemia and is an emergency. Cut the barrier opening about 1/8 inch (3 mm) larger than the stoma so effluent does not touch skin and the barrier does not constrict it. Empty the pouch when it is one-third to one-half full so weight does not break the seal. Ileostomy output is liquid to pasty and typically 500–1,000 mL daily; sustained output above roughly 1,200 mL per day is a dehydration and electrolyte emergency in the making. A colostomy in the descending or sigmoid colon produces formed stool.
Delegation, red flags and the SBAR call
Delegation is a nursing skill with a legal edge. Use the five rights of delegation — right task, right circumstance, right person, right direction and communication, right supervision and evaluation. The RN may delegate a task; the RN may never delegate the nursing process. Assessment, nursing diagnosis, planning, patient teaching and evaluation of response stay with the RN, as does any care for an unstable or unpredictable patient, and the accountability for the outcome stays with the RN regardless of who performed the task.
| May be delegated to UAP | Stays with the RN (or LPN/LVN per state scope) |
|---|---|
| Bathing, oral care, perineal care and shaving for a stable patient | The skin assessment and Braden scoring performed during that bath |
| Turning and repositioning on an established schedule; passive ROM already taught | Deciding the turning schedule, evaluating whether it is working, staging a wound |
| Ambulating a stable patient with an established plan and device | The first ambulation, any post-operative or newly-unsteady patient, and any gait assessment |
| Vital signs on a stable patient; recording intake and output; emptying drainage bags | Interpreting the vital signs and acting on them; evaluating urine output trends |
| Feeding a patient without swallowing risk; setting up meals; measuring weights | Feeding anyone with dysphagia; nutrition assessment; teaching |
| Applying nonskid footwear, activating a bed alarm, keeping call light in reach | Fall-risk scoring, restraint initiation and assessment, post-fall assessment |
| Assisting with a bedpan, emptying an ostomy pouch (per policy) | Medication administration, sterile catheter insertion, first ostomy assessment and teaching, nail care in a diabetic patient |
Now the findings that mean stop and call. Adult reference values for context: temperature 36.5–37.5°C (97.7–99.5°F) orally, heart rate 60–100, respiratory rate 12–20, blood pressure under 120/80, oxygen saturation 95–100 percent on room air. Ranges shift by age — newborn heart rate 100–160 and respiratory rate 30–60; infant 100–160 and 30–53; toddler 90–140 and 22–37; preschooler 80–120 and 20–28; school-age 70–120 and 18–25; adolescent and adult 60–100 and 12–20. In older adults the baseline temperature runs lower, so an oral temperature of 37.2°C (99°F), or a rise of 1.1°C (2°F) above the patient’s own baseline, may be the only sign of serious infection — and new confusion in an older adult is a vital sign in its own right.
| Red flag from this chapter’s skills | What it may mean | Act now |
|---|---|---|
| New purple or maroon patch over the sacrum or heel, skin intact | Deep tissue pressure injury — can become Stage 4 in days | Offload immediately, notify provider, wound consult, photograph per policy |
| Unilateral calf swelling, warmth, tenderness after immobility | Deep vein thrombosis | Do not massage the limb; keep the patient at rest pending evaluation, notify provider now, anticipate duplex ultrasound — ambulation resumes once anticoagulation is started |
| Sudden dyspnea, pleuritic chest pain, tachycardia, SpO2 drop | Pulmonary embolism | Oxygen, upright position, rapid response call |
| Urine output under 30 mL/hr for 2 hours, or no output from a catheter | Obstruction, hypovolemia or acute kidney injury | Check for kinks and dependent loops, bladder scan, notify provider |
| Stoma dusky, purple or black | Stomal ischemia or necrosis | Notify surgeon immediately — surgical emergency |
| Rigid, board-like abdomen with absent bowel sounds and severe pain | Peritonitis or perforation | NPO, do not give an enema or laxative, urgent provider notification |
| Fall with head strike in a patient on an anticoagulant | Intracranial hemorrhage, possibly delayed | Neuro checks, immediate provider notification, anticipate CT |
| Restrained limb that is cool, dusky, numb or pulseless | Circulatory compromise from the device | Release the restraint immediately, assess, notify provider, document |
The SBAR call. “S — Dr. Reyes, this is Priya Shah, RN on 4 West. I’m calling about Mr. Delacroix in 412. He has a new dusky purple stoma and I’m concerned about stomal ischemia. B — He is post-op day 2 from a sigmoid colectomy with an end colostomy. The stoma was beefy red and budded at 0800 this morning. A — At 1500 the stoma is dark purple across the entire surface, cool to touch, and does not bleed with gentle cleansing. Peristomal skin is intact. No output since 1100. Vitals: BP 148/88, HR 104, RR 20, temp 37.4 C, SpO2 96 percent on room air. Abdomen firm and tender, bowel sounds hypoactive. He rates pain 7/10, up from 3/10. R — I need you to come evaluate the stoma now. I’ve kept him NPO, held the 1600 stool softener, and I have the light and the pouch open for you. Do you want a lactate and a CBC drawn while you’re on your way, and should I notify the on-call surgeon?” Note the structure: one sentence of concern, the relevant history only, hard numbers, and a specific request with a closed-loop read-back at the end.
Verify medications three times against two identifiers, keep catheters and pouches out of trouble with technique rather than luck, remember that the abdomen is auscultated before it is touched, and escalate every red flag with a structured SBAR that ends in a specific request.
The chapter in one breath
The fundamentals are where assessment and intervention become the same act. A bed bath is a full-body skin survey performed clean to dirty with water near 110–115°F, and the sacrum, heels and every device site must be looked at by you, not just by whoever did the washing. Immobility costs about one to one and a half percent of muscle strength per day and drives atelectasis, thromboembolism, orthostasis, constipation and pressure injury, so mobilize by protocol, dangle before standing, and move patients with equipment because the honest one-nurse manual lift limit is 35 pounds. Screen falls with the Morse Scale — 45 or higher is high risk — or a Timed Up and Go of 12 seconds or more, and after a fall assess before moving. Restraints are a last resort with hard order limits: four hours for adults with behavioral restraint, two hours ages 9 to 17, one hour under 9, a face-to-face within one hour, tied to the frame with a quick-release knot. Score Braden from 6 to 23 where lower means worse, stage by the deepest visible tissue, and find Stage 1 in darker skin by temperature, firmness and pain rather than redness. Give medications by the rights with three checks and two identifiers, prevent CAUTI by not placing the catheter, auscultate the abdomen before you percuss or palpate it, and escalate every red flag in SBAR that ends with a specific ask.
Words worth knowing
| Term | What it means |
|---|---|
| Blanchable erythema | Redness that whitens under fingertip pressure and returns; normal reactive hyperemia, resolving within about 30 minutes of offloading |
| Non-blanchable erythema | Redness or darkening that persists under pressure; over a bony prominence with intact skin this is a Stage 1 pressure injury — but purple, maroon or deep red discoloration over intact skin is a deep tissue pressure injury, not a Stage 1 |
| Deep tissue pressure injury | Persistent deep red, maroon or purple discoloration, or a blood-filled blister, from damage at the bone-muscle interface; not assigned a number and may deteriorate rapidly |
| Unstageable pressure injury | Full-thickness loss whose base is obscured by slough or eschar; stage only after debridement, and never debride stable dry eschar on an ischemic heel |
| Braden Scale | Six-subscale pressure-injury risk tool scoring 6 to 23; lower is higher risk, with 18 or below generally considered at risk |
| Shear | Force from skeleton sliding inside the skin, as when the head of bed is raised above 30 degrees; it strangles the sacral microcirculation without visible surface friction |
| Friction | Surface abrasion from dragging skin across linen; prevented with lift sheets and slide devices, never by pulling |
| Orthostatic hypotension | Drop of at least 20 mmHg systolic or 10 mmHg diastolic within 3 minutes of standing; measured supine, then at 1 and 3 minutes standing |
| Morse Fall Scale | Six-item inpatient fall-risk tool scoring 0 to 125; commonly 45 or higher is high risk |
| Timed Up and Go | Rise from a chair, walk 10 feet, turn, return and sit; 12 seconds or longer signals increased fall risk |
| Restraint | Any device, material or drug that restricts free movement and is not standard treatment; requires an order, is never PRN, and is time-limited by age and indication |
| Quick-release knot | The only acceptable restraint knot, tied to a movable bed frame — never a side rail — and releasable with one hand in a single pull |
| Safe patient handling | Program of lifts, slide sheets and team moves built on the 35-pound recommended maximum manual lift for one caregiver |
| Gait belt | Belt applied over clothing with two fingers of room, used from the patient’s weaker side; contraindicated over abdominal incisions, ostomies, chest tubes and pregnancy |
| Rights of medication administration | Patient, drug, dose, route, time, plus documentation, reason, response, refusal and education — verified with three checks and two identifiers |
| Independent double check | Second-nurse verification of high-alert medications such as insulin, heparin and concentrated electrolytes, performed separately and not simply co-signed |
| CAUTI | Catheter-associated urinary tract infection; prevented by avoiding the catheter, closed drainage, bag below bladder, securement and daily necessity review |
| Fecal impaction with overflow | Continuous liquid leakage around a hardened stool mass in a patient with no formed bowel movement; mistaking it for diarrhea and treating with antidiarrheals is dangerous |
| Bristol Stool Form Scale | Seven-type stool descriptor: types 1–2 constipation, 3–4 normal, 5–7 loose to liquid |
| SBAR | Situation, Background, Assessment, Recommendation — the structured escalation format that must end in a specific request |