Musculoskeletal & Integumentary
This final chapter covers the frame and the wrapping — the bones and joints that hold us up and the skin that keeps the world out. It runs from fractures and their dangerous complications through the common joint diseases, then across the skin’s own disorders, infections, and the whole-body emergency of a serious burn.
By the end of this chapter you can
- Describe fracture types and the stages of bone healing.
- Recognize compartment syndrome and fat embolism as emergencies.
- Tell osteoarthritis from rheumatoid arthritis, and recognize gout and osteoporosis.
- Stage pressure injuries and recognize melanoma (ABCDE).
- Assess burn depth and size and name the priorities.
Section 1Fractures & bone healing
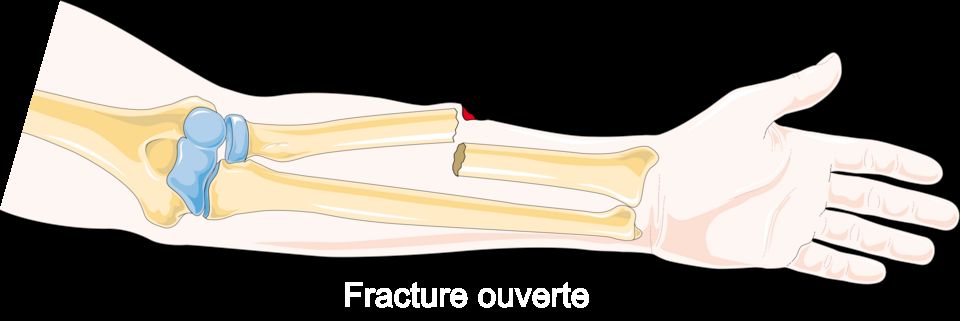
Bone looks solid and permanent, but it is actually living tissue that constantly rebuilds itself. A tough outer shell of compact (cortical) bone surrounds a spongy inner layer, and the whole thing is wrapped in a thin, blood-rich, nerve-rich membrane called the periosteum. Inside, bone cells work in a lifelong partnership: osteoblasts lay down new matrix, and osteoclasts break old matrix down. Because bone is loaded with blood vessels and nerves, a break bleeds and hurts a lot. A fracture is simply a break in the continuity of a bone, and it happens when the force applied is greater than the bone can absorb, whether from a fall, a crash, repetitive stress, or a bone already weakened by disease.
Types of fractures
Naming a fracture describes what actually happened to the bone, which guides how it is treated. The first question is always whether the skin is broken.
| Feature | Closed (simple) | Open (compound) |
|---|---|---|
| Skin | Intact over the break | Bone pierces skin or wound reaches the bone |
| Infection risk | Lower | High, an orthopedic emergency |
| Priority | Alignment and immobilization | Prevent infection (osteomyelitis), then repair |
Beyond that, we describe the break pattern. A complete fracture goes all the way through, splitting the bone into pieces. An incomplete fracture only cracks part way, and the classic example is a greenstick fracture, where a soft child's bone bends and splinters on one side like a young twig. Other common patterns include comminuted (the bone shatters into three or more fragments, often from high-energy trauma), transverse (a straight break across the shaft), oblique (an angled line), spiral (a twisting force, sometimes a red flag for abuse), compression (bone is crushed, typical in osteoporotic vertebrae), and pathologic (a break through bone already weakened by tumor or disease). A stress fracture is a tiny crack from repeated overuse.
How bone heals
Bone is one of the few tissues that can heal without a scar, rebuilding itself back to living bone. It moves through overlapping stages, usually taking weeks to months.
- Hematoma formation (first hours to days): torn vessels bleed, and a clot forms at the break. This fracture hematoma seals the ends and delivers inflammatory cells that clean up debris. This is why the area is swollen, warm, and painful early on.
- Soft callus (roughly days to 2-3 weeks): fibroblasts and chondroblasts build a soft bridge of fibrous tissue and cartilage between the fragments. It is fragile, which is exactly why the bone must stay still now.
- Hard callus (about 3 weeks to several months): osteoblasts replace the soft callus with woven bone, forming a bumpy but sturdy bony callus that unites the pieces.
- Remodeling (months to years): osteoclasts and osteoblasts reshape the callus along lines of mechanical stress, restoring the bone's original strength and contour.
Signs of a fracture, and why we align and immobilize
Suspect a fracture with pain that worsens with movement, swelling, bruising (ecchymosis), obvious deformity or shortening, loss of function, and sometimes crepitus, a grating sound or feel as bone ends rub. Alignment (reduction) puts the fragments back into their normal position so the callus bridges correctly and the limb heals straight. Immobilization with a cast, splint, or fixation holds that alignment so healing can proceed and, just as importantly, protects nearby nerves and vessels from being torn by sharp bone ends.
Why osteoporosis raises fracture risk
In a healthy adult, bone breakdown and rebuilding stay balanced. In osteoporosis, osteoclast activity outpaces osteoblast activity, so bone is resorbed faster than it is replaced. The result is low bone mass and deteriorated microarchitecture, leaving bone porous and brittle. It is often called a silent disease because there are no symptoms until a bone breaks. Falling estrogen after menopause is a major driver, since estrogen normally restrains osteoclasts. That is why postmenopausal women often suffer fragility fractures of the hip, wrist, and spine from forces that would never break healthy bone, sometimes just a minor bump or even a hard cough.
The interactive figure lets you compare fracture patterns and walk through the healing stages, so explore it below.
- A fracture is a break in bone continuity; describe it by skin status (open vs closed) and pattern (complete, greenstick, comminuted, and others) because those details guide treatment.
- Healing proceeds through hematoma, soft callus, hard callus, then remodeling, and the soft-callus stage is fragile, which is why immobilization matters.
- Classic signs include pain, swelling, deformity, loss of function, and crepitus; always check neurovascular status (the 5 P's) distal to the injury.
- Reduction restores alignment and immobilization holds it, allowing straight healing and protecting nearby nerves and vessels.
- Osteoporosis tips the balance toward resorption, creating porous, brittle bone and fragility fractures, especially in postmenopausal women.
Section 2Fracture complications
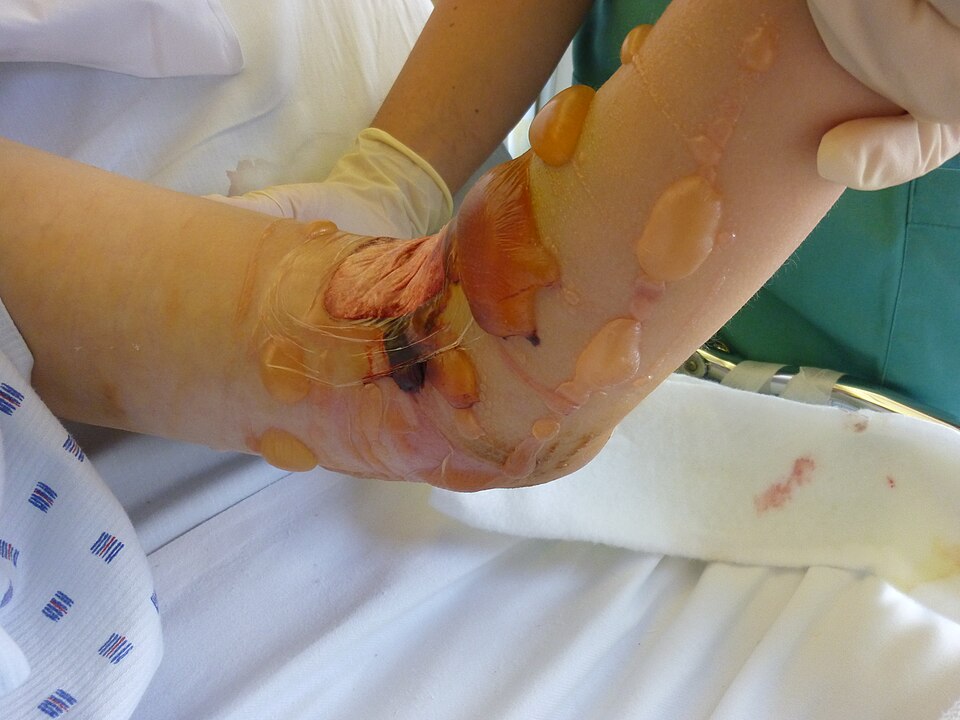
When a bone breaks, the body kicks off a beautifully organized repair project. Blood pools at the fracture site and clots into a hematoma, inflammatory cells clean up debris, a soft cartilage callus bridges the gap, and over weeks that callus is replaced by hard bone and finally remodeled back to shape. For this to work, the tissue around the break needs steady blood flow, oxygen, and room to swell. Most fracture complications happen when one of those requirements is violated: pressure builds where it cannot escape, clots or fat droplets travel where they should not, or the healing timeline stalls. Explore the interactive figure below as you read.
Compartment syndrome: pressure with nowhere to go
Muscles are packed into compartments wrapped by tough, inelastic fascia. After a fracture (classically the tibia or forearm), bleeding and swelling raise the pressure inside that closed box. Because the fascia will not stretch, rising pressure first collapses the thin-walled veins, so blood backs up and swelling worsens, then it squeezes capillaries until tissue no longer gets oxygen. This is acute compartment syndrome, and it is a surgical emergency: without prompt fasciotomy to open the compartment, muscle and nerve die within hours, sometimes costing the limb.
Bedside recognition rests on the 6 P's. The earliest and most reliable is pain out of proportion to the injury, especially pain on passive stretch of the fingers or toes. The others are paresthesia (pins-and-needles from nerve ischemia), pallor, poikilothermia (the limb drifts toward room temperature and feels cool), paralysis, and pulselessness. On palpation the compartment also feels tight and tense - a useful extra finding, but it is not one of the six P's. A crucial teaching point: pulselessness is a late sign. Waiting for the pulse to disappear means waiting until the muscle is already dying.
Fat embolism syndrome: droplets on the move
Long bones such as the femur and tibia, and the flat, irregular bones of the pelvis, all contain fatty yellow marrow. When they fracture, marrow fat can enter torn venous channels, travel to the lungs, and trigger an inflammatory cascade. Classic fat embolism syndrome (FES) shows up 12 to 72 hours after injury as a triad: respiratory distress (hypoxemia, tachypnea, dyspnea from fat lodging in pulmonary capillaries), neurologic changes (confusion, restlessness, decreased level of consciousness), and a petechial rash across the chest, axillae, and conjunctivae. Those petechiae are fairly specific, so watch for them. Care is largely supportive with oxygen; the best medicine is prevention through early fracture stabilization.
Clots from lying still: DVT and PE
Immobility after a fracture checks every box of Virchow's triad: venous stasis (no calf-muscle pumping), hypercoagulability (the injury itself is prothrombotic), and endothelial injury. The result is deep vein thrombosis (DVT), usually in the calf, with unilateral swelling, warmth, and tenderness. The feared sequel is a piece breaking off and lodging in the lung, a pulmonary embolism (PE), presenting as sudden dyspnea, pleuritic chest pain, tachycardia, and hypoxia. Prevention is nursing gold: early mobilization, sequential compression devices, and prophylactic anticoagulation.
| Feature | Fat embolism | Pulmonary embolism (from DVT) |
|---|---|---|
| Usual timing | 12 to 72 hours post-fracture | Days to weeks (immobility) |
| Embolic material | Marrow fat droplets | Blood clot |
| Telltale sign | Petechiae + confusion | Sudden pleuritic chest pain, leg DVT |
| Fracture link | Long-bone / pelvic | Any, from immobility |
When healing stalls: delayed union, nonunion, and infection
Healing needs blood supply, stability, and apposed bone ends. Delayed union is healing that is slower than expected but still progressing. Nonunion is a fracture that stops healing altogether, often from poor blood flow, too much motion, a wide gap, or infection, and typically requires surgery or bone grafting. Malunion heals in a crooked position. Osteomyelitis, a bone infection, is a special threat in open fractures where skin is broken and bacteria reach bone directly; it presents with localized pain, warmth, drainage, and fever, and is notoriously stubborn to clear.
- Compartment syndrome is a surgical emergency: pain out of proportion is the earliest sign and pulselessness is late, treat with fasciotomy, and never ice or elevate above the heart.
- The 6 P's: pain, paresthesia, pallor, poikilothermia (coolness), paralysis, pulselessness - with a tight, tense compartment as an extra palpation finding.
- Fat embolism follows long-bone or pelvic fractures at 12 to 72 hours with respiratory distress, neuro changes, and petechiae; prevent it with early stabilization.
- Immobility drives DVT and PE via Virchow's triad, prevent with early mobility, SCDs, and anticoagulation.
- Nonunion, malunion, and osteomyelitis stall recovery; frequent neurovascular checks are the nursing priority for catching complications early.
Section 3Musculoskeletal disorders
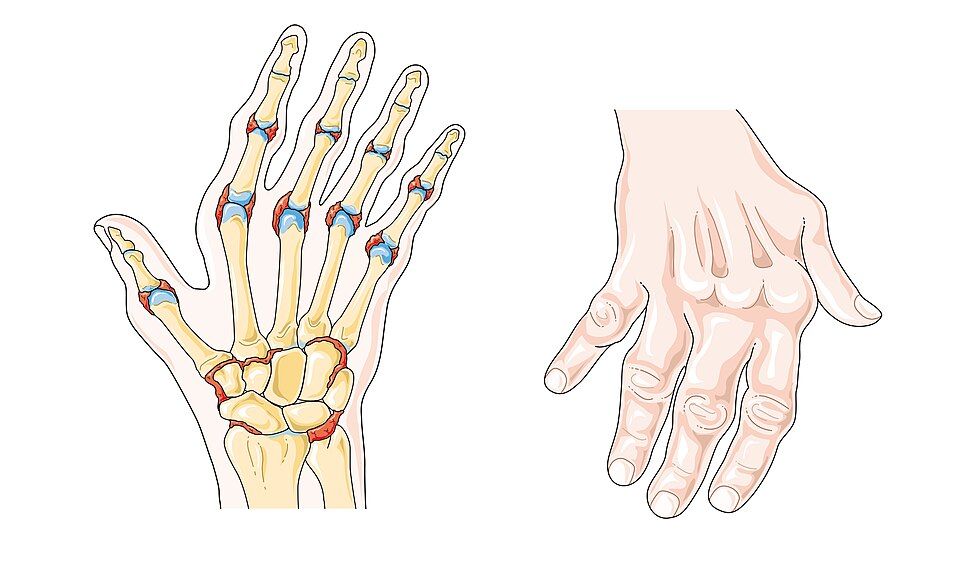
Bone can feel like the most lifeless part of us, but it is actually living, changing tissue. Throughout your whole life, two crews are at work: osteoblasts lay down new bone, and osteoclasts chew old bone away. This constant teardown-and-rebuild is called remodeling, and when the two crews stay balanced, bone stays strong. Joints, meanwhile, glide smoothly because the ends of bones are capped with slick articular cartilage and cushioned by synovial fluid. When that balance or that cushioning breaks down, you get the disorders below. Explore the interactive figure below to see each one.
Osteoporosis: quietly losing bone
In osteoporosis, the osteoclasts outpace the osteoblasts, so more bone is removed than replaced. The bone that remains is normal in chemistry but there is simply less of it - lower bone mineral density (BMD) and a thinner, more porous internal scaffold. The result is fragility: bones that snap under loads a healthy skeleton would shrug off. This is why a minor fall, or even a hard cough, can cause a fragility fracture, classically at the hip, wrist, and vertebrae. Vertebral compression fractures explain the height loss and stooped upper-back curve (kyphosis) often seen in older adults.
The scary part is that it is usually silent until something breaks - patients feel nothing while density slips away. Risk climbs with age, being female (estrogen normally restrains osteoclasts, so density often drops sharply after menopause), small body frame, smoking, low calcium and vitamin D, and long-term corticosteroid use. Screening is done with a DEXA scan, reported as a T-score; a value of -2.5 or lower usually defines osteoporosis.
Osteoarthritis vs rheumatoid arthritis
Both are called "arthritis," but they are completely different problems. Osteoarthritis (OA) is a mechanical, wear-and-tear process: over years, the articular cartilage cushioning a joint frays and thins until bone rubs on bone. It targets the weight-bearing joints - knees, hips, spine - plus the small joints at the fingertips. The pain is use-related: worse after activity and at the end of the day, better with rest. Because it is local mechanical damage, there are no systemic signs - no fever, no fatigue. Any morning stiffness is brief, usually under 30 minutes.
Rheumatoid arthritis (RA) is an autoimmune disease. The immune system attacks the synovium (the joint lining), inflaming it into a destructive tissue called pannus that erodes cartilage and bone from within. RA is symmetric (both hands, both wrists) and favors the small joints of the hands and feet. Its hallmark is morning stiffness lasting longer than an hour. Because it is a body-wide immune process, it brings systemic signs: fatigue, low-grade fever, and elevated inflammatory markers (ESR, CRP). Over time it can deform joints into patterns like ulnar deviation.
| Feature | Osteoarthritis | Rheumatoid arthritis |
|---|---|---|
| Cause | Wear-and-tear cartilage loss | Autoimmune synovial attack |
| Joints | Weight-bearing, often asymmetric | Small joints, symmetric |
| Pain pattern | Worse with use, better with rest | Stiff after rest, eases with movement |
| Morning stiffness | Usually < 30 min | Usually > 1 hour |
| Systemic signs | None | Fatigue, fever, high ESR/CRP |
Gout: crystals in the joint
Gout comes from too much uric acid, a waste product of purine breakdown. When blood uric acid stays high (hyperuricemia), needle-shaped monosodium urate crystals precipitate inside a joint. The immune system treats these crystals as invaders and mounts a fierce inflammatory response. The result is a sudden, severe attack - often overnight - with a joint that is red, hot, swollen, and so tender that even a bedsheet hurts. The classic first target is the big toe (the first metatarsophalangeal joint), a presentation called podagra. Attacks are often triggered by red meat, shellfish, alcohol, or dehydration.
Telling them apart at the bedside
A few quick questions usually sort these out. Ask about tempo: gout explodes over hours; OA and RA build over years. Ask about pattern: OA hits big weight-bearing joints and worsens with use; RA hits small joints symmetrically with long morning stiffness; gout usually strikes one joint, classically the toe. Ask about the whole body: fatigue and fever point toward RA (or an acute gout flare), while OA stays purely local. And remember osteoporosis lives in a different lane entirely - it is painless until a fragile bone fractures.
- Osteoporosis is silent low bone density (osteoclasts > osteoblasts) leading to fragility fractures of the hip, wrist, and spine; diagnosed by DEXA T-score.
- Osteoarthritis is mechanical cartilage wear in weight-bearing joints, worse with use, with brief stiffness and no systemic signs.
- Rheumatoid arthritis is autoimmune synovitis: symmetric small joints, morning stiffness > 1 hour, and systemic features (fatigue, fever, high ESR/CRP).
- Gout is urate crystal deposition causing a sudden, severe, single hot joint - classically the big toe (podagra).
- At the bedside, sort by tempo, pattern, and systemic signs: hours vs years, one joint vs symmetric, local vs whole-body.
Section 4Skin conditions
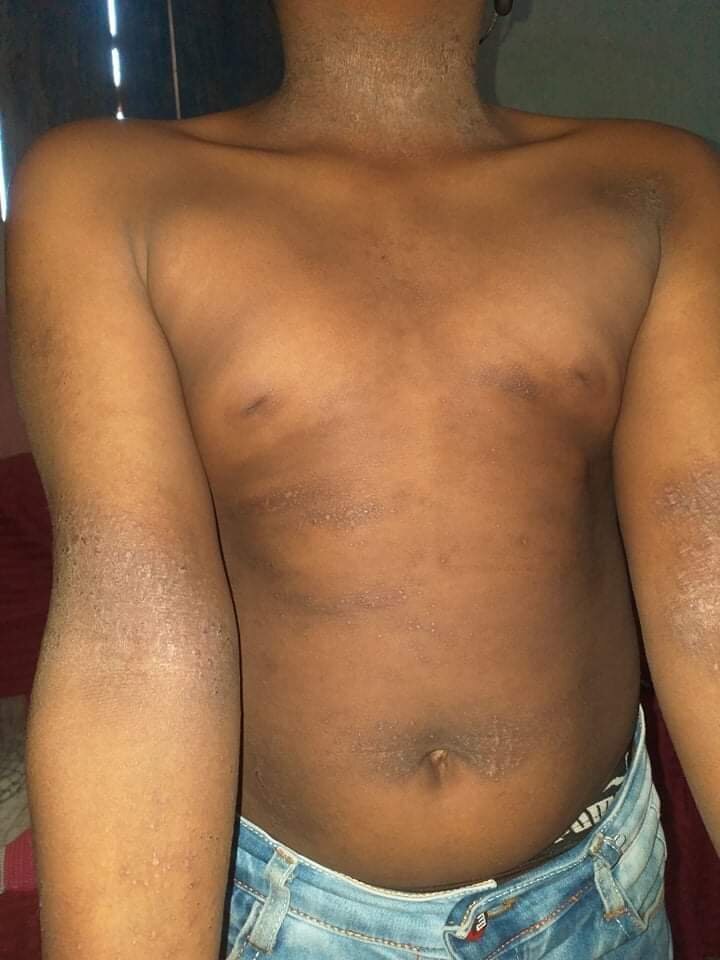
Your skin is the largest organ you have, and its main job is to be a barrier - a smart, self-repairing wall between your insides and the outside world. It keeps water in, keeps microbes out, senses touch and temperature, and helps regulate body heat. When you understand that barrier job, most skin diseases start to make sense: they are what happens when the wall gets inflamed, overbuilt, broken down, or invaded.
Skin has three layers. The epidermis is the thin, tough outer layer that makes the waterproof keratin shell and constantly sheds and regrows. Beneath it, the dermis holds collagen, blood vessels, nerves, hair follicles, and sweat glands. Under that sits the subcutaneous (hypodermis) layer of fat and connective tissue for insulation and cushioning. Damage that stays in the epidermis usually heals cleanly; damage that reaches the dermis or deeper is where scarring and serious injury begin.
Dermatitis (eczema) and psoriasis
Dermatitis, often called eczema in its atopic form, is inflammation of the epidermis. The skin barrier is leaky, so it loses water and lets irritants and allergens in. The immune system overreacts, and the result is red, itchy, sometimes weepy or crusted skin. Because it is inflammatory and often allergic, it tends to flare with triggers - soaps, stress, dry air - and improves with moisturizers and topical steroids that calm the inflammation.
Psoriasis looks different because the mechanism is different. Here the problem is rapid epidermal turnover: skin cells that normally take about a month to rise and shed do so in just days, driven by an overactive immune (T-cell) response. The cells pile up faster than they can mature, forming thick plaques topped with silvery scales, classically on elbows, knees, and scalp. It is chronic and autoimmune in nature, so it is managed, not cured.
| Feature | Eczema/Dermatitis | Psoriasis |
|---|---|---|
| Core mechanism | Barrier defect + allergic inflammation | Rapid cell turnover (autoimmune) |
| Look | Red, weepy, crusted, very itchy | Thick plaques with silvery scale |
| Typical sites | Flexural folds, hands, face | Elbows, knees, scalp (extensor) |
Pressure injuries
A pressure injury (formerly pressure ulcer or bedsore) happens when sustained pressure - usually over a bony spot like the sacrum, heels, or hips - squeezes blood vessels shut. Without blood flow, tissue is starved of oxygen (ischemia) and begins to die. Shear and moisture make it worse. This is why immobile patients are so vulnerable, and why prevention is a nursing priority. Standard staging:
- Stage 1: intact skin with non-blanchable redness.
- Stage 2: partial-thickness loss into the dermis; a shallow open sore or blister.
- Stage 3: full-thickness loss with visible fat.
- Stage 4: full-thickness loss exposing muscle, tendon, or bone.
- Unstageable (base obscured by slough/eschar) and deep tissue injury (persistent maroon/purple area) are separate categories.
Prevention centers on relieving pressure: reposition usually every 2 hours, offload heels, use support surfaces, keep skin clean and dry, and maintain nutrition and hydration so tissue can repair.
Skin cancers and the ABCDE rule
Most skin cancers trace back to UV-damaged DNA in epidermal cells that then grow uncontrolled. The three big ones differ sharply in danger.
- Basal cell carcinoma: the most common and least aggressive. Arises from basal keratinocytes; often a pearly, pink, or waxy bump that may ulcerate. It rarely spreads (metastasizes) but destroys local tissue.
- Squamous cell carcinoma: from upper keratinocytes; a scaly, crusted, or firm red nodule. More likely than basal cell to metastasize if ignored.
- Melanoma: the deadliest, arising from pigment-making melanocytes. It grows and metastasizes quickly, so early recognition saves lives.
Screen suspicious moles with ABCDE: Asymmetry, Border irregularity, Color variation, Diameter larger than about 6 mm (pencil eraser), and Evolving - any change in size, shape, color, or new bleeding/itching.
Take a look at the interactive figure below to compare how these common skin conditions actually appear.
- The skin's three layers (epidermis, dermis, subcutaneous) form a barrier, and most skin disease is that barrier inflamed, overbuilt, broken down, or invaded.
- Eczema is a leaky-barrier allergic inflammation (red, weepy, itchy); psoriasis is rapid autoimmune turnover producing thick, silvery plaques.
- Pressure injuries come from ischemia under sustained pressure; stage 1 (non-blanchable redness) through stage 4 (muscle/bone exposed), prevented by repositioning, offloading, skin care, and nutrition.
- Basal cell is common and local, squamous cell can metastasize, and melanoma is the deadliest because it spreads early.
- Use ABCDE - Asymmetry, Border, Color, Diameter >6 mm, Evolving - to flag suspicious lesions for evaluation.
Section 5Skin infections
Your skin is your body's largest organ and its first wall of defense. Two layers do the heavy lifting: the tough outer epidermis, waterproofed by a protein called keratin, and the deeper dermis, which holds blood vessels, nerves, and hair follicles. On top of all this lives a healthy crowd of harmless bacteria and fungi called the normal skin flora, plus an oily, slightly acidic film (the acid mantle) that keeps troublemakers in check. Infection happens when that barrier is breached, a cut, a scratch, cracked skin, a bug bite, or a weakened immune system, and organisms slip past the wall and multiply faster than your defenses can clear them.
Bacterial infections: cellulitis, impetigo, and MRSA
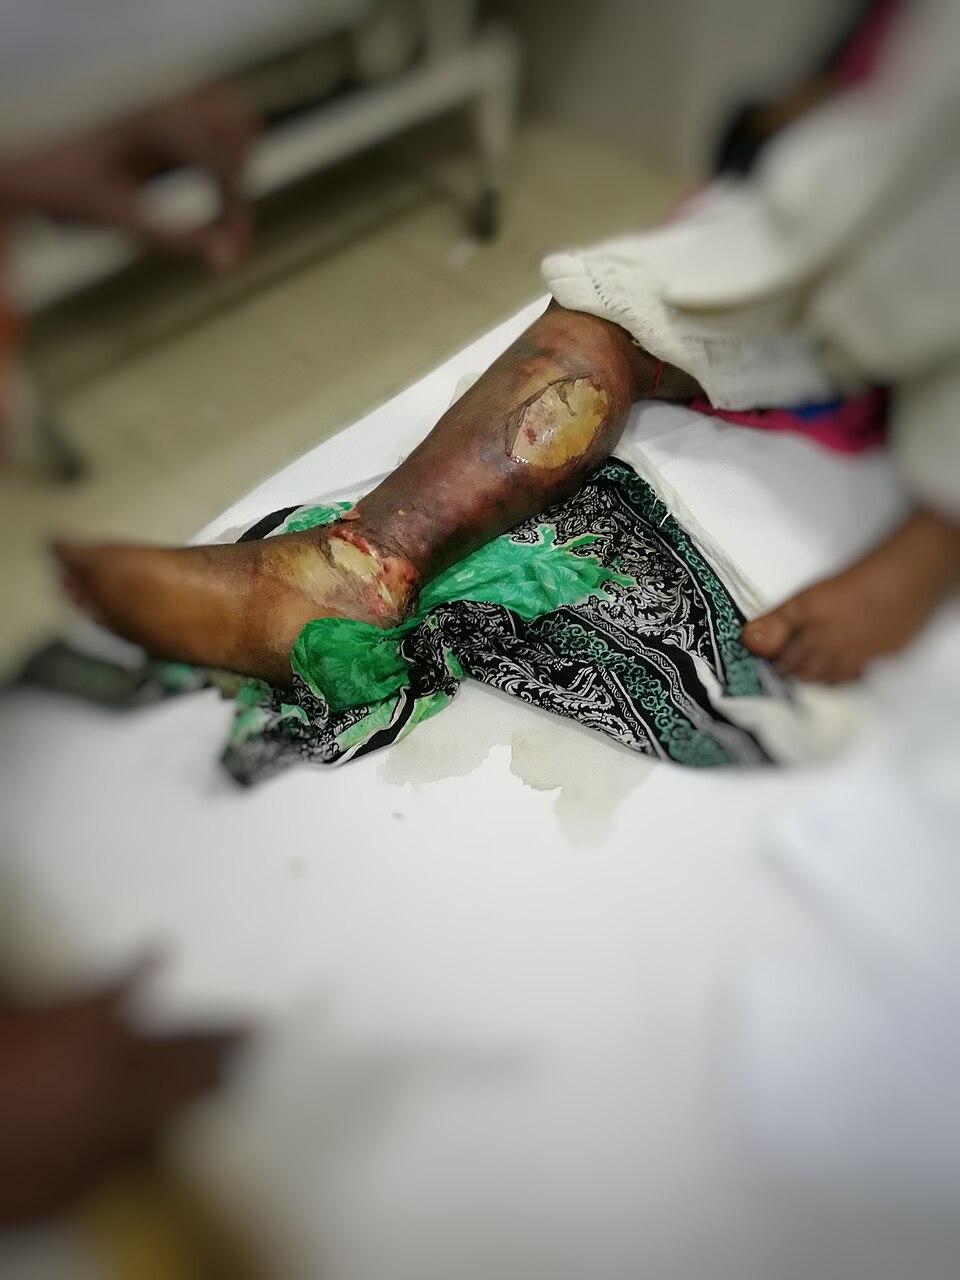
Cellulitis is a deep infection of the dermis and the fat below it, usually caused by Streptococcus or Staphylococcus aureus. Bacteria enter through a break in the skin and your immune system floods the area, which is exactly why you see the classic signs: redness, warmth, swelling, and pain. Those aren't the bacteria, they're inflammation, dilated vessels bringing white blood cells and fluid. The border is often poorly defined and spreading; nurses frequently outline the edge with a pen and note the time so the team can see if it advances.
Impetigo is a superficial infection of the epidermis, most common in children. It produces oozing sores that dry into a signature honey-colored crust. It is highly contagious by direct contact and easily spreads with scratching. MRSA (methicillin-resistant Staphylococcus aureus) is not a different disease but a resistant strain, it shrugs off common penicillin-family antibiotics because of an altered penicillin-binding protein. MRSA often looks like an angry, painful abscess or boil that patients swear is a "spider bite." It demands specific antibiotics and, for abscesses, drainage.
Fungal infections: tinea and candida
Fungi love warm, dark, moist places, which tells you exactly where to look. Tinea (dermatophyte infection) feeds on keratin in the dead outer skin. As the fungus grows outward and the center clears, it forms the ring-with-raised-scaly-edge that gives ringworm its name (there is no worm involved). Tinea gets body-part names: tinea pedis (athlete's foot), tinea cruris (jock itch), tinea capitis (scalp).
Candida is a yeast that normally lives quietly on us but overgrows in skin folds, under breasts, in the groin, in diaper areas, producing a beefy-red rash with satellite lesions (small separate spots at the edges). It thrives after antibiotics wipe out competing bacteria and in patients with diabetes or immune suppression, a reason high blood sugar and recurrent yeast infections often travel together.
Viral infections: herpes simplex and herpes zoster
Herpes viruses share a signature trick: after the first infection they hide in nerve cells for life and reactivate under stress, illness, sunlight, or immune suppression. Herpes simplex virus (HSV) causes painful, grouped, fluid-filled vesicles, cold sores around the mouth (HSV-1) or genital lesions (HSV-2).
Herpes zoster (shingles) is the reactivation of the chickenpox virus, varicella-zoster, which had been lying dormant in a sensory (dorsal root) ganglion since childhood. When it wakes, it travels down that single nerve and erupts as a painful blistering rash in a dermatome, the strip of skin one nerve supplies. That's why shingles classically appears as a stripe on one side of the body that stops abruptly at the midline. Burning pain often precedes the rash, and pain can linger for months as postherpetic neuralgia.
| Feature | Herpes simplex | Herpes zoster (shingles) |
|---|---|---|
| Virus | HSV-1 / HSV-2 | Varicella-zoster (reactivated) |
| Pattern | Grouped vesicles, mouth or genitals | Single dermatome, one side, stops at midline |
| Recurs? | Yes, same site | Usually once; pain can persist |
When skin infection turns dangerous: necrotizing fasciitis
Necrotizing fasciitis, sometimes called "flesh-eating" infection, is a surgical emergency. Aggressive bacteria race along the fascia (the sheet beneath the skin and fat), releasing toxins that kill tissue and clot off its blood supply. The tell-tale clue is pain out of proportion to what you see, the surface may look only mildly red while the patient is in agony. Later signs include rapid spread, dusky or purple skin, blisters, crepitus (crackling from gas in tissue), and a patient who looks systemically sick. Treatment is emergent surgical removal of dead tissue plus IV antibiotics; delay costs limbs and lives. Explore the infection types in the interactive figure below.
- Skin infection starts when the epidermal barrier is breached; redness, warmth, and swelling are inflammation, not the microbe itself.
- Cellulitis is deep and spreading (mark the border); impetigo shows honey-colored crusts; MRSA is antibiotic-resistant staph, often a painful abscess.
- Fungi (tinea, candida) favor warm, moist areas; candida overgrows after antibiotics and in diabetes.
- HSV and zoster hide in nerves and reactivate; shingles follows a single dermatome and stops at the midline.
- Necrotizing fasciitis is a surgical emergency, pain out of proportion to the exam is the warning sign.
Section 6Burns
Your skin is the largest organ you have, and it does a lot of quiet work you never think about. It holds fluid in, keeps germs out, senses touch and temperature, and helps regulate your body heat. A burn injures this barrier, and once enough of it is gone, the problems ripple far beyond the skin itself. That is the single most important idea in burn care: a large burn is a whole-body emergency, not just a wound.
Burn depth: how deep did the injury go?
Skin has layers. The thin outer epidermis sits on top of the thicker dermis, which holds blood vessels, nerve endings, hair follicles, and sweat glands. Below that is subcutaneous fat, then muscle and bone. How deep a burn reaches determines how it looks, how much it hurts, and whether it can heal on its own.
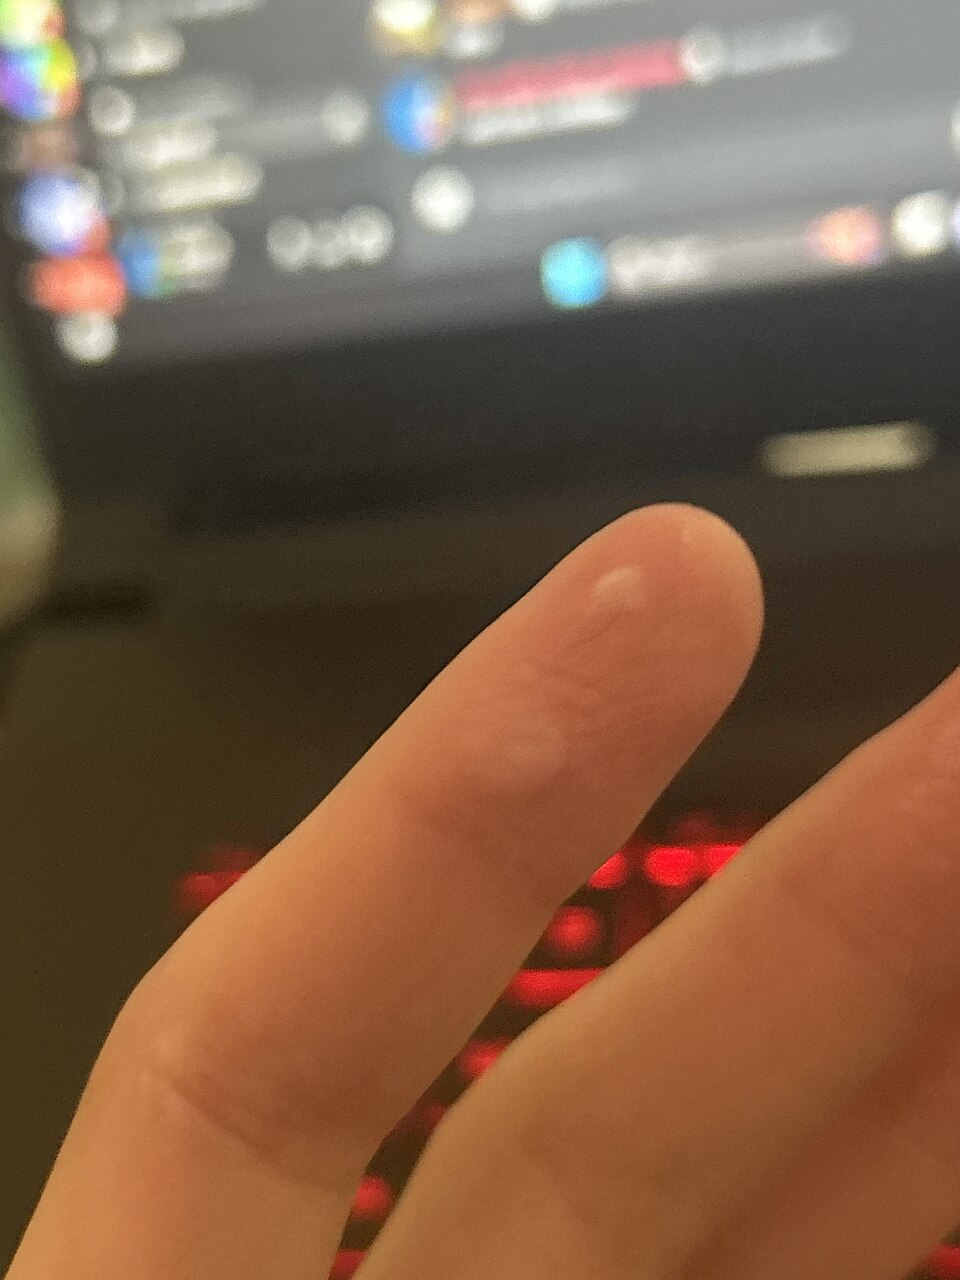
| Feature | Superficial | Partial-thickness | Full-thickness |
|---|---|---|---|
| Layers involved | Epidermis only | Epidermis + part of dermis | All of epidermis and dermis (may reach fat, muscle, bone) |
| Old name | First-degree | Second-degree | Third-degree |
| Appearance | Red, dry, no blisters | Red, moist, blisters, weeping | White, leathery, waxy, or charred; dry |
| Pain | Painful | Very painful | Often painless in the deepest areas |
| Healing | Days, no scar | Weeks, may scar | Cannot self-heal; needs grafting |
The pain pattern surprises students. A superficial burn (think mild sunburn) hurts because the nerve endings are irritated but intact. A full-thickness burn can be eerily painless in its center because the sensory nerves themselves were destroyed. So a quiet, leathery, white patch is often worse than a screaming red blistered one. Deeper full-thickness burns can also form a tight, inelastic band of dead tissue called an eschar, which may need to be surgically released (an escharotomy) if it constricts a limb or the chest.
Estimating burn size: the rule of nines
Depth tells you how bad; size tells you how big the whole-body threat is. Clinicians estimate the total body surface area (TBSA) burned using the rule of nines, which divides the adult body into sections worth about 9% each (or multiples of 9): head and neck 9%, each arm 9%, the front of the torso 18%, the back 18%, each leg 18%, and the genital area 1%. For scattered small burns, the patient's own palm is roughly 1% TBSA. Children have proportionally larger heads, so pediatric charts differ. TBSA matters because it drives fluid resuscitation math and decisions about transfer to a burn center.
Why a big burn threatens the whole body
Once TBSA climbs past roughly 20-25%, the injury stops being local. Damaged tissue releases inflammatory mediators that make capillaries everywhere leaky. Plasma, protein, and fluid pour out of the bloodstream into the tissues, causing massive third-spacing and edema. The result is burn shock, a form of hypovolemic shock: blood volume drops even though total body water has not, so blood pressure falls and organs are underperfused. This is why we prioritize the ABCs.
- Airway first. If someone was burned in an enclosed space, watch for inhalation injury. Clues include facial burns, singed nose hairs, soot in the mouth, hoarseness, and carbonaceous sputum. Hot gases and swelling can close the airway fast, so early intubation is often chosen before swelling makes it impossible.
- Breathing and circulation. Suspect carbon monoxide poisoning in smoke exposure; give high-flow oxygen. A pulse oximeter can read falsely normal because it cannot tell oxygen from carbon monoxide.
- Fluid resuscitation. Large burns need aggressive IV fluids, usually lactated Ringer's, guided by a formula such as the Parkland formula and titrated to urine output (often about 0.5 mL/kg/hr in adults). Too little fluid worsens shock; too much causes dangerous edema.
The delayed threat: infection
The burned skin barrier is gone, and the burn wound is a warm, protein-rich surface that bacteria love. After the first day or two, infection and sepsis become the leading cause of death in major burns. This is why burn wounds get meticulous cleaning, topical antimicrobials, and strict aseptic technique. The immune disruption plus the huge open surface make these patients extraordinarily vulnerable.
- Depth ranges from superficial (red, dry, painful) to partial-thickness (blistered, weeping, very painful) to full-thickness (white/leathery, often painless because nerves are destroyed).
- The rule of nines estimates TBSA (head 9%, each arm 9%, front torso 18%, back 18%, each leg 18%, genitals 1%; palm about 1%) and drives fluid and transfer decisions.
- Large burns cause leaky capillaries and third-spacing, producing hypovolemic burn shock despite intact total body water.
- Priorities follow time: airway first (inhalation injury), then fluid resuscitation (lactated Ringer's, titrated to urine output), then infection/sepsis prevention.
- A large burn is a whole-body emergency, not just a skin wound.
The chapter in one breath
- Fracture healing moves through hematoma, soft then hard callus, and remodeling, so pain, swelling, and deformity are the body walling off and rebuilding bone over weeks to months.
- Compartment syndrome is the can't-miss fracture emergency: rising pressure in a closed muscle compartment is diagnosed EARLY by pain out of proportion to injury and pain with passive stretch, with paresthesia as an early sensory sign; pulselessness, pallor, paralysis, and poikilothermia are LATE, ominous signs that tissue is already dying, so although the classic list is the 6 P's (pain, paresthesia, pallor, pulselessness, paralysis, poikilothermia), do not wait for the late P's — a palpable pulse does not rule it out — and it demands a fasciotomy before tissue dies.
- Fat embolism usually follows long-bone or pelvic fractures within 24 to 72 hours, classically showing dyspnea, confusion, and a petechial rash as marrow fat lodges in the lungs and brain.
- Osteoporosis is silent low bone density from bone resorption outpacing formation, so the first sign is often a fragility fracture of the hip, wrist, or a vertebra rather than pain.
- Tell the arthritides apart: osteoarthritis is asymmetric wear-and-tear joint pain worse with use, while rheumatoid arthritis is symmetric autoimmune inflammation with prolonged morning stiffness, and gout is monosodium urate crystals causing a hot, red, exquisitely painful great-toe (podagra) attack.
- Learn skin cancer by ABCDE (Asymmetry, Border, Color, Diameter >6 mm, Evolving), because melanoma is the deadliest due to early metastasis, unlike the more common but rarely fatal basal and squamous cell carcinomas.
- Cellulitis is a deeper dermal and subcutaneous bacterial infection (often Staph or Strep) that is warm, red, swollen, and tender with poorly defined borders, and it can turn systemic with fever.
- Estimate burn extent with the rule of nines and depth by tissue: superficial reddens and blanches, partial-thickness blisters and hurts intensely, and full-thickness is leathery, painless, and needs grafting.
- For major burns the killer is hypovolemic (burn) shock from massive capillary fluid leak, so fluid resuscitation (often Parkland formula) and airway watch for inhalation injury come first.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- ABCDE rule
- A quick screening checklist for suspicious skin lesions, prompting you to watch for Asymmetry, irregular Borders, uneven Color, Diameter greater than about 6 mm, and any Evolving change in size, shape, or color over time.
- Callus
- The soft, new woven bone and cartilage that forms as a bridge around a healing fracture, which the body later remodels into stronger, mature lamellar bone.
- Cellulitis
- A deeper bacterial skin infection (usually Staphylococcus or Streptococcus) that spreads through the dermis and subcutaneous tissue, producing warmth, redness, swelling, and tenderness with poorly defined edges.
- Compartment syndrome
- A limb-threatening emergency in which swelling or bleeding inside a closed muscle compartment raises pressure high enough to cut off circulation, classically signaled by pain out of proportion and worsening with passive stretch.
- Fat embolism
- A complication, most often after long-bone or pelvic fractures, in which fat globules from the marrow enter the bloodstream and lodge in the lungs or brain, typically causing shortness of breath, confusion, and a petechial rash.
- Fracture
- A break or disruption in the continuity of a bone, ranging from a tiny hairline crack to a complete separation, caused when force exceeds what the bone can absorb.
- Gout
- A form of inflammatory arthritis caused by uric acid crystals depositing in a joint (classically the big toe), triggering sudden severe pain, redness, warmth, and swelling.
- Herpes zoster
- Also called shingles, a painful blistering rash that erupts along a single dermatome when the dormant varicella-zoster (chickenpox) virus reactivates in a nerve root.
- Melanoma
- The most dangerous skin cancer, arising from pigment-producing melanocytes, which can spread (metastasize) early and is often first spotted by applying the ABCDE rule to a changing mole.
- Osteoarthritis
- A degenerative "wear-and-tear" joint disease in which cartilage gradually breaks down, causing pain and stiffness that worsens with use and typically eases with rest.
- Osteoporosis
- A condition of low bone mass and weakened bone microstructure that leaves bones porous and fragile, greatly raising the risk of fractures, especially in the hip, spine, and wrist.
- Partial-thickness burn
- A burn that damages the epidermis and part of the dermis, usually appearing red, moist, and blistered, and remaining painful because sensory nerve endings are still intact.
- Pressure injury
- Localized damage to skin and underlying tissue over a bony prominence caused by sustained pressure that cuts off blood flow (ischemia), often developing in immobile patients over the sacrum, heels, or hips.
- Psoriasis
- A chronic autoimmune skin disorder in which skin cells turn over far too quickly, building up into well-defined red plaques covered by silvery scales, commonly on the elbows, knees, and scalp.
- Rheumatoid arthritis
- A chronic autoimmune disease in which the body attacks the joint lining (synovium), producing symmetric pain, swelling, and morning stiffness that typically improves with movement.
- Rule of nines
- A rapid method for estimating the percentage of total body surface area burned by dividing the adult body into regions worth about 9% each (or multiples of nine), used to guide fluid resuscitation.
DrillFlashcards for this unit
These are the Week 14 cards — the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it; hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.