IMMUNE AND RHEUMATOLOGIC DISORDERS
The immune system fails in only three interesting ways: it overreacts, it underperforms, or it mistakes the patient for the enemy. Everything in this chapter falls into one of those three buckets, and knowing which bucket you are in tells you what to do. The patient whose lips are swelling twelve minutes after a first dose of cefazolin needs intramuscular epinephrine in the next sixty seconds, not an antihistamine and a reassessment. The patient with a CD4 count of 140 and a dry cough needs an oxygen saturation on ambulation, not on the pillow. The woman with lupus whose complement is falling and whose urine is suddenly frothy is losing a kidney quietly while her joints get the attention. And the patient on a tumour necrosis factor inhibitor who feels “a little off” without a fever may be septic, because you have chemically removed her ability to mount one. Immunology at the bedside is pattern recognition plus ruthless prioritisation.
By the end of this chapter you can
- Distinguish the four hypersensitivity types by mechanism and name a clinical example of each, including Type I IgE-mediated and Type IV delayed cell-mediated reactions.
- Recognise anaphylaxis within seconds and state the first drug, the correct dose, the correct route and the correct site without hesitation.
- Interpret a CD4 count and HIV viral load, identify the threshold that defines AIDS, and match CD4 strata to opportunistic infection prophylaxis.
- Explain the antibody profile, organ involvement and flare markers of systemic lupus erythematosus, including anti-dsDNA and falling complement (C3, C4).
- Compare rheumatoid arthritis, osteoarthritis and gout by joint distribution, stiffness pattern, laboratory findings and treatment.
- Describe the monitoring, screening and teaching that must precede and accompany methotrexate, biologic DMARDs and JAK inhibitors.
- Differentiate hyperacute, acute and chronic transplant rejection and identify the nursing assessments that detect each.
- Apply SBAR escalation to red flags including anaphylaxis, giant cell arteritis with visual change, scleroderma renal crisis and neutropenic fever.
- Delegate appropriately in the immunosuppressed patient, retaining assessment, teaching, evaluation and unstable patients for the registered nurse.
Section 1When the Immune System Overreacts: Hypersensitivity, Allergy and Anaphylaxis
The four hypersensitivity patterns
Hypersensitivity means the immune response causes more damage than the antigen would have. Four mechanisms are described, and the mechanism predicts both the timing and the treatment. Type I is immediate and IgE-mediated: a previously sensitised patient re-encounters the antigen, IgE bound to mast cells and basophils cross-links, and the cells degranulate within minutes, dumping histamine, tryptase, leukotrienes and prostaglandins. The result is vasodilation, capillary leak, bronchoconstriction and urticaria — anaphylaxis, allergic rhinitis, atopic asthma, food and insect sting allergy. Because it requires prior sensitisation, the first exposure is often uneventful and the second is the catastrophe. Students remember this as “the second dose is the dangerous one,” which is why you never relax during a second antibiotic dose.
Type II is antibody-mediated cytotoxicity: IgG or IgM binds antigen on the surface of the patient’s own cells and marks them for complement lysis or phagocytosis. Acute haemolytic transfusion reaction from ABO incompatibility is the classic, along with immune thrombocytopenia, heparin-induced thrombocytopenia, Graves disease and Goodpasture syndrome. Type III is immune complex disease: antigen and antibody form soluble complexes that deposit in vessel walls, glomeruli, skin and synovium, fixing complement and drawing neutrophils. Serum sickness, post-streptococcal glomerulonephritis and much of the organ damage in systemic lupus erythematosus are Type III. This is why serum complement falls in a lupus flare — it is being consumed by the complexes.
Type IV is delayed and cell-mediated, driven by sensitised T lymphocytes rather than antibody, and it takes 24 to 72 hours to appear. The tuberculin skin test read at 48 to 72 hours is a deliberately induced Type IV reaction. So is contact dermatitis to nickel or poison ivy, most solid-organ graft rejection, and the severe cutaneous drug reactions Stevens–Johnson syndrome and toxic epidermal necrolysis. The nursing implication is timing: a Type IV reaction will not be caught in a thirty-minute post-dose observation, so patients started on a new sulfonamide, allopurinol, lamotrigine or antiepileptic must be taught to report a spreading rash, mucosal blistering or fever days into therapy.
| Type | Mechanism | Onset | Clinical examples |
|---|---|---|---|
| I — Immediate | IgE on mast cells, degranulation | Seconds to 30 minutes | Anaphylaxis, food and sting allergy, allergic rhinitis, atopic asthma |
| II — Cytotoxic | IgG or IgM against cell-surface antigen, complement lysis | Minutes to hours | ABO haemolytic transfusion reaction, immune thrombocytopenia, heparin-induced thrombocytopenia, Goodpasture |
| III — Immune complex | Antigen–antibody complexes deposit in tissue, complement consumed | Hours to weeks | Serum sickness, post-streptococcal glomerulonephritis, lupus nephritis and vasculitis |
| IV — Delayed | Sensitised T cells and macrophages, no antibody | 24 to 72 hours or longer | Tuberculin skin test, contact dermatitis, graft rejection, Stevens–Johnson syndrome |
Anaphylaxis: recognise it in seconds, treat it in one
Anaphylaxis is a clinical diagnosis, not a laboratory one, and it does not require hives. Suspect it when a patient develops acute onset of illness involving skin or mucosa (urticaria, flushing, swollen lips or tongue) plus either respiratory compromise (stridor, wheeze, hypoxaemia, throat tightness) or hypotension and end-organ dysfunction. It should also be suspected when two or more body systems light up quickly after a likely allergen — skin, respiratory, cardiovascular, or persistent gastrointestinal cramping and vomiting — or when a known allergen is followed by hypotension alone. In hospital the usual culprits are beta-lactam antibiotics, vancomycin, contrast media, neuromuscular blockers, latex and blood products. Onset is typically within five to thirty minutes of an intravenous agent, and faster is worse.
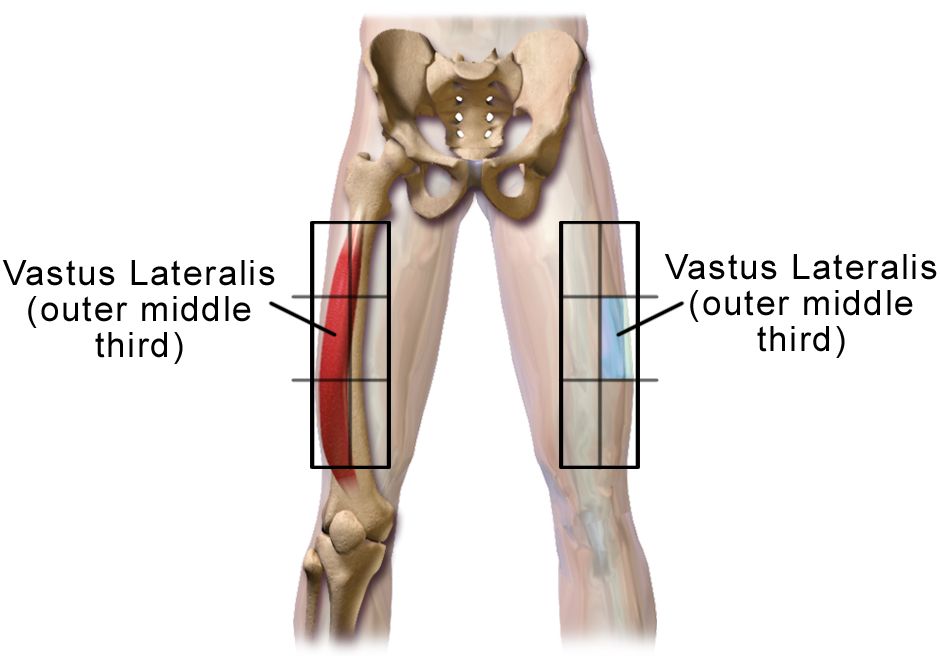
The first action is epinephrine 0.3 to 0.5 mg of the 1 mg/mL concentration, intramuscularly into the anterolateral thigh (vastus lateralis), repeated every five to fifteen minutes as needed. Not subcutaneous, not the deltoid, not intravenous unless the patient is in arrest or a physician is titrating an infusion in a monitored setting, and not after you have tried an antihistamine. Epinephrine works because alpha-1 stimulation reverses vasodilation and mucosal oedema while beta-2 stimulation bronchodilates and beta-1 supports cardiac output. Antihistamines relieve itch and hives; they do nothing for airway or blood pressure. Corticosteroids take hours. The paediatric dose is 0.01 mg/kg to a maximum of 0.3 mg (0.5 mg in adolescents). At the same time, stop the infusion, call for help, apply high-flow oxygen, and place the patient supine with the legs elevated unless vomiting or severe respiratory distress demands otherwise — abruptly sitting a hypotensive anaphylactic patient upright can empty the vena cava and cause cardiac arrest.
Adjuncts follow: rapid crystalloid boluses of 1 to 2 L for hypotension (capillary leak can shift a third of the plasma volume in ten minutes), an H1 blocker such as diphenhydramine 25 to 50 mg IV, an H2 blocker such as famotidine 20 mg IV, nebulised albuterol for persistent bronchospasm, and methylprednisolone 125 mg IV to blunt a late-phase reaction. If the patient takes a beta blocker and is refractory to epinephrine, glucagon 1 to 5 mg IV over five minutes bypasses the beta receptor. Serum tryptase drawn between fifteen minutes and three hours after onset can confirm mast cell degranulation retrospectively, but it never delays treatment. Because a biphasic reaction can recur one to eight hours later (occasionally up to seventy-two hours) without re-exposure, observe for a minimum of four to six hours — longer after severe reactions, repeat epinephrine doses, or asthma history.
Allergy, latex and drug reaction on a busy floor
Every admission assessment includes allergies, but a name alone is useless documentation. Ask what happened and when: nausea after codeine is an intolerance, hives and throat swelling after penicillin is an allergy, and the distinction changes what the patient may safely receive for the rest of their life. Roughly ninety percent of patients labelled penicillin-allergic tolerate penicillin on formal evaluation, and that mislabel pushes them toward broader, more toxic and less effective antibiotics. Document the reaction, the timing and the severity, and refer for allergy evaluation rather than perpetuating a forty-year-old label.
Latex allergy deserves its own line. Natural rubber latex proteins cause a Type I reaction; the accelerators in gloves cause a Type IV contact dermatitis with delayed erythema and fissuring. Highest risk are patients with spina bifida, urogenital anomalies, and anyone with repeated procedures or occupational exposure. Cross-reactivity with banana, avocado, kiwi, chestnut, papaya and passion fruit is real, so a patient who reports lip tingling with kiwi is telling you something about their glove tolerance. A latex-allergic patient needs a documented latex-safe environment: synthetic gloves, latex-free tourniquets, blood pressure cuff barriers, medication vials with non-latex stoppers, and a band and chart flag. Powdered latex gloves aerosolise protein, so the exposure risk is airborne, not just contact.
Two other reactions on the floor are commonly mislabelled as allergy. Vancomycin infusion reaction (formerly “red man syndrome”) is a direct, non-IgE mast cell degranulation from rapid infusion: flushing of the face, neck and upper torso with pruritus, sometimes hypotension. It is managed by stopping the infusion, giving an antihistamine, and restarting at a slower rate — typically no faster than 1 g per hour — not by permanently banning vancomycin. Contrast-associated reactions are also usually non-IgE, and premedication with corticosteroids and antihistamines is often used for a documented prior reaction. Finally, teach the discharged patient with a true anaphylaxis history to carry two epinephrine autoinjectors, demonstrate the technique back to you, replace them before expiry, and call emergency services after using one even if symptoms resolve.
In suspected anaphylaxis, intramuscular epinephrine into the anterolateral thigh is the first and non-negotiable action — every other drug is an adjunct that treats symptoms rather than the shock.
Section 2When the Immune System Fails: Immunodeficiency and HIV
Primary and secondary immunodeficiency
Primary immunodeficiencies are inherited defects in a specific arm of immunity and usually declare themselves in childhood: recurrent sinopulmonary infection with encapsulated organisms in antibody deficiencies such as common variable immunodeficiency, or opportunistic and fungal infection in T cell defects. Adults reach the medical–surgical floor more often with secondary immunodeficiency, and the causes are the ordinary furniture of hospital medicine: corticosteroids and other immunosuppressants, chemotherapy, malignancy (particularly haematologic), chronic kidney disease and dialysis, cirrhosis, poorly controlled diabetes, malnutrition, splenectomy, advanced age and HIV infection.
Two practical consequences follow. First, an immunocompromised patient may not mount the signs you rely on: no fever, no leucocytosis, minimal infiltrate on chest radiograph, no purulence at a wound because there are too few neutrophils to make pus. In a neutropenic patient a single temperature of 38.3 degrees C, or 38.0 degrees C sustained for one hour, with an absolute neutrophil count under 500 cells/mm3, is an emergency requiring blood cultures and antibiotics within one hour. Second, asplenic patients — surgical or functional, as in sickle cell disease — are at lifelong risk of overwhelming sepsis from encapsulated organisms and must have pneumococcal, meningococcal and Haemophilus influenzae type b vaccination plus a standing plan for febrile illness.
HIV: virology, testing and staging
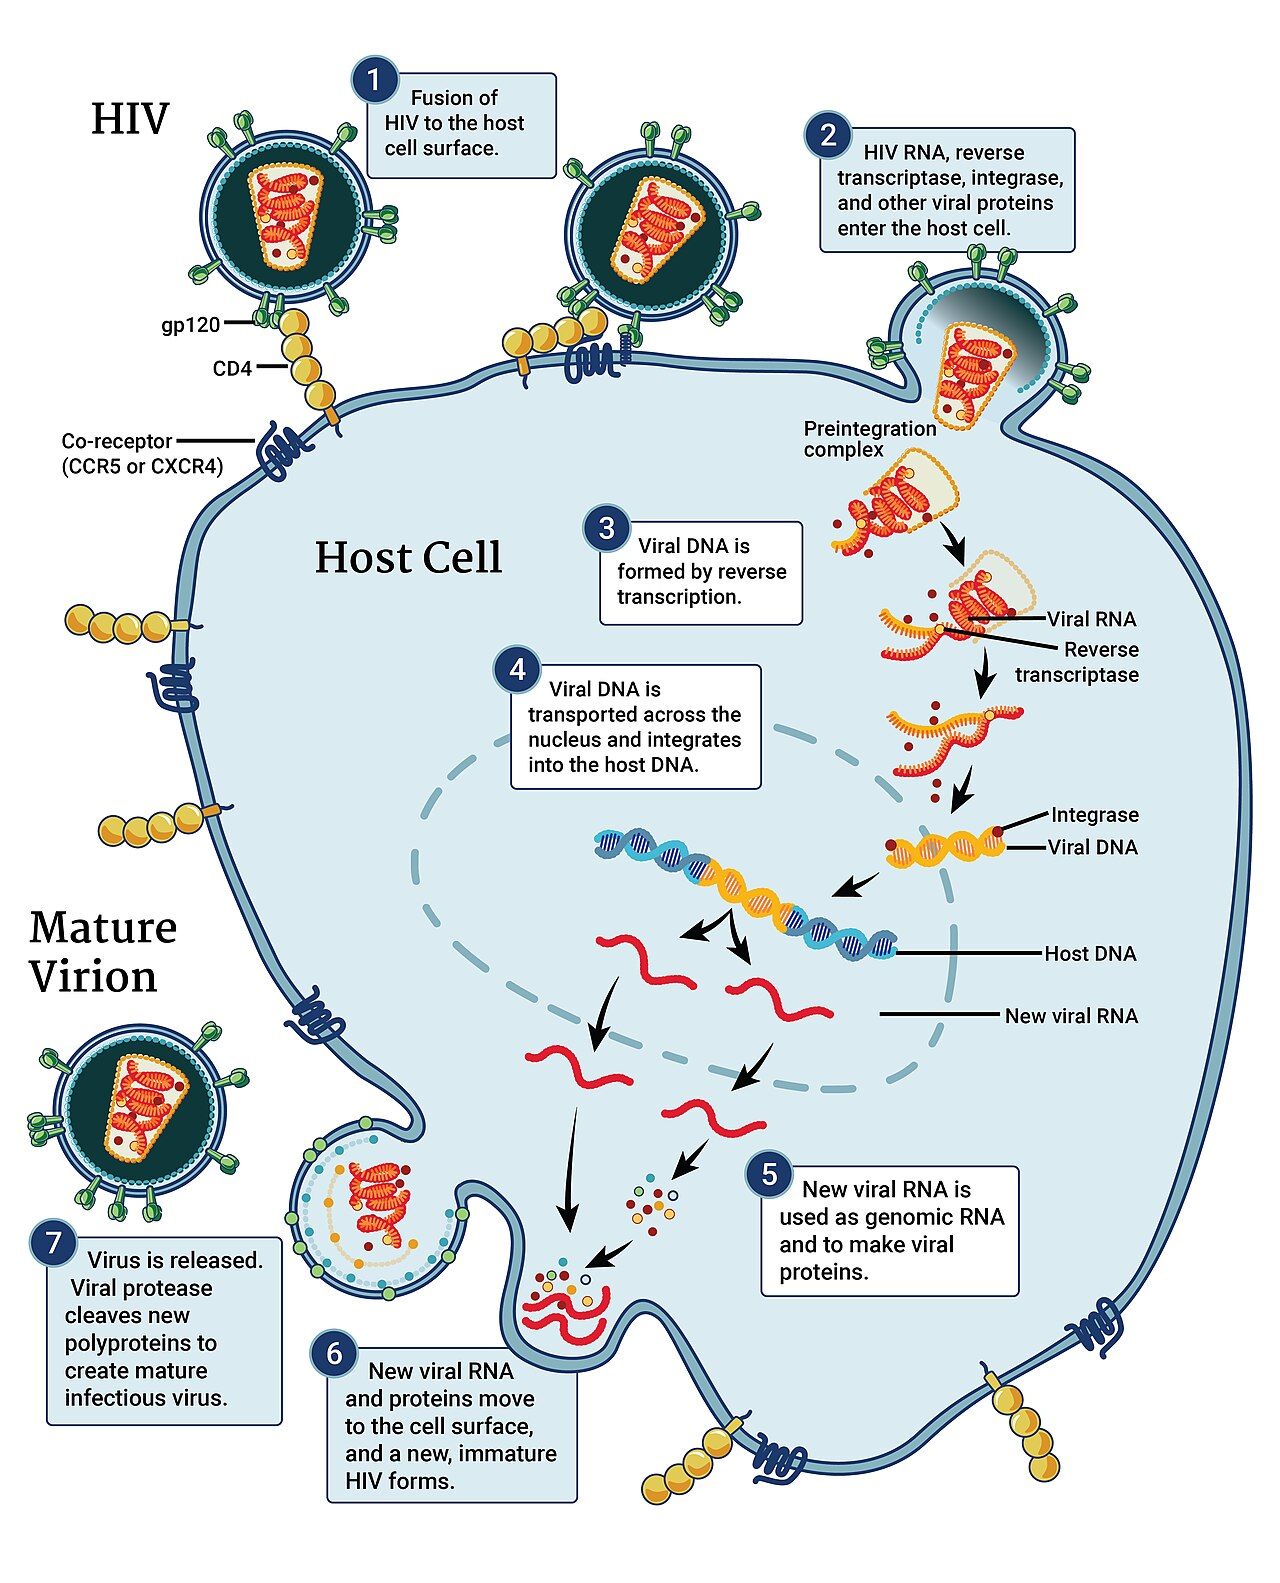
HIV is a retrovirus that binds the CD4 receptor and a co-receptor on helper T lymphocytes, reverse-transcribes its RNA into DNA, integrates into the host genome and turns the cell into a virus factory. The progressive loss of CD4 T cells dismantles cell-mediated immunity, which is precisely the arm that controls intracellular pathogens, fungi and certain cancers. Transmission is through blood, semen, vaginal and rectal fluids, and breast milk — not through saliva, tears, sweat, casual contact or shared utensils. Standard precautions protect the nurse; the occupational risk from a hollow-bore needlestick with infected blood is roughly 0.3 percent, and lower still when the source patient is virally suppressed.
Testing follows a defined algorithm. The screening test is a fourth-generation antigen/antibody combination immunoassay that detects HIV-1 and HIV-2 antibodies plus the p24 antigen, shortening the window period to roughly eighteen to forty-five days. A reactive screen is followed by an HIV-1/HIV-2 antibody differentiation immunoassay; if that is negative or indeterminate, an HIV-1 nucleic acid test resolves it. Never tell a patient the screening result is a diagnosis before confirmation. Acute retroviral syndrome — fever, pharyngitis, lymphadenopathy, rash, myalgia two to four weeks after exposure — occurs when antibody may still be negative but viral load is enormous and transmissibility is highest, so a nucleic acid test is the right test in that window.
Two numbers drive care. The CD4 count (normal roughly 500 to 1,600 cells/mm3) measures immune damage and predicts opportunistic infection. The viral load measures how well treatment is working; the goal is undetectable, usually reported as fewer than 20 to 50 copies/mL. A diagnosis of AIDS is made when the CD4 count falls below 200 cells/mm3, when the CD4 percentage is below 14, or when an AIDS-defining illness occurs — Pneumocystis jirovecii pneumonia, oesophageal candidiasis, disseminated Mycobacterium avium complex, cryptococcal meningitis, cytomegalovirus retinitis, Kaposi sarcoma, central nervous system lymphoma, or HIV wasting. Once the AIDS stage is reached the diagnosis does not revert even if the CD4 recovers on therapy.
| CD4 count (cells/mm3) | Risk | Standard prophylaxis |
|---|---|---|
| Above 500 | Near-normal immunity | None; routine vaccination and ART |
| 200 to 500 | Bacterial pneumonia, tuberculosis, herpes zoster, oral candidiasis | None specific; treat and vaccinate |
| Below 200 | Pneumocystis jirovecii pneumonia | Trimethoprim–sulfamethoxazole one double-strength tablet daily |
| Below 100 | Toxoplasma encephalitis, cryptococcal disease | Trimethoprim–sulfamethoxazole (covers toxoplasma if IgG positive) |
| Below 50 | Disseminated Mycobacterium avium complex, cytomegalovirus retinitis | Azithromycin 1,200 mg weekly if ART cannot be started promptly; dilated eye exams |
Antiretroviral therapy, adherence and prevention
Antiretroviral therapy is started as soon as possible after diagnosis, at any CD4 count, ideally the same day. Regimens combine agents from different classes so the virus cannot mutate around a single pressure point, and most first-line regimens are a single daily tablet built on an integrase strand transfer inhibitor: bictegravir with emtricitabine and tenofovir alafenamide, or dolutegravir paired with two nucleoside analogues. The other classes are nucleoside and nucleotide reverse transcriptase inhibitors (tenofovir, emtricitabine, lamivudine, abacavir, zidovudine), non-nucleoside reverse transcriptase inhibitors (efavirenz, rilpivirine, doravirine), protease inhibitors (darunavir, atazanavir, usually boosted with ritonavir or cobicistat), a CCR5 antagonist (maraviroc), a fusion inhibitor (enfuvirtide) and a capsid inhibitor (lenacapavir).
The nursing implications are concrete. Abacavir requires HLA-B*5701 testing before the first dose; a positive result predicts a potentially fatal hypersensitivity reaction and the drug is never rechallenged. Tenofovir disoproxil fumarate is nephrotoxic and reduces bone density, so monitor creatinine, estimated glomerular filtration rate and urine protein; the alafenamide form is gentler on kidney and bone. Integrase inhibitors are well tolerated but cause weight gain and chelate with polyvalent cations — calcium, magnesium, aluminium, iron — so the integrase inhibitor is given at least two hours before, or six hours after, any antacid, calcium, magnesium, iron or multivitamin product. Protease inhibitors are potent cytochrome P450 inhibitors, making drug interaction review mandatory at every admission; statins, rifampin, some anticoagulants and inhaled fluticasone are common collisions. Adherence must exceed roughly ninety-five percent to prevent resistance, so assess barriers honestly: cost, stigma, housing, mental health, substance use, pill burden, and simple forgetting.
Immune reconstitution inflammatory syndrome can appear in the first weeks to months after starting therapy in patients with very low CD4 counts. As immunity returns, the body mounts a florid inflammatory response to a previously silent organism, and the patient looks worse on effective treatment — new fever, enlarging nodes, worsening infiltrates. It is not treatment failure and therapy is usually continued while the underlying infection is treated. For prevention, pre-exposure prophylaxis requires a documented negative HIV test before the first dose, and the retesting interval follows the formulation: daily oral tenofovir/emtricitabine is retested at least every three months, while long-acting injectable cabotegravir — given every two months — requires an HIV test before every injection, because a breakthrough infection left on a long-acting agent is exposed to prolonged effective monotherapy and selects integrase-inhibitor resistance. Post-exposure prophylaxis after occupational or sexual exposure is a twenty-eight-day three-drug regimen started as soon as possible and within seventy-two hours. Finally, teach and reinforce U=U: a person with sustained undetectable viral load does not transmit HIV sexually. That fact is both accurate and therapeutic.
The CD4 count tells you what infection the patient is vulnerable to and therefore what to prophylax and monitor; the viral load tells you whether the antiretroviral regimen and the patient’s adherence are working.
Section 3When the Immune System Turns Inward: Lupus and Connective Tissue Disease
Systemic lupus erythematosus
Lupus is a chronic multisystem autoimmune disease in which autoantibodies against nuclear antigens form immune complexes that deposit in skin, joints, serosal membranes, kidney, blood vessels and brain. It affects women about nine times as often as men, most commonly between fifteen and forty-five years of age, and is more prevalent and more severe in Black, Hispanic, Asian and Indigenous populations — a disparity driven by both biology and access to care. The course is relapsing and remitting, and flares are frequently triggered by ultraviolet light, infection, physical or emotional stress, pregnancy and the postpartum period, and certain drugs.
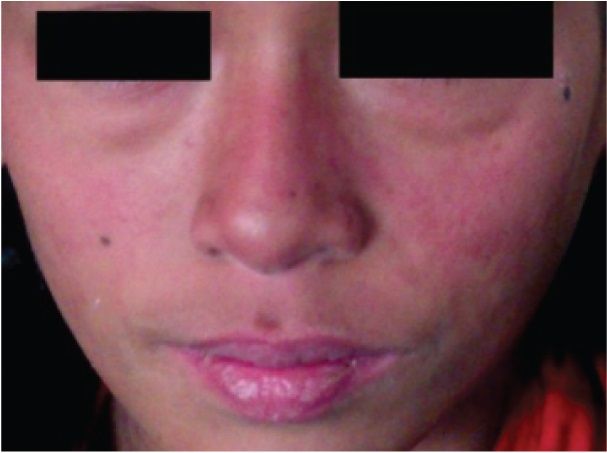
The classic findings are worth memorising because they map to the diagnostic criteria. Constitutional: fatigue that is out of proportion to activity, low-grade fever, weight loss. Skin: the malar rash across the cheeks and nasal bridge sparing the nasolabial folds, discoid plaques that scar, photosensitivity, non-scarring alopecia and painless oral or nasal ulcers. Joints: a symmetric, non-erosive, non-deforming polyarthritis of the small joints. Serosa: pleuritis with pleuritic chest pain, pericarditis with a friction rub. Renal: proteinuria and cellular casts. Neurologic: seizures, psychosis, cognitive dysfunction, stroke. Haematologic: haemolytic anaemia, leucopenia below 4,000/mm3, lymphopenia below 1,000/mm3, thrombocytopenia below 100,000/mm3. Raynaud phenomenon is common. Drug-induced lupus — from hydralazine, procainamide, isoniazid, minocycline or tumour necrosis factor inhibitors — produces arthralgia, serositis and anti-histone antibodies, spares the kidney and brain, and resolves when the drug is stopped.
Serologically, the antinuclear antibody is positive in roughly ninety-eight percent of patients: extremely sensitive, poorly specific, and positive in many healthy older adults, so it screens but never diagnoses. Anti-double-stranded DNA is specific and its titre tracks disease activity, particularly nephritis. Anti-Smith is the most specific antibody but is present in only about a third. Complement components C3 and C4 fall during an active flare because circulating immune complexes consume them, which is the opposite of the intuition that inflammation raises everything. The erythrocyte sedimentation rate rises with activity while C-reactive protein often stays relatively low — a markedly elevated CRP in a lupus patient should raise suspicion for infection or serositis rather than assuming a flare.
Lupus nephritis, antiphospholipid syndrome and managing the flare
Kidney involvement occurs in roughly half of patients and is the leading determinant of long-term outcome, yet it is nearly silent early. That makes urinalysis the highest-yield cheap test you will order: look for proteinuria, red cells and cellular casts, and follow the spot urine protein-to-creatinine ratio. Rising blood pressure, new peripheral oedema, weight gain and foamy urine in a lupus patient are nephritis until proven otherwise. Renal biopsy classifies the lesion, and proliferative disease (Class III or IV) requires induction immunosuppression — glucocorticoids with mycophenolate mofetil or cyclophosphamide, increasingly combined with belimumab or voclosporin — followed by prolonged maintenance.
Antiphospholipid antibodies (lupus anticoagulant, anticardiolipin, anti-beta-2 glycoprotein I) occur in about a third of lupus patients and, when accompanied by thrombosis or recurrent pregnancy loss, define antiphospholipid syndrome. The name is a trap: the lupus anticoagulant prolongs the activated partial thromboplastin time in the test tube but causes clotting in the patient. These patients require long-term anticoagulation with warfarin after an event — direct oral anticoagulants perform worse in triple-positive disease — and their contraception, surgical and immobility risk must be managed aggressively.
Baseline therapy for essentially every lupus patient is hydroxychloroquine, which reduces flares, protects the kidney, lowers thrombosis risk and improves survival. Dose it at or below 5 mg/kg of actual body weight, obtain a baseline retinal examination, and screen annually after five years of use because retinal toxicity is dose- and duration-dependent and irreversible. Glucocorticoids control flares but the goal is always the lowest dose for the shortest time. Nursing care is largely teaching: rigorous photoprotection with broad-spectrum sunscreen of SPF 30 or higher, hats and long sleeves; energy conservation and paced activity for fatigue; prompt reporting of fever because infection is a leading cause of death and immunosuppression masks it; pregnancy planning with a rheumatologist, since conception should occur during six months of quiescent disease and mycophenolate, cyclophosphamide and methotrexate are teratogenic while hydroxychloroquine is continued.
Scleroderma, Sjögren syndrome and giant cell arteritis
Systemic sclerosis is fibrosis driven by immune activation and vascular injury. Limited cutaneous disease presents as the CREST pattern: calcinosis, Raynaud phenomenon, oesophageal dysmotility, sclerodactyly and telangiectasia, associated with anticentromere antibody and a risk of pulmonary arterial hypertension. Diffuse disease spreads proximally and carries anti-Scl-70 (topoisomerase I) antibody with interstitial lung disease, or anti-RNA polymerase III with scleroderma renal crisis — abrupt severe hypertension, headache, rising creatinine and microangiopathic haemolysis. This is a medical emergency: a new blood pressure rise in a scleroderma patient is escalated the same hour, because delay costs the kidney permanently. Renal crisis is treated with an angiotensin-converting enzyme inhibitor, captopril being the traditional choice, and it is one of the few situations where high-dose corticosteroids increase the risk and are avoided. Nursing priorities are warmth and vasospasm avoidance (layered clothing, gloves in the frozen-food aisle, no smoking, calcium channel blockers such as nifedipine for Raynaud), small frequent meals with upright positioning for ninety minutes after eating and a proton pump inhibitor for reflux, meticulous skin care and range of motion to preserve hand function, and daily blood pressure checks at home.
Sjögren syndrome is lymphocytic destruction of exocrine glands producing dry eyes (keratoconjunctivitis sicca) and dry mouth (xerostomia), with anti-SSA/Ro and anti-SSB/La antibodies and a positive Schirmer test. It is not a nuisance diagnosis: xerostomia causes rampant dental caries and candidiasis, dryness causes corneal damage, and there is a substantially increased lifetime risk of non-Hodgkin lymphoma, so a new persistent parotid mass or lymphadenopathy must be evaluated. Teach preservative-free artificial tears, sugar-free gum or lozenges, frequent water sips, meticulous oral hygiene with fluoride and quarterly dental review, humidified air, and avoidance of anticholinergic drugs that worsen dryness. Pilocarpine or cevimeline stimulate residual glandular secretion.
Giant cell arteritis is the rheumatologic emergency of the older adult. In a patient over fifty with a new temporal or occipital headache, scalp tenderness (the pillow or the comb hurts), jaw claudication when chewing, constitutional symptoms and a sedimentation rate often above 50 mm/h with elevated C-reactive protein, the threat is irreversible monocular blindness from anterior ischaemic optic neuropathy. Transient visual loss or diplopia is the warning shot. Start high-dose glucocorticoids immediately — do not wait for the temporal artery biopsy, which remains positive for one to two weeks after steroids are begun. Prednisone 40 to 60 mg daily for uncomplicated disease; intravenous methylprednisolone 500 to 1,000 mg daily for three days when vision is threatened or lost. Tocilizumab is used as a steroid-sparing agent. Its cousin, polymyalgia rheumatica, causes bilateral shoulder and hip girdle aching and morning stiffness with a dramatic response to low-dose prednisone of 12.5 to 25 mg daily; up to a fifth of these patients also have arteritis, so screen every one of them for headache and visual symptoms at each contact.
| Antibody | Points toward | Bedside meaning |
|---|---|---|
| Antinuclear antibody | Lupus and most connective tissue disease | Sensitive screen only; positive in healthy older adults |
| Anti-double-stranded DNA | Systemic lupus erythematosus | Specific; titre tracks activity and nephritis |
| Anti-Smith | Systemic lupus erythematosus | Most specific for lupus; present in about one third |
| Anti-histone | Drug-induced lupus | Look for hydralazine, procainamide, isoniazid, minocycline |
| Anticentromere | Limited systemic sclerosis (CREST) | Screen for pulmonary arterial hypertension |
| Anti-Scl-70 (topoisomerase I) | Diffuse systemic sclerosis | Interstitial lung disease risk; monitor lung function |
| Anti-RNA polymerase III | Diffuse systemic sclerosis | Renal crisis risk; daily blood pressure at home |
| Anti-SSA/Ro, anti-SSB/La | Sjögren syndrome, neonatal lupus | Dryness care; fetal heart block risk in pregnancy |
| Anti-cyclic citrullinated peptide | Rheumatoid arthritis | Highly specific; predicts erosive disease |
In lupus a rising anti-dsDNA titre with falling C3 and C4 signals an active flare, while a new headache with jaw claudication or visual change in an adult over fifty means starting steroids for giant cell arteritis before any biopsy is arranged.
Section 4Inflammatory Joint Disease: Rheumatoid Arthritis, Spondyloarthritis and Gout
Rheumatoid arthritis
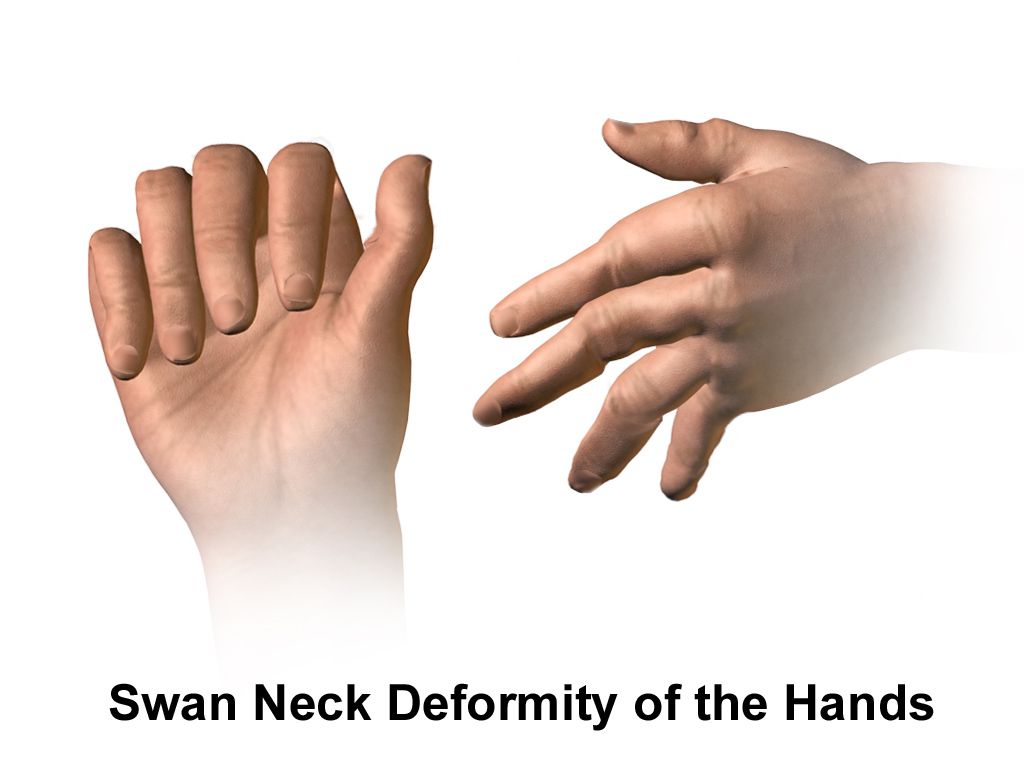
Rheumatoid arthritis is a chronic systemic autoimmune disease in which synovial inflammation forms an invasive pannus that erodes cartilage and bone. The joint pattern is the diagnosis: symmetric involvement of the small joints — metacarpophalangeal, proximal interphalangeal, wrists and metatarsophalangeal — with characteristic sparing of the distal interphalangeal joints. Morning stiffness lasts longer than sixty minutes and improves with use, the exact inverse of osteoarthritis, where brief stiffness worsens through the day with activity. Late deformities include ulnar deviation, swan-neck and boutonnière fingers, and subluxation. Systemic features are prominent: fatigue, low-grade fever, weight loss, rheumatoid nodules over pressure points, interstitial lung disease, pericarditis, scleritis, secondary Sjögren syndrome, and Felty syndrome (rheumatoid arthritis with splenomegaly and neutropenia). Cardiovascular risk is elevated roughly like that of diabetes, so lipids, blood pressure and smoking cessation are part of arthritis care.
Laboratory support comes from rheumatoid factor, positive in seventy to eighty percent but also positive in hepatitis C, Sjögren and healthy older adults, and anti-cyclic citrullinated peptide antibody, which is roughly ninety-five percent specific, appears years before symptoms and predicts erosive disease. Sedimentation rate and C-reactive protein track activity, and a normocytic anaemia of chronic inflammation is typical. Radiographs show periarticular osteopenia and marginal erosions; ultrasound and magnetic resonance imaging detect synovitis earlier. One finding must never be forgotten on a medical–surgical unit: atlantoaxial subluxation. Erosion of the transverse ligament at C1–C2 lets the odontoid impinge on the spinal cord during neck flexion, so any patient with long-standing rheumatoid arthritis needs cervical spine evaluation before intubation, positioning under anaesthesia or aggressive neck manipulation, and new neck pain with paraesthesia or gait change is escalated immediately.
Treatment is treat-to-target and time-sensitive: a conventional disease-modifying antirheumatic drug should start within three months of symptom onset because erosions that occur are permanent. Methotrexate is the anchor, 7.5 to 25 mg once weekly with folic acid 1 mg daily to reduce mucositis and cytopenias. Daily dosing of methotrexate is a classic fatal medication error; when you take that order or reconcile that home list, verify the day of the week and that the patient can say it back. Monitor complete blood count, liver enzymes and creatinine every two to three months, avoid alcohol, hold with active infection, and remember it is a potent teratogen requiring reliable contraception. Alternatives and add-ons include hydroxychloroquine, sulfasalazine (avoid with sulfa allergy or G6PD deficiency; warn about orange discolouration of urine and skin) and leflunomide (teratogenic, with a cholestyramine washout protocol). Non-steroidal anti-inflammatory drugs and short steroid bursts control symptoms but do not stop erosion. Nursing care emphasises heat before activity and cold for acute swelling, joint protection and larger-joint techniques, splints, paced activity with rest periods, occupational therapy for adaptive devices, and structured low-impact exercise.
| Feature | Rheumatoid arthritis | Osteoarthritis | Gout |
|---|---|---|---|
| Pattern | Symmetric, small joints, spares distal interphalangeal | Asymmetric, weight-bearing, distal interphalangeal and first carpometacarpal | Monoarticular, first metatarsophalangeal, midfoot, ankle, knee |
| Stiffness | Over 60 minutes, improves with use | Under 30 minutes, worsens with use | Sudden severe pain, often overnight, peaks in 12 to 24 hours |
| Systemic signs | Fatigue, fever, nodules, lung and eye disease | None | Occasional low-grade fever; tophi in chronic disease |
| Key tests | Anti-CCP, rheumatoid factor, elevated ESR and CRP | Clinical, radiographic joint space narrowing and osteophytes | Arthrocentesis: needle-shaped negatively birefringent crystals |
| Core treatment | Methotrexate and biologic DMARDs | Exercise, weight loss, acetaminophen, topical NSAIDs | Acute: NSAID, colchicine, steroid. Long term: allopurinol |
Spondyloarthritis and the non-inflammatory mimics
Axial spondyloarthritis, including ankylosing spondylitis, is inflammation of the sacroiliac joints and spinal entheses, typically beginning before age forty-five in a patient carrying HLA-B27. The history is the giveaway: inflammatory back pain that is worse at rest and in the second half of the night, better with movement and exercise, with morning stiffness over thirty minutes and insidious onset over months. Over years, syndesmophytes bridge the vertebrae to produce the fused “bamboo spine,” restricting chest expansion and creating a restrictive ventilatory defect. Extra-articular features are anterior uveitis (a painful red eye with photophobia that needs same-day ophthalmology), inflammatory bowel disease, psoriasis and aortic regurgitation. Related conditions include psoriatic arthritis with dactylitis and nail pitting, and reactive arthritis following genitourinary or enteric infection.
Management is exercise-forward: daily extension and postural exercises, sleeping supine on a firm mattress with a thin pillow, swimming, and smoking cessation because smoking accelerates fusion and lung restriction. Non-steroidal anti-inflammatory drugs are first-line pharmacotherapy, and tumour necrosis factor or interleukin-17 inhibitors are added for inadequate response. A safety point that catches nurses out: the rigid ankylosed spine fractures with trivial trauma, often at the cervicothoracic junction, and the fracture is unstable. A spondylitic patient who falls from standing height and reports new neck pain gets full spinal precautions and imaging, not reassurance.
Not every aching patient is inflamed. Fibromyalgia is a disorder of central pain processing producing widespread pain, unrefreshing sleep, cognitive fog and fatigue with normal sedimentation rate, C-reactive protein and imaging. It coexists with rheumatoid arthritis and lupus and is frequently mistaken for a flare, leading to unnecessary steroid escalation. Treatment is graded aerobic exercise, sleep hygiene, cognitive behavioural therapy, and medications acting centrally — duloxetine, milnacipran, pregabalin or low-dose amitriptyline — not opioids and not immunosuppression. Validating the pain while explaining that the tests are normal because the problem is amplification, not destruction, is a genuine nursing skill.
Gout and calcium pyrophosphate deposition
Gout is the deposition of monosodium urate crystals in joints and soft tissue when serum urate exceeds its solubility, roughly 6.8 mg/dL. Risk rises with male sex, obesity, chronic kidney disease, alcohol (beer especially), high-fructose beverages, purine-rich foods, and drugs that raise urate — thiazide and loop diuretics, low-dose aspirin, cyclosporine, niacin. The acute attack is a red-hot, exquisitely tender monoarthritis, classically the first metatarsophalangeal joint (podagra), often waking the patient at night and peaking within twelve to twenty-four hours. Chronic untreated disease produces tophi over the helix of the ear, olecranon and finger pads, and erosive joint destruction.
The definitive test is arthrocentesis: urate crystals are needle-shaped and negatively birefringent (yellow when parallel to the polariser), while calcium pyrophosphate crystals in pseudogout are rhomboid and positively birefringent, favouring the knee and wrist in older adults. Aspiration also answers the far more dangerous question — is this septic arthritis? A synovial white cell count above 50,000/mm3 with a neutrophil predominance points to infection, which is a surgical and antibiotic emergency. Note that serum uric acid is often normal or low during an acute attack, so a normal level never excludes gout; measure it two weeks or more after the flare settles.
Acute treatment is anti-inflammatory: a full-dose non-steroidal anti-inflammatory drug, colchicine 1.2 mg followed by 0.6 mg one hour later, or corticosteroids (oral prednisone or intra-articular injection) when kidney disease, anticoagulation or heart failure make the others unsafe. Colchicine causes dose-limiting diarrhoea, needs dose reduction in renal and hepatic impairment, and interacts dangerously with clarithromycin, verapamil, diltiazem and statins. Urate-lowering therapy is indicated for recurrent flares, tophi, erosions or urate nephrolithiasis: allopurinol, a xanthine oxidase inhibitor, started low at 100 mg daily (50 mg in advanced chronic kidney disease) and titrated to a serum urate below 6.0 mg/dL. Screen for HLA-B*5801 in patients of Han Chinese, Thai or Korean ancestry because of severe cutaneous reactions, and never combine full-dose allopurinol with azathioprine or mercaptopurine without a large dose reduction. Prophylactic low-dose colchicine or an NSAID for three to six months prevents the mobilisation flares that occur as tophi dissolve. Classically, urate-lowering therapy is deferred until a flare settles; current guidance permits starting during a flare provided anti-inflammatory prophylaxis is running — but the drug is never stopped mid-flare once established. Teach 2 to 3 L of fluid daily, weight loss, limiting organ meats, sardines, anchovies, shellfish and red meat, avoiding beer and sweetened beverages, and note that low-fat dairy appears protective.
Joint distribution and stiffness pattern separate the arthritides at the bedside — symmetric small joints with prolonged morning stiffness that eases with use is rheumatoid, and a single hot joint always earns an aspiration before it earns a diagnosis.
Section 5Immunosuppression, Biologics and Transplant: Keeping the Treatment From Becoming the Problem
Corticosteroids: the drug that treats everything and complicates everything
Glucocorticoids suppress essentially every inflammatory pathway, which is why they appear in the treatment of every disease in this chapter and why their adverse effects are a syllabus of their own. Expect hyperglycaemia even in non-diabetics, hypertension and fluid retention, hypokalaemia, weight gain with central fat redistribution, mood lability and insomnia, cataract and glaucoma, thin fragile skin with bruising and poor wound healing, proximal myopathy, osteoporosis, avascular necrosis of the femoral head, peptic ulceration when combined with NSAIDs, and blunted fever and inflammatory markers that mask infection. Give the daily dose in the morning to mimic the cortisol rhythm and reduce insomnia, and administer with food.
Two teaching points prevent readmissions. First, never stop systemic steroids abruptly after more than about two to three weeks of therapy; the hypothalamic–pituitary–adrenal axis is suppressed and abrupt withdrawal precipitates adrenal crisis with hypotension, hypoglycaemia, hyponatraemia, vomiting and shock. Doses are tapered, and patients on chronic therapy need stress dosing for surgery, serious illness or trauma plus a medical alert identifier. Second, protect the skeleton from the outset: 1,000 to 1,200 mg of calcium and 800 international units of vitamin D daily, weight-bearing exercise, smoking and alcohol reduction, baseline bone densitometry, and bisphosphonate therapy for patients who will take the equivalent of 2.5 to 5 mg of prednisone or more for three months or longer. Monitor capillary glucose in every hospitalised patient started on high-dose steroids, whether or not they carry a diabetes diagnosis.
Conventional DMARDs, biologics and JAK inhibitors
Biologic disease-modifying agents target single cytokines or cell populations, and their power is matched by their infection risk. Before the first dose of a tumour necrosis factor inhibitor — etanercept, adalimumab, infliximab, golimumab, certolizumab — the patient must be screened for latent tuberculosis with an interferon-gamma release assay or tuberculin skin test plus chest radiograph, and for hepatitis B and C. These drugs reactivate latent tuberculosis, often extrapulmonary and disseminated. They also worsen moderate to severe heart failure and are avoided in New York Heart Association class III and IV disease, may unmask demyelinating disease, and carry a small lymphoma signal. Interleukin-6 inhibitors (tocilizumab, sarilumab) suppress C-reactive protein and fever, so a patient on one of them can be septic with a normal CRP and a normal temperature; they also raise the risk of gastrointestinal perforation in patients with diverticular disease. Rituximab, an anti-CD20 antibody, causes infusion reactions, reactivates hepatitis B, and rarely causes progressive multifocal leukoencephalopathy. JAK inhibitors (tofacitinib, baricitinib, upadacitinib) carry a boxed warning for serious infection, mortality, major adverse cardiovascular events, malignancy and thrombosis, and commonly reactivate herpes zoster.
Across the whole class the nursing rules are the same. Hold the drug during an active infection and before major surgery, per protocol. Give no live vaccines while immunosuppressed — that excludes intranasal influenza, measles-mumps-rubella, varicella, yellow fever and oral typhoid; any live vaccine that is genuinely indicated must be completed at least four weeks before immunosuppression begins. Inactivated and recombinant vaccines are encouraged and are ideally given at least two weeks before starting therapy, though they may be given at any point during it. The recombinant zoster vaccine is not live and is recommended. Teach subcutaneous self-injection with site rotation, storage in the refrigerator with the pen allowed to reach room temperature for about thirty minutes before injection, safe sharps disposal, and never shaking the pen. Report fever, cough, night sweats, unexplained weight loss, new or spreading rash, or a non-healing wound. Screen for skin cancer annually and use sunscreen, since long-term immunosuppression raises non-melanoma skin cancer risk substantially.
| Agent | Screen before starting | Ongoing monitoring | Teach the patient |
|---|---|---|---|
| Methotrexate | CBC, LFTs, creatinine, pregnancy test, hepatitis serology | CBC, LFTs, creatinine every 2 to 3 months | Once weekly only; daily folic acid; no alcohol; report mouth sores, cough, bruising |
| Hydroxychloroquine | Baseline dilated eye exam | Annual retinal screening after 5 years; keep dose at or below 5 mg/kg | Report blurred vision or difficulty reading; takes 2 to 3 months to work |
| Sulfasalazine | CBC, LFTs, G6PD if indicated, sulfa allergy history | CBC and LFTs periodically | Orange discolouration of urine and skin; drink fluids; report sore throat or rash |
| TNF inhibitors | Latent TB test, chest radiograph, hepatitis B and C, heart failure history | Annual TB screening; infection surveillance | Hold when febrile or infected; no live vaccines; refrigerate pens |
| IL-6 inhibitors | TB and hepatitis screen, lipid panel, diverticular history | CBC, LFTs, lipids; neutrophil count | Fever and CRP may be suppressed — report any new symptom, not just fever |
| Rituximab | Hepatitis B surface antigen and core antibody, immunoglobulins | Infusion reaction monitoring, CBC, immunoglobulin levels | Report new neurologic symptoms, infection, or infusion-site reaction |
| JAK inhibitors | TB and hepatitis screen, lipids, CBC, thrombosis and cardiovascular risk | CBC, lipids, LFTs, creatinine; zoster vigilance | Report shingles rash, chest pain, leg swelling or shortness of breath urgently |
Transplant immunosuppression and rejection
Solid-organ rejection is graded by timing and mechanism. Hyperacute rejection occurs within minutes to hours in the operating room from preformed recipient antibodies against donor antigen; the graft thromboses and must be removed, which is why ABO and crossmatch verification is a two-nurse, no-shortcuts process. Acute rejection is T cell mediated and occurs days to months after transplant — the patient presents with fever, tenderness over the graft, weight gain, decreased urine output and rising creatinine in a kidney recipient, or rising transaminases and bilirubin in a liver recipient. It is treatable with pulse methylprednisolone, antithymocyte globulin or intensified maintenance therapy, so early detection matters enormously. Chronic rejection develops over months to years as fibrosis and vasculopathy, is not reversible, and is managed by slowing decline and planning re-transplantation.
Maintenance therapy is typically triple: a calcineurin inhibitor, an antimetabolite and a corticosteroid. Tacrolimus is monitored by trough level drawn immediately before the morning dose — commonly targeted in the range of 5 to 15 ng/mL early after transplant and lower thereafter, per the transplant centre’s protocol. Its toxicities are nephrotoxicity, tremor and neurotoxicity, hyperglycaemia and post-transplant diabetes, hyperkalaemia, hypomagnesaemia and hypertension. It is metabolised by CYP3A4, so grapefruit juice, azole antifungals, macrolides, diltiazem and many others raise levels while rifampin and St John’s wort drop them into rejection range. Cyclosporine is similar with the added signatures of gingival hyperplasia and hirsutism. Mycophenolate causes gastrointestinal upset and cytopenias and is a known teratogen requiring pregnancy testing and effective contraception under a risk management programme. Azathioprine requires thiopurine methyltransferase assessment and interacts catastrophically with allopurinol. Prophylaxis against opportunistic infection — trimethoprim–sulfamethoxazole for Pneumocystis, valganciclovir for cytomegalovirus, antifungal coverage as indicated — runs for months after transplant.
Nursing care of the immunosuppressed inpatient is unglamorous and decisive: strict hand hygiene as the single highest-yield intervention, private room with protective environment precautions where indicated, daily assessment of every line, wound, mucous membrane and perineum, oral care, no fresh flowers or standing water in profound neutropenia, avoidance of undercooked meat and eggs, unpasteurised dairy and unwashed produce, no rectal temperatures, suppositories or enemas in neutropenic patients, and never assume the absence of fever means the absence of infection. Family and visitors with respiratory symptoms are redirected. Daily weight, intake and output, blood pressure and graft-specific parameters are the early warning system.
Immunosuppressive therapy removes the very signs you use to detect infection, so in these patients a subtle change in mental status, blood pressure or function outranks a normal temperature and white count every single time.
The chapter in one breath
Immune disease reduces to overreaction, underperformance and misdirected attack, and each has its own first move. Overreaction is hypersensitivity: Type I IgE reactions arrive in minutes and anaphylaxis is treated with intramuscular epinephrine 0.3 to 0.5 mg in the anterolateral thigh before any antihistamine or steroid, with supine positioning, fluids, oxygen and four to six hours of observation for a biphasic reaction. Underperformance is immunodeficiency, most commonly drug-induced or from HIV, where the CD4 count predicts which opportunistic infection to fear and prophylax, a count below 200 cells/mm3 defines AIDS, and the viral load reports adherence and regimen success. Misdirected attack is autoimmunity: lupus with a positive antinuclear antibody, a specific anti-dsDNA titre and falling complement during flares, silent nephritis found on urinalysis, and hydroxychloroquine for nearly everyone with a baseline retinal examination and annual screening after five years of use; scleroderma with renal crisis treated urgently by an ACE inhibitor and not by high-dose steroids; giant cell arteritis where steroids precede biopsy because blindness is irreversible; rheumatoid arthritis with symmetric small-joint disease, prolonged morning stiffness, anti-CCP antibody and weekly methotrexate; and gout confirmed by needle-shaped negatively birefringent crystals and controlled to a urate below 6.0 mg/dL. Every therapy in this chapter suppresses immunity, so infection surveillance without relying on fever is the through-line of nursing care.
Words worth knowing
| Term | What it means |
|---|---|
| Anaphylaxis | Rapid, life-threatening Type I hypersensitivity with airway, breathing or circulatory compromise; treated first with intramuscular epinephrine. |
| Biphasic reaction | Recurrence of anaphylaxis one to eight hours (occasionally up to seventy-two) after apparent resolution, without re-exposure. |
| Type IV hypersensitivity | Delayed, T cell mediated reaction appearing 24 to 72 hours later; includes contact dermatitis, tuberculin reaction and graft rejection. |
| CD4 count | Helper T lymphocyte count (normal roughly 500 to 1,600 cells/mm3) that gauges immune damage in HIV; below 200 defines AIDS. |
| Viral load | HIV RNA copies per millilitre of plasma; the treatment target is undetectable, usually fewer than 20 to 50 copies/mL. |
| Immune reconstitution inflammatory syndrome | Paradoxical worsening of a latent infection weeks after starting antiretroviral therapy as immunity recovers. |
| U=U | Undetectable equals untransmittable — sustained viral suppression prevents sexual transmission of HIV. |
| Antinuclear antibody | Highly sensitive but non-specific autoantibody screen; positive in about 98 percent of lupus and in many healthy older adults. |
| Anti-double-stranded DNA | Lupus-specific antibody whose titre rises with disease activity, especially nephritis. |
| Complement (C3, C4) | Serum proteins consumed by immune complexes; falling levels signal an active lupus flare. |
| Antiphospholipid syndrome | Autoantibodies causing thrombosis and pregnancy loss despite a prolonged aPTT in the test tube. |
| Scleroderma renal crisis | Abrupt hypertension with rising creatinine in systemic sclerosis; treated with an ACE inhibitor, worsened by high-dose steroids. |
| Jaw claudication | Pain in the masseters while chewing; a hallmark of giant cell arteritis that precedes irreversible vision loss. |
| Pannus | Invasive inflamed synovial tissue in rheumatoid arthritis that erodes cartilage and bone. |
| Anti-cyclic citrullinated peptide | Antibody roughly 95 percent specific for rheumatoid arthritis that predicts erosive disease. |
| Atlantoaxial subluxation | C1–C2 instability in long-standing rheumatoid arthritis risking cord compression during neck flexion or intubation. |
| Podagra | Acute gouty arthritis of the first metatarsophalangeal joint. |
| Negatively birefringent crystals | Needle-shaped monosodium urate crystals seen on polarised microscopy of synovial fluid; diagnostic of gout. |
| Tophus | Firm subcutaneous deposit of urate crystals in chronic gout, typically on the ear helix, olecranon or finger pads. |
| Acute rejection | T cell mediated graft injury days to months after transplant, reversible with pulse steroids or antithymocyte globulin. |