The Urinary System
Every minute, about a fifth of the blood your heart pumps takes a detour through two fist-sized organs tucked against your back — and comes out cleaner, better balanced, and more precisely tuned than it went in. This chapter follows that journey. You will meet the four organs of the urinary system, cut open a kidney to see how it is built, shrink down to the microscopic nephron where urine is actually made, and watch the three steps — filter, reclaim, and fine-tune — that turn 180 liters of filtered plasma a day into barely a liter and a half of urine. Along the way you will see how a handful of hormones let the kidney set your blood volume and blood pressure, and how a simple spinal reflex — one you learned to override as a toddler — empties the bladder. If homeostasis is the theme of the whole course, the kidney is its master craftsman.
By the end of this chapter you can
- List the four organs of the urinary system and state the job of each, and describe the many homeostatic roles the kidneys play beyond making urine.
- Identify the major gross structures of the kidney — cortex, medulla, pyramids, calyces, and renal pelvis — and trace the path urine takes to leave.
- Describe the nephron as the functional unit of the kidney and name its segments in order from renal corpuscle to collecting duct.
- Explain the filtration membrane and how the renal corpuscle produces a protein-free filtrate.
- Distinguish the three processes of urine formation — filtration, reabsorption, and secretion — and say where each happens.
- Explain how ADH, aldosterone, the renin–angiotensin–aldosterone system, and ANP adjust water and salt to control blood volume and pressure.
- Describe the micturition reflex and how voluntary control of the external sphincter lets you decide when to void.
Section 1What the urinary system does
Not just a waste line
It is tempting to file the urinary system under "waste disposal" and move on — but that badly undersells it. Yes, the kidneys clear nitrogen wastes like urea (from protein breakdown) and creatinine (from muscle). But their deeper job is homeostasis: minute by minute, they decide exactly how much water, sodium, potassium, calcium, and acid to keep and how much to let go, holding the blood's composition inside the narrow ranges cells need to survive. The kidney is where the abstract idea of a steady internal environment becomes a real, physical machine. When you drink a large glass of water, the kidney sheds the excess within the hour; when you are dehydrated, it clamps down and concentrates the urine to save every drop. It also does jobs that have nothing to do with urine at all — it helps set blood pressure, tells the bone marrow to make red blood cells, and activates vitamin D.
The four organs, in order
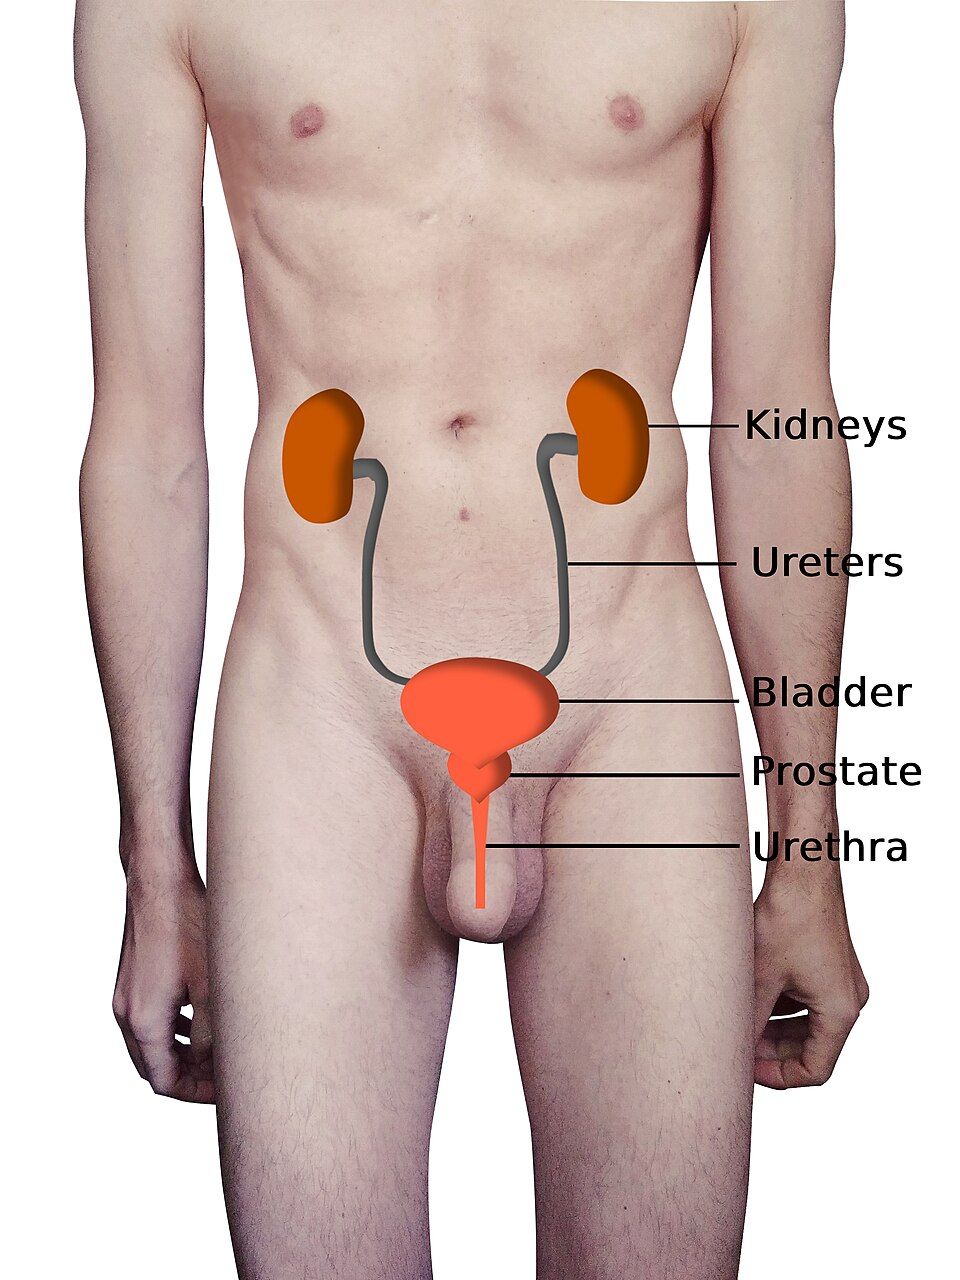
The plumbing is refreshingly simple. Two kidneys make urine. Two ureters carry it downhill. One urinary bladder stores it. One urethra carries it out. Everything upstream of the ureters is about chemistry — adjusting the blood — and everything from the ureters down is about transport and storage. The kidneys sit high on the back wall of the abdomen, one on each side of the spine, retroperitoneal (behind the lining of the abdominal cavity rather than inside it). The right kidney rides a little lower than the left because the large liver sits above it.
| Organ | Number | Main job |
|---|---|---|
| Kidneys | 2 | Filter blood and form urine; balance water, salts, and pH; help set blood pressure and red-cell count |
| Ureters | 2 | Carry urine from kidney to bladder by peristalsis (muscular waves) |
| Urinary bladder | 1 | Stores urine until it is convenient to release it |
| Urethra | 1 | Carries urine from bladder to the outside of the body |
A river of blood, a trickle of urine
The scale of the kidney's work is startling. Together the kidneys receive roughly 20–25% of the entire cardiac output — more blood per gram than almost any other organ — and from it they filter about 180 liters of fluid every day. If that all left as urine you would be in serious trouble, so the kidney reclaims more than 99% of it, and only about 1–2 liters actually leaves as urine. That enormous filter-then-reclaim strategy is the secret to the kidney's precision: by pushing a huge volume out and then choosing exactly what to take back, it can regulate dozens of substances independently.
Tap each of the four organs in the interactive to see where it sits and what it does.
- The urinary system has four organs: two kidneys (make urine), two ureters (transport), one bladder (store), one urethra (void).
- The kidneys do far more than clear waste — they regulate water, electrolytes, and pH, and help control blood pressure, red-cell production, and vitamin D.
- The kidneys are retroperitoneal and receive ~20–25% of cardiac output, filtering ~180 L/day but excreting only 1–2 L of urine.
Section 2Inside the kidney
The layers from outside in
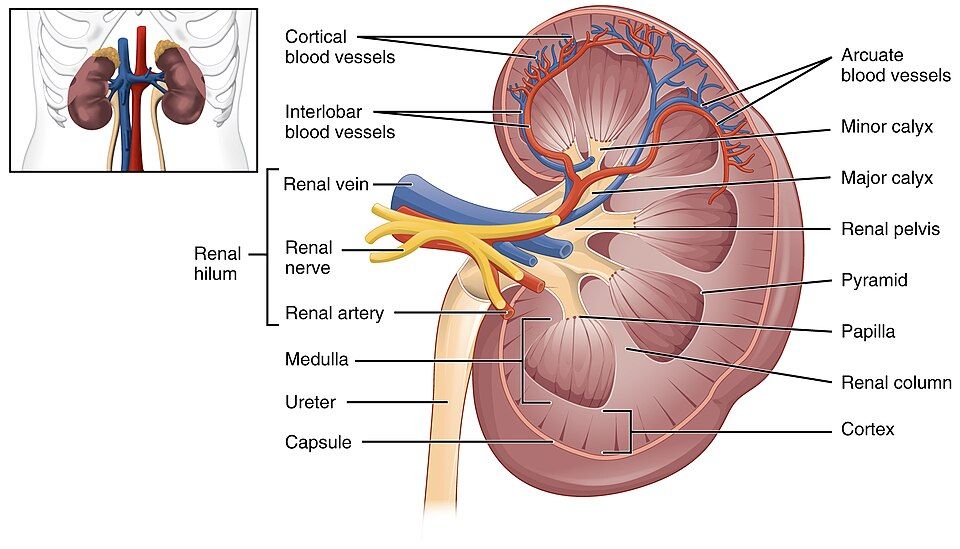
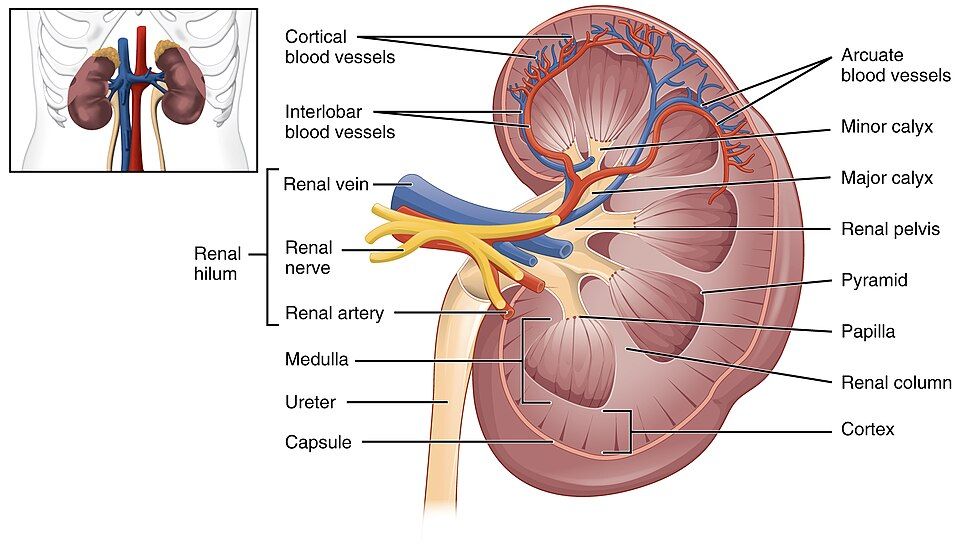
Slice a kidney down the middle like a bean and it reveals a beautifully organized set of layers. A tough fibrous renal capsule wraps the surface. Just beneath it is the renal cortex, the granular outer working layer where filtration begins. Deeper still is the renal medulla, arranged into 8–18 cone-shaped renal pyramids. The pyramids point inward, and the tip of each cone — the renal papilla — drips finished urine into the collecting spaces. Stripes of cortex called renal columns dip down between the pyramids, carrying blood vessels. The whole apparatus curves around a notch on the medial border, the hilum, where the renal artery enters, and the renal vein and ureter leave.
The drainage route
Once urine drips off a papilla it never touches kidney tissue again — it is simply collected and drained. The route is worth memorizing because it names the structures a kidney stone travels through: urine leaves the papilla into a cup-shaped minor calyx, several of which merge into a major calyx, and the major calyces empty into the funnel-shaped renal pelvis. The renal pelvis narrows at the hilum to become the ureter. From papilla to bladder, then, the path is: papilla → minor calyx → major calyx → renal pelvis → ureter.
| Structure | Location | What happens there |
|---|---|---|
| Renal capsule | Outer surface | Fibrous coat that protects the kidney |
| Renal cortex | Outer working layer | Holds the renal corpuscles; filtration begins here |
| Renal medulla (pyramids) | Deep to the cortex | Holds the loops and collecting ducts that concentrate urine |
| Renal papilla | Tip of each pyramid | Drips finished urine into a minor calyx |
| Calyces & renal pelvis | Central collecting space | Funnel urine toward the ureter (no further processing) |
| Hilum | Medial notch | Entry/exit for renal artery, renal vein, and ureter |
Two capillary beds in a row
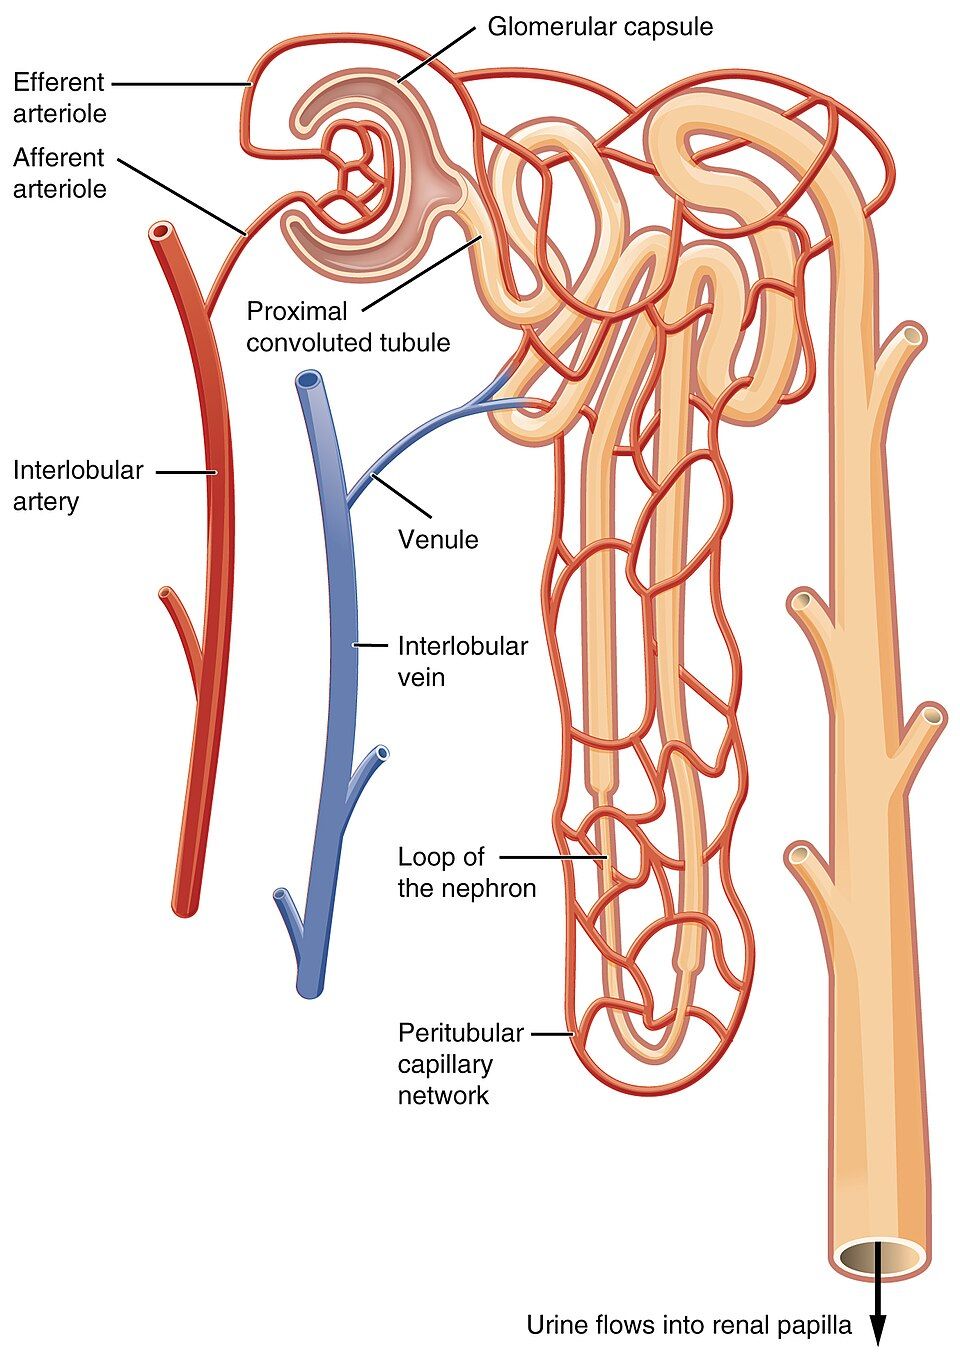
The kidney's blood supply has one unusual feature that makes everything else work. Most organs have a single capillary bed; the kidney has two capillary beds in series. Blood arrives through the renal artery, branches down to a tiny afferent arteriole, and enters the first bed — a high-pressure knot of capillaries called the glomerulus, where filtration happens. Instead of draining into a vein, blood leaves the glomerulus through an efferent arteriole and enters a second bed, the peritubular capillaries that wrap around the tubules. This two-bed design lets the kidney filter under high pressure in the first bed and then reabsorb under low pressure in the second — two opposite jobs, done in sequence.
Explore each zone by slicing the kidney in the interactive below.
- From outside in: capsule → cortex → medulla (pyramids), with cortex-filled renal columns between the pyramids.
- Urine drains: papilla → minor calyx → major calyx → renal pelvis → ureter, with no further processing after the papilla.
- The kidney has two capillary beds in series — the high-pressure glomerulus (filtration) and the low-pressure peritubular capillaries (reabsorption).
Section 3The nephron
A million tiny factories
The kidney does not filter as one big sieve. Its work is divided among roughly one million microscopic units per kidney called nephrons, and each is a complete little urine factory. A nephron has two parts: the renal corpuscle, where filtrate is made, and a long, winding renal tubule, where that filtrate is processed into urine. Understanding one nephron means understanding the whole kidney — the organ is just this same unit repeated a million times over.
The renal corpuscle and the filtration membrane
The renal corpuscle is where blood becomes filtrate. It has two components: the glomerulus (that high-pressure ball of capillaries) sitting inside a cup called the glomerular capsule (Bowman's capsule). Fluid squeezes out of the glomerular blood, across a three-layered filtration membrane, into the capsule. The membrane is exquisitely selective. Its first layer is the fenestrated ("windowed") capillary wall, riddled with pores. Its middle layer is a basement membrane whose negative charge repels proteins. Its third layer is made of octopus-like cells called podocytes, whose interlocking foot processes leave narrow filtration slits. Together these layers let water and small solutes through freely while holding back blood cells and plasma proteins — so normal filtrate is essentially protein-free plasma. Finding protein or blood in the urine is a red flag that this membrane is damaged.
Following the tubule
From the capsule, filtrate flows through the tubule's named segments in a fixed order, and each segment has its own personality: the proximal convoluted tubule (PCT), the hairpin loop of Henle (a descending limb and an ascending limb), the distal convoluted tubule (DCT), and finally the collecting duct, which gathers filtrate from many nephrons and carries it toward the papilla. Some nephrons sit almost entirely in the cortex (cortical nephrons); a smaller group, the juxtamedullary nephrons, have long loops that plunge deep into the medulla and are what make concentrated urine possible.
| Segment | Location | Main role |
|---|---|---|
| Renal corpuscle | Cortex | Filtration — makes protein-free filtrate |
| Proximal convoluted tubule (PCT) | Cortex | Bulk reabsorption of water, Na⁺, glucose, amino acids |
| Loop of Henle | Medulla | Sets up the salty gradient that lets the kidney concentrate urine |
| Distal convoluted tubule (DCT) | Cortex | Fine-tuning under hormone control (Na⁺, K⁺, Ca²⁺) |
| Collecting duct | Cortex & medulla | Final water reabsorption (ADH-controlled); drains to papilla |
Trace the filtrate through every twist of the nephron in the interactive.
- The nephron is the functional unit of the kidney (~1 million per kidney), made of a renal corpuscle plus a renal tubule.
- The filtration membrane — fenestrated capillary, basement membrane, podocyte slits — passes water and small solutes but holds back cells and proteins.
- Tubule order: corpuscle → PCT → loop of Henle → DCT → collecting duct; long-looped juxtamedullary nephrons concentrate the urine.
Section 4How urine is made
Three steps: dump, reclaim, fine-tune
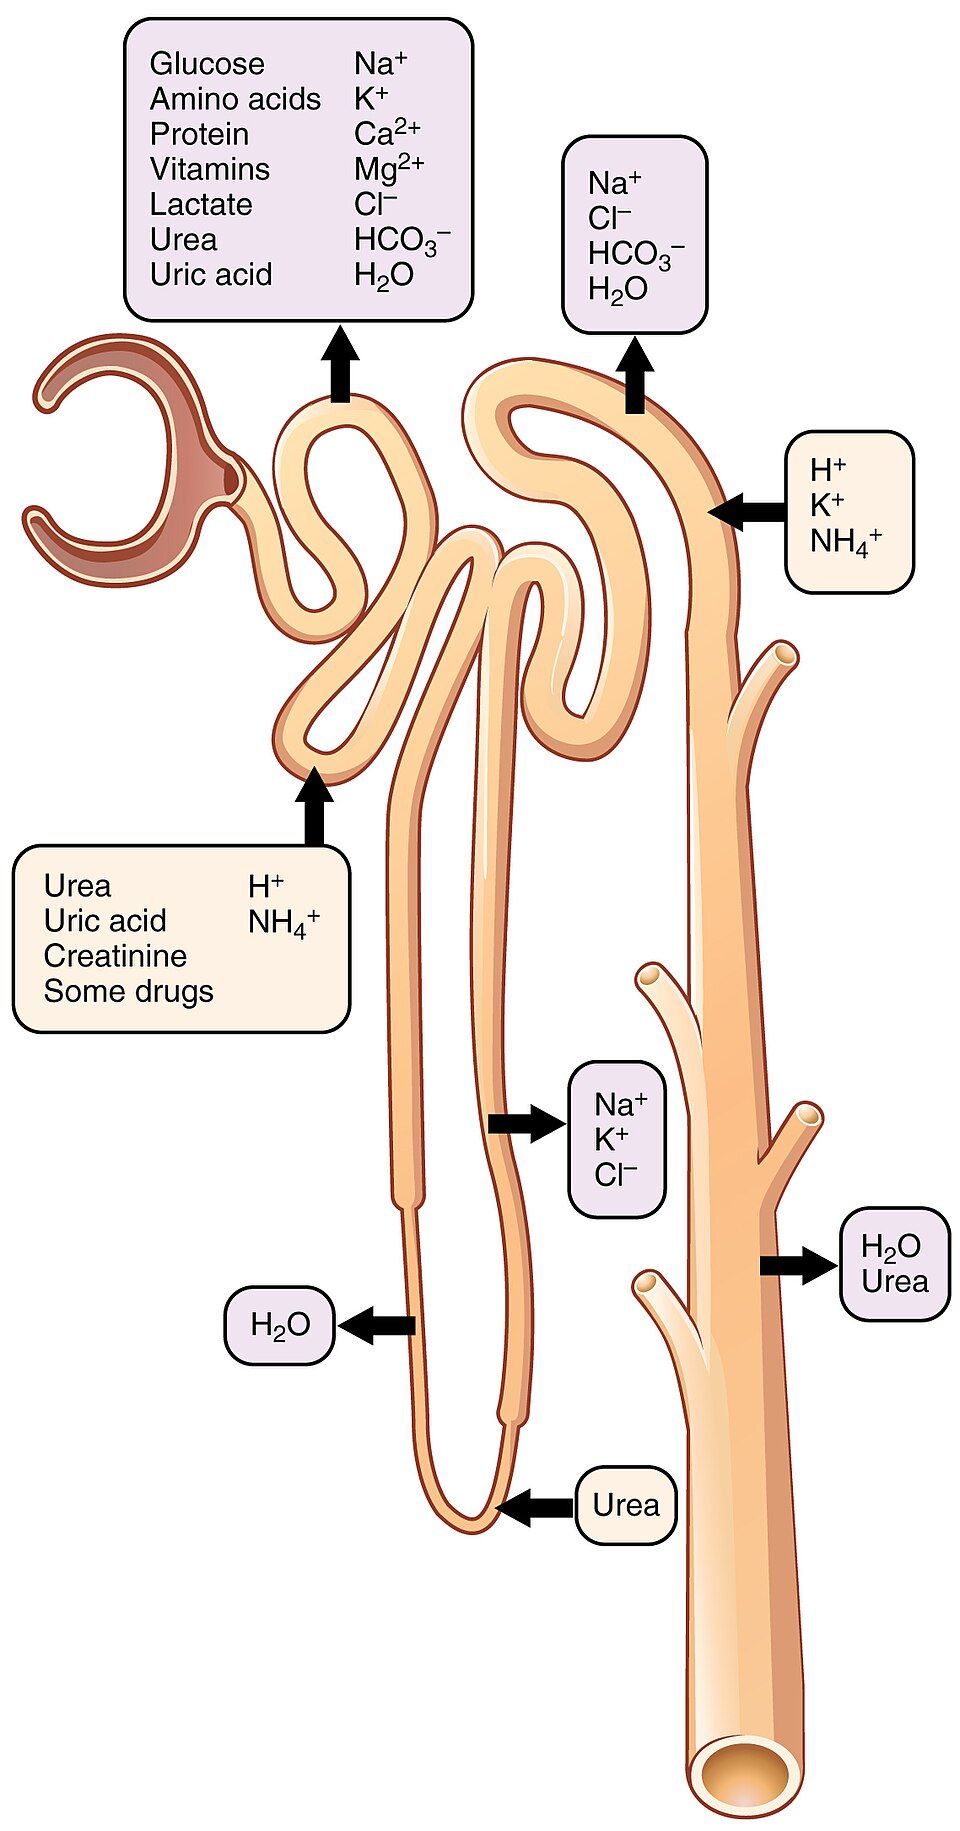
The kidney makes urine using a strategy that seems wasteful but is actually genius: dump almost everything out, then take back what you want. This happens in three steps, in order. First, glomerular filtration pushes a large volume of fluid out of the blood into the tubule. Second, tubular reabsorption reclaims the water and useful solutes, returning them to the blood. Third, tubular secretion adds a few extra wastes and ions from the blood into the tubule for disposal. Whatever remains in the tubule after all three steps is the urine. The genius is control: by filtering a huge amount and then reabsorbing selectively, the kidney can adjust each substance independently.
Step one: glomerular filtration
Filtration is driven by pure pressure. Blood enters the glomerulus under high hydrostatic pressure (thanks to that wide afferent arteriole feeding a narrow efferent one), and that pressure forces fluid across the filtration membrane into the capsule. The rate at which all the glomeruli together produce filtrate is the glomerular filtration rate (GFR) — normally about 125 mL per minute, which adds up to roughly 180 L a day. GFR is a vital sign for the kidney; a falling GFR is the central measure of kidney failure. The kidney guards its GFR fiercely, adjusting the diameter of the afferent and efferent arterioles to keep filtration steady even as blood pressure swings.
Steps two and three: reabsorption and secretion
If filtration were the whole story you would urinate 180 liters a day and die of dehydration in an hour. Reabsorption saves you. The PCT alone reclaims about 65% of the filtered water and sodium, and essentially 100% of the glucose and amino acids — nutrients are too valuable to waste. The loop of Henle builds a salty medulla so that, later, water can be pulled back osmotically. By the time filtrate reaches the collecting duct, only fine adjustments remain. Meanwhile secretion runs the opposite direction, moving substances from the blood into the tubule — hydrogen ions (H⁺) to control pH, excess potassium (K⁺), and many drugs and toxins. Secretion is the kidney's way of clearing things too big or too slow to filter well.
| Process | Direction | Where | What moves |
|---|---|---|---|
| Filtration | Blood → tubule | Renal corpuscle | Water & small solutes (pressure-driven, ~125 mL/min) |
| Reabsorption | Tubule → blood | Whole tubule (mostly PCT) | Water, Na⁺, glucose, amino acids — the useful stuff |
| Secretion | Blood → tubule | PCT, DCT, collecting duct | H⁺, K⁺, drugs, toxins — extra waste |
Step through filtration, reabsorption, and secretion in the interactive below.
- Urine formation has three steps: filtration (blood→tubule), reabsorption (tubule→blood), and secretion (blood→tubule).
- GFR is about 125 mL/min and is the key measure of kidney function; the kidney regulates arteriole diameter to keep it steady.
- The PCT reabsorbs the bulk (~65% of water and Na⁺, ~all glucose); secretion clears H⁺, K⁺, and drugs.
Section 5Hormonal control
Water: antidiuretic hormone
The kidney does not decide alone how much water to keep — the body signals it with hormones, and the most important water hormone is antidiuretic hormone (ADH), also called vasopressin. When you are dehydrated and blood becomes too concentrated, the hypothalamus senses it and the posterior pituitary releases ADH. ADH acts on the collecting duct, inserting water channels called aquaporins into its wall so that water is pulled back into the salty medulla. The result is a small volume of concentrated urine and conserved body water. When you are well hydrated, ADH falls, the channels are removed, water stays in the tubule, and you produce a large volume of dilute urine. Alcohol suppresses ADH — which is why a night of drinking leaves you dehydrated.
Salt and pressure: the renin–angiotensin–aldosterone system
To control blood pressure, the kidney manages sodium — because where sodium goes, water follows, and water is volume, and volume is pressure. The master circuit is the renin–angiotensin–aldosterone system (RAAS). When blood pressure drops, the kidney's granular cells release renin. Renin converts a liver protein into angiotensin I, which an enzyme in the lungs (ACE) converts to angiotensin II. Angiotensin II is a powerful actor: it constricts blood vessels directly (raising pressure at once) and it stimulates the adrenal gland to release aldosterone, which tells the DCT and collecting duct to reabsorb more sodium (and water with it) while dumping potassium. More sodium reabsorbed means more water retained, more blood volume, and higher pressure — a slower but sustained boost.
Letting go: atrial natriuretic peptide
Every regulator needs an opposite. When blood volume runs high, the stretched walls of the heart's atria release atrial natriuretic peptide (ANP), which does the reverse of RAAS: it promotes the loss of sodium and water in the urine, lowering blood volume and pressure. Between ADH tuning water, RAAS raising pressure, and ANP lowering it, the kidney sits at the center of a constant push-and-pull that keeps your blood volume — and therefore your blood pressure — remarkably steady.
| Hormone | Trigger | Effect on the kidney | Net result |
|---|---|---|---|
| ADH (vasopressin) | Concentrated / low-volume blood | Adds aquaporins to collecting duct → reabsorb water | Less, more concentrated urine; water saved |
| Aldosterone | Angiotensin II; high K⁺ | Reabsorb Na⁺ (and water), secrete K⁺ | ↑ blood volume & pressure |
| Renin / angiotensin II | Low blood pressure | Constricts vessels; drives aldosterone release | ↑ blood pressure (fast & slow) |
| ANP | High blood volume (atrial stretch) | Promotes Na⁺ and water excretion | ↓ blood volume & pressure |
Tap each hormone in the interactive to see how it shifts water and salt.
- ADH controls water: it inserts aquaporins in the collecting duct to concentrate urine and conserve water.
- The RAAS controls sodium and pressure: low pressure → renin → angiotensin II → aldosterone → Na⁺ and water reabsorption → higher blood volume and pressure.
- ANP opposes RAAS, shedding Na⁺ and water when blood volume is high; together these hormones stabilize blood pressure.
Section 6Storing and voiding urine
The storage plumbing
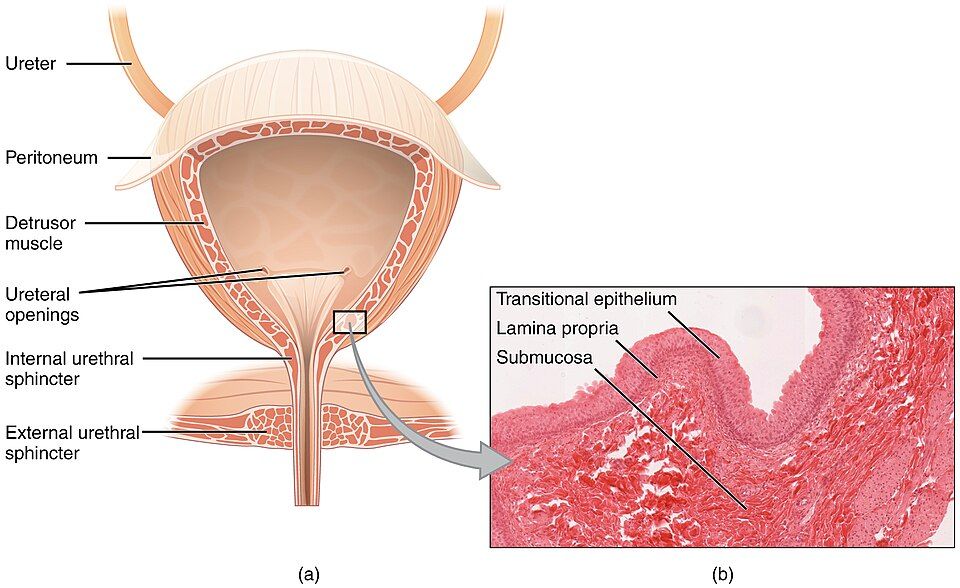
Once urine leaves the kidney it is finished — the rest is transport and storage. The ureters squeeze urine downhill to the bladder with waves of smooth-muscle peristalsis, so urine keeps moving even when you lie down. The urinary bladder is a muscular, expandable bag lined by transitional epithelium that can stretch flat as the bladder fills, and thrown into folds called rugae when it is empty. Its muscular wall is the detrusor muscle, and a smooth triangular region on its floor, the trigone, funnels urine toward the exit. Two gates guard the outlet: an involuntary internal urethral sphincter (smooth muscle, works automatically) and a voluntary external urethral sphincter (skeletal muscle, under your conscious control). The urethra then carries urine out — short in females (about 4 cm) and longer in males (about 20 cm, because it also passes through the penis).
The micturition reflex
Emptying the bladder starts as a simple spinal reflex. As the bladder fills to around 200–400 mL, stretch receptors in the detrusor wall fire and send signals to the sacral region of the spinal cord. The cord answers with a parasympathetic command that does two things at once: it contracts the detrusor muscle to squeeze the bladder, and it relaxes the internal sphincter to open the first gate. This is the micturition reflex, and in an infant — whose nervous system has not yet learned control — it simply proceeds to the end, and the baby voids.
The voluntary override
What makes you different from an infant is the second gate. The external urethral sphincter is skeletal muscle you can consciously hold shut, and higher brain centers (a control area in the pons, guided by the cortex) can either permit or postpone urination. When the reflex fires but the moment is wrong, your brain keeps the external sphincter contracted and the urge passes — for a while. When you decide it is time, the brain relaxes the external sphincter, the reflex completes, and the bladder empties. Learning this override is exactly what "potty training" teaches, and losing it — through spinal injury, stroke, or age — is what causes many forms of incontinence.
| Step | What happens |
|---|---|
| 1. Fill | Urine collects; the detrusor stretches as volume nears 200–400 mL |
| 2. Sense | Stretch receptors fire and signal the sacral spinal cord |
| 3. Reflex | Parasympathetic output contracts the detrusor and relaxes the internal sphincter |
| 4. Decide | The brain (pons/cortex) holds or releases the external sphincter — the voluntary gate |
| 5. Void | External sphincter relaxes; bladder empties through the urethra |
Fill the bladder and release it in the interactive to watch the reflex play out.
- Ureters move urine by peristalsis; the bladder (detrusor muscle, transitional epithelium, trigone) stores it behind two sphincters.
- The micturition reflex is a sacral spinal reflex: stretch → parasympathetic → detrusor contracts and the internal sphincter opens.
- The external sphincter is skeletal muscle under conscious (pons/cortex) control — the voluntary override that lets you choose when to void.
The chapter in one breath
- The urinary system's four organs — two kidneys, two ureters, one bladder, one urethra — filter blood, balance water and salts, and drain urine; the kidneys also help set blood pressure, red-cell count, and vitamin D.
- A kidney is layered cortex over medulla (pyramids); urine drains papilla → calyces → renal pelvis → ureter, and blood passes through two capillary beds in series.
- The nephron (~1 million per kidney) is the functional unit: a renal corpuscle that filters plus a tubule (PCT → loop of Henle → DCT → collecting duct) that processes.
- Urine forms in three steps — filtration (blood→tubule), reabsorption (tubule→blood), and secretion (blood→tubule); GFR is about 125 mL/min.
- ADH conserves water, the RAAS retains sodium to raise blood pressure, and ANP sheds sodium and water to lower it.
- Urine is stored in the bladder and released by the micturition reflex, with the voluntary external sphincter letting you decide when to void.
- Above all, the kidney is the body's great homeostatic organ — it turns the idea of a stable internal environment into a working machine.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Aldosterone
- An adrenal hormone that tells the distal tubule and collecting duct to reabsorb sodium (and water with it) while secreting potassium, raising blood volume and pressure.
- Antidiuretic hormone (ADH)
- A posterior-pituitary hormone that inserts aquaporins into the collecting duct so water is reabsorbed, producing concentrated urine and conserving body water.
- Calyx
- A cup-shaped chamber that collects urine dripping from a renal papilla; minor calyces merge into major calyces, which drain into the renal pelvis.
- Collecting duct
- The final tubule segment, shared by many nephrons, where ADH controls the last of water reabsorption before urine reaches the papilla.
- Detrusor muscle
- The smooth muscle of the bladder wall that contracts to expel urine during the micturition reflex.
- Glomerular filtration rate (GFR)
- The volume of filtrate all the glomeruli produce per minute (normally ~125 mL/min); the central measure of kidney function.
- Glomerulus
- The high-pressure ball of capillaries inside the renal corpuscle where blood is filtered into the glomerular capsule.
- Juxtaglomerular apparatus
- The junction where a nephron's ascending limb meets its afferent arteriole; its cells sense salt and pressure and release renin.
- Loop of Henle
- The hairpin tubule segment (descending and ascending limbs) that builds the salty medullary gradient needed to concentrate urine.
- Micturition
- Urination — the emptying of the bladder, triggered by a spinal stretch reflex and permitted or delayed by voluntary control.
- Nephron
- The microscopic functional unit of the kidney (~1 million per kidney), consisting of a renal corpuscle and a renal tubule.
- Podocyte
- An octopus-shaped cell of the filtration membrane whose foot processes form narrow filtration slits that help hold back proteins.
- Proximal convoluted tubule (PCT)
- The first tubule segment after the corpuscle; site of bulk reabsorption of water, sodium, glucose, and amino acids.
- Reabsorption (tubular)
- The movement of water and useful solutes out of the tubule and back into the blood.
- Renal corpuscle
- The filtering component of the nephron — the glomerulus plus its surrounding glomerular (Bowman's) capsule.
- Renin
- An enzyme released by the kidney when blood pressure falls; it starts the cascade that produces angiotensin II and aldosterone.
- Retroperitoneal
- Positioned behind the peritoneum, against the posterior abdominal wall — the location of the kidneys and ureters.
- Secretion (tubular)
- The movement of wastes and ions (H⁺, K⁺, drugs) out of the blood and into the tubule for disposal.
- Trigone
- The smooth triangular region on the bladder floor, marked by the two ureter openings and the urethral outlet.
- Ureter
- The muscular tube that carries urine from a kidney to the bladder by peristalsis.
- Urethra
- The tube that carries urine from the bladder to the outside; short in females, longer in males.