Joints
Bones give the body its frame, but a frame that could not bend would be a statue. Wherever two bones meet, there is a joint — and joints are where movement is born. In this chapter you will learn the two ways anatomists sort every joint in the body, meet the six shapes of the freely-moving synovial joints, take apart the fluid-filled capsule that lets them glide, and put a name to every motion your body can make. Along the way you will see the single theme that governs all of them: a constant, unavoidable trade-off between how much a joint moves and how stable it stays.
By the end of this chapter you can
- Classify any joint two ways — structurally (fibrous, cartilaginous, synovial) and functionally (synarthrosis, amphiarthrosis, diarthrosis) — and explain how the two schemes line up.
- State the mobility–stability trade-off and predict it from a joint's structure.
- Name the six types of synovial joint, describe the movement each allows, and give a body example of each.
- Label the parts of a synovial joint and explain the three jobs of synovial fluid.
- Perform and name the body movements in their opposite pairs, including the special movements of the forearm, foot, and thumb.
- Distinguish the subtypes of fibrous (suture, syndesmosis, gomphosis) and cartilaginous (synchondrosis, symphysis) joints.
- Describe the structure and signature weakness of the shoulder, hip, knee, and elbow.
- Connect common injuries — sprains, dislocations, torn menisci, arthritis — to the joint structures that fail.
Section 1Two ways to classify a joint
What is a joint, and why do we sort them twice?
A joint (or articulation) is simply any place where two bones — or a bone and cartilage, or a tooth and bone — come together. That is a huge and varied group: the immovable seams of the skull are joints, and so is the wildly mobile shoulder. To make sense of that range, anatomists describe every joint in two independent ways at once, and you should get in the habit of giving both.
The first scheme is structural — it asks what material binds the bones together, and is there a fluid-filled space between them? By that test there are exactly three kinds: fibrous joints, held by dense connective tissue with no cavity; cartilaginous joints, held by cartilage with no cavity; and synovial joints, which have a fluid-filled cavity between the bones. The second scheme is functional — it asks the simpler question how much does it move? A synarthrosis is immovable, an amphiarthrosis is slightly movable, and a diarthrosis is freely movable.
Movement versus stability: the great trade-off
These two schemes are not random — they track each other, because the material that holds a joint together decides how much it can move. Bind two bones with tough fibers and you get a rock-solid but nearly motionless union (fibrous, usually a synarthrosis). Cushion them with cartilage and you get a little give (cartilaginous, usually an amphiarthrosis). Put a slippery fluid-filled gap between them and they can swing freely — but now nothing but ligaments and muscles holds them in place (synovial, always a diarthrosis).
That is the single most important idea in the whole chapter: mobility and stability pull against each other. Every joint in your body sits somewhere on that spectrum, and its design is a compromise chosen for the job it does. The skull needs to protect the brain, so it trades away all movement for maximum stability. The shoulder needs to throw and reach, so it trades away stability for a huge range of motion — which is exactly why it is the joint people dislocate most.
| Functional class | Movement | Usual structure | Example |
|---|---|---|---|
| Synarthrosis | Immovable | Fibrous (some cartilaginous) | Skull sutures; a tooth in its socket |
| Amphiarthrosis | Slightly movable | Cartilaginous (some fibrous) | Pubic symphysis; intervertebral discs |
| Diarthrosis | Freely movable | Synovial | Shoulder, hip, knee, elbow, fingers |
Tap through the classification tree in the interactive and watch how much each joint actually moves.
- Every joint is described twice: structurally (fibrous / cartilaginous / synovial) and functionally (synarthrosis / amphiarthrosis / diarthrosis).
- Structure = the binding material and whether there is a cavity; function = how much it moves.
- The schemes track each other because material dictates motion: fibrous → immovable, cartilaginous → slightly movable, synovial → freely movable.
- The master theme is the mobility–stability trade-off: more movement always costs stability.
Section 2The six synovial joints
Same blueprint, six shapes
All synovial joints share the same fluid-filled design (that is the next section), but the shape of the two bone ends that meet determines how the joint can move. There are six shapes, and each allows a characteristic set of motions. The tidy way to keep them straight is by their axes of movement — the number of directions in which the bones can swing.
A nonaxial joint slides but does not swing. A uniaxial joint moves in one plane, like a door on a hinge. A biaxial joint moves in two planes, and a multiaxial joint moves in all directions and can spin as well. As you go down that list, mobility climbs — and, true to the chapter's theme, stability falls.
| Type | Axes / movement | Where you have one |
|---|---|---|
| Plane (gliding) | Nonaxial — flat surfaces slide back and forth | Intercarpal joints of the wrist; between vertebral facets |
| Hinge | Uniaxial — flexion and extension only | Elbow, knee, joints of the fingers |
| Pivot | Uniaxial — rotation around a single long axis | Atlas–axis (shaking “no”); radius at the elbow |
| Condyloid (ellipsoid) | Biaxial — flexion/extension + abduction/adduction | Knuckles (metacarpophalangeal); wrist |
| Saddle | Biaxial, with a wider range than condyloid | Base of the thumb (first carpometacarpal) |
| Ball-and-socket | Multiaxial — movement in every plane plus rotation | Shoulder and hip |
Reading the shape tells you the move
Once you can picture the shape, the motion follows automatically. A hinge is a convex end sitting in a concave trough, so it can only rock one way — the elbow cannot swing side to side any more than a door can. A ball-and-socket is a rounded head buried in a cup, free to swing in any direction and to spin, which is why the shoulder and hip are the two most mobile joints you own. The saddle joint at the base of your thumb, where each bone is shaped like a rider on a saddle, is what gives humans a truly opposable thumb — the anatomy behind every grip.
Tap each of the six shapes in the interactive to see the motion it allows and where you have one.
- All six synovial types share one design; the shape of the bone ends sets the movement.
- By axes: plane (nonaxial) → hinge and pivot (uniaxial) → condyloid and saddle (biaxial) → ball-and-socket (multiaxial).
- Ball-and-socket (shoulder, hip) is the most mobile; plane joints only glide.
- The saddle joint at the thumb base makes the human grip possible.
Section 3Inside a synovial joint
The essential parts
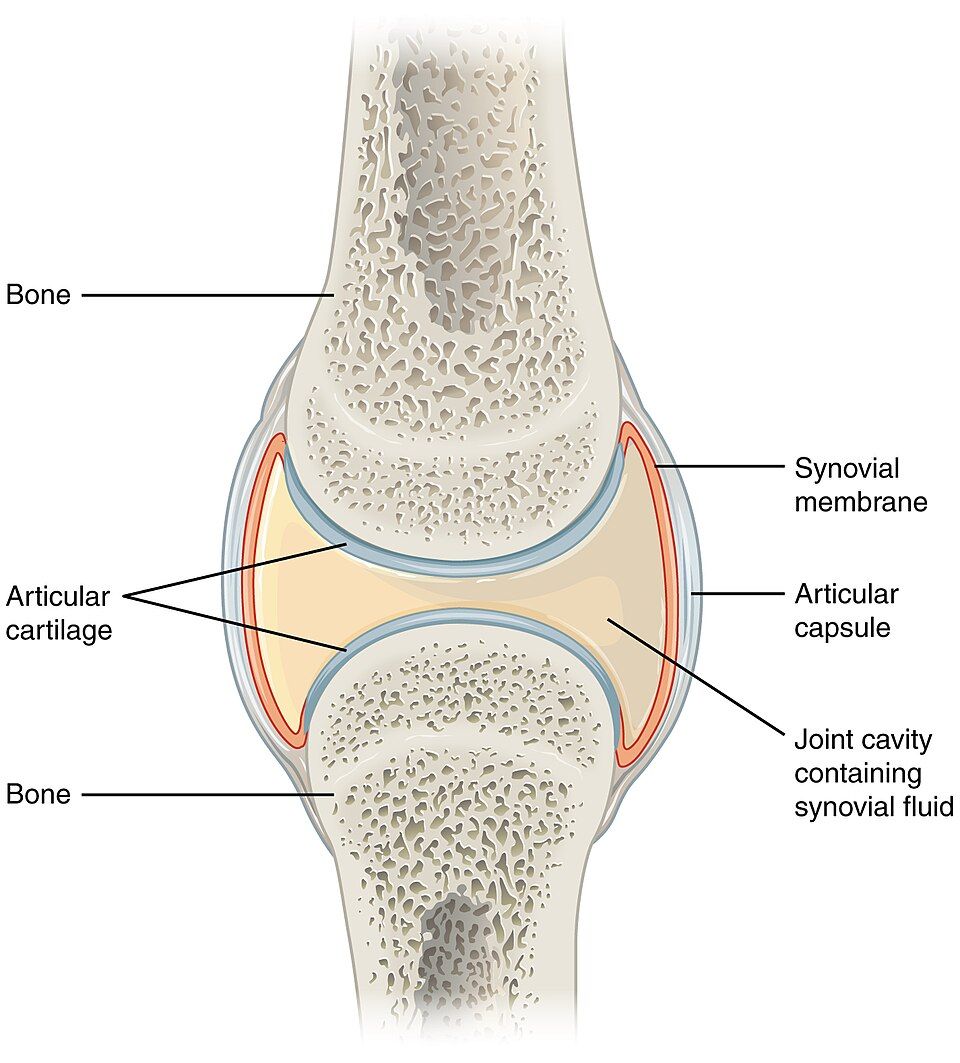
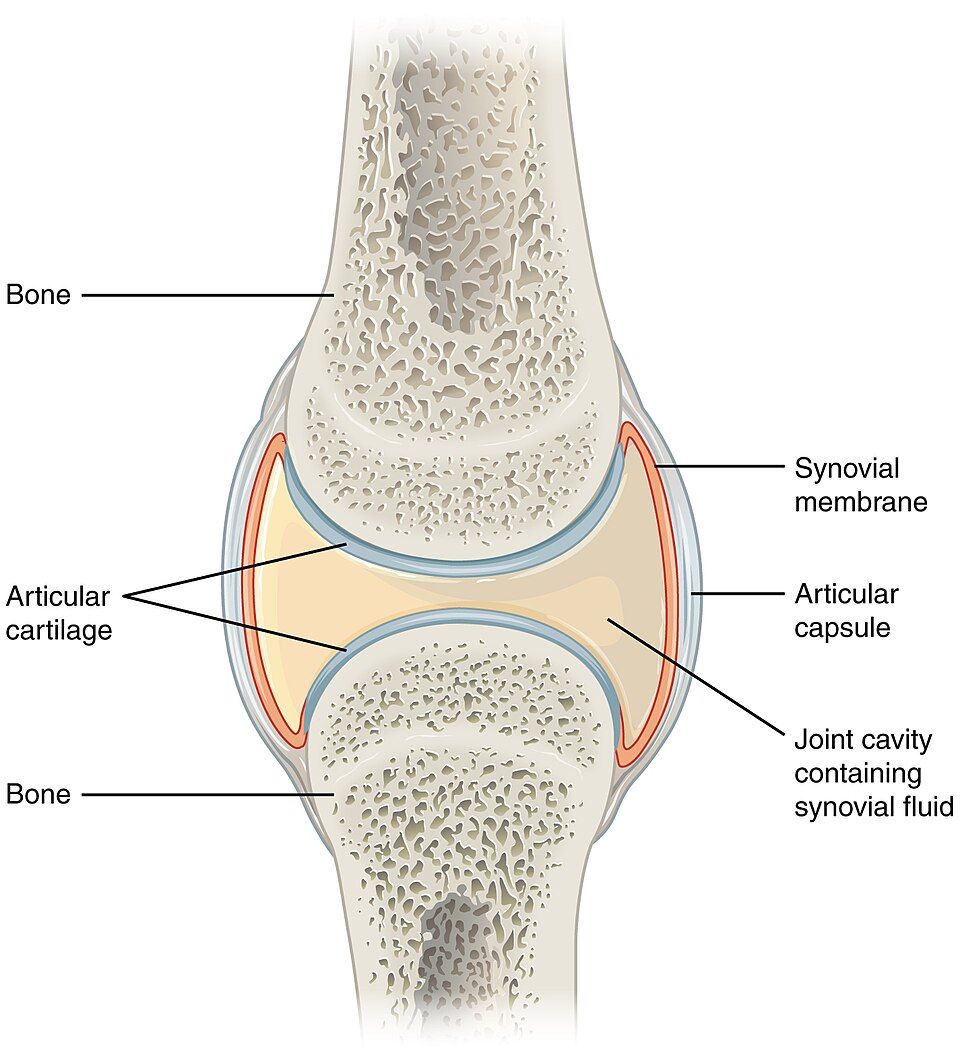
What lets a synovial joint move so freely is a small fluid-filled space, the joint (synovial) cavity, sitting between the two bone ends so they never actually touch. Everything else in the joint exists to protect, feed, and lubricate that gap. Learn these parts and you can label any synovial joint in the body.
Each bone end is capped with a smooth layer of articular cartilage — glassy hyaline cartilage that presents a nearly frictionless surface and cushions the impact of every step. The whole joint is enclosed by a two-layered articular capsule: a tough outer fibrous layer that is continuous with the bones' covering and holds everything together, and a delicate inner synovial membrane that lines the cavity and makes its fluid. That fluid, synovial fluid, fills the cavity like oil in a hinge.
| Structure | What it does |
|---|---|
| Articular cartilage | Hyaline cartilage capping each bone end; a smooth, shock-absorbing surface |
| Joint (synovial) cavity | Fluid-filled space between the bones that allows free movement |
| Articular capsule | Outer fibrous layer for strength; inner synovial membrane that secretes fluid |
| Synovial fluid | Slippery fluid rich in hyaluronic acid — lubricates, feeds cartilage, absorbs shock |
| Ligaments | Bands of dense connective tissue that tie bone to bone and reinforce the capsule |
| Bursae & tendon sheaths | Fluid-filled sacs that cushion where tendons or skin rub over the joint |
Synovial fluid: oil, food, and cushion
Synovial fluid quietly does three jobs at once. First, it lubricates — its hyaluronic acid makes it slick, so the cartilage surfaces glide with less friction than ice on ice. Second, it feeds the cartilage: articular cartilage has no blood supply of its own, so it soaks up oxygen and nutrients from the fluid and dumps waste back into it. Third, it absorbs shock. When you press on a joint, fluid is squeezed out of the compressed cartilage; when you release, it seeps back in — a self-oiling mechanism called weeping lubrication, which is one reason gentle movement is good for aching joints.
Bursae: the joint's shock pads
Around many joints sit small flattened sacs of synovial fluid called bursae, positioned wherever a tendon, ligament, or patch of skin would otherwise chafe against bone. They act like greased cushions. Overuse them — kneeling all day, an overhead throwing motion — and a bursa can become inflamed and painful, the condition called bursitis.
Tap each labeled part in the interactive to see how the capsule, cavity, cartilage, and fluid fit together.
- The defining feature is a fluid-filled joint cavity that keeps the bone ends apart.
- Articular cartilage caps the bones; the articular capsule has a tough fibrous outer layer and a fluid-making synovial membrane inside.
- Synovial fluid does three jobs: lubricate, feed the avascular cartilage, and absorb shock.
- Bursae cushion tendons and skin over the joint; their inflammation is bursitis, and worn cartilage causes osteoarthritis.
Section 4The movements of the body
Motions come in opposite pairs
Every movement a synovial joint produces has a precise name, and the beauty of the system is that the names come in opposing pairs — learn one and you have practically learned its partner. All of them are described from the anatomical position, the same upright, palms-forward pose you met in Chapter 1.
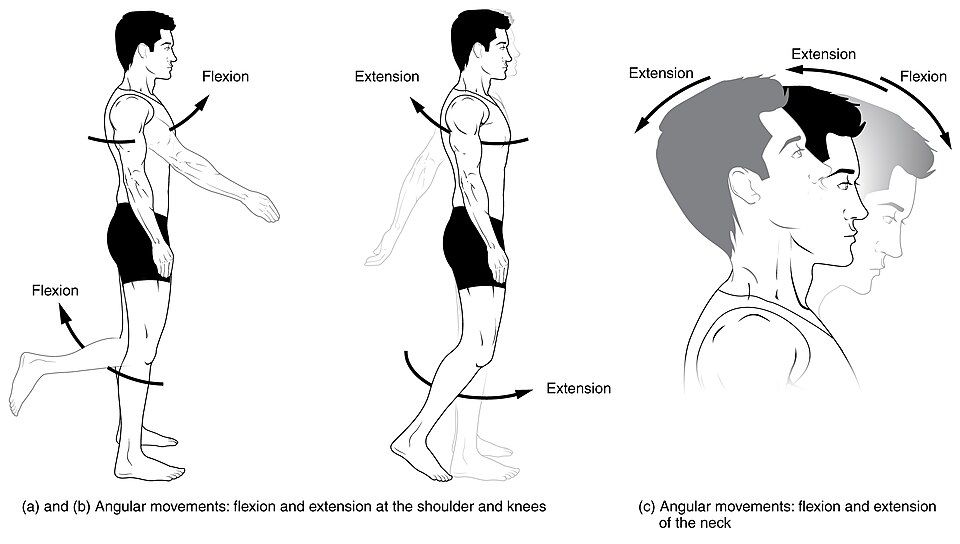
The most common pair is flexion and extension. Flexion decreases the angle at a joint (bending the elbow, curling forward at the waist); extension increases it, straightening the joint back out. Push a joint past its straight position and you get hyperextension — tilting the head back to look at the ceiling. The next pair moves limbs toward or away from the body's midline: abduction carries a limb away from the midline, adduction brings it back toward the midline. Trace a full cone with an outstretched arm and you have circumduction, which strings flexion, abduction, extension, and adduction into one circle. Finally, rotation turns a bone around its own long axis — shaking your head “no” rotates the skull on the spine.
| Movement | What happens | Everyday example |
|---|---|---|
| Flexion / Extension | Decrease / increase the joint angle | Bending vs. straightening the elbow |
| Abduction / Adduction | Away from / toward the midline | Raising the arm out to the side and back down |
| Circumduction | Cone-shaped circling of a limb | Windmilling the whole arm |
| Rotation | Turning a bone on its long axis | Shaking the head “no” |
| Supination / Pronation | Palm turned up / palm turned down | Turning a doorknob back and forth |
| Dorsiflexion / Plantar flexion | Toes toward the shin / toes pointing down | Standing on the heels vs. the toes |
| Inversion / Eversion | Sole turned inward / outward | Rolling the ankle in or out |
| Elevation / Depression | Raising / lowering a part | Shrugging and dropping the shoulders |
The special movements
A handful of joints make motions that need their own names. At the forearm, supination turns the palm up (as if carrying soup) and pronation turns it down. At the ankle, lifting the toes toward the shin is dorsiflexion and pointing them down is plantar flexion, while turning the sole inward is inversion and outward is eversion. The jaw and shoulders can protract (move forward) and retract (move back), and elevate and depress. And the thumb performs opposition, crossing the palm to meet the fingertips — the movement that makes the human hand a tool.
Tap each movement in the interactive to watch a body perform it and see its opposite.
- Movements are named in opposite pairs and defined from the anatomical position.
- Flexion/extension change a joint angle; abduction/adduction move a limb away from/toward the midline; rotation spins a bone on its axis; circumduction is the combined cone.
- Special movements include supination/pronation (forearm), dorsiflexion/plantar flexion and inversion/eversion (foot), elevation/depression and protraction/retraction, and opposition of the thumb.
Section 5Fibrous & cartilaginous joints
Joints without a cavity
Not every joint is built for motion. The two structural classes that lack a synovial cavity — fibrous and cartilaginous joints — trade movement for the stability the body needs at certain spots. They hold bones together with tissue rather than a fluid gap, and most of them fall on the immovable or barely-movable end of the functional scale.
Fibrous joints: bound by tough fibers
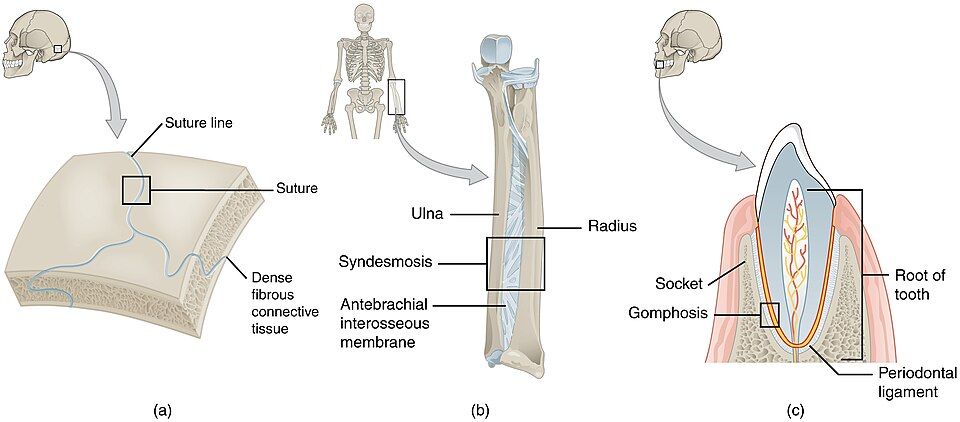
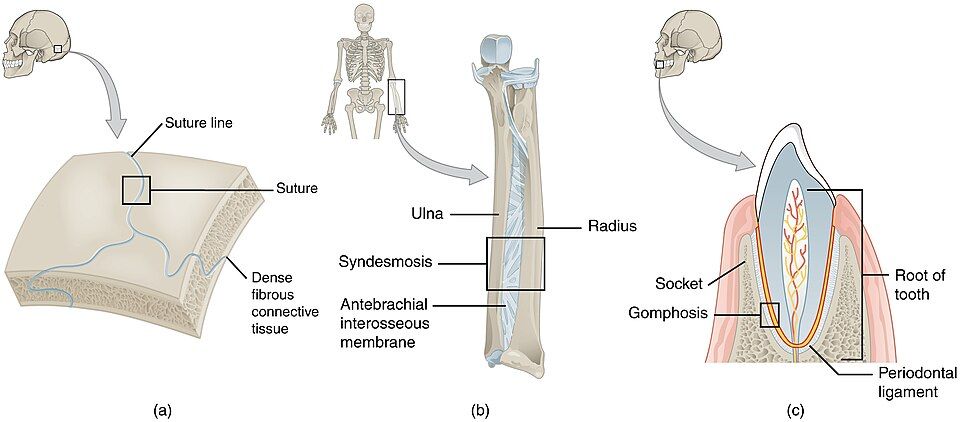
In a fibrous joint, dense fibrous connective tissue stitches the bones directly together. There are three kinds. A suture is the jagged, interlocking seam between the flat bones of the skull, held by a thin layer of fibrous tissue — essentially immovable (a synarthrosis), which is exactly what a case protecting the brain should be. A syndesmosis connects two parallel bones across a broader sheet or cord of fibrous tissue, such as the interosseous membrane between the radius and ulna; it permits a little give (an amphiarthrosis). A gomphosis is the peg-in-socket joint that anchors each tooth in its bony socket, held by the periodontal ligament — also immovable.
Cartilaginous joints: bound by cartilage
In a cartilaginous joint, cartilage does the binding. A synchondrosis uses hyaline cartilage: the classic example is the epiphyseal (growth) plate in a growing long bone, and the joint between the first rib and the sternum — both immovable. A symphysis uses tough, resilient fibrocartilage and allows slight movement (an amphiarthrosis); the pubic symphysis at the front of the pelvis and the intervertebral discs between the vertebrae are the two you must know — the discs let the spine bend a little at each level, which adds up to a flexible back.
| Structural type | Subtype | Binding material | Movement | Example |
|---|---|---|---|---|
| Fibrous | Suture | Thin fibrous tissue | Immovable | Skull seams |
| Syndesmosis | Sheet/cord of fibrous tissue | Slightly movable | Radius–ulna membrane | |
| Gomphosis | Periodontal ligament | Immovable | Tooth in its socket | |
| Cartilaginous | Synchondrosis | Hyaline cartilage | Immovable | Epiphyseal plate; 1st rib to sternum |
| Symphysis | Fibrocartilage | Slightly movable | Pubic symphysis; intervertebral discs |
Tap each fibrous and cartilaginous type in the interactive to see how it trades movement for stability.
- Fibrous and cartilaginous joints have no cavity and favor stability over movement.
- Fibrous subtypes: suture (skull, immovable), syndesmosis (radius–ulna membrane, slightly movable), gomphosis (tooth, immovable).
- Cartilaginous subtypes: synchondrosis (hyaline — growth plate, immovable) and symphysis (fibrocartilage — pubic symphysis and discs, slightly movable).
- A growth plate is a temporary joint that later fuses into a synostosis.
Section 6Four joints that do the work
Shoulder and hip: two ball-and-sockets, two philosophies
The shoulder and the hip are both ball-and-socket joints, yet they answer the mobility–stability question in opposite ways. The shoulder (glenohumeral) joint is built for reach: the ball of the humerus sits against a shallow, saucer-like socket, giving it the widest range of any joint in the body. The price is fragility — the socket barely holds the ball, so muscles of the rotator cuff are its main stabilizers, and it is the joint people dislocate most often. The hip joint makes the opposite bargain: the head of the femur is sunk deep into a true cup, the acetabulum, and ringed by thick ligaments. It gives up some range to become one of the body's most stable joints — it has to be, because it carries your whole body weight with every step.
The knee: a hinge that does more than hinge
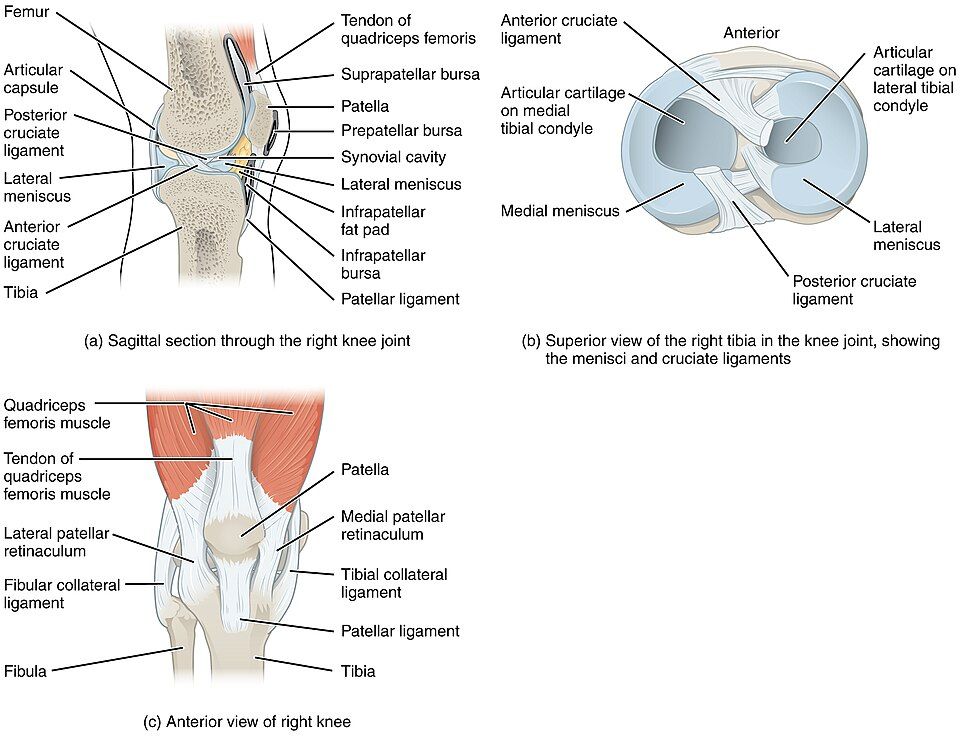
The knee is the largest and most complex joint in the body. It works mainly as a hinge — flexing and extending the leg — but it also allows a little rotation when bent, which is where trouble starts. Two crescents of fibrocartilage, the menisci, sit on top of the tibia to spread load and cushion the joint, and two crossing ligaments deep inside, the anterior and posterior cruciate ligaments (ACL and PCL), keep the femur and tibia from sliding past each other. A hard twist on a planted foot can tear the ACL and meniscus together — the reason knee injuries end so many athletic seasons.
The elbow: stability by design
The elbow shows what a joint looks like when the body chooses stability. It is a hinge where the humerus and ulna interlock so snugly that the joint moves cleanly in one plane and rarely dislocates. Strong collateral ligaments on each side reinforce it, and a separate pivot at the radius lets the forearm rotate into supination and pronation without loosening the hinge. It is a quiet lesson in the chapter's theme: a joint that gives up range gains a durability the shoulder can only envy.
| Joint | Type | Main stabilizers | Signature injury |
|---|---|---|---|
| Shoulder (glenohumeral) | Ball-and-socket | Rotator-cuff muscles (shallow socket) | Dislocation; rotator-cuff tear |
| Hip | Ball-and-socket | Deep socket + thick ligaments | Fracture (often with age) |
| Knee | Hinge (+ slight rotation) | Cruciate ligaments, menisci, collaterals | ACL / meniscus tear |
| Elbow | Hinge (+ pivot) | Bony interlock + collateral ligaments | Dislocation (uncommon) |
Tap each of the four joints in the interactive to compare how each balances mobility against stability.
- The shoulder maximizes mobility with a shallow socket — and pays for it as the most-dislocated joint, stabilized by the rotator cuff.
- The hip is a deep, ligament-bound ball-and-socket built for stable weight-bearing.
- The knee is a complex hinge stabilized by menisci and cruciate ligaments; twisting injuries tear them.
- The elbow trades range for a snug, durable hinge, with a pivot for forearm rotation.
The chapter in one breath
- A joint is any place two bones meet; every joint is classified structurally (fibrous, cartilaginous, synovial) and functionally (synarthrosis, amphiarthrosis, diarthrosis).
- The two schemes align because material dictates motion, and the master theme is the mobility–stability trade-off: more movement always costs stability.
- Synovial joints are the freely-movable ones and come in six shapes — plane, hinge, pivot, condyloid, saddle, and ball-and-socket — from nonaxial to multiaxial.
- A synovial joint centers on a fluid-filled cavity between cartilage-capped bones inside an articular capsule; synovial fluid lubricates, feeds the avascular cartilage, and absorbs shock.
- Movements are named in opposite pairs — flexion/extension, abduction/adduction, rotation, circumduction — plus special motions like supination/pronation and opposition.
- Fibrous (suture, syndesmosis, gomphosis) and cartilaginous (synchondrosis, symphysis) joints have no cavity and favor stability; some, like the growth plate, later fuse into bone.
- The shoulder, hip, knee, and elbow each strike the mobility–stability balance differently, which predicts how each one gets injured.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Abduction
- Movement of a limb away from the body's midline (raising the arm out to the side).
- Adduction
- Movement of a limb toward the midline, back to the body.
- Amphiarthrosis
- A functionally slightly-movable joint (for example, the pubic symphysis or an intervertebral disc).
- Articular capsule
- The two-layered sleeve enclosing a synovial joint — a tough fibrous outer layer and a fluid-secreting synovial membrane inside.
- Articular cartilage
- The smooth hyaline cartilage that caps each bone end in a synovial joint, reducing friction and absorbing shock.
- Bursa
- A small fluid-filled sac that cushions where a tendon, ligament, or skin rubs over bone; its inflammation is bursitis.
- Circumduction
- Cone-shaped movement of a limb that combines flexion, abduction, extension, and adduction in sequence.
- Diarthrosis
- A functionally freely-movable joint; all synovial joints are diarthroses.
- Fibrous joint
- A joint in which dense fibrous connective tissue directly binds the bones, with no cavity (suture, syndesmosis, gomphosis).
- Flexion
- A movement that decreases the angle at a joint, such as bending the elbow.
- Gomphosis
- The immovable peg-in-socket fibrous joint anchoring a tooth in its bony socket via the periodontal ligament.
- Ligament
- A band of dense connective tissue that connects bone to bone and reinforces a joint.
- Meniscus
- A crescent of fibrocartilage (as in the knee) that sits between bone ends to spread load and improve fit.
- Suture
- An immovable fibrous joint forming the interlocking seams between the flat bones of the skull.
- Symphysis
- A slightly-movable cartilaginous joint united by fibrocartilage (pubic symphysis, intervertebral discs).
- Synarthrosis
- A functionally immovable joint (for example, a skull suture).
- Synchondrosis
- A cartilaginous joint united by hyaline cartilage, such as the epiphyseal growth plate.
- Syndesmosis
- A fibrous joint in which a sheet or cord of connective tissue links two bones, allowing slight movement (radius–ulna).
- Synovial fluid
- The slippery, hyaluronic-acid–rich fluid filling a joint cavity; it lubricates, nourishes cartilage, and cushions.
- Synovial joint
- A freely-movable joint with a fluid-filled cavity between cartilage-capped bones enclosed in a capsule.