Reproductive System Drugs
Almost none of these drugs cure a disease. They prevent a pregnancy, permit one, soften a menopause, restart a stalled labor, shrink a prostate, or restore an erection — and every one of them touches something a patient may find intensely private. That makes reproductive pharmacology unusual: the science is demanding and the conversation is delicate, and you have to be good at both at the same time. This chapter walks through the hormones and the drugs that mimic, block, or trick them, and then does what matters most — it names exactly what the nurse watches, teaches, and refuses to let slide. Two of the drugs in this chapter are on the high-alert list, one of them kills people who were given nitroglycerin in a chest-pain workup, and one is dangerous to a pregnant person who merely picks up a broken tablet.
By the end of this chapter you can
- Explain how estrogen and progestin prevent ovulation, and compare combined with progestin-only contraception.
- Identify the patients in whom estrogen-containing contraception is contraindicated because of clot risk, and teach the ACHES warning signs.
- Describe the role of hormone replacement therapy, why a uterus requires added progestin, and what the boxed warnings say.
- Explain how clomiphene induces ovulation and which adverse effect means stop the drug and call.
- Titrate and monitor oxytocin safely, recognize tachysystole, and state the emergency response.
- Compare tocolytics and describe magnesium sulfate monitoring and its antidote.
- Teach testosterone safety (including transfer risk) and explain why PDE-5 inhibitors plus nitrates can be fatal.
- Contrast alpha-1 blockers and 5-alpha reductase inhibitors in BPH, including onset, PSA effects, and pregnancy handling precautions.
Section 1Female hormones and contraception
The two hormones behind almost everything in this section
Estrogen (the body's main one is estradiol) builds: it thickens the endometrium in the first half of the cycle, maintains bone density, keeps vaginal tissue plump and lubricated, and shapes the lipid panel favorably. Progesterone stabilizes: after ovulation it converts that proliferating endometrium into a quiet, secretory lining ready to receive an embryo, thickens cervical mucus into a plug, and calms uterine muscle. When progesterone falls, the lining sheds — that withdrawal is a period.
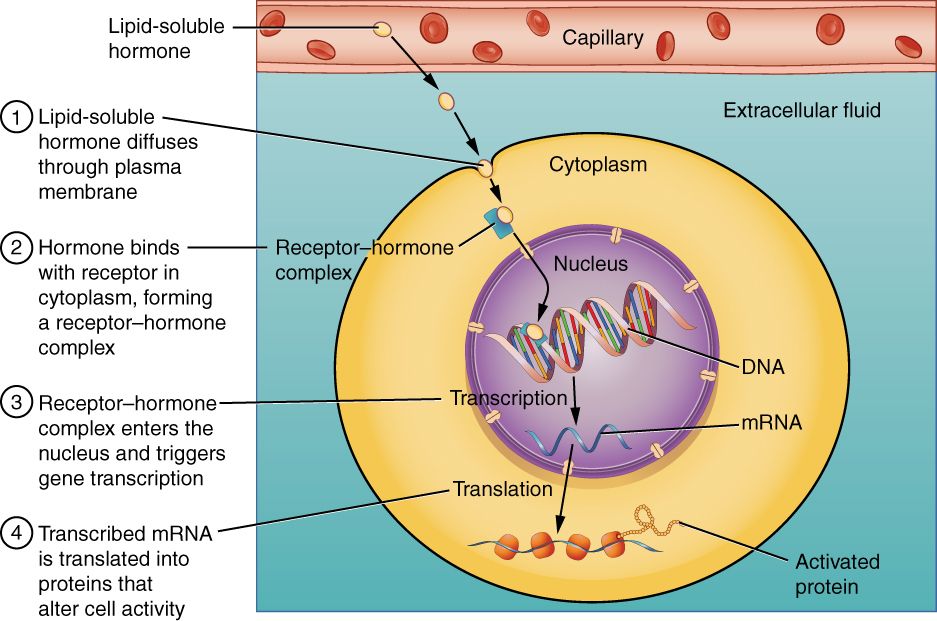
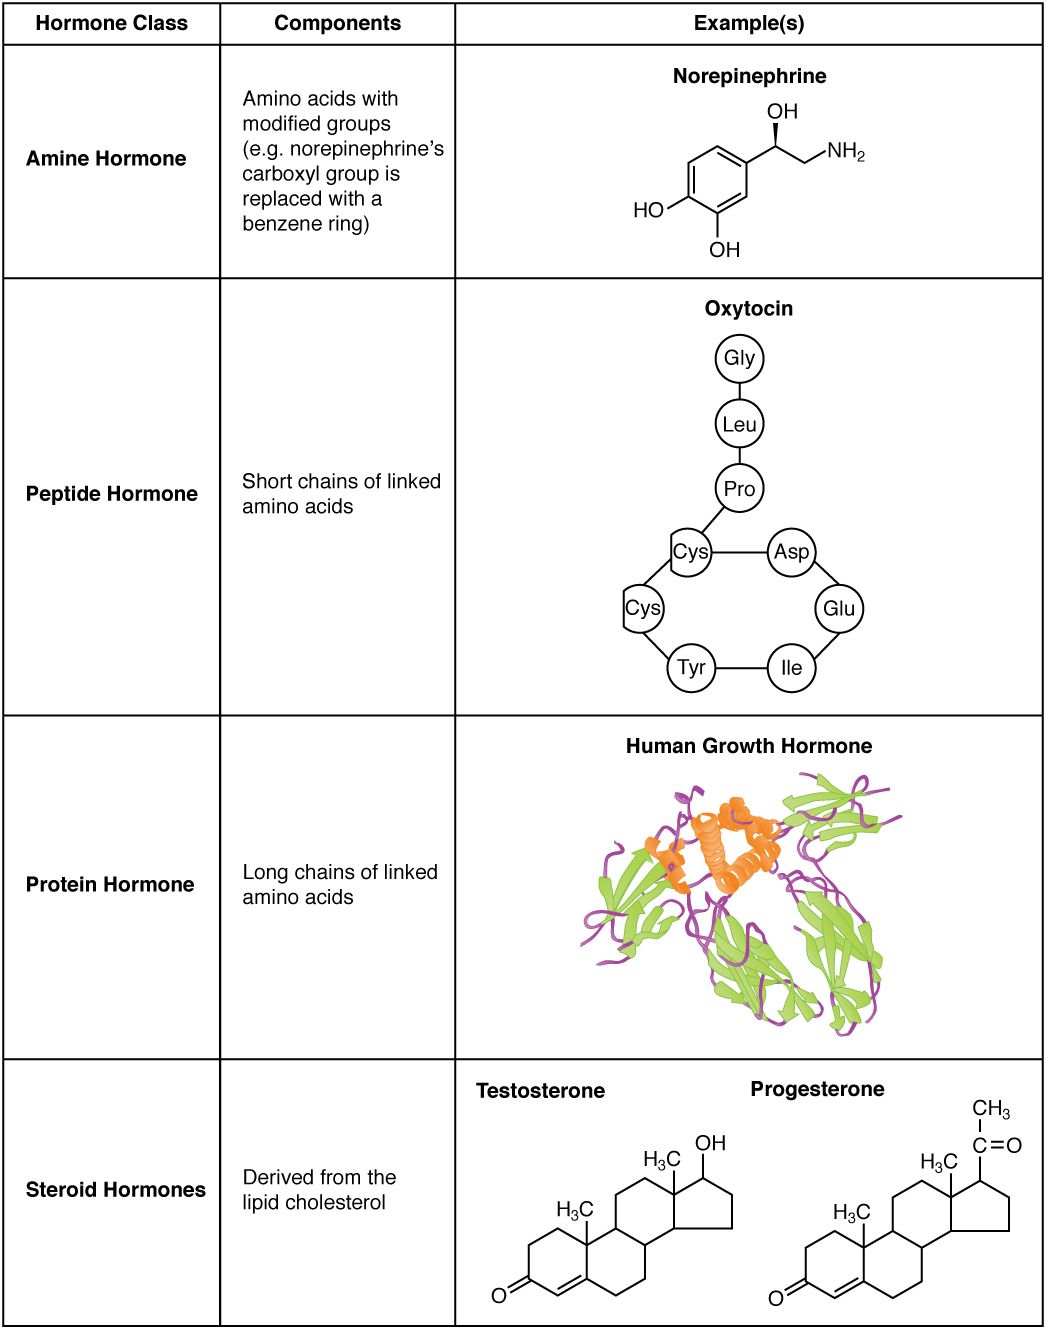
Both are steroid hormones, which explains a great deal of their pharmacology. Being lipid-soluble, they diffuse straight through the cell membrane and bind receptors inside the cell that then act on DNA. Effects therefore take days to build and days to fade — nobody feels a birth control pill work. It also explains why they are given orally at all: a synthetic tweak (adding an ethinyl group to make ethinyl estradiol) protects the molecule from first-pass destruction in the liver. That same liver pass is where the trouble starts, because the liver responds to oral estrogen by making more clotting factors.
How contraception actually works
A combined hormonal contraceptive contains a synthetic estrogen (almost always ethinyl estradiol) plus a progestin (norethindrone, levonorgestrel, norgestimate, drospirenone, and others). Steady hormone levels feed back on the hypothalamus and pituitary and flatten the mid-cycle LH surge. No surge, no ovulation. The progestin adds two backup layers: it thickens cervical mucus so sperm cannot swim through, and it thins the endometrium so implantation is unlikely. The estrogen's other job is unglamorous but important — it stabilizes the lining so the patient does not spot constantly.
A progestin-only method drops the estrogen entirely. The classic norethindrone "mini-pill" relies mostly on mucus and endometrial effects and suppresses ovulation only inconsistently, which is why it has an unforgiving three-hour window — more than three hours late is a missed dose, take it and use backup for 48 hours. A newer drospirenone-only pill has a friendlier 24-hour window. The injection, implant, and hormonal IUD are progestin-only too, and because the patient cannot forget them daily, they are far more effective in real use.
| Method | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| Combined oral pill | Ethinyl estradiol + norethindrone / levonorgestrel | Blocks the LH surge; thickens mucus; thins endometrium | Contains estrogen — screen for clot risk; teach ACHES; same time daily |
| Transdermal patch | Norelgestromin + ethinyl estradiol | Weekly patch ×3, then a patch-free week | Higher estrogen exposure than pills — greater VTE risk; less effective at higher body weight; rotate sites, never the breast |
| Vaginal ring | Etonogestrel + ethinyl estradiol | In 3 weeks, out 1 week (or a 1-year reusable ring) | Still estrogen — same contraindications; may be out up to 3 h; no refrigeration hysteria, just teach the schedule |
| Progestin-only pill | Norethindrone 0.35 mg | Mucus + endometrium; inconsistent ovulation block | 3-hour window. Safe when estrogen is not — breastfeeding, migraine with aura, VTE history |
| Injection | Medroxyprogesterone acetate (DMPA) IM/SubQ every 13 weeks | Reliably suppresses ovulation | Boxed warning: bone mineral density loss with prolonged use — calcium, vitamin D, weight-bearing exercise; return delayed up to 10–18 months |
| Implant | Etonogestrel, up to 5 years, subdermal upper arm | Most effective reversible method | Duration was extended from 3 to 5 years — confirm the removal date against current labeling. Irregular bleeding is the top reason for removal — say so before insertion, not after |
| Hormonal IUD | Levonorgestrel, 3–8 years | Local progestin; often stops periods entirely | Teach string checks; sudden severe pelvic pain or a positive pregnancy test needs same-day evaluation (ectopic) |
| Emergency contraception | Levonorgestrel 1.5 mg (OTC); ulipristal 30 mg (Rx); copper IUD | Delays or blocks ovulation; copper IUD is most effective | Not an abortifacient — it will not end an established pregnancy. Sooner is better; efficacy of levonorgestrel drops at higher body weight |
Clot risk, and the conversations that flow from it
This is the part of the chapter that saves lives. Oral estrogen passes the liver and pushes it to make more procoagulant factors while lowering some natural anticoagulants. The net result is roughly a three- to fourfold rise in venous thromboembolism risk — still a small absolute number in a healthy young person (and lower than the clot risk of pregnancy itself, which is worth saying out loud to a frightened patient), but not small at all once another risk factor stacks on top.
Estrogen-containing methods are contraindicated in a patient who smokes and is 35 or older, who has migraine with aura at any age, who has had a VTE or has a known thrombophilia, who has uncontrolled hypertension, who is less than 21 days postpartum, who has active breast cancer, who has lupus with antiphospholipid antibodies, or who has vascular complications of diabetes. Notice how many of these are things you learn only by asking. "Do your headaches come with flashing lights, zigzag lines, or a blind spot before the pain starts?" is a question that changes a prescription. For nearly all of these patients a progestin-only method is the answer, because it does not carry the estrogen clot risk. The one exception worth memorizing: current breast cancer contraindicates progestin-only methods too — the tumor may be hormone-responsive, so that patient needs a nonhormonal method (copper IUD, barrier, or sterilization), not a switch to the mini-pill.
Teach the ACHES warning signs and make the patient repeat them back: Abdominal pain (severe), Chest pain or shortness of breath, Headache (severe, sudden, or new with neuro symptoms), Eye problems (vision loss, blurring), Severe leg pain or swelling, especially one calf. Any of these means stop the pill and be seen today.
One more teaching point that gets mangled constantly: most antibiotics do not reduce contraceptive efficacy. The real offenders are strong CYP3A4 inducers — rifampin and rifabutin, carbamazepine, phenytoin, phenobarbital, primidone, higher-dose topiramate, some HIV protease inhibitors, and St. John's wort. They speed hormone metabolism and can drop levels below the contraceptive threshold. Ask about herbals by name; patients rarely volunteer them.
Hormone therapy at menopause
When the ovaries retire, estrogen falls and some people are miserable: hot flashes, night sweats, sleep destruction, vaginal dryness and painful sex (now called genitourinary syndrome of menopause), and accelerating bone loss. Menopausal hormone therapy is the most effective treatment for vasomotor symptoms that exists, and it is also the drug class the Women's Health Initiative made everyone afraid of. The honest modern position sits between the extremes: for a symptomatic patient under 60 or within 10 years of menopause with no contraindications, benefits generally outweigh risks; started later, the arithmetic flips.
The single rule you must never forget: a patient with a uterus needs a progestin. Unopposed estrogen drives the endometrium to proliferate without ever shedding, and that is a straight road to endometrial hyperplasia and cancer. If the uterus has been removed, estrogen alone is appropriate and actually carries a better risk profile. Systemic estrogen carries boxed warnings for endometrial cancer, cardiovascular events including stroke and VTE, probable dementia when started in older women, and (with added progestin) breast cancer. Give the lowest effective dose for the shortest reasonable time, and revisit the decision annually.
For a patient whose only complaint is vaginal dryness or dyspareunia, low-dose vaginal estrogen (cream, tablet, or ring) is a different animal: systemic absorption is minimal, it does not carry the same warnings in practice, and it usually does not require a progestin. Teach that it takes several weeks and that stopping means the symptoms return.
- Combined contraceptives work by flattening the LH surge (no ovulation), plus thick mucus and a thin endometrium.
- Estrogen raises clot risk — contraindicated with smoking at 35+, migraine with aura, VTE history, uncontrolled hypertension, early postpartum; use a progestin-only method instead.
- Teach ACHES; teach that CYP3A4 inducers (rifampin, several anticonvulsants, St. John's wort) — not ordinary antibiotics — can cause failure.
- In hormone therapy, a uterus means a progestin; DMPA's boxed warning is bone loss.
Section 2Fertility and pregnancy drugs
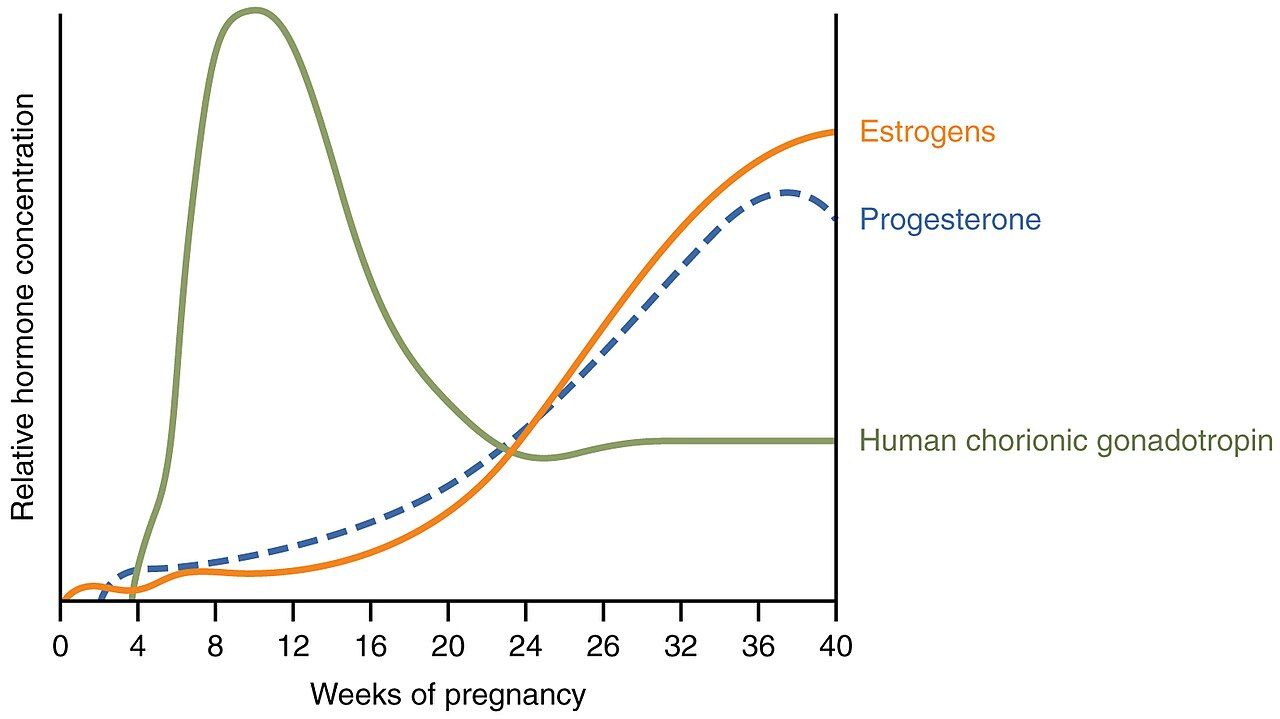
Making ovulation happen: clomiphene and its relatives
Clomiphene citrate is a lovely piece of pharmacologic trickery. It is a selective estrogen receptor modulator that blocks estrogen receptors in the hypothalamus. The hypothalamus, deprived of the estrogen signal it uses to know that estrogen exists, concludes that levels are low and increases GnRH pulses. The pituitary answers with more FSH and LH, follicles grow, and ovulation follows. It is usually taken for five days early in the cycle (commonly days 5 through 9), with ovulation expected roughly 5 to 10 days after the last tablet — timing the patient needs, because the drug does nothing if nobody knows when to try.
The adverse effects follow logically from "temporary chemical estrogen deficiency plus stimulated ovaries": hot flashes, mood swings, breast tenderness, abdominal bloating, and ovarian enlargement. Two matter more. Visual disturbances — blurring, floaters, light flashes, afterimages — mean stop the drug and report immediately; they are usually reversible but not always. And clomiphene raises the chance of multiple gestation to roughly 5 to 10 percent (mostly twins), which is a real conversation, not a footnote. Letrozole, an aromatase inhibitor borrowed from oncology, has quietly become first-line for ovulation induction in polycystic ovary syndrome — higher live-birth rates and fewer multiples than clomiphene.
When those fail, injectable gonadotropins (menotropins, follitropin alfa) stimulate the ovary directly and an hCG trigger finishes maturation and releases the egg. Their signature danger is ovarian hyperstimulation syndrome: ovaries swell, capillaries leak, and fluid pours into the abdomen and chest. Teach the patient to call for rapid weight gain (more than about 2 pounds a day), abdominal distension, severe pain, nausea and vomiting, decreased urine output, or shortness of breath. Severe OHSS is a hospitalization with a genuine thrombosis risk, not a bad week.
Oxytocin: the drug that demands a nurse
Oxytocin binds receptors on uterine smooth muscle and makes it contract. Receptor density climbs steeply toward term, which is why the same dose that does nothing at 20 weeks can hyperstimulate at 40. It is a high-alert medication — the kind where an error is more likely to cause serious harm — and it earns that label honestly, because there is no antidote and no way to un-ring the bell of a contraction that has already compressed the cord.
Give it as a dilute secondary (piggyback) infusion into a mainline IV, always on a programmable pump, connected at the port closest to the patient so it can be shut off instantly with minimal drug still in the line. Doses are ordered in milliunits per minute and titrated up slowly against contraction response. Postpartum, the goal flips: a much larger dose runs to clamp a boggy uterus down and stop atony-driven hemorrhage.
What you watch: contraction frequency, duration, intensity, and resting tone, plus the fetal heart rate pattern. Tachysystole means more than five contractions in 10 minutes averaged over 30 minutes — and if it comes with a nonreassuring FHR pattern, act. The sequence to have memorized: stop the oxytocin, reposition to left lateral, give an IV fluid bolus, give oxygen if indicated, notify the provider, and anticipate a tocolytic such as terbutaline to relax the uterus. Oxytocin also resembles ADH structurally, so prolonged high-dose infusions with hypotonic fluid can cause water intoxication — watch intake and output, headache, confusion, and falling sodium.
| Class | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| Ovulation inducer (SERM) | Clomiphene citrate | Blocks hypothalamic estrogen receptors, raising FSH/LH | Visual changes = stop and report. Counsel on multiples and OHSS |
| Ovulation inducer (aromatase inhibitor) | Letrozole | Lowers estrogen synthesis, raising FSH — first-line in PCOS | Fewer multiples than clomiphene; still monitor for OHSS |
| Uterotonic (posterior pituitary) | Oxytocin | Contracts uterine smooth muscle; induces/augments labor; controls postpartum atony | HIGH ALERT. Pump + piggyback at the closest port. Tachysystole (>5/10 min) → stop the infusion, left lateral, fluids, O₂, notify. Watch for water intoxication |
| Uterotonic (ergot) | Methylergonovine | Sustained uterine contraction for postpartum hemorrhage | Check the BP first — contraindicated in hypertension and preeclampsia (severe vasoconstriction) |
| Uterotonic (prostaglandin) | Carboprost tromethamine | Powerful contraction for refractory atony | Contraindicated in asthma (bronchospasm). Expect fever, diarrhea, vomiting — premedicate |
| Cervical ripening / uterotonic | Misoprostol | Softens the cervix; also contracts the uterus | Do not use for ripening with a prior cesarean scar (rupture risk); teratogenic if given for other indications in pregnancy |
| Tocolytic (CCB) | Nifedipine | Relaxes uterine muscle — usual first-line to delay preterm birth | Watch for maternal hypotension, flushing, headache. Avoid combining with magnesium (neuromuscular blockade) |
| Tocolytic (beta-2 agonist) | Terbutaline | Relaxes the uterus; also rescues tachysystole | Short-term only — FDA warns against prolonged use (maternal cardiac events, death). Watch tachycardia, tremor, pulmonary edema, hyperglycemia |
| Tocolytic (NSAID) | Indomethacin | Inhibits prostaglandins — used briefly before 32 weeks | Fetal ductus arteriosus constriction and oligohydramnios — limit to about 48 hours |
| Anticonvulsant / neuroprotectant | Magnesium sulfate | Seizure prophylaxis in preeclampsia; fetal neuroprotection before 32 weeks | HIGH ALERT. Monitor DTRs, RR ≥12, urine output ≥30 mL/h, LOC. Antidote: calcium gluconate |
| Antenatal corticosteroid | Betamethasone | Accelerates fetal lung maturity (surfactant) | Two IM doses 24 h apart — the benefit is time-dependent, so give on schedule. Watch maternal glucose |
| Immune globulin | Rho(D) immune globulin | Prevents maternal Rh sensitization | At ~28 weeks and within 72 hours of birth of an Rh-positive infant, and after any sensitizing event |
Stopping labor, and the drug that watches the drug
Tocolytics buy time, not term. Nobody stays pregnant to 40 weeks because of nifedipine. The realistic goal is 48 hours — long enough for two doses of betamethasone to mature fetal lungs and long enough to transfer to a facility with a NICU. Framing it that way for a frightened patient is honest and oddly reassuring: we are not failing, we are buying the two days that matter most.
Magnesium sulfate deserves its own paragraph because it is the drug students most often get asked about and most often see. It is not really used as a tocolytic anymore; its jobs are preventing eclamptic seizures and protecting the preterm fetal brain. Magnesium is a CNS depressant, and toxicity climbs a predictable ladder as the level rises: deep tendon reflexes disappear first, then respirations fall, then cardiac conduction fails — bradycardia, heart block, arrest. That order is a gift — it means checking reflexes gives you warning long before anything catastrophic. Urine output is not a rung on that ladder; it is the reason the ladder gets climbed. Because magnesium is cleared renally, urine under 30 mL/h means the drug is accumulating, so it is a hold-and-notify parameter in its own right — stop the infusion, tell the provider, and get a magnesium level, before reflexes or respirations are lost. Keep calcium gluconate at the bedside; 1 gram IV displaces magnesium and reverses it, and it is reserved for respiratory depression or cardiac toxicity, not for oliguria alone.
- Clomiphene blocks hypothalamic estrogen receptors → more FSH/LH → ovulation; visual disturbances mean stop the drug; counsel on multiples and OHSS.
- Oxytocin is high-alert: pump, piggyback, milliunits/min, continuous contraction and FHR monitoring.
- Tachysystole is >5 contractions/10 min — stop the infusion, left lateral, fluids, oxygen, notify, consider terbutaline.
- Magnesium sulfate: watch DTRs, RR, urine output, LOC — reflexes vanish first, then respirations, then cardiac conduction; urine <30 mL/h is a hold-and-notify sign of accumulation, and calcium gluconate is the antidote for respiratory or cardiac toxicity.
Section 3Male hormones and ED drugs
Testosterone: replacement, not enhancement
Testosterone is made mostly by the Leydig cells of the testes under LH control. It builds muscle and bone, drives libido and spermatogenesis, and produces the secondary sex characteristics. Give it as a drug and it is a Schedule III controlled substance in the United States, because it is widely misused for physique and performance.
The legitimate indication is confirmed hypogonadism — symptoms plus at least two low morning total testosterone levels — not "feeling tired at fifty." That distinction matters clinically, not moralistically: replacement in a man with normal testosterone offers no benefit while delivering the full adverse-effect profile and shutting down his own production.
Plain oral testosterone fails at the first pass through the liver, and the older 17-alpha-alkylated androgens that survived it were hepatotoxic — which is why the routes are creative. (Newer oral testosterone undecanoate capsules get around this by absorbing through the lymphatics rather than the portal vein; they must be taken with food and carry a boxed warning for blood pressure elevation.) Topical gels carry a boxed warning for secondary exposure — the drug transfers by skin contact and has virilized children and partners who simply hugged the patient. Teach it every single time: apply to shoulders, upper arms, or abdomen per the product, wash your hands immediately, let it dry, cover the site with clothing, and wash the area before skin-to-skin contact. Intramuscular cypionate or enanthate runs every 1 to 2 weeks and produces a peak-and-trough mood and energy roller coaster patients notice. Intramuscular undecanoate lasts about 10 weeks but requires a REMS program with a 30-minute in-office observation because of pulmonary oil microembolism and anaphylaxis. Patches, buccal tablets, nasal gel, and implanted pellets round out the list.
What the nurse monitors is specific and testable. Hematocrit — testosterone stimulates erythropoiesis, and a hematocrit climbing past roughly 54 percent means hold the drug and reassess, because hyperviscosity causes strokes. PSA and prostate exam at baseline and on follow-up; testosterone is contraindicated in known prostate or male breast cancer. Testosterone levels themselves, lipids, blood pressure, and symptoms of worsening sleep apnea. Expect acne, oily skin, edema, mood changes, testicular atrophy, and — the one patients are never told and must be — infertility, because exogenous testosterone suppresses the LH and FSH that drive sperm production. A man trying to conceive should not be on testosterone. It is also contraindicated in pregnancy and can virilize a female fetus.
PDE-5 inhibitors, and the interaction that kills
An erection is a plumbing event with a chemical trigger. Sexual stimulation releases nitric oxide in the corpus cavernosum; NO raises cGMP; cGMP relaxes arterial smooth muscle; blood floods in and compresses the outflow veins. The enzyme phosphodiesterase type 5 degrades cGMP and ends the event. PDE-5 inhibitors — sildenafil, tadalafil, vardenafil, avanafil — block that enzyme so cGMP persists and the erection is firmer and lasts. Critically, they amplify a signal, they do not create one: without sexual stimulation and NO release, nothing happens. Patients who expect an automatic result are disappointed and stop the drug, so say it plainly.
Now the part that must never be fumbled. Nitrates — nitroglycerin, isosorbide mononitrate or dinitrate, and the recreational inhaled "poppers" (amyl or butyl nitrite) — work by donating nitric oxide. Combine a drug that floods the system with NO and a drug that prevents cGMP breakdown, and you get profound, prolonged, refractory hypotension that does not respond well to fluids or pressors. People have died. This is an absolute contraindication, not a caution.
The scenario to burn in: a middle-aged man arrives with chest pain. The reflex is sublingual nitroglycerin. Ask about PDE-5 inhibitors first — and ask in a way that gets an honest answer, privately, without a spouse or an audience. Required nitrate-free intervals before a nitrate may be given: at least 12 hours after avanafil, the shortest-acting of the group; 24 hours after sildenafil or vardenafil; and at least 48 hours after tadalafil, which is much longer-acting. Also ask about poppers, which patients do not think of as medication at all.
| Drug | Onset / duration | Key effect | Nursing alert |
|---|---|---|---|
| Sildenafil | ~30–60 min; ~4–6 h | PDE-5 inhibition; also approved, under a separate name and dose, for pulmonary arterial hypertension | Fatty meals delay onset. Bluish vision tinge (PDE-6 cross-effect). No nitrate for 24 h |
| Tadalafil | ~30–45 min; up to 36 h | Longest acting; also 2.5–5 mg daily for ED and/or BPH symptoms | No nitrate for 48 h — the long tail is the trap. Back pain and myalgia are common |
| Vardenafil | ~30–60 min; ~4–6 h | PDE-5 inhibition | QT prolongation — avoid with class IA/III antiarrhythmics. No nitrate for 24 h |
| Avanafil | ~15–30 min; ~6 h | Fastest onset, shortest acting, more PDE-5 selective | No nitrate for at least 12 h — the shortest hold of the class |
| Alprostadil | Minutes; ~1 h | Prostaglandin E1 — intracavernosal injection or urethral suppository; works without NO | An option when PDE-5 is contraindicated. Teach injection technique and the priapism rule |
| Testosterone | Route-dependent | Androgen replacement in confirmed hypogonadism | Schedule III. Gel transfer boxed warning. Monitor hematocrit, PSA, lipids; causes infertility |
The rest of the safety picture
PDE-5 inhibitors also stack with alpha-1 blockers (many of these patients are on tamsulosin or doxazosin for BPH) — both drop blood pressure, so start at the lowest dose, be sure the alpha blocker is already at a stable dose, and separate administration. Strong CYP3A4 inhibitors such as ritonavir, ketoconazole, itraconazole, and clarithromycin raise levels sharply and require dose reduction. Ordinary adverse effects — headache, facial flushing, dyspepsia, nasal congestion — are annoying, not dangerous.
Three things are emergencies, and patients must know them cold. Priapism: an erection lasting more than 4 hours needs the ED, because ischemic tissue becomes permanently fibrotic. NAION: sudden painless vision loss in one eye — stop the drug, go now. Sudden hearing loss, sometimes with tinnitus or dizziness — same rule. Finally, remember that sex is exercise; a man too cardiovascularly fragile to climb two flights of stairs needs a cardiology conversation before an ED prescription, not after.
- Testosterone is Schedule III, for confirmed hypogonadism only; monitor hematocrit (hold near 54%), PSA, lipids; it causes infertility.
- Topical testosterone has a boxed warning for transfer — wash hands, cover the site, wash before contact.
- PDE-5 inhibitors preserve cGMP and require sexual stimulation to work at all.
- Nitrates are absolutely contraindicated: hold 12 h after avanafil, 24 h after sildenafil or vardenafil, 48 h after tadalafil; priapism >4 h, sudden vision loss, or sudden hearing loss are emergencies.
Section 4BPH drugs
Why the prostate is a plumbing problem
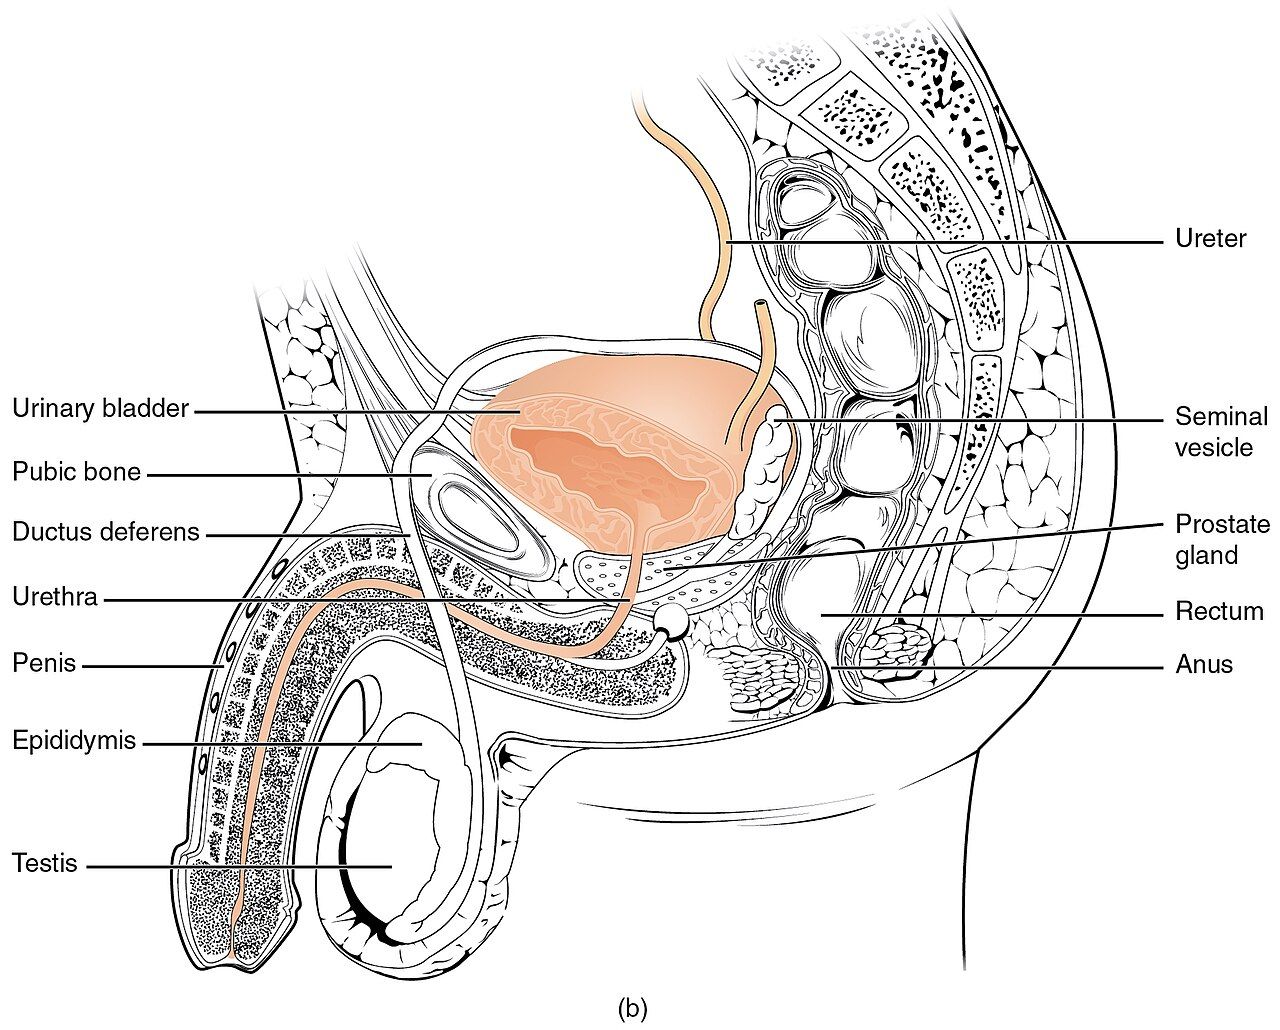
The prostate encircles the urethra like a ring on a garden hose. With age it enlarges — benign prostatic hyperplasia, benign meaning not cancer, not meaning harmless. Symptoms come in two flavors: obstructive (weak stream, hesitancy, dribbling, incomplete emptying) and irritative (frequency, urgency, nocturia). Untreated, it can progress to recurrent UTIs, bladder stones, acute urinary retention, and kidney damage.
Two things narrow that urethra, and each has its own drug class. There is dynamic obstruction — smooth muscle tone in the prostate and bladder neck, held tight by alpha-1 adrenergic receptors — and static obstruction, the sheer bulk of glandular tissue grown under the influence of dihydrotestosterone. Relax the muscle and relief comes in days. Shrink the gland and relief comes in months. That difference in onset is the single most useful thing to teach a patient, because a man who expects finasteride to work by Friday will throw it away by Monday.
Alpha-1 blockers: fast relief, watch the blood pressure
Alpha-1 blockers relax smooth muscle at the bladder neck and prostate, widening the channel. Patients notice improvement within days. They split into two useful groups. The uroselective agents — tamsulosin, silodosin, and alfuzosin (structurally nonselective but clinically uroselective in its extended-release form) — act on the alpha-1A receptors concentrated in the prostate and affect blood pressure comparatively little. The older nonselective agents — doxazosin, terazosin — also block alpha-1B receptors in blood vessels, so they lower blood pressure meaningfully. That is a bonus if the man also has hypertension and a liability if he does not.
The classic teaching point is the first-dose phenomenon: pronounced orthostatic hypotension and possible syncope with the first dose or after a dose increase. Give the first dose at bedtime, teach the patient to rise slowly and sit at the edge of the bed first, and put a fall-risk plan in place for an older adult. (The one exception to bedtime dosing is alfuzosin ER, which is labeled to be taken immediately after the same meal each day — the orthostasis teaching still applies.) Two more counseling points matter. Retrograde ejaculation — semen going backward into the bladder, producing "dry" orgasm and cloudy urine — is common with tamsulosin and silodosin; it is harmless and reversible, but a man who is not warned will assume something is badly wrong. And intraoperative floppy iris syndrome: alpha blockers relax the iris dilator muscle and can make cataract surgery treacherous, sometimes years after the drug is stopped. Any patient on one of these must tell the ophthalmologist before eye surgery. Note what alpha blockers do not do: they do not shrink the prostate, do not slow disease progression, and do not change the PSA.
5-alpha reductase inhibitors: slow, real, and hazardous to a fetus
Inside prostate cells, the enzyme 5-alpha reductase converts testosterone into dihydrotestosterone, a far more potent androgen that is the actual growth signal for prostate tissue. Block that enzyme with finasteride or dutasteride and the gland shrinks by roughly 20 to 25 percent. This is the only class that changes the natural history — it reduces the risk of acute urinary retention and the need for surgery. The cost is patience: 3 to 6 months before meaningful symptom relief, and up to a year for the full effect. It works best in men with genuinely large prostates.
Two facts you cannot afford to get wrong. First, 5-alpha reductase inhibitors cut PSA roughly in half within 6 to 12 months. If nobody accounts for that, a prostate cancer hides behind a reassuring number. The clinical rule of thumb: double the PSA in a man who has been on the drug for at least six months, and investigate any rise from his new baseline. Document the drug next to the lab value.
Second, and this is the safety point of the whole section: these drugs are teratogenic. DHT drives development of the male external genitalia, so blocking it can feminize a male fetus. A pregnant person — or one who might become pregnant — must not handle crushed or broken finasteride tablets or leaking dutasteride capsules, because the drug is absorbed through skin. Intact, coated tablets are safe to handle. Neither drug should be crushed. Men on these drugs should not donate blood, so a pregnant recipient is never transfused with it — and the two deferral periods differ: at least 1 month after the last finasteride dose, but at least 6 months after the last dutasteride dose, because dutasteride's half-life is about 5 weeks and it lingers for months.
| Class | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| Alpha-1 blocker, uroselective | Tamsulosin, silodosin, alfuzosin | Relaxes prostatic/bladder-neck smooth muscle — relief in days; minimal BP effect | Retrograde ejaculation (harmless — warn first). IFIS — tell the eye surgeon. Still teach slow rising. Alfuzosin ER: take immediately after the same meal daily |
| Alpha-1 blocker, nonselective | Doxazosin, terazosin | Same relief, plus a real drop in blood pressure | First-dose syncope — give at bedtime, rise slowly, fall precautions. Additive hypotension with PDE-5 inhibitors and antihypertensives |
| 5-alpha reductase inhibitor | Finasteride, dutasteride | Blocks testosterone → DHT; shrinks the gland ~20–25%; reduces retention and surgery | 3–6 months to work. Halves the PSA — double the value. Teratogenic: no handling of broken tablets by anyone pregnant; no blood donation (1 month after finasteride, 6 months after dutasteride) |
| Combination | Dutasteride + tamsulosin | Fast relief plus long-term shrinkage — best for large glands | Both alert sets apply at once |
| PDE-5 inhibitor | Tadalafil 5 mg daily | Improves BPH symptoms and ED together | Absolute nitrate contraindication still applies — 48 h. Additive hypotension with alpha blockers |
| Antimuscarinic / beta-3 agonist | Oxybutynin, tolterodine; mirabegron | Added for persistent urgency and frequency | Antimuscarinics can precipitate urinary retention — check post-void residual first; watch confusion in older adults |
Finally, the drugs to avoid. Over-the-counter decongestants containing pseudoephedrine or phenylephrine are alpha agonists — they tighten exactly the muscle you are trying to relax and can tip a man into acute retention. First-generation antihistamines such as diphenhydramine add anticholinergic bladder relaxation on top. Every cold-and-flu aisle contains both. Teach the patient to read labels and ask the pharmacist, because "it's just a decongestant" has sent many men to the emergency department with a Foley in their future. Saw palmetto, meanwhile, has repeatedly failed to beat placebo in good trials — do not argue about it, just make sure it is not replacing something that works.
- Alpha-1 blockers relax smooth muscle — relief in days; teach bedtime first dose, slow rising, retrograde ejaculation, and to warn the eye surgeon (IFIS).
- 5-alpha reductase inhibitors block testosterone→DHT and shrink the gland — 3–6 months, and they alone reduce retention and surgery.
- These drugs halve the PSA — double it after six months of therapy or a cancer can hide.
- They are teratogenic: pregnant persons must not handle broken tablets; no blood donation (1 month after finasteride, 6 months after dutasteride). Avoid decongestants and first-generation antihistamines in BPH.
Section 5Reproductive nursing care
Teaching: the drug only works if the conversation does
Reproductive drugs fail for social reasons more than pharmacologic ones. A pill missed because the schedule was never explained. A patch left off because nobody said it survives showering. An injection appointment skipped. A finasteride bottle thrown away at week three. A man who quietly stops tamsulosin because of a symptom he was too embarrassed to name. None of these are the molecule's fault.
So build the visit deliberately. Get privacy first — not the hallway, not with a partner or a parent in the room unless the patient explicitly wants them there. Ask permission before the sensitive questions and explain why you need the answer: "I need to ask about your sexual health because it changes which medication is safe for you — is now a good time?" Use plain words and let the patient use theirs; "does the semen come out?" beats "have you experienced retrograde ejaculation." Do not moralize about sexual activity, gender, number of partners, or substance use — a patient who feels judged withholds the popper history, and that history is the one that stops you from giving nitroglycerin. Finish with teach-back: not "any questions?" but "tell me what you'll do if you miss two pills."
The teaching points that carry the most weight, per class:
- Combined contraception — same time daily; missed-pill rules and 7 days of backup; ACHES; disclose smoking honestly; name your herbals; nausea fades in 2–3 months; spotting is common early and is not failure. It does not protect against sexually transmitted infection — condoms still matter.
- DMPA — the 13-week return date is not a suggestion; calcium, vitamin D, weight-bearing exercise for bone protection; fertility may take 10–18 months to return, so it is a poor choice if pregnancy is planned soon.
- Hormone therapy — a uterus means a progestin; report any postmenopausal bleeding, new leg swelling, chest pain, or neuro symptoms; this is a decision revisited yearly, not a lifetime prescription.
- Clomiphene — the timing is the therapy; stop and call for visual changes; call for rapid weight gain, bloating, or breathlessness (OHSS); multiples are a real possibility.
- Testosterone — hands washed, site covered, no skin contact until washed; expect infertility; report leg swelling, worsening snoring, or excessive sleepiness; keep the lab appointments, because the hematocrit is the point.
- PDE-5 inhibitors — sexual stimulation is required; no nitrates in any form including poppers; erection over 4 hours, sudden vision loss, or sudden hearing loss means the emergency department; a fatty meal delays sildenafil.
- Alpha blockers — first dose at bedtime; rise slowly; the dry orgasm is expected and harmless; tell the eye surgeon.
- 5-alpha reductase inhibitors — three to six months before you judge it; nobody pregnant touches a broken tablet; no blood donation (1 month after finasteride, 6 months after dutasteride); remind every clinician who draws your PSA that you take this.
Monitoring: what to measure and when to stop
| Drug | What you monitor | Act when |
|---|---|---|
| Combined contraceptive | Blood pressure, smoking status, migraine character, leg/chest symptoms | Any ACHES sign; new hypertension; aura appears → switch to progestin-only |
| Hormone therapy | Postmenopausal bleeding, breast exam/mammography, BP, VTE symptoms | Any bleeding after menopause — investigate before adjusting the dose |
| DMPA | Injection date, bone risk factors, weight | Reassess prolonged use; reinforce calcium, vitamin D, exercise |
| Clomiphene / gonadotropins | Vision, weight, abdominal girth, urine output, dyspnea | Visual change → stop. Rapid weight gain or breathlessness → evaluate for OHSS today |
| Oxytocin | Contraction frequency, duration, intensity, resting tone; FHR; I&O; sodium; LOC | Tachysystole or nonreassuring FHR → stop the infusion, left lateral, fluids, O₂, notify |
| Magnesium sulfate | DTRs, respiratory rate, urine output, LOC, magnesium level | Reflexes absent or RR <12 → stop and give calcium gluconate. Urine <30 mL/h → stop, notify, check a level — the drug is accumulating (not yet an antidote situation) |
| Terbutaline | Maternal HR, lung sounds, glucose, fetal HR | Maternal HR >120, chest pain, or crackles (pulmonary edema) → stop and notify |
| Methylergonovine | Blood pressure, uterine tone, bleeding | Hold and notify if hypertensive — do not give in preeclampsia |
| Testosterone | Hematocrit, PSA, testosterone level, lipids, BP, sleep apnea symptoms | Hematocrit near/over ~54% → hold; PSA rise → urology |
| PDE-5 inhibitor | Nitrate use (every single time), BP, cardiac capacity, alpha blocker doses | Any nitrate on board → do not give; erection >4 h → ED |
| Alpha-1 blocker | Orthostatic BP, dizziness, falls, urinary stream, post-void residual | Symptomatic orthostasis → hold, notify, fall precautions |
| 5-alpha reductase inhibitor | PSA (doubled), symptom score, mood, sexual function | PSA rising from the new baseline → workup, do not assume the drug |
Safety: the four places this chapter hurts people
High-alert drugs. Oxytocin and magnesium sulfate both sit on the high-alert list, meaning an error carries outsized risk. Treat them accordingly: an independent double-check of the drug, concentration, pump programming, and line at initiation and at every rate change; standardized concentrations; the secondary line into the port nearest the patient; and the antidote (calcium gluconate for magnesium) physically at the bedside, not "on the unit somewhere." Oxytocin has no antidote — your off switch is the whole treatment.
The nitrate question. Build it into every chest-pain assessment, every preoperative history, and every medication reconciliation for an adult male. Ask about ED drugs and about poppers, ask privately, and document the answer with a time. If the patient cannot answer — unconscious, confused — and the family cannot either, treat the ischemia with agents other than nitrates and write down why.
Teratogen handling. Finasteride and dutasteride are absorbed through skin from broken dosage forms. Never crush them. If a staff member who is or may be pregnant is passing them, that is a handling conversation, not a shrug. The same principle covers testosterone gel: an invisible film on a father's shoulder has virilized his toddler.
Confidentiality and dignity. Reproductive information is among the most sensitive in the chart. Do not discuss it in a hallway, at a nursing station, or on a speakerphone. Do not disclose contraception, fertility care, ED treatment, or gender-affirming therapy to family members without the patient's explicit permission. Offer a chaperone for intimate exams and document it. Use the patient's name and pronouns. These are not soft skills layered on top of the pharmacology — they are the mechanism by which you obtain the history that makes the pharmacology safe.
- Oxytocin and magnesium sulfate are high-alert: independent double-check, pump, standardized concentration, antidote at the bedside.
- Ask about nitrates and PDE-5 inhibitors (including poppers) before nitroglycerin — privately, every time, documented.
- Never crush finasteride or dutasteride; pregnant persons must not handle broken forms; testosterone gel transfers by touch.
- Privacy, plain language, non-judgment, and teach-back are what make the history — and therefore the safety — possible.
The chapter in one breath
- Combined contraceptives flatten the LH surge to block ovulation; the estrogen is what raises clot risk, so smokers over 35, migraine with aura, and VTE history get a progestin-only method instead. Teach ACHES.
- CYP3A4 inducers — rifampin, several anticonvulsants, St. John's wort — cause contraceptive failure; ordinary antibiotics do not. In menopausal hormone therapy, a uterus always means added progestin.
- Clomiphene tricks the hypothalamus into raising FSH and LH; visual disturbances mean stop the drug, and OHSS and multiple gestation are the counseling points.
- Oxytocin is high-alert: pump, piggyback, milliunits per minute; tachysystole means stop the infusion first, then left lateral, fluids, oxygen, notify.
- Magnesium sulfate toxicity climbs a predictable ladder — reflexes, then respirations, then cardiac conduction; falling urine output is not a rung but a hold-and-notify sign that the renally cleared drug is accumulating. The antidote for respiratory or cardiac toxicity is calcium gluconate. Tocolytics buy 48 hours for betamethasone, not a term pregnancy.
- Testosterone is Schedule III for confirmed hypogonadism; monitor hematocrit and PSA, expect infertility, and treat gel transfer as a boxed-warning-level teaching point.
- PDE-5 inhibitors plus nitrates equals lethal hypotension — hold nitrates at least 12 hours (avanafil), 24 hours (sildenafil, vardenafil), or 48 hours (tadalafil); priapism over 4 hours is an emergency.
- In BPH, alpha-1 blockers relax and relieve in days (orthostasis, retrograde ejaculation, IFIS), while 5-alpha reductase inhibitors shrink over 3–6 months, halve the PSA, and are teratogenic to handle.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- 5-alpha reductase inhibitor
- A drug (finasteride, dutasteride) that blocks testosterone-to-DHT conversion, shrinking the prostate over 3–6 months; halves the PSA and is teratogenic.
- ACHES
- The warning-sign mnemonic for estrogen-containing contraception: Abdominal pain, Chest pain, Headache, Eye problems, Severe leg pain. Any one means stop the drug and be evaluated.
- Alpha-1 blocker
- A drug that relaxes smooth muscle in the prostate and bladder neck (tamsulosin, doxazosin), relieving BPH symptoms within days without shrinking the gland.
- Benign prostatic hyperplasia (BPH)
- Age-related, non-cancerous enlargement of the prostate that compresses the urethra, producing obstructive and irritative urinary symptoms.
- Combined hormonal contraceptive
- A method containing both an estrogen (usually ethinyl estradiol) and a progestin; works chiefly by suppressing the LH surge.
- Dihydrotestosterone (DHT)
- The potent androgen made from testosterone by 5-alpha reductase; the growth signal for prostate tissue and the target of finasteride and dutasteride.
- Estrogen
- The steroid hormone (chiefly estradiol) that builds the endometrium, maintains bone and vaginal tissue, and — when given orally — raises hepatic clotting factor production.
- First-dose phenomenon
- Marked orthostatic hypotension or syncope after the first dose or a dose increase of an alpha-1 blocker; prevented by bedtime dosing and slow rising.
- Genitourinary syndrome of menopause
- Vaginal dryness, irritation, painful sex, and urinary symptoms from estrogen loss; often best treated with low-dose vaginal estrogen.
- High-alert medication
- A drug that carries a heightened risk of significant harm when used in error — oxytocin and magnesium sulfate are examples requiring independent double-checks.
- Intraoperative floppy iris syndrome (IFIS)
- Iris instability during cataract surgery caused by alpha-1 blockers, sometimes persisting long after the drug is stopped; the eye surgeon must be told.
- Menopausal hormone therapy
- Estrogen (plus a progestin if the uterus is intact) given for vasomotor and genitourinary symptoms of menopause; carries boxed warnings and is reassessed at least yearly.
- NAION
- Nonarteritic anterior ischemic optic neuropathy — sudden painless vision loss reported with PDE-5 inhibitors; stop the drug and seek care immediately.
- Ovarian hyperstimulation syndrome (OHSS)
- A complication of ovulation induction in which enlarged ovaries leak fluid into the abdomen and chest; signs include rapid weight gain, distension, low urine output, and dyspnea.
- Oxytocin
- The posterior pituitary hormone, given as a high-alert IV infusion in milliunits per minute, that contracts uterine smooth muscle to induce or augment labor and control postpartum atony.
- PDE-5 inhibitor
- A drug (sildenafil, tadalafil, vardenafil, avanafil) that blocks cGMP breakdown in the corpus cavernosum, amplifying an erection; absolutely contraindicated with nitrates.
- Priapism
- A prolonged erection lasting more than 4 hours; an emergency, because ischemic tissue becomes permanently fibrotic.
- Progestin
- A synthetic progesterone-like drug (norethindrone, levonorgestrel, drospirenone, medroxyprogesterone) that thickens cervical mucus, thins the endometrium, and protects the uterus from unopposed estrogen.
- Retrograde ejaculation
- Semen passing backward into the bladder rather than out the urethra, common with tamsulosin and silodosin; harmless, reversible, and alarming if not explained in advance.
- Tachysystole
- More than five uterine contractions in 10 minutes averaged over 30 minutes; with oxytocin the first intervention is to stop the infusion.
- Tocolytic
- A drug (nifedipine, terbutaline, indomethacin) given to delay preterm birth, realistically for about 48 hours — long enough for antenatal steroids and transfer.
- Venous thromboembolism (VTE)
- Deep vein thrombosis or pulmonary embolism; the risk that drives nearly every contraindication to estrogen-containing therapy.