Pulmonary
Every cell in your body runs on oxygen. The lungs are where oxygen gets in and carbon dioxide gets out. This chapter follows one breath from the air into the blood and back. You will see why ventilation and perfusion have to match, what happens when airways narrow or a clot lodges, and how to read the story in a patient’s lung sounds.
By the end of this chapter you can
- Explain ventilation, perfusion, and V/Q mismatch (dead space vs shunt).
- Tell chronic bronchitis apart from emphysema in COPD.
- Describe the three problems in asthma, and rescue vs controller inhalers.
- Spot a pulmonary embolism and what sets it up (Virchow’s triad).
- Match lung sounds (crackles, wheezes, stridor) to their causes.
Section 1How breathing works: ventilation, perfusion & V/Q
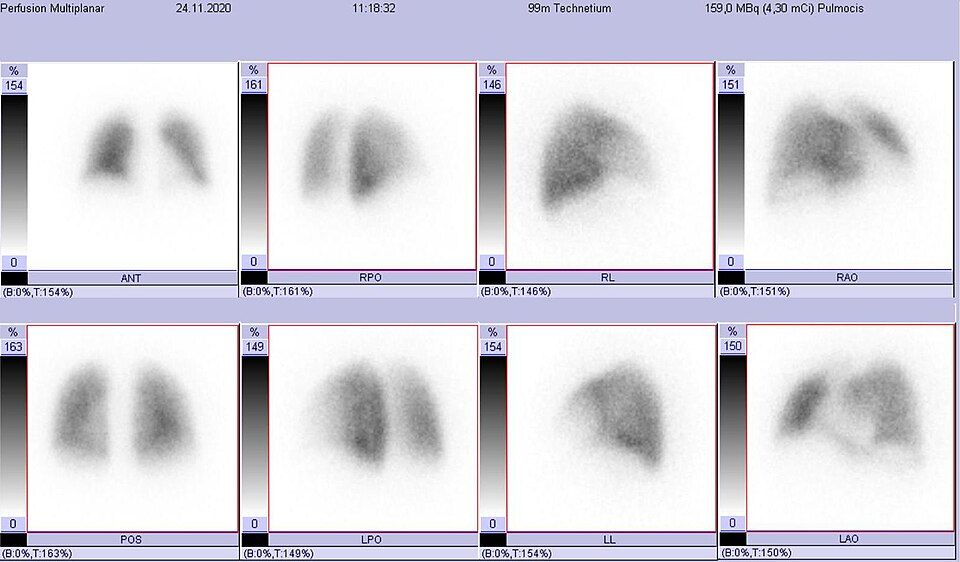
Every breath does two jobs at once, and the two jobs have to line up. Ventilation is air moving in and out of the lungs. It carries fresh oxygen down to the tiny air sacs called alveoli, and it carries carbon dioxide away. Perfusion is blood flowing through the pulmonary capillaries that wrap around those air sacs. Picture a loading dock. Ventilation drops off the packages, which are oxygen. Perfusion is the fleet of trucks that picks them up. If the packages arrive and no trucks come, nothing moves. If the trucks arrive and there are no packages, nothing moves either. Gas exchange needs air and blood in the same place at the same time.
Matching air to blood: the V/Q ratio
The V/Q ratio says how well air and blood line up. V stands for ventilation, and Q stands for perfusion, which is blood flow. In a healthy lung, the whole-lung ratio sits near 0.8. It lands just under 1 because blood flow is a bit greater than airflow. The ratio is not the same in every part of the lung. Gravity pulls blood downward, so the bases (the bottoms) get more blood flow. The apices (the tops) get relatively more air. So the ratio shifts as you move from top to bottom. What matters is balance. When air and blood are close to matched, oxygen crosses into the blood and carbon dioxide is blown off well. When they fall out of balance, you have a V/Q mismatch. It happens in two ways.
Two ways it goes wrong: dead space and shunt
A high V/Q means air arrives with no matching blood flow. The air gets there, but no blood is waiting to pick up the oxygen. That wasted air is called dead space. The classic cause is a pulmonary embolism, a clot that blocks a pulmonary artery. The air sacs fill with air, but the blood truck never shows up.
A low V/Q means blood arrives with no matching air. Blood keeps flowing past air sacs that are not getting fresh air. It returns to the heart still low on oxygen. This is called a shunt. Think of pneumonia filling air sacs with pus. Think of pulmonary edema flooding them with fluid. Think of atelectasis, which means collapsed air sacs. Here is one useful clue. A pure shunt responds poorly to extra oxygen. That oxygen cannot reach blood that is flowing past blocked sacs.
| Feature | Dead space (high V/Q) | Shunt (low V/Q) |
|---|---|---|
| What is missing | Perfusion (blood flow) | Ventilation (air) |
| The picture | Air arrives, no blood to load it | Blood arrives, no fresh air to load |
| Classic cause | Pulmonary embolism | Pneumonia, pulmonary edema, atelectasis |
| Response to oxygen | Usually helps (the open areas still load the extra oxygen) | Poor (the air cannot reach that blood) |
Gas exchange across the alveolar membrane
Air and blood actually meet at the alveolar-capillary membrane. This barrier is amazingly thin, only a few cells thick. Gases cross it by diffusion, which means they drift from high pressure to low pressure. Oxygen is more crowded in the air sac than in the arriving blood, so it moves into the blood. Carbon dioxide is more crowded in the blood, so it moves out into the air sac and gets exhaled. Anything that thickens this membrane slows diffusion down. Fluid, scar tissue, and swelling all do that. Gas exchange then gets worse, even when air and blood both show up.
Hypoxemia vs hypoxia, and how oxygen travels
These two words sound alike, but they mean different things. The difference matters a great deal. Hypoxemia is a low oxygen level in the blood. You see it as a low PaO2 on an arterial blood gas, or a low SpO2 on the pulse oximeter. Hypoxia is low oxygen reaching the tissues. The two often travel together, but not always. Severe anemia is a good example. It can starve the tissues of oxygen while the blood oxygen level (PaO2) still looks normal. There are simply not enough carriers to deliver it.
Those carriers hold the whole system up. About 97 percent of the oxygen in blood rides on hemoglobin inside red blood cells. Only a tiny share dissolves in the plasma. Play with the figure below to watch ventilation, perfusion, and V/Q matching work together.
- Ventilation is air moving in and out. Perfusion is blood flowing past the air sacs. The two must match in the same place at the same time. The normal V/Q ratio is about 0.8.
- Dead space is air with no blood flow (high V/Q). The classic cause is a pulmonary embolism. Shunt is blood flow with no air (low V/Q). Classic causes are pneumonia, edema, and atelectasis.
- Gases cross the thin alveolar-capillary membrane by diffusion, from high pressure to low. A thickened membrane slows oxygen uptake.
- Hypoxemia is low oxygen in the blood. Hypoxia is low oxygen in the tissues. You can have one without the other.
- About 97 percent of oxygen rides on hemoglobin. So delivery depends on the carriers too, not just on the lungs.
Section 2Obstructive disease: COPD

Each breath travels down your windpipe and splits into smaller and smaller tubes. Those tubes are the bronchi and the bronchioles. At the end sit millions of tiny balloon-like sacs called alveoli. Oxygen slips into the blood there, and carbon dioxide slips out. Two things make this work. The airways have to stay open, and the lung tissue has to stay springy. That springiness is called elastic recoil, and it quietly squeezes air back out when you exhale. Breathing out is normally passive and takes no work.
In chronic obstructive pulmonary disease (COPD), that easy exhale falls apart. The airways narrow and the springiness is lost. Air flows in, then gets stuck on the way out. So think of COPD as trouble getting air OUT, not in. Stale air piles up behind the narrowing. That pile-up is called air trapping, and it leaves the lungs over-inflated. This is why patients push air out through pursed lips, and why their exhale drags on so long.
Why air gets trapped
COPD is really two problems that overlap. Most patients have some of each.
Chronic bronchitis is an airway problem. Years of irritation inflame the lining of the bronchi, so the walls swell. The mucus glands grow bigger and pump out thick, sticky secretions. Now the airway is narrowed by swelling and by mucus. The tiny sweeping hairs that clear mucus, called cilia, are damaged too. Mucus sits still and grows bacteria, so infections keep coming back. The clinical definition is a productive cough for at least 3 months in each of 2 years in a row.
Emphysema is a tissue problem. The walls between air sacs break down and merge into fewer, bigger, floppy sacs. That costs surface area for gas exchange. It also costs the elastic recoil that props small airways open and drives the exhale. Without that support, airways collapse as you breathe out and trap even more air.
| Feature | Chronic bronchitis (blue bloater) | Emphysema (pink puffer) |
|---|---|---|
| Core problem | Swollen, mucus-clogged airways | Broken-down air sac walls, lost recoil |
| Classic look | Bluish, often heavy, swollen with fluid | Thin, barrel chest, leaning forward |
| Cough & mucus | Heavy wet cough | Little cough, little sputum |
| Oxygen level | Lower early (hypoxemia, blue tint) | Held closer to normal by fast breathing |
| Breathing style | Wet, congested | Pursed-lip, working hard to exhale |
The nicknames are memory hooks, not real patient types. The blue bloater looks blue and puffy because fluid backs up. The pink puffer stays pinker by breathing fast and hard. When the trapped air makes the chest round and stiff, we call it a barrel chest. That means the chest has grown deeper from front to back (an increased anteroposterior diameter).
The leading cause
Cigarette smoking is by far the number-one cause. Smoke keeps the airways inflamed. It also floods the lung with enzymes that chew up the walls of the air sacs, and it overwhelms the body’s natural guard against those enzymes. Over years that drives both the bronchitis and the emphysema. A smaller group inherits alpha-1 antitrypsin deficiency. That takes the natural guard away, so emphysema can show up even in people who never smoked. Quitting smoking is the single most powerful way to slow the disease.
When the strain reaches the heart
Low oxygen in the lungs for a long time makes lung blood vessels clamp down. That response is called hypoxic pulmonary vasoconstriction. It raises the pressure in the pulmonary arteries, which is pulmonary hypertension. Now the right side of the heart has to pump against that pressure. Over time the right ventricle gets bigger and then fails, and that is cor pulmonale. You see bulging neck veins, a large liver, and peripheral edema. That swelling is part of why the blue bloater looks puffy.
You can explore how a clogged airway and a broken-down air sac differ in the figure below.
- COPD is trouble getting air OUT. Narrowed airways and lost elastic recoil cause air trapping and a long, labored exhale.
- Chronic bronchitis is swollen, mucus-filled airways, with a wet cough (blue bloater). Emphysema is broken-down air sac walls with lost recoil (barrel chest, pink puffer).
- Smoking is the leading cause, and quitting slows the disease more than anything else.
- Low oxygen over time plus pulmonary hypertension can strain the right heart into cor pulmonale, with edema and bulging neck veins (JVD).
- Give oxygen with care, usually to a target SpO2 of 88 to 92 percent. Very high-flow oxygen can make CO2 retention worse.
Section 3Asthma
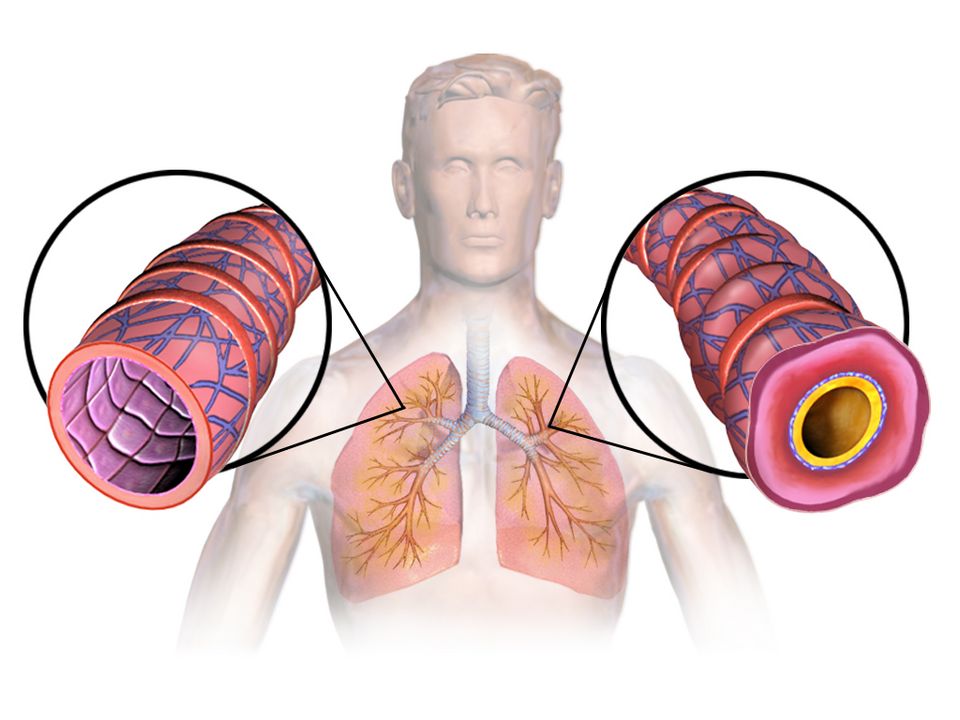
Take a slow breath in. Air rushes down your windpipe and splits into two bronchi. Those branch again and again into ever-smaller bronchioles, and then reach the tiny sacs where gas exchange happens. A thin layer of smooth muscle wraps those small airways, and a moist lining coats the inside. They are built to stay open and springy, so air moves with almost no effort. In a healthy lung, breathing out is passive and quiet. The airways stay wide and the air just leaves.
In asthma, those small airways turn hyperreactive, which means they overreact. Things that should be harmless set them off, and the airway narrows. The key word in asthma is reversible obstruction. Emphysema causes fixed damage, but an asthma attack can open back up with treatment, or even on its own. While it is happening, though, air gets trapped and the person has to fight to move it.
Three problems at once
An asthma attack is not one thing going wrong. Three processes hit the airway together, which is why it can get worse so fast.
- Bronchospasm. The ring of smooth muscle around the bronchioles squeezes tight. That narrows the tube itself. This is the fast part, and it is what rescue inhalers go after.
- Airway inflammation. The lining swells up with fluid (edema) as immune cells release histamine, leukotrienes, and other chemical messengers. A swollen wall makes a narrow tube even tighter.
- Mucus. Irritated airways pour out thick mucus, which plugs the passage from the inside.
So you have muscle squeeze, plus swollen walls, plus mucus plugs. The same amount of air now has a much smaller opening to move through. Use the figure below to see how bronchospasm and swelling stack up.
What sets it off
Asthma airways are twitchy, and each person has their own triggers. Common ones are allergens like pollen, dust mites, pet dander, and mold. Others are exercise, which is worse in dry air, cold air, and respiratory infections such as a common cold. Cigarette smoke, strong smells, and air pollution set it off too. Part of good asthma care is helping your patient name and dodge their own triggers.
Why it sounds the way it does
Air forced through those narrowed airways makes a high-pitched musical whistle. That sound is a wheeze, and you classically hear it on expiration. One part of this is easy to get backwards. Getting air in is easier than getting it out. Breathing in pulls the airways wider. Breathing out lets them narrow a little. So air gets trapped, and you see prolonged expiration, a long and labored breath out, as your patient fights to empty the lungs.
The two inhalers
Patients often carry two inhalers that do very different jobs. Mixing them up is dangerous.
| Feature | Rescue (reliever) | Controller (preventer) |
|---|---|---|
| Drug class | Short-acting beta-agonist (SABA), such as albuterol | Inhaled corticosteroid (ICS) |
| What it does | Relaxes airway muscle fast (bronchodilation) | Calms the swelling in the airway over time |
| When to use | During an attack, for quick relief | Every day, even on good days |
| Onset | Minutes | Days to weeks of steady use |
The rescue inhaler breaks the muscle spasm in minutes, but it does nothing for the swelling. The controller quiets the swelling, but it is useless in a sudden attack. A patient who reaches for the rescue inhaler more and more often is telling you the asthma is not controlled.
When it will not break: status asthmaticus
Status asthmaticus is a severe, drawn-out attack that does not answer the usual rescue treatment. It is a medical emergency. The patient wears out, gas exchange fails, and carbon dioxide climbs. Watch for a silent chest and for neck and shoulder muscles pulling with each breath. Watch the breathing rate rise and then slow down as the patient tires. Look for a bluish color, and for a rising PaCO2 on a blood gas. That rising PaCO2 is dangerous, because a tiring asthma patient should be blowing CO2 off, not holding it in. These patients need aggressive care, and often close monitoring in an intensive care unit.
- Asthma is reversible airway narrowing from three things at once: bronchospasm, inflammation with swelling (edema), and mucus.
- Common triggers are allergens, exercise, cold air, and respiratory infections.
- Expect wheezing and prolonged expiration. A silent chest means almost no air is moving, and that is an emergency sign.
- Rescue SABA inhalers such as albuterol break the spasm fast. Daily controller inhaled corticosteroids treat the swelling, but they do not help an attack in progress.
- Status asthmaticus is a severe attack that standard treatment does not fix. A rising PaCO2 warns that respiratory failure is close.
Section 4Pulmonary embolism
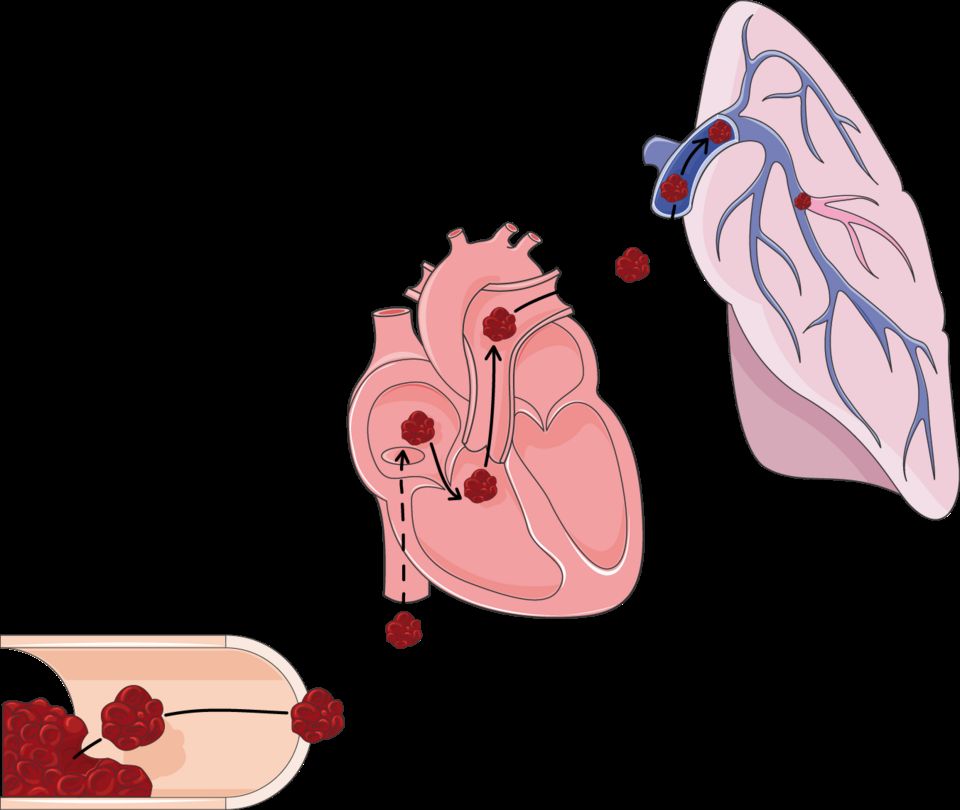
Breathing in is only half the job. Your lungs pull in oxygen, but that oxygen does nothing unless blood flows past the air sacs to pick it up. Normally the right side of your heart pumps blood through the pulmonary arteries into a lacy net of capillaries. Those capillaries wrap around millions of tiny air sacs called alveoli. There, oxygen loads onto red blood cells and carbon dioxide unloads. Air and blood work as partners. A pulmonary embolism (PE) is what happens when a plug in the pipe suddenly breaks that partnership.
What actually goes wrong
A PE is a clot that lodges in a pulmonary artery and blocks blood flow to part of the lung. Most of the time the clot did not form in the lung at all. It usually starts as a deep vein thrombosis (DVT) in a leg vein or a pelvic vein. Then a piece breaks loose. Once it is traveling, we call that clot an embolus. It rides the blood up to the right heart, gets pumped into the lung circulation, and wedges where the vessel gets too narrow to pass. The lung tissue past the clot still gets air. No blood arrives to pick up its oxygen.
Why the clot forms: Virchow’s triad
Clots do not show up at random. In the 1800s, Rudolf Virchow named three conditions that set the stage. We still use his triad to spot patients at risk:
- Venous stasis, which means blood pooling and sitting still. Long flights, bed rest, surgery, not moving, and heart failure all slow the flow. Clotting factors build up instead of washing away.
- Hypercoagulability, which means blood that clots too easily. Pregnancy, birth control with estrogen, cancer, dehydration, and inherited clotting disorders all tip the balance toward clotting.
- Endothelial injury, which means damage to the inner lining of the vessel. Trauma, surgery, central lines, and inflammation expose surfaces that start a clot.
When two or three of these overlap, a DVT gets much more likely. And a DVT is the seed of most PEs.
Dead space: ventilation without perfusion
Here is the core problem in one phrase: ventilation without perfusion. That blocked part of the lung still fills with air, but no blood flows past it. So the air is wasted. Air with no blood flow is called alveolar dead space. Gas exchange simply cannot happen there. Meanwhile the blood that should have gone to that area gets shoved into the vessels that are still open. The mismatch drops the oxygen level in the blood, which is hypoxemia. This is why a PE is a true medical emergency. A large clot can crash the oxygen level and strain the right heart within minutes.
Why the signs happen
PE symptoms come on suddenly. Each one traces straight back to the mechanism:
- Sudden dyspnea, which means shortness of breath, along with hypoxia. A chunk of lung can no longer load oxygen onto blood, so the body runs short and cries out for more air.
- Pleuritic chest pain, a sharp pain that gets worse with a deep breath. The oxygen-starved lung tissue and its lining, the pleura, get irritated and inflamed.
- Tachycardia, which means a fast heart rate. The heart speeds up to push blood past the blockage and to make up for the falling oxygen. You may also see fast breathing, worry, and a cough.
| Feature | Normal lung unit | Pulmonary embolism |
|---|---|---|
| Air in alveoli | Yes | Yes (still gets air) |
| Blood flow past alveoli | Yes | No (the clot blocks it) |
| Gas exchange | Works well | Fails in the blocked zone |
| Result | Normal oxygen | Dead space, hypoxemia |
Explore the figure below to see a clot stuck in a pulmonary artery, and how it cuts off blood flow to the lung past it.
- A PE is usually a leg DVT that broke loose, traveled as an embolus, and lodged in a pulmonary artery. It blocks blood flow to part of the lung.
- Virchow’s triad sets up the clot in the first place: stasis, hypercoagulability, and endothelial injury. Prevention targets all three.
- The blocked lung gets air but no blood flow. That makes alveolar dead space, which is ventilation without perfusion, and the blood oxygen drops.
- Classic signs are sudden dyspnea, pleuritic chest pain, tachycardia, and hypoxia. Each one comes from lost gas exchange and the body trying to make up for it.
- PE is a medical emergency. A swollen, tender calf is an early clue that a DVT could break loose.
Section 5Pneumonia & respiratory infections
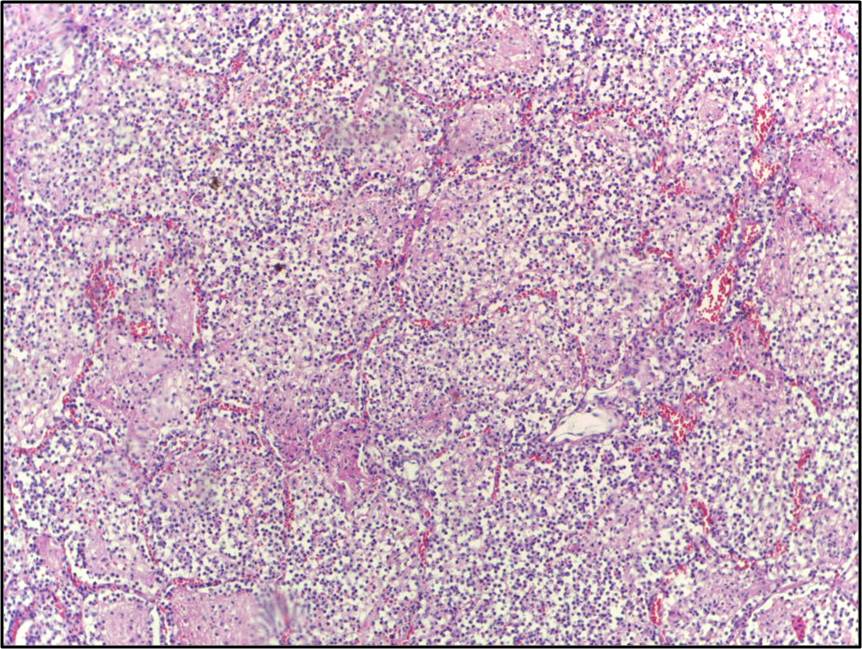
Each breath you take travels down to about 300 million tiny air sacs called alveoli. A fine mesh of capillaries wraps around each sac. Their walls are amazingly thin, roughly one cell thick. That lets oxygen slip across into the blood while carbon dioxide slips out. This trade is gas exchange, and it needs those sacs to stay open, dry, and full of air. Pneumonia is what happens when that clean, air-filled space turns into a battleground.
What goes wrong: the alveoli flood
Pneumonia is an infection of the lung tissue itself. Bacteria cause it most often, classically Streptococcus pneumoniae, but viruses and fungi can too. When a germ reaches the air sacs, the immune system rushes in. White blood cells, fluid, and cell debris pour into the sacs and build up pus and inflammatory exudate. Here is the problem. A sac full of fluid and pus cannot hold air. Oxygen crosses a wall of liquid far worse than it crosses air, so gas exchange breaks down. That is why the hallmark of pneumonia is hypoxemia, which is low blood oxygen, along with shortness of breath, or dyspnea. When enough neighboring sacs fill and clump into one solid, airless area, we call it consolidation. It shows up as a white patch on a chest X-ray.
The classic signs, and the mechanism behind each
Pneumonia tends to announce itself with a cluster you learn to recognize:
- Fever and chills are the body answering an infection. Chemical signals called pyrogens turn the brain’s thermostat up, which makes the body a harsher place for germs.
- Productive cough brings up thick sputum, often yellow, green, or rust-colored. That is the pus and debris being cleared out of flooded airways.
- Tachypnea and tachycardia, meaning fast breathing and a fast heart rate, are the body making up for lost oxygen. It moves more air and pumps the oxygen-poor blood faster.
- Pleuritic chest pain is a sharp pain that gets worse with a deep breath. It shows up when the swelling reaches the lining of the lung.
On imaging, that patch of consolidation confirms the flooded area. In older patients and in patients with weak immune systems, the picture is often quieter. Confusion, or simply "not acting right," may be the only early sign.
Where you caught it matters
Care changes with where the infection started. The likely germs differ, and so does how well drugs work on them.
| Feature | Community-acquired (CAP) | Hospital-acquired (HAP / VAP) |
|---|---|---|
| Where acquired | Out in daily life; starts before admission or within 48 hrs of it | 48+ hrs after admission; VAP is the type tied to a ventilator |
| Common germs | S. pneumoniae, respiratory viruses, atypicals | Often Pseudomonas, Staph aureus including MRSA |
| Drug resistance | Usually lower | Often higher, and harder to treat |
| Typical severity | Mild to severe | Often sicker, with higher mortality |
Ventilator-associated pneumonia (VAP) is worth a note of its own. A breathing tube goes right past the filtering and coughing defenses of the upper airway. That hands bacteria a direct highway into the lungs. This is why care teams follow a "VAP bundle," which includes keeping the head of the bed raised and giving regular mouth care.
Who is most at risk
Anyone with weaker defenses is more open to pneumonia. That includes the very young and adults over 65, people who smoke, and people with chronic lung disease such as COPD. It also includes patients with weak immune systems and patients who have trouble swallowing. Those patients may aspirate, which means food or secretions go down into the lungs. Add anyone whose cough reflex is dulled by sedation or by a decreased level of consciousness.
A word on tuberculosis
Tuberculosis (TB) is a different infection, spread through the air by Mycobacterium tuberculosis. The immune system walls the bacteria inside a shell called a granuloma. TB can sit quiet for years as latent TB, with no symptoms and no spread to others. Later it can wake up into active TB, with cough, weight loss, and night sweats. Explore the figure below to see how infection fills the air sacs.
- Pneumonia fills the air sacs with fluid and pus. Oxygen cannot cross into the blood, so you get hypoxemia, dyspnea, and consolidation on imaging.
- Classic signs are fever, a wet cough, crackles from air sacs popping open, and pleuritic chest pain. Older adults may show only confusion.
- Community-acquired pneumonia (CAP) is usually less drug resistant. Hospital-acquired (HAP) and ventilator-associated (VAP) pneumonia bring tougher germs like Pseudomonas and MRSA.
- Highest risk: the very young, adults over 65, smokers, COPD, weak immune systems, and patients who aspirate. Vaccines and deep breathing help prevent it.
- TB is a separate infection spread through the air and walled into granulomas. It is either latent, meaning quiet and not contagious, or active disease.
Section 6Lung sounds & assessment
Each breath rushes down the windpipe, splits into smaller and smaller tubes, and ends at millions of tiny air sacs called alveoli. When the airways are open and the sacs are dry and springy, air moves smoothly and quietly. That smooth flow is exactly what a stethoscope listens for. Put your stethoscope on someone’s chest and you are listening in on how easily air gets in and out. You are also listening for anything in the way, such as fluid, mucus, swelling, or scarring.
Normal breath sounds: the quiet baseline
Over most of the lung you should hear vesicular breath sounds. They are a soft, low, rustling whoosh, louder when the patient breathes in and fading fast when they breathe out. Over the big central airways, the trachea and the area near the sternum, sounds are naturally louder and more hollow. Those are bronchial and bronchovesicular sounds. Here is the key idea. Normal air movement is clear and quiet. Anything extra layered on top is an adventitious sound, which simply means an added sound. Each type tells you a different story about what is happening inside the airways.
Crackles: air popping open through fluid
Crackles, once called rales, are brief popping or bubbling sounds that come in bursts. People compare them to Velcro pulling apart, or to hair rubbed between your fingers. They happen when air suddenly pushes open small airways and air sacs that were stuck shut or full of fluid. You hear them most when the patient breathes in, because that is when the collapsed spaces snap open. Crackles usually point to fluid or collapse in the air sacs. The classic causes are pneumonia, from inflammatory exudate, and heart failure, where fluid backs up into the lungs as pulmonary edema. In heart failure they often start at the lung bases, because gravity pools the fluid there.
Wheezes: air squeezing through narrowed tubes
Wheezes are high-pitched musical whistling sounds, usually loudest when the patient breathes out. Picture blowing through a straw that is almost pinched shut. They happen when airways are narrowed by bronchospasm, swelling (edema), or mucus. Air is forced through a tight channel and the walls vibrate. Wheezes are the signature of asthma and COPD. One safety note matters here. If a wheeze suddenly goes silent in someone struggling to breathe, that is ominous. Airflow may have dropped so low that no sound is being made, which is called a "silent chest." That is an emergency, not an improvement.
Stridor: the upper-airway alarm bell
Stridor is a harsh, high-pitched crowing sound. You can hear it without a stethoscope, and you usually hear it when the patient breathes in. It comes from a blockage high up in the upper airway, in the larynx or trachea. Causes include swelling from croup, epiglottitis, or anaphylaxis, and a stuck foreign body. Treat stridor as an airway emergency. The tube that keeps a person alive is narrowing, and it can close.
Pleural friction rub: surfaces that should glide, grating instead
Two thin membranes wrap the lungs. They are the pleura, and they normally slide past each other in silence. When they get inflamed, a problem called pleuritis that often follows an infection, they grate together instead. That makes a pleural friction rub, a low-pitched, grating, leathery sound. You hear it both when the patient breathes in and when they breathe out, and it often comes with pain on breathing.
| Feature | Crackles | Wheezes |
|---|---|---|
| Sound | Popping / bubbling | Musical / whistling |
| Cause | Fluid or collapsed air sacs | Narrowed airways |
| Timing | Mainly breathing in | Mainly breathing out |
| Points toward | Pneumonia, heart failure | Asthma, COPD |
Pulse oximetry: seeing the result of all this airflow
Listening tells you how air is moving. The pulse oximeter (SpO2) tells you the result, which is how much oxygen is reaching the blood. It clips on a finger and estimates the percent of hemoglobin carrying oxygen. In healthy adults that runs 95 to 100%. When crackles, wheezes, or a blockage keep oxygen from reaching the air sacs, the SpO2 often falls. That fall is hypoxemia.
Tie this back to the arterial blood gas (ABG) from Week 1. The pulse oximeter is a quick estimate, and it needs no needle. The ABG is the exact lab measurement, and it gives you true PaO2, PaCO2, and pH. Remember the oxyhemoglobin dissociation curve. Its S-shape means that once SpO2 drops below about 90%, the PaO2 has often fallen much further than the number makes it look. Trust the ABG for the full picture. Trust it especially for carbon dioxide, which the pulse oximeter cannot see at all.
Explore the figure below to hear how normal breath sounds differ from crackles, wheezes, stridor, and a friction rub.
- Normal breath sounds are clear and quiet. Any added (adventitious) sound means something is getting in the way of airflow.
- Crackles mean fluid or air sacs popping open, as in pneumonia and heart failure, and you hear them mostly on the breath in. Wheezes mean narrowed airways, as in asthma and COPD, mostly on the breath out.
- Stridor is a harsh sound on the breath in, from a blocked upper airway. Treat it as an emergency. A pleural friction rub is grating and painful, from inflamed pleura.
- Pulse oximetry (SpO2, usually 95 to 100%) estimates oxygen saturation with no needle, but it cannot measure CO2 and it can read falsely.
- The ABG confirms true oxygen, CO2, and pH. Always weigh the numbers against how your patient actually looks.
The chapter in one breath
- Ventilation is air moving in and out of the air sacs. When it drops, which is hypoventilation, CO2 backs up and the pH falls. That is respiratory acidosis.
- Perfusion is blood flow through the pulmonary capillaries. Gas exchange only works where air-filled sacs meet blood-filled capillaries.
- A normal V/Q ratio is about 0.8. A blocked airway, as in pneumonia or mucus, makes a low-V/Q shunt. A blocked vessel, as in PE, makes a high-V/Q dead space.
- COPD is lasting airflow limitation from emphysema plus chronic bronchitis. Air trapping and a barrel chest give a long breath out and chronically held CO2.
- Asthma is reversible bronchospasm with airway swelling and mucus, and it gives wheezing on the breath out. A silent chest with a rising CO2 means dangerous fatigue, not improvement.
- Pulmonary embolism is a clot, often from a DVT, lodging in the pulmonary artery. It causes sudden dyspnea, pleuritic chest pain, tachycardia, and hypoxemia, with a low CO2 from breathing fast.
- Pneumonia fills air sacs with inflammatory exudate. You see fever, a wet cough, crackles, and consolidation that blocks oxygen uptake.
- Adventitious lung sounds place the problem for you. Crackles mean fluid or sacs popping open, wheezes mean narrowed airways, and stridor means a dangerous upper-airway blockage.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Bronchospasm
- A sudden tightening of the smooth muscle wrapped around the bronchi and bronchioles. It narrows the airways, makes air harder to move (especially out), and often causes wheezing.
- Chronic bronchitis
- A form of COPD. The clinical definition is a productive cough lasting at least 3 months in each of 2 years in a row. It comes from lasting airway inflammation, mucus glands that grow larger (mucus-gland hypertrophy), and too much sputum.
- Consolidation
- Lung tissue filled with fluid, pus, blood, or inflammatory cells instead of air, as in pneumonia. That area turns solid, and gas exchange suffers.
- COPD (chronic obstructive pulmonary disease)
- A disease that limits airflow, gets worse over time, and is largely not reversible. It usually comes from smoking. It blends emphysema and chronic bronchitis, and it traps air on the breath out.
- Crackles
- Brief popping or bubbling sounds that come in bursts, heard mostly on the breath in. They happen when collapsed or fluid-filled air sacs and small airways snap open. They often signal fluid or infection.
- Dead space
- Air that you breathe in but that never takes part in gas exchange. It is either the conducting airways (anatomic) or air sacs that get air but no blood flow (physiologic).
- Emphysema
- A form of COPD in which the walls of the air sacs are destroyed and the sacs enlarge. That cuts the surface area for gas exchange and the elastic recoil that normally pushes air out.
- Hypoxemia
- A lower than normal oxygen level in the arterial blood, usually a PaO2 under about 80 mmHg or an SaO2 under about 95%. Left uncorrected, it starves the tissues of oxygen.
- Perfusion
- Blood flowing through the pulmonary capillaries that surround the air sacs. The blood releases carbon dioxide to be exhaled and picks up oxygen from the air in the sacs.
- Pulmonary embolism
- A blockage of a pulmonary artery, most often by a clot that traveled from a deep vein. It suddenly cuts off blood flow to part of the lung, creates dead space, and often causes sharp dyspnea and hypoxemia.
- Shunt
- Blood that passes through the lungs without picking up oxygen, because it flows past air sacs that get blood but no air, as in consolidation or collapse. It causes hypoxemia that oxygen alone often cannot fix.
- Status asthmaticus
- A severe, drawn-out asthma attack that does not respond to the usual bronchodilators. It is a medical emergency and can turn into respiratory failure.
- Stridor
- A harsh, high-pitched sound heard mainly on the breath in. It signals narrowing or blockage of the upper airway, in the larynx or trachea, and it needs urgent attention.
- Ventilation
- Air moving in and out of the lungs. It brings oxygen to the air sacs and carries carbon dioxide away.
- V/Q ratio
- The balance between ventilation (V, airflow) and perfusion (Q, blood flow) in a region of lung, normally about 0.8. A mismatch in either direction hurts gas exchange.
- Wheeze
- A steady, musical, usually high-pitched whistling sound, often loudest on the breath out. Air forced through narrowed lower airways makes it, as in asthma or COPD.
DrillFlashcards for this unit
These are the Week 10 cards, the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.