Pain
Pain is the body’s alarm system — usually protective, sometimes broken, and always personal. This chapter traces a pain signal from the nerve ending that detects damage all the way to the brain that feels it, sorts pain into its types, explains why rubbing a bump helps, and covers how nurses assess and safely relieve it.
By the end of this chapter you can
- Trace the pain pathway through transduction, transmission, perception, and modulation.
- Distinguish somatic, visceral, and neuropathic pain, and acute from chronic.
- Explain the gate control theory and the body’s own pain-relief system.
- Predict referred-pain patterns and assess pain in patients who cannot self-report.
- Apply the WHO analgesic ladder and name the key risks of opioids.
Section 1Nociception & the pain pathway
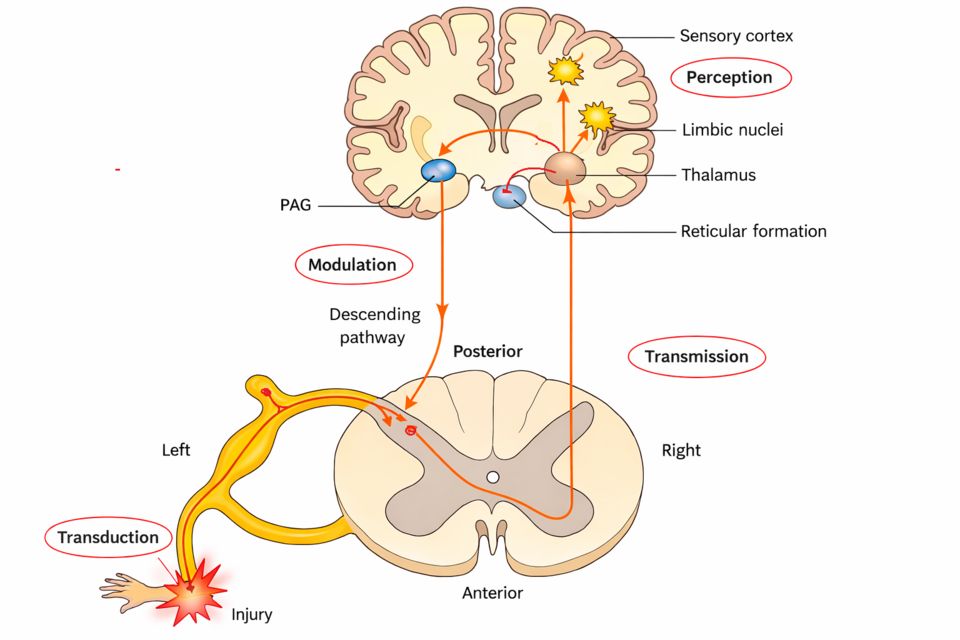
Pain feels like a problem, but in most cases it is your body's alarm system doing exactly what it should. When tissue is threatened or damaged, specialized nerve endings fire and send a warning racing toward your brain: stop, protect this spot, something is wrong. Understanding how that signal is born, how it travels, and how the body can turn the volume up or down is the foundation for everything you will do in pain management.
Nociceptors: the sensors that detect damage
The journey starts with nociceptors - free nerve endings scattered through the skin, muscles, joints, and internal organs. Think of them as tiny smoke detectors. They do not respond to gentle touch; they wake up only when a stimulus is intense enough to signal real or potential tissue damage. That trigger can be mechanical (a cut or crush), thermal (a hot stove), or chemical. When cells are injured they spill out a soup of substances - prostaglandins, bradykinin, histamine, substance P, and hydrogen ions - and this inflammatory soup lowers the firing threshold so the nociceptors become easier to set off. This is why a sunburned shoulder screams at a light pat: the sensors have been sensitized.
The four steps of nociception
Textbooks break the pain process into four linked steps. Learn them in order, because nursing interventions target specific steps.
- Transduction - the noxious stimulus is converted into an electrical signal at the nociceptor. This is where NSAIDs work, blocking prostaglandin production so the sensors stay quieter.
- Transmission - the electrical impulse travels along peripheral nerve fibers to the dorsal horn of the spinal cord, then upward to the brain. Local anesthetics interrupt this step.
- Perception - the brain (cortex and limbic system) becomes consciously aware of the pain and gives it meaning and emotion. This is where distraction, relaxation, and imagery help.
- Modulation - the nervous system turns the signal up or down. Descending pathways release the body's own endogenous opioids (endorphins, enkephalins) plus serotonin and norepinephrine, which dampen the message. Opioids and many antidepressants boost this natural braking system.
Two kinds of fibers, two kinds of pain
Not all pain messages travel at the same speed, and this explains a common experience: stub your toe and you feel a sharp jolt first, then a throbbing ache a moment later. Two different fibers are talking. A-delta fibers are lightly myelinated, so they conduct fast - they carry the sharp, bright, easy-to-pinpoint pain that makes you pull your hand away instantly. C fibers are unmyelinated and slow, carrying the dull, aching, burning, poorly localized pain that lingers afterward. Both fibers hand their signal off in the dorsal horn and cross to the opposite side, then ride the spinothalamic tract up to the thalamus, which relays it to the cortex for perception.
| Feature | A-delta fibers | C fibers |
|---|---|---|
| Myelin | Thinly myelinated | Unmyelinated |
| Speed | Fast | Slow |
| Quality of pain | Sharp, pricking | Dull, aching, burning |
| Localization | Well localized | Diffuse, hard to pinpoint |
| Timing | First (fast) pain | Second (slow) pain |
Why pain protects us - and what happens when it is gone
All of this machinery exists for one reason: survival. Pain forces you to withdraw from harm, to guard an injured limb, and to seek help. It is protective. That is exactly why losing the ability to feel pain is so dangerous. In diabetic peripheral neuropathy, chronic high blood glucose damages the small sensory nerves in the feet, so the nociceptors and their fibers can no longer sound the alarm. A patient may step on a tack, develop a blister from ill-fitting shoes, or walk on an open ulcer for days - completely unaware. Without the warning signal, minor injuries go unnoticed, become infected, and can progress to serious wounds or even amputation. The lesson for nursing practice is powerful: absent pain is not a blessing but a hazard, which is why we teach daily foot inspection and protective footwear for anyone with sensory loss.
Explore the pathway below to trace a single signal from the moment of injury, up the spinothalamic tract, all the way to conscious perception in the brain.
- Nociceptors are free nerve endings that detect mechanical, thermal, and chemical stimuli signaling tissue damage; injury releases prostaglandins and bradykinin that sensitize them.
- Nociception has four steps - transduction, transmission, perception, and modulation - and each is a distinct target for pain-relieving interventions.
- A-delta fibers carry fast, sharp, well-localized pain while C fibers carry slow, dull, aching pain; both ascend the spinothalamic tract to the brain.
- The body modulates pain by releasing endogenous opioids (endorphins, enkephalins) through descending pathways, which is why opioids and some antidepressants relieve pain.
- Pain is protective; when it is absent, as in diabetic neuropathy, unnoticed foot injuries can progress to ulcers, infection, and amputation - so protective foot care is essential.
Section 2The types of pain
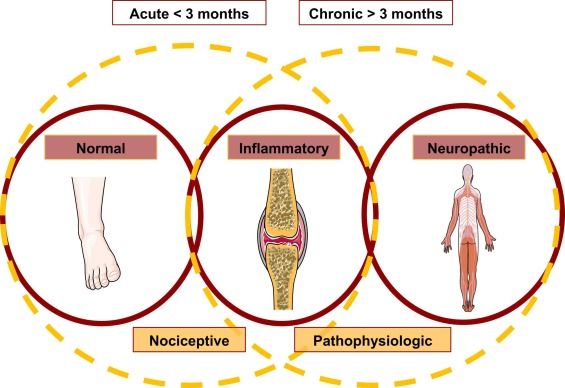
Pain is not a design flaw. In a healthy body, it is one of your best-working alarm systems. Specialized nerve endings called nociceptors sit in your skin, muscles, joints, and organs, quietly waiting. When something threatens to damage tissue, they fire, sending a signal up the spinal cord to the brain, which reads it as "that hurts, do something." This protective alarm makes you pull your hand off a hot stove before you even think about it. The trouble starts when the alarm rings for the wrong reasons, keeps ringing after the danger is gone, or wires itself into a permanent problem. Understanding what kind of pain you are dealing with is the first step, because different pain comes from different places and answers to different treatments.
Nociceptive pain: the normal alarm working as intended
Nociceptive pain is the pain of actual or threatened tissue damage picked up by nociceptors. It is the most familiar type, and it splits into two flavors depending on where those nerve endings live.
Somatic pain comes from the "body wall" tissues you can point to, such as skin, muscle, bone, and joints. These areas are densely supplied with nerves and mapped precisely in the brain, so somatic pain is usually sharp, throbbing, and well-localized. A sprained ankle or a surgical incision hurts right there, and the patient can put a finger on it.
Visceral pain comes from the internal organs such as the gut, bladder, and heart. These organs have fewer, more scattered nociceptors, and their signals travel on nerves that share spinal pathways with the skin. The result is pain that is usually dull, deep, cramping, and poorly localized, often described as "somewhere in my belly." Because of that shared wiring, visceral pain is frequently referred, meaning it is felt in a body-wall location away from the actual organ. The classic example is cardiac pain felt in the left arm or jaw. Visceral pain also tends to bring along nausea, sweating, and restlessness because it activates the autonomic nervous system.
| Feature | Somatic | Visceral |
|---|---|---|
| Source | Skin, muscle, bone, joints | Internal organs |
| Quality | Sharp, throbbing, aching | Dull, deep, cramping |
| Localization | Well-localized, easy to point to | Poorly localized, vague |
| Referred? | Rarely | Often (e.g., MI to arm/jaw) |
Neuropathic pain: the alarm system itself is damaged
Neuropathic pain is different in kind. Here the problem is not tissue damage sending a signal, but damage or dysfunction of the nerves that carry the signal. Injured nerves become abnormally excitable and fire on their own, so the alarm sounds without any real threat. Patients describe it in electrical, burning language, such as burning, shooting, stabbing, tingling, or "pins and needles." They may also have allodynia (pain from something that should not hurt, like a bedsheet) and hyperalgesia (an exaggerated response to a mildly painful stimulus). Common causes include diabetic peripheral neuropathy, phantom limb pain after amputation, and sciatica from a compressed nerve root. This matters clinically because ordinary painkillers often barely touch it.
Acute versus chronic: how long the alarm rings
A separate way to sort pain is by its time course. Acute pain is the protective alarm doing its job. It comes on with an identifiable injury, warns you, and usually resolves as the tissue heals, typically within days to a few weeks. It often carries visible sympathetic signs such as increased heart rate, elevated blood pressure, and sweating.
Chronic pain is pain that persists beyond about three months, or beyond the expected healing time. At this point the nervous system can undergo central sensitization, becoming more efficient at transmitting and amplifying pain, so the pain outlives its usefulness and becomes its own disease. Chronic pain frequently loses the obvious sympathetic signs and instead shows up as fatigue, depression, sleep disruption, and withdrawal. Treating it means looking beyond the original injury to the whole person.
Why the type steers the treatment
Matching the mechanism to the therapy is the whole point of classifying pain. Nociceptive pain generally responds to NSAIDs, acetaminophen, and, for severe cases, opioids. Neuropathic pain usually needs anticonvulsants or antidepressants that calm overactive nerves. Acute pain is treated aggressively and briefly to allow healing, while chronic pain calls for a multimodal plan that combines medications with physical therapy, psychological support, and non-drug strategies.
- Nociceptive pain reflects tissue damage: somatic is sharp and well-localized; visceral is dull, poorly localized, and often referred.
- Neuropathic pain comes from damaged nerves firing on their own, feels burning or shooting, and is seen in diabetic neuropathy, phantom limb, and sciatica.
- Acute pain is protective and resolves with healing; chronic pain lasts beyond ~3 months and becomes its own problem via central sensitization.
- The type of pain guides therapy: NSAIDs/opioids for nociceptive, anticonvulsants/antidepressants for neuropathic, and multimodal plans for chronic pain.
Section 3How pain is modulated
Here is something strange but true: pain is not a fixed signal traveling a one-way wire from your finger to your brain. The nervous system is constantly editing the pain message on its way up, turning the volume up or down before you ever feel it. This editing is called pain modulation, and it happens at every level, from the spinal cord to the brain. Understanding it explains a lot of everyday things, like why rubbing a stubbed toe helps, why a soldier or athlete can keep going despite a serious injury, and why some people hurt for years after the tissue has completely healed.
The gate control theory: crowding out the pain signal
In 1965, Melzack and Wall proposed the gate control theory, and it still guides nursing practice today. Picture a gate in the dorsal horn of the spinal cord where incoming signals compete for passage to the brain. Pain travels on small, slow fibers: thinly myelinated A-delta fibers (sharp, fast pain) and unmyelinated C fibers (dull, aching, burning pain). Touch, pressure, and vibration travel on large, fast A-beta fibers.
Here is the key idea: when you activate the big A-beta fibers, they excite inhibitory interneurons in the dorsal horn that partly close the gate on the pain fibers. The non-painful input literally crowds out some of the painful input. This is the mechanism behind rubbing a bumped elbow, applying heat or cold, massage, and TENS (transcutaneous electrical nerve stimulation), which delivers a mild buzzing current to flood those large fibers and dampen the pain message.
The brain talks back: endogenous opioids and descending inhibition
The gate is not controlled only from below. The brain sends signals downward to the spinal cord to quiet pain, a process called descending inhibition. Nuclei in the midbrain (the periaqueductal gray) and brainstem release neurotransmitters, including serotonin and norepinephrine, that suppress transmission in the dorsal horn. This is also why certain antidepressants (SNRIs, tricyclics) help chronic pain: they boost these descending pathways.
The body also makes its own opioids, called endogenous opioids. The main families are endorphins and enkephalins (plus dynorphins). They bind the same opioid receptors (mu, delta, kappa) that morphine does, blocking the release of pain neurotransmitters like substance P. This is the chemistry behind the calm after intense exercise, the reduced pain during a crisis, and part of why placebo relief is real, not imaginary.
| Feature | Gate closes (less pain) | Gate opens (more pain) |
|---|---|---|
| Fiber activity | Large A-beta touch fibers firing | A-delta and C pain fibers firing |
| From the brain | Descending inhibition active | Descending pathways weak or fatigued |
| Chemistry | Endorphins, enkephalins, serotonin, norepinephrine | Substance P, glutamate |
| State of mind | Relaxed, distracted, hopeful | Anxious, exhausted, focused on the pain |
| Nursing levers | Heat/cold, massage, TENS, distraction, opioids | Untreated anxiety, poor sleep, fear |
When the volume knob gets stuck: central sensitization and wind-up
Normally, modulation keeps pain proportional to injury. But when pain signaling continues intensely and repeatedly, the nervous system can start amplifying itself. Rapid, repeated firing of C fibers produces wind-up, where each stimulus triggers a progressively bigger response in dorsal horn neurons, often through overactivation of NMDA receptors by glutamate. Over time this settles into central sensitization: the spinal cord and brain become hyper-responsive, essentially turning up their own gain.
Two classic signs follow. In hyperalgesia, a painful stimulus hurts far more than it should. In allodynia, something that should not hurt at all, like a bedsheet, a light touch, or a breeze, is felt as pain. These are not exaggeration or drug-seeking; they are the fingerprint of a sensitized nervous system.
Why chronic pain outlasts the injury
This is the crux of chronic pain. Once central sensitization is established, the nervous system keeps generating pain even after the original tissue has healed. The alarm keeps ringing after the fire is out. Reasons include lasting changes in dorsal horn wiring, weakened descending inhibition, and remodeling in pain-processing brain regions. That is why chronic pain (usually defined as pain lasting more than about three months) is now understood as a disease of the nervous system in its own right, not simply ongoing tissue damage. It also explains why chronic pain often needs a broader plan, such as SNRIs or tricyclics, gabapentinoids, graded activity, cognitive strategies, and good sleep, rather than opioids alone, since the problem lives largely in the modulation system itself.
- Pain is modulated, not fixed: the spinal cord and brain turn the signal up or down before you feel it.
- Gate control: large A-beta touch fibers can close the spinal gate on A-delta and C pain fibers, which is why rubbing, heat/cold, and TENS help.
- The brain fights back: descending inhibition plus endogenous opioids (endorphins and enkephalins), serotonin, and norepinephrine suppress pain in the dorsal horn.
- Central sensitization and wind-up turn up the nervous system's own volume, producing hyperalgesia and allodynia.
- Chronic pain can persist after healing because the sensitized nervous system keeps sounding the alarm, so it often needs a multimodal, non-opioid-centered plan.
Section 4Referred pain & special patterns
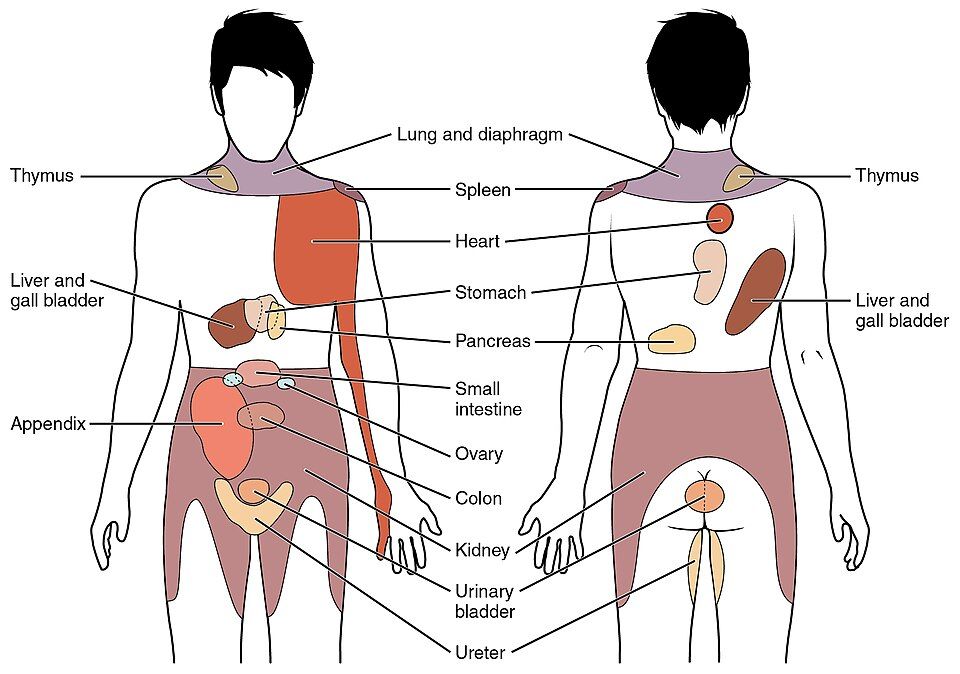
Normally, your brain is very good at telling you where something hurts. A nerve carries a pain signal from a specific spot, travels to a specific level of the spinal cord, and your brain reads the return address and points to the right place. This mapping is usually accurate for skin and muscle, which have dense, well-organized sensory nerves. But some pain does not follow the rules, and understanding why helps you catch dangerous problems and treat pain you cannot easily see.
Referred pain: the crossed-wire problem
Referred pain is pain felt in a body area away from the organ actually causing it. The classic example: a heart attack (myocardial infarction) often hurts in the left arm, jaw, neck, or shoulder rather than only the chest. Why? The nerves carrying pain from the heart enter the spinal cord at the same segments (roughly T1 to T4) as the nerves from the skin of the arm and chest wall. This is called convergence: visceral (organ) signals and somatic (skin) signals share the same second-order neurons on their way up. The brain has spent your whole life feeling your arm and almost never feeling your heart, so when a shared pathway fires, it guesses the familiar source and projects the pain outward to the skin.
Organs give vague, poorly localized pain because their sensory nerves are sparse. That is why visceral pain is often described as deep, dull, cramping, or squeezing, while somatic pain from skin or bone is sharp and easy to pinpoint. Knowing common referral patterns is a safety skill: diaphragm irritation refers to the shoulder tip, gallbladder pain to the right shoulder/scapula, and cardiac pain to the left arm or jaw.
Phantom limb pain
After an amputation, many people still feel the missing limb, and a large share feel pain in it, sometimes burning, cramping, or shooting. This is phantom limb pain. The limb is gone, but the nerves, spinal cord, and the brain's somatosensory map that once served it are still there. Cut nerve endings can form tangled neuromas that fire on their own, the spinal cord becomes hyperexcitable (central sensitization), and the brain's map reorganizes, sometimes misreading nearby signals as coming from the lost limb. It is real neuropathic pain, not imagination, and validating it matters. Treatments target the nervous system: neuropathic agents (gabapentin, certain antidepressants), and mirror therapy, which uses the reflection of the intact limb to help the brain remap.
Assessing pain when the person cannot tell you
Pain is whatever the person says it is, but some people cannot say. Infants, patients who are sedated or intubated, and people with advanced dementia or cognitive impairment need behavioral (observational) pain scales. You watch the body instead of asking a number.
| Population | Tool | What you observe |
|---|---|---|
| Nonverbal older adult / dementia | PAINAD | Breathing, vocalization, facial expression, body language, consolability |
| Critically ill / intubated adult | CPOT or BPS | Facial expression, muscle tension, ventilator compliance |
| Infant / young child | FLACC | Face, Legs, Activity, Cry, Consolability |
Look for grimacing, guarding, restlessness, moaning, or a rigid body. Also watch for physiologic clues, though these are less reliable over time: raised heart rate, blood pressure, and respiratory rate. Consider the situation too; if a procedure or condition would hurt you, assume it hurts them, and treat.
Why pain is under-treated in older adults
Older adults are frequently under-medicated, and it usually comes from stacked barriers rather than one cause:
- Communication gaps: dementia, aphasia, or delirium make self-report hard, so pain gets missed.
- False beliefs: both patients and staff may wrongly assume pain is a normal part of aging, so no one treats it.
- Stoicism and fear: older patients may under-report to avoid being a burden, or fear addiction and side effects.
- Prescriber caution: real worries about falls, confusion, kidney function, and drug interactions make clinicians hesitant, sometimes to the point of undertreatment.
Untreated pain is not benign; it drives delirium, poor sleep, immobility (raising risks of pneumonia, pressure injuries, and clots), depression, and slower recovery. The nursing goal is honest, proactive assessment using the right tool, then advocating for adequate, carefully titrated relief.
- Referred pain happens because visceral and somatic nerves converge at the same spinal segment; cardiac pain classically refers to the left arm, jaw, or shoulder.
- Learn common referral patterns and treat atypical presentations (jaw pain, nausea, dyspnea) as possible MI, especially in women, older adults, and people with diabetes.
- Phantom limb pain is real neuropathic pain from neuroma firing, central sensitization, and cortical remapping; mirror therapy and neuropathic agents help.
- When patients cannot self-report, use behavioral scales: FLACC (infants), PAINAD (dementia), CPOT/BPS (critically ill), watching face, body, and consolability.
- Pain in older adults is often under-treated due to communication barriers and false beliefs; untreated pain fuels delirium, immobility, and complications, so assess proactively and advocate.
Section 5Assessing & managing pain
Pain is your body's alarm system, and it usually does an important job. When tissue is threatened or damaged, specialized nerve endings called nociceptors fire and send a signal up the spinal cord to the brain, where it is finally interpreted as "that hurts." This pathway (transduction, transmission, perception, and modulation) is protective. It makes you pull your hand off a hot stove and guard a sprained ankle so it can heal. The trouble is that the alarm is invisible. You cannot see it on a monitor or draw it in a tube, which is exactly why pain is one of the hardest things a nurse assesses.
Pain is whatever the patient says it is
The guiding rule in nursing is that pain is a subjective, self-reported experience. Margo McCaffery's classic definition still holds: pain is whatever the person says it is, existing whenever they say it does. Two people with the same surgery can report a 3 and a 9, and both are correct, because pain is shaped by nerves and by fear, culture, past experience, and mood. So we ask the patient rather than guessing.
To turn that report into something we can track, we use rating scales. The tool has to match the patient in front of you.
- 0-10 Numeric Rating Scale - for alert adults who can think in numbers. Zero is no pain, ten is the worst imaginable.
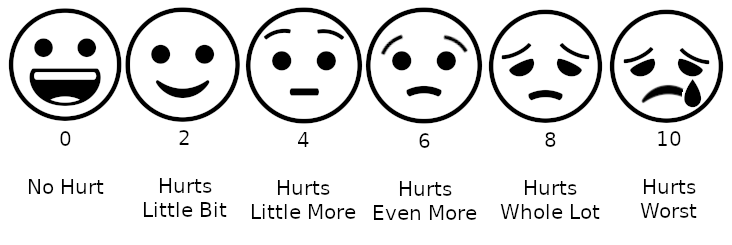
- Wong-Baker FACES - cartoon faces from smiling to crying, useful for young children (usually around age 3 and up) or anyone who struggles with numbers.
- FLACC - a behavioral score (Face, Legs, Activity, Cry, Consolability) for infants and preverbal children who cannot self-report.
- PAINAD - Pain Assessment in Advanced Dementia, which reads breathing, vocalization, facial expression, body language, and consolability in nonverbal older adults.
Whichever scale you pick, keep using the same one for that patient so the numbers are comparable, and pair the score with a fuller assessment such as OLDCARTS or PQRST (location, quality, radiation, timing, what makes it better or worse).
Climbing the WHO analgesic ladder
The World Health Organization (WHO) analgesic ladder is a simple, stepwise plan for matching drug strength to pain intensity. It was built for cancer pain but the logic guides much of pain management.
- Step 1 - mild pain: non-opioid analgesics such as acetaminophen or NSAIDs, with or without an adjuvant (a helper drug like an antidepressant or anticonvulsant for nerve pain).
- Step 2 - moderate pain: a weak opioid (for example codeine or tramadol) added to the non-opioid.
- Step 3 - severe pain: a strong opioid such as morphine, hydromorphone, or fentanyl, still combined with non-opioids and adjuvants.
Two ideas make the ladder work: use multimodal analgesia (drugs that attack pain by different mechanisms so you need less of any one), and dose around the clock for constant pain rather than waiting for it to spike.
Non-opioids vs opioids
Non-opioids work mostly at the site of injury. NSAIDs (ibuprofen, ketorolac, naproxen) block cyclooxygenase (COX) enzymes, so less prostaglandin is made and the nociceptors quiet down; this also fights inflammation but can irritate the stomach lining and stress the kidneys. Acetaminophen relieves pain and fever centrally with little anti-inflammatory effect and, importantly, no GI bleeding risk, but too much (usually more than about 4 grams a day) can cause hepatotoxicity. Opioids act differently: they bind mu receptors in the brain and spinal cord to dampen how pain is transmitted and perceived. They are powerful and have no organ-damaging ceiling, but they carry serious risks.
| Feature | Non-opioids | Opioids |
|---|---|---|
| Main site of action | Peripheral (injury site); acetaminophen more central | Central mu receptors (brain, spinal cord) |
| Dose ceiling | Yes - max daily dose to protect liver/GI/kidney | No true ceiling; titrate to effect |
| Key risks | GI bleed, kidney injury (NSAIDs); liver damage (acetaminophen) | Respiratory depression, constipation, sedation, tolerance, dependence |
| Best for | Mild pain, inflammation, fever | Moderate to severe pain |
The opioid risk you watch hardest is respiratory depression. Mu receptors in the brainstem blunt the drive to breathe, so an oversedated patient breathes slowly and shallowly before the rate ever crashes. Rising sedation is the early warning sign; check level of consciousness and respiratory rate, and keep naloxone (the opioid antagonist) available. Nearly every patient also gets constipation, because gut mu receptors slow motility, so a bowel regimen starts alongside the opioid. Over time patients may develop tolerance (needing more drug for the same relief) and physical dependence (withdrawal if stopped abruptly) - normal physiologic adaptations that are not the same as addiction, which is compulsive use despite harm.
Non-pharmacologic methods
Medication is not the whole plan. Non-drug measures work through the gate control theory - competing signals and top-down input can partly "close the gate" in the spinal cord and reduce how much pain reaches awareness. Cold numbs and slows nerve conduction and eases swelling in fresh injuries; heat relaxes muscle and boosts blood flow for stiffness and cramping. Positioning and support offload strained tissue, while distraction, guided imagery, music, and relaxation or slow breathing lower anxiety and muscle tension, which turns down the pain volume. These pair with drugs and often let you use lower doses.
- Pain is subjective and self-reported; believe the patient and match the scale to them - 0-10 for alert adults, FACES for children, FLACC for the preverbal, PAINAD for advanced dementia.
- The WHO ladder steps from non-opioids to strong opioids, using multimodal, around-the-clock dosing for constant pain.
- Non-opioids act mostly peripherally with organ-based dose ceilings (NSAIDs: GI/kidney; acetaminophen: liver), while opioids act centrally on mu receptors with no true ceiling.
- Watch opioids for respiratory depression - rising sedation is the earliest sign - and expect constipation, tolerance, and dependence; keep naloxone ready.
- Non-drug methods (heat/cold, positioning, distraction, relaxation) work via gate control and let you achieve comfort with lower drug doses.
The chapter in one breath
- Nociception has four steps — transduction (tissue damage releases prostaglandins, bradykinin, and substance P that fire the nerve ending), transmission up the spinal cord, perception in the brain, and modulation that dials the signal up or down.
- Fast, sharp, well-localized pain travels on myelinated A-delta fibers, while dull, aching, poorly-localized pain crawls along unmyelinated C fibers — which is why you feel a pinprick before the throb.
- Nociceptive pain comes from actual tissue injury (somatic = sharp/localized, visceral = deep/cramping), whereas neuropathic pain comes from nerve damage itself and is described as burning, shooting, or electric.
- The gate control theory explains why rubbing a bump helps — large A-beta touch fibers "close the gate" in the dorsal horn, blocking the smaller pain fibers, the same principle behind heat, massage, and TENS.
- Descending modulation from the brainstem releases the body's own endogenous opioids (endorphins, enkephalins) plus serotonin and norepinephrine to naturally quiet pain signals.
- Referred pain is felt away from its source because visceral and somatic nerves converge on the same spinal segment — classically cardiac pain radiating to the left arm or jaw.
- Pain is subjective, so "whatever the patient says it is" is the standard — use a validated tool (0–10 numeric, Wong-Baker FACES, or the behavioral FLACC/PAINAD for nonverbal patients) and a full OLDCARTS/PQRST assessment.
- Treat pain with a multimodal, stepwise plan (the WHO ladder), pairing non-opioids like acetaminophen and NSAIDs with adjuvants and opioids only as needed to hit the lowest effective dose.
- The most dangerous opioid side effect is respiratory depression — watch for a rate < 12 and rising sedation (sedation precedes respiratory depression), keep naloxone ready, and manage the near-universal constipation proactively.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- A-delta fiber
- A thin, myelinated nerve fiber that conducts pain signals quickly, carrying the sharp, well-localized "first pain" you feel the instant you touch something harmful.
- Analgesic
- Any medication or agent that relieves pain without causing loss of consciousness, such as acetaminophen, NSAIDs, or opioids.
- C fiber
- A small, unmyelinated nerve fiber that conducts pain slowly, producing the dull, aching, poorly localized "second pain" that lingers after an injury.
- Central sensitization
- A state in which the central nervous system becomes hyperexcitable and amplifies pain signals, so that even normally non-painful stimuli begin to hurt (often part of chronic pain).
- Endorphin
- A naturally occurring opioid-like chemical the body releases to bind opioid receptors, block pain transmission, and produce a sense of relief or well-being.
- Gate control theory
- The idea that the spinal cord contains a neural "gate" where non-painful input (like rubbing the skin) can close the gate and reduce how many pain signals reach the brain.
- Modulation
- The fourth step of pain processing, in which the body dampens or intensifies pain signals along the pathway, often by releasing its own chemicals like endorphins and serotonin.
- Neuropathic pain
- Pain caused by damage to or dysfunction of the nerves themselves, usually described as burning, shooting, tingling, or "pins-and-needles."
- Nociceptor
- A specialized sensory nerve ending that detects actual or potential tissue damage and starts the pain signal traveling toward the spinal cord and brain.
- Perception
- The third step of pain processing, in which the brain becomes consciously aware of the pain and gives it meaning, intensity, and emotional weight.
- Phantom limb pain
- Pain that feels as if it is coming from a body part that has been amputated, thought to arise from continued nerve and brain signaling after the limb is gone.
- Referred pain
- Pain that is felt in a body area different from its actual source, such as jaw or left-arm pain during a heart attack, because sensory nerves share spinal cord pathways.
- Somatic pain
- Pain arising from the skin, muscles, bones, or joints that is usually sharp, aching, and easy to pinpoint.
- Transduction
- The first step of pain processing, in which a harmful stimulus (heat, pressure, or chemicals) is converted into an electrical nerve impulse at the nociceptor.
- Transmission
- The second step of pain processing, in which the electrical impulse travels from the injury site along nerve fibers to the spinal cord and up to the brain.
- Visceral pain
- Pain arising from the internal organs that is typically dull, cramping, or squeezing, hard to localize, and often accompanied by nausea or sweating.
DrillFlashcards for this unit
These are the Week 4 cards — the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it; hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.