The Respiratory System
Breathing is the one vital sign a patient can hear themselves, and the respiratory chapter is where medical language stops being abstract. Every term here maps onto something you will watch, count or listen to at the bedside: a rate, a colour, a sound, a number on a monitor. The vocabulary is built from a short, orderly stack of structures — nose, pharynx, larynx, trachea, bronchi, bronchioles, alveoli, pleura — and a small set of suffixes that describe breathing itself, chief among them -pnea. Learn the stack and the suffixes and you can decode terms you have never seen: laryngotracheobronchitis, bronchiectasis, pneumoconiosis, hypercapnia. This chapter walks the airway from nostril to alveolus, then works outward through pathology, diagnostics, surgery and the abbreviations that crowd a real respiratory chart. Along the way it flags the traps that cost students points and, later, cost clinicians clarity: pneum/o against pulmon/o, -ptysis against -ptosis, tracheotomy against tracheostomy.
By the end of this chapter you can
- Name and spell the combining forms for the respiratory structures, including rhin/o, pharyng/o, laryng/o, trache/o, bronch/o, alveol/o, pleur/o and pneumon/o.
- Distinguish pneum/o, pneumon/o and pulmon/o and explain why pneumothorax has nothing to do with infection.
- Build and decode terms using the breathing suffixes -pnea, -capnia, -oxia, -ptysis, -thorax, -ectasis and -phonia.
- Form the plurals of bronchus, alveolus, pleura, larynx, pharynx and apex correctly.
- Define the major upper- and lower-airway disorders, including epistaxis, croup, asthma, emphysema, atelectasis, pleural effusion and pneumoconiosis.
- Translate the diagnostic vocabulary of spirometry, pulse oximetry, arterial blood gases, bronchoscopy and chest imaging.
- Describe the sounds a clinician documents on auscultation — crackles, wheezes, rhonchi, stridor and friction rub — using the correct terms.
- Separate the surgical suffixes -tomy, -stomy, -ectomy and -centesis as they apply to the trachea, thorax and lung.
- Expand and use the abbreviations found on a respiratory chart, including COPD, ABG, PFT, SOB, OSA, V/Q and CPAP.
Section 1Walking the Airway: The Combining Forms
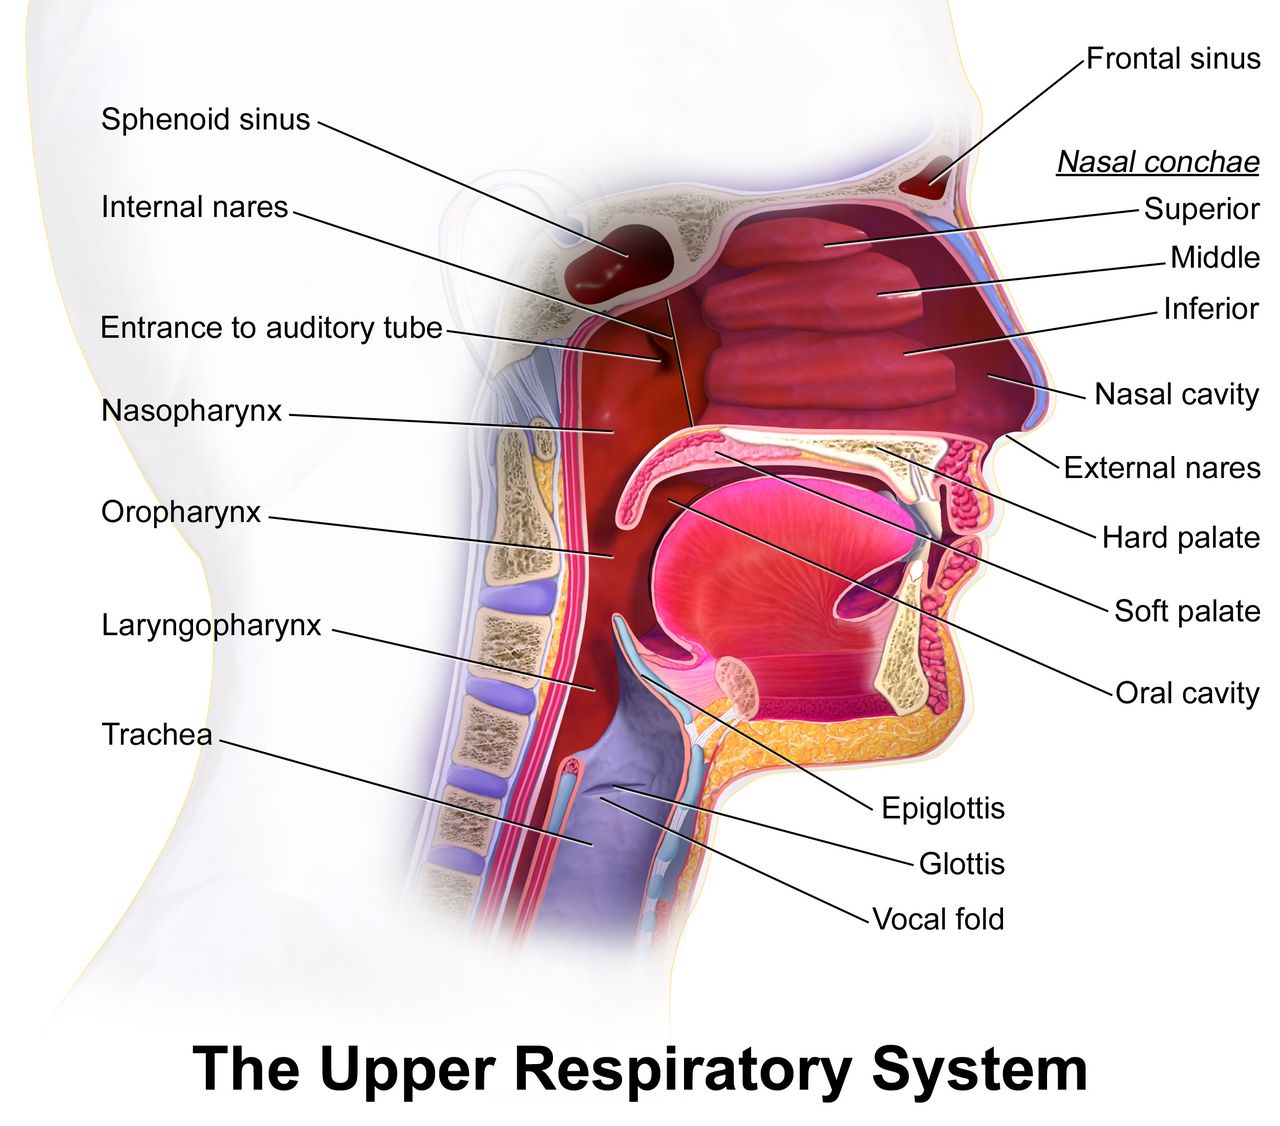
The upper airway: nose, sinuses, pharynx and larynx
Respiratory terminology is unusually kind to the beginner because it follows a physical path. Air enters at the nose, crosses the pharynx, passes the larynx, drops down the trachea, divides into bronchi, narrows into bronchioles and finally arrives at the alveoli. Learn the combining forms in that order and you have learned them in the order a disease travels, the order a bronchoscope travels and the order a chart describes.
The nose contributes two combining forms, one Latin and one Greek, and English kept both. Nas/o gives us anatomical adjectives such as nasal and nasogastric; rhin/o gives us disease and surgery words such as rhinitis and rhinoplasty. Decode rhin/o/rrhea (rye-noh-REE-ah) as nose + discharge — a runny nose — and rhin/o/plasty (RYE-noh-plas-tee) as nose + surgical repair. The air-filled cavities in the skull around the nose are the paranasal sinuses, from sinus/o, and the wall that divides the nasal cavity in half is the septum, from sept/o. A nosebleed has its own Greek word, epistaxis (ep-ih-STAK-sis), which is worth memorising because it does not decode neatly.
Behind the nose and mouth is the pharynx, or throat, from pharyng/o. It is a shared corridor: food and air both cross it, which is exactly why swallowing problems and breathing problems overlap clinically. Below and in front of the pharynx sits the larynx, or voice box, from laryng/o. The larynx holds the vocal cords, so voice terms live here too: dys/phonia (dis-FOH-nee-ah) is difficult or hoarse voice, and a/phonia (ah-FOH-nee-ah) is no voice at all. Guarding the top of the larynx is the epiglottis (ep-ih-GLOT-is), the flap that folds over the airway during a swallow; inflame it and you get epiglottitis, an airway emergency in a child.
| Combining form | Meaning | Example term | What the example means |
|---|---|---|---|
| nas/o | nose | nasopharyngeal | pertaining to the nose and the pharynx |
| rhin/o | nose | rhinitis | inflammation of the nasal lining |
| sept/o | partition, septum | septoplasty | surgical repair of the nasal septum |
| sinus/o | sinus, cavity | sinusitis | inflammation of a paranasal sinus |
| pharyng/o | pharynx, throat | pharyngitis | inflammation of the throat |
| laryng/o | larynx, voice box | laryngoscopy | visual examination of the larynx |
| epiglott/o | epiglottis | epiglottitis | inflammation of the epiglottis |
| tonsill/o | tonsil | tonsillectomy | surgical removal of the tonsils |
| adenoid/o | adenoids | adenoidectomy | surgical removal of the adenoids |
| uvul/o | uvula | uvulectomy | surgical removal of the uvula |
| palat/o | palate | palatoplasty | surgical repair of the palate |
| osm/o | sense of smell | anosmia | absence of the sense of smell |
The lower airway: trachea, bronchi, bronchioles, alveoli
The trachea, or windpipe, comes from trache/o — a form you will meet constantly, because the trachea is where emergency airways are placed. It divides at the carina into two main bronchi, from bronch/o or bronchi/o. Those branch again and again until the tubes are too small to hold cartilage; at that point they are bronchioles, from bronchiol/o. Note the pattern: the diminutive endings -ole and -ule both mean small, as in arteriole and venule. Bronchiolitis is therefore inflammation of the smallest airways, a disease of infants, while bronchitis is inflammation of the larger ones.
At the end of every terminal bronchiole is a cluster of microscopic sacs, the alveoli, from alveol/o. This is where gas exchange happens and where pneumonia lives. Air reaches the alveolus and oxygen crosses into a capillary; carbon dioxide crosses the other way. Anything that fills the alveolus — pus, water, blood — blocks that exchange, and much of respiratory pathology is simply a catalogue of what can occupy an alveolar space.
The lung as a whole has three combining forms and students routinely mix them. Pulmon/o is Latin and gives adjectives and specialties: pulmonary, pulmonologist. Pneumon/o is Greek for lung and gives pneumonia (noo-MOH-nee-ah) and pneumonectomy. Pneum/o is the troublemaker, because it can mean lung or air. In pneumothorax it means air; in pneumococcal it points at the lung. Each lung is divided into lobes, from lob/o — three on the right, two on the left — and the notch where vessels and bronchi enter is the hilum (HIGH-lum), from hil/o.
| Combining form | Meaning | Example term | What the example means |
|---|---|---|---|
| trache/o | trachea, windpipe | tracheal | pertaining to the trachea |
| bronch/o, bronchi/o | bronchus | bronchoscopy | visual examination inside the bronchi |
| bronchiol/o | bronchiole | bronchiolitis | inflammation of the bronchioles |
| alveol/o | alveolus, air sac | alveolar | pertaining to the air sacs |
| pulmon/o | lung | pulmonologist | physician specialising in the lungs |
| pneumon/o | lung | pneumonectomy | surgical removal of a lung |
| pneum/o | lung; air, gas | pneumothorax | air in the chest cavity |
| lob/o | lobe | lobectomy | surgical removal of a lobe |
| hil/o | hilum | hilar | pertaining to the hilum of the lung |
| cili/o | cilia, hairlike processes | ciliary | pertaining to the cilia that sweep mucus upward |
| muc/o | mucus | mucopurulent | containing both mucus and pus |
The chest wall, pleura and diaphragm
The lungs do not float free. They sit inside the thorax, from thorac/o, wrapped in a two-layered membrane called the pleura, from pleur/o. The visceral pleura clings to the lung, the parietal pleura lines the chest wall, and the thin film between them is the pleural space. That space is the site of an enormous amount of vocabulary: air in it is a pneumothorax, blood is a hemothorax, pus is a pyothorax or empyema, and serous fluid is a pleural effusion. The suffix -thorax is doing all the work, and whatever sits in front of it names the contents.
The floor of the thorax is the diaphragm, the dome-shaped muscle that does most of the work of quiet breathing. It has two combining forms, phren/o and diaphragmat/o. Be warned that phren/o historically also meant mind, which is why schizophrenia exists; in respiratory context it means diaphragm, as in the phrenic nerve that drives it. Between the ribs, from cost/o, run the intercostal muscles; the space between the two lungs, holding heart, oesophagus and great vessels, is the mediastinum (mee-dee-as-TYE-num).
Two more forms round out the section because they describe what we measure rather than what we cut. Spir/o means to breathe, and it is buried in spirometry, inspiration, expiration and respiration. Ox/i and ox/o mean oxygen, as in oximetry and hypoxia, and capn/o means carbon dioxide, as in capnography and hypercapnia. Together these three give you the language of every ventilator screen you will ever stand in front of.
| Combining form | Meaning | Example term | What the example means |
|---|---|---|---|
| thorac/o | chest, thorax | thoracic | pertaining to the chest |
| steth/o | chest | stethoscope | instrument for listening to the chest |
| pleur/o | pleura | pleuritis | inflammation of the pleura |
| phren/o | diaphragm; mind | phrenic | pertaining to the diaphragm |
| diaphragmat/o | diaphragm | diaphragmatic | pertaining to the diaphragm |
| cost/o | rib | intercostal | between the ribs |
| mediastin/o | mediastinum | mediastinoscopy | visual examination of the mediastinum |
| spir/o | to breathe | spirometer | instrument that measures breathing |
| ox/i, ox/o | oxygen | oximetry | measurement of oxygen saturation |
| capn/o | carbon dioxide | capnography | recording of exhaled carbon dioxide |
| phon/o | voice, sound | dysphonia | difficult or impaired voice |
| coni/o | dust | pneumoconiosis | abnormal lung condition caused by dust |
Respiratory vocabulary is organised anatomically from nostril to alveolus, so learning the combining forms in airway order also teaches you where each disease sits.
Section 2The Grammar of Breathing: Suffixes, Prefixes and Plurals
-pnea and its family
If you learn one respiratory suffix, learn -pnea, meaning breathing. The p is silent only when it opens a word, as in pneumonia; inside a compound it is sounded and clings to the syllable in front of it, which is why apnea is AP-nee-ah and dyspnea is DISP-nee-ah. Almost every complaint a patient brings to a clinic can be written with it. Normal, easy breathing is eu/pnea (yoop-NEE-ah), from eu- meaning good or normal. Difficult breathing is dys/pnea (DISP-nee-ah). Absence of breathing is a/pnea (AP-nee-ah). Fast breathing is tachy/pnea (tak-ip-NEE-ah) and slow breathing is brady/pnea (brad-ip-NEE-ah).
Two more deserve special attention because they carry diagnostic weight. Ortho/pnea (or-thop-NEE-ah) decodes as straight + breathing: the patient can breathe only when sitting upright. Charted as three-pillow orthopnea, it is one of the classic signs of heart failure, and it is a good reminder that a respiratory word can point at a cardiac diagnosis. Hyper/pnea means deep, increased breathing — a change in depth, not necessarily rate — while hypo/pnea means shallow breathing, a term you will meet in sleep studies where hypopneas are counted alongside apneas.
Watch the difference between hyperpnea and hyperventilation. Hyperpnea describes deep breathing that may be entirely appropriate, as during exercise. Hyperventilation describes breathing in excess of metabolic need, which drops the carbon dioxide level and produces hypocapnia. The vocabulary of gases sits alongside the vocabulary of breathing, and clinicians move between them constantly: too little oxygen in the blood is hypoxemia (high-pok-SEE-mee-ah), too little oxygen in the tissue is hypoxia, and too much carbon dioxide in the blood is hypercapnia (high-per-KAP-nee-ah).
| Term | Word parts | Literal decode | Clinical meaning |
|---|---|---|---|
| eupnea | eu- + -pnea | good + breathing | normal, unlaboured breathing |
| dyspnea | dys- + -pnea | difficult + breathing | shortness of breath |
| apnea | a- + -pnea | without + breathing | cessation of breathing |
| tachypnea | tachy- + -pnea | fast + breathing | respiratory rate above normal |
| bradypnea | brady- + -pnea | slow + breathing | respiratory rate below normal |
| orthopnea | orth/o + -pnea | straight + breathing | breathlessness relieved by sitting upright |
| hyperpnea | hyper- + -pnea | above + breathing | abnormally deep breathing |
| hypopnea | hypo- + -pnea | below + breathing | abnormally shallow breathing |
The other respiratory suffixes
Beyond -pnea, a compact set of suffixes covers most of what the chest can do wrong. -thorax names the contents of the pleural space, as we saw. -ectasis means stretching, dilation or expansion; it appears in bronchi/ectasis (brong-kee-EK-tah-sis), permanent dilation of bronchi, and in atel/ectasis (at-eh-LEK-tah-sis), where the combining form atel/o meaning incomplete flips the sense to collapse — incomplete expansion.
-ptysis means spitting. It has essentially one common home: hem/o/ptysis (hee-MOP-tih-sis), coughing up blood from the lower airway. Do not confuse it with -ptosis, meaning drooping or prolapse, as in blepharoptosis, a drooping eyelid. One letter separates a lung finding from an eyelid finding. Similarly, -capnia (carbon dioxide) and -pnea (breathing) look alike but are unrelated; a patient can have apnea and hypercapnia at the same time, and the two words are describing different measurements.
The remaining suffixes are the general-purpose ones you already own from earlier chapters, and they behave predictably here. -itis gives every inflammation on the tract: rhinitis, sinusitis, pharyngitis, laryngitis, tracheitis, bronchitis, bronchiolitis, alveolitis, pleuritis. -scopy and -scope give the looking words. -metry and -meter give the measuring words. -graphy, -gram and -graph give the recording words. String a long root onto them and even a frightening term collapses: laryng/o/trache/o/bronch/itis (lah-ring-goh-tray-kee-oh-brong-KYE-tis) is inflammation of the larynx, trachea and bronchi — which is simply croup.
| Suffix | Meaning | Example term | What the example means |
|---|---|---|---|
| -pnea | breathing | dyspnea | difficult breathing |
| -capnia | carbon dioxide | hypercapnia | excess carbon dioxide in the blood |
| -oxia | oxygen (in tissue) | hypoxia | deficient oxygen in the tissues |
| -emia | blood condition | hypoxemia | deficient oxygen in the blood |
| -thorax | chest, pleural cavity | hemothorax | blood in the pleural cavity |
| -ectasis | dilation, expansion | bronchiectasis | permanent dilation of the bronchi |
| -ptysis | spitting | hemoptysis | coughing up blood |
| -phonia | voice | aphonia | loss of voice |
| -osmia | sense of smell | hyposmia | reduced sense of smell |
| -spasm | sudden involuntary contraction | bronchospasm | sudden narrowing of the bronchi |
| -stenosis | narrowing | tracheostenosis | narrowing of the trachea |
| -pexy | surgical fixation | pleuropexy | surgical fixation of the pleura |
| -centesis | surgical puncture to remove fluid | thoracentesis | puncture of the chest wall to drain fluid |
Prefixes and the plural rules
The prefixes that matter most here are the ones of rate, amount and position. A- and an- mean without; dys- means difficult or painful; eu- means normal; tachy- and brady- mean fast and slow; hyper- and hypo- mean above and below normal. Position prefixes matter for the pleura and chest wall: endo- and intra- mean within, as in endotracheal; peri- means around; para- means beside, as in paranasal; trans- means across, as in transtracheal. Learn a- before a consonant and an- before a vowel, which is why we say a/pnea but an/osmia (an-OZ-mee-ah).
Respiratory anatomy is a graveyard of irregular plurals, and charting demands you get them right. The rules are the same ones from Chapter 1, applied to a dense cluster of Latin and Greek nouns. A single air sac is an alveolus (al-VEE-oh-lus); many are alveoli (al-VEE-oh-lye). One bronchus becomes two bronchi (BRONG-kye). The membrane is a pleura; both layers together are the pleurae (PLOO-ree). Words ending in -nx change to -nges: one larynx, two larynges (lah-RIN-jeez), and likewise pharynx to pharynges. The top of the lung is the apex; both tops are the apices (AY-pih-seez).
Adjective forms follow their own conventions and are worth noticing because they change spelling in ways that trip up dictation. Larynx becomes laryngeal (lah-RIN-jee-al), with a hard-to-hear g. Pharynx becomes pharyngeal. Mucus is the noun and mucous is the adjective, so a mucous membrane secretes mucus — never the reverse. And pleura becomes pleural, which sounds identical to plural in speech; context, not sound, tells you which one a dictation means.
| Singular | Plural | Rule | Note |
|---|---|---|---|
| alveolus | alveoli | -us becomes -i | al-VEE-oh-lye |
| bronchus | bronchi | -us becomes -i | BRONG-kye |
| pleura | pleurae | -a becomes -ae | PLOO-ree |
| larynx | larynges | -nx becomes -nges | lah-RIN-jeez |
| pharynx | pharynges | -nx becomes -nges | fah-RIN-jeez |
| apex | apices | -ex becomes -ices | AY-pih-seez |
| septum | septa | -um becomes -a | the nasal septum, the alveolar septa |
| bronchiolus | bronchioli | -us becomes -i | usually written bronchiole / bronchioles in English |
| thorax | thoraces | -x becomes -ces | THOR-ah-seez; rare in charting |
The suffix -pnea plus a handful of rate and amount prefixes generates most of the vocabulary you will use to describe a patient’s breathing, and the irregular plurals of the airway must be memorised as pairs.
Section 3What Goes Wrong: Respiratory Pathology
Upper-airway disorders
Most upper-airway terms are a combining form plus -itis, and their clinical weight rises as you move downward. Rhinitis is inflammation of the nasal lining, allergic or infectious, and produces rhinorrhea. Sinusitis, now often written rhinosinusitis because the two cavities inflame together, adds facial pressure and postnasal drip. Pharyngitis is a sore throat; tonsillitis and adenoiditis name the lymphoid tissue that swells with it. Laryngitis takes the voice, producing dysphonia or aphonia. Epiglottitis is the dangerous one: rapid swelling of the epiglottis that can close the airway within hours.
Three upper-airway terms do not decode and simply have to be learned. Epistaxis is a nosebleed. Croup is the childhood illness whose formal name is laryngotracheobronchitis, marked by a barking cough and inspiratory stridor (STRY-dor), the harsh crowing sound of a narrowed upper airway. Pertussis (per-TUS-is), or whooping cough, is a bacterial infection named from Latin for intense cough. Structural problems round out the list: a deviated septum displaces the nasal partition to one side, nasal polyps are soft benign growths in the nasal lining, and obstructive sleep apnea is repeated collapse of the pharyngeal airway during sleep.
| Term | Decode | Meaning |
|---|---|---|
| rhinitis | rhin/o + -itis | inflammation of the nasal mucosa |
| rhinorrhea | rhin/o + -rrhea | discharge from the nose |
| sinusitis | sinus/o + -itis | inflammation of the paranasal sinuses |
| epistaxis | (Greek, not decodable) | nosebleed |
| pharyngitis | pharyng/o + -itis | inflammation of the throat |
| laryngitis | laryng/o + -itis | inflammation of the voice box |
| epiglottitis | epiglott/o + -itis | inflammation of the epiglottis; airway emergency |
| laryngotracheobronchitis | laryng/o + trache/o + bronch/o + -itis | croup |
| tracheostenosis | trache/o + -stenosis | narrowing of the trachea |
| anosmia | an- + -osmia | total loss of the sense of smell |
Obstructive and chronic lower-airway disease
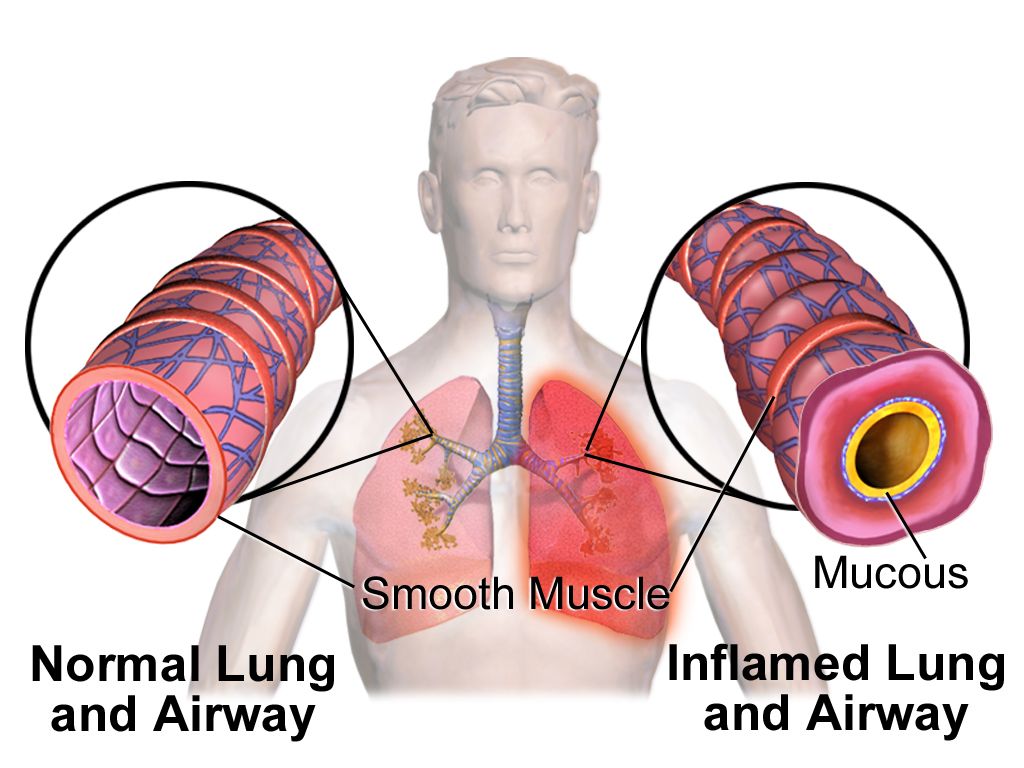
Asthma (AZ-mah) is reversible narrowing of the airways from bronchospasm, mucosal swelling and mucus. Its terminology borrows heavily from Section 2: an attack produces bronchospasm, wheezing, dyspnea and prolonged expiration, and treatment is aimed at bronchodilation. Chronic obstructive pulmonary disease, abbreviated COPD, is the umbrella term for airflow limitation that does not fully reverse. Its two classical components are chronic bronchitis, defined by a productive cough over time, and emphysema (em-fih-SEE-mah), in which alveolar walls are destroyed so the lung loses elastic recoil and traps air.
Bronchiectasis is permanent, abnormal dilation of bronchi from repeated infection or from cystic fibrosis, a genetic disease that makes secretions thick and hard to clear. Atelectasis is collapse of alveoli — commonly after surgery, when shallow breathing lets segments of lung close. These two words are nearly identical in spelling and opposite in meaning, which is exactly why students lose points on them.
Two more chronic groups belong here. Pneumoconiosis (noo-moh-koh-nee-OH-sis) decodes as lung + dust + abnormal condition and names the occupational dust diseases: anthracosis (an-thrah-KOH-sis) from coal dust, also called black lung; silicosis (sil-ih-KOH-sis) from silica; and asbestosis (as-bes-TOH-sis) from asbestos fibres. And pulmonary fibrosis is scarring of lung tissue, which stiffens the lung and makes it hard to expand — a restrictive rather than obstructive pattern.
Infection, fluid and the pleural space
Pneumonia is infection and inflammation of the alveoli, which fill with exudate. Modifiers do most of the diagnostic work: lobar pneumonia occupies a whole lobe, bronchopneumonia is patchy around the airways, aspiration pneumonia follows inhaled stomach contents, and community-acquired and hospital-acquired describe where it was contracted. Pneumonitis is the more general word for lung inflammation without necessarily an infection, as after radiation or chemical inhalation. Tuberculosis, caused by Mycobacterium tuberculosis, forms granulomas and can lie dormant for years; influenza and RSV are the viral names you will meet every winter.
Fluid problems are named by what fills the space and where. Pulmonary edema is fluid inside the alveoli, most often from left-sided heart failure. Pleural effusion is fluid in the pleural space, outside the lung. Empyema (em-pye-EE-mah) is pus in the pleural space, and pleurisy (PLOOR-ih-see), also written pleuritis (ploo-RYE-tis), is inflammation of the pleura, classically producing sharp pain that worsens with inspiration. Acute respiratory distress syndrome, or ARDS, is diffuse alveolar injury with severe hypoxemia that does not correct easily with oxygen.
Two vascular and mechanical emergencies complete the picture. A pulmonary embolism (PE) is a clot, usually from a deep leg vein, that lodges in the pulmonary circulation and blocks perfusion. A pneumothorax (noo-moh-THOR-aks) is air in the pleural space that lets the lung collapse; a tension pneumothorax traps that air under pressure and pushes the mediastinum sideways. Hemothorax is blood in the same space, common after chest trauma. Malignancy uses its own compact vocabulary: bronchogenic carcinoma (brong-koh-JEN-ik) is lung cancer arising in the bronchial lining, and mesothelioma (mez-oh-thee-lee-OH-mah) is a cancer of the pleural lining strongly linked to asbestos exposure.
| Term | Decode | Meaning |
|---|---|---|
| pneumonia | pneumon/o + -ia | infection and inflammation filling the alveoli |
| pneumonitis | pneumon/o + -itis | inflammation of lung tissue, often non-infectious |
| atelectasis | atel/o + -ectasis | incomplete expansion; alveolar collapse |
| bronchiectasis | bronchi/o + -ectasis | permanent dilation of the bronchi |
| emphysema | (Greek, to inflate) | destruction of alveolar walls with air trapping |
| pneumoconiosis | pneum/o + coni/o + -osis | lung disease caused by inhaled dust |
| anthracosis | anthrac/o + -osis | coal-dust lung disease, black lung |
| pneumothorax | pneum/o + -thorax | air in the pleural space |
| hemothorax | hem/o + -thorax | blood in the pleural space |
| pyothorax | py/o + -thorax | pus in the pleural space; empyema |
| hydrothorax | hydr/o + -thorax | watery fluid in the pleural space |
| pleurisy | pleur/o + -itis | inflammation of the pleura with pleuritic pain |
| mesothelioma | mes/o + theli/o + -oma | tumour of the mesothelial lining of the pleura |
| hemoptysis | hem/o + -ptysis | coughing up blood |
Respiratory pathology sorts into three buckets — airway narrowing, alveolar filling and pleural-space contents — and the term almost always tells you which bucket it belongs to.
Section 4Assessment and Diagnostic Terms
What the examiner sees, feels and hears
A respiratory assessment is documented in a fixed order — inspection, palpation, percussion, auscultation — and each step has its own words. On inspection you may record cyanosis (sye-ah-NOH-sis), the bluish tint of poorly oxygenated tissue; clubbing, the bulbous fingertip change of chronic hypoxia; retractions, the visible sucking-in of soft tissue between and below the ribs; and accessory muscle use, when the neck and shoulder muscles are recruited to breathe. Chest shape gets its own terms: barrel chest in advanced emphysema, pectus excavatum for a sunken sternum, pectus carinatum for a protruding one.
Percussion (per-KUSH-un) is tapping the chest wall and listening to the note. Air-filled lung is resonant; hyperresonance suggests too much air, as in emphysema or pneumothorax; dullness suggests fluid or consolidation, as in effusion or pneumonia. Auscultation (aws-kul-TAY-shun) is listening with a stethoscope, and its findings are the vocabulary students most often garble. Normal breath sounds are vesicular over the lung fields. Abnormal sounds are collectively called adventitious sounds.
Learn the five adventitious sounds as a set — four of them auscultated with a stethoscope, plus stridor, which stands apart because it is audible without one. Crackles, formerly called rales, are discontinuous popping sounds made by fluid or by collapsed alveoli snapping open; they suggest pneumonia, pulmonary edema or fibrosis. Wheezes are continuous musical sounds from narrowed lower airways, classically expiratory in asthma. Rhonchi (RONG-kye) are low-pitched, snoring sounds from secretions in larger airways that often clear with a cough. Stridor is a harsh, high-pitched sound of upper-airway obstruction, usually heard on inspiration and without a stethoscope — a red-flag finding. A pleural friction rub is the grating sound of inflamed pleural surfaces sliding on each other.
| Term | Word parts or origin | What it describes |
|---|---|---|
| auscultation | Latin, to listen | listening to body sounds with a stethoscope |
| percussion | Latin, to strike | tapping the chest to judge the underlying tissue |
| adventitious sounds | Latin, added | any abnormal added breath sound |
| crackles (rales) | descriptive | discontinuous popping from fluid or collapsed alveoli |
| rhonchi | Greek, snoring | low-pitched sounds from secretions in large airways |
| stridor | Latin, harsh sound | high-pitched upper-airway obstruction sound |
| cyanosis | cyan/o + -osis | bluish discolouration from deoxygenated blood |
| sputum | Latin, spit | material coughed up from the lower airway |
| expectoration | ex- + pector/o + -ation | the act of coughing material out of the chest |
| hemoptysis | hem/o + -ptysis | blood in the expectorated sputum |
| apnea of infancy | a- + -pnea | pauses in an infant’s breathing |
| paroxysmal nocturnal dyspnea | dys- + -pnea | sudden night-time breathlessness that wakes the patient |
Measuring the breath: spirometry, oximetry and blood gases
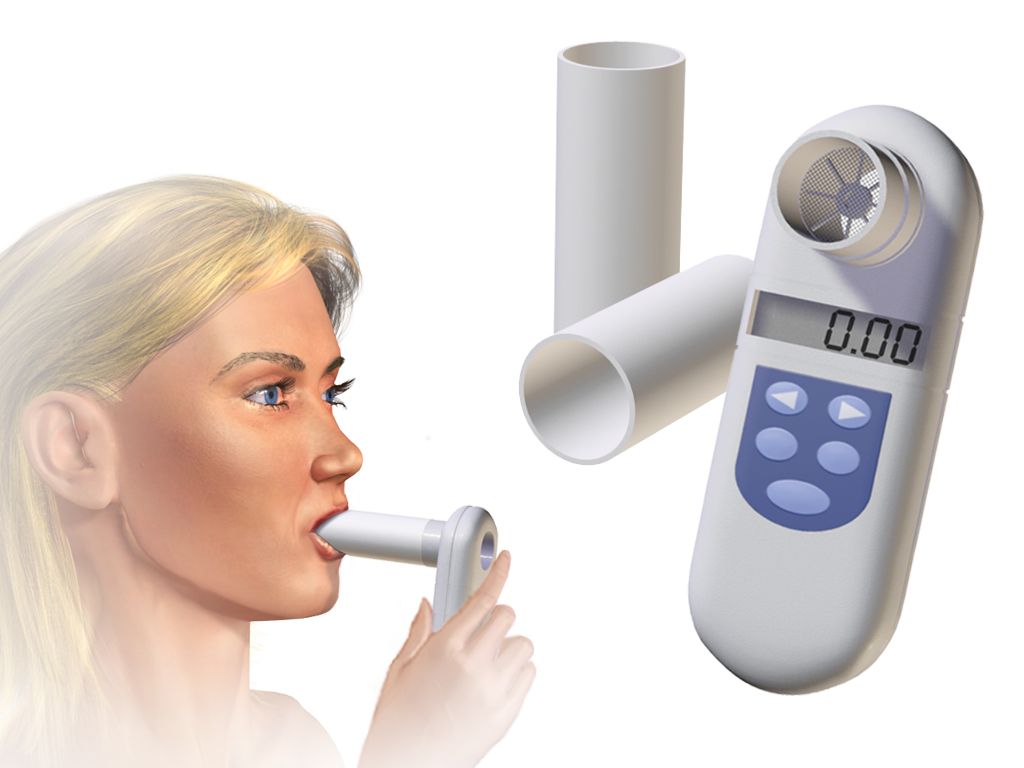
Spirometry (spy-ROM-eh-tree) decodes as breathe + measurement and is the core of pulmonary function testing (PFT). The patient blows into a spirometer, and the machine reports volumes and flows. Vital capacity (VC) is the greatest volume that can be exhaled after a maximal inhalation; forced vital capacity (FVC) is that same manoeuvre done as fast as possible; FEV1 is the volume forced out in the first second. The ratio FEV1 divided by FVC separates the two great patterns: a low ratio means obstruction, as in asthma or COPD, while a preserved ratio with small volumes means restriction, as in fibrosis. Tidal volume is the volume of one ordinary breath, and residual volume is what stays behind after a maximal exhalation.
Pulse oximetry clips a probe to a finger and estimates the percentage of hemoglobin carrying oxygen; that number is charted as SpO2. It is quick, painless and blind to carbon dioxide. An arterial blood gas (ABG) samples arterial blood directly and reports pH, PaO2, PaCO2 and bicarbonate. Only the ABG can diagnose hypercapnia, which is why a patient with normal oximetry can still be in respiratory failure. Capnography (kap-NOG-rah-fee) records exhaled carbon dioxide continuously and is standard during intubation and sedation.
Two more measurement words appear on charts and in patient teaching. A peak flow meter gives a home measurement of maximal expiratory flow, letting an asthma patient track control day to day. Polysomnography (pol-ee-som-NOG-rah-fee) decodes as many + sleep + recording process and is the overnight sleep study that counts apneas and hypopneas to diagnose obstructive sleep apnea.
Imaging, scoping and sampling
Imaging vocabulary is built from familiar suffixes. A chest radiograph or chest x-ray (CXR) is the first study in nearly every respiratory complaint. Computed tomography (CT) of the chest slices the lung far more finely; a CT pulmonary angiogram adds contrast to hunt for pulmonary embolism. A ventilation-perfusion scan, charted as V/Q scan, compares where air goes with where blood goes and is used when contrast cannot be given. Pulmonary angiography images the pulmonary vessels directly.
The endoscopic terms all end in -scopy, and the root tells you where the scope goes. Bronchoscopy (brong-KOS-koh-pee) passes a flexible scope into the bronchi to see, biopsy, wash or retrieve. Laryngoscopy views the larynx, either as a clinic examination or as the step before placing an endotracheal tube. Mediastinoscopy enters the mediastinum through a small suprasternal incision to sample lymph nodes for cancer staging. Thoracoscopy looks inside the pleural cavity.
Sampling terms complete the workup. A sputum culture and sensitivity identifies the organism and the antibiotic that will kill it. An AFB smear looks for acid-fast bacilli, the staining behaviour of tuberculosis. The PPD or tuberculin skin test and the newer interferon-gamma release assay screen for tuberculosis exposure. Thoracentesis (thor-ah-sen-TEE-sis) decodes as chest + surgical puncture and both drains and samples pleural fluid; the laboratory then classifies that fluid as a transudate, driven by pressure, or an exudate, driven by inflammation.
| Procedure | Decode | What it does |
|---|---|---|
| spirometry | spir/o + -metry | measures breathing volumes and flows |
| oximetry | ox/i + -metry | measures oxygen saturation of hemoglobin |
| capnography | capn/o + -graphy | records exhaled carbon dioxide |
| polysomnography | poly- + somn/o + -graphy | overnight sleep study |
| bronchoscopy | bronch/o + -scopy | visual examination of the bronchi |
| laryngoscopy | laryng/o + -scopy | visual examination of the larynx |
| mediastinoscopy | mediastin/o + -scopy | visual examination of the mediastinum |
| thoracoscopy | thorac/o + -scopy | visual examination of the pleural cavity |
| thoracentesis | thorac/o + -centesis | puncture of the chest wall to remove pleural fluid |
| pleural biopsy | pleur/o + bi/o + -opsy | tissue sample of the pleura for examination |
| bronchoalveolar lavage | bronch/o + alveol/o | washing and sampling of distal airways during bronchoscopy |
Respiratory diagnostics splits into what you hear, what you measure and what you image, and the suffix — -metry, -graphy, -scopy, -centesis — tells you which kind of test you are reading about.
Section 5Procedures, Therapies and the Chart
Surgical terms of the airway and chest
Respiratory surgery is where the four operative suffixes finally have to be separated cleanly. -tomy is an incision, a cut made and then closed. -stomy is the creation of an opening intended to stay open. -ectomy is removal. -centesis is a puncture to withdraw fluid. Apply them to the trachea and the difference is immediate: a tracheotomy is the incision into the trachea, while a tracheostomy (tray-kee-OS-toh-mee) is the resulting opening through which a tube breathes for the patient. The words are used loosely in speech; in documentation they are not the same thing.
Apply the same suffixes to the chest wall. A thoracotomy (thor-ah-KOT-oh-mee) is a surgical incision into the chest, the open approach used for major lung surgery. A thoracostomy (thor-ah-KOS-toh-mee) is the creation of an opening for a chest tube, so that air or fluid can drain continuously. A thoracentesis is a needle puncture that drains once and comes out. Three procedures, one root, three different suffixes, three different levels of invasiveness.
Removal terms scale with how much lung is taken. A wedge resection removes a small non-anatomic piece; a segmentectomy removes one bronchopulmonary segment; a lobectomy (loh-BEK-toh-mee) removes an entire lobe; a pneumonectomy (noo-moh-NEK-toh-mee) removes a whole lung. Upper-airway procedures follow the same logic: tonsillectomy and adenoidectomy, often performed together and charted as T&A; septoplasty to straighten a deviated septum; rhinoplasty to reshape the nose; laryngectomy (lair-in-JEK-toh-mee) to remove the voice box for cancer, after which the patient breathes through a permanent neck stoma. Pleurodesis (ploo-ROD-eh-sis) deliberately scars the two pleural layers together so the space cannot refill, and video-assisted thoracoscopic surgery, or VATS, does much of this work through small ports instead of an open thoracotomy.
Airway support, oxygen and drug delivery
When a patient cannot protect or maintain an airway, an endotracheal tube (ETT) is passed through the mouth into the trachea; the act is intubation and its reversal is extubation. The tube is then attached to mechanical ventilation, and the settings carry their own vocabulary: rate, tidal volume, FiO2 for the fraction of inspired oxygen, and PEEP for positive end-expiratory pressure, which holds alveoli open between breaths. Non-invasive ventilation avoids a tube: CPAP delivers one continuous pressure and is standard therapy for obstructive sleep apnea, while BiPAP delivers a higher pressure on inhalation and a lower one on exhalation.
Supplemental oxygen is described by the device and the flow. A nasal cannula delivers low-flow oxygen through two prongs; a simple mask and a non-rebreather mask deliver progressively higher concentrations; high-flow nasal cannula (HFNC) delivers heated, humidified gas at flows that exceed the patient’s own inspiratory demand. In extreme failure, extracorporeal membrane oxygenation (ECMO) oxygenates blood outside the body altogether. Note the shared root: oxygenation, oximetry and hypoxemia are all built on ox/i.
Inhaled medication has its own delivery words. A nebulizer turns liquid drug into a mist breathed in over several minutes. A metered-dose inhaler (MDI) delivers a measured puff, often used with a spacer to improve deposition. A dry powder inhaler (DPI) requires a fast, deep breath instead of a propellant. The drug classes follow the pathology: bronchodilators widen narrowed airways, corticosteroids reduce airway inflammation, mucolytics thin secretions, and antitussives suppress cough — from tussis, Latin for cough, the same root inside pertussis. Supportive therapies include incentive spirometry to prevent postoperative atelectasis, chest physiotherapy with percussion and postural drainage, and pulmonary rehabilitation for chronic disease.
| Procedure or therapy | Decode | What it means |
|---|---|---|
| tracheotomy | trache/o + -tomy | surgical incision into the trachea |
| tracheostomy | trache/o + -stomy | surgically created opening into the trachea |
| thoracotomy | thorac/o + -tomy | surgical incision into the chest wall |
| thoracostomy | thorac/o + -stomy | opening into the chest for a drainage tube |
| lobectomy | lob/o + -ectomy | removal of a lobe of the lung |
| pneumonectomy | pneumon/o + -ectomy | removal of an entire lung |
| septoplasty | sept/o + -plasty | surgical repair of the nasal septum |
| rhinoplasty | rhin/o + -plasty | surgical reshaping of the nose |
| laryngectomy | laryng/o + -ectomy | removal of the larynx |
| tonsillectomy | tonsill/o + -ectomy | removal of the tonsils |
| pleurodesis | pleur/o + -desis | binding of the pleural layers together |
| bronchoplasty | bronch/o + -plasty | surgical repair of a bronchus |
| oxygenation | ox/i + -ation | the process of supplying oxygen |
The abbreviations on a real respiratory chart
Respiratory notes are among the most abbreviation-dense documents in a hospital, partly because so many values are recorded every hour. Expand them mentally as you read, because several look alike and mean very different things. Note in particular that SOB and DOE both mean breathlessness but differ in trigger, that PE in a pulmonary note means pulmonary embolism while in other contexts it can mean physical examination, and that lung-lobe abbreviations use the first letter for side, the second for position: RUL, RML, RLL, LUL, LLL. There is no left middle lobe, because the left lung has only two.
Be careful with abbreviations that official patient-safety lists discourage. Writing O2, CO2 and SpO2 is standard, but sloppy handwriting turns numbers into letters, and units matter: an FiO2 written as a percentage and a decimal fraction are the same idea on two scales. When you are unsure, spell the term out. The rule for the whole book applies with extra force here: an abbreviation is a convenience for the writer and a risk for the reader.
| Abbreviation | Expansion | Note |
|---|---|---|
| ABG | arterial blood gas | the only test that measures PaCO2 directly |
| ARDS | acute respiratory distress syndrome | diffuse alveolar injury with refractory hypoxemia |
| COPD | chronic obstructive pulmonary disease | umbrella for chronic bronchitis and emphysema |
| CPAP / BiPAP | continuous / bilevel positive airway pressure | non-invasive ventilation modes |
| CXR | chest x-ray | first-line chest imaging |
| DOE | dyspnea on exertion | breathlessness brought on by activity |
| ETT | endotracheal tube | placed by intubation |
| FEV1 / FVC | forced expiratory volume in 1 second / forced vital capacity | ratio separates obstruction from restriction |
| FiO2 | fraction of inspired oxygen | room air is 0.21, or 21 percent |
| HFNC | high-flow nasal cannula | heated, humidified high-flow oxygen |
| LLL, LUL, RLL, RML, RUL | lung lobes by side and position | no left middle lobe exists |
| MDI | metered-dose inhaler | often used with a spacer |
| OSA | obstructive sleep apnea | diagnosed by polysomnography |
| PE | pulmonary embolism | clot obstructing pulmonary circulation |
| PEEP | positive end-expiratory pressure | ventilator setting that keeps alveoli open |
| PFT | pulmonary function test | includes spirometry |
| PND | paroxysmal nocturnal dyspnea | sudden night-time breathlessness |
| PPD | purified protein derivative | tuberculin skin test |
| RSV | respiratory syncytial virus | common cause of bronchiolitis in infants |
| SOB | shortness of breath | the plain-language equivalent of dyspnea |
| SpO2 / PaO2 | peripheral oxygen saturation / arterial oxygen partial pressure | different scales, never interchangeable |
| TB | tuberculosis | screened by PPD or IGRA |
| T&A | tonsillectomy and adenoidectomy | frequently performed together |
| URI / LRTI | upper respiratory infection / lower respiratory tract infection | anatomic split at the larynx |
| VATS | video-assisted thoracoscopic surgery | minimally invasive chest surgery |
| V/Q | ventilation-perfusion | scan comparing airflow with blood flow |
The operative suffix, not the root, tells you what was actually done to the airway or chest, and every abbreviation on a respiratory chart should be expandable in your head before you act on it.
The chapter in one breath
Respiratory terminology follows the path of air. Rhin/o and nas/o open at the nose, pharyng/o and laryng/o cross the throat and voice box, trache/o descends the windpipe, bronch/o and bronchiol/o branch, and alveol/o ends at the air sacs where gas exchange happens. Around all of it sit pleur/o, thorac/o and phren/o. Three roots mean lung — pulmon/o, pneumon/o and the slippery pneum/o, which often means air instead. On top of these roots the suffix -pnea builds the entire language of breathing, from eupnea to apnea, tachypnea, orthopnea and dyspnea, while -capnia, -oxia and -emia handle the gases. Pathology sorts into narrowed airways, filled alveoli and occupied pleural space, and the term names the bucket: asthma and bronchiectasis against pneumonia and atelectasis against pneumothorax and empyema. Diagnosis is heard, measured or imaged, marked by -scopy, -metry, -graphy and -centesis. Surgery turns on four suffixes that decide whether the patient leaves with an incision, an opening, a missing lobe or a drained space. Master those distinctions and a respiratory chart reads as ordinary English.
Words worth knowing
| Term | What it means |
|---|---|
| alveolus (pl. alveoli) | microscopic air sac where oxygen and carbon dioxide are exchanged |
| apnea | absence of breathing; a- (without) + -pnea (breathing) |
| atelectasis | collapse or incomplete expansion of alveoli; atel/o + -ectasis |
| bronchiectasis | permanent abnormal dilation of the bronchi |
| bronchoscopy | visual examination of the bronchi with a flexible scope |
| croup | childhood laryngotracheobronchitis with barking cough and stridor |
| dyspnea | difficult or laboured breathing; charted in plain language as SOB |
| emphysema | destruction of alveolar walls with loss of recoil and air trapping |
| empyema | pus within the pleural space; also called pyothorax |
| epistaxis | nosebleed |
| hemoptysis | coughing up blood from the lower airway; hem/o + -ptysis |
| hypercapnia | excess carbon dioxide in the arterial blood |
| hypoxemia | deficient oxygen in the arterial blood; measured directly as PaO2 and estimated by SpO2 |
| orthopnea | breathlessness relieved by sitting or standing upright |
| pleural effusion | abnormal collection of fluid in the pleural space |
| pneumoconiosis | lung disease caused by chronically inhaled dust |
| pneumothorax | air in the pleural space allowing the lung to collapse |
| spirometry | measurement of breathing volumes and flows; core of pulmonary function testing |
| stridor | harsh, high-pitched sound of upper-airway obstruction |
| tracheostomy | surgically created opening into the trachea, kept open by a tube |