Family-Centred Care, Reproductive Health, Equity and Accountability
Maternity and paediatric nursing is the only branch of practice in which the patient arrives attached to another patient, and in which the person who will deliver most of the care after discharge is standing in the room the whole time. That fact reorganises everything: assessment, teaching, consent, escalation and the way you speak. This opening chapter builds the floor the rest of the book stands on. You will meet the four pillars of family-centred care and the language that carries them; you will re-learn reproductive anatomy and the hormonal cycle well enough to explain contraception, infertility and pregnancy dating to a patient; and you will take on the two foundations that decide whether any of that ever reaches the patient in front of you — cultural humility and the social conditions that shape who survives childbearing and who does not, and the law and ethics of consent, confidentiality and the nurse’s own accountability. Everything the later chapters teach about labour, birth, the newborn and the sick child is built on this floor.
By the end of this chapter you can
- Explain the four core concepts of family-centred care — dignity and respect, information sharing, participation and collaboration — and apply atraumatic care and cultural humility to a maternity or paediatric encounter.
- Rewrite blaming clinical language (“failure to progress”, “poor feeder”) into accurate, non-blaming description, and use inclusive terms such as birthing parent and chestfeeding where they fit the situation.
- Apply the five rights of delegation and state which tasks stay with the RN — assessment, teaching, evaluation and any unstable patient.
- Describe the ovarian and endometrial cycles, the FSH/LH/oestrogen/progesterone sequence and the timing of ovulation, outline spermatogenesis and its 64-to-74-day interval, and use Nägele’s rule to date a pregnancy.
- Tier contraceptive methods by typical-use effectiveness, identify absolute contraindications to combined hormonal contraception, and counsel on emergency contraception within its time windows.
- Recognise primary and secondary dysmenorrhoea, endometriosis and polycystic ovary syndrome, classify abnormal uterine bleeding with PALM-COEIN, outline the infertility work-up beginning with a semen analysis, and describe routine sexually transmitted infection and cervical screening and preconception care including folic acid dosing.
- Distinguish cultural competence from cultural humility, trace how the social determinants of health reach a maternity or paediatric bedside, and explain disparities in maternal mortality, preterm birth and infant mortality as consequences of structural racism and unequal access rather than of race itself.
- Work with a trained interpreter correctly, apply trauma-informed principles, recognise how implicit bias turns a dismissed report of pain into a preventable death, and escalate on the patient’s own concern using SBAR with a named red flag and a specific request.
- State what makes consent informed, describe decision-making capacity as understanding, appreciation, reasoning and the communication of a consistent choice and distinguish it from agreement, separate the nurse’s role as witness from the provider’s duty to obtain it, uphold the right to refuse — including in pregnancy — and apply confidentiality, documentation, scope-of-practice and mandatory reporting duties to a maternity or paediatric encounter.
Section 1The Family as the Unit of Care
The four pillars, and what each one looks like at 3 a.m.
Family-centred care rests on four concepts that are easy to recite and hard to practise. Dignity and respect means you build the plan around what this family values, not around what the last family valued. Information sharing means you give complete, unfiltered, timely information in language the family can actually use — a parent who is told the potassium is 2.9 mmol/L and nothing else has been informed of nothing. Participation means the family chooses the level of involvement they want, which may be more than you expected or less. Collaboration means families are consulted about unit policy, discharge design and their own child’s plan, not merely about which arm you take blood from.
At the bedside these translate into concrete behaviours. Sit down. Use the child’s name and the parents’ names, and ask what the child is called at home. Ask the parent what they are noticing — parents detect deterioration before monitors do, and a parent saying “he is not himself” is a clinical finding you document and act on, not reassurance you dispense. Offer family presence during procedures and, where unit policy permits, during resuscitation; the evidence is that presence does not impair the team and reduces long-term parental distress, provided a designated staff member stays with the family to narrate what is happening.
Family structure is whatever the family says it is: two parents, one parent, grandparents raising grandchildren, blended households, same-sex parents, foster and kinship carers, a birthing person with a doula and no partner. Document the actual caregivers and who holds legal decision-making authority, because those two are not always the same person. Ask, do not assume, who may receive clinical information.
Atraumatic care and the language we use
Atraumatic care means minimising physical and psychological distress from the care itself. Practically: cluster painful procedures, do them in a treatment room rather than in the child’s bed so the bed stays a safe place, use topical anaesthetic for planned venepuncture, offer sucrose and non-nutritive sucking for neonatal procedural pain, allow a parent to hold the infant skin-to-skin during heel sticks, and let a preschooler make real choices about things that are genuinely optional (which arm, which plaster) while never offering a false choice about something that must happen.
Language is a clinical intervention. The phrase failure to progress assigns blame to a person for the behaviour of a uterus; describe the labour pattern instead — “cervical change from 5 to 6 cm over four hours with adequate contractions”. A newborn is not a “poor feeder”; the observation is “latch is shallow, transfers 5 mL in 20 minutes, tires at the breast”. A parent is not “non-compliant”; the finding is “has missed two appointments, reports no transport and no childcare”, which is a problem a nurse can solve. Use birthing parent and chestfeeding where they fit and mother and breastfeeding where they fit; ask the patient which words they use, record it, and use it consistently.
Trauma-informed practice belongs in the same paragraph. A substantial proportion of birthing patients have a history of sexual trauma, and the intimate examinations of maternity care can re-trigger it, so care is delivered on the assumption that trauma may be present. Section 4 sets out the principles and the practical rules that follow from it.
Consent, assent and who may sign
A minor generally cannot give legal consent; a parent or guardian gives permission and the child gives assent, which is expected from about seven years of age and involves developmentally appropriate explanation and a genuine willingness to proceed. Emancipated minors (married, in military service, living independently, or so declared by a court) consent for themselves. A mature minor is one whom a clinician or a court judges to have sufficient maturity to consent to a particular treatment, and mature-minor provisions and category-specific statutes extend independent consent further. Every United States jurisdiction allows a minor to consent to diagnosis and treatment of sexually transmitted infections, though the ages and conditions differ; consent for contraception, pregnancy care and mental health or substance use care varies far more widely by jurisdiction, so you must know your own. In a true emergency, consent for life-saving treatment is implied.
Delegation and what stays with the RN
| Task | RN responsibility | May be delegated to LPN/LVN | May be delegated to UAP |
|---|---|---|---|
| Initial and ongoing assessment; interpreting findings | Yes (non-delegable) | No (may collect data and report) | No |
| Patient and family teaching; evaluating understanding | Yes (non-delegable) | May reinforce teaching the RN has already given; the RN evaluates understanding | No |
| Care of the unstable patient or the patient whose status is changing | Yes (non-delegable) | No | No |
| Evaluating response to an intervention | Yes (non-delegable) | No | No |
| Fundal assessment and evaluation of lochia (the vaginal discharge that follows birth) in the first 24 hours | Yes (non-delegable) | No (may report what is observed while giving care) | No |
| Interpreting fetal heart rate patterns (the continuous tracing of the baby’s heart rate in labour); titrating oxytocin or magnesium (infusions adjusted against the patient’s minute-to-minute response) — both taken up in the labour and birth chapter | Yes (non-delegable) | No | No |
| Vital signs, intake and output, daily weights on a stable patient | — | Yes | Yes |
| Bathing, positioning, feeding an established stable feeder, ambulation | — | Yes | Yes |
| Oral and most routine medications | — | Yes (route rules vary by state) | No |
| IV push medication; blood product administration | Yes (non-delegable in most jurisdictions) | No, unless the state nurse practice act expressly permits it | No |
Apply the five rights of delegation every time: right task, right circumstance, right person, right direction and communication, right supervision and evaluation. Delegating a vital sign set is safe on a stable postpartum patient at hour 20; the identical task is not safe at hour two on a patient with a boggy fundus — a uterus that feels soft rather than firm, meaning it is not clamping its own vessels shut — because the value needs interpreting in real time by the person accountable for the outcome. Note also that assessment, teaching, evaluation and the unstable patient are the memorable core rather than the whole list: your jurisdiction’s medication and monitoring rules decide which further tasks are non-delegable, and in most jurisdictions titrating oxytocin or magnesium, and giving IV push medication or a blood product, are among them.
In maternity and paediatrics the family is the unit of care and the permanent care team, so the RN’s non-delegable work — assessment, teaching, evaluation and the unstable patient — is also the work that determines what happens after discharge.
Section 2Reproductive Anatomy and the Menstrual Cycle
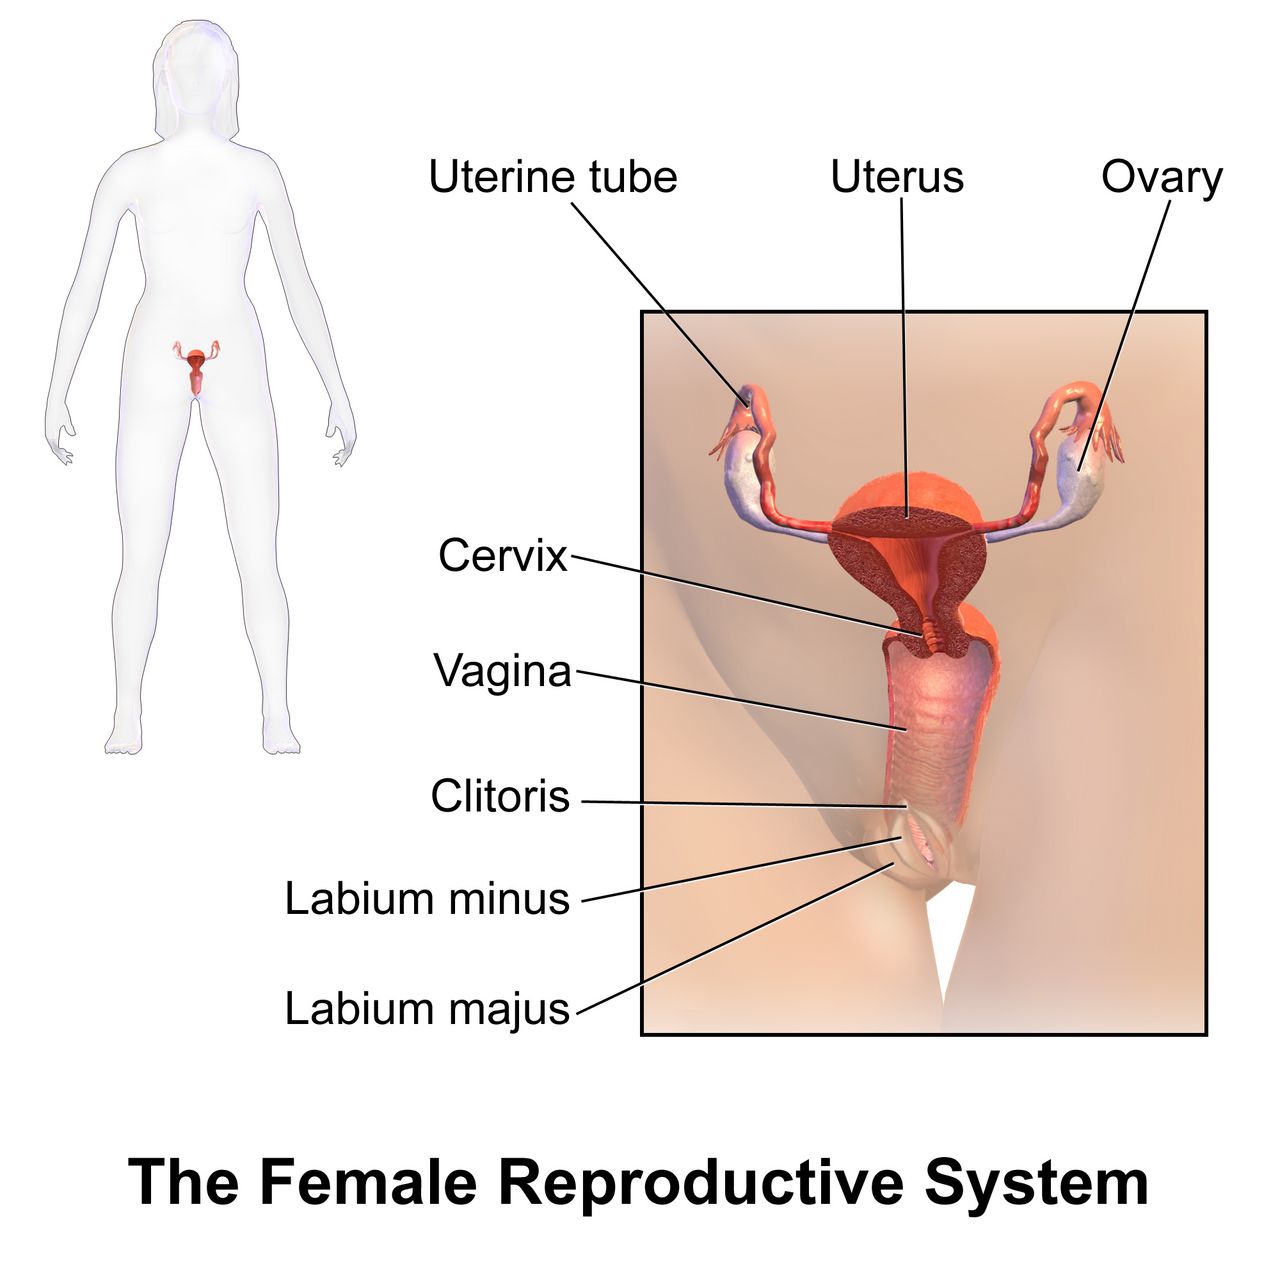
Structures, and why each one matters clinically
The uterus has three layers. The endometrium is the functional lining that thickens, secretes and sheds each cycle and is the bed the blastocyst implants into. The myometrium is three interlacing layers of smooth muscle; the middle layer wraps figure-of-eight fibres around the radial and arcuate vessels that run through the muscle wall, so when it contracts after birth it clamps those vessels shut. The muscle is in that sense a living ligature, and a uterus that stays soft is a uterus that is not compressing its own vessels — what is done about that when bleeding follows a birth belongs to the postpartum and obstetric-emergency chapters. The perimetrium is the outer serosa.
The uterine tube runs from the fimbriae, which sweep the ovulated ovum from the peritoneal surface, through the wide ampulla where fertilisation normally occurs, then the narrow isthmus and the interstitial segment through the uterine wall. Ciliary motion and peristalsis move the zygote to the uterus over roughly three to four days. Anything that scars the tube — pelvic inflammatory disease, endometriosis, previous tubal surgery — slows that transit and raises the risk of an ectopic implantation.
The cervix is a fibrous canal with an internal and external os, lined by mucus that is thick and hostile for most of the cycle and thin, alkaline and stretchy around ovulation. Pelvic architecture and clinical pelvimetry matter at birth rather than here, and are taken up in the labour and birth chapter.
On the male side, spermatogenesis takes roughly 64 to 74 days from spermatogonium to mature sperm, and the testes sit outside the body because that process needs a temperature about 2 to 3 °C below core. LH stimulates Leydig cells to make testosterone; FSH acts on Sertoli cells to support sperm maturation. That 64-to-74-day production cycle is why an abnormal semen analysis — the first test in an infertility work-up, later in this chapter — is repeated after about three months rather than immediately: a sample taken sooner still reflects the same batch of sperm. Sperm remain viable in the female tract for up to five days; the ovum is fertilisable for only 12 to 24 hours. That asymmetry is why the “fertile window” is the five days before ovulation plus the day of ovulation, and why fertility-awareness methods must predict ovulation in advance rather than detect it afterwards.
The ovarian cycle: FSH, LH and the surge
Pulsatile GnRH from the hypothalamus drives anterior pituitary release of FSH and LH. In the follicular phase, FSH recruits a cohort of follicles; one becomes dominant and its granulosa cells secrete rising oestradiol. Early on, oestradiol feeds back negatively and holds LH down. Once oestradiol is high and sustained for roughly two days, the feedback flips to positive and triggers the LH surge. Ovulation follows about 24 to 36 hours after the surge begins, roughly 10 to 12 hours after the LH peak — which is exactly what a urinary LH predictor kit detects, and why the kit tells a couple to have intercourse now rather than tomorrow.
The endometrial cycle runs underneath in lockstep: menstrual shedding, then the oestradiol-driven proliferative phase that regrows the functional layer during the follicular phase, then the progesterone-driven secretory phase after ovulation. The ruptured follicle becomes the corpus luteum and secretes progesterone, which raises basal body temperature by about 0.3 to 0.6 °C and converts the endometrium to that secretory, implantation-ready surface. If fertilisation does not occur, the corpus luteum involutes after a remarkably fixed 14 ± 2 days, progesterone and oestrogen fall, the spiral arterioles constrict, the functional layer becomes ischaemic and sheds. If implantation does occur, trophoblastic hCG rescues the corpus luteum, which sustains the pregnancy until the placenta takes over hormone production at around 8 to 10 weeks.
Because the luteal phase is fixed and the follicular phase is variable, cycle-length differences come from the follicular phase. A person with a 35-day cycle ovulates around day 21, not day 14 as the 28-day assumption would predict. Teach it this way — ovulation is 14 days before the next period, not 14 days after the last one — and both contraception counselling and infertility timing become intuitive.
| Parameter | Typical range | Why the nurse cares |
|---|---|---|
| Age at menarche | 12–13 years (normal 9–15) | No menses by 15 with breast development, or by 13 with none, warrants evaluation |
| Cycle length | 24–38 days (average 28) | Outside this range is abnormal uterine bleeding, not “just irregular” |
| Duration of flow | 8 days or less | More than 8 days suggests anovulation, fibroids or a bleeding disorder |
| Blood loss per cycle | 5–80 mL | Soaking a pad or tampon hourly for 2 or more hours is heavy bleeding — check haemoglobin and ferritin |
| Luteal phase length | 14 ± 2 days (fixed) | Anchors ovulation timing and pregnancy dating |
| Age at menopause | Average 51 (normal 45–55) | Diagnosed retrospectively after 12 consecutive months without menses |
Reading the cycle at the bedside
Three findings let a patient track their own cycle. Cervical mucus shifts from scant and tacky to abundant, clear and stretchy at ovulation — spinnbarkeit, stretching 6 cm or more between the fingers, and ferning in a dried smear under the microscope, both driven by oestrogen. Basal body temperature taken before rising each morning steps up after ovulation under progesterone and stays up; it confirms ovulation has happened but cannot predict it, which is why BBT alone is a poor contraceptive. Mittelschmerz, a brief unilateral mid-cycle pelvic pain, marks follicular rupture in some people.
Anything that disrupts pulsatile GnRH stops the cycle: significant weight loss, low energy availability in athletes and high stress produce functional hypothalamic amenorrhoea. That label is a diagnosis of exclusion — thyroid disease and hyperprolactinaemia are separate endocrine causes of amenorrhoea and must be ruled out first with a TSH and a prolactin level, with pituitary imaging if the prolactin is raised. The nursing point is that amenorrhoea in an adolescent athlete is not a training success — it belongs to the female athlete triad with low energy availability and low bone density, and it needs nutrition and endocrine evaluation.
Ovulation occurs 14 days before the next menses, driven by an oestrogen-triggered LH surge; the fixed 14-day luteal phase is what makes cycle tracking, pregnancy dating and contraceptive counselling calculable.
Section 3Menstrual Disorders, Contraception and Fertility
Menstrual disorders and common gynaecological conditions
Primary dysmenorrhoea is prostaglandin-mediated cramping that begins with ovulatory cycles in adolescence, peaks in the first 24 to 48 hours of flow and has no underlying pathology. NSAIDs are first line and work best when started at the first sign of bleeding or 24 to 48 hours before it, because they inhibit prostaglandin synthesis rather than block prostaglandin already made. Heat, exercise and combined hormonal contraception all help. Secondary dysmenorrhoea starts later, worsens over time and points to endometriosis, adenomyosis, fibroids or pelvic inflammatory disease.
Endometriosis is endometrial-like tissue outside the uterus that bleeds cyclically into a closed space, producing the classic triad of dysmenorrhoea, dyspareunia and infertility, often with dyschezia. Diagnosis has historically required laparoscopy, and the average delay from symptom onset to diagnosis is measured in years — largely because adolescents reporting severe period pain are told it is normal. Believe them and refer. Polycystic ovary syndrome is diagnosed by the Rotterdam criteria when two of three are present: oligo- or anovulation, clinical or biochemical hyperandrogenism, and polycystic ovarian morphology on ultrasound. In adolescents that third limb does not apply: multifollicular ovaries are physiological after menarche, so neither ovarian morphology nor anti-Müllerian hormone may be used to diagnose PCOS within 8 years of menarche — in that window both irregular cycles and hyperandrogenism are required, and everyone else is designated “at risk” and re-assessed later. It carries insulin resistance, so screening for impaired glucose tolerance and counselling on weight-neutral metabolic health matter as much as cycle regulation.
Abnormal uterine bleeding is classified by PALM-COEIN: structural causes are Polyp, Adenomyosis, Leiomyoma and Malignancy; non-structural are Coagulopathy, Ovulatory dysfunction, Endometrial, Iatrogenic and Not otherwise classified. In an adolescent with very heavy bleeding from menarche, think coagulopathy — von Willebrand disease is present in a meaningful minority and is routinely missed.
Contraception: counsel by effectiveness tier
| Tier | Method | Typical-use failure per year | Key teaching or caution |
|---|---|---|---|
| Tier 1 — most effective | Etonogestrel implant | Under 1 in 100 (about 0.1%) | Subdermal, now approved for up to 5 years of use (originally 3) — check the current label for the product in use; irregular spotting is the top reason for removal, so pre-counsel it |
| Levonorgestrel IUD | Under 1 in 100 | 3–8 years by product; lightens or stops bleeding, useful for heavy menses | |
| Copper IUD | Under 1 in 100 | 10 years; hormone-free but heavier, crampier periods; also the emergency contraceptive with the longest evidence base | |
| Tubal ligation / vasectomy | Under 1 in 100 | Considered permanent; vasectomy needs a confirmatory semen analysis before relying on it | |
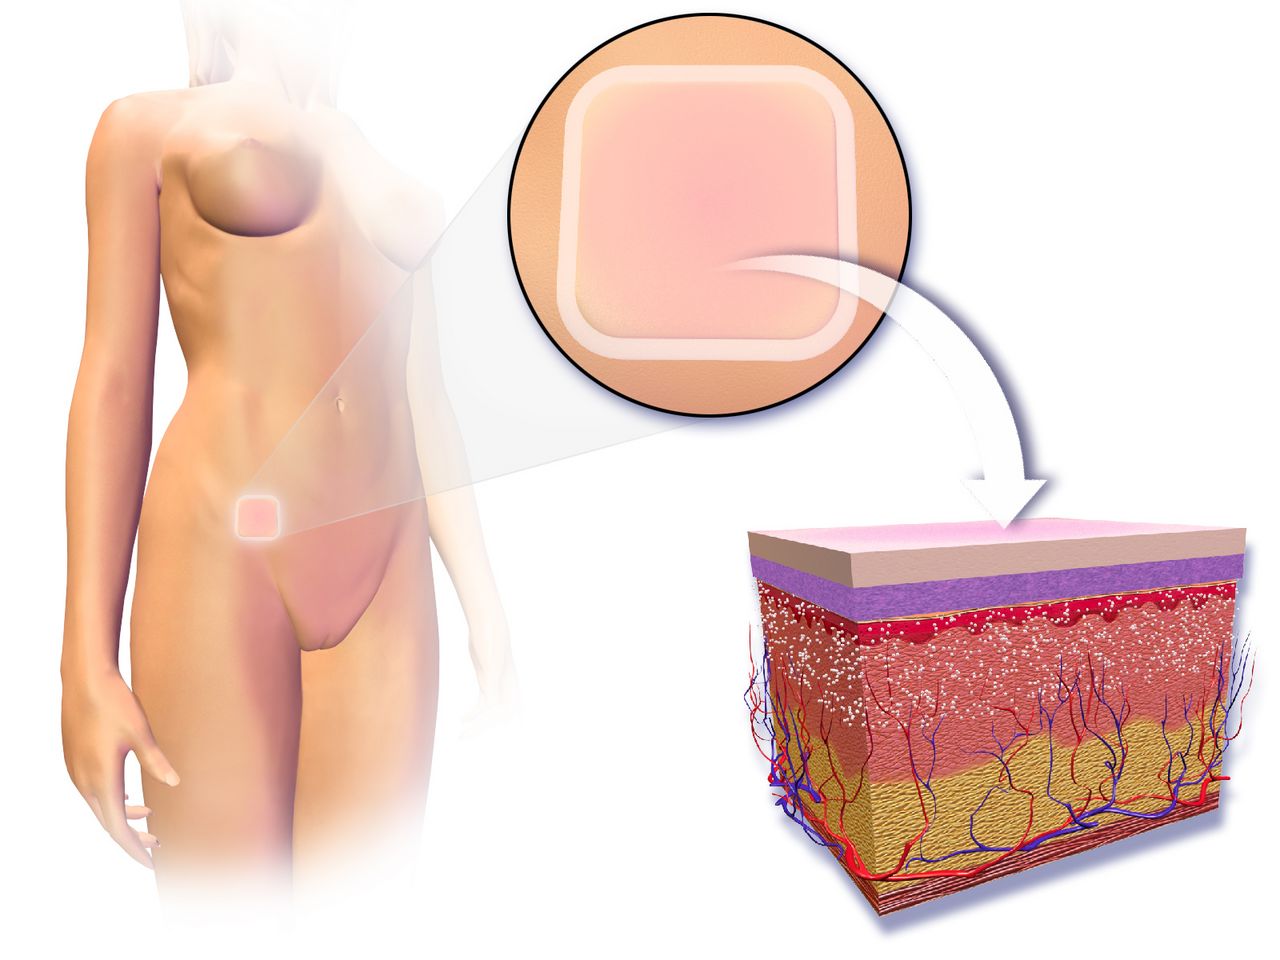
| Tier 2 — effective if used consistently | Combined pill, patch, ring | About 7 in 100 | Oestrogen-containing; screen contraindications; patch changed weekly, ring monthly |
| Progestin-only pill | About 7 in 100 | No oestrogen, so usable where combined methods are contraindicated; timing-sensitive — the traditional norethindrone pill must be taken within the same 3-hour window daily | |
| Depot medroxyprogesterone acetate | About 4–6 in 100 | 150 mg IM or 104 mg SC every 13 weeks; reversible bone density loss — ensure calcium and vitamin D | |
| Tier 3 — least effective | External condom | About 13 in 100 | Only method that also reduces STI transmission; no oil-based lubricants with latex |
| Withdrawal | About 20 in 100 | Requires perfect control every single time | |
| Fertility-awareness methods | About 11–23 in 100 by method | Needs regular cycles, daily tracking and abstinence or backup during the fertile window |
Combined hormonal contraception is contraindicated whenever the oestrogen’s cardiovascular risk outweighs the benefit: age 35 or older and smoking at all — generally avoid at any daily amount, and an absolute contraindication at 15 or more cigarettes daily; migraine with aura at any age; personal history of venous thromboembolism or known thrombophilia; major surgery with prolonged immobilisation; a history of ischaemic heart disease or of stroke; complicated valvular heart disease (pulmonary hypertension, atrial fibrillation, a history of subacute bacterial endocarditis); peripartum cardiomyopathy; systemic lupus erythematosus with positive or unknown antiphospholipid antibodies; diabetes with nephropathy, retinopathy, neuropathy or other vascular disease, or of more than 20 years’ duration; uncontrolled hypertension — systolic 160 mmHg or above or diastolic 100 mmHg or above, either value on its own being enough; active liver disease; current breast cancer; and the first 21 days postpartum, with the method also generally avoided from 21 to 42 days postpartum when any additional venous thromboembolism risk factor is present (obesity, caesarean birth, haemorrhage or transfusion, pre-eclampsia, immobility, smoking). The mechanisms behind that list are not all the same, and separating them is what makes it memorable rather than arbitrary. Four entries are thrombotic: previous venous thromboembolism or thrombophilia, major surgery with immobilisation, the postpartum window, and systemic lupus erythematosus with positive or unknown antiphospholipid antibodies, which carry a thrombotic risk in the venous and the arterial bed alike. Six are arterial — migraine with aura, smoking at 35 or older, uncontrolled hypertension, established ischaemic heart disease or stroke, complicated valvular disease and long-standing or vascular diabetes all raise the risk of ischaemic stroke and myocardial infarction, not of clot in a vein. The remaining three turn on neither: current breast cancer is a hormone-responsive tumour, active liver disease is a question of hepatic metabolism and decompensation, and peripartum cardiomyopathy is a question of cardiac function — a ventricle that is already failing does not tolerate the added thrombotic and volume load. Teach the ACHES warning signs to every patient who starts one — Abdominal pain, Chest pain or shortness of breath, Headache that is severe or new, Eye changes or visual loss, Severe leg pain or swelling — and tell them to stop the method and seek care rather than wait for the next appointment.
Fertility, infection and preventive screening
Infertility is 12 months of regular unprotected intercourse without conception, or 6 months if the person with ovaries is 35 or older, or immediately when there is known pathology such as amenorrhoea or bilateral tubal disease. Causes distribute roughly evenly — about a third female factor, about a third male factor, and the remainder combined or unexplained — so evaluate both partners together. The first test is a semen analysis, because it is cheap, fast and non-invasive, and it is unreasonable to put one partner through a hysterosalpingogram before the other has produced a sample. Ovarian reserve is assessed with day-3 FSH and anti-Müllerian hormone; tubal patency with hysterosalpingography. Infertility care is grief work as much as procedure work: name the losses, ask about the treatment burden, and screen for depression.
Sexually transmitted infection screening is a routine nursing responsibility. Screen for chlamydia and gonorrhoea annually in all sexually active women under 25 and in older women with risk factors; screen for HIV at least once for everyone aged 15 to 65 on an opt-out basis; screen for HIV, syphilis, hepatitis B and hepatitis C at the first prenatal visit in every pregnancy, repeat syphilis at about 28 weeks and again at delivery for every pregnant patient, and repeat HIV in the third trimester where risk or local prevalence indicates. Chlamydia in a non-pregnant adult is treated with doxycycline 100 mg orally twice daily for 7 days; azithromycin 1 g as a single dose is used in pregnancy, with a test of cure 4 weeks after treatment in pregnancy and retesting of everyone at about 3 months. Gonorrhoea is treated with ceftriaxone 500 mg IM as a single dose (1 g IM at 150 kg or more), plus doxycycline 100 mg orally twice daily for 7 days if chlamydial infection has not been excluded — azithromycin 1 g in pregnancy. Syphilis is treated with benzathine penicillin G (Bicillin L-A, never the combination Bicillin C-R, a dispensing error that undertreats): 2.4 million units IM as a single dose for primary, secondary or early latent disease, and 2.4 million units IM weekly for 3 doses for late latent syphilis or latent syphilis of unknown duration; in pregnancy with early syphilis a second dose one week later is recommended. And a pregnant patient with a penicillin allergy must be desensitised and given penicillin, because no alternative reliably treats the fetus.
Cervical cancer screening begins at 21 regardless of sexual debut. From 21 to 29, cytology every 3 years; from 30 to 65, cytology every 3 years, primary HPV testing every 5 years, or co-testing every 5 years. HPV vaccination is routine at ages 11 to 12, may start at 9, and is a two-dose series if begun before the 15th birthday and a three-dose series if begun at 15 or later or if immunocompromised. Preconception care is the highest-yield visit in obstetrics: start folic acid 400 micrograms daily at least one month before conception and continue through the first trimester, or 4 mg daily for someone with a previous neural-tube-defect-affected pregnancy; confirm rubella and varicella immunity and vaccinate before conception, since these are live vaccines — give them at least 4 weeks before conception and advise reliable contraception for those 28 days, and if non-immunity is found during pregnancy, defer and vaccinate immediately postpartum, which is compatible with breastfeeding; optimise glycaemic control toward an HbA1c below 6.5%; and review medications for teratogens including isotretinoin, ACE inhibitors and ARBs, warfarin and valproate.
Counsel contraception by typical-use effectiveness tier and screen every oestrogen-containing method against the absolute contraindications, and start folic acid before conception rather than after the pregnancy test — the neural tube closes by 28 days after conception, about 6 weeks from the LMP — roughly two weeks after the first missed period, and usually before the pregnancy has been confirmed or a first antenatal visit has happened.
Section 4Cultural Humility, Equity and the Social Determinants of Maternal-Child Health
Humility is the practice; competence is the illusion
Cultural competence treats culture as a syllabus: learn what “this group” believes about birth, and you are finished. It reliably produces the nurse who has memorised a list and applies it to a patient who does not recognise herself in it — stereotyping with a certificate attached. Cultural humility begins from the opposite premise: you cannot finish learning a person, so you ask, and keep asking. Its three parts are lifelong examination of your own assumptions, deliberate correction of the power imbalance between the person in the uniform and the person in the gown, and accountability to the communities you serve.
At the bedside that converts statements into questions. Ask who this family wants in the room and who kept out; what they eat, avoid or need warm after birth; whether the placenta is kept; when a child is named; and who actually makes decisions, which is not always the person doing the talking. Record the answers so the family is not re-interviewed every shift, and honour what you were told unless it is unsafe — where it is unsafe, negotiate the smallest possible change rather than issuing a prohibition.
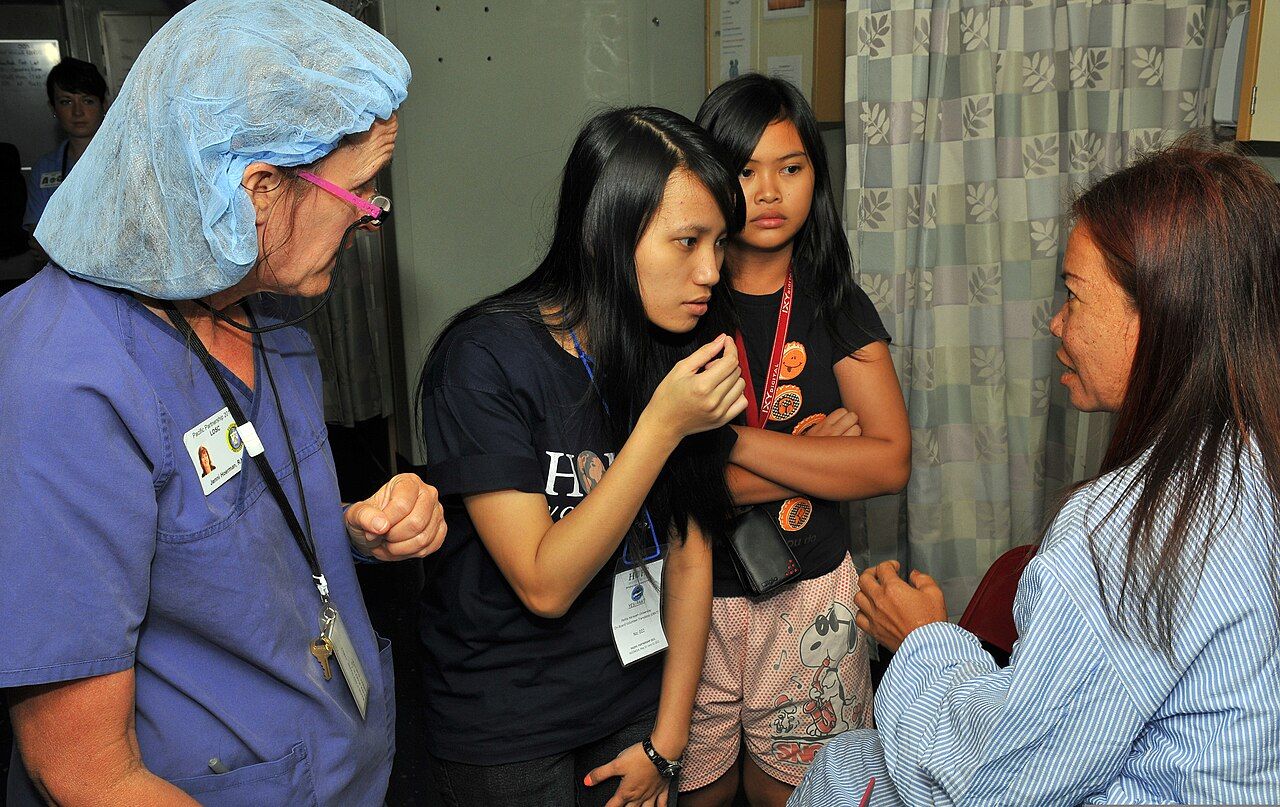
Working across language is the same discipline with a legal floor beneath it: in facilities receiving federal funding, meaningful language access is a civil rights obligation, and clinically it is the difference between a consent and a signature. Use a trained interpreter whenever the patient’s preferred language for health care is not yours, and for the whole encounter — consent, medication teaching and discharge instructions, not merely the history. The interpreter may be in person, by video or by telephone. Never a family member, and never a child. Relatives edit: they soften a prognosis, omit the questions about sexual history and intimate partner violence, and answer on the patient’s behalf. A child asked to interpret her mother’s miscarriage is harmed by the task itself.
Many patients here carry a history of trauma, and this specialty is full of what reawakens it: intimate examination, loss of control, pain, exposure, being spoken about rather than to. Trauma-informed care does not require you to know the history; it asks you to assume it may be present and to deliver care that does not add to the injury. Its principles are safety, trustworthiness and transparency, peer support, collaboration and mutuality, empowerment through voice and choice, and attention to cultural, historical and gender issues. In practice: explain before you touch and ask permission every time rather than once, offer real choices about position and pace, stop when asked and mean it, and read the frightened or “difficult” patient as a nervous system doing what it learned to do.
The social determinants arrive with the patient
The social determinants of health — economic stability, education, health care access, neighbourhood and built environment, and social and community context — are the conditions in which people are born, grow, work, live and age. In this specialty they are not background colour. They help set birth weight; they decide whether the antibiotic is collected, whether the baby has a safe surface to sleep on, whether the immunisation is given on time, and whether the patient comes back at all. They explain most of what gets recorded as non-adherence.
So the language discipline from Section 1 earns its keep: a parent who has missed two appointments has a barrier, not a character flaw, and barriers are solvable by nurses in a way that character flaws are not. Ask about the determinants as you would anything else clinical — but observe the rule that separates screening from voyeurism: never ask about a need you have no route to address. Two specifics are worth carrying. A family stretching a tin of formula with extra water is a cause of hyponatraemic seizures, so the answer to a family who cannot afford formula is exact mixing instructions and a same-day referral for supply, never a warning. And Medicaid pays for roughly four in ten United States births, with postpartum coverage that once ended at 60 days now extendable to twelve months in most states — confirm coverage and book the postpartum contact before discharge. The table below sets out those same five domains in the forms a nurse actually meets, which is why it runs to more rows than there are domains: income and employment and food security sit inside economic stability, and housing and transport inside neighbourhood and built environment.
| Determinant | How it shows up in maternity or paediatrics | What the nurse does about it |
|---|---|---|
| Income and employment | No paid leave, early return to work, milk supply falls, medicine competes with rent | Ask about leave at the first postpartum contact; refer to social work; teach expression and storage |
| Housing | No safe sleep surface, overcrowding, damp and pests driving asthma, lead in older housing | Ask where the baby sleeps; arrange a cot; screen for lead on schedule; refer to a housing navigator |
| Food security | Anaemia in pregnancy, formula stretched with water, the parent skipping meals first | Screen with the two-question Hunger Vital Sign — worried the food would run out, and the food bought did not last; refer to WIC and SNAP; teach exact mixing, never dilution |
| Transport | Missed antenatal, postnatal and well-child visits, recorded as non-adherence | Chart the barrier as the reason; arrange the transport benefit; consolidate visits; offer telehealth |
| Education and health literacy | Instructions given at a reading level nobody checked | Plain language, teach-back, written material in her language, pictures for dosing |
| Health care access and insurance | Coverage gaps after birth, no usual source of care, long waits for the postpartum visit | Confirm coverage; book the postpartum contact before discharge; teach the warning signs to everyone |
| Neighbourhood and built environment | Pharmacy and grocery deserts, unsafe streets, poor air quality | Check the prescription can be filled nearby; prefer once-daily options; ask before advising exercise |
| Social and community context | Isolation, intimate partner violence, discrimination, fear related to immigration status | Screen privately with the patient alone; have the advocate’s number before you ask |
Disparities are produced, and bias is how they reach the bedside
In the United States, Black birthing people die of pregnancy-related causes at roughly three times the rate of white birthing people, and American Indian and Alaska Native people are also substantially over-represented; preterm birth is about half again as common among Black birthing people, and Black infants die in the first year at more than twice the rate of white infants. Severe maternal morbidity — surviving an event that could have killed you, such as massive transfusion, eclampsia or intensive care admission — follows the same pattern and affects many times more patients than death does.
The tempting explanation is poverty, and it is insufficient: the gap does not close at the top of the income or education distribution, where a Black patient with a degree, a job and insurance still fares worse than a white patient with none of those. Race is a social category, not a biological one, and no gene produces a difference of that size. What produces it is structural racism and unequal access — delivery concentrated in lower-resourced hospitals, different treatment inside the same hospital by the same staff, the physiological cost of living with discrimination, and generations of policy deciding which neighbourhoods received clinics, groceries, clean air and mortgages. Teach it, and chart it, as an exposure rather than an attribute. Two findings make it actionable: state review committees judge more than four in five pregnancy-related deaths preventable, and most occur after the birth, roughly a third between six weeks and one year — so the postpartum period is not one visit at six weeks.
Implicit bias carries all of this into a single room: automatic associations operating outside awareness that can contradict what you sincerely believe. It shows itself most reliably in pain — patients of colour are less likely to be offered analgesia for the same presentation, and in one widely cited study half of a sample of white medical students and residents endorsed at least one false belief about biological differences in how Black and white patients feel pain. The failure mode is repeatable: a patient says something is wrong, the observations are near enough to normal, the report is written down as anxiety, and the next contact is the emergency department.
So take her report as a clinical finding and document it verbatim in quotation marks. Perform the assessment the symptom demands rather than the one the chart’s labels suggest. Escalate on the concern and not only the number, using SBAR — Situation, Background, Assessment, Recommendation — to name the red flag and make a specific, time-bound request. In one sentence: “Twelve days postpartum, calling about a headache (situation); normal pressures at discharge and a note describing her as anxious (background); three days of headache that paracetamol is not touching, and she says she knows something is wrong (assessment); I want her seen today with a blood pressure, a urine protein and bloods (recommendation).” Ask whether you would arrange this same assessment for a different patient. Teach the urgent maternal warning signs before discharge — a headache that will not go away, visual change, chest pain or breathlessness, seizure, fever, heavy bleeding, swelling or pain in one leg, and thoughts of harming herself or the baby — and know the referral routes, because advocacy that stops at sympathy is not advocacy.
Cultural humility asks rather than assumes and a trained interpreter is a clinical requirement rather than a courtesy; the racial gaps in maternal mortality, preterm birth and infant mortality are produced by structural racism and unequal access rather than by race — which is why a patient’s own report of pain or of something being wrong is data you document verbatim and act on, not anxiety you reassure.
Section 5Consent, Confidentiality and the Nurse’s Role
What makes consent informed, and what your signature says
Consent is a conversation; the form is only its receipt. It is informed when the patient has been told, in language she genuinely understands, the diagnosis or nature of the problem; what is proposed and why; the material risks and expected benefits; the reasonable alternatives with their own risks; and what happens if nothing is done. She must also know that the decision is voluntary and revocable at any point — including after the form is signed. A signature without those elements is paper, not consent, and it protects nobody.
Two conditions sit underneath. She must have capacity, and the information must actually reach her — a trained interpreter if her preferred language is not yours, the form read aloud if she cannot read. Timing matters as much as content: consent taken after an opioid or a sedative, or from a patient in severe pain, is fragile at best, so planned procedures are discussed while she is comfortable and unhurried. In a genuine emergency, where delay would threaten life or limb and no decision-maker is reachable, consent is implied; document the emergency and the attempts you made.
Now the distinction students most often get wrong. The duty to obtain consent belongs to the clinician performing the procedure and cannot be handed to nursing. When the nurse signs she is witnessing three narrow things: that the signer is who she says she is, that the signature is voluntary, and that she appeared to have capacity. She is not attesting that the patient understood the medicine. The real work happens before the pen moves — ask her to say in her own words what will be done and why, and whether she knows any alternative including doing nothing. If the answer is wrong, vague or absent, stop, do not have her sign, and call the clinician back. That is not obstruction; it is the only mechanism the system has for catching a consent that never took place.
Autonomy, refusal and the adolescent patient
The right to refuse follows from the right to consent, and it is the harder half. A patient with capacity may decline any recommended treatment, and the pregnant patient is no exception: she remains the decision-maker for her own body through pregnancy, labour and birth. Professional guidance in obstetrics is explicit that coercion — threats, court orders, child-protection referral used as leverage — is ethically unjustified in all but the rarest circumstances, and it drives patients out of antenatal care, falling hardest on those already described in Section 4. Keep the relationship: explore what the refusal is really about, offer alternatives, and make clear she may change her mind. Then document the recommendation, the risks explained, her decision in her own words, that the refusal was informed, and that care is still offered. Escalate to an ethics consultation, not a judge.
Adolescent care adds a second axis: Section 1 covered who may consent, and the question here is who may be told. Every United States jurisdiction allows a minor to consent to diagnosis and treatment of sexually transmitted infections, though ages and conditions differ; consent for contraception, prenatal care and mental health or substance use care varies far more widely, and abortion law differs by state and keeps changing — so know your own jurisdiction rather than recite a national answer. Where she lawfully consents she generally controls that part of the record, and a parent is not automatically entitled to it.
Two habits follow. Interview every adolescent alone for part of every visit, so that it reads as routine rather than as suspicion of the family. And state the limits of confidentiality before she tells you anything: what she says stays between you except where someone is being hurt or she is at risk of serious harm. Promise only what you can keep, and warn her that an explanation-of-benefits statement mailed to the policyholder can disclose the very visit confidentiality was meant to protect. Tell her in advance and offer what workarounds exist: a confidential-communication request to the insurer, care through a Title X or school-based clinic, or self-payment.
Privacy, documentation and the duties that stay with you
Privacy here is unusually hard because the room is unusually full. The patient decides who receives information about her — her partner, her mother, the baby’s other parent, the friend at the door. Ask on admission who may be told what and who may visit, record it, and follow it without editorialising; in maternity, one reason a patient gives no reason is that the person asking is the source of the harm. Offer exclusion from the facility directory, and watch the ordinary leaks: the whiteboard, the corridor handover, the open screen. In paediatrics the record belongs to the parent or guardian, except for care an adolescent consented to independently and where a court has restricted a parent’s rights — read the custody paperwork rather than assuming.
Documentation is a clinical act before it is a legal one, and it is both. Chart contemporaneously, objectively and specifically: what you assessed, what you found in measurable terms, what you did, whom you notified, at what time, and what followed. Use her own words in quotation marks for symptoms, concerns and refusals — that is the entry that survives a later dispute about whether anybody listened. Never chart in advance or for another nurse, and correct an error with a single line through it, the correction, your initials, time and date. A concern you raised and did not document is one you cannot prove you raised.
Your scope of practice is set by your jurisdiction’s nurse practice act, not by the habits of the unit: policy may narrow it and can never widen it, and “the provider told me to” is no defence for working outside it. The five rights of delegation from Section 1 apply every time you hand a task on, and accountability stays with the RN who delegated.
Some duties cannot be delegated, referred or shared. Nurses are mandated reporters of suspected child abuse and neglect in every United States jurisdiction; the threshold is reasonable suspicion rather than proof, and the duty belongs personally to the nurse who formed the suspicion — telling the charge nurse does not discharge it unless a report is actually made. Good-faith reports carry statutory immunity. Federal child-welfare law separately requires that an infant identified as affected by substance exposure or withdrawal be notified to child protective services and given a plan of safe care, a support mechanism rather than a finding of abuse. Rules for intimate partner violence against a competent adult differ by jurisdiction — in most places the adult decides, and reporting without her consent can increase the danger she is in — so learn your own rule, and tell the patient before you make a report about her.
Finally, the conflict that most often leaves nurses stuck: the patient wants one thing and the family another. If the adult patient has capacity she decides, and your task is to build the conditions in which she can — usually by emptying the room and asking her alone, never with the person she may fear. In paediatrics the parents decide, but within limits: the choice must be one a reasonable parent could make for that child, assent should be sought from around seven, and a sustained refusal by an older child is a finding rather than a nuisance. When a parental decision risks serious harm, escalate rather than argue — charge nurse, treating clinician, chain of command, ethics — and in a genuine emergency treat under implied consent.
| Situation | Who holds the decision | What the nurse does |
|---|---|---|
| Adult with capacity, any recommended treatment | The patient | Make sure the information and an interpreter actually reached her; support the decision; document |
| Pregnant patient refusing a recommended caesarean or transfusion | The pregnant patient | Document informed refusal in her own words; keep offering care; request ethics support, never coercion |
| Adult who has lost capacity, no advance directive | Surrogate under the jurisdiction’s hierarchy | Confirm who the legal surrogate is; do not default to whoever speaks loudest |
| Child below the age of consent | Parent or legal guardian, with the child’s assent from about age 7 | Seek assent; escalate a parental refusal that risks serious harm |
| Adolescent consenting independently under a minor-consent statute | The adolescent | Protect that part of the record; warn her that billing statements can disclose the visit |
| Emancipated minor | The minor | Verify and document the basis once, then treat the consent as an adult’s |
| Life-threatening emergency, no decision-maker reachable | Consent is implied | Treat; document the emergency and the attempts made to reach a decision-maker |
| Child in foster or kinship placement | Varies — agency, court, or birth parent by order | Read the placement paperwork before any non-emergency consent |
Consent is the conversation and the form is only its receipt: the clinician performing the procedure must obtain it, the nurse witnesses identity, voluntariness and apparent capacity, and a patient with capacity — pregnant or not — may refuse. Confidentiality is defined by the patient, documentation is contemporaneous and in her own words, and scope of practice and mandatory reporting are duties owed by you personally that cannot be handed to anyone else.
The chapter in one breath
Maternal-newborn and paediatric nursing treats the family as the unit of care, built on dignity and respect, information sharing, participation and collaboration, and delivered through atraumatic care, cultural humility and language that describes rather than blames. The RN retains assessment, teaching, evaluation and the unstable patient no matter how busy the shift. Reproductive physiology is the grammar of the specialty: pulsatile GnRH drives FSH and LH, rising oestradiol triggers the LH surge, ovulation follows 24 to 36 hours later and about 14 days (14 ± 2) before the next menses, and progesterone from the corpus luteum prepares the endometrium until hCG rescues it or the lining sheds; on the male side a 64-to-74-day spermatogenic cycle sets how soon an abnormal semen analysis can usefully be repeated. That grammar underwrites pregnancy dating by Nägele’s rule, contraceptive counselling by effectiveness tier, and preconception folic acid started before conception rather than after. The same grammar organises the rest of Section 3: dysmenorrhoea, endometriosis and polycystic ovary syndrome, abnormal uterine bleeding classified by PALM-COEIN, an infertility work-up that begins with a semen analysis and evaluates both partners together, and the routine screening that surrounds all of it — sexually transmitted infection screening and treatment, cervical cytology and HPV testing, and HPV vaccination. Two foundations then decide whether any of that knowledge reaches the patient. The first is humility: culture is asked about rather than memorised, language access runs through a trained interpreter and never a family member or a child, the social determinants are screened for only where a referral route already exists, and the racial gaps in maternal mortality, preterm birth and infant mortality are taught as products of structural racism and unequal access rather than of race — which is why a patient’s own report that something is wrong is documented verbatim and acted on rather than filed as anxiety. The second is accountability: consent is the conversation and the form only its receipt, the provider obtains it while the nurse witnesses identity, voluntariness and apparent capacity, a patient with capacity may refuse and a pregnant patient remains the decision-maker for her own body, confidentiality is defined by the patient and complicated by adolescence, and documentation, scope of practice and mandatory reporting are duties the individual nurse cannot hand to anyone else.
Words worth knowing
| Term | What it means |
|---|---|
| Family-centred care | Practice model built on dignity and respect, information sharing, participation and collaboration with the family as partner |
| Assent | A child’s developmentally appropriate agreement to treatment, expected from about age 7, alongside parental permission |
| Emancipated minor | A minor who may consent independently by virtue of marriage, military service, independent living or court declaration |
| Mature minor | A minor judged by a clinician or a court to have sufficient maturity to consent to a particular treatment |
| LH surge | Oestradiol-triggered pituitary release that causes ovulation 24 to 36 hours later |
| Corpus luteum | Post-ovulatory follicular remnant secreting progesterone for a fixed 14 ± 2 days unless rescued by hCG |
| Spinnbarkeit | The stretchy, clear, oestrogen-driven quality of cervical mucus at ovulation |
| Nägele’s rule | Estimated date of birth = first day of LMP − 3 months + 7 days + 1 year |
| PALM-COEIN | Classification of abnormal uterine bleeding into structural and non-structural causes |
| Rotterdam criteria | Two of three findings — anovulation, hyperandrogenism, polycystic morphology — diagnose PCOS in adults; within 8 years of menarche the morphology limb does not apply and both of the other two are required |
| ACHES | Warning signs on combined hormonal contraception: abdominal pain, chest pain, headache, eye changes, severe leg pain |
| Trained interpreter | A qualified interpreter used for the whole encounter whenever the patient’s preferred language for health care is not the nurse’s — never a family member and never a child |
| SBAR | Escalation format — situation, background, assessment, recommendation — used to name a red flag and make a specific, time-bound request |
| Cultural humility | Lifelong self-examination, correction of the clinician–patient power imbalance and accountability to communities — asking rather than assuming, in contrast to cultural competence |
| Social determinants of health | Economic stability, education, health care access, neighbourhood and social context — the conditions that decide whether a plan of care is achievable |
| Structural racism | Policies and systems that distribute resources and treatment unequally by race, producing the disparities that race itself does not explain |
| Implicit bias | Automatic associations operating outside awareness that can contradict stated values; classically expressed as under-treated pain |
| Trauma-informed care | Assuming trauma may be present and building safety, transparency, collaboration and choice into every interaction so care does not re-injure |
| Capacity | Ability to understand, appreciate, reason and communicate a consistent choice; decision-specific, and not lost by disagreeing with the clinician |
| Mandated reporter | Nurse’s personal, non-delegable duty to report suspected child abuse or neglect on reasonable suspicion rather than proof |