Assessing the Heart and Peripheral Vascular System
Cardiovascular disease is the leading cause of death in this country, and the nurse at the bedside is the person most likely to notice it turning. This chapter teaches the cardiac and peripheral vascular exam the way it is actually performed: where the valve areas sit on the chest wall, how to find the apical impulse with your fingertips, how to tell a jugular pulsation from a carotid one, when to use the bell and when the diaphragm, and how to grade a pulse, an edema and a murmur so the next nurse can tell whether the patient improved. You will learn the four-step order — inspection, palpation, percussion, auscultation — and the single exception to it. You will learn the real numbers: heart rate and blood pressure across the lifespan, capillary refill, ankle-brachial index, the size and location of a normal apical impulse. And you will learn which findings do not wait for morning rounds, because a cold pulseless foot and a new S3 in a patient gaining weight are both clocks that have already started.
By the end of this chapter you can
- Trace blood through the chambers and valves of the heart and relate systole and diastole to the production of S1 and S2.
- Locate the aortic, pulmonic, Erb’s point, tricuspid and mitral (apical) auscultatory areas and perform the precordial exam in the correct order — inspection, palpation, percussion, auscultation — naming the abdomen as the one exception.
- Assess the point of maximal impulse, thrills and heaves, and measure jugular venous pressure, distinguishing a jugular from a carotid pulsation.
- State expected heart rate and blood pressure values for the newborn, infant, toddler, preschooler, school-age child, adolescent, adult, pregnant patient and older adult.
- Differentiate normal S1 and S2 from physiologic splitting, S3, S4, murmurs, an opening snap and a pericardial friction rub, and grade a murmur on the six-point scale.
- Grade peripheral pulses and pitting edema, measure capillary refill and interpret the ankle-brachial index.
- Contrast arterial and venous insufficiency and recognize the six Ps of acute arterial occlusion and the signs of deep vein thrombosis.
- Recognize cardiovascular red flags requiring immediate escalation and communicate them using SBAR.
- Document a cardiovascular assessment in precise, defensible language and apply the five rights of delegation to cardiac and vascular tasks.
Section 1The Pump, the Cycle and the Cardiac Baseline
Chambers, valves and the direction of flow
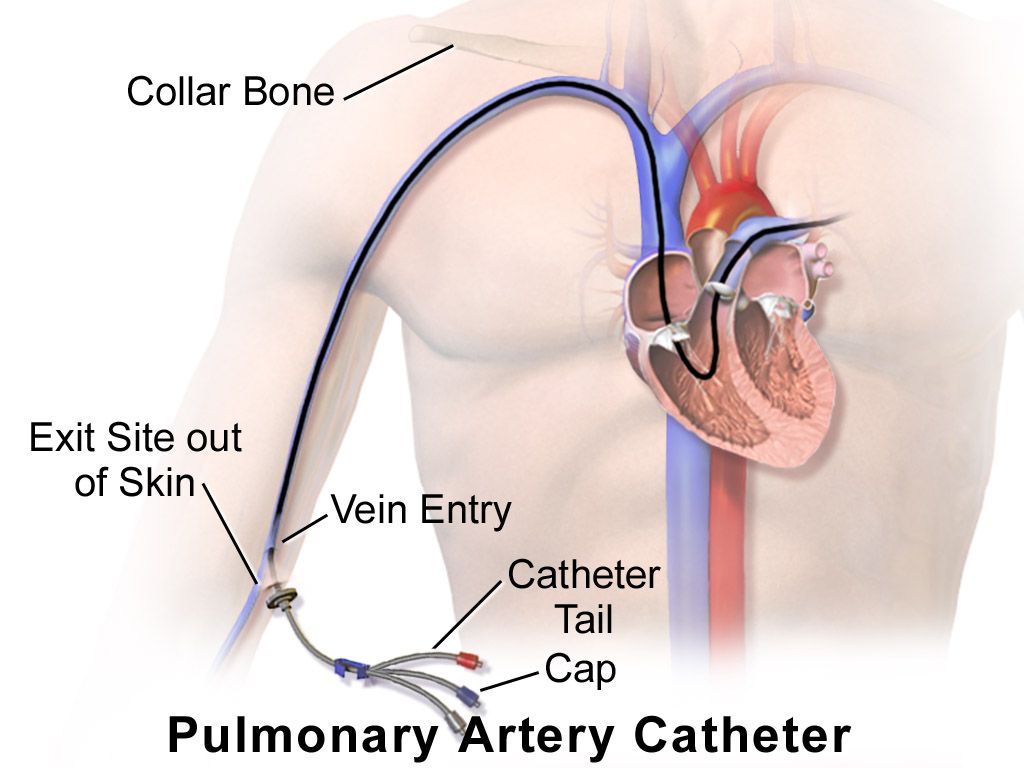
The heart sits in the mediastinum behind the sternum, roughly two thirds of it to the left of the midline, with its broad base up under the second intercostal spaces and its pointed apex down and to the left at about the fifth intercostal space. That orientation is upside down from how students first picture it, and it matters: the valves closest to the base are the ones you hear best at the top of the chest, and the apex — the tip of the left ventricle — is what taps your fingers low on the left chest wall.
Deoxygenated blood returns from the body through the superior and inferior vena cava into the right atrium, crosses the tricuspid valve into the right ventricle, and is pumped through the pulmonic valve into the pulmonary artery and on to the lungs. Oxygenated blood returns through the four pulmonary veins into the left atrium, crosses the mitral valve into the left ventricle, and is ejected through the aortic valve into the aorta. The tricuspid and mitral valves are the atrioventricular valves; the pulmonic and aortic are the semilunar valves. The left ventricle does the systemic work and is therefore the thickest chamber, which is why it is the chamber you can feel and the chamber that hypertrophies under a lifetime of high blood pressure.
The heart is wrapped in the pericardium, a two-layered sac with a thin film of fluid between the layers. When those layers inflame they scrape against each other and produce a friction rub; when fluid accumulates rapidly between them the ventricles cannot fill, which is cardiac tamponade. The coronary arteries branch off the aorta immediately above the aortic valve and fill during diastole, not systole, which is why a very fast heart rate — by shortening diastole — worsens myocardial ischemia even when nothing else changes.
The cardiac cycle and what makes the sounds
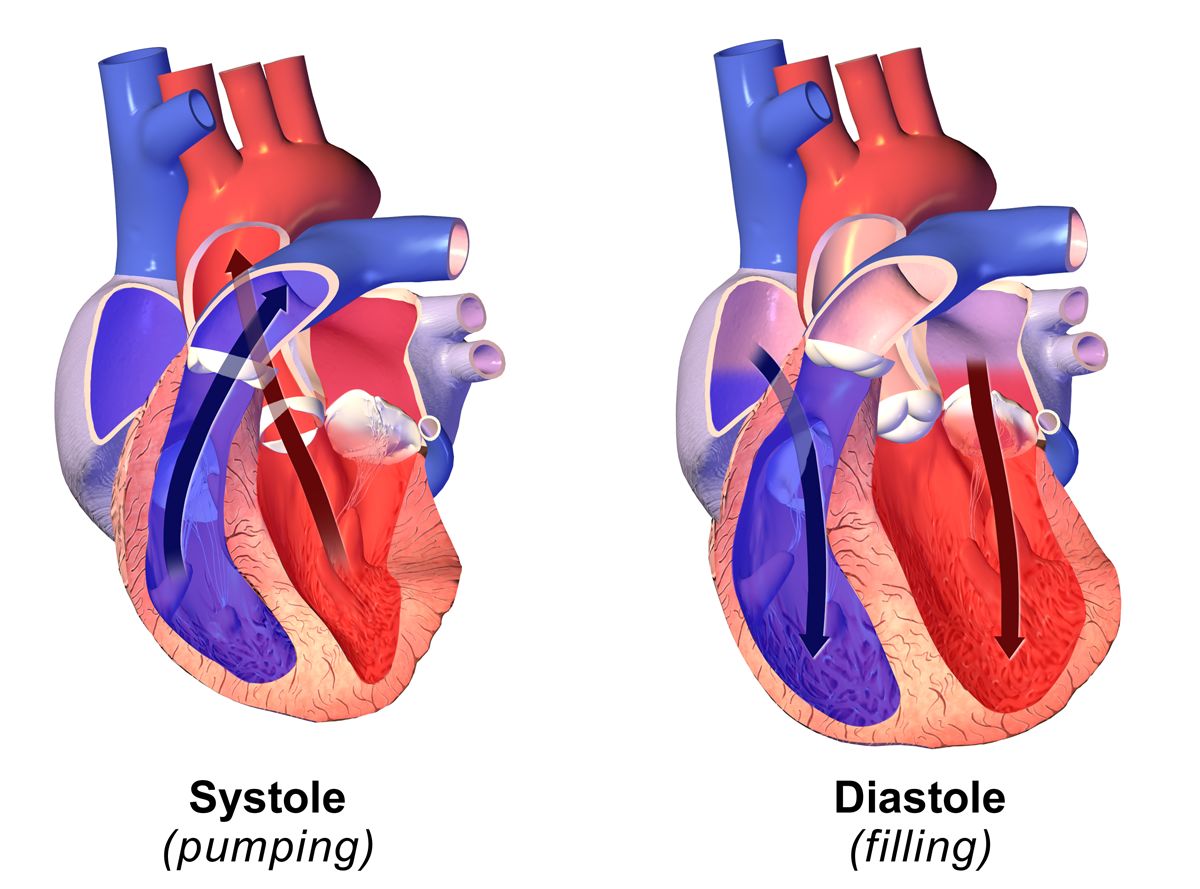
Systole is ventricular contraction and ejection; diastole is ventricular relaxation and filling. Diastole is normally the longer of the two at rest, occupying roughly two thirds of the cycle. The heart sounds are not made by valves opening — opening is silent — but by the abrupt deceleration of blood and the vibration of structures when valves close.
S1, the “lub,” is closure of the mitral and tricuspid valves and marks the beginning of systole. It is lower pitched, slightly longer, and loudest at the apex. S2, the “dub,” is closure of the aortic and pulmonic valves and marks the end of systole. It is higher pitched, shorter, and loudest at the base. The interval between S1 and S2 is systole; the longer interval between S2 and the next S1 is diastole. If you cannot tell which sound is which — and at a rate over about 120 you often cannot — palpate the carotid pulse while you listen: the carotid upstroke coincides with S1.
Two more facts turn this into usable clinical information. First, S2 normally splits during inspiration, because negative intrathoracic pressure increases venous return to the right heart, prolongs right ventricular ejection and delays pulmonic closure behind aortic closure. Physiologic splitting is heard best at the second left intercostal space, appears on inspiration and vanishes on expiration, and is a normal finding, most obvious in children and thin young adults. Splitting that persists through expiration, or that widens on expiration, is not normal. Second, the atria contribute a final “atrial kick” of about 20 to 30 percent of ventricular filling at the very end of diastole. When the atria fibrillate, that kick disappears — which is why patients who go into atrial fibrillation often drop their blood pressure, and why an S4, which is generated by atrial contraction, can never exist in atrial fibrillation.
Precordial landmarks and the auscultatory areas
The five listening areas are not directly over their valves. They are the spots on the chest wall where blood flow carries each valve’s sound most clearly, so you must learn them as surface locations, counted from the sternal angle (angle of Louis) exactly as you learned to count ribs in the chest exam.
| Area | Surface location | Sound heard best here |
|---|---|---|
| Aortic | Second intercostal space, right sternal border | S2 louder than S1; aortic stenosis, aortic sclerosis |
| Pulmonic | Second intercostal space, left sternal border | S2 louder than S1; physiologic splitting of S2 is assessed here |
| Erb’s point | Third intercostal space, left sternal border | S1 and S2 roughly equal; aortic regurgitation, many murmurs are audible here |
| Tricuspid | Fourth to fifth intercostal space, left sternal border | S1 louder than S2; tricuspid regurgitation, right-sided S3 and S4 |
| Mitral (apical, PMI) | Fifth intercostal space, left midclavicular line | S1 louder than S2; mitral murmurs, S3 and S4 (use the bell) |
A common mnemonic runs All People Enjoy Time Magazine — aortic, pulmonic, Erb’s, tricuspid, mitral — and it tracks the standard base-to-apex sequence. Move in that order or its reverse, but move in an order and use the same one every time. Do not skip from spot to spot; slide the stethoscope in small steps so you do not miss a murmur that lives between two named areas.
The cardiac baseline: rate, rhythm and pressure
The apical pulse is auscultated at the mitral area with the diaphragm and counted for a full 60 seconds whenever the rhythm is irregular, whenever the patient is an infant or young child, and before administering any medication with a heart-rate parameter. Digoxin is the classic example: hold the dose and notify the provider if the apical rate is under 60 in an adult, under 70 in a child or under 90 in an infant, and always follow the parameters actually written in the order.
A pulse deficit is the difference between the apical rate and the radial rate counted over the same minute. It is measured by two clinicians counting simultaneously, or by counting apical then radial back to back if only one nurse is available, and it means that some ventricular contractions are too weak to generate a peripheral pulse. A deficit is common in atrial fibrillation and with frequent premature ventricular contractions, and it is always the apical rate — never the radial — that is the true heart rate.
| Age group | Expected heart rate (beats/min) | Expected blood pressure (mmHg) | Bedside notes |
|---|---|---|---|
| Newborn (birth to 1 month) | 100–205 awake; 90–160 asleep | Roughly 60–90 systolic | Hypotension if systolic is under 60; brachial or apical pulse only — never assess a carotid in an infant |
| Infant (1–12 months) | 100–180 awake; 90–160 asleep | Roughly 87–105 / 53–66 | Hypotension if systolic is under 70; bradycardia in an infant is usually hypoxia until proven otherwise |
| Toddler (1–2 years) | 98–140 | Roughly 95–105 / 53–66 | Hypotension if systolic is under 70 plus twice the age in years |
| Preschooler (3–5 years) | 80–120 | Roughly 95–110 / 56–70 | Innocent systolic murmurs are common and change with position |
| School-age (6–11 years) | 75–118 | Roughly 97–112 / 57–71 | Pediatric blood pressure norms depend on height percentile as well as age |
| Adolescent (12–18 years) | 60–100 | Roughly 112–128 / 66–80 | Hypotension if systolic is under 90 from age 10 upward |
| Adult | 60–100 | Under 120 and under 80 is normal | Elevated 120–129 and under 80; stage 1 hypertension 130–139 or 80–89; stage 2 at 140 or higher, or 90 or higher |
| Pregnancy | Baseline plus 10–20 (resting 70–90 is typical) | Diastolic falls 10–15 mmHg in the second trimester, returns to baseline by term | 140/90 or higher after 20 weeks is never normal; 160/110 or higher is a severe-range emergency |
| Older adult | 60–100; maximum rate and rate response are blunted | Same targets, but isolated systolic hypertension and a widened pulse pressure are common | May not mount a tachycardia in shock, especially on a beta blocker |
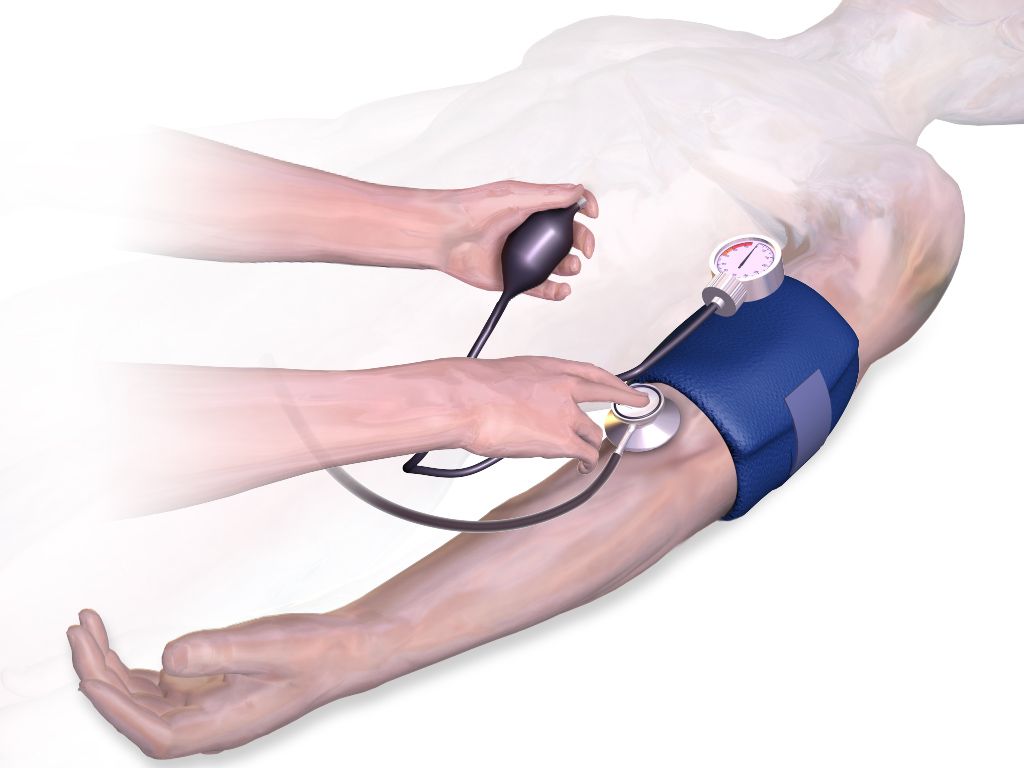
Pulse pressure is systolic minus diastolic and is normally about 30 to 40 mmHg, up to roughly 50. A narrow pulse pressure suggests reduced stroke volume — hypovolemia, heart failure, aortic stenosis, tamponade. A wide pulse pressure suggests stiff arteries in an older adult, or aortic regurgitation, thyrotoxicosis, anemia or fever. Cuff technique changes the number: the bladder width should be about 40 percent of the arm circumference and the bladder length about 80 percent, the arm must be supported at heart level, and the patient should sit quietly for five minutes with the back supported, feet flat on the floor, legs uncrossed, and should not talk during the measurement. An unsupported back raises the diastolic reading and crossed legs raise the systolic reading. A cuff that is too small or too loose reads falsely high; an arm held below heart level reads falsely high; an arm held above heart level reads falsely low.
Orthostatic vital signs are a cardiovascular test, not a courtesy. Measure blood pressure and heart rate after the patient has been supine at least five minutes, then repeat sitting and again standing at one minute and at three minutes. Orthostatic hypotension is a drop of 20 mmHg or more in systolic pressure, or 10 mmHg or more in diastolic pressure, within three minutes of standing; a compensatory rise in heart rate of 20 beats per minute or more is corroborating. Stay with the patient. If they become dizzy or pale, sit them down and abandon the test — you have your answer.
Every heart sound needs a location and a timing before it means anything. “Murmur heard” is not an assessment. “Grade II/VI systolic murmur at the second right intercostal space radiating to the carotids” is an assessment, and it points at one valve. Train yourself to answer three questions about any sound before you chart it: where is it loudest, is it in systole or diastole, and where does it go.
S1 opens systole and is loudest at the apex, S2 closes systole and is loudest at the base — and every murmur you will ever describe is located relative to those two sounds.
Section 2Inspecting and Palpating the Precordium and Neck Vessels
Setting up, and the order of the exam
The cardiovascular exam follows the same fixed sequence as the rest of the body: inspection, palpation, percussion, auscultation. The abdomen is the single exception — there you inspect, then auscultate, then percuss, then palpate, because pressing on the abdomen first alters bowel motility and produces falsely absent or falsely hyperactive bowel sounds. Nothing about the heart uses that modified order.
Position matters more here than anywhere else in the physical exam. Begin with the patient supine with the head of the bed at 30 to 45 degrees, chest exposed, room warm, and stand on the patient’s right side if you can. You will use two more positions later: the left lateral decubitus position, which rolls the apex of the heart toward the chest wall and brings out low-pitched apical sounds such as S3, S4 and the rumble of mitral stenosis; and sitting upright and leaning forward, which brings the base of the heart forward and brings out the soft early-diastolic murmur of aortic regurgitation and a pericardial friction rub. Tell the patient what you are doing and drape a female patient so that only the area being examined is uncovered; when breast tissue overlies the apex, ask the patient to lift the breast or displace it upward yourself with the back of your hand.
Inspection and palpation of the precordium
Inspect with tangential light across the chest so that movement casts a shadow. Look for the apical impulse, which is visible in roughly half of adults and in most thin patients and children, and for any other pulsation, lift or retraction. Note the chest wall itself: pectus excavatum can displace the heart, a median sternotomy scar tells you about prior surgery, and a firm rectangular bulge below the left clavicle is a pacemaker or defibrillator generator, which should be documented along with the site’s appearance.
Now palpate. Use the finger pads for pulsations and the ball of the hand at the base of the fingers for the low-frequency buzzing of a thrill. Palpate systematically at the apex, the left lower sternal border, the left and right second intercostal spaces and the epigastrium. The point of maximal impulse, or PMI, is the apical impulse and normally sits at the fifth intercostal space at or just medial to the left midclavicular line. It is small — about 1 to 2 cm across, no more than the size of a quarter, roughly one interspace — it is a brief gentle tap occupying the first half of systole, and it is easiest to feel with the patient rolled to the left side or in full expiration. If you cannot find it, that alone is not abnormal: obesity, a muscular chest wall, emphysema and large breasts all conceal it.
| Palpation finding | Expected | Abnormal and what it suggests |
|---|---|---|
| PMI location | Fifth intercostal space, at or just medial to the left midclavicular line | Displaced laterally and downward: left ventricular dilation from heart failure or volume overload. Displaced laterally without enlargement: pregnancy, ascites, large pleural effusion, tension pneumothorax pushing the mediastinum |
| PMI size | 1–2 cm, confined to one interspace | Diffuse, over 3 cm or spanning two interspaces: ventricular dilation |
| PMI quality and duration | Brief, gentle tap in early systole | Sustained through systole and forceful: left ventricular hypertrophy from hypertension or aortic stenosis. Hyperdynamic and brief: fever, anemia, anxiety, hyperthyroidism |
| Thrill | None | A palpable, purring, cat-like vibration over a valve area; means turbulent flow and automatically makes any murmur at least grade IV/VI |
| Heave or lift | None | A sustained forceful thrust that lifts your hand. At the left lower sternal border, right ventricular hypertrophy (pulmonary hypertension, COPD, pulmonary embolism). At the apex, left ventricular hypertrophy |
| Epigastric pulsation | Slight, or none; may be normal in thin patients | A wide, forceful, expansile pulsation may indicate an abdominal aortic aneurysm — do not palpate deeply, and report it |
Percussion of the heart is the third step in the sequence, and honesty is owed to students here: it is now rarely performed and has largely been replaced by chest radiography and echocardiography, because percussing the left cardiac border is imprecise and unreliable. It is still taught, and if you perform it you percuss from resonance in the left anterior axillary line medially toward the sternum at the third, fourth and fifth interspaces, listening for the change to dullness, which normally occurs at or medial to the midclavicular line. Cardiac dullness extending well past the midclavicular line suggests cardiac enlargement. Chart what you did and did not perform; do not chart a percussion you skipped.
The neck vessels: carotids and jugular venous pressure
The carotid arteries and internal jugular veins are the two windows onto the heart that sit outside the chest. Assess the carotid arteries one at a time, never both simultaneously — simultaneous compression can reduce cerebral perfusion, and pressure over the carotid sinus can trigger a reflex bradycardia or even asystole in a susceptible patient. Palpate low in the neck, medial to the sternocleidomastoid, below the level of the thyroid cartilage, using light pressure. The normal carotid upstroke is brisk, smooth and symmetric, graded 2+, and it coincides with S1. A weak, slow-rising and delayed upstroke suggests aortic stenosis; a bounding upstroke suggests aortic regurgitation, fever, anemia or hyperthyroidism.
Auscultate the carotids before you palpate them in any patient over about 50, or with known atherosclerosis, hypertension, diabetes, or a history of stroke or transient ischemic attack. Place the bell lightly over each carotid at the angle of the jaw, at the midcervical level and at the base of the neck, and ask the patient to hold their breath briefly so tracheal sounds do not mask what you are listening for. A bruit is a blowing, swishing sound of turbulent flow and requires reporting. Be aware that a bruit does not reliably indicate the degree of stenosis: a tightly narrowed artery may be silent because so little blood is moving through it.
Jugular venous pressure is a direct bedside estimate of right atrial filling pressure and volume status, and it is one of the most useful skills in this chapter. Position the patient at 30 to 45 degrees, turn the head slightly away from the side you are examining, and use tangential lighting. Look for the flickering pulsation of the internal jugular between the two heads of the sternocleidomastoid. Identify the highest point at which the pulsation is visible, then measure the vertical distance in centimeters from that point up from the horizontal plane of the sternal angle. Normal is 3 cm or less above the sternal angle; because the sternal angle sits about 5 cm above the right atrium in any position, that corresponds to a central venous pressure of roughly 8 cm of water or less. A jugular pulsation visible with the patient sitting fully upright at 90 degrees is markedly elevated.
| Feature | Internal jugular vein | Carotid artery |
|---|---|---|
| Palpable? | No — the pulsation is visible only | Yes — a definite palpable thrust |
| Waveform | Undulating, soft, two peaks per cardiac cycle | A single brisk outward stroke per cycle |
| Effect of position | Level falls as the patient sits up, rises as they lie flat | Unchanged by position |
| Effect of light pressure at the base of the neck | Obliterated easily | Not obliterated |
| Effect of respiration | Level normally falls with inspiration | No change |
Elevated jugular venous pressure, commonly charted as jugular venous distention, means the right side of the heart cannot handle its returning volume: right-sided heart failure, fluid overload, tricuspid regurgitation, pulmonary hypertension, cardiac tamponade, constrictive pericarditis or tension pneumothorax. Flat neck veins in a patient lying supine suggest the opposite — hypovolemia. Hepatojugular reflux refines the finding: with the patient at 30 to 45 degrees and breathing normally through an open mouth, press firmly over the right upper quadrant for 10 to 15 seconds. A sustained rise in jugular pressure of more than 3 cm that persists throughout the pressure suggests the right ventricle cannot accommodate additional volume. Stop if the patient reports pain.
If you can feel it, it is the carotid. If you can only see it, it is the jugular. That single rule prevents the most common error on the neck exam, and it also prevents the most dangerous one: pressing on both carotids at once while trying to compare them.
An apical impulse that has moved laterally and become diffuse, a heave at the sternal border, or jugular pulsation more than 3 cm above the sternal angle tell you the heart is failing before any sound does.
Section 3Auscultating the Heart: Normal Sounds, Extra Sounds and Murmurs
Technique: bell, diaphragm, position and sequence
Auscultate on bare skin in a quiet room. Clothing and gowns generate rustling that beginners mistake for murmurs and rubs. Warm the endpiece. Then use both sides of the stethoscope deliberately, because they filter different frequencies: the diaphragm, pressed firmly enough to leave a light ring, transmits high-pitched sounds — S1, S2, most murmurs, and friction rubs. The bell, applied lightly enough that it barely dimples the skin, transmits low-pitched sounds — S3, S4 and the diastolic rumble of mitral stenosis. Pressing the bell firmly stretches the skin beneath it into a diaphragm and eliminates exactly the sounds you were trying to hear, which is why so many students never hear an S3.
Go through all five areas with the diaphragm first, then repeat all five with the bell. At every site, listen for one thing at a time rather than trying to hear everything at once. Identify S1, then S2, then the systolic interval between them, then diastole, and only then listen for extra sounds. Note the rate and the rhythm: regular, regularly irregular (a repeating pattern, as in bigeminy or second-degree block) or irregularly irregular (no pattern at all, the hallmark of atrial fibrillation).
Finally, use the two special positions. Roll the patient into the left lateral decubitus position and listen at the apex with the bell — this is where S3, S4 and mitral stenosis appear. Then sit the patient up, ask them to lean forward and exhale fully and hold, and listen along the left sternal border and at the base with the diaphragm — this is where aortic regurgitation and a pericardial friction rub appear. Skipping these two maneuvers is why soft diastolic murmurs get missed on the unit and found in the cath lab.
S1, S2 and normal variation
At the apex, S1 is louder than S2; at the base, S2 is louder than S1. Both should be crisp. Muffled or distant heart sounds occur with obesity, emphysema, a thick chest wall, and — urgently — with pericardial effusion and cardiac tamponade, where muffled sounds join hypotension and jugular distention to form Beck’s triad. An accentuated S1 occurs with tachycardia, fever, anemia, exercise and mitral stenosis; a diminished S1 occurs with first-degree heart block and with mitral regurgitation. Variable S1 intensity from beat to beat is a clue to atrial fibrillation or complete heart block, because the relationship between atrial and ventricular contraction keeps changing.
Physiologic splitting of S2, described earlier, is normal when it appears on inspiration and disappears on expiration at the pulmonic area. Persistent splitting through both phases, fixed splitting that never varies with respiration (classically atrial septal defect) and paradoxical splitting that appears on expiration and disappears on inspiration (left bundle branch block, severe aortic stenosis) are all abnormal and reportable. A nurse is not expected to name the lesion; a nurse is expected to notice that the second sound is doing something it should not and to describe it accurately.
S3, S4, and the other extra sounds
| Sound | Timing and how it sounds | How to hear it | What it means |
|---|---|---|---|
| S3 (ventricular gallop) | Early diastole, just after S2; low-pitched and dull. Cadence of “Ken-tuc-KY,” the stressed syllable being the extra sound | Bell, lightly, at the apex, patient in left lateral decubitus | Rapid ventricular filling into a volume-overloaded ventricle. Normal in children, in healthy adults up to roughly age 35 to 40, and in pregnancy. After age 40 it is heart failure or volume overload until proven otherwise, and it is often the earliest sign of decompensation |
| S4 (atrial gallop) | Late diastole, just before S1; low-pitched. Cadence of “TEN-nes-see,” the stressed syllable again being the extra sound | Bell, lightly, at the apex, patient in left lateral decubitus | The atrium contracting against a stiff, non-compliant ventricle: hypertension, left ventricular hypertrophy, aortic stenosis, coronary disease, acute myocardial infarction. Common and often benign in older adults. Impossible in atrial fibrillation, because there is no organized atrial contraction |
| Summation gallop | S3 and S4 merging into one loud extra sound at fast rates | Bell at the apex | Tachycardia plus significant ventricular dysfunction — an ominous combination |
| Opening snap | Early diastole, shortly after S2; sharp and high-pitched | Diaphragm, apex to left sternal border | A stenotic mitral valve snapping open; usually followed by the diastolic rumble of mitral stenosis |
| Ejection click | Early systole, just after S1; sharp | Diaphragm, base | A stiffened aortic or pulmonic valve or a dilated great vessel |
| Midsystolic click | Mid to late systole; sharp and clicking, often followed by a late systolic murmur | Diaphragm, apex | Mitral valve prolapse |
| Pericardial friction rub | Scratchy, scraping, leathery; up to three components across the cycle | Diaphragm, left lower sternal border, patient sitting, leaning forward, breath held after exhalation | Pericarditis, including post-myocardial-infarction and uremic pericarditis. Unlike a pleural rub, a pericardial rub persists when the breath is held — that is how you tell them apart |
Learn the two gallops by their rhythm, not by their pitch, because a low-pitched sound is hard for a beginner to isolate but a three-beat cadence is not. If the extra beat falls after the “dub” you have S3; if it falls before the “lub” you have S4. Say the mnemonics aloud in your head while you listen. And note the age rule carefully in both directions: an S3 in a 22-year-old athlete or a pregnant patient at 32 weeks may be entirely physiologic, and an S3 in a 68-year-old who has gained four pounds since yesterday is a phone call.
Murmurs: grading them and describing them
A murmur is the sound of turbulent flow — blood forced through a narrowed valve, leaking backward through an incompetent one, moving through an abnormal opening, or simply moving fast through a normal heart. Intensity is graded on the six-point Levine scale, and the grade is always written as a fraction so the reader knows which scale you used: II/VI, not “grade 2.”
| Grade | What it takes to hear it |
|---|---|
| I/VI | Very faint; heard only after listening carefully for several beats, and not in all positions |
| II/VI | Quiet but heard immediately on placing the stethoscope |
| III/VI | Moderately loud, easily heard; no thrill |
| IV/VI | Loud, with a palpable thrill |
| V/VI | Very loud with a thrill; audible with the stethoscope only partly touching the chest |
| VI/VI | Audible with the stethoscope lifted just off the chest wall |
Grade IV and above always includes a thrill, so palpation and auscultation cross-check each other: if you graded a murmur IV/VI you should be able to feel it, and if you can feel it, it is at least IV/VI. Beyond intensity, describe six more attributes: timing (systolic or diastolic, and where within the phase), location of maximum intensity, radiation, pitch (high, medium, low), quality (blowing, harsh, rumbling, musical) and what changes it (position, respiration, exercise). A single clinical rule is worth memorizing: most systolic murmurs may be benign, but a diastolic murmur is never innocent and always requires evaluation.
| Murmur | Timing and quality | Loudest at | Radiates to | Associated findings |
|---|---|---|---|---|
| Aortic stenosis | Midsystolic, crescendo-decrescendo, harsh | Second right intercostal space | The carotids | Slow-rising weak carotid upstroke, narrow pulse pressure, sustained PMI; exertional syncope, angina and dyspnea are the classic triad |
| Mitral regurgitation | Holosystolic (pansystolic), blowing, high-pitched | Apex | The left axilla | Often an S3; may follow papillary muscle rupture after myocardial infarction |
| Tricuspid regurgitation | Holosystolic, blowing | Left lower sternal border | Right sternal border | Louder on inspiration; jugular distention, peripheral edema, pulsatile liver |
| Mitral valve prolapse | Midsystolic click then late systolic murmur | Apex | Little | Often in young, thin patients; frequently benign |
| Aortic regurgitation | Early diastolic, decrescendo, soft and blowing, high-pitched | Third to fourth left intercostal space | Toward the apex | Best heard — and often only heard — with the patient sitting, leaning forward and holding exhalation, but a soft early-diastolic murmur may still be audible in the routine position and is never dismissed; wide pulse pressure, bounding pulses |
| Mitral stenosis | Mid to late diastolic low rumble after an opening snap | Apex, a small area | Little | Requires the bell and the left lateral decubitus position; associated with atrial fibrillation |
| Innocent or physiologic murmur | Early to midsystolic, soft, grade I–II/VI, musical or vibratory | Left sternal border or pulmonic area | None | Changes markedly with position, disappears on sitting or standing; no thrill, normal S1 and S2, no symptoms. Common in children, fever, anemia, pregnancy, hyperthyroidism |
A murmur you can hear with the diaphragm pressed hard but that vanishes when you switch to a light bell was probably high-pitched all along; a sound that appears only under a light bell and vanishes under pressure is a genuine low-frequency gallop. Practice the switch on a patient known to have an S3 — once your ear has heard one real one, you will find them for the rest of your career.
New murmur plus new symptoms is a different animal from a chronic murmur charted on admission. A new holosystolic murmur at the apex in a patient two days after a myocardial infarction, especially with sudden dyspnea, can be papillary muscle rupture. Do not put it in the note for the day shift to notice — call.
Use the diaphragm firmly for high-pitched sounds and the bell lightly for S3, S4 and mitral stenosis, listen in the left lateral and forward-leaning positions every time, and remember that a diastolic murmur is never innocent.
Section 4The Peripheral Vascular Exam
Arteries: pulses, perfusion and the numbers that go with them
Palpate each pulse with the pads of two or three fingers — never the thumb, which has its own pulse strong enough to fool you — using light pressure that you increase only until you feel the maximum impulse. Assess rate, rhythm, amplitude, contour and symmetry, and always compare the two sides. The sites are temporal, carotid, brachial, radial, ulnar, femoral, popliteal, dorsalis pedis and posterior tibial. In infants, use the brachial pulse for the pulse check, not the carotid, and use the femoral to screen for coarctation of the aorta: a femoral pulse that is weaker than the brachial, or delayed behind it, is a classic sign.
| Grade | Description | Interpretation |
|---|---|---|
| 0 | Absent — no pulse palpable at the site | Occlusion; an emergency if new. Confirm with a Doppler and chart the two findings separately: not palpable but present by Doppler, or absent by Doppler |
| 1+ | Diminished, weak, thready; fades under light pressure | Reduced perfusion: peripheral arterial disease, low cardiac output, hypovolemia |
| 2+ | Normal: brisk, expected, easily palpated | Expected finding |
| 3+ | Increased, full | Hyperdynamic states: fever, anxiety, anemia, exercise, hyperthyroidism |
| 4+ | Bounding; cannot be obliterated by pressure | Aortic regurgitation, severe hypertension, fluid overload |
Facilities differ: some use a 0 to 3+ scale in which 3+ means bounding. Chart with the scale your facility uses and state it, and describe rather than rely on the number alone. When a pulse is not palpable, obtain a Doppler ultrasound probe and document explicitly: “right dorsalis pedis not palpable, present by Doppler” is a materially different finding from “absent by Doppler.” Mark the location of a Doppler-only pulse with a skin pen so the next nurse finds the same spot.
Two anatomic facts prevent unnecessary alarm and unnecessary reassurance. The dorsalis pedis pulse is congenitally absent or anatomically variant in roughly 2 to 10 percent of healthy people, so an isolated absent dorsalis pedis with a strong posterior tibial and warm pink foot is usually benign. The posterior tibial is rarely absent in healthy adults, and both pedal pulses absent in the same foot is abnormal until proven otherwise.
Capillary refill is assessed by compressing a nail bed until it blanches, holding for about five seconds, releasing and counting until color returns, with the hand or foot held at the level of the heart. Normal is under 2 seconds in children and adults; up to 3 seconds is generally accepted in neonates and in a cold room. Prolonged refill suggests poor perfusion, shock, hypothermia or peripheral arterial disease, and it is a soft sign in older adults with chronically thickened nails. The ankle-brachial index (ABI) is the systolic pressure at the ankle divided by the higher of the two brachial systolic pressures, measured with a Doppler: 1.00 to 1.40 is normal, 0.91 to 0.99 is borderline, 0.90 or less indicates peripheral arterial disease, under 0.40 indicates severe disease with a risk of critical limb ischemia, and a value above 1.40 means the vessels are calcified and non-compressible — a falsely reassuring high number seen in long-standing diabetes and renal disease.
The modified Allen test checks ulnar collateral flow before radial artery puncture or cannulation. Have the patient make a tight fist while you occlude both the radial and ulnar arteries, then have them open the hand, which will look pale. Release the ulnar artery only and watch. Color should return to the entire palm within about 5 to 7 seconds; return taking longer than 15 seconds is abnormal and the radial artery on that side should not be used.
Veins, edema and the two kinds of insufficiency
Inspect the legs with the patient both lying and standing. Note varicosities, which are dilated tortuous superficial veins made obvious by standing; note color, hair distribution, nail thickness, temperature compared side to side using the back of your hand, and any ulceration with its exact location, size in centimeters, border and wound-bed appearance. Measure calf circumference at a marked, reproducible point — conventionally 10 cm below the tibial tuberosity — and record the measurement so the next nurse measures the same place. A difference of more than 3 cm between the calves is one of the criteria used in deep vein thrombosis scoring.
Assess pitting edema by pressing firmly with your thumb for at least five seconds over a bony prominence — the dorsum of the foot, behind the medial malleolus, or over the tibia — then removing your thumb and observing the depth and rebound. In a patient on bed rest, also press over the sacrum, because dependent edema follows gravity and will collect there rather than in the feet.
| Grade | Depth of pit | Rebound |
|---|---|---|
| 1+ | About 2 mm; barely perceptible | Immediate |
| 2+ | About 4 mm | About 10 to 15 seconds |
| 3+ | About 6 mm; the extremity looks visibly swollen | More than 1 minute |
| 4+ | About 8 mm; the extremity is grossly distorted | Roughly 2 to 5 minutes |
Edema-grading scales vary between textbooks and facilities, which makes the number alone a weak communication tool. Strengthen it by charting depth in millimeters, the anatomic level to which the edema extends, whether it pits, whether it is unilateral or bilateral, and the rebound time. Non-pitting edema that feels firm or woody is a different problem — lymphedema, chronic venous change or myxedema — and should be described as such rather than forced onto a pitting scale. Daily weight is the most sensitive fluid measure you have: measure at the same time each morning, after voiding, in the same clothing, on the same scale. Each kilogram of gain represents roughly a liter of retained fluid, so a gain of about 1 kilogram, or 2 pounds, in 24 hours or about 2.3 kilograms, 5 pounds, in a week is a reportable threshold in heart failure.
| Feature | Arterial insufficiency | Venous insufficiency |
|---|---|---|
| Pain | Intermittent claudication: cramping calf pain with a predictable amount of walking, relieved by rest. Rest pain is worse when the leg is elevated and relieved by hanging the leg down | Dull ache, heaviness, worse with prolonged standing, relieved by elevation |
| Pulses | Diminished or absent | Present, though hard to feel through swelling |
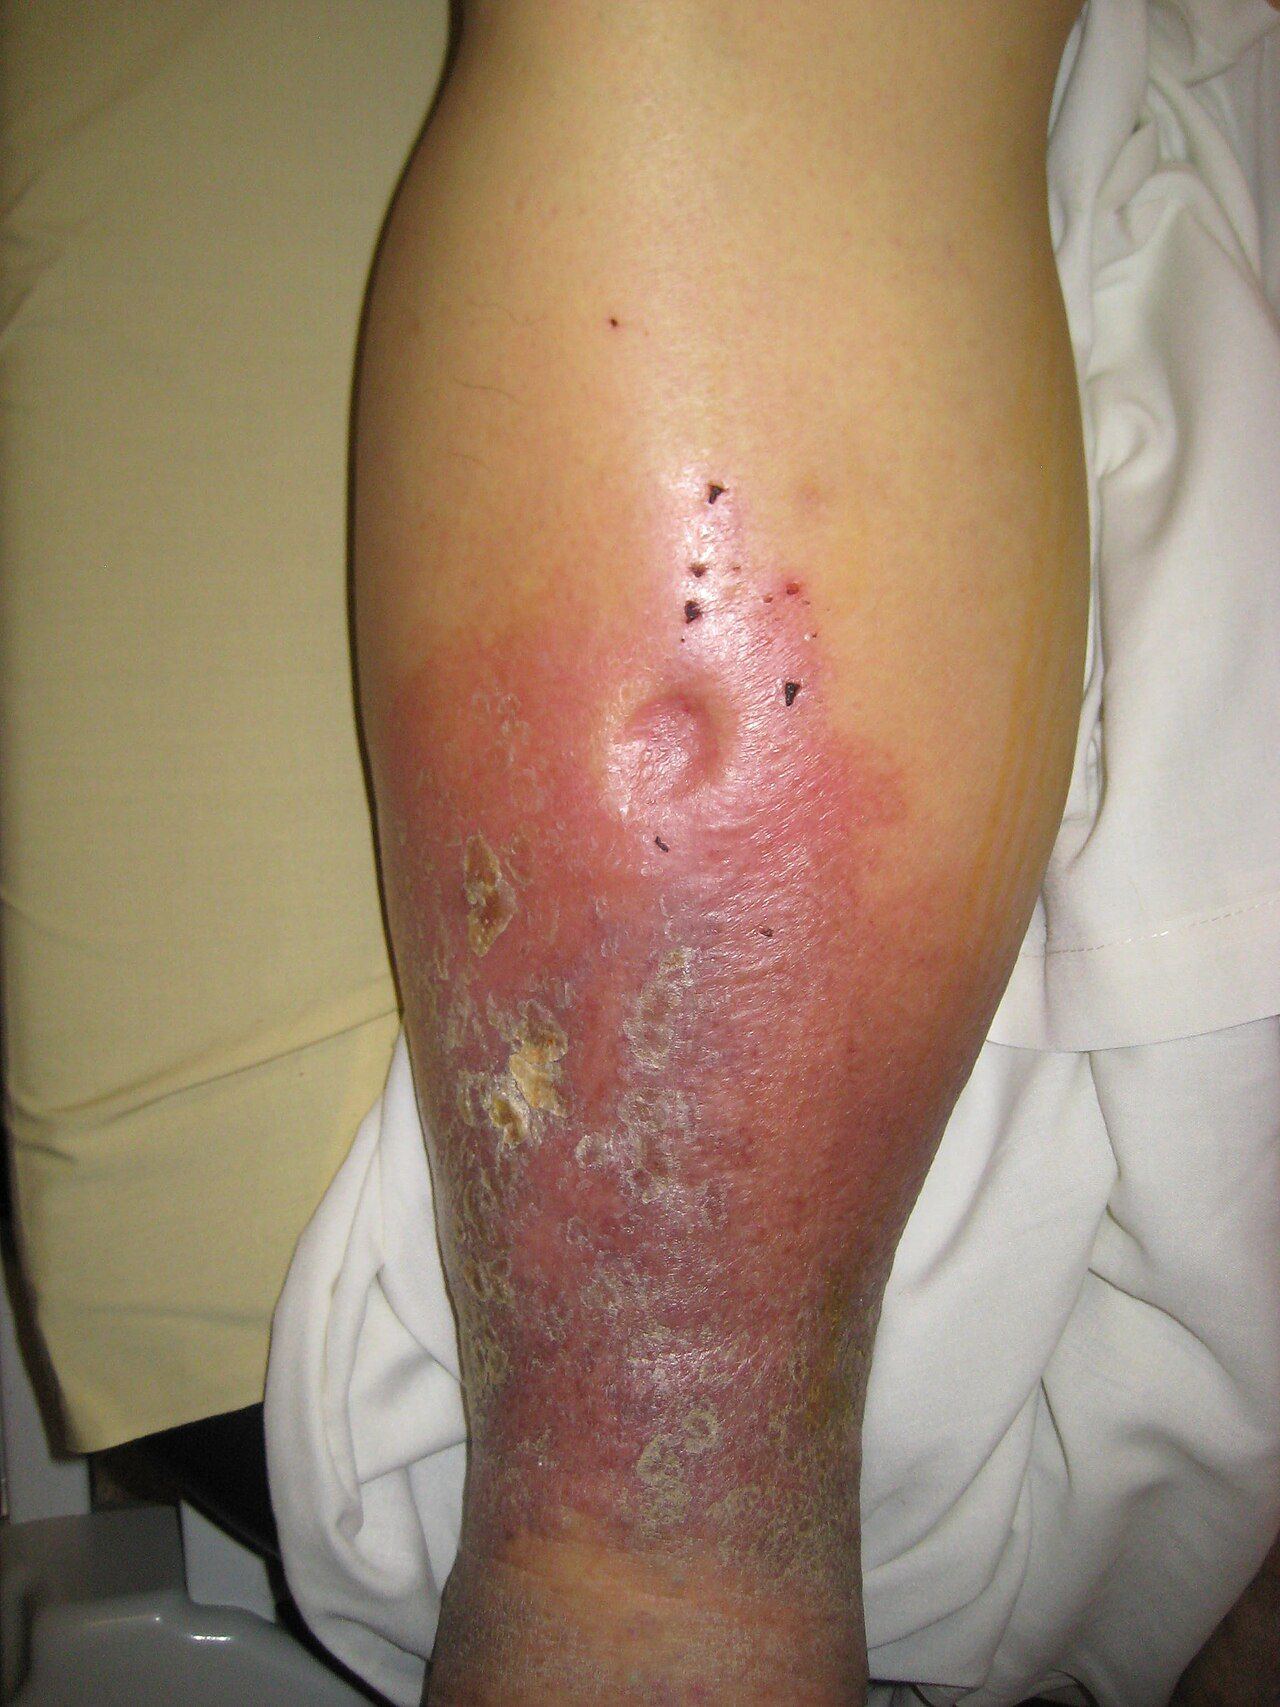
| Skin color (in richly pigmented skin, judge these on the sole, the nail beds and against the opposite limb, and weigh temperature, pulses and capillary refill more heavily than color) | Pallor on elevation, dependent rubor (dusky red when the leg hangs down; may read as deepened brown or gray rather than red) | Brown hemosiderin staining around the ankles, stasis dermatitis; on darker skin the staining may be barely distinguishable from surrounding tone, so palpate for the firm, thickened texture |
| Temperature | Cool to cold | Warm |
| Skin and nails | Thin, shiny, taut, hairless; thick brittle nails | Thickened, sometimes weeping; hair usually present |
| Edema | Minimal or absent | Present, often marked; improves overnight |
| Ulcer location | Toes, heels, lateral malleolus, over pressure points | Medial malleolus, gaiter area |
| Ulcer appearance and pain | Punched-out, well-defined edges, pale or necrotic base; very painful | Irregular edges, ruddy granulation base, exudate; mildly painful |
| Capillary refill | Prolonged, over 3 seconds | Usually normal |
| Key nursing implication | Never elevate an ischemic leg and never apply compression without an ABI and an order | Elevate above heart level; compression therapy is the mainstay once arterial disease is excluded |
The vascular emergencies
Acute arterial occlusion is memorized as the six Ps: Pain (sudden and severe), Pallor, Pulselessness, Paresthesia, Paralysis and Poikilothermia (the limb takes on room temperature, feeling cold). Pain and pulselessness come first; paresthesia and paralysis are late and signal nerve and muscle death. Pallor is the least reliable of the six in richly pigmented skin — compare the sole, palm and nail beds against the opposite limb, and weigh sudden pain, absent pulses, coolness and numbness far more heavily than color. The limb is generally salvageable for only about six hours, so this is a call-now finding, not an end-of-shift note. The same six Ps drive neurovascular checks after orthopedic surgery, casting or trauma, where they also warn of compartment syndrome — in which the earliest and most reliable sign is pain out of proportion to the injury and pain on passive stretch of the muscle, appearing well before any pulse disappears. A cast that feels tight and a patient asking for more analgesia than the injury explains is an emergency assessment, not a medication question.
Deep vein thrombosis presents as unilateral calf or thigh swelling, warmth, erythema or a dusky discoloration, tenderness along the deep venous course, and sometimes a low-grade fever. Measure and compare calf circumferences and document both numbers. Do not perform Homans sign. Dorsiflexing the foot to elicit calf pain has poor sensitivity and poor specificity, is positive in many patients without thrombosis and negative in many with it, and offers no benefit that justifies manipulating a possibly clotted limb. Assess instead for the constellation of findings, escalate for imaging, and watch for the complication that actually kills: sudden dyspnea, pleuritic chest pain, tachycardia and hypoxemia signaling pulmonary embolism.
Elevation is the fork in the road. Elevating a venous leg drains it and relieves the ache; elevating an arterial leg removes what little gravity-assisted perfusion the foot had and can turn ischemia into necrosis. Before you prop a swollen leg on pillows or apply a compression stocking, ask one question: are the pulses there and is the foot warm?
Compare limb to limb and grade what you feel: a cool, pale, pulseless, painful extremity is an arterial emergency with a six-hour clock, while a warm, swollen, brown-stained ankle with palpable pulses is chronic venous disease.
Section 5Red Flags, Lifespan Variation, Documentation and Escalation
Findings that mean escalate now
Chest pain is assessed with a structured tool — OPQRST: onset, provocation and palliation, quality, region and radiation, severity on a 0 to 10 scale, and timing. But do not let the absence of classic chest pain reassure you. Women, older adults and people with diabetes frequently present with no chest pain at all: unexplained fatigue, dyspnea, nausea, indigestion, diaphoresis, back, jaw or shoulder discomfort, or simply new confusion may be the entire presentation of an acute coronary syndrome. Diabetic neuropathy blunts the pain signal, and a silent infarction is still an infarction.
| Red flag | Why it is urgent | Immediate nursing action |
|---|---|---|
| New or worsening chest pain, pressure or heaviness, especially with diaphoresis, nausea or dyspnea | Acute coronary syndrome; myocardium dies by the minute | Stay with the patient, vital signs, oxygen if saturation is under the ordered target, obtain a 12-lead ECG within 10 minutes, notify the provider, follow the chest-pain protocol for nitroglycerin and aspirin |
| New irregularly irregular rhythm, or a new pulse deficit | New atrial fibrillation with loss of atrial kick and stroke risk | Apical rate for a full minute, blood pressure, mental status and neurologic check, ECG, notify |
| Heart rate under 50 with symptoms, or over 150 | Cardiac output falls at both extremes — too few beats per minute when the rate is slow, and too little diastolic filling time when it is fast | Full vital signs, ECG, assess perfusion and level of consciousness, notify urgently. Before any rate-slowing drug, check the ordered parameters, which usually specify a minimum blood pressure as well as a minimum heart rate; hold the dose and notify if the patient falls outside them |
| Beck’s triad: hypotension, jugular venous distention, muffled heart sounds | Cardiac tamponade — obstructive shock | Emergency. Rapid response, oxygen, large-bore access, prepare for pericardiocentesis |
| New S3 in a patient over 40, plus weight gain, orthopnea or new crackles | Decompensating heart failure — S3 often precedes the crackles | Daily weight, intake and output, upright positioning, oxygen per order, notify before the patient needs intubation |
| Cool, pale, pulseless, painful extremity (six Ps) | Acute arterial occlusion — roughly six hours to save the limb | Do not elevate, do not apply heat or cold, do not massage the limb; keep it at or slightly below heart level, mark pulse sites, keep the patient nothing by mouth pending possible revascularization, notify vascular surgery immediately |
| Pain out of proportion after a cast, fracture or vascular procedure, worse on passive stretch | Compartment syndrome; pulses are preserved until very late | Do not elevate above heart level, do not bivalve a cast on your own authority, notify surgery urgently |
| New unilateral leg swelling, warmth and pain, then sudden dyspnea or pleuritic chest pain | Deep vein thrombosis progressing to pulmonary embolism | Do not massage the calf, oxygen, vital signs, escalate urgently. Hold ambulation only until the patient is evaluated and anticoagulation is started — prolonged bed rest is outdated and once treatment begins early ambulation is safe and encouraged |
| Systolic drop of 20 mmHg or diastolic drop of 10 mmHg on standing, with symptoms | Orthostatic hypotension — a fall and syncope risk | Return the patient to bed, initiate fall precautions, review antihypertensives and diuretics, notify |
| Blood pressure 180/120 or higher with headache, visual change, chest pain, dyspnea or neurologic change | Hypertensive emergency with end-organ damage | Repeat in the other arm, neurologic check, notify immediately — this is not a “recheck in an hour” number |
| Blood pressure 140/90 or higher after 20 weeks of pregnancy, especially with headache, epigastric pain or visual change | Preeclampsia; 160/110 or higher is severe range | Repeat after 15 minutes with correct cuff size, assess reflexes and proteinuria per protocol, notify obstetrics immediately |
| Bleeding or expanding hematoma at a femoral sheath or catheterization site | Arterial bleeding can be rapid and concealed retroperitoneally | Hold direct pressure above the puncture site, keep the leg straight, vital signs, call for help without leaving the patient |
Lifespan and skin-tone variation
Infants and children. The apical impulse sits higher and more laterally the younger the child: in an infant and toddler it is at the fourth intercostal space slightly lateral to the midclavicular line, from about age four to six it is at the fourth space at the midclavicular line, and by roughly age seven it has descended to the adult position at the fifth space at or just medial to the midclavicular line. Sinus arrhythmia — heart rate accelerating with inspiration and slowing with expiration — is a normal, healthy finding in children and young adults. Count apically for a full minute. Innocent murmurs are extremely common in childhood; the reassuring features are grade I to II, systolic only, no radiation, marked change with position, and a completely well child with normal growth. The alarming pediatric findings are a diastolic murmur, a murmur with a thrill, cyanosis — which in a darker-skinned infant will show as a gray or ashen tongue, oral mucosa and nail beds rather than a blue tint, so look in the mouth and not only at the skin — poor feeding, diaphoresis with feeds, failure to thrive, hepatomegaly and weak or delayed femoral pulses. Remember that in infants bradycardia is a hypoxia sign, and that in children hypotension is a very late sign of shock — prolonged capillary refill, cool mottled extremities, weak peripheral pulses and tachycardia come first.
Pregnancy. Blood volume rises 30 to 50 percent, cardiac output rises 30 to 50 percent, resting heart rate rises 10 to 20 beats per minute, and systemic vascular resistance falls so that diastolic pressure drops 10 to 15 mmHg in the second trimester before returning to baseline near term. The heart is displaced upward and to the left, so the apical impulse shifts up and laterally. A soft systolic ejection murmur and an S3 are found in most pregnancies and are physiologic. A diastolic murmur is not. From about 20 weeks, position the patient in a left lateral tilt rather than flat supine, because the gravid uterus compresses the inferior vena cava and can drop cardiac output sharply — supine hypotensive syndrome. Dependent edema of the feet and ankles is expected; sudden facial or hand edema with headache or visual change is preeclampsia until proven otherwise.
Older adults. Arteries stiffen, so systolic pressure and pulse pressure rise and isolated systolic hypertension is common. Ventricular compliance falls, so an S4 is a frequent and often benign finding while an S3 remains ominous. A soft systolic murmur from aortic sclerosis is very common. Baroreceptor reflexes blunt, making orthostatic hypotension and falls more likely, especially with diuretics, antihypertensives and after prolonged bed rest. Maximum heart rate and the ability to mount a tachycardia both decline, and a beta blocker will mask the tachycardia of hemorrhage or sepsis entirely — so a “normal” heart rate of 78 in a septic older adult on metoprolol is not reassurance. Peripheral pulses become harder to palpate as vessels calcify, and the presenting sign of a myocardial infarction may be confusion, a fall, weakness or dyspnea rather than pain.
Skin tone. Color changes central to cardiovascular assessment are unreliable when judged only on the outer skin of patients with richly pigmented skin. Assess the oral mucosa, tongue, lips, conjunctivae, palms, soles and nail beds, in natural or full-spectrum light. Central cyanosis appears as a gray or ashen cast to the lips, tongue and oral mucosa rather than a blue tint, and requires roughly 5 g/dL of deoxygenated hemoglobin — so it is a late sign in anyone and may never appear in a profoundly anemic patient. Pallor may present as ashen, gray or yellow-brown rather than white; check the conjunctivae and palmar creases. Erythema, as in cellulitis or phlebitis, may appear violaceous, deep brown or simply darker than surrounding skin, and is often easier to feel than to see — compare warmth, induration and tenderness against the opposite limb, and outline the border with a skin pen and time it so progression is measurable. Dependent rubor and hemosiderin staining are likewise subtler; rely on temperature, pulses, capillary refill and the pattern of hair loss. Finally, remember that pulse oximetry systematically overestimates arterial saturation in patients with darker skin pigmentation, producing occult hypoxemia; when the number looks acceptable but the patient looks unwell, believe the patient.
Charting the cardiovascular exam
Chart what you measured and observed, not what you concluded. Include rate and rhythm with the method used, the location and character of the apical impulse, the sounds at each area, the murmur description with its grade as a fraction, pulses with their grade and whether Doppler was needed, edema with depth and level, capillary refill, temperature and color of the extremities, jugular venous pressure with the head-of-bed angle, and the patient’s own words in quotation marks.
| Vague and indefensible | Precise and useful |
|---|---|
| “Heart sounds normal. Pulses present.” | “0800. Apical rate 76, regular, counted 60 seconds; radial 76, no pulse deficit. BP 118/72 right arm, sitting, adult cuff. S1 and S2 crisp at all five areas, no S3, no S4, no murmur, no rub. PMI at fifth ICS, left MCL, approximately 2 cm, non-sustained. No heaves or thrills. JVP 2 cm above sternal angle at 45 degrees. Radial, dorsalis pedis and posterior tibial pulses 2+ and equal bilaterally. Extremities warm and dry, capillary refill under 2 seconds, no edema.” |
| “Legs swollen. Elevated.” | “1500. Bilateral pitting edema of both lower legs, 4 mm pits with rebound at approximately 12 seconds, extending to mid-calf; right calf 39 cm, left calf 38.5 cm at 10 cm below the tibial tuberosity. Both feet warm, dorsalis pedis and posterior tibial 2+ bilaterally, capillary refill under 2 seconds. Weight 84.2 kg, up 1.4 kg from 0600 yesterday. New S3 at apex, bell, left lateral position. JVP 5 cm above sternal angle at 45 degrees. Patient states ‘I had to sleep on three pillows last night, I usually use one.’ Legs elevated, provider notified 1508 — see SBAR note.” |
| “Foot looks bad. Will monitor.” | “2140. Right foot pale and cool to mid-calf compared with warm left foot. Right dorsalis pedis and posterior tibial not palpable and not audible by Doppler; left 2+ both sites. Capillary refill right great toe over 5 seconds. Patient reports sudden severe right foot pain rated 9/10 starting at 2120 and new numbness of the toes. Right foot kept level, no heat or cold applied. Rapid response activated 2142, vascular surgery notified.” |
Chart the negatives that matter. “No murmur, no rub, no gallop, no jugular distention, no edema, pulses 2+ and equal” is not filler — it is the record that proves you looked, and it is the baseline that lets the next nurse prove the patient changed. A note reading only “heart sounds normal” cannot show anything.
Delegation, scope and the SBAR call
Apply the five rights of delegation: right task, right circumstance, right person, right direction and communication, right supervision and evaluation. The registered nurse may delegate routine data collection on a stable patient, but never delegates assessment, interpretation, teaching, evaluation, or any aspect of care for an unstable or deteriorating patient. Delegating the task never transfers accountability for the outcome.
| May be delegated to UAP (stable patient, facility policy permitting) | Stays with the RN — never delegated |
|---|---|
| Measuring blood pressure with an automated cuff and reporting the number | Interpreting a blood pressure trend and deciding whether to hold an antihypertensive |
| Counting and reporting a radial pulse | Auscultating an apical pulse, identifying a rhythm, and measuring a pulse deficit |
| Applying antiembolism stockings or sequential compression devices already ordered and sized | Deciding whether compression is safe — that requires an arterial assessment |
| Obtaining a daily weight and recording intake and output | Interpreting a 1.4 kg overnight weight gain and its implication for heart failure |
| Repositioning, elevating legs per the established plan of care, ambulating a stable patient | Doppler pulse assessment, neurovascular checks, capillary refill interpretation |
| Reporting observations such as “his legs look more swollen” or “she felt dizzy standing up” | Teaching about sodium restriction, daily weights or anticoagulants; care of any patient with chest pain, new dysrhythmia or a compromised limb |
When a red flag appears, escalate with SBAR. Have the chart, the last two sets of vital signs, the medication list and the most recent laboratory values in front of you before you dial. A worked example: Situation — “This is Priya Raman, RN, on 6 East. I am calling about Mr. Whitfield in room 618, a 71-year-old admitted two days ago with a heart failure exacerbation. He has new orthopnea and his weight is up 1.4 kilograms since yesterday morning.” Background — “He has a history of ischemic cardiomyopathy with an ejection fraction of 30 percent, hypertension and chronic kidney disease. He is on furosemide 40 milligrams IV twice daily, metoprolol and lisinopril. Admission weight was 82.8 kilograms; this morning he is 84.2. Baseline blood pressure has been running around 118 over 70.” Assessment — “Apical rate 104 and regular, blood pressure 102 over 64, respirations 26, SpO2 91 percent on room air rising to 95 percent on 2 liters nasal cannula. He now has an S3 at the apex that was not there yesterday, jugular venous pressure 5 centimeters above the sternal angle at 45 degrees, bilateral pitting edema to mid-calf at 4 millimeters, and fine crackles at both bases that do not clear with cough. He needed three pillows last night instead of one. Urine output has been 20 milliliters an hour for the last four hours. Pedal pulses are 2 plus and both feet are warm.” Recommendation — “I think he is decompensating and I would like him seen now. I am requesting an additional diuretic dose, a basic metabolic panel and BNP, a chest x-ray, and an order for oxygen to keep his saturation above 92 percent. Do you want strict intake and output and a repeat weight this evening? Can you come to the bedside?” Then close the loop: read the orders back, document the time of the call and the response, and reassess after the intervention.
A new S3, a rising weight, a new irregular rhythm or a limb that has lost its pulse are all escalation events — assess, measure, and call with SBAR rather than waiting for the next scheduled round.
The chapter in one breath
The cardiovascular exam follows the same fixed order as the rest of the body — inspection, palpation, percussion, auscultation — with the abdomen standing alone as the exception where auscultation moves ahead of percussion and palpation. Count ribs from the sternal angle to find the aortic, pulmonic, Erb’s point, tricuspid and mitral areas, and remember that S1 closes the AV valves and opens systole at the apex while S2 closes the semilunar valves and ends systole at the base. Hold the real numbers: adult heart rate 60 to 100 and blood pressure under 120 over 80, newborn heart rate 100 to 205, an apical impulse 1 to 2 cm at the fifth intercostal space and left midclavicular line, jugular pulsation no more than 3 cm above the sternal angle at 30 to 45 degrees, capillary refill under 2 seconds, pulses 2+ and symmetric, and an ankle-brachial index of 1.00 to 1.40. Use the diaphragm firmly for high-pitched sounds and the bell lightly at the apex in the left lateral position for S3 and S4, and never dismiss a diastolic murmur. In the limbs, cool and pulseless and painful means arterial and never elevate; warm and swollen and brown-stained means venous and elevate. Chart what you measured, delegate only routine data collection on stable patients, and escalate with SBAR.
Words worth knowing
| Term | What it means |
|---|---|
| Ankle-brachial index (ABI) | Ankle systolic pressure divided by the higher brachial systolic pressure; 1.00 to 1.40 is normal, 0.90 or less indicates peripheral arterial disease, and above 1.40 indicates non-compressible calcified vessels. |
| Beck’s triad | Hypotension, jugular venous distention and muffled heart sounds — the classic combination of cardiac tamponade. |
| Bruit | A blowing or swishing sound of turbulent arterial flow, heard with the bell over a carotid, femoral, renal or aortic vessel; always reported. |
| Capillary refill | Time for color to return to a compressed nail bed held at heart level; normally under 2 seconds in adults and children, up to 3 seconds in neonates. |
| Claudication | Reproducible cramping muscle pain brought on by a predictable amount of walking and relieved by rest; the hallmark symptom of peripheral arterial disease. |
| Dependent rubor | Dusky red discoloration of a foot when it hangs down, with pallor on elevation; a sign of chronic arterial insufficiency. |
| Erb’s point | The third intercostal space at the left sternal border, where S1 and S2 are roughly equal and many murmurs are audible. |
| Hepatojugular reflux | A sustained rise in jugular venous pressure of more than 3 cm during 10 to 15 seconds of firm right upper quadrant pressure, suggesting the right ventricle cannot accept more volume. |
| Jugular venous pressure (JVP) | The vertical height of the internal jugular pulsation above the sternal angle with the head of the bed at 30 to 45 degrees; normally 3 cm or less. |
| Levine scale | The six-point murmur intensity scale, written as a fraction; grade IV/VI and above always includes a palpable thrill. |
| Point of maximal impulse (PMI) | The apical impulse, normally 1 to 2 cm at the fifth intercostal space at or just medial to the left midclavicular line; displaced laterally and downward in left ventricular dilation. |
| Pulse deficit | The difference between the apical and radial rates counted over the same minute; indicates contractions too weak to perfuse the periphery, as in atrial fibrillation. |
| Pulse pressure | Systolic minus diastolic pressure, normally about 30 to 40 mmHg; narrow with low stroke volume, wide with stiff arteries or aortic regurgitation. |
| S1 | Closure of the mitral and tricuspid valves; the beginning of systole, loudest at the apex. |
| S2 | Closure of the aortic and pulmonic valves; the end of systole, loudest at the base, normally split on inspiration. |
| S3 (ventricular gallop) | A low-pitched early diastolic sound heard with the bell at the apex; physiologic under about age 40 and in pregnancy, a sign of volume overload and heart failure after that. |
| S4 (atrial gallop) | A low-pitched late diastolic sound from atrial contraction against a stiff ventricle; impossible in atrial fibrillation. |
| Six Ps | Pain, pallor, pulselessness, paresthesia, paralysis and poikilothermia — the signs of acute arterial occlusion, with roughly a six-hour window to save the limb. |
| Thrill | A palpable purring vibration over a valve area from turbulent flow; its presence makes a murmur at least grade IV/VI. |
| Heave (lift) | A sustained forceful precordial thrust that lifts the palpating hand; suggests ventricular hypertrophy. |