Assessing Skin, Hair and Nails
The integument is the only organ you can examine in full without a single piece of technology, and it is the organ most likely to tell you something before the monitor does. Skin reports perfusion, oxygenation, hydration, hepatic function, nutrition, immune status, medication reactions and — bluntly — the quality of the nursing care a patient has received. A pressure injury is one of the few adverse events that is almost always preventable and almost always attributable, which is why regulators count them. This chapter teaches you to look with intent rather than glance: how to set up the room and the light, how to move through inspection and palpation in a fixed order so you never skip the heel or the sacrum or the skin under the oxygen tubing, how to name a lesion by its primary morphology and size, how to recognize pallor, cyanosis, jaundice and erythema in every skin tone rather than only in pale skin, how to stage a pressure injury without reverse–staging it, how to chart what you saw in words a wound nurse can act on, and when to stop charting and escalate by SBAR right now.
By the end of this chapter you can
- Describe the layers and appendages of the integumentary system and explain what each structure allows you to infer at the bedside.
- Perform a systematic skin, hair and nail examination using inspection and palpation in sequence, and state where this differs from the standard inspection, palpation, percussion, auscultation order and why the abdomen is the exception.
- Assess skin turgor, temperature, moisture, texture, capillary refill and edema, and report exact values and grades rather than adjectives.
- Differentiate primary from secondary lesions by morphology and size in centimeters, and describe configuration, distribution and blanching.
- Identify pallor, cyanosis, jaundice and erythema across the full range of skin tones by examining oral mucosa, conjunctivae, palms, soles and sclerae, and by palpating for warmth and induration.
- Recognize expected variations in newborns, children, pregnancy and older adults, including acrocyanosis, milia, striae gravidarum and senile purpura.
- Stage a pressure injury from Stage 1 through Stage 4, unstageable and deep tissue pressure injury, distinguish it from moisture–associated skin damage, and apply the Braden Scale.
- Document a skin or wound finding in precise, measurable, reproducible language and contrast it with a vague entry.
- Name the integumentary red flags that require escalation within minutes, deliver that escalation using SBAR, and state which skin–related tasks may be delegated to UAP and which may not.
Section 1The Skin as an Organ You Can Actually See
Three layers, and what each one tells you
The epidermis is avascular, thin as tissue paper over the eyelid and thick as a callus over the sole, and it turns over roughly every 28 days. Because it has no blood supply of its own, it is nourished by diffusion from the dermis below — which is exactly why a patient with poor perfusion gets shiny, fragile, slow–healing skin. The basal layer holds melanocytes. Every person has approximately the same number of melanocytes; what differs across skin tones is how much melanin those cells produce and how it is packaged. This single fact matters enormously at the bedside: it means a patient with deeply pigmented skin has the same underlying physiology of pallor, cyanosis and erythema as a patient with pale skin, but the visual signal is filtered through pigment. You do not change the assessment. You change where you look.
The dermis is the working layer: collagen and elastin for tensile strength and recoil, capillary loops for the color you see through the epidermis, sensory nerve endings for touch, pressure, temperature and pain, and the sebaceous and sweat glands. When you assess turgor you are testing dermal elastin and interstitial fluid. When you see erythema you are seeing dilated dermal capillaries. When a Stage 2 pressure injury shows a pink, moist, shiny wound bed, you are looking directly at exposed dermis — and because the dermis holds the nerve endings, that wound hurts. A wound that has destroyed the dermis entirely, on the other hand, may be strangely painless, which is a warning sign rather than a reassurance.
The subcutaneous layer (hypodermis) is adipose and connective tissue. It insulates, cushions bony prominences and stores energy. This is why the cachectic patient, the frail older adult and the critically ill patient who has lost 12 kg in three weeks are at extreme pressure–injury risk: the padding over the sacrum, ischial tuberosities, greater trochanters, heels and occiput is simply gone. When you can see visible adipose in a wound bed, you are looking at a full–thickness injury — at minimum a Stage 3.
The appendages: hair, nails and glands
Hair follicles, nails, eccrine sweat glands, apocrine glands and sebaceous glands are all epidermal derivatives, which is why systemic illness marks all of them at once. Eccrine glands are distributed nearly everywhere and are your thermoregulatory workhorse; diaphoresis in a patient who is not hot is a sympathetic surge and deserves a set of vital signs, not a towel. Apocrine glands sit in the axillae and groin, become active at puberty and produce body odor when bacteria act on their secretions. Sebaceous glands produce sebum, which keeps the stratum corneum pliable; they decline with age, which is one reason older adults develop xerosis (dry, scaling, itchy skin) and why moisturizing is a nursing intervention rather than a courtesy.
Nails are keratinized plates growing from the nail matrix under the proximal fold. Fingernails grow about 0.1 mm per day — roughly 3 mm per month, so a full fingernail replaces itself in about six months. Toenails grow at about a third of that rate and take 12 to 18 months. That growth rate is clinically useful: if you see a transverse groove (a Beau line) 6 mm from the cuticle, the systemic insult that arrested nail growth happened roughly two months ago. Hair likewise grows in cycles, and a diffuse shed two to three months after a major stressor — childbirth, sepsis, surgery, severe illness — is telogen effluvium, not disease.
Functions, and the assessment question each one implies
Teaching the functions of skin as a memorized list wastes them. Each function is really an assessment question. Barrier: is the skin intact, and where is it not? Thermoregulation: is this patient hot, cold, diaphoretic, mottled? Sensation: can this patient feel the pressure of their own heel on the mattress, or has neuropathy, spinal cord injury, sedation or an epidural taken that protective feedback away? Vitamin D synthesis, immune surveillance via Langerhans cells, fluid and electrolyte conservation, excretion, and identity — the face and hands a patient recognizes as their own. That last one is not sentimental. Disfiguring skin disease and visible wounds carry real psychological weight, and a patient who will not look at their own stoma or their own burn is telling you something you must document and address.
| Structure | What it does | What its failure looks like at the bedside |
|---|---|---|
| Epidermis / stratum corneum | Barrier to microbes, chemicals, water loss | Maceration, skin tears, fissures, portal of entry for infection |
| Melanocytes (basal layer) | Melanin production, UV protection | Hyper– or hypopigmentation after inflammation; melanoma |
| Dermal capillary loops | Perfusion, color, thermoregulation | Pallor, cyanosis, mottling, prolonged capillary refill |
| Collagen and elastin | Strength and recoil | Tenting (poor turgor), striae, senile purpura, fragile tearing skin |
| Dermal nerve endings | Touch, pressure, temperature, pain | Unfelt pressure, unnoticed burns, painless diabetic foot ulcer |
| Subcutaneous adipose | Cushion over bony prominences, insulation | Rapid pressure injury in cachexia; visible fat in a Stage 3 wound |
| Eccrine glands | Thermoregulatory sweat | Diaphoresis with shock, pain, hypoglycemia; anhidrosis with heat stroke |
| Sebaceous glands | Sebum, skin pliability | Xerosis, pruritus, cracking — especially in older adults |
| Nail matrix | Continuous nail plate growth | Beau lines, splinter hemorrhages, clubbing, koilonychia |
Melanocyte number is essentially the same in all humans; melanin output is what varies. So the physiology of cyanosis is identical in every patient — only the viewing window changes. When pigment obscures the skin surface, move to the conjunctivae, oral mucosa, tongue, palms and soles, and compare the patient to their own baseline rather than to a photograph in a textbook.
Baseline variation across the lifespan
Nothing in skin assessment makes sense until you know what is normal for the age in front of you. A newborn is covered in vernix caseosa and fine lanugo, has pinpoint white milia across the nose and chin, and commonly develops erythema toxicum neonatorum — blotchy erythematous macules with tiny central papules appearing at 24 to 72 hours and resolving on its own. Acrocyanosis (blue hands and feet with a pink trunk and pink mucous membranes) is expected in the first 24 to 48 hours of life. Central cyanosis — blue lips, tongue and oral mucosa — is never normal at any age. Congenital dermal melanocytosis, the blue–gray patches over the sacrum and buttocks seen most often in infants with darker skin tones, is a benign finding that must be documented on admission with location and size so it is never mistaken for bruising.
Older adults lose dermal thickness, elastin, subcutaneous fat, sebum and capillary density. Expect thin, dry, wrinkled, cool skin; solar lentigines (liver spots); seborrheic keratoses (the greasy, stuck–on brown plaques); cherry angiomas; and senile purpura — flat, dark purple patches on the forearms and dorsal hands from fragile vessels and thin dermis, which is not evidence of abuse by itself. Turgor is unreliable over the hand in an older adult; test over the sternum or below the clavicle instead. In pregnancy expect melasma, linea nigra, striae gravidarum, spider angiomas and palmar erythema, all driven by estrogen and increased cutaneous blood flow.
| Group | Expected findings | Do not mistake for |
|---|---|---|
| Newborn / neonate | Vernix, lanugo, milia, erythema toxicum, acrocyanosis first 24–48 h, congenital dermal melanocytosis, physiologic jaundice appearing after 24 h | Infection, bruising, abuse; jaundice in the first 24 h is pathologic — escalate |
| Infant / toddler | Diaper dermatitis, cradle cap, congenital dermal melanocytosis fading, high surface–area–to–mass ratio | Bruising or abuse — congenital dermal melanocytosis is flat, blue–gray and present from birth, and the term “mongolian spot” is obsolete. Dehydration — test turgor on the abdomen or inner thigh, not the hand |
| Child / adolescent | Acne, increased sebum and apocrine activity, tinea, traction alopecia from tight styles | Tinea capitis mistaken for dandruff; traction alopecia mistaken for a normal hairline. Patterned bruising, or any bruising in a non–ambulatory infant, is a mandated–reporter concern |
| Pregnancy | Melasma, linea nigra, striae gravidarum, spider angiomas, palmar erythema, increased sweating | Severe generalized pruritus of palms and soles with no rash suggests intrahepatic cholestasis — report same day |
| Older adult | Xerosis, thinning, decreased turgor, solar lentigines, seborrheic keratoses, senile purpura, nails that are thickened, longitudinally ridged and brittle with a dull yellow–gray hue but a plate that is still adherent and a clean subungual space, reduced axillary and pubic hair | Dehydration (use sternum), abuse (senile purpura is flat and on extensor forearms). Do not make the reverse error either — thick, yellow–brown, crumbling nails with debris beneath the plate are onychomycosis, not aging, so inspect for crumbling and subungual debris before calling a discolored toenail normal, especially in diabetes or peripheral arterial disease |
Skin is a whole organ with predictable structure, so every visible finding — color, turgor, temperature, texture, a wound bed — maps back to a specific layer or appendage, and knowing the layer tells you how deep the problem goes.
Section 2Technique: How the Examination Is Actually Performed
The order of techniques, and the one exception you must memorize
The standard sequence of physical examination is inspection, palpation, percussion, auscultation — least invasive to most, so that each technique does not corrupt the one after it. For the integument only the first two apply: you inspect, then you palpate. There is nothing to percuss and nothing to auscultate on skin, with the narrow exception of listening over a vascular lesion or graft for a bruit. Learn the four–step order anyway, because it governs every other regional examination in this book.
The exception is the abdomen, and it is the single most tested sequence variation in nursing school: inspect, auscultate, percuss, palpate. Auscultation moves to second position because percussing and palpating the abdomen mechanically stimulates the bowel and alters the frequency and character of bowel sounds. If you palpate first, whatever you hear afterward is an artifact of your own hands. Every other region — skin, thorax, heart, extremities — keeps inspection, palpation, percussion, auscultation.
Two more sequencing rules matter for skin. First, inspect and palpate region by region as you undrape, rather than exposing the whole patient at once; this preserves dignity and warmth and reduces the chance you skip a region. Second, always compare side to side. Symmetry is your control group. A warm, red, swollen left calf means far more when you have just palpated a cool, normal right calf thirty seconds earlier.
Setting up: light, warmth, gloves, ruler
Poor lighting is the most common reason a skin finding is missed. Use natural daylight if you can, or a strong daylight–balanced overhead light plus a penlight; fluorescent light adds a green cast that masks jaundice, and the amber glow of a night light will hide early erythema entirely. Use tangential lighting — shine the penlight across the surface at a low angle — to raise the shadow of a lesion that is flat under direct light and to reveal the subtle contour of a healing wound. Warm the room; a cold patient will be pale, mottled and vasoconstricted, and you will misread perfusion. Perform hand hygiene, wear gloves for any contact with non–intact skin, mucous membrane or drainage, and change gloves and repeat hand hygiene between a wound and clean skin, and between one wound and the next.
Carry a flexible centimeter ruler, not an inch ruler and not your own estimate. “Dime–sized” and “golf–ball–sized” are not measurements and cannot be trended. Carry a penlight, a magnifier if available, and know that a transparent glass slide or clear plastic pressed on a red lesion (diascopy) will tell you whether it blanches — a two–second maneuver that separates a benign erythema from a hemorrhagic rash.
A repeatable head–to–toe route
Use the same route every time so that omission becomes impossible. Scalp and behind the ears, then face, then neck and the skin folds under the chin, then anterior trunk including under the breasts and in the axillae, then arms and hands with the palms and interdigital webs, then abdomen and the panniculus folds, then perineum and the gluteal cleft, then legs, then feet including between every toe and the plantar surfaces, then log–roll and inspect the entire posterior surface: occiput, scapulae, spine, sacrum, ischial tuberosities and heels. Then inspect under and around every device — oxygen tubing over the ears and nares, the nasogastric tube against the nostril, pulse oximeter probes, the collar of a cervical brace, compression sleeves, casts, ID bands, the tubing coiled under the patient’s thigh. Device–related pressure injuries are common and they conform to the shape of the device.
On palpation you are gathering five things: temperature, moisture, texture, turgor and mobility, plus tenderness and any masses. Use the dorsum of your hand for temperature because it is more thermally sensitive than the palm, and compare bilaterally. Test turgor by gently pinching a fold of skin — over the sternum or beneath the clavicle in adults and especially in older adults, over the abdomen or inner thigh in infants. Expected: the fold returns immediately, in under 2 seconds. Tenting that persists 3 seconds or more suggests volume depletion, though it is unreliable in isolation in older adults, so pair it with mucous membranes, urine output, orthostatic vital signs and daily weight. Assess capillary refill by pressing the nail bed or a fingertip pulp for 5 seconds and releasing; expected refill is under 2 seconds in adults and children.
| What you palpate | Expected (normal) | Abnormal | What abnormal suggests |
|---|---|---|---|
| Temperature (dorsum of hand, bilateral) | Warm, equal side to side | Generalized cool; unilateral cool; localized hot | Shock or hypothermia; arterial occlusion in that limb; cellulitis, abscess or inflammation |
| Moisture | Dry with minimal dampness in folds | Diaphoresis; drenching sweats; very dry and flaking | Pain, fever, hypoglycemia, MI, sympathetic surge; dehydration, hypothyroidism, xerosis |
| Texture | Smooth, soft, even | Rough, thickened; velvety hyperpigmented axillae; paper–thin | Hypothyroidism; acanthosis nigricans and insulin resistance; steroid use, aging |
| Turgor (sternum in adults) | Recoils immediately, under 2 s | Tenting 3 s or more | Volume depletion; unreliable alone in older adults |
| Capillary refill | Under 2 s | Over 3 s with cool, mottled skin | Poor perfusion, hypovolemia, shock, arterial compromise |
| Mobility and edema | Skin lifts and returns; no pitting | Pitting graded 1+ to 4+; non–pitting brawny edema | Heart failure, hypoalbuminemia, venous insufficiency, DVT; lymphedema |
Edema, and the numbers that frame every skin finding
Grade pitting edema by pressing your thumb firmly over a bony prominence — the tibia, the medial malleolus, the dorsum of the foot, or the sacrum in a bedbound patient — for 5 seconds and then observing the indentation. The conventional scale is 1+ = about 2 mm, barely detectable, rebounds immediately; 2+ = about 4 mm, rebounds in a few seconds; 3+ = about 6 mm, deep pit, the limb looks swollen, rebound may take 10 to 30 seconds; 4+ = about 8 mm, very deep pit, gross swelling, indentation lasts more than 30 seconds. Record the grade, the depth, the location and how far up the limb it extends: “3+ pitting edema bilateral lower extremities to mid–calf” is usable data.
Skin findings are interpreted against vital signs, so know the real numbers. In a healthy adult: oral temperature 36.5 to 37.5 °C (97.7 to 99.5 °F) with an average near 37 °C (98.6 °F); pulse 60 to 100 beats per minute; respirations 12 to 20 per minute; blood pressure less than 120/80 mm Hg as normal; oxygen saturation 95 to 100 percent on room air. A hot, red, tender leg with a temperature of 38.6 °C, a heart rate of 118 and a systolic of 88 is not a dermatology consult — it is sepsis until proven otherwise.
| Age group | Heart rate (bpm) | Respirations (per min) | Typical systolic BP (mm Hg) |
|---|---|---|---|
| Newborn (0–1 month) | 100–160 | 30–60 | 60–90 |
| Infant (1–12 months) | 100–150 | 25–40 | 70–100 |
| Toddler (1–3 years) | 90–140 | 20–35 | 80–110 |
| Preschool (3–5 years) | 80–120 | 20–30 | 85–110 |
| School–age (6–12 years) | 70–110 | 18–25 | 90–120 |
| Adolescent (13–18 years) | 60–100 | 12–20 | 100–120 |
| Adult | 60–100 | 12–20 | Less than 120 (with diastolic less than 80) |
| Older adult (65+) | 60–100 | 12–20 | Often higher; widened pulse pressure common |
Two lifespan cautions. Infants and young children lose heat fast because of a high body–surface–area–to–mass ratio and thin subcutaneous fat, so uncover them briefly and re–cover them. Older adults run a lower baseline temperature and blunt the febrile response, so a reading of 37.8 °C (100 °F), or a rise of 1.1 °C (2 °F) above that person’s own baseline, can represent significant infection — a cellulitis in an 84–year–old may present as new confusion and a temperature of 37.6 °C rather than a spiking fever.
If you learn only one sequencing fact this year, learn this one: every region is inspect, palpate, percuss, auscultate — except the abdomen, which is inspect, auscultate, percuss, palpate, because palpating first stimulates the bowel and changes the very sounds you are about to listen for.
A skin examination is only as good as its setup and its route: strong tangential light, a warm room, gloves, a centimeter ruler, a fixed head–to–toe path that includes the posterior surface, between the toes and under every device, and bilateral comparison at every step.
Section 3Color, Lesions and Vascular Findings — Normal Beside Abnormal
Reading color in every skin tone
The traditional description of cyanosis as “bluish skin” and pallor as “white skin” was written for one narrow band of complexions, and students who learn it that way miss hypoxia in patients with deeply pigmented skin. Fix this by changing your viewing windows, not your standards. For cyanosis, examine the oral mucosa, tongue, lips, conjunctivae, nail beds, palms and soles; in darker skin tones cyanosis appears ashen, gray or dusky rather than blue, and the tongue and buccal mucosa are the most reliable sites because they are minimally pigmented in almost everyone. Never wait for cyanosis to diagnose hypoxia; it requires roughly 5 g/dL of deoxygenated hemoglobin, which means a severely anemic patient can be dangerously hypoxic and never turn blue at all.
For pallor, examine the conjunctivae, oral mucosa, nail beds and palmar creases. In brown skin, pallor may look yellow–brown; in black skin, ashen or gray; the underlying skin loses its normal red undertone. For jaundice, examine the sclerae (near the limbus, avoiding the peripheral fat pad, which can look yellow normally in darker–skinned patients), the hard palate under bright light, the sublingual area, and the palms and soles. For erythema, do not rely on redness at all in deeply pigmented skin: it presents as a deeper violet, purple, maroon or eggplant hue and is often invisible under artificial light. Instead palpate — compare the area to the same site on the opposite side for increased warmth, induration, firmness, boggy softness, edema and tenderness, and ask the patient whether that spot itches, burns or hurts. Warmth and induration in a patient reporting pain over a bony prominence is a Stage 1 pressure injury or early cellulitis whether or not you can see red.
| Finding | Light skin tones | Medium to deeply pigmented skin tones | Best sites to examine |
|---|---|---|---|
| Pallor | Pale, whitish, loss of pink | Ashen gray or yellow–brown; loss of red undertone | Conjunctivae, oral mucosa, nail beds, palmar creases |
| Cyanosis | Bluish lips, nail beds, skin | Ashen, gray, dusky; skin looks “dulled” | Tongue, buccal mucosa, lips, conjunctivae, palms, soles, nail beds |
| Jaundice | Yellow skin and sclerae | Yellow sclerae near the limbus; hard palate; yellow palms and soles | Sclerae, hard palate, sublingual, palms, soles |
| Erythema / inflammation | Red, blanching with pressure | Deep purple, violet, maroon, eggplant; often not visible | Palpate for warmth, induration, edema, tenderness; compare bilaterally in natural light |
| Petechiae / purpura | Red–purple, non–blanching | Look at buccal mucosa and conjunctivae, where they are visible | Oral mucosa, conjunctivae, palms, soles |
Naming the lesion: primary, secondary, size
A primary lesion arises on previously normal skin. A secondary lesion results from a change in a primary lesion — scratching, infection, healing or time. Naming the morphology and giving a measurement in centimeters is what turns your note into data. “Rash on chest” is useless. “Multiple erythematous, blanchable macules 2 to 4 mm, coalescing into patches up to 6 cm, distributed over anterior chest and both upper arms, sparing palms and soles, no mucosal involvement” lets a provider act from the hallway.
| Primary lesion | Definition and size | Common example |
|---|---|---|
| Macule | Flat, circumscribed color change, less than 1 cm | Freckle, petechia, measles rash |
| Patch | Flat color change, greater than 1 cm | Vitiligo, melasma, congenital dermal melanocytosis |
| Papule | Raised, solid, less than 1 cm | Wart, elevated nevus, acne papule |
| Plaque | Raised, flat–topped, greater than 1 cm | Psoriasis |
| Nodule | Raised, solid, deeper, 1 to 2 cm | Lipoma, rheumatoid nodule |
| Tumor | Raised, solid, greater than 2 cm | Large lipoma, neoplasm |
| Vesicle | Fluid–filled, clear, less than 1 cm | Herpes simplex, varicella, early shingles |
| Bulla | Fluid–filled, greater than 1 cm | Second–degree burn blister, bullous pemphigoid |
| Pustule | Pus–filled, any size | Impetigo, folliculitis, acne pustule |
| Wheal | Raised, edematous, transient, irregular border | Urticaria (hives), mosquito bite, allergic reaction |
| Cyst | Encapsulated, fluid or semisolid, in dermis or subcutis | Epidermoid cyst |
| Secondary lesion | What it is | Nursing significance |
|---|---|---|
| Scale | Flakes of shed stratum corneum | Psoriasis, eczema, xerosis; treat dryness |
| Crust | Dried serum, blood or pus | Honey–colored crust suggests impetigo — contagious |
| Erosion | Loss of epidermis only; moist, heals without scar | Ruptured vesicle; corresponds to a Stage 2 pressure injury depth |
| Ulcer | Loss of epidermis and dermis or deeper; scars | Pressure, arterial, venous or diabetic; measure and stage |
| Fissure | Linear crack through epidermis into dermis | Portal of entry for infection; common at heels and between toes |
| Excoriation | Self–inflicted scratch or abrasion | Confirms pruritus; risk of secondary infection |
| Lichenification | Thickened skin with exaggerated skin lines | Chronic rubbing, chronic eczema |
| Atrophy | Thinning, translucent, paper–like | Topical or systemic steroids, aging; skin–tear risk |
| Scar / keloid | Fibrous replacement; keloid extends beyond wound borders | Keloids are more common in patients with darker skin tones — counsel before elective procedures |
Configuration, distribution and blanching
Three modifiers finish the description. Configuration: annular (ring), linear, grouped or herpetiform, target/iris, serpiginous, confluent. Distribution: localized, generalized, symmetric, dermatomal, sun–exposed, intertriginous, acral (hands and feet). Distribution is diagnostic on its own — a painful vesicular eruption in a band on one side of the trunk that stops abruptly at the midline is herpes zoster, following a single dermatome; a symmetric rash on palms and soles carries an entirely different differential than the same rash on the trunk.
Blanching is the fastest and highest–yield maneuver in the entire skin examination. Press a red area with your fingertip or a clear slide for 3 seconds and release. If it whitens and refills, the redness is intravascular — blood inside dilated vessels — and the causes are inflammation, fever, flushing, drug eruption, reactive hyperemia. If it does not blanch, blood has leaked out of the vessels into the tissue, and the differential turns serious: petechiae, purpura, thrombocytopenia, vasculitis, meningococcemia, disseminated intravascular coagulation. Non–blanching erythema over a bony prominence in skin that is still intact is, by definition, a Stage 1 pressure injury — but if that non–blanchable area is deep red, maroon or purple, or is a blood–filled blister, call it a deep tissue pressure injury instead, because it is deeper and can deteriorate within hours.
| Vascular finding | Size | Blanches? | Suggests |
|---|---|---|---|
| Erythema | Variable | Yes | Inflammation, infection, fever, reactive hyperemia |
| Petechiae | Less than 3 mm | No | Thrombocytopenia, sepsis, vasculitis, straining — with fever, an emergency |
| Purpura | 3 mm to 1 cm | No | Vasculitis, coagulopathy, DIC, meningococcemia |
| Ecchymosis | Greater than 1 cm | No | Trauma, anticoagulation, fragile vessels; patterned shapes raise abuse concern |
| Hematoma | Variable, raised | No | Collected blood; measure and mark the border, trend it |
| Spider angioma | Under 2 cm with radiating legs | Yes, from the center | Normal in pregnancy; multiple ones suggest liver disease |
| Cherry angioma | 1 to 5 mm, bright red papule | Partially | Benign, increases with age |
The lesion you must not walk past: ABCDE
Nurses see more undressed skin than any other clinician, which makes you the most likely person to find a melanoma. Screen every pigmented lesion with ABCDE: Asymmetry (one half unlike the other), Border irregular, notched or blurred, Color varied within a single lesion — brown, black, red, white, blue, Diameter greater than 6 mm (about a pencil eraser), Evolving — changing in size, shape, color, elevation, or newly itching, bleeding or crusting. Add the ugly duckling rule: the mole that looks unlike all the patient’s other moles deserves attention even if it passes ABCDE. Evolution is the most important letter; a patient who says “that one has changed” is reporting a red flag.
Skin cancer is not a light–skin–only disease, and the reason patients with darker skin tones have worse melanoma survival is later detection. The most common melanoma subtype in Black patients is acral lentiginous melanoma, which appears on the palms, soles, and under the nails — sites that get skipped by clinicians who inspect only sun–exposed skin. So examine the soles and the interdigital spaces on every patient, and take a new dark longitudinal band in a nail, especially one that widens or spreads pigment onto the surrounding nail fold, as a finding to report rather than a cosmetic curiosity.
Press the red. Blanching erythema is blood inside vessels; non–blanching erythema is blood outside them. That single 3–second maneuver separates reactive hyperemia from a Stage 1 pressure injury, and a viral exanthem from meningococcemia. In deeply pigmented skin, where you cannot judge color reliably, substitute palpation: warmth, induration, boggy or firm texture, and patient–reported pain.
Describe every skin finding with four elements — morphology, size in centimeters, configuration and distribution — then test blanching, and adapt the viewing window to the patient’s skin tone rather than lowering the standard of the assessment.
Section 4Hair, Scalp and Nails
Hair and scalp
Inspect and palpate hair for distribution, quantity, texture, color and the condition of the scalp beneath it — separate the hair in several places rather than looking at the surface, and always inspect behind the ears and at the nape, where lice, seborrheic scale and device pressure hide. Expect terminal hair on the scalp, axillae and pubic area after puberty and fine vellus hair elsewhere. Expect gradual thinning, graying and reduced axillary and pubic hair in older adults.
Patterns matter more than amount. Alopecia areata produces sharply defined round bald patches with smooth underlying scalp. Traction alopecia thins the frontal and temporal hairline and follows tight braids, weaves, extensions or a ponytail worn the same way for years; it is reversible early and permanent late, which makes it a genuine teaching opportunity rather than a cosmetic aside. Telogen effluvium is a diffuse shed 2 to 3 months after childbirth, surgery, severe illness or major weight loss and regrows. Tinea capitis gives scaly patches with broken–off hairs and is contagious. Hirsutism — coarse terminal hair in a male pattern on a female patient’s face, chest or abdomen — warrants reporting for endocrine evaluation.
One hair finding is a vascular emergency in slow motion: loss of hair over the lower legs, ankles and toes together with shiny, thin, cool, pale skin and thickened nails is classic peripheral arterial disease. Pair that with dependent rubor, pallor on elevation, diminished pulses and painful, punched–out ulcers on the toes or lateral malleolus, and you have a limb at risk. Contrast it with venous insufficiency: warm limb, brown hemosiderin staining, edema, and a shallow, weepy, irregular ulcer at the medial malleolus. The two are managed in opposite directions — compression helps venous disease and can destroy an arterial limb — so the distinction is not academic.
Nails: angle, surface, color, and the bed beneath
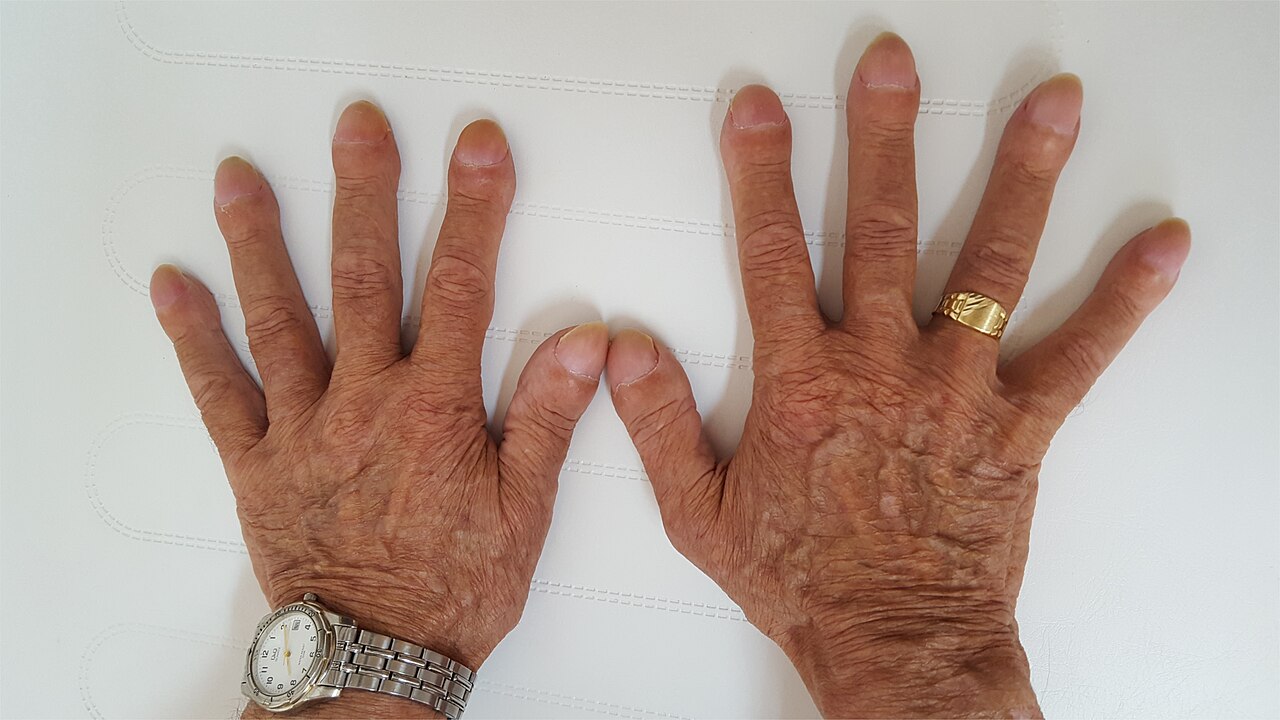
Inspect nail shape, contour, surface, thickness, color and the surrounding folds, and palpate the nail plate for firmness and adherence to the bed. The normal nail base angle (Lovibond angle) is approximately 160 degrees; the nail is firmly adherent, smooth, and the bed is pink with capillary refill under 2 seconds. In clubbing the angle flattens and then exceeds 180 degrees, the nail base becomes spongy or floating, and the fingertip bulbs. Use the Schamroth window test: have the patient place the dorsal surfaces of two matching fingernails together. Normally a small diamond–shaped window of light appears between them; in clubbing the window disappears. Clubbing develops over months and points to chronic hypoxemia or shunting — cystic fibrosis, congenital cyanotic heart disease, bronchiectasis, interstitial lung disease, lung cancer, cirrhosis, inflammatory bowel disease.
| Expected finding | Abnormal finding | What it suggests |
|---|---|---|
| Nail base angle about 160 degrees; Schamroth window present | Angle over 180 degrees, spongy base, no window (clubbing) | Chronic hypoxia, cardiopulmonary disease, cirrhosis, IBD |
| Smooth, evenly convex plate | Concave, spoon–shaped (koilonychia) | Iron–deficiency anemia, hemochromatosis |
| Uniform surface without grooves | Transverse depressions (Beau lines) | Systemic insult that arrested nail growth — date it at about 3 mm per month |
| Pink bed, refill under 2 s | Pale or cyanotic bed; refill over 3 s | Anemia, hypoxia, hypovolemia, poor perfusion |
| Clear bed without streaks | Red–brown longitudinal splinter hemorrhages | Usually trauma; with fever and a murmur, suspect infective endocarditis |
| Plate adherent to bed | Distal separation (onycholysis) | Trauma, psoriasis, thyroid disease, fungal infection |
| Nail folds intact, non–tender | Red, swollen, tender, possibly purulent fold (paronychia) | Bacterial or candidal infection — common in diabetes and frequent hand–wetting |
| Thin, translucent plate | Thick, yellow, crumbling, debris beneath (onychomycosis) | Fungal infection; very common in older adults and diabetes |
| Even color | Proximal white with distal brown band (Terry nails); proximal white, distal red–brown (half–and–half nails) | Cirrhosis and hypoalbuminemia; chronic kidney disease |
| Longitudinal pigment bands may be normal in darker skin tones | New, single, widening dark band; pigment spreading onto the nail fold (Hutchinson sign) | Possible subungual melanoma — report for evaluation |
Infestations and the findings that change the room
Pediculosis capitis (head lice) shows as intense itching with tiny gray–white nits cemented to hair shafts, most densely behind the ears and at the nape; nits found within about 6 mm (a quarter inch) of the scalp indicate active infestation, while nits far out on the shaft are usually old. Scabies presents as relentless itching that is worst at night with thin, wavy burrows in the finger webs, flexor wrists, axillae, waistband area, and genitals; in infants it involves the palms, soles and scalp. Both findings change nursing practice immediately: initiate contact precautions per facility policy, bag linens, notify the provider and infection prevention, and treat the itching as real distress rather than a complaint. Neither is a marker of poor hygiene, and telling the patient so plainly is part of care.
Ask before you assess the nails and hair: nail polish, gel or acrylic hides cyanosis, splinter hemorrhages, onycholysis and melanonychia, and it can interfere with a pulse oximeter reading. Remove polish from at least one finger on admission, or clip the oximeter probe sideways across the finger or use the earlobe. And never assume a hair or nail practice is neglect — ask how the patient normally cares for their hair, and document the plan they agree to.
Hair and nails are slow–motion recorders of systemic health — clubbing means months of hypoxia, Beau lines date a past insult by about 3 mm per month, and hairless shiny legs with thick nails point to arterial disease long before the limb becomes an emergency.
Section 5Skin Integrity, Documentation, Red Flags and Scope
Risk, prevention and the Braden Scale
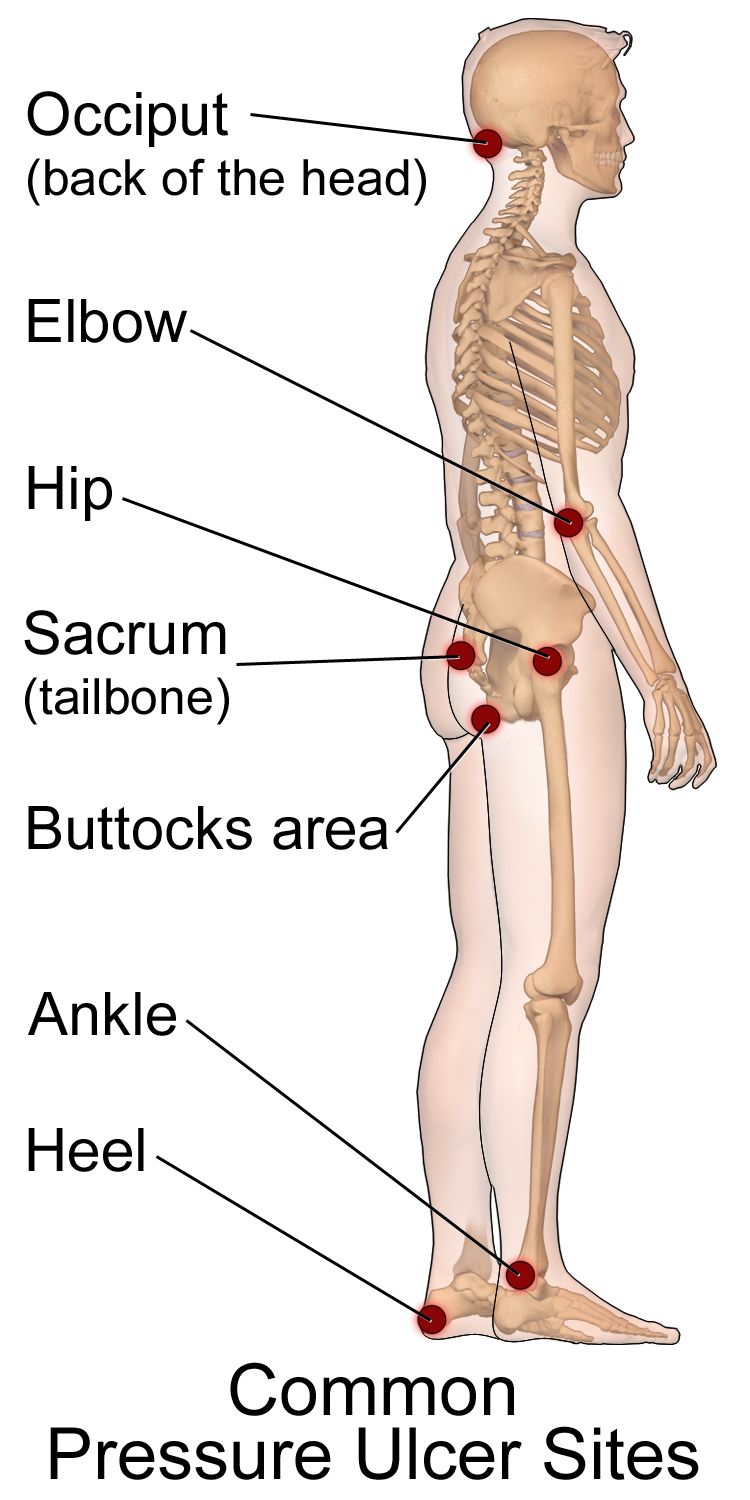
Pressure injuries develop where soft tissue is compressed between bone and a surface long enough to occlude capillary flow, and they are accelerated by shear, friction, moisture, poor nutrition and impaired sensation. Assess risk on admission, at every shift change or per facility policy, and with any change in condition, using the Braden Scale. It scores six subscales — sensory perception, moisture, activity, mobility, nutrition, and friction and shear — for a total of 6 to 23, where a lower score means higher risk. Conventional cutoffs: 19 to 23 no risk, 15 to 18 mild, 13 to 14 moderate, 10 to 12 high, 9 or below very high. A score of 18 or less should trigger a prevention bundle, and many facilities use a higher threshold for older adults and patients with darker skin tones because visual detection of early injury is less reliable.
The prevention bundle is nursing work, not an order set: reposition a bedbound patient at least every 2 hours and a chair–bound patient every 1 hour (or teach small shifts every 15 minutes if they can); use a 30–degree lateral tilt rather than direct side–lying on the trochanter; keep the head of bed at 30 degrees or less unless contraindicated, because higher elevation drives shear at the sacrum; float the heels off the bed entirely with a pillow under the calves or a heel offloading boot; use lift sheets and never drag; keep skin clean and dry with a barrier product for incontinence; optimize protein and calorie intake and involve dietitian services; and do not massage over bony prominences or reddened areas — massage over compromised tissue increases damage.
Staging — and the errors that get students in trouble
| Stage | Defining feature | Presentation in darker skin tones |
|---|---|---|
| Stage 1 | Intact skin with localized non–blanchable erythema | May not appear red at all — look for an area whose hue simply differs from the surrounding skin, and palpate for warmth, coolness, firmness, bogginess and pain. A persistent deep purple or maroon hue points to a deep tissue pressure injury rather than Stage 1 |
| Stage 2 | Partial–thickness loss with exposed dermis; pink or red, moist, shiny; may be an intact or ruptured serum–filled blister. No slough, eschar, granulation or visible adipose | Wound bed color may be less pink; periwound may look violaceous |
| Stage 3 | Full–thickness loss; adipose (fat) visible; granulation tissue and rolled edges (epibole) may be present; slough or eschar may be present but does not obscure the depth; no fascia, muscle, tendon or bone visible; undermining and tunneling may occur | Same depth criteria; assess periwound by palpation |
| Stage 4 | Full–thickness loss with exposed or directly palpable fascia, muscle, tendon, ligament, cartilage or bone; undermining and tunneling common; osteomyelitis risk | Same depth criteria |
| Unstageable | Full–thickness loss in which the base is obscured by slough or eschar; stage cannot be determined until enough is removed to see the base | Same |
| Deep tissue pressure injury (DTPI) | Intact or non–intact skin with localized, persistent non–blanchable deep red, maroon or purple discoloration, or a blood–filled blister, or epidermal separation revealing a dark wound bed | Discoloration is harder to see — palpation for a boggy, firm or temperature–different area is essential; may deteriorate rapidly |
Four rules save you. First, do not reverse–stage. A healing Stage 4 does not become a Stage 2; it is a “healing Stage 4” forever, because lost muscle and fat are replaced by scar, not by the original tissue. Second, do not stage a wound that is not a pressure injury. Staging language belongs only to pressure injuries; skin tears, surgical wounds, venous ulcers, arterial ulcers, diabetic foot ulcers and burns are described by depth and characteristics instead. Third, do not remove stable eschar on a heel. Dry, adherent, intact eschar on an ischemic heel without erythema, fluctuance, drainage or odor is a biological cover; leave it, offload the heel and report. If it becomes soft, boggy, draining or surrounded by erythema, escalate. Fourth, distinguish pressure injury from moisture–associated skin damage.
| Pressure injury | Incontinence–associated dermatitis (a form of MASD) | |
|---|---|---|
| Location | Over a bony prominence or under a device | Perineum, perianal, gluteal cleft, groin, inner thighs, skin folds — over soft tissue |
| Edges | Distinct, defined | Diffuse, irregular, poorly defined |
| Depth | May be full–thickness | Partial–thickness only; erythema, maceration, denudement |
| Cause | Pressure, shear | Prolonged moisture, urine, stool, sweat, wound exudate |
| Intervention | Offload, reposition, support surface | Cleanse, protect with barrier, manage incontinence, toileting schedule |
How to chart it
Documentation is a clinical intervention. It is how the next nurse detects deterioration, how the wound team plans, and how the record demonstrates that an injury was present on admission rather than acquired on your unit. Chart what you observed and measured, not what you concluded. Wounds are measured in centimeters as length × width × depth, with length head–to–toe and width side–to–side, and undermining or tunneling described by depth in centimeters and by clock position with 12 o’clock toward the patient’s head.
| Vague entry (do not write this) | Precise entry (write this) |
|---|---|
| “Skin okay.” | “Skin warm, dry, intact, appropriate for patient’s tone; turgor recoils immediately over sternum; no lesions, rashes or edema noted head to toe including posterior surface, heels and between toes; no redness under O2 tubing or SCD sleeves.” |
| “Bedsore on bottom, looks worse.” | “Sacrum: full–thickness open wound 4.2 cm (L) × 3.0 cm (W) × 0.8 cm (D), subcutaneous adipose visible, no exposed bone, tendon or muscle. Wound bed 70 percent red granulation, 30 percent adherent yellow slough. Undermining 1.5 cm at 3 o’clock. Moderate serosanguineous exudate, no odor. Periwound induration and warmth extending 1 cm, edges attached. Patient rates pain 6/10 with dressing change. Stage 3 pressure injury, unchanged in stage, increased in size from 3.5 × 2.6 cm on 07/28. Wound care RN notified 1410.” |
| “Rash on arms.” | “Multiple raised, erythematous, blanchable wheals 1 to 4 cm with irregular borders over bilateral forearms and anterior trunk, onset approximately 30 min after first dose of IV cefazolin. Patient reports itching 8/10. No lip or tongue swelling, no stridor, no wheeze, no dyspnea. Lungs clear. VS 37.2 °C, HR 96, RR 18, BP 128/76, SpO2 98 percent RA. Rapid response criteria reviewed; provider notified 0915.” |
| “Leg red and warm, will monitor.” | “Right lower leg: area of warmth, induration and deep violet discoloration extending from ankle to mid–calf, border marked with skin marker at 2200, 14 cm at widest point; 3 cm larger than the border marked at 1800. Tenderness rated 9/10, described as out of proportion to appearance. Two tense bullae over lateral calf. T 38.9 °C, HR 124, RR 26, BP 92/54, SpO2 94 percent RA. Rapid response called 2205.” |
Mark the border of a spreading erythema with a skin marker and write the time next to it. It costs ten seconds, it converts “seems bigger” into measurable data, and it is often the single piece of evidence that persuades a provider to come to the bedside now.
Red flags and the SBAR that follows
Some skin findings buy you hours. These do not.
| Red flag finding | Suspect | Act |
|---|---|---|
| Non–blanching petechial or purpuric rash with fever, headache, neck stiffness or altered mental status | Meningococcemia, DIC, sepsis | Rapid response NOW; droplet precautions; do not wait for the next round |
| Pain far out of proportion to appearance, rapidly advancing erythema, crepitus, dusky skin, bullae, systemic toxicity | Necrotizing soft–tissue infection | Rapid response NOW; surgical emergency; mark border, keep NPO |
| Urticaria with lip or tongue swelling, stridor, wheeze, hypotension | Anaphylaxis | Stop the infusion, call for help, epinephrine per protocol, airway, oxygen, IV fluids |
| Painful, dusky, blistering rash with mouth, eye or genital mucosal involvement; skin sloughs with lateral pressure (Nikolsky sign) | Stevens–Johnson syndrome / toxic epidermal necrolysis | Stop the suspected drug, escalate immediately; burn–center level care |
| Central cyanosis of lips, tongue or oral mucosa at any age | Hypoxemia, shunt, methemoglobinemia | Oxygen, airway assessment, SpO2, rapid response |
| Cold, pale, pulseless, painful, paresthetic, paralyzed limb (the six Ps) | Acute arterial occlusion | Emergency; do not elevate, do not apply compression, call now |
| Newborn jaundice within the first 24 hours of life | Pathologic hyperbilirubinemia, hemolysis | Notify provider immediately; bilirubin level |
| New deep tissue pressure injury or unstageable wound | Ongoing pressure damage | Offload immediately, notify provider and wound team, photograph per policy |
| Patterned bruising, burns with clear margins, injuries inconsistent with history, bruising in a non–ambulatory infant | Abuse or neglect | Ensure safety, document objectively with measurements, report as a mandated reporter |
Escalate with SBAR, which turns anxiety into a plan. Situation: “Dr. Ellis, this is Marcus Reed, RN, on 4 West. I’m calling about Mr. Alvarez in 412 — I’m concerned he has a rapidly spreading soft–tissue infection of the right leg.” Background: “He’s a 62–year–old admitted two days ago for cellulitis after a lawn–mower laceration, on IV vancomycin, with type 2 diabetes and an A1c of 9.4.” Assessment: “At 1800 the erythema was marked at the ankle. It’s now 3 cm past that mark, the skin is dusky with two tense bullae, I feel crepitus over the lateral calf, and his pain is 9 out of 10 and out of proportion to what I see. Temperature 38.9, heart rate 124, respirations 26, blood pressure 92/54 down from 132/78, SpO2 94 percent on room air.” Recommendation: “I need you to see him now. I’ve activated rapid response, held his diet, and I’m requesting surgical consult, blood cultures and fluid resuscitation orders.” Notice the recommendation is specific. “Something is wrong” is not an SBAR.
Delegation and scope
The five rights of delegation — right task, right circumstance, right person, right direction and communication, right supervision and evaluation — apply constantly in skin care, because so much skin work happens during hygiene, which is frequently delegated. The line is simple and absolute: assessment, interpretation, staging, teaching, evaluation and the care of an unstable patient stay with the RN. Unlicensed assistive personnel may observe and report what they see; they may never assess what it means. Delegating a task never delegates accountability, and the RN must give explicit direction about what to report and when.
| May be delegated to UAP | Stays with the RN (or LPN/LVN per state scope) |
|---|---|
| Bathing, perineal care, applying prescribed moisturizer or barrier cream to intact skin | The head–to–toe skin assessment itself and its interpretation |
| Turning and repositioning on a set schedule; floating heels; applying prescribed offloading boots | Braden scoring, pressure–injury staging, wound bed assessment and measurement |
| Reporting observations — “there is redness on his tailbone,” “the skin under the oxygen tubing looks sore” | Deciding what that redness means and what the plan of care becomes |
| Keeping linens dry and wrinkle–free; managing incontinence care | Patient and family teaching about prevention, nutrition and skin self–examination |
| Measuring and recording intake and output, weights, and routine vital signs on a stable patient | Any care of an unstable patient, first assessments, and evaluation of whether interventions worked |
| Assisting with ambulation and range of motion as directed | Sterile dressing changes and wound irrigation (per facility policy and state scope; never UAP) |
The bath is the assessment. The single highest–yield habit in skin care is to be present during hygiene — that is when the sacrum, the gluteal cleft, the heels, the skin folds and the areas under devices are actually visible. If you delegate the bath and never look, you have delegated your assessment, and you cannot.
Prevention, correct staging, precise measurable charting, immediate SBAR escalation for the findings that kill, and a hard line between what a UAP may observe and what only an RN may assess — those five behaviors are what make skin care nursing rather than housekeeping.
The chapter in one breath
Skin, hair and nails are examined by inspection and palpation, in that order, under strong tangential light in a warm room, along a fixed head–to–toe route that includes the posterior surface, between the toes, the skin folds and under every device — and you learn the full inspect, palpate, percuss, auscultate sequence here because every region follows it except the abdomen, where auscultation moves second so palpation does not alter bowel sounds. Palpate for temperature with the dorsum of your hand, moisture, texture, turgor (sternum in adults, immediate recoil, tenting at 3 seconds or more), capillary refill under 2 seconds, and pitting edema graded 1+ through 4+. Name lesions by morphology and size in centimeters, add configuration and distribution, and press the redness: blanching means blood inside vessels, non–blanching means blood outside them. Assess color across skin tones at the conjunctivae, oral mucosa, sclerae, palms and soles, and substitute palpation for color when pigment obscures erythema. Know the Braden Scale, the four pressure–injury stages plus unstageable and deep tissue injury, and never reverse–stage. Chart measurements, not impressions. Escalate purpura with fever, pain out of proportion, mucosal sloughing, central cyanosis and a pulseless limb with a specific SBAR recommendation. UAP observe and report; RNs assess.
Words worth knowing
| Term | What it means |
|---|---|
| Integument | The skin and its appendages — hair, nails, and sebaceous, eccrine and apocrine glands; the body’s largest organ. |
| Turgor | Skin elasticity, tested by pinching a fold over the sternum in adults; immediate recoil is expected, tenting of 3 seconds or more suggests volume depletion. |
| Capillary refill | Time for color to return to a compressed nail bed or fingertip; expected under 2 seconds in adults and children. |
| Blanching | Whitening of erythema under pressure, indicating blood is still inside dilated vessels; non–blanching means blood has leaked into tissue. |
| Cyanosis | Dusky, gray or blue discoloration from deoxygenated hemoglobin; central cyanosis of lips, tongue and mucosa is never normal. |
| Acrocyanosis | Blue hands and feet with a pink trunk and pink mucosa, expected in a newborn during the first 24 to 48 hours. |
| Jaundice | Yellow discoloration from bilirubin; best seen in the sclerae near the limbus, the hard palate, and the palms and soles. |
| Macule / papule | A flat color change under 1 cm / a raised solid lesion under 1 cm; the two most commonly confused primary lesions. |
| Vesicle / bulla | A fluid–filled lesion under 1 cm / over 1 cm. |
| Wheal | A transient, raised, edematous lesion with an irregular border — a hive. |
| Petechiae / purpura / ecchymosis | Non–blanching hemorrhage into skin: under 3 mm / 3 mm to 1 cm / over 1 cm. |
| Nikolsky sign | Sloughing of the epidermis with gentle lateral pressure; a hallmark of Stevens–Johnson syndrome and toxic epidermal necrolysis. |
| ABCDE | Melanoma screening: Asymmetry, Border irregularity, Color variation, Diameter over 6 mm, Evolving. |
| Clubbing | Loss of the normal 160–degree nail base angle to more than 180 degrees with a spongy nail base; indicates chronic hypoxia. |
| Beau lines | Transverse grooves in the nail from a systemic insult that halted nail growth; dated at roughly 3 mm per month of fingernail growth. |
| Koilonychia | Spoon–shaped, concave nails classically associated with iron–deficiency anemia. |
| Braden Scale | Pressure–injury risk tool scoring six subscales for a total of 6 to 23; lower is higher risk, and 18 or less triggers prevention. |
| Deep tissue pressure injury | Persistent non–blanchable deep red, maroon or purple discoloration, or a blood–filled blister, over intact or non–intact skin. |
| Unstageable | A full–thickness pressure injury whose base is obscured by slough or eschar, so depth and stage cannot yet be determined. |
| SBAR | Situation, Background, Assessment, Recommendation — the structured format for escalating a finding, ending in a specific request. |