Social Justice, Equity and Discrimination
Nobody in the story that follows wakes up intending to shorten a stranger’s life by fifteen years. That is precisely the difficulty. Chapter 6 gave you justice as a philosophical argument — Rawls against Nozick, distribution against capability — and Chapter 8 gave you justice as one principle among four at the bedside. This chapter takes the argument outdoors, into mortgage maps, hiring algorithms, pulse oximeters and admissions files, and asks what a person of ordinary decency owes when the harm is real, measurable and produced by institutions rather than by anyone’s malice. You will meet the vocabulary that makes these arguments tractable: equality against equity, disparate treatment against disparate impact, structural against interpersonal. You will also meet the places where careful people genuinely disagree, and where the empirical evidence is thinner than the confidence with which it is usually quoted. Both matter. An ethics of social justice that cannot survive contact with contrary data is not an ethics; it is a mood.
By the end of this chapter you can
- Distinguish formal equality, equality of opportunity, equity, equality of outcome and relational equality, and say which is doing the work in a given argument.
- Explain structural injustice with a documented mechanism — redlining, the Federal Housing Administration underwriting rules and their effect on the racial wealth gap — rather than as a slogan.
- Separate direct discrimination from indirect discrimination, and disparate treatment from disparate impact, using Griggs v. Duke Power, the Civil Rights Act of 1991 and Ricci v. DeStefano.
- State and evaluate three theories of why discrimination is wrong — harm, demeaning and deliberative freedom — and explain why statistical discrimination is not rescued by being statistically accurate.
- Summarise what the evidence on implicit bias and audit studies does and does not establish, including the limits of the Implicit Association Test.
- Describe the social gradient in health from the Whitehall studies and the Marmot reviews, and quote current disparity figures in maternal mortality and life expectancy accurately.
- Identify bias embedded in clinical tools — pulse oximetry, cost-based risk algorithms, the VBAC calculator, spirometry correction — and explain the mechanism in each case.
- Compare remedies — antidiscrimination enforcement, affirmative action after Students for Fair Admissions, targeted universalism, reparations — and give the strongest objection to each.
- Apply epistemic injustice and cultural humility to your own practice, and defend a considered position on what individuals owe for harms they did not personally cause.
Section 1Equality, Equity and the Shape of Structural Injustice
Five things people mean by “equality”
Most arguments about social justice are not disagreements about facts. They are two people using one word for five different ideas. It is worth slowing down and naming them, because once you can hear which sense a speaker is using, a great many heated exchanges resolve into something calmer and more interesting.
Formal equality is the rule that like cases be treated alike: the same law, the same procedure, the same price for everyone. It is the oldest and thinnest idea in the family, and it is genuinely powerful — it is what makes “whites only” signage indefensible on its face. Its weakness is that it is silent about what makes cases alike. A poll tax applied to every voter is formally equal, and was for decades one of the more effective instruments of disenfranchisement in the American South. Equality of opportunity adds that the starting line should be fair: careers open to talents, no arbitrary barriers. In its narrow version it forbids only deliberate exclusion. In the version philosophers call fair equality of opportunity, it demands that people of similar native talent and willingness to use it should have similar prospects, whatever their social origin — a far more demanding claim, since it implicates schools, housing, childhood nutrition and the accident of who your parents were.
Equity is the idea that treating people identically can entrench a difference rather than correct it, so resources should be distributed according to need. This is the reasoning behind wheelchair ramps, interpreter services, Title I school funding and insulin coverage. The popular illustration — three people of different heights behind a fence, given identical crates in one panel and different crates in the next — is useful and also slightly misleading, since its most common third panel simply removes the fence. That third panel is the point: much of what equity chases is a barrier somebody built. Equality of outcome goes further and evaluates the end state directly. Almost nobody defends it in its strict form for individuals, since it would flatten every difference produced by effort and choice. It reappears in a defensible form as a diagnostic: a large, persistent gap between groups is not proof of injustice, but it is a reason to look hard for one.
The fifth idea reframes the whole discussion. In a 1999 article in Ethics called “What Is the Point of Equality?”, the philosopher Elizabeth Anderson argued that egalitarians had spent decades on the wrong question. The point of equality, she said, is not to equalise a quantity of stuff or luck; it is to abolish social hierarchy — to create a society in which people stand as equals and none must grovel, defer or beg. This is relational equality, and its target is domination, humiliation and exclusion rather than the shape of a distribution. Anderson pressed the objection hard against luck egalitarianism, the view associated with Ronald Dworkin, G. A. Cohen and Richard Arneson that inequalities are unjust when they stem from brute luck rather than choice. Luck egalitarianism, she noted, must divide claimants into the deserving and the undeserving, demand that people prove their misfortune was not their fault, and then hand them aid stamped with that judgement. A welfare system built on it would be humiliating by design. Defenders reply that the theory concerns what justice requires, not what a bureaucracy should say out loud. The exchange is unresolved and worth knowing, because both instincts live inside every real policy debate.
| Conception | Core demand | Typical policy | Strongest objection |
|---|---|---|---|
| Formal equality | Same rule applied to all | Anti-segregation law; uniform pricing | Neutral rules can reproduce prior advantage |
| Equality of opportunity (narrow) | No deliberate barriers to competition | Ban on refusing to hire by race or sex | Leaves the starting line untouched |
| Fair equality of opportunity | Similar talent, similar prospects | School finance reform; early childhood programmes | Very demanding; intrudes on family life |
| Equity | Distribute according to need | Ramps, interpreters, Title I funding | Who decides need, and when does it end? |
| Equality of outcome | Equal end states across groups | Hard quotas | Ignores choice and effort; rarely defended strictly |
| Relational equality | No one stands below anyone | Union rights, accessible public space, voice in institutions | Vague about how much material inequality it tolerates |
Injustice with no one at the wheel
Chapter 6 introduced Iris Marion Young’s claim that distribution is not the whole of justice and her social connection model of responsibility. Here is the machinery underneath it, in a case where the paper trail is unusually complete.
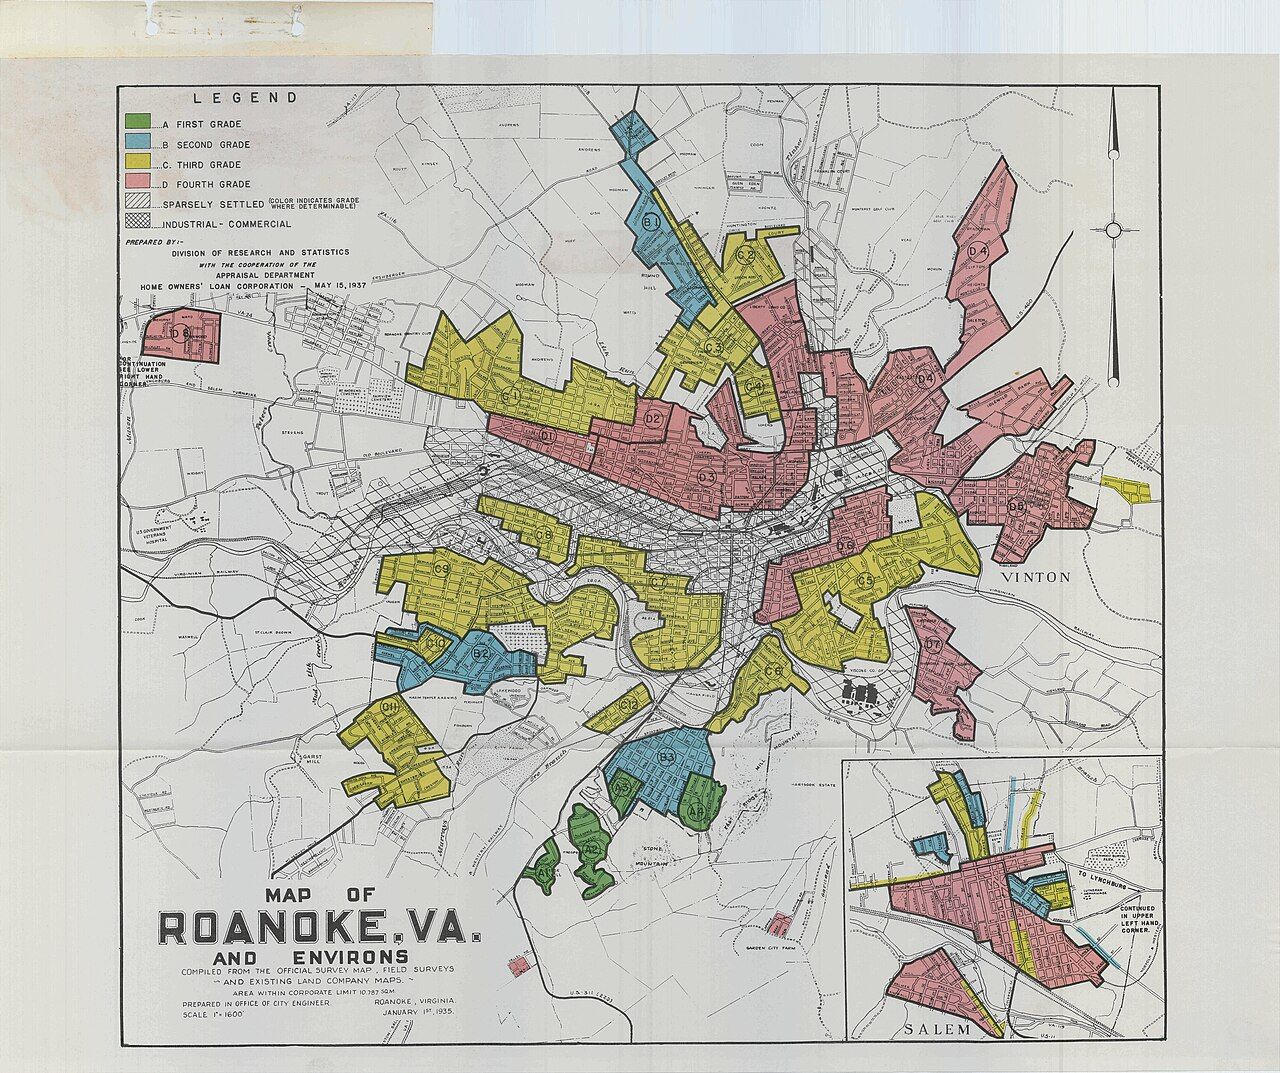
In 1933 Congress created the Home Owners’ Loan Corporation to refinance mortgages during the Depression. Between 1935 and 1940, working with local lenders, it produced residential security maps for 239 cities, grading neighbourhoods A through D. Grade D was outlined in red — hence redlining — and the accompanying area descriptions state the criterion plainly: the presence of Black, immigrant or Jewish residents was recorded as a hazard to property values. The Federal Housing Administration then wrote the logic into national policy. Its Underwriting Manual, issued in 1936 and revised in 1938, advised that neighbourhoods should be protected from “inharmonious racial groups” and recommended restrictive covenants as a means of doing so. The FHA insured mortgages; without that insurance, the thirty-year low-down-payment loan that built the American middle class was largely unavailable. Between 1934 and 1968, by most estimates, the overwhelming majority of FHA-insured loans went to white borrowers.
Now follow the consequences forward, because this is where structural analysis earns its keep. A family shut out of the insured mortgage market bought on contract instead — the arrangement Ta-Nehisi Coates documented in North Lawndale, Chicago, in his June 2014 Atlantic essay, in which the buyer accumulated no equity and could be evicted after one missed payment. Housing equity is the principal asset of most American families and the main channel of inherited wealth. Property taxes fund schools. School quality shapes admission and earnings. Neighbourhood shapes exposure to lead, traffic pollution, food retail, policing and green space. The Federal Reserve’s 2022 Survey of Consumer Finances reported median net worth of about $285,000 for white families, $44,900 for Black families and $61,600 for Hispanic families — a gap far larger than the income gap, and one that a single generation of equal wages could not close. Redlining was outlawed by the Fair Housing Act of 1968. The maps stopped; the distribution they created did not.
That is what structural injustice means: a pattern of disadvantage produced by the ordinary, often lawful, functioning of many separate institutions, in which no current participant need harbour any hostility at all. It is worth being precise about the causal claim, since imprecision here invites justified scepticism. Historians and economists debate how much of the present-day gap is attributable to the HOLC maps specifically as against the broader system of covenants, violence, employment discrimination and unequal schooling that the maps recorded. Daniel Aaronson and colleagues, using boundary discontinuities, found substantial and long-lasting effects of the map lines themselves on homeownership and house values; others argue the maps mostly ratified segregation that private actors were already enforcing. The honest summary is that the mechanism is well documented and the precise share of blame between instruments is contested. That is a normal state of affairs in social science, and it does not rescue the claim that nothing happened.
Equality is five different demands wearing one word, and the most consequential injustices are produced not by villains but by neutral-looking institutions compounding an advantage somebody engineered decades ago.
Section 2What Discrimination Is, and Why It Is Wrong
Two shapes of wrong: treatment and impact
Direct discrimination — in American law, disparate treatment — is treating someone worse because of a protected characteristic. It requires, at least in principle, a causal link between the trait and the decision. In the United States the operative statute is Title VII of the Civil Rights Act of 1964, which forbids employment discrimination on grounds of race, colour, religion, sex and national origin; later statutes added age (1967), disability (1990) and, through judicial interpretation, sexual orientation and gender identity (Bostock v. Clayton County, June 2020, where Justice Gorsuch reasoned that firing a man for loving men is impossible to describe without reference to his sex).
Indirect discrimination, or disparate impact, is the harder and more useful concept. A rule that says nothing about race or sex may still fall far more heavily on one group, and it may not be justifiable by the job. The founding case is Griggs v. Duke Power Co., decided unanimously by the Supreme Court on 8 March 1971. Duke Power’s Dan River Steam Station in Draper, North Carolina, had openly restricted Black employees to the labour department until the day Title VII took effect. A high school diploma had been required for the better departments since 1955; on the day the Act took effect the company added satisfactory scores on two standardised aptitude tests, the Wonderlic and the Bennett Mechanical Comprehension Test. In North Carolina at the time, roughly 34 percent of white men and 12 percent of Black men held high school diplomas, and the pass rates on the tests diverged sharply. Chief Justice Burger wrote that the Act “proscribes not only overt discrimination but also practices that are fair in form, but discriminatory in operation,” and required that a challenged practice be shown to bear a demonstrable relationship to the job. Good intent was no defence: Congress had directed its attention to consequences.
The doctrine has had a contested career. In Wards Cove Packing v. Atonio (1989) the Court shifted most of the burden back onto plaintiffs; Congress reversed that in the Civil Rights Act of 1991, codifying the framework in which a plaintiff identifies a specific practice causing the disparity, the employer must show job-relatedness and business necessity, and the plaintiff may still prevail by showing a less discriminatory alternative. Then Ricci v. DeStefano (2009) exposed the fault line. New Haven, Connecticut, administered a promotion exam for firefighters; no Black candidate scored high enough to be promoted, and the city, fearing disparate-impact liability, discarded the results. Twenty white and Hispanic firefighters sued for disparate treatment and won 5–4. The two halves of antidiscrimination law had been set against each other, and the Court held that an employer may not throw out results merely because of the racial distribution unless it has a strong basis in evidence for believing it would otherwise be liable. Whatever you think of the outcome, the structural lesson is durable: a legal regime that forbids both group-blind harm and group-conscious correction leaves institutions a very narrow corridor to walk.
A third shape belongs beside these two and is often forgotten in ethics courses. Under the Rehabilitation Act of 1973 and the Americans with Disabilities Act of 1990, an employer or school may be obliged to change the rule itself — to provide reasonable accommodation unless doing so imposes undue hardship. This is not equality of treatment and not merely a defence against impact; it is an affirmative duty to restructure. It is the clearest place in existing law where equity, in the sense from Section 1, has statutory teeth.
| Legal shape | What plaintiff must show | Employer’s defence | Landmark |
|---|---|---|---|
| Disparate treatment | Adverse action because of a protected trait | Legitimate non-discriminatory reason, not a pretext | McDonnell Douglas v. Green (1973) |
| Disparate impact | A specific neutral practice causing a substantial disparity | Job-related and consistent with business necessity | Griggs v. Duke Power (1971) |
| Hostile environment | Conduct severe or pervasive enough to alter conditions of work | Prompt corrective action; no notice | Meritor Savings Bank v. Vinson (1986) |
| Failure to accommodate | Known disability, needed adjustment, employer refused | Undue hardship; not otherwise qualified | ADA (1990), Title I |
| Intersectional claim | Harm falling on a compound category, e.g. Black women | Varies; courts long resisted combined claims | DeGraffenreid v. General Motors (1976) |
Why it is wrong — three answers, and one bad excuse
Suppose we agree an act is discriminatory. Why exactly is that a moral objection rather than merely a legal one? Three families of answer compete, and they diverge in cases you will meet.
The harm-based account says discrimination is wrong because it sets back interests: the job not offered, the loan denied, the accumulated psychological cost of vigilance. It is intuitive and it fits the compensation logic of the courts. Its difficulty is that it struggles with harmless discrimination. If a restaurant refuses to seat a couple and an equally good restaurant next door seats them immediately, the harm may be trivial while the wrong plainly is not. Deborah Hellman’s demeaning account, developed in When Is Discrimination Wrong? (2008), answers that the wrong lies in expressing that someone is of lesser worth — an act with social meaning, performed by someone with the standing to make it stick. That explains the restaurant. It also explains why a “whites only” sign and a “no shirt, no service” sign are not the same kind of object. Sophia Moreau’s deliberative freedom account says the wrong is that certain traits should not have to figure in your practical reasoning at all: you should be able to decide where to live, whom to marry, what career to attempt without factoring in your race or religion as a cost. Each account captures something. In practice most people reason with all three and should notice which one is carrying the argument.
Now the excuse. Statistical discrimination, analysed by Edmund Phelps and Kenneth Arrow in the early 1970s, is the practice of using group membership as a proxy for an unobserved individual trait — declining to hire young women because some will take parental leave, charging a higher premium because a group’s average claims are higher. The defence offered is that the inference is accurate and the decision-maker is merely rational under uncertainty. There are several good replies. First, accuracy is frequently overstated: the group average is a poor predictor of the individual in front of you, and the practice suppresses the very information that would refine it. Second, it is self-fulfilling. If employers assume a group will not be promoted, members of that group invest less in the credentials that lead to promotion, and the statistic renews itself. Third, and decisively for our purposes, the moral objection does not turn on accuracy. On Hellman’s account you have treated a person as a specimen of a category; on Moreau’s, you have made her race or her fertility a permanent line item in her own life planning. A correct prediction can still be a wrong to the person predicted. This is the single most useful thing to be able to say aloud when someone offers you a spreadsheet as a moral argument.
Implicit bias: what the evidence supports
In 1995 Anthony Greenwald and Mahzarin Banaji proposed that much social cognition is automatic and unavailable to introspection, and in 1998 Greenwald, Debbie McGhee and Jordan Schwartz introduced the Implicit Association Test, which times how quickly people pair category words with evaluative words. The IAT has been taken tens of millions of times and has become the public face of the concept. It also carries more weight in workplace training than the evidence can bear, and you should know why.
Two meta-analyses did the damage. Frederick Oswald and colleagues, in 2013, found IAT scores predicted discriminatory behaviour only weakly, with correlations in the range of roughly 0.1 to 0.15. Patrick Forscher and colleagues, in a 2019 synthesis of 492 studies, found that interventions can shift implicit measures but that those shifts did not reliably produce changes in behaviour. Test–retest reliability of the IAT is modest, meaning an individual’s score bounces. Greenwald and Banaji themselves have written that the IAT is not diagnostic for individuals and should not be used to select or screen people. The responsible conclusion is not that bias is a myth. It is that the IAT is a research instrument for detecting aggregate patterns, not a character assessment, and that awareness training built on the premise of individual diagnosis has a poor track record.
Meanwhile the field-experimental evidence for discrimination itself is strong, and it does not depend on any theory of the unconscious. Marianne Bertrand and Sendhil Mullainathan sent about 5,000 fabricated resumes to help-wanted advertisements in Boston and Chicago in 2001 and 2002, randomly assigning names such as Emily and Greg or Lakisha and Jamal. White-sounding names received 50 percent more callbacks — 9.65 percent against 6.45 percent — a gap equivalent to about eight additional years of experience, and higher-quality resumes raised callbacks for white names much more than for Black names. Two decades later, Patrick Kline, Evan Rose and Christopher Walters sent more than 80,000 applications to 108 large firms and found distinctively white names contacted roughly nine percent more often overall — with the striking result that a fifth of the firms accounted for nearly half of the total gap. That finding matters practically: discrimination in hiring is concentrated, not evenly smeared, which means enforcement aimed at specific employers can accomplish a great deal.
Discrimination has two legal shapes and at least three moral explanations, and the strongest evidence for its persistence comes from field experiments on real employers rather than from any test of what is going on inside anyone’s head.
Section 3The Gradient: Equity Where It Is Measured Best
Whitehall: the finding that reframed public health
Health is where social justice becomes arithmetic, because the outcome variable is death and the records are good. The pivotal work began in 1967, when Donald Reid and Geoffrey Rose enrolled 17,530 male British civil servants into what became known as Whitehall I. Every man had a job, an income, health care free at the point of use and an office in central London. The expectation was that stress and heart disease would cluster at the top — the executive with the ulcer was a fixture of popular imagination. The opposite appeared. Over ten years, men in the lowest employment grade, the messengers and doorkeepers, died of coronary heart disease at roughly three times the rate of the administrators at the top. More striking still, the relationship was not a cliff between poor and comfortable but a smooth social gradient: each grade did worse than the one above it, all the way up. Professional and executive grades did worse than administrators. Nobody in the study was poor.
Michael Marmot, who led the follow-up study Whitehall II from 1985 with 10,308 participants including women, spent his career on the implication. Smoking, blood pressure and cholesterol explained only a minority of the gradient — in the original analyses, roughly a third. What remained tracked something about position itself: control over one’s work, the predictability of demands, the degree to which effort was reciprocated with reward, and participation in social life. This is why social determinants of health is not a euphemism for poverty. It is a claim that where you stand in a hierarchy affects how long you live, at every rung, and it converges neatly with Anderson’s relational egalitarianism from Section 1.
Britain has an unusually clear policy record here. The Black Report, commissioned under a Labour government and delivered in 1980 to a Conservative one, documented widening class differences in mortality; it was released on an August bank holiday weekend in a print run of 260 duplicated copies, an act of burial that made it famous. The Marmot Review, Fair Society, Healthy Lives, followed in February 2010 with six policy objectives and the phrase proportionate universalism — services offered to everyone but with intensity scaled to need. Its ten-year follow-up in February 2020 reported that improvement in English life expectancy had stalled after 2010 for the first time in a century, that the gap between the most and least deprived areas had widened, and that life expectancy for women in the most deprived decile outside London had actually fallen. Marmot attributed this to austerity policy; others point to opioid and alcohol deaths, influenza seasons and the natural exhaustion of cardiovascular gains. The stall itself is not in dispute.
American numbers, quoted accurately
Precision matters here more than passion, because these figures are frequently mangled in both directions. Raj Chetty and colleagues, in JAMA in April 2016, linked 1.4 billion tax records to mortality data and found that at age 40, men in the top one percent of the income distribution could expect to live 14.6 years longer than men in the bottom one percent; for women the gap was 10.1 years. Crucially, life expectancy for the poor varied enormously by city — the poor lived longest in places like New York and San Francisco and shortest in parts of the industrial Midwest — which tells you the gap is not a fixed law of income but a product of local conditions and policy.
On maternal death, the CDC reported a 2021 maternal mortality rate of 32.9 per 100,000 live births overall, with 69.9 for non-Hispanic Black women against 26.6 for non-Hispanic white women — a ratio of about 2.6 to 1. The 2022 figures fell substantially, to 22.3 overall and 49.5 for Black women, as pandemic-related deaths receded; the ratio persisted. Two features of this disparity deserve emphasis because they defeat the easy explanations. It is not abolished by education or income: analyses of New York City data found that Black women with a college degree had worse severe maternal morbidity than white women who had not finished high school. And the pattern is specific — hypertensive disorders, haemorrhage and embolism, with the CDC’s maternal mortality review committees judging a large majority of these deaths preventable. Whatever the mechanism, it is operating inside the health system, not merely upstream of it.
Research funding shows the same shape. Sickle cell disease affects roughly 100,000 people in the United States, predominantly Black; cystic fibrosis affects roughly 30,000, predominantly white. A 2020 analysis in JAMA Network Open by Faheem Farooq and colleagues found average annual federal funding per affected person of about $812 for sickle cell against $2,807 for cystic fibrosis, and private foundation expenditure of about $102 against $7,690. Some of that gap has innocent explanations — foundation money follows the donors a community can mobilise, and cystic fibrosis research had a compelling molecular target. Some of it does not. Both diseases are single-gene disorders of comparable severity, and only one of them spent decades with patients routinely suspected of drug-seeking when they presented in crisis.
Bias built into the instrument
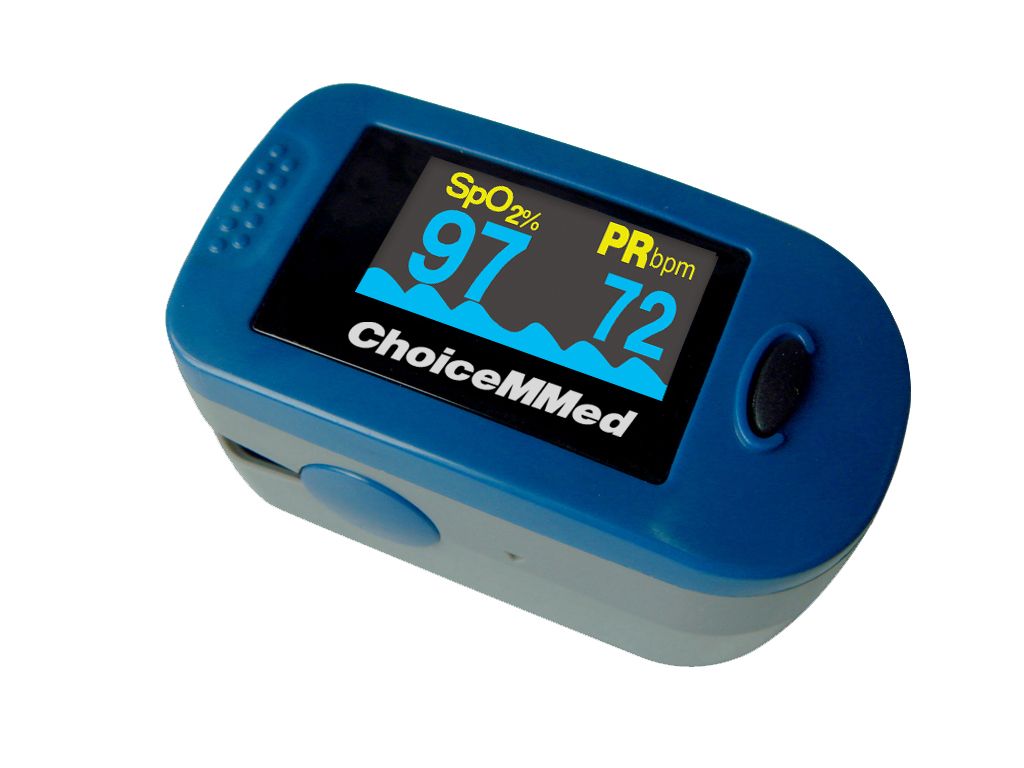
The most instructive contemporary examples are technical, because they show injustice arriving through a validation sample rather than an attitude. Pulse oximetry estimates arterial oxygen saturation from the different absorption of red and infrared light by oxygenated and deoxygenated haemoglobin. Melanin absorbs in the same range. In December 2020, Michael Sjoding and colleagues published in the New England Journal of Medicine a comparison of nearly 50,000 paired oximeter and arterial blood gas readings and found occult hypoxaemia — a true arterial saturation below 88 percent in a patient whose device read a reassuring 92 to 96 percent. Among the patients whose oximeter read in that range, 11.7 percent of Black patients were nonetheless occultly hypoxaemic, against 3.6 percent of white patients — roughly a threefold difference. During the pandemic this was not academic: oxygen saturation gated admission, oxygen therapy, dexamethasone and remdesivir eligibility. The FDA convened an advisory committee in November 2022 and issued draft guidance on device performance across skin pigmentation in January 2025.
A second example is algorithmic. In Science in October 2019, Ziad Obermeyer and colleagues examined a widely used commercial system that flagged patients for high-risk care management programmes, covering some 200 million people annually. The algorithm did not use race. It predicted future health care costs, on the reasonable-sounding assumption that costly patients are sick patients. But less money is spent on Black patients at any given level of illness — because of access, distrust, insurance and clinician behaviour — so at an identical risk score, Black patients were substantially sicker. Correcting the target variable from cost to a direct measure of illness would have raised the share of Black patients auto-enrolled in the programme from 17.7 percent to 46.5 percent. Nobody wrote a racist line of code. The proxy did the work.
Race-adjusted clinical equations belong in the same family. Chapter 8 discussed the removal of the race coefficient from estimated glomerular filtration rate in 2021. The vaginal birth after caesarean calculator, developed by the Maternal-Fetal Medicine Units Network, included terms that lowered the predicted probability of success for Black and Hispanic women, plausibly steering them toward repeat caesarean; a revised race-free version was published in 2021. Spirometry has for a century applied a “correction” assuming lower normal lung volumes in Black patients — a practice with roots in nineteenth-century arguments about slavery — and the American Thoracic Society moved in 2023 to recommend race-neutral reference equations. In every case the debate is real: removing a variable that carries genuine predictive signal can reduce a model’s accuracy, and some clinicians argue that a crude social proxy is better than nothing. The counter-argument, which has largely prevailed, is that race is standing in for exposures, access and structural conditions, and that a model which encodes the consequence of injustice as though it were biology will reproduce that injustice at scale.
| Tool | How bias entered | Clinical consequence | Status |
|---|---|---|---|
| Pulse oximeter | Calibrated largely on light-skinned volunteers; melanin absorbs red light | Missed hypoxaemia; delayed oxygen and COVID therapies | FDA advisory 2022; draft guidance January 2025 |
| Cost-based risk algorithm | Used spending as a proxy for illness | Sicker Black patients not referred to care management | Documented 2019; vendor revised the label |
| eGFR equation | Race coefficient raised reported kidney function | Delayed referral and transplant listing | Race-free CKD-EPI adopted 2021 |
| VBAC calculator | Race and ethnicity terms lowered predicted success | Steering toward repeat caesarean | Race-free version published 2021 |
| Spirometry reference values | Historic assumption of lower “normal” lung volumes | Under-recognised impairment; disability and compensation effects | ATS recommended race-neutral equations 2023 |
Health inequity is a gradient rather than a cliff, it persists after income and education are accounted for, and some of it is manufactured inside clinical practice by devices, equations and proxies that nobody intended as instruments of harm.
Section 4Remedies, and the Best Case Against Each
Preference, and the long argument about it
If a neutral rule reproduces an old injustice, one obvious response is a rule that is not neutral. Affirmative action in the American sense — the phrase entered federal civil-rights policy in President Kennedy’s Executive Order 10925 in March 1961 — has meant everything from outreach and recruitment to explicit preference. The Supreme Court’s treatment of it in higher education is worth knowing in sequence, because each decision narrows the permissible justification.
In Regents of the University of California v. Bakke (1978), Allan Bakke, a white applicant twice rejected by the medical school at UC Davis, challenged a programme reserving sixteen of one hundred places for minority applicants. The Court fractured; Justice Powell’s controlling opinion struck the set-aside as a quota but held that a university’s interest in a diverse student body could justify considering race as one factor among many. Note what happened there: remedying past societal discrimination was rejected as too amorphous a justification, and diversity — an educational-benefits rationale — became the only surviving one. Twenty-five years later, in Grutter v. Bollinger (2003), Justice O’Connor upheld the University of Michigan Law School’s individualised holistic review while the companion case Gratz struck the undergraduate system that awarded a fixed twenty points for minority status. O’Connor added the sentence everyone remembers: the Court expected that in twenty-five years such preferences would no longer be necessary. Fisher v. University of Texas (2016) upheld a narrowly tailored programme 4–3.
On 29 June 2023, in Students for Fair Admissions v. Harvard and its companion against the University of North Carolina, the Court ended it. Chief Justice Roberts, writing for a six-justice majority (Justice Jackson recused in the Harvard case), held that the programmes lacked measurable objectives, used race as a negative and as a stereotype, and had no logical endpoint, and so failed strict scrutiny under the Equal Protection Clause and Title VI. The opinion left two openings: military academies were expressly not addressed, and an applicant may still write about how race has affected her life — though universities may not use that essay as a proxy for the prohibited classification. Institutions across American higher education, including nursing and medical schools with express mission statements about workforce diversity, have since rebuilt admissions around socio-economic indicators, geography and pipeline programmes.
What should you make of it? Take the strongest arguments on each side rather than the convenient ones. For preference: the pipeline argument is empirical and reasonably well supported — physician workforce diversity is associated with improved access and, in several studies, better outcomes for underserved patients, and California’s Proposition 209 in 1996 was followed by sharp declines in underrepresented enrolment at the flagship campuses. Against: preference at the point of admission is a late and blunt intervention that mostly benefits the more advantaged members of the preferred group while imposing the cost on individual applicants who did nothing wrong; and the mismatch hypothesis, argued by Richard Sander, holds that students admitted with substantially weaker preparation may fare worse than they would have at a better-matched institution. Mismatch is genuinely contested — several careful studies find no such effect, and Sander’s bar-passage analyses have been challenged on methodology — and an honest instructor tells you that rather than pretending the literature is settled.
Universalism, targeting, and repair
A different strategy avoids the individual-preference problem entirely. Targeted universalism, developed by john a. powell and colleagues at Berkeley’s Othering and Belonging Institute, sets a universal goal — every child reads at grade level, every pregnancy is safe — then measures how far each group sits from it and tailors the strategy to each group’s actual obstacle. The goal is shared, so the politics are less brittle; the means differ, so the intervention is effective. It is a policy design rule rather than a moral theory, and it maps closely onto Marmot’s proportionate universalism. The Special Supplemental Nutrition Program for Women, Infants and Children and the community health worker model are recognisable instances.
Reparations raises the sharpest version of the question this chapter keeps circling: what is owed for an injustice whose perpetrators and direct victims are dead? Coates’s 2014 essay argued the case largely on twentieth-century housing policy rather than slavery, precisely to answer that objection with living plaintiffs. Concrete programmes exist. Evanston, Illinois, approved in March 2021 the first municipal programme in the United States, funded initially by cannabis tax revenue and offering $25,000 housing grants to residents harmed by discriminatory housing policy between 1919 and 1969. California’s state task force, created by AB 3121, delivered a roughly 1,100-page final report in June 2023 with more than a hundred recommendations. Georgetown University confronted its 1838 sale of 272 enslaved people; students voted in 2019 to tax themselves for a fund benefiting descendants. Federal legislation to study reparations, H.R. 40, has been introduced in every Congress since 1989 without passing. The objections are serious and worth stating fully: identifying eligible recipients and payers, the arbitrariness of drawing lines among many wronged groups, and the political risk that a large transfer discredits the broader project. The counter-argument is that we routinely accept inherited obligations — national debt, treaty commitments, property title itself — and that the ongoing advantage from the original harm is measurable in the balance sheet.
Finally, the unglamorous evidence about what organisations can actually do. Frank Dobbin and Alexandra Kalev, analysing three decades of federal EEO-1 data from 829 firms, reported in the Harvard Business Review in 2016 that the three most popular tools — mandatory diversity training, hiring tests and formal grievance procedures — were associated with declines in managerial diversity, plausibly because compulsion triggers reactance and because grievance systems retaliate against complainants. What worked was structural and voluntary: targeted college recruitment, formal mentoring, self-managed teams, cross-training, diversity task forces and accountable managers. Formal mentoring was associated with increases of roughly 9 to 24 percent in the management representation of Black, Hispanic and Asian-American women and of Hispanic and Asian-American men. The lesson generalises well beyond firms: interventions that change who is in the room and who is accountable outperform interventions that try to change what is in people’s heads.
| Remedy | Mechanism | Best evidence for | Strongest objection |
|---|---|---|---|
| Antidiscrimination enforcement | Penalise identified conduct | Hiring gaps concentrated in a minority of firms | Reaches only provable individual acts |
| Race-conscious preference | Weight the trait at selection | Enrolment collapse after Proposition 209 | Now unlawful in US admissions; cost falls on individuals |
| Class-based preference | Weight income, wealth or school context | Politically durable; captures real disadvantage | Replaces only part of the racial effect |
| Targeted universalism | Shared goal, group-specific strategy | WIC, community health worker programmes | Requires good data and sustained funding |
| Reparations | Direct transfer for documented harm | Evanston (2021); precedent in other settlements | Eligibility, financing, political backlash |
| Structural workplace change | Recruitment, mentoring, accountability | Dobbin & Kalev, 829 firms over 30 years | Slow; invisible; hard to advertise |
Every remedy for structural injustice imposes a real cost on someone, and the serious work is choosing among imperfect instruments on evidence rather than defending one instrument as though it were the principle itself.
Section 5What This Asks of You, Personally

Intersections, and the categories that lose people
In 1976, five Black women sued General Motors in DeGraffenreid v. General Motors. The company had hired Black men into factory jobs and white women into office jobs; it had hired almost no Black women before 1964, and a seniority-based layoff eliminated those hired after. The court dismissed the claim. GM hired Black people, so there was no race discrimination; GM hired women, so there was no sex discrimination; and the plaintiffs could not, the court held, combine the two into a “super-remedy” the statute had not created. Kimberlé Crenshaw used that case in 1989 to name intersectionality: a person standing where two roads cross can be struck by traffic from either direction, and a legal or analytic framework that examines one road at a time will report that nothing hit her.
The concept has since travelled far from its origin, and in some popular usage it has become a ranking system for grievance, which is not what the argument says and not what it is good for. Used well, it is a methodological warning: check whether your data, your policy or your quality-improvement project is averaging away a subgroup. The maternal mortality figures in Section 3 are an intersectional finding — the interaction of race and sex, not the sum of two main effects. So is the observation that disabled women report far higher rates of intimate partner violence than either disabled men or non-disabled women, and that clinical screening protocols designed around one category routinely miss them.
Epistemic injustice: the wrong of not being believed
Miranda Fricker’s Epistemic Injustice (2007) identified a kind of harm the frameworks above do not capture: being wronged specifically in your capacity as a knower. She distinguished two forms. Testimonial injustice occurs when a hearer discounts a speaker’s credibility because of prejudice about her identity — the patient described in the notes as a poor historian who was in fact describing her symptoms accurately to someone who had decided in advance what they were worth. Hermeneutical injustice is subtler: a gap in the shared interpretive resources means an experience cannot be named at all. Fricker’s example is sexual harassment before the term existed. Carmita Wood left her job at Cornell in 1975 because of a professor’s conduct and was denied unemployment benefits because she could not explain her reason for leaving in any language the system recognised; the phrase was coined that year by the group that took up her case.
Health care supplies the clearest current evidence for the first form. In a 2016 study in PNAS, Kelly Hoffman and colleagues surveyed 222 white medical students and residents and found that about half endorsed at least one false biological belief about racial difference — that Black people have thicker skin, or less sensitive nerve endings. Those who endorsed such beliefs rated a Black patient’s pain lower and made less accurate treatment recommendations. This aligns with decades of emergency department data, beginning with Knox Todd’s studies in the 1990s, showing that Black and Hispanic patients with long-bone fractures received analgesia less often than white patients with the same injury. Nursing has looked at itself as well: the National Commission to Address Racism in Nursing, convened by the American Nurses Association, reported in 2022 that 63 percent of surveyed nurses said they had personally experienced an act of racism at work, most commonly from a peer or a patient.
The practical upshot is unusually concrete. Testimonial injustice is repaired by a habit, not a belief: take the history again, in the patient’s words, when your working impression depends on discounting what she is telling you. That habit is also good clinical practice, which is a recurring feature of this material.
Competence, humility and the checklist trap
For twenty years the standard answer to all of this was cultural competence: learn the health beliefs, dietary rules and communication norms of the groups you serve. It produced useful knowledge and one predictable failure mode — the culture card, which converts a person into a representative of a category and invites exactly the stereotyping it was designed to prevent. In 1998 Melanie Tervalon and Jann Murray-García proposed cultural humility instead: a lifelong commitment to self-evaluation, redressing the power imbalance in the clinical encounter, and building accountable partnerships with communities. The difference is that competence is a body of knowledge you can finish acquiring, and humility is a stance you maintain. The best current practice uses both: know that Ramadan affects medication timing, and ask this patient what she actually does.
| Dimension | Cultural competence | Cultural humility |
|---|---|---|
| Goal | Acquire knowledge of group practices | Maintain self-critical openness |
| Endpoint | Achievable; certifiable | Lifelong; never complete |
| Expert in the room | The clinician | The patient, about her own life |
| Failure mode | Stereotyping by checklist | Vagueness; no measurable content |
| Power | Largely unexamined | Explicitly named and addressed |
What you owe for something you did not do
The objection arrives eventually, usually in these words: I never redlined anyone; my family arrived in 1961; why is this my problem? It deserves a serious answer, not a reprimand. The answer runs in two steps. First, guilt and responsibility are different. Guilt is backward-looking and attaches to acts; you are not guilty of the FHA underwriting manual. Responsibility, in Young’s social connection model introduced in Chapter 6, is forward-looking and attaches to participation: because you take part in institutions whose ordinary functioning produces the outcome, you share an obligation to change how they function. That obligation is political and collective, and it is discharged with others, not alone. Second, it is scaled by what Young called parameters of reasoning — your power, your privilege, your interest and your collective ability. A staff nurse and a chief nursing officer do not owe the same thing, and neither owes everything.
Which leaves the question of what a competent professional actually does on a Wednesday. The American Nurses Association’s Code of Ethics states the duty in its eighth and ninth provisions, obliging collaboration to protect human rights and reduce health disparities and requiring professional organisations to integrate principles of social justice. Translating that into practice, five questions do most of the work: Who is missing from this room, this dataset, this trial? What does this rule cost the person least able to comply with it? Whose account am I discounting, and on what evidence? Is this tool validated on people like my patient? And what is the smallest structural change — a schedule, a form, an interpreter line, a referral pathway — that I have the standing to make? None of these requires a movement. All of them are the sort of thing that, done consistently by people in the middle of an institution, changes what the institution produces.
You are not guilty of injustices you did not commit, but you are responsible for the institutions you participate in, and that responsibility is discharged through specific, scaled, unglamorous changes to how your part of the system works.
The chapter in one breath
Social justice becomes tractable once you stop treating “equality” as one idea. Formal equality forbids different rules; equality of opportunity attends to the starting line; equity distributes by need; relational equality targets hierarchy itself. Discrimination has two legal shapes — disparate treatment and disparate impact, the second built in Griggs from the recognition that a neutral rule can do a segregationist’s work — and at least three moral explanations, none of which is defeated by the observation that a statistical generalisation happens to be accurate. The evidence for ongoing discrimination is strongest not in tests of unconscious attitude, where the IAT has proved a weak predictor of behaviour, but in field experiments on real employers. Health is where all of this is measured best: the Whitehall studies found a smooth gradient of mortality by rank among people who were none of them poor, and American maternal mortality remains roughly two and a half times higher for Black women, a gap that education and income do not close. Some of that harm is manufactured by instruments — oximeters, cost proxies, race-adjusted equations — that no one built with malice. Remedies all cost someone something, so choose them on evidence. And responsibility, unlike guilt, follows participation forward rather than blame backward.
Words worth knowing
| Term | What it means |
|---|---|
| Formal equality | The requirement that the same rule be applied to everyone, without regard to protected traits. |
| Equity | Distribution according to need, on the view that identical treatment can entrench an existing difference. |
| Relational equality | Anderson’s view that the point of equality is to end social hierarchy and domination, not to equalise a quantity. |
| Luck egalitarianism | The view that inequalities are unjust when they trace to brute luck rather than to a person’s own choices. |
| Structural injustice | Disadvantage produced by the ordinary functioning of many institutions, without any current agent intending it. |
| Redlining | The 1930s practice of grading neighbourhoods for mortgage risk using the presence of Black and immigrant residents as a hazard. |
| Disparate treatment | Adverse action taken because of a protected characteristic; requires a causal link to the trait. |
| Disparate impact | A facially neutral practice that falls far more heavily on a protected group and is not justified by business necessity. |
| Reasonable accommodation | The duty under the ADA to modify a rule or setting for a disabled person unless doing so imposes undue hardship. |
| Statistical discrimination | Using group membership as a proxy for an unobserved individual trait; accurate on average and still a wrong to the individual. |
| Demeaning account | Hellman’s theory that discrimination is wrong because it expresses that a person is of lesser worth. |
| Deliberative freedom | Moreau’s theory that certain traits should not have to enter a person’s own practical reasoning about her life. |
| Implicit Association Test | A reaction-time measure of automatic association; useful in aggregate research, a weak predictor of individual behaviour. |
| Social gradient | The Whitehall finding that mortality rises stepwise as occupational rank falls, at every level and not only among the poor. |
| Social determinants of health | The conditions of life — work, housing, control, income, environment — that shape health outcomes more than clinical care does. |
| Occult hypoxaemia | True arterial oxygen saturation below 88 percent despite a reassuring pulse oximeter reading of 92 to 96 percent; among patients reading in that range, about three times as frequent in Black as in white patients. |
| Targeted universalism | Setting one universal goal and tailoring the strategy to each group’s distance from it and specific obstacles. |
| Intersectionality | Crenshaw’s point that harm falling on a compound category is invisible to frameworks that examine one category at a time. |
| Testimonial injustice | Discounting a speaker’s credibility because of prejudice about her identity; a wrong done to her as a knower. |
| Cultural humility | A lifelong stance of self-evaluation and attention to power in the clinical relationship, contrasted with a finishable body of cultural knowledge. |