Anatomy & Physiology
An Introduction to the Human Body
Before you study any one organ, you need two things: a map and a compass. This chapter gives you both. First, you will see how the body is built in nested levels, from tiny atoms up to a whole person. Next, you will meet the eleven organ systems that share the work of staying alive. Then you will learn the one big idea under all of body science. It is homeostasis, the body's constant push to keep things steady inside. Last, you will learn the exact language used to say where body parts are. After that, words like "left," "above," and "in front" will always mean the right thing.
By the end of this chapter you can
- Tell anatomy apart from physiology. Explain why we always study how a part is built and what it does together.
- Put the six levels of structural organization in order, from chemical to organism. Give an example of each level.
- Name the eleven organ systems and the main job of each. Say which system a given organ belongs to.
- Define homeostasis. Draw a negative feedback loop with its three parts: receptor, control center, and effector.
- Compare negative and positive feedback. Give a real example of each.
- Describe the anatomical position. Use directional terms in the right pairs, like superior/inferior and proximal/distal.
- Name the three body planes and the body cavities. Find a body part by its region or quadrant.
Section 1The levels of organization
Two questions, always asked together
This whole book grows out of two words. Anatomy is the study of body parts. It asks what is it, and where is it? It looks at a part's shape, pieces, and place. Physiology is the study of how the body works. It asks how does it work? It looks at the job a part does and the steps it takes.
You can't really split the two, because in the body structure always fits function. In other words, how a part is built matches the job it does. The wall of a tiny air sac in your lung is as thin as tissue paper. That lets oxygen cross it in a split second. The wall of the heart's main pumping chamber is thick and full of muscle. It has to be strong to push blood to your whole body. Change how a part is built, and you change what it can do. You will see this rule again and again.
Small parts build bigger parts
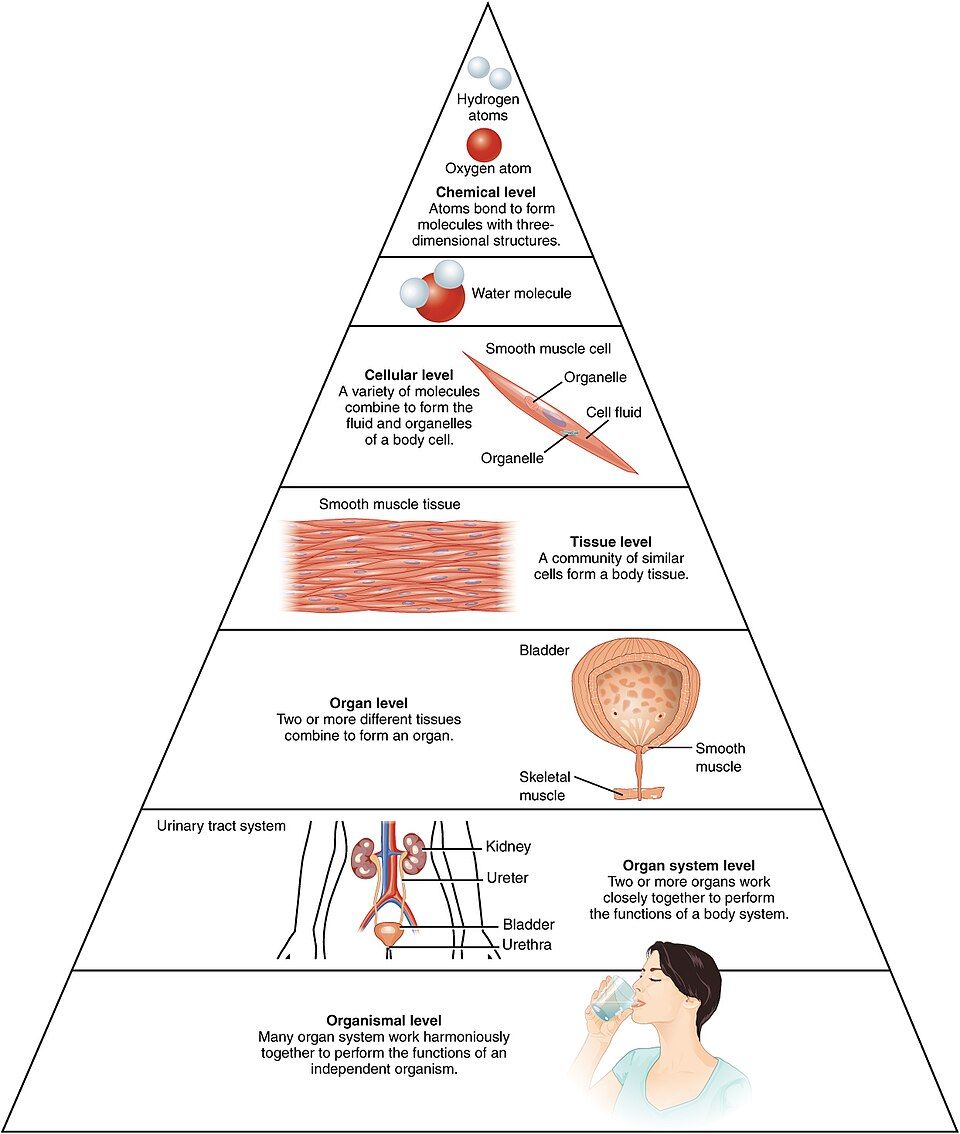
The body is set up like a set of nesting dolls. Each level is built from the one below it. There are six levels, and it helps to know them in order:
| Level | What it is | Example |
|---|---|---|
| 1. Chemical | Atoms join to make molecules | Hydrogen + oxygen → a water molecule; amino acids → a protein |
| 2. Cellular | Molecules come together to make the smallest living unit | A muscle cell, a nerve cell (neuron), a red blood cell |
| 3. Tissue | A group of alike cells doing one job together | Heart (cardiac) muscle tissue; nerve tissue |
| 4. Organ | Two or more kinds of tissue that form a part with a job | The heart, the stomach, the skin |
| 5. Organ system | Organs that team up on a big job | The cardiovascular system (heart + blood vessels + blood) |
| 6. Organism | All the systems together = one living person | You |
You can read this ladder in either direction. Going up, tiny parts join into bigger and more useful parts. In the end, they add up to a living human. Going down, you can trace any disease to a lower level. Take a heart attack. It is an organ problem. But it starts with cells that don't get enough oxygen. That happens because a molecule (cholesterol) built up in a blood vessel wall. Moving up and down this ladder is one of the most useful habits you can build.
Zoom in and out through all six levels in the interactive below.
- Anatomy is about how a part is built and where it is. Physiology is about what it does and how. Structure always fits function.
- The six levels, from low to high, are chemical → cellular → tissue → organ → organ system → organism.
- The cell is the smallest living unit. It is the line between chemistry and life.
- You can trace a disease down the ladder to the tissue, cell, or molecule where it began.
Section 2The organ systems
Eleven teams, one goal
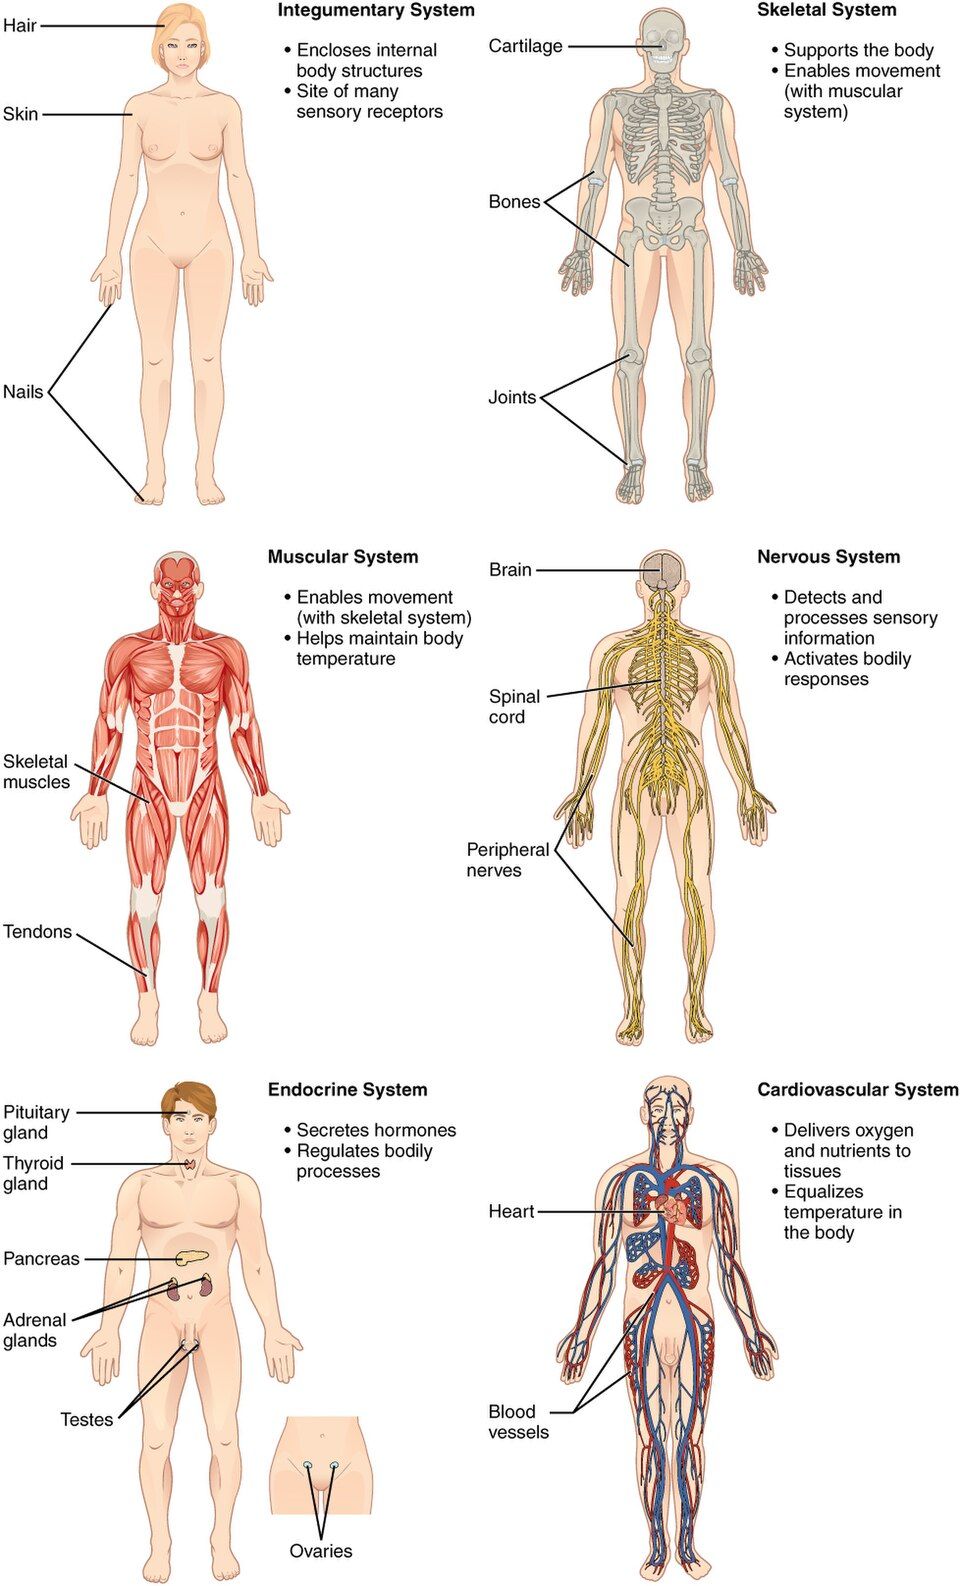
Keeping a person alive is too big a job for one organ. So the work is split among eleven organ systems. They are not really separate. They overlap and depend on each other all the time. But sorting them by their main job makes the body easier to learn.
A handy trick is to group the systems by the kind of job they do. Some cover and support the body. Some control it and carry messages. Some move things around. And some make new people.
| System | Main job | Key organs |
|---|---|---|
| Integumentary | Covers and protects the body; helps control temperature; senses touch; makes vitamin D | Skin, hair, nails |
| Skeletal | Holds the body up; protects organs; acts as levers for movement; makes blood cells; stores minerals | Bones, cartilage, joints |
| Muscular | Moves the body; holds posture; makes heat | Skeletal muscles |
| Nervous | Fast control and messages | Brain, spinal cord, nerves |
| Endocrine | Slow control using hormones | Thyroid, pancreas, adrenal, pituitary |
| Cardiovascular | Carries blood, O₂, nutrients, and wastes | Heart, blood vessels, blood |
| Lymphatic / Immune | Returns fluid to the blood and fights germs (pathogens) | Lymph nodes, spleen, thymus, lymph vessels |
| Respiratory | Gas exchange: O₂ in, CO₂ out | Lungs, airways |
| Digestive | Breaks down food, takes in nutrients, gets rid of waste | Stomach, intestines, liver, pancreas |
| Urinary | Cleans the blood; balances water, salts, and pH; makes urine | Kidneys, ureters, bladder |
| Reproductive | Makes children (offspring) and sex hormones | Ovaries/uterus; testes |
No system works alone
The real magic is in how the systems team up. Take one breath and follow it. The respiratory system brings in oxygen. But the cardiovascular system carries that oxygen to your tissues. The muscular system (the diaphragm) did the pulling. The nervous system set how fast you breathe. And the skeletal system (the rib cage) gave the lungs a frame to grow inside. When you learn about a disease later on, ask which systems it touches. The answer is almost never just one.
Tap each system in the interactive to watch its organs light up on the body.
- There are eleven organ systems. Know each system's main job and one key organ.
- The systems team up all the time. Just one breath uses five or more of them at once.
- Some organs work in two systems. The pancreas is both digestive and endocrine.
Section 3Homeostasis & feedback
The single big idea of physiology
If you remember just one word from this book, make it homeostasis. It means keeping the inside of the body steady, even when the world outside changes. Your body temperature stays near 37 °C, whether you are in a snowstorm or a sauna. Your blood sugar (glucose), blood pH, and fluid amount all stay inside narrow ranges too.
These values don't stay perfectly still. They wobble a little around a set point, the target value the body aims for. Think of a person on a tightrope, always making tiny fixes to stay balanced. That moving balance is health. If a value moves too far out of range, cells stop working. If it moves even further, the person dies. Almost every disease in this book comes down to a failure of homeostasis.
The negative feedback loop: three parts
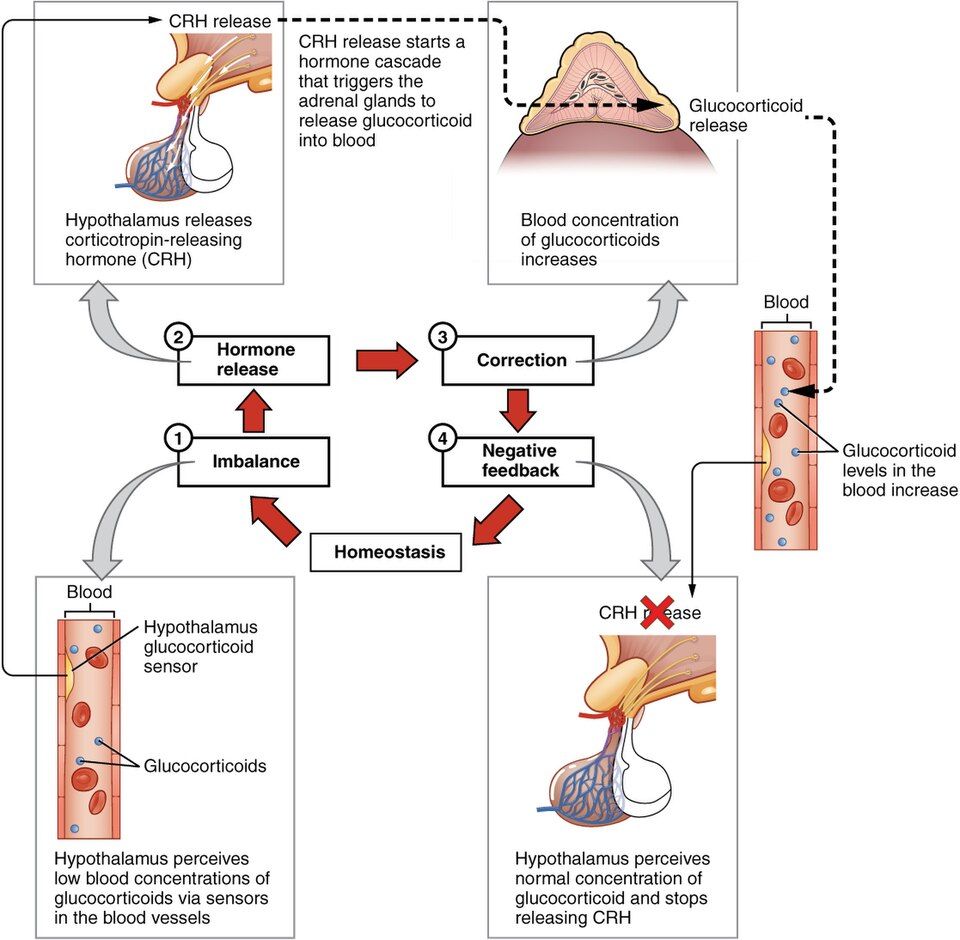
The body keeps values steady mostly through negative feedback. This is a loop that undoes a change. Every negative feedback loop has the same three parts. Learn them once, and you can follow any loop in the body:
- A receptor (a sensor) notices the change and reports it.
- A control center (often the brain or a hormone gland) compares the reading to the set point. Then it decides what to do.
- An effector (a muscle or gland) carries out the response. This pushes the value back toward normal.
It is called negative feedback because the response works against the first change. If the value goes up, the loop brings it down. If it goes down, the loop brings it up. Body temperature is the classic example. Say you step out into the cold. Temperature receptors in your skin send signals. The control center in your brain (the hypothalamus) reads "too cold." It then turns on the effectors. Blood vessels in your skin get narrower to hold heat in. Your muscles shiver to make heat. Your temperature climbs back to the set point, and the loop calms down. A home thermostat works the same way. It senses, compares, and fixes.
Positive feedback: the rare amplifier
Once in a while, the body wants the opposite. It needs a signal that builds on itself until a job is done. This is positive feedback. It is rare because it can quickly get out of hand.
Childbirth is one example. The baby's head stretches the cervix, the opening of the womb. This stretch causes the release of the hormone oxytocin. Oxytocin makes contractions stronger, which stretches the cervix even more. The cycle snowballs until the baby is born, which ends it. Blood clotting works the same way. The first platelets that stick to a cut give off chemicals. These call in more platelets, which call in still more. This seals the wound fast. Positive feedback always needs a built-in stop, like a birth or a finished clot. Without one, it would run out of control.
| Feature | Negative feedback | Positive feedback |
|---|---|---|
| What it does to the change | Works against it and reverses it | Makes it bigger and keeps it going |
| Result | Goes back to the set point (steady) | Pushes on until an event is finished |
| How common | The rule: most loops | The exception: only a few |
| Examples | Temperature, blood sugar, blood pressure, pH | Childbirth, blood clotting, milk release (lactation) |
Knock a value off its set point in the interactive and watch a negative feedback loop pull it home.
- Homeostasis means keeping the inside of the body steady, near a set point. Losing it is the root of most disease.
- A negative feedback loop has three parts: receptor → control center → effector. Its response works against the change to bring things back to normal.
- Positive feedback makes a change bigger until an event stops it. Examples are childbirth, clotting, and milk release.
Section 4The language of position
Start from the anatomical position
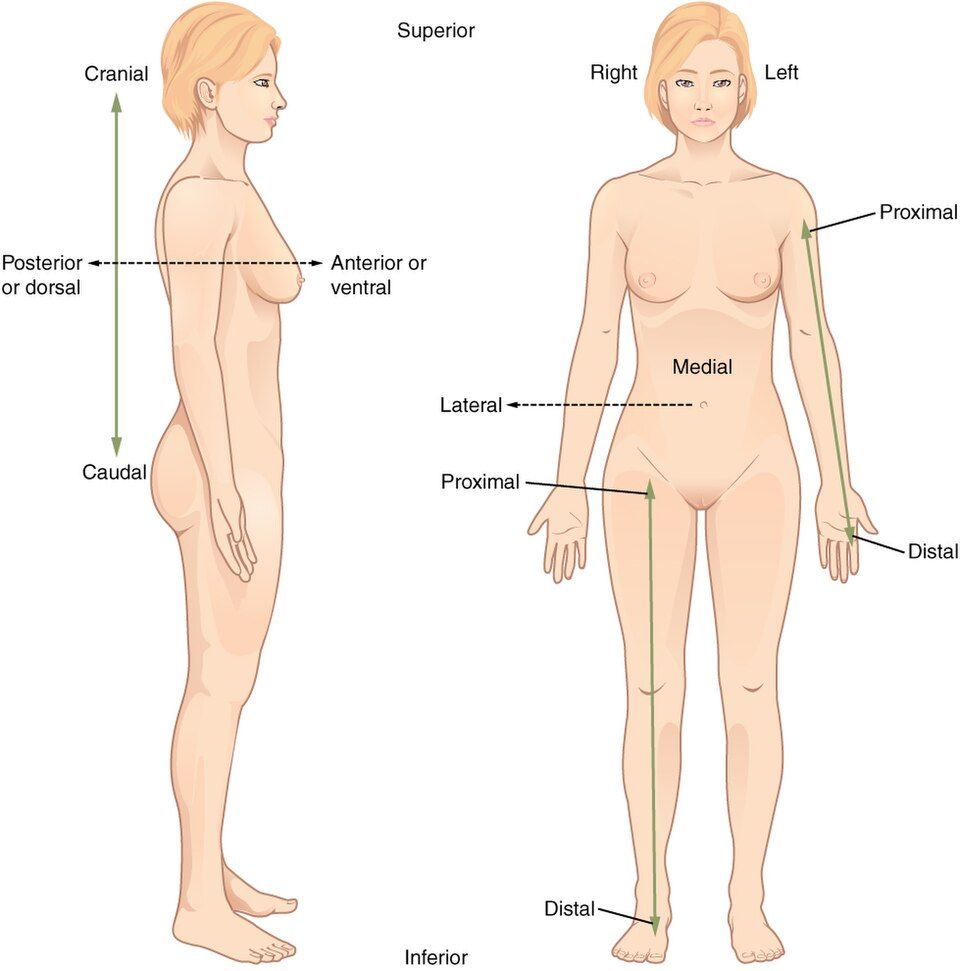
To say where things are without mix-ups, everyone starts from the same pose. It is called the anatomical position. The body stands upright and faces forward. The feet are a little apart. The arms hang at the sides with the palms facing forward. Every direction word is based on this pose. So a part's description never changes, even if the real patient is lying down or upside down.
One more rule trips up a lot of people. "Right" and "left" always mean the patient's own right and left. They do not mean your right and left as you look at the patient.
The directional pairs
Direction words come in opposite pairs. That makes them easy to learn two at a time:
| Term | Meaning | Example |
|---|---|---|
| Superior / Inferior | Above / below (toward the head / toward the feet) | The heart is superior to the stomach |
| Anterior / Posterior | Front / back (also called ventral / dorsal) | The breastbone (sternum) is anterior to the heart |
| Medial / Lateral | Toward the midline / away from it | The nose is medial to the eyes |
| Proximal / Distal | Closer to / farther from the trunk (for arms and legs) | The elbow is proximal to the wrist |
| Superficial / Deep | Toward the surface / away from it | The skin is superficial to the muscle |
Two of these pairs need extra care. Proximal and distal are used mostly for the arms and legs. They are always measured from where the limb joins the trunk. So the shoulder is proximal, and the fingertips are distal. Medial and lateral are measured from the midline, an imaginary line down the center of the body. Parts near the center are medial. Parts out toward the sides are lateral.
See each pair drawn on a body in anatomical position below.
- All direction words are based on the anatomical position: upright, facing forward, palms forward.
- Right and left always mean the patient's right and left.
- Learn the pairs: superior/inferior, anterior/posterior, medial/lateral, proximal/distal, and superficial/deep. Use them to compare two parts ("X is [term] to Y").
Section 5Planes & sections
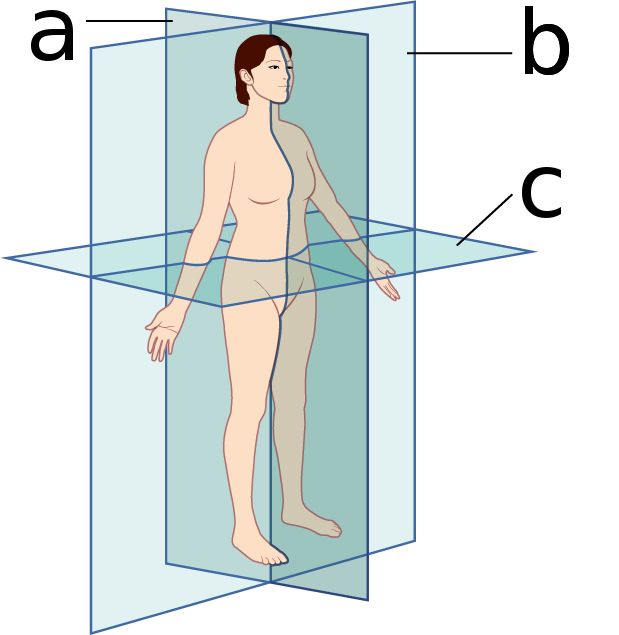
Three ways to slice
To see inside the body, we picture cutting it along flat surfaces called planes. This might be on a body in a lab or on a CT scan. There are three planes, and each one is at a right angle to the others:
- The sagittal plane splits the body into left and right. A cut right down the midline is a midsagittal section. A cut off to one side is parasagittal.
- The frontal (coronal) plane splits the body into front and back (anterior and posterior).
- The transverse (horizontal) plane splits the body into top and bottom (superior and inferior). This is the "slice" view you see on a CT scan.
Why does this matter to a nurse or other health worker? Medical images are always taken in one of these planes. To read a scan, you have to know which slice you are looking at. A transverse CT of the belly shows the organs cut straight across. A sagittal MRI of the spine is seen from the side. It shows the bones of the spine stacked from top to bottom (superior to inferior). Naming the plane is always the first step in making sense of an image.
Watch each plane sweep through the body in the interactive below.
- Sagittal = left and right. Frontal (coronal) = front and back. Transverse = top and bottom.
- A midsagittal cut makes two equal mirror halves. Other sagittal cuts (parasagittal) do not.
- To read a medical image (CT, MRI), first name its plane.
Section 6Cavities & regions
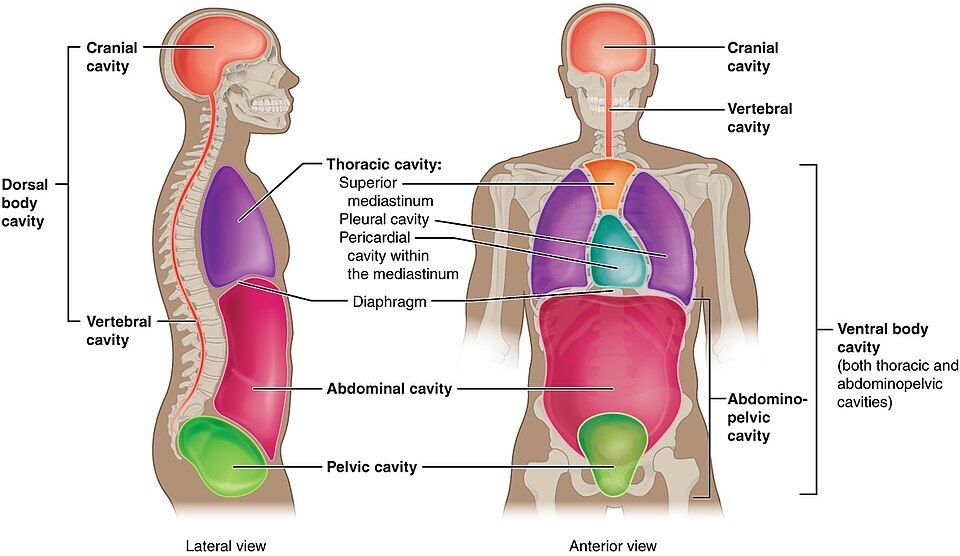
Where the organs live
Your organs are not loose inside you. They sit in closed spaces called body cavities. These spaces protect the organs and give them room to move. There are two main groups.
The dorsal (posterior) cavity runs along the back. It holds the nervous system. It has two parts: the cranial cavity, which holds the brain, and the vertebral cavity, which holds the spinal cord. The bigger ventral (anterior) cavity holds most of the other organs. A sheet of muscle called the diaphragm splits it in two. Above it is the thoracic cavity, or chest, with the heart and lungs. Below it is the abdominopelvic cavity, or belly and hip area. It holds the digestive organs, with the pelvic organs lower down.
Serous membranes: the slippery linings
Organs in the ventral cavity are wrapped in thin serous membranes. These are two-layered linings that give off a slippery fluid. The fluid lets organs slide past each other without rubbing. Each membrane has two layers with paired names. The parietal layer lines the wall of the cavity. The visceral layer hugs the organ itself.
There are three of these membranes. The parietal and visceral pleura wrap the lungs. The parietal and visceral pericardium wrap the heart. The parietal and visceral peritoneum wrap the belly organs. When one of them gets inflamed (red and swollen), you get an "-itis" disease. These are pleuritis, pericarditis, and peritonitis. The rubbing or fluid buildup can cause real trouble.
Mapping the abdomen: regions and quadrants
A lot can go wrong in the belly. So health workers split its surface into a grid. This lets them say exactly where a pain or a lump is. The simple version uses four quadrants: right and left, upper and lower. These are called RUQ, LUQ, RLQ, and LLQ. The more detailed version uses nine regions, like a tic-tac-toe grid. The umbilical region is in the center, around the belly button. The epigastric region is above it, and the hypogastric region is below it. More regions line up on each side. Saying "RLQ pain" quickly narrows down the cause, since the appendix sits there.
Explore the cavities, membranes, and the region/quadrant grids in the interactive.
- The dorsal cavity (cranial + vertebral) holds the brain and spinal cord, the central nervous system (CNS). The diaphragm splits the ventral cavity into the thoracic and abdominopelvic cavities.
- Serous membranes (pleura, pericardium, peritoneum) cut down on rubbing. When they get inflamed, you get the "-itis" diseases.
- The belly can be mapped into 4 quadrants or 9 regions. Where it hurts helps point to the cause.
The chapter in one breath
- Anatomy is how the body is built. Physiology is how it works. Structure always fits function.
- The body is built in six nested levels: chemical → cellular → tissue → organ → organ system → organism. The cell is the smallest living unit.
- Eleven organ systems share the work of staying alive, and they team up all the time. Know each one's main job.
- Homeostasis is a steady inside state, and it is what health looks like. Most disease is a failure of it.
- Negative feedback (receptor → control center → effector) works against a change to get back to a set point. Positive feedback makes a change bigger to finish an event, like childbirth or clotting.
- Body language starts from the anatomical position. Direction words come in pairs that compare two parts. Right and left mean the patient's sides.
- Three planes (sagittal, frontal, transverse) slice the body. Organs sit in dorsal and ventral cavities, lined by serous membranes. The belly is mapped into quadrants and regions.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back any time a word trips you up.
- Anatomical position
- The standard pose used to describe the body. You stand upright and face forward, with arms at your sides and palms forward. All direction words are based on it.
- Anatomy
- The study of the body's parts and how they sit next to each other. It asks what a part is and where it is.
- Anterior (ventral)
- Toward the front of the body.
- Control center
- The part of a feedback loop that compares a reading to the set point. It then decides on a response. It is often the brain or a hormone (endocrine) gland.
- Distal
- Farther from where a limb joins the trunk. The fingers are distal to the elbow.
- Effector
- The muscle or gland in a feedback loop that carries out the fix.
- Frontal (coronal) plane
- An up-and-down plane that splits the body into front (anterior) and back (posterior) parts.
- Homeostasis
- Keeping the inside of the body fairly steady, even when things outside change. Feedback keeps it near a set point.
- Medial
- Toward the midline of the body.
- Negative feedback
- A loop whose response works against the first change and reverses it. This brings the value back to its set point. It is the body's main way of keeping things steady.
- Organ
- A body part made of two or more kinds of tissue that does a certain job. The heart and stomach are organs.
- Physiology
- The study of how the body's parts work and the processes that keep you alive.
- Positive feedback
- A loop whose response makes the first change bigger. It keeps going until an event stops it, such as childbirth or a finished blood clot.
- Proximal
- Closer to where a limb joins the trunk. The elbow is proximal to the wrist.
- Sagittal plane
- An up-and-down plane that splits the body into left and right parts. A cut right down the midline is midsagittal.
- Serous membrane
- A thin, two-layered lining of a ventral cavity, such as the pleura, pericardium, or peritoneum. It gives off fluid so organs don't rub.
- Set point
- The target value the body tries to hold something near. For body temperature, it is about 37 °C.
- Superior
- Toward the head or the upper part of the body.
- Transverse (horizontal) plane
- A plane that splits the body into top (superior) and bottom (inferior) parts. It gives a cross-section, or slice, view.
Check yourself
The Chemical Level of Organization
Every heartbeat, every thought, and every drop of sweat starts as chemistry. Before a cell can divide or a nerve can fire, atoms must join, reactions must run, and water must do its quiet but vital work. This chapter takes you down to the chemical level. It is the base that the rest of this book is built on.
First you will meet the atom and the few elements that make up almost all of you. You will learn the three bonds that hold molecules together. You will watch reactions rearrange matter and see how enzymes speed them up. You will find out why water is perfect for life. You will learn to read pH and meet the buffers that guard your blood. Last, you will meet the four big families of molecules that build your body. Take your time here. Everything else in the body rests on this floor.
By the end of this chapter you can
- Describe the parts of an atom: protons, neutrons, and electrons. Explain how the atomic number tells you which element it is.
- Name the major elements that make up most of the body. Tell them apart from trace elements and isotopes.
- Compare ionic, covalent (polar and nonpolar), and hydrogen bonds. Explain the octet rule, the reason atoms bond.
- Sort chemical reactions into synthesis, decomposition, or exchange. Explain activation energy and how enzymes lower it.
- Explain how water's polarity makes it the body's solvent, heat buffer, and lubricant.
- Read the pH scale and tell acids from bases. Describe how buffers keep blood near 7.4.
- Name the four organic macromolecule families (carbohydrates, lipids, proteins, nucleic acids) plus ATP. Give a job for each.
- Compare dehydration synthesis and hydrolysis, the ways big molecules are built and broken.
Section 1Atoms & the elements
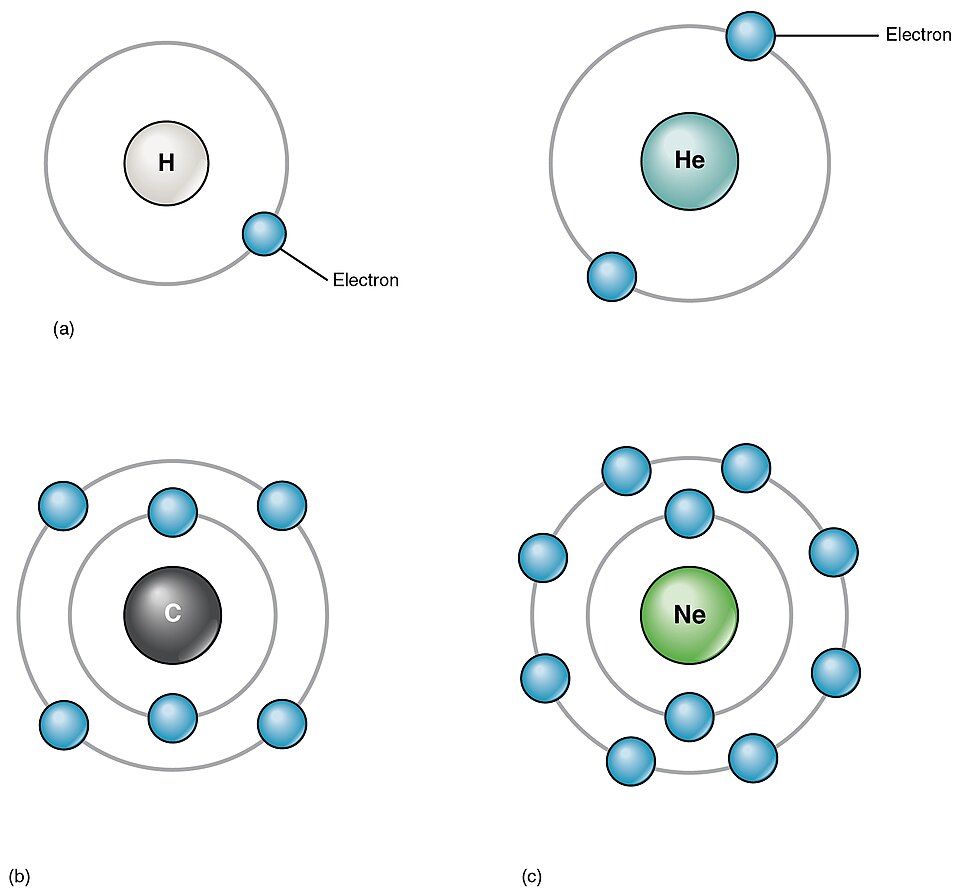
Matter, elements, and the atom
Anything that takes up space and has mass is matter. Your bones, your blood, and the air in your lungs are all matter. All matter is made of elements. An element is a pure substance that normal chemistry can't break into anything simpler. There are 118 known elements. But life uses only a few of them. Only about two dozen show up in the body. Just six of them make up about 99% of your mass. They are oxygen, carbon, hydrogen, nitrogen, calcium, and phosphorus.
The smallest bit of an element that still acts like that element is an atom. If you split an atom apart, you no longer have the element. You just have its raw parts.
| Element | Symbol | ~% of body mass | A job it does |
|---|---|---|---|
| Oxygen | O | 65% | Part of water; takes the electrons at the last step of making energy from food (cell respiration) |
| Carbon | C | 18% | The backbone of every organic molecule |
| Hydrogen | H | 10% | Part of water; as the H⁺ ion, it sets pH |
| Nitrogen | N | 3% | Found in every protein and nucleic acid |
| Calcium | Ca | 1.5% | Bone mineral; helps muscles and nerves send signals |
| Phosphorus | P | 1% | Bone; the energy-rich bonds of ATP; the backbone of DNA |
Inside the atom: three particles
An atom has a packed center called the nucleus. A cloud of moving electrons surrounds it. Only three tiny particles matter for this book. Protons have a positive charge and sit in the nucleus. Neutrons have no charge. They share the nucleus with the protons and add weight but no charge. Electrons have a negative charge and weigh almost nothing. They zip around the nucleus in layers called shells (energy levels).
Protons and electrons have equal but opposite charges. So a neutral atom has just as many electrons as protons. The charges cancel out, and the atom has no overall charge.
| Particle | Charge | Where it is | Relative mass |
|---|---|---|---|
| Proton | +1 | Nucleus | 1 (heavy) |
| Neutron | 0 | Nucleus | 1 (heavy) |
| Electron | −1 | Shells around the nucleus | ~1/1800 (almost nothing) |
Atomic number, isotopes, and the outer shell
One number is like an atom's fingerprint. It is the atomic number, the number of protons in the nucleus. Change it, and you change the element itself. An atom with 1 proton is always hydrogen. One with 6 is always carbon, and one with 8 is always oxygen. The mass number is the protons and neutrons added together.
Atoms of the same element can have different numbers of neutrons. These are called isotopes. Carbon-12 and carbon-14 are both carbon, with 6 protons each. But carbon-14 has two extra neutrons, and it is radioactive. That is why radioactive isotopes are so useful for medical scans and for dating old things.
Still, an atom's chemistry doesn't come from its nucleus. It comes from its outermost electrons, in the valence shell. Atoms are most stable, or "happiest," when that outer shell is full. For most atoms in the body, full means eight electrons. This is the octet rule. An atom with a full outer shell doesn't react. An atom missing a few electrons is reactive and ready to bond.
Pick an element and watch its atom take shape in the interactive below. You will see the nucleus in the center and the electrons filling their shells.
- An atom has a nucleus of positive protons and neutral neutrons. Negative electrons circle it in shells.
- The atomic number (number of protons) tells you the element. A neutral atom has equal protons and electrons.
- Isotopes are the same element with different numbers of neutrons. Some are radioactive and useful in medicine.
- The valence (outer) shell drives chemistry. Atoms bond to get a stable, full shell (the octet rule).
Section 2Chemical bonds
Why atoms bond at all
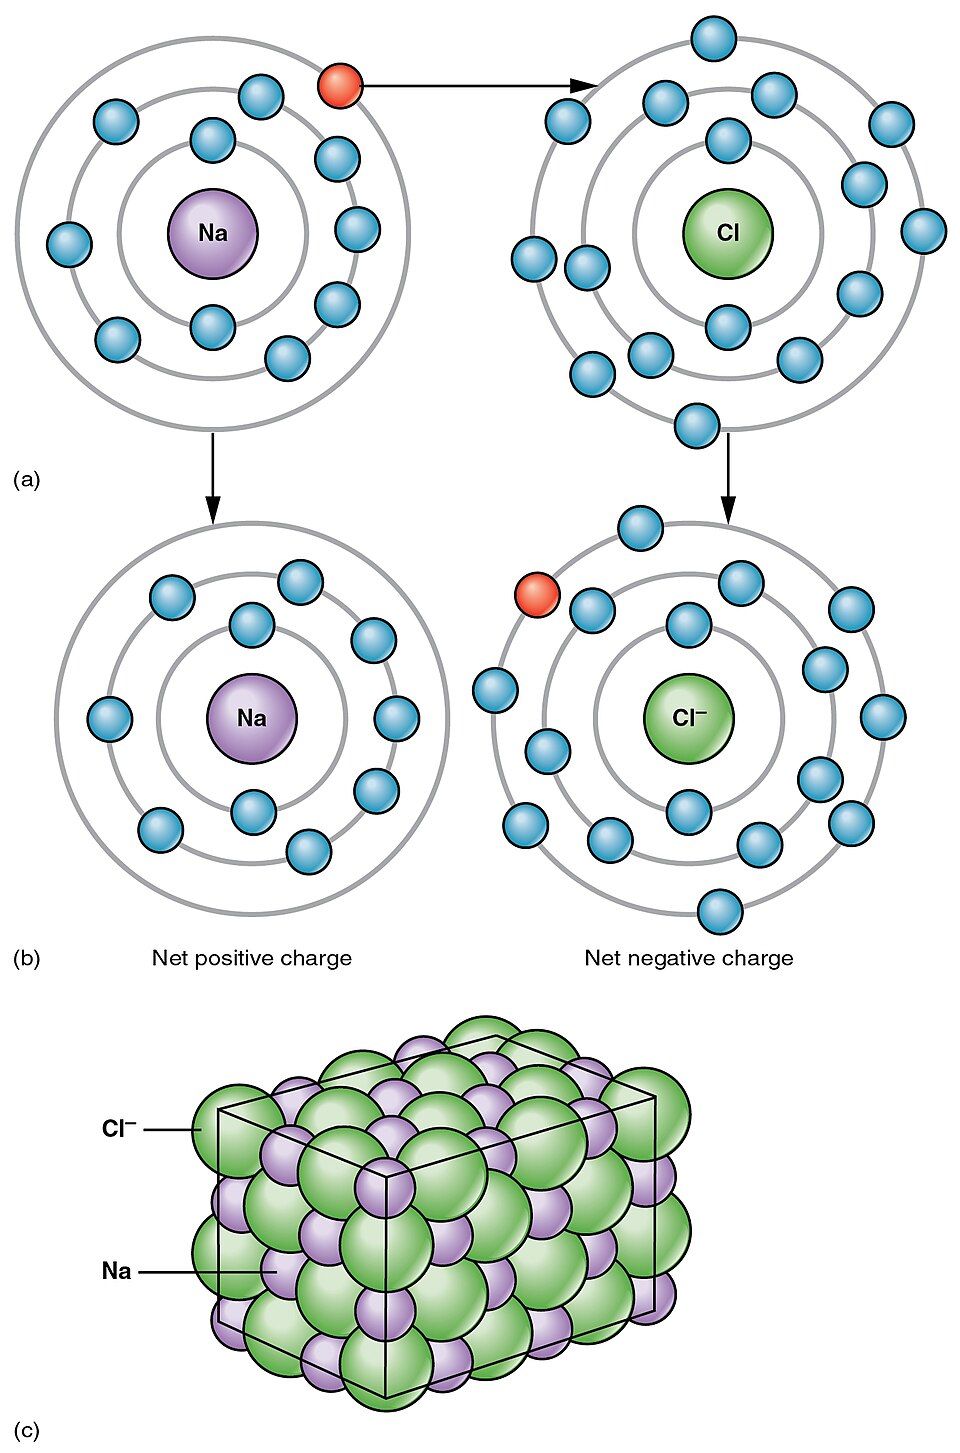
Atoms bond for one reason: to get a stable, full outer shell. An atom with a half-empty outer shell will do almost anything to fill it. It may give electrons away, take them, or share them. Each of these ways makes a different kind of bond. The noble gases, like helium, neon, and argon, already have full shells. So they drift around and don't react. Every other atom is looking for a partner. There are three main bonds: ionic, covalent, and hydrogen. Once you know them, you can predict how almost every molecule in the body behaves.
Ionic bonds: give and take
Sometimes the easiest way to fill a shell is to hand an electron over for good. One atom gives an electron, and another takes it. Then both end up with a charge. The giver becomes a positive ion called a cation. The taker becomes a negative ion called an anion. Opposite charges attract, and that pull is the ionic bond.
Table salt is the classic example. Sodium hands its one outer electron to chlorine and becomes Na⁺. Chlorine becomes Cl⁻. The two cling together as NaCl. In water, ionic compounds break apart into separate ions. These charged bits floating in body fluids are your electrolytes, such as Na⁺, K⁺, Ca⁺⁺, and Cl⁻. They run nerve signals, muscle contractions, and fluid balance.
Covalent bonds: sharing, polar and nonpolar
More often, two atoms just share a pair of electrons. Both atoms count the pair toward a full shell. This is a covalent bond. It is the strongest and most common bond in the body. Carbon builds all of life with covalent bonds.
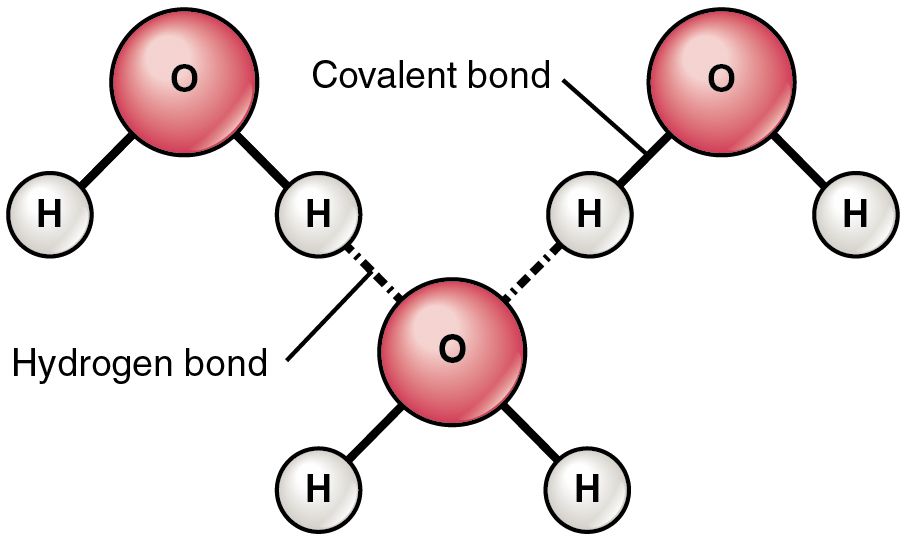
But sharing is not always fair. When both atoms pull the same amount, the shared electrons sit in the middle. The bond is nonpolar, as in O₂ or the carbon–hydrogen bonds of fats. When one atom pulls harder, it hogs the electrons. The bond becomes polar. One end is slightly negative, and the other end is slightly positive. Water is the great polar molecule. Its oxygen pulls the shared electrons away from its two hydrogens. So the oxygen has a partial negative charge, and the hydrogens have a partial positive charge. As you will see, this lopsided charge makes life possible.
Hydrogen bonds: weak but mighty
A hydrogen bond is not a bond inside a molecule. It is a gentle pull between molecules, or between far-apart parts of one big molecule. It forms when the slightly positive hydrogen of one polar molecule is drawn to the slightly negative oxygen or nitrogen of another.
One hydrogen bond on its own is weak, only a small part of the strength of a covalent bond. But millions of them together are mighty. Hydrogen bonds hold liquid water together. They zip the two strands of DNA into a double helix, like the teeth of a zipper. They also fold proteins into their working shapes. They are strong enough to give shape, but weak enough to break and form again. That is just what living molecules need.
| Bond | How it forms | Strength | Example |
|---|---|---|---|
| Ionic | One atom gives an electron to another; the opposite charges attract | Strong (weak once it dissolves in water) | Na⁺Cl⁻ (table salt) |
| Covalent (nonpolar) | Electrons are shared equally | Strong (covalent bonds are the strongest in the body) | O₂; C–H bonds in fats |
| Covalent (polar) | Electrons are shared unequally, so each end gets a partial charge | Strong (covalent bonds are the strongest in the body) | Water (H₂O) |
| Hydrogen | A pull between partial + and partial − charges on polar molecules | Weak (strong in large numbers) | Between water molecules; between DNA strands |
Flip between ionic, covalent, and hydrogen bonds and watch how each one forms in the interactive.
- Atoms bond to fill their valence shell. A full shell is stable and does not react.
- Ionic bonds pass electrons from one atom to another. This makes charged ions (electrolytes) that split apart in water.
- Covalent bonds share electrons, either equally (nonpolar) or unequally (polar). They are the body's strongest bonds.
- Hydrogen bonds are weak pulls between polar molecules. Added up, they hold water, DNA, and proteins together.
Section 3Chemical reactions & enzymes
Reactants, products, and three ways to rearrange atoms
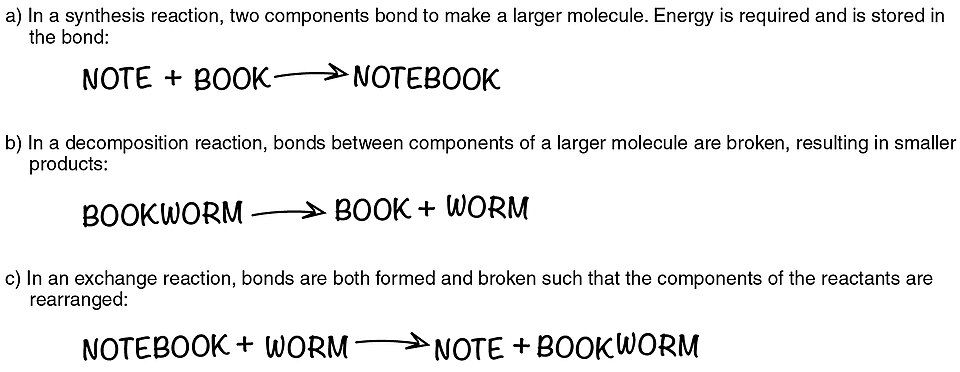
A chemical reaction is just the making or breaking of bonds. Atoms let go of old partners and grab new ones. The starting materials are the reactants. What you end up with are the products. No atoms are made or destroyed. They are only moved around.
Almost every reaction in the body fits one of three patterns. Synthesis reactions join small parts into a bigger molecule (A + B → AB). These are the building, or anabolic, reactions. Decomposition reactions break a big molecule into smaller pieces (AB → A + B). These are the breaking-down, or catabolic, reactions, like digesting a meal. Exchange reactions do both at once and swap partners (AB + CD → AC + BD). Many reactions are also reversible. They can run either way, depending on conditions.
| Type | Pattern | What it does | Body example |
|---|---|---|---|
| Synthesis (anabolic) | A + B → AB | Builds bigger molecules | Amino acids joined into a protein |
| Decomposition (catabolic) | AB → A + B | Breaks molecules apart | Digesting starch into glucose |
| Exchange | AB + CD → AC + BD | Swaps partners | Buffers trading H⁺ in the blood |
Energy: the hill every reaction must climb
Chemical bonds store energy, so moving them around always changes energy. Reactions that give off energy, often as heat, are exergonic. These power the body, like breaking down glucose. Reactions that take in energy are endergonic. Building big molecules costs energy.
But here is the catch. Even a reaction that gives off energy must first get over a small hump. This hump is the activation energy, the energy needed to get a reaction started. Picture a boulder resting in a small dip near the top of a hill. It will roll down and release lots of energy. But first, something has to lift it over the lip of the dip. That lip is the activation energy. At body temperature, most reactions would sit stuck behind it for hours or even years.
Enzymes: shrinking the hill
The body can't wait hours. It can't just turn up the heat, either. So it uses enzymes. An enzyme is a catalyst, a helper that speeds up a reaction. Enzymes are almost always proteins. They lower the activation energy. This lets reactions run thousands or millions of times faster at a safe 37 °C. And an enzyme is not used up. It does its job and is free to do it again.
Each enzyme is very specific. It has an active site shaped to fit one certain molecule, its substrate. Think of a key in a lock. A better picture is a glove that shapes itself around a hand. Since enzymes are proteins, anything that unfolds a protein can harm them. A high fever or the wrong pH can do this. That is one reason your body guards its temperature and pH so closely.
Watch a reaction climb over its energy hill in the interactive below. Then switch on an enzyme and see the hill shrink.
- Reactions move atoms around to turn reactants into products. The three types are synthesis, decomposition, and exchange.
- Exergonic reactions give off energy. Endergonic reactions take it in. Every reaction must first get over its activation energy.
- Enzymes are protein helpers that lower activation energy. They can be used again, and each one is very specific to its substrate.
- Enzymes depend on their shape. So very high heat or the wrong pH can stop them from working.
Section 4Water, the solvent of life
Polarity: the source of all water's tricks
You are about 60% water, and that is no accident. Almost everything special about water comes from one fact: it is polar. Recall from Section 2 that oxygen hogs the shared electrons in each O–H bond. So a water molecule (H₂O) is slightly negative at the oxygen end. It is slightly positive at the two hydrogen ends. Opposite charges attract. So each water molecule clings to the ones around it by hydrogen bonds. This shifting web of hydrogen bonds is the hidden reason water can be a solvent, a heat buffer, and a lubricant.
The universal solvent
Water is called the universal solvent. Its charged ends surround other charged or polar substances and pull them apart. They spread out evenly to form a solution. The liquid that does the dissolving is the solvent. The substance that gets dissolved is the solute.
Molecules that mix into water, like salts, sugars, and amino acids, are hydrophilic ("water-loving"). Nonpolar molecules, like fats, are hydrophobic ("water-fearing"). They won't dissolve in water. This split does real work in the body. It is why cell membranes, made of hydrophobic lipids, can form watertight walls in your watery body. So much of the body's chemistry happens in water. Nutrients travel in it, wastes dissolve in it, and reactions happen in it. Blood plasma is really just water carrying dissolved cargo.
Heat, cushioning, and chemistry
Water's hydrogen bonds also give it a very high heat capacity. It takes a lot of energy to warm water up. So your water-filled body resists sudden changes in temperature and stays near 37 °C. And when water evaporates, it carries away a lot of heat. That is why sweating cools you so well on a hot day.
Water molecules also stick to each other. This lets water form slippery films that protect and cushion. The fluid in serous membranes, the fluid in your joints (synovial fluid), and the mucus lining your airways all depend on it. Last, water doesn't just sit by during chemistry. It takes part. The body builds big molecules by taking water out (dehydration synthesis). It breaks them down by adding water in (hydrolysis). You will see these two reactions again in Section 6.
| Property | Why (from polarity) | What it does for you |
|---|---|---|
| Solvent | Its charged ends pull solutes apart | Carries nutrients, wastes, and ions in the blood |
| High heat capacity | Hydrogen bonds soak up heat | Keeps body temperature steady near 37 °C |
| Evaporative cooling | Breaking hydrogen bonds carries heat away | Sweating cools the body |
| Cohesion / lubrication | Water molecules stick to each other | Slippery films in joints, membranes, and airways |
| Reactant | Can be added or taken out in reactions | Builds and breaks big molecules |
Explore what water's lopsided charge does for you in the interactive. See how it dissolves things, sticks together, and soaks up heat.
- Water is polar, so its molecules form hydrogen bonds with each other. This is the source of all its special traits.
- As the universal solvent, water dissolves hydrophilic solutes but not hydrophobic ones. This split shapes cell membranes.
- A high heat capacity and cooling by evaporation let water keep body temperature steady and make sweating work.
- Water is a reactant. It is taken out in dehydration synthesis and added in hydrolysis.
Section 5pH, acids, bases & buffers
What pH actually measures
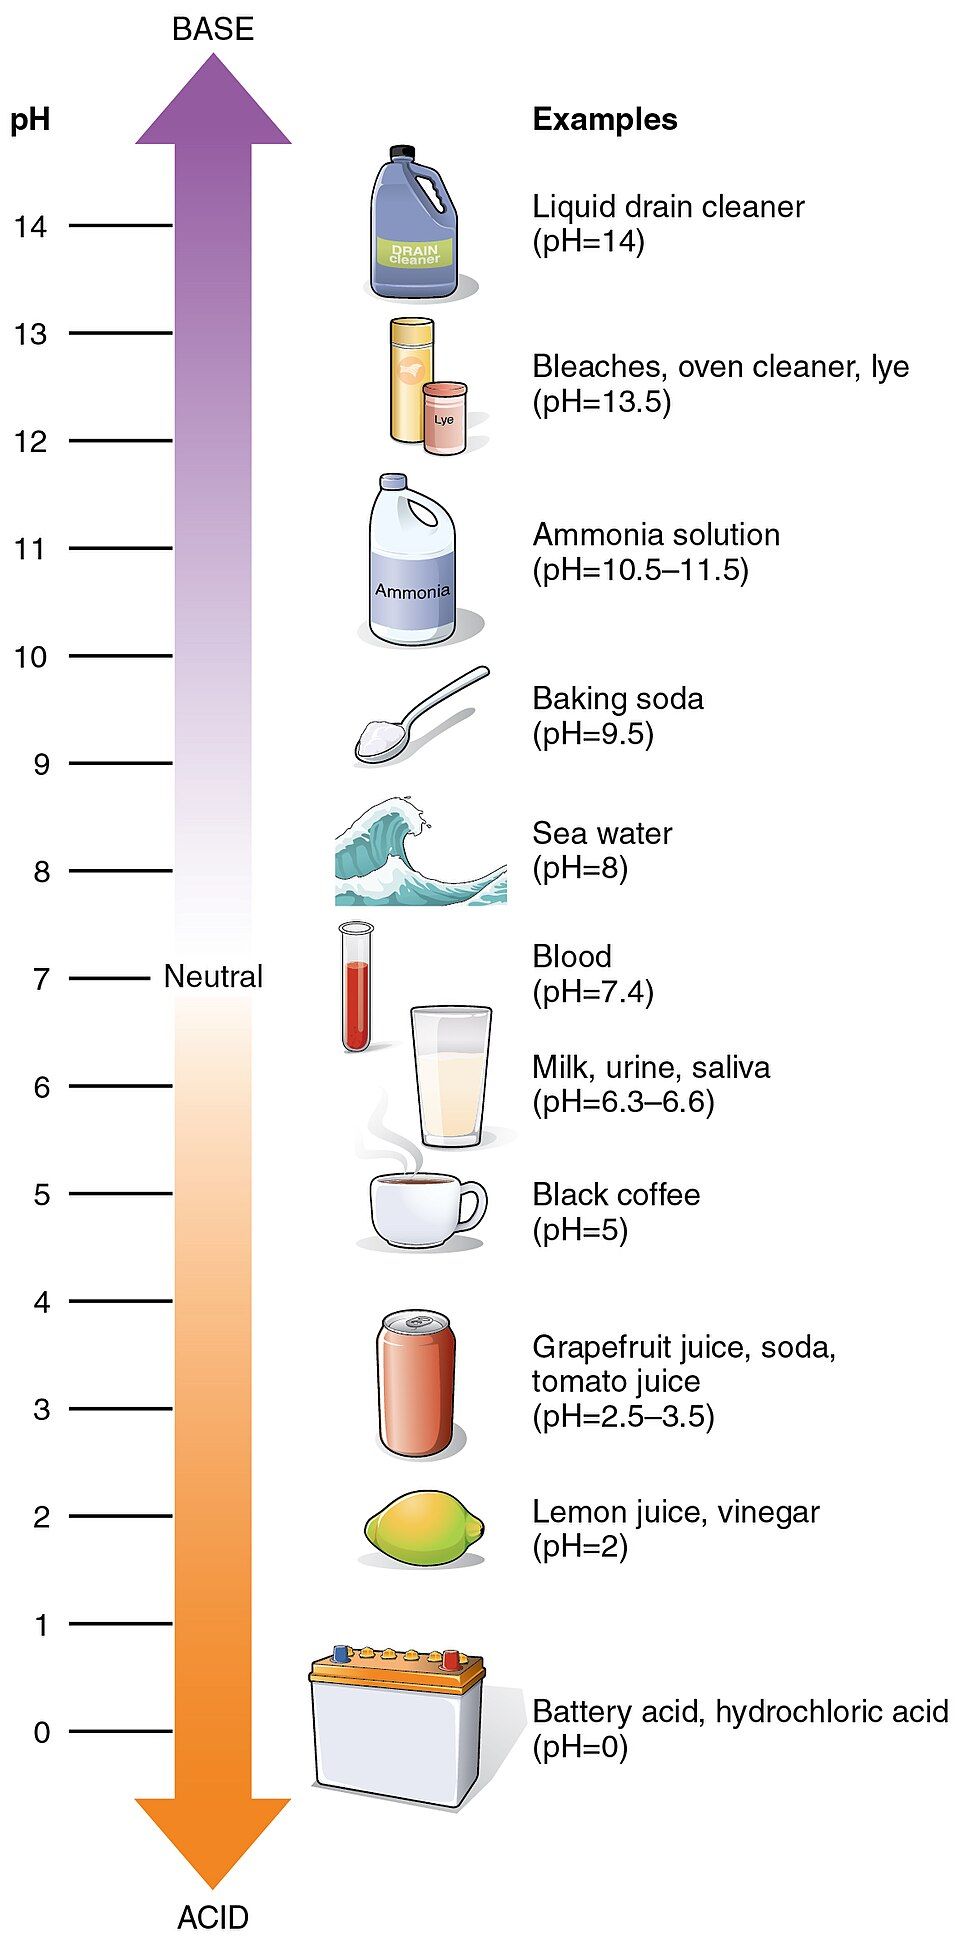
pH measures how many free hydrogen ions (H⁺) are floating loose in a fluid. The more H⁺ there is, the more acidic the fluid. The less there is, the more basic (alkaline) it is. The scale runs from 0 to 14. 7 is neutral, like pure water. Below 7 is acidic, and above 7 is basic.
There is one twist you must keep in mind. The scale is logarithmic. That means each whole step is a tenfold change in H⁺. A fluid at pH 4 is not just a bit more acidic than one at pH 5. It holds ten times more hydrogen ions. That is why a shift of even a few tenths of a pH unit in the blood is a real emergency.
Acids, bases, and the number that matters most
An acid is a substance that gives off H⁺ into a fluid. This pushes the pH down. Stomach acid is near pH 2. A base takes up H⁺ (or gives off OH⁻). This pushes the pH up. Household bleach and the juices from the pancreas are basic.
The most important pH in the body is the pH of blood. It must stay in the very narrow range of 7.35 to 7.45, or about 7.4. If it drops below 7.35, that is acidosis. If it rises above 7.45, that is alkalosis. If it goes past about 6.8 or 7.8, proteins lose their shape and enzymes fail. Then life is in danger. The pH of the world outside swings a lot. But the body keeps its blood almost perfectly steady.
| Fluid | About what pH | Acidic / basic |
|---|---|---|
| Stomach acid | ~2 | Strongly acidic |
| Urine | ~6 | Slightly acidic |
| Pure water | 7 | Neutral |
| Blood | 7.35–7.45 | Slightly basic |
| Pancreatic juice | ~8 | Basic |
Buffers: holding the line at 7.4
Acids pour into the blood from every meal and every working muscle. So how does blood keep its pH so steady? The answer is buffers. A buffer is a team of chemicals that soaks up extra H⁺ when a fluid gets too acidic. It gives off H⁺ when the fluid gets too basic.
The body's first line of defense is the bicarbonate system. It is made of carbonic acid (H₂CO₃) and the bicarbonate ion (HCO₃⁻). The two trade hydrogen ions back and forth to soften any swing. Buffers don't make acid go away. They soften the blow and buy time. Then the lungs and kidneys fix the real balance. The lungs breathe out CO₂, and the kidneys get rid of H⁺ in urine. This is homeostasis at the level of molecules. It is also a sneak peek at the acid–base chapters later in the book.
Push the pH up and down in the interactive and watch buffers fight to pull it back toward neutral.
- pH measures free H⁺. Below 7 is acidic, and above 7 is basic. The scale is logarithmic, so each unit is a 10× change.
- Acids give off H⁺, and bases take it up. Blood must stay in the narrow range of 7.35–7.45.
- Going out of range causes acidosis (too low) or alkalosis (too high). Both are dangerous.
- Buffers, mainly the bicarbonate system, soak up or give off H⁺ to keep pH steady.
Section 6The molecules of life
Organic molecules and the carbon backbone
Now let's move from small inorganic molecules, like water, salts, and gases, to the big organic ones. These are the true building blocks of the body. Organic molecules are built on a frame of carbon. Carbon is the perfect building atom. It can form four covalent bonds at once. This lets it link into long chains, branch out, and close into rings.
The biggest of these molecules are called macromolecules. Most are polymers, long chains snapped together from small repeating units called monomers. Think of beads on a string. The body builds a polymer by dehydration synthesis. It takes out a water molecule to join two monomers. It breaks a polymer apart by hydrolysis. It adds water to split the bond. Almost everything you are made of belongs to just four families. There is also one special molecule that powers it all.
The four families
Carbohydrates are sugars and chains of sugars. Their monomers are called monosaccharides, such as glucose. These link up into polysaccharides, such as glycogen and starch. Carbohydrates are the body's quick, favorite fuel.
Lipids are the oily molecules that don't mix with water. Triglycerides store energy and keep you warm. Phospholipids build every cell membrane. Steroids, like cholesterol, are used to make hormones. Lipids avoid water, and that is exactly what makes membranes work.
Proteins are the body's workhorses. They are built from twenty kinds of amino acids linked in a chain. The chain then folds into an exact 3-D shape. A protein's shape decides its job. So if a protein unfolds (denatures) from heat or the wrong pH, it stops working. Think of egg white turning solid in a hot pan. Proteins act as enzymes, building fibers, carriers, and messengers.
Nucleic acids, DNA and RNA, are chains of nucleotides. They store and carry the genetic instructions for building every protein in your body.
| Family | Monomer / unit | Example | Main job |
|---|---|---|---|
| Carbohydrate | Monosaccharide (glucose) | Glycogen, starch | Quick energy; short-term fuel storage |
| Lipid | Fatty acids + glycerol | Triglyceride, phospholipid, cholesterol | Energy storage, keeping warm, membranes, hormones |
| Protein | Amino acid (20 kinds) | Enzymes, keratin, hemoglobin | Structure, speeding up reactions, carrying things, sending signals |
| Nucleic acid | Nucleotide | DNA, RNA | Store and use genetic information |
ATP: the cell's energy currency
One small molecule gets its own spotlight. It is adenosine triphosphate, or ATP. ATP is the energy "money" that every cell spends. It has a tail of three phosphate groups. The bond to the last phosphate is like a loaded spring.
When a cell needs power, it snaps off that last phosphate (ATP → ADP + phosphate). The energy that comes out does the work. This might be making a muscle contract, pumping an ion, or building a molecule. Then the cell uses energy from food to turn ADP back into ATP. In a real sense, you remake about your own body weight in ATP every day. Your body spends and rebuilds it billions of times a second.
Pick a molecule family in the interactive below and watch it snap together from its monomers.
- Organic molecules are built on carbon, which forms four bonds. Big ones are polymers made of repeating monomers.
- Polymers are built by dehydration synthesis (taking out water). They are broken by hydrolysis (adding water).
- The four families are carbohydrates (fuel), lipids (membranes, storage, hormones), proteins (workhorses whose shape sets their job), and nucleic acids (genetic information).
- ATP is the cell's energy currency. It gives off energy when its last phosphate is removed.
The chapter in one breath
- All matter is made of elements. The smallest unit of an element is the atom. It has a nucleus of protons and neutrons, with electrons around it. The atomic number (number of protons) tells you the element.
- Six elements, O, C, H, N, Ca, P, make up about 99% of the body. Atoms bond to fill their outer shell (the octet rule).
- Three bonds hold molecules together. Ionic bonds pass electrons and make ions. Covalent bonds share electrons and can be polar or nonpolar. Hydrogen bonds are weak.
- Reactions move atoms around by synthesis, decomposition, or exchange. Each must get over an activation energy hill, and enzymes lower that hill.
- Water is polar. This makes it the body's solvent, heat buffer, and lubricant. It also takes part in building and breaking molecules.
- pH tracks free H⁺ on a logarithmic scale. Buffers such as bicarbonate keep blood at 7.35–7.45.
- Life is built from four organic families: carbohydrates, lipids, proteins, nucleic acids. ATP powers the work. These molecules are built by dehydration synthesis and broken by hydrolysis.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back any time a word trips you up.
- Acid
- A substance that gives off hydrogen ions (H⁺) into a fluid. It lowers the pH below 7.
- Activation energy
- The first energy hump a reaction must get over before it can go. Enzymes lower it.
- Atom
- The smallest unit of an element that still acts like that element. It has a nucleus of protons and neutrons, with electrons around it.
- Atomic number
- The number of protons in an atom's nucleus. It tells you which element the atom is.
- ATP (adenosine triphosphate)
- The cell's energy currency. It gives off usable energy when its last phosphate is removed, which turns it into ADP.
- Base
- A substance that takes up hydrogen ions (or gives off OH⁻). It raises the pH above 7.
- Buffer
- A set of chemicals that keeps pH from changing by soaking up or giving off H⁺. The bicarbonate buffer in blood is one example.
- Carbohydrate
- A family of organic molecules made of sugars and chains of sugars, like glucose and glycogen. They are used mainly for quick energy.
- Covalent bond
- A bond in which atoms share electrons. Equal sharing is nonpolar. Unequal sharing is polar.
- Dehydration synthesis
- Building a polymer by taking out a water molecule to join two monomers.
- Electron
- A tiny, almost weightless particle with a negative charge. It moves around the nucleus in shells and drives chemical bonding.
- Element
- A pure substance that can't be broken down by chemistry. The body is built mostly from six of them.
- Enzyme
- A helper molecule, usually a protein, that speeds up a reaction by lowering its activation energy. It is not used up.
- Hydrogen bond
- A weak pull between the slightly positive hydrogen of one polar molecule and a slightly negative atom of another.
- Hydrolysis
- Breaking a polymer apart by adding a water molecule across a bond.
- Ionic bond
- A bond that forms when one atom gives an electron to another. This makes two ions with opposite charges that attract.
- Isotope
- An atom of an element with the usual number of protons but a different number of neutrons.
- Lipid
- A family of organic molecules that avoid water (hydrophobic). It includes triglycerides, phospholipids, and steroids. They are used for energy storage, membranes, and hormones.
- Nucleic acid
- A chain of nucleotides, either DNA or RNA. It stores and uses genetic information.
- pH
- A logarithmic measure of how many free hydrogen ions are in a fluid. 7 is neutral, lower is acidic, and higher is basic.
- Polar molecule
- A molecule with an uneven charge, such as water. One end is slightly negative, and the other end is slightly positive.
- Protein
- A chain of amino acids folded into an exact shape. Its shape sets its job, such as an enzyme, a building block, a carrier, or a messenger.
Check yourself
The Cellular Level of Organization
The last chapter looked at the whole body. This one zooms all the way in, to the smallest thing that is still alive. The cell is where the body's work really happens. It is where oxygen is used to make energy. It is where genes are read to make proteins. It is where the choice to grow or divide is made. In this chapter you will meet the membrane, the thin wrap around every cell that picks what gets in and out. You will tour the organelles, the tiny parts that share the work inside. You will follow a gene, a set of instructions, as it becomes a working protein. Then you will watch one cell become two. Once you know the cell, the rest of the body makes more sense. Every tissue, organ, and system is just cells working together.
By the end of this chapter you can
- Describe the fluid mosaic model. Explain the jobs of the phospholipid bilayer, membrane proteins, cholesterol, and the sugar coat.
- Tell passive transport from active transport. Put diffusion, facilitated diffusion, osmosis, the Na⁺/K⁺ pump, and bulk transport in the right group.
- Name the main organelles and give the job of each one.
- Explain how the nucleus stores DNA. Explain how that DNA is packed into chromatin and chromosomes.
- Follow protein synthesis from gene to protein, through transcription and translation.
- Put the phases of the cell cycle in order. Describe what happens in each stage of mitosis.
- Predict what happens to a cell in isotonic, hypotonic, and hypertonic fluids. Link this to how an IV fluid is chosen.
Section 1The cell membrane
A smart wall
Every cell in your body is wrapped in a plasma membrane. This is the thin outer skin of the cell. It is so thin that you cannot see it with a normal light microscope. Yet it is smart enough to decide what comes in and what goes out. Without it, a cell would just fall apart into the fluid around it.
The membrane does three big jobs at once. First, it separates the inside of the cell from the outside. Second, it controls traffic across that border. It is selectively permeable, which means it lets some things through and blocks others. Third, it communicates. It carries receptors and ID tags, so the cell can sense signals and be known by other cells. Everything else in this chapter depends on this one wall doing its job.
The fluid mosaic model
Scientists picture the membrane with the fluid mosaic model. Both words matter. Mosaic means it is a patchwork of many pieces. Fats, proteins, and sugars sit side by side like tiles. Fluid means the pieces are not glued down. They drift and wiggle sideways in the sheet. So the membrane acts more like a thin film of oil than a hard wall.
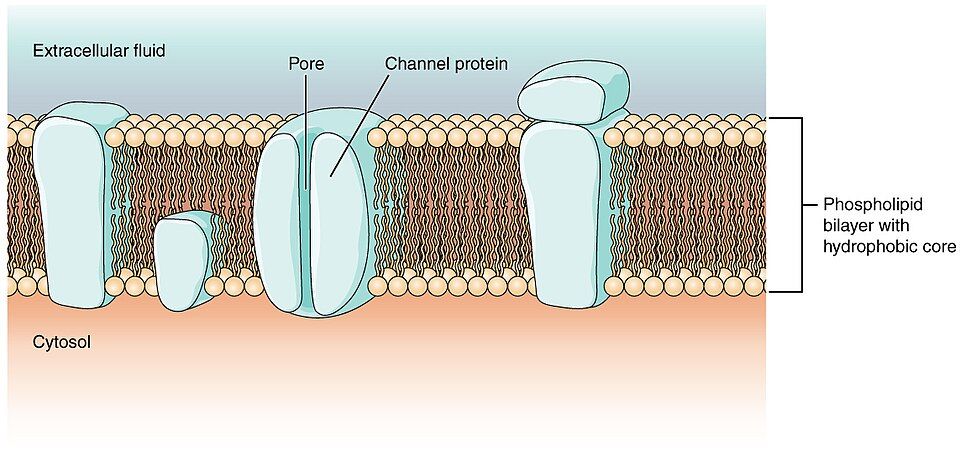
The base of the membrane is the phospholipid bilayer. It is two layers of fat molecules called phospholipids, lined up tail to tail. Each phospholipid is amphipathic, which means it has two very different ends. It has a hydrophilic ("water-loving") head and two hydrophobic ("water-fearing") fatty tails. Put these molecules in water and they line up on their own. The heads face the watery fluid on both sides. The oily tails hide in the middle, away from water.
That oily middle is the secret to how picky the membrane is. Small molecules that dissolve in fat slip right through it. Ions and other water-loving molecules get turned away. They need a protein doorway to get across.
Set into this fat sheet are the membrane proteins, and they do most of the work. Integral (transmembrane) proteins pass all the way through the membrane. They form the channels, carriers, and pumps that move things across. Peripheral proteins stick to just one surface. They often act as enzymes, which speed up reactions, or as anchors. Some proteins are receptors that catch hormones and other signals. Others are identity markers that label the cell as "self," part of your own body.
Tucked between the fats are molecules of cholesterol. Cholesterol keeps the membrane just right. It stops the membrane from getting too stiff when cold or too runny when warm. Last, short sugar chains stick to the outside of some proteins and fats. Together they form the glycocalyx, a fuzzy sugar coat on the cell's outer face. It helps cells know each other, stick together, and tell "self" from "not self."
| Part | What it is | Main job |
|---|---|---|
| Phospholipid bilayer | Two layers of amphipathic phospholipids, tails inward | The basic wall. Blocks water-loving molecules and lets small fat-soluble ones pass. |
| Integral proteins | Proteins that span the whole membrane | Channels, carriers, and pumps that move things; receptors |
| Peripheral proteins | Proteins stuck to one surface | Enzymes, anchors, and support for cell shape |
| Cholesterol | Fat molecules tucked between phospholipids | Keeps the membrane from getting too stiff or too runny as temperature changes |
| Glycocalyx | Sugar chains on glycoproteins and glycolipids | Helps cells know each other and stick together; "self" ID tags |
Tap each part of the membrane below to see it up close.
- The plasma membrane separates, controls traffic (it is selectively permeable), and communicates.
- The fluid mosaic model: a fluid phospholipid bilayer with proteins, cholesterol, and sugars set into it. The water-loving (hydrophilic) heads face out. The water-fearing (hydrophobic) tails face in.
- Small fat-soluble molecules cross the oily middle easily. Ions and other water-loving molecules need protein channels or carriers.
- Water seeps through the membrane slowly on its own. It moves much faster through aquaporin channels.
- Cholesterol keeps the membrane from getting too stiff or too runny. The glycocalyx helps cells know each other and mark "self."
Section 2Moving things across
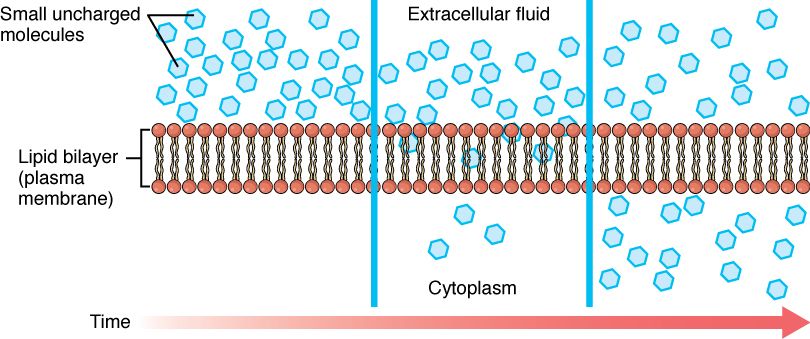
The one question to ask: does it cost energy?
A cell must always bring in food, push out waste, and keep the right mix of salts and water. It has many ways to move things across its membrane. Every one of them falls into one of two groups. The dividing line is energy.
In passive transport, things move down their concentration gradient. That means they go from where there is a lot of them to where there is less. This costs the cell no ATP, because it just goes with the natural flow. In active transport, the cell moves things up a gradient. They go against the flow, from low amounts to high amounts. That always takes energy, most often ATP. So before you learn the names, ask one thing. Is it rolling downhill for free (passive)? Or is it being pushed uphill at a cost (active)?
Passive transport: rolling downhill
The simplest kind is simple diffusion. Molecules are always moving around at random. Over time, they spread out from crowded places to less crowded places, until they are evenly mixed. Small molecules with no charge, like oxygen and carbon dioxide, slip right through the fat layer. That is how O₂ gets into every cell and CO₂ gets out.
Some molecules are too big or too charged to cross the fat layer alone. They use facilitated diffusion. They still move downhill for free. But they go through a protein channel or carrier that gives them a way in. Glucose, a sugar, getting into a cell is the classic example.
One special and vital kind of passive transport is osmosis. Osmosis is the diffusion of water across a selectively permeable membrane. It is so important that it gets its own section at the end of this chapter.
Active transport: pushing uphill
Sometimes a cell needs more of a substance on one side than the other. That means moving it against its gradient, which takes energy. In primary active transport, a pump uses ATP directly. The best known is the sodium–potassium pump (Na⁺/K⁺ pump). For every ATP it uses, it pushes 3 Na⁺ out of the cell and brings 2 K⁺ in. This pump runs in every cell you have. It sets up the electrical charge that lets nerves send signals and muscles squeeze.
In secondary active transport, the cell uses the gradient that a primary pump already built. One ion rushes downhill, and it drags another substance uphill along with it. It is a bit like a water wheel that uses falling water to lift something else.
Some cargo is far too big for any channel, like whole droplets or bits of matter. For these the cell uses bulk transport. It wraps the cargo in a piece of membrane. Endocytosis brings cargo in. This includes phagocytosis, "cell eating," and pinocytosis, "cell drinking." Exocytosis sends cargo out.
| Method | Energy? | Direction and example |
|---|---|---|
| Simple diffusion | No (passive) | Downhill, right through the fat layer: O₂, CO₂ |
| Facilitated diffusion | No (passive) | Downhill, through a protein: glucose, ions |
| Osmosis | No (passive) | Water moves toward the saltier side |
| Primary active transport | Yes, uses ATP directly | Uphill, by a pump: Na⁺/K⁺ pump (3 out, 2 in) |
| Secondary active transport | Yes, uses an ion gradient | Rides another ion's gradient: glucose and Na⁺ moving in together in the gut |
| Bulk transport | Yes (active) | Cargo wrapped in membrane: endocytosis (in), exocytosis (out) |
Pick a transport method below and watch the molecules cross.
- Passive transport moves things down their gradient for free. Active transport moves them up a gradient, and it costs energy.
- Passive types: simple diffusion, facilitated diffusion (through a protein), and osmosis (water).
- The Na⁺/K⁺ pump moves 3 Na⁺ out and 2 K⁺ in for each ATP. It is primary active transport. It powers the electrical signals of nerves and muscles.
- Bulk transport moves the biggest cargo: endocytosis in, exocytosis out.
Section 3Inside the cell: the organelles
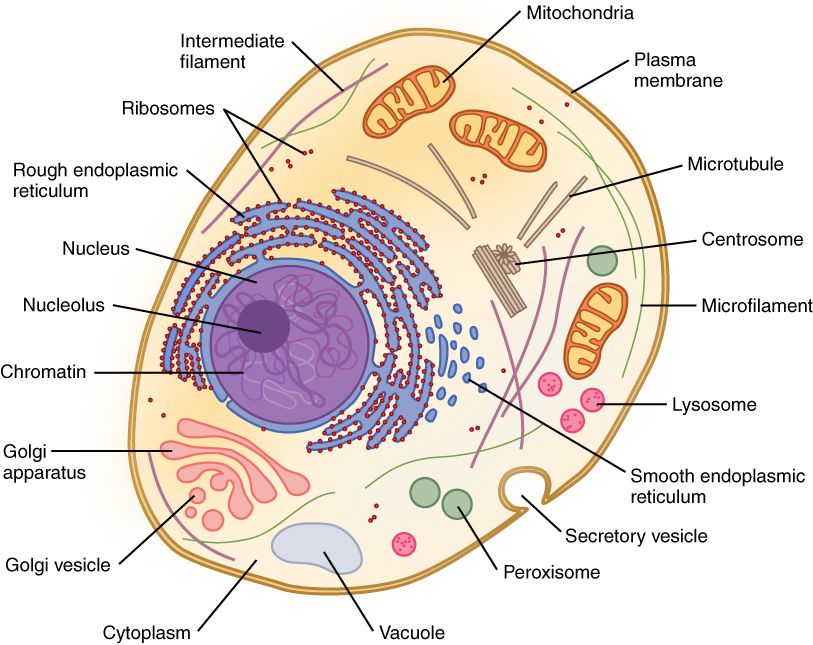
A factory with departments
Look inside the membrane and you will not find an empty bag. You will find a busy, well-run workshop. The cell is filled with a jelly-like fluid called the cytosol. Floating in it are the organelles, which means "little organs." Each one is a department with its own job.
Splitting up the work lets the cell run many chemical jobs at once without them getting in each other's way. It is like the walls that separate the rooms of a factory. Many organelles have their own membrane that seals off what happens inside. A few, like ribosomes, do not. To learn the cell, you learn who does what.
The control room and the assembly line
The largest organelle is usually the nucleus, the cell's control center. It is wrapped in a double membrane called the nuclear envelope. The envelope has small holes, or pores, that let messages in and out. The nucleus holds the cell's DNA. DNA is the master set of instructions for making every protein.
Most of the time, DNA is spread out as a loose tangle called chromatin. When the cell gets ready to divide, the DNA packs tightly into chromosomes that you can see. Inside the nucleus is a dark spot called the nucleolus. This is where ribosomes are built.
Ribosomes are the machines that build proteins. Some float free in the cytosol. Others dot the rough endoplasmic reticulum (rough ER). The rough ER is a folded network of membrane. It makes and packs proteins that will be sent out of the cell or placed in the membrane. Next to it is the smooth ER, which has no ribosomes. The smooth ER makes fats, breaks down harmful substances, and stores calcium.
Proteins and fats then move to the Golgi apparatus. The Golgi is the cell's shipping center. It changes, sorts, and packs them into small bubbles called vesicles. Each vesicle is sent to where it is needed.
Power, cleanup, and shape
All this work needs energy. That energy comes from the mitochondria, the "powerhouses" of the cell. Here food and oxygen are turned into ATP, the energy the cell can spend. Cells that work hard, like muscle and liver cells, are packed with mitochondria.
Two organelles handle cleanup. Lysosomes are sacs full of digestive enzymes. They break down worn-out parts, germs, and junk. Peroxisomes make harmful by-products safe.
The cytoskeleton holds the whole cell together. It is a frame of protein threads. It gives the cell its shape, holds organelles in place, and helps things move. The centrosome, with its pair of centrioles, organizes this frame. It also builds the fibers that pull chromosomes apart when the cell divides.
| Organelle | Job | Memory hook |
|---|---|---|
| Nucleus | Stores DNA; runs the cell | The control room or library |
| Nucleolus | Builds ribosomes | Ribosome factory inside the nucleus |
| Ribosome | Builds proteins by reading mRNA | The 3-D printer |
| Rough ER | Makes and packs proteins (has ribosomes) | Protein assembly line |
| Smooth ER | Makes fats, breaks down harmful substances, stores Ca²⁺ | Fat and cleanup lab |
| Golgi apparatus | Changes, sorts, and ships proteins in vesicles | The post office |
| Mitochondrion | Makes ATP from food + O₂ | The powerhouse |
| Lysosome | Breaks down junk and worn-out parts | The recycling and wrecking crew |
| Cytoskeleton | Shape, support, moving things, movement | The inside frame |
Tap an organelle to light it up, or press Tour to walk the whole factory floor.
- Organelles are departments that float in the cytosol. Their membranes keep their jobs apart.
- The nucleus stores DNA as chromatin, which packs into chromosomes before division. The nucleolus builds ribosomes.
- The protein path is ribosomes → rough ER → Golgi → vesicles. The smooth ER makes fats and stores calcium.
- Mitochondria make ATP. Lysosomes break down junk. The cytoskeleton gives shape and moves cargo.
Section 4From gene to protein
The recipe and the problem
Your DNA is like a recipe book. Each gene is one recipe for one protein. But there is a problem. The DNA is locked inside the nucleus. Proteins are built by ribosomes out in the cytoplasm, the space outside the nucleus. The master book can never leave the library.
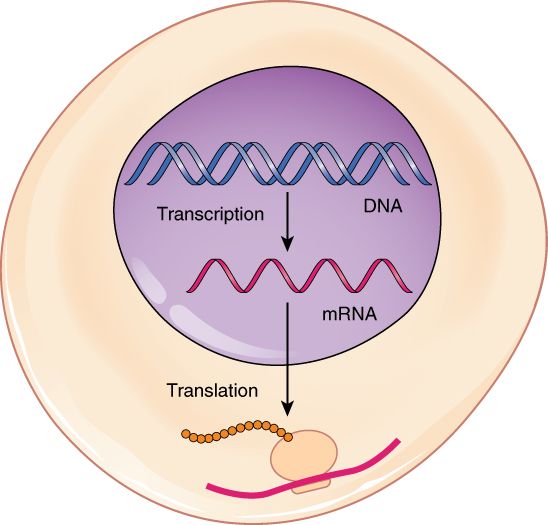
The fix is to make a throwaway copy of just the one recipe you need. That copy is carried out to the workshop. This is the heart of protein synthesis, and it takes two steps. Transcription copies the gene. Translation reads the copy and builds the protein. This flow of information, from DNA to RNA to protein, is so basic that it is called the central dogma of biology.
Transcription: copying the gene
Transcription happens inside the nucleus. An enzyme called RNA polymerase unzips the DNA at the gene it needs. It reads one strand and builds a matching strand of messenger RNA (mRNA). RNA is a lot like DNA. But it has only one strand, and some of its parts are a little different. For example, it uses the base uracil (U) in every place where DNA would use thymine.
The matching rules are strict. DNA's C pairs with G. DNA's A calls for a U in the RNA. The finished mRNA is a copy of the gene you can carry around. It is the working copy. It slips out through a pore in the nucleus and goes off to find a ribosome.
Translation: reading the copy
Translation happens at a ribosome. Here the mRNA is read three bases at a time. Each group of three is called a codon. Each codon stands for one amino acid, a building block of proteins.
The amino acids are brought in by transfer RNA (tRNA). Each tRNA carries one kind of amino acid. It also has a three-base anticodon that matches one codon. The ribosome moves along the mRNA one codon at a time. The tRNAs line up in order, and the ribosome links their amino acids into a growing chain.
When the ribosome reaches a "stop" codon, it lets the finished chain go. The chain folds into its working shape and becomes a protein. The whole path is DNA → mRNA → protein. It turns a stored instruction into a real molecule that does a job.
| Step | Where | What happens |
|---|---|---|
| Transcription | Nucleus | RNA polymerase copies a gene from DNA into mRNA |
| mRNA leaves | Nuclear pore | The working copy moves out to the cytoplasm |
| Translation | Ribosome | Codons are read three bases at a time. tRNA anticodons bring the matching amino acids. |
| Product | Cytoplasm or ER | Amino acids link into a chain that folds into a working protein |
Step through the whole trip from gene to protein below.
- A gene is the recipe for one protein. The central dogma is DNA → RNA → protein.
- Transcription happens in the nucleus. It copies a gene into mRNA. RNA uses uracil in place of thymine.
- Translation happens at a ribosome. It reads mRNA in three-base codons. tRNA anticodons bring the matching amino acids.
- A change in one base can change one amino acid and break the protein, as in sickle cell disease.
Section 5The cell cycle & mitosis
Living, then dividing
Your body makes billions of new cells every day. It needs them to grow, to heal a cut, and to replace skin and blood cells that wear out. Every new cell comes from an old cell that grew and split in two. The steps a cell follows to do this are called the cell cycle.
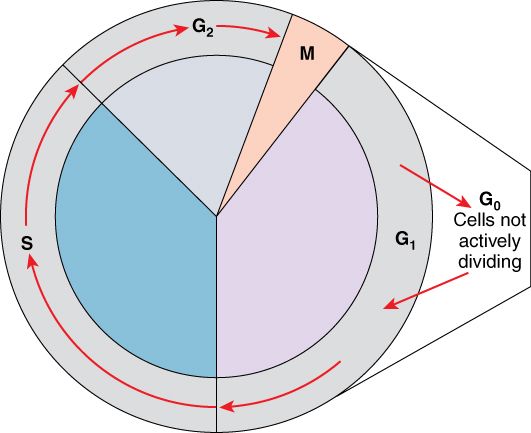
The cell cycle has two very unequal parts. The long part is interphase. This is the cell's normal working life. It grows, does its job, and quietly gets ready to divide. The short, dramatic ending is mitosis, when the nucleus actually splits. A cell spends most of its life in interphase. Mitosis is over quickly.
Interphase: grow, copy, get ready
Interphase has three stages. In G₁ (first gap), the cell grows, makes proteins, and does its normal work. In S phase (synthesis), the cell copies all of its DNA. That way, each new cell will get a full set. This is the most important step in getting ready to divide. In G₂ (second gap), the cell finishes growing. It builds the organelles it will need and checks the copied DNA for mistakes.
Only after all this does the cell commit to dividing. Checkpoints guard each step. They are quality-control stops, like a safety check before a plane takes off. At each one, the cell makes sure everything is in order before it moves on.
Mitosis: splitting the nucleus, then the cell
Mitosis splits the copied DNA evenly into two nuclei. It has four stages. You can remember them as PMAT.
In prophase, the copied chromatin packs into chromosomes you can see, and spindle fibers start to form. In metaphase, the chromosomes line up single file across the middle of the cell. In anaphase, the spindle fibers pull the two copies of each chromosome apart, toward opposite ends. In telophase, a new nuclear envelope forms around each of the two sets.
Mitosis splits the nucleus. A separate step, cytokinesis, pinches the rest of the cell in two. The result is two genetically identical daughter cells. Each has the same DNA, and each is ready to start its own interphase.
| Phase | Part of cycle | What happens |
|---|---|---|
| G₁ | Interphase | Cell grows and does its normal work |
| S | Interphase | All the DNA is copied |
| G₂ | Interphase | Last growth; DNA is checked for mistakes |
| Prophase | Mitosis | Chromatin packs into chromosomes; spindle forms |
| Metaphase | Mitosis | Chromosomes line up across the middle |
| Anaphase | Mitosis | Chromosome copies are pulled to opposite ends |
| Telophase | Mitosis | Two new nuclei form; cytokinesis splits the cell |
Step through interphase and the four phases of mitosis below.
- The cell cycle is a long interphase (G₁ → S → G₂) plus a short mitosis. DNA is copied in S phase.
- The order of mitosis is PMAT: prophase, metaphase, anaphase, telophase. Then cytokinesis splits the rest of the cell.
- The result is two genetically identical daughter cells.
- Checkpoints, guarded by genes like p53, stop damaged cells from dividing. When they fail, cancer can follow.
Section 6Osmosis & tonicity
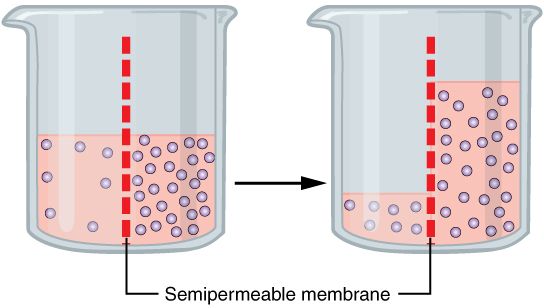
Water chases salt
We saved the kind of transport that matters most in hospitals for last. Osmosis is the movement of water across a selectively permeable membrane. It follows one simple rule. Water moves toward the side with more dissolved particles. We call that side the one with more solute, or the "saltier" side.
The membrane keeps the solute from moving across to even things out. So water moves instead. It flows toward the saltier side until the two sides are balanced. A cell's membrane lets water pass freely but holds many solutes in place. So the amount of solute outside the cell decides which way water flows. That decides whether the cell gains or loses water.
Tonicity: three fluids, three results
Tonicity tells you how a fluid will change a cell's water balance. It compares the solute outside the cell to the solute inside. There are three cases.
An isotonic fluid has the same amount of solute as the inside of the cell. Water moves in and out equally, so the cell stays the same. This is its normal, healthy state.
A hypotonic fluid is more watery than the cell, with less solute outside. So water rushes in. The cell swells. If enough water gets in, the cell can burst. This is called lysis. In red blood cells it is called hemolysis.
A hypertonic fluid is saltier than the cell, with more solute outside. So water is pulled out. The cell shrivels. This shrinking is called crenation. Here is the trick to keep them straight. Water always follows the solute. Find the saltier side, and water goes there.
| Fluid | Outside vs. cell | Water moves | What happens to the cell |
|---|---|---|---|
| Isotonic | Same amount of solute | In = out (no overall change) | Stays normal |
| Hypotonic | Less solute outside (watery) | Into the cell | Swells and may burst (lysis) |
| Hypertonic | More solute outside (salty) | Out of the cell | Shrivels (crenation) |
Drop a cell into each fluid below and see what happens to it.
- Osmosis is water moving across a membrane toward the side with more solute.
- Isotonic → no overall change. Hypotonic → water goes in, and the cell swells or bursts (lysis). Hypertonic → water goes out, and the cell shrivels (crenation).
- Water always follows the solute. Find the saltier side.
- IV fluids use this rule. 0.9% normal saline is isotonic. Never give pure water into a vein.
The chapter in one breath
- Every cell is wrapped in a selectively permeable plasma membrane. The fluid mosaic model describes it as a fluid phospholipid bilayer with proteins, cholesterol, and sugars set into it.
- Things cross by passive transport or active transport. Passive means downhill and free: diffusion, facilitated diffusion, and osmosis. Active means uphill and costs energy: the Na⁺/K⁺ pump and bulk transport.
- Inside, organelles share the work. The nucleus stores DNA. Ribosomes → ER → Golgi build and ship proteins. Mitochondria make ATP. Lysosomes clean up.
- Protein synthesis flows from DNA → RNA → protein. Transcription copies a gene into mRNA in the nucleus. Translation reads its codons at a ribosome to build the protein.
- The cell cycle is a long interphase (G₁/S/G₂, with DNA copied in S). Then comes a short mitosis (PMAT) and cytokinesis. The result is two identical daughter cells. Broken checkpoints lead to cancer.
- Osmosis moves water toward the saltier side. Tonicity decides what happens to a cell. Isotonic keeps it normal. Hypotonic makes it swell or burst. Hypertonic makes it shrivel. This is exactly why IV fluids are chosen with care.
ReferenceWords worth knowing
Here are the key words from this chapter. Skim them now, or come back any time a word trips you up.
- Active transport
- Moving a substance up its concentration gradient, from low to high. It needs energy, such as ATP.
- Codon
- A group of three mRNA bases. It stands for one amino acid during translation.
- Crenation
- The shriveling of a cell that loses water in a hypertonic fluid.
- Cytokinesis
- The splitting of the cytoplasm after mitosis. It turns one cell into two.
- Cytoskeleton
- The inside frame of protein threads. It gives a cell shape and support and moves things around.
- Diffusion
- The free spreading of molecules from where there are many to where there are few, until they are evenly mixed.
- Fluid mosaic model
- The picture of the cell membrane as a fluid phospholipid bilayer. Proteins, cholesterol, and sugars sit in it like tiles.
- Golgi apparatus
- The organelle that changes, sorts, and packs proteins and fats into vesicles for delivery.
- Hypertonic
- A fluid with more solute than the cell. Water leaves the cell, and the cell shrivels.
- Hypotonic
- A fluid with less solute than the cell. Water enters the cell, and the cell swells or bursts.
- Interphase
- The long part of the cell cycle (G₁, S, G₂). The cell grows, copies its DNA, and gets ready to divide.
- Isotonic
- A fluid with the same amount of solute as the cell. Water does not move in or out overall, so the cell keeps its normal shape.
- Lysosome
- A sac of digestive enzymes wrapped in membrane. It breaks down junk, worn-out organelles, and things the cell takes in.
- Mitochondrion
- The organelle that makes ATP from food and oxygen. It is the cell's powerhouse.
- Mitosis
- The splitting of the nucleus into two nuclei with identical DNA. It goes through prophase, metaphase, anaphase, and telophase.
- Nucleus
- The control center of the cell, wrapped in membrane. It stores the cell's DNA and directs what the cell does.
- Osmosis
- The diffusion of water across a selectively permeable membrane. Water moves toward the side with more solute.
- Passive transport
- Moving a substance down its concentration gradient. It needs no energy from the cell.
- Phospholipid bilayer
- The double layer of amphipathic phospholipids that forms the core of the membrane. The water-loving heads face out, and the water-fearing tails face in.
- Sodium–potassium pump
- A primary active transport protein. For each ATP, it pushes 3 Na⁺ out and brings 2 K⁺ in. This keeps the cell's ion gradients in place.
- Transcription
- Copying a gene from DNA into messenger RNA. It happens inside the nucleus.
- Translation
- Reading mRNA codons at a ribosome to join amino acids into a protein.
Check yourself
The Tissue Level of Organization
In the last chapter we zoomed in on a single cell. Now we take one step back up the ladder. Cells rarely work alone. They gather into tissues, which are teams of similar cells that share a job. Together, they do things no single cell could do. The amazing part is how few kinds there are. Your whole body, and every organ in it, is built from just four primary tissues. This chapter introduces all four. You will see how each looks under the microscope, where it lives, and what it does. The chapter ends with a story every tissue must tell sooner or later: how it heals when it gets hurt.
By the end of this chapter you can
- Define tissue. Name the four primary tissue types and give the general job of each.
- List the features all epithelial tissue shares. Name any epithelium by its layering and cell shape.
- Describe the basic plan of all connective tissue: cells spread out in an extracellular matrix of fibers and ground substance. Name its main types.
- Tell the three muscle tissues apart by stripes, by whether you control them, and by cell shape.
- Draw a neuron and label its parts. Show how nervous tissue carries a signal in one direction.
- List the four stages of tissue repair. Compare regeneration with fibrosis (scarring).
- Explain how the four tissues join to build organs and body membranes.
Section 1The four tissue types
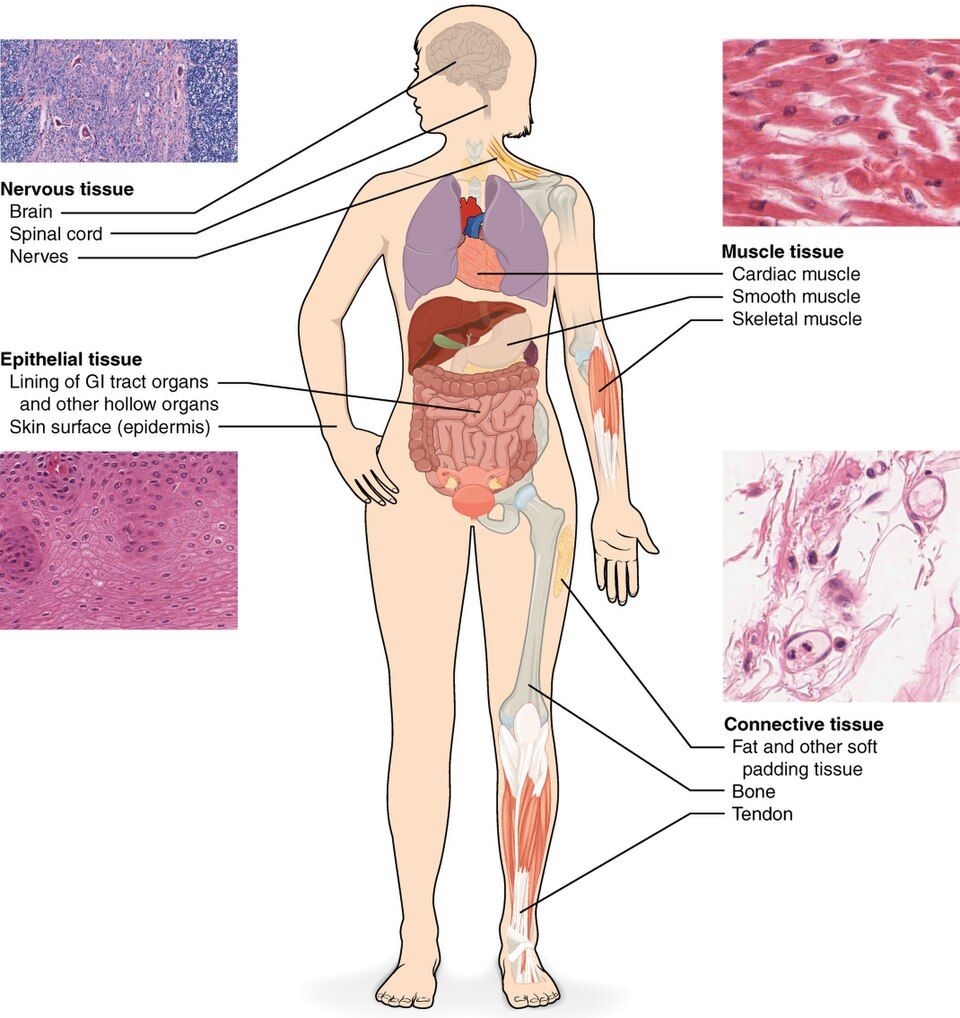
A team of cells
A tissue is a group of similar cells that work together to do a shared job. That is the whole definition. But the word "together" matters a lot. The cells in a tissue are not just neighbors that look alike. They work as a team. They are held in place by links between them, or by material they make around themselves. And each tissue is built for one kind of job.
The study of tissues under the microscope is called histology. It is really anatomy at very high zoom. Instead of asking what an organ looks like to the eye, we ask what it is made of.
Four families do all the work
Here is what makes this subject easy to learn. No matter how complex an organ looks, it is built from only four primary tissue types. Learn these four, and you have the words to describe any part of the body. Each family meets a different basic need. A body must cover and line its surfaces. It must bind and support its parts. It must move. And it must communicate.
| Tissue | What it does | Where you find it |
|---|---|---|
| Epithelial | Covers surfaces, lines spaces, and forms glands. It protects, absorbs, and releases substances. | Skin surface, gut lining, kidney tubes, gland cells |
| Connective | Binds, supports, protects, stores, and carries things. It is the body's packing material. | Bone, fat, tendon, cartilage, blood |
| Muscle | Squeezes (contracts) to make movement and force. It also makes heat. | Skeletal muscles, heart wall, walls of hollow organs |
| Nervous | Senses, sorts out, and quickly sends electrical signals | Brain, spinal cord, nerves in the rest of the body |
Notice how different the four are in how much room the cells give each other. Epithelial cells are packed so tightly that there is almost no space between them. That is what makes them a good barrier. Connective tissue is the opposite. Its cells are few and far apart. They float in a sea of non-living material that they make. This one contrast is one of the fastest ways to tell the first two tissues apart on a slide. Look for crowded cells or cells spread out in a matrix.
From tissues to organs and membranes
An organ is two or more tissue types layered together. The whole organ can do something none of its tissues could do alone. The stomach is the clearest example. It has an epithelial lining that makes acid and mucus. It has a connective tissue layer that carries its blood vessels and nerves. It has smooth muscle that churns food. And it has nervous tissue that times the churning. That is four tissues in one organ.
The simplest of these teams is a body membrane. This is a thin sheet that covers or lines a surface. There are only four kinds.
The cutaneous membrane is the skin itself. It is stratified squamous epithelium on top of dense irregular connective tissue. It is the only membrane that is dry. A mucous membrane lines every space that opens to the outside. This includes the airway, the gut, and the urinary and reproductive tracts. It pairs an epithelium with a loose connective layer under it, called the lamina propria.
A serous membrane lines the closed body spaces in the front of the trunk and wraps the organs inside them. Examples are the pleura, pericardium, and peritoneum. It joins a simple squamous epithelium called mesothelium to a thin areolar layer. It makes a watery fluid so organs can slide past each other. The synovial membrane is the odd one out. It lines the spaces inside joints. It is made of connective tissue only, with no epithelium at all.
Meet all four tissues side by side in the interactive below.
- A tissue is a group of similar cells doing a shared job. The study of tissues is histology.
- The body has four primary tissues: epithelial (cover and line), connective (bind and support), muscle (move), and nervous (communicate).
- Epithelial cells are tightly packed. Connective cells are spread out in a matrix. This is a quick way to tell them apart.
- Tissues layer together to build organs and the four body membranes. These are cutaneous (skin, dry), mucous (lines spaces open to the outside), serous (lines closed spaces in the front of the trunk), and synovial (joint spaces, connective tissue only).
Section 2Naming an epithelium
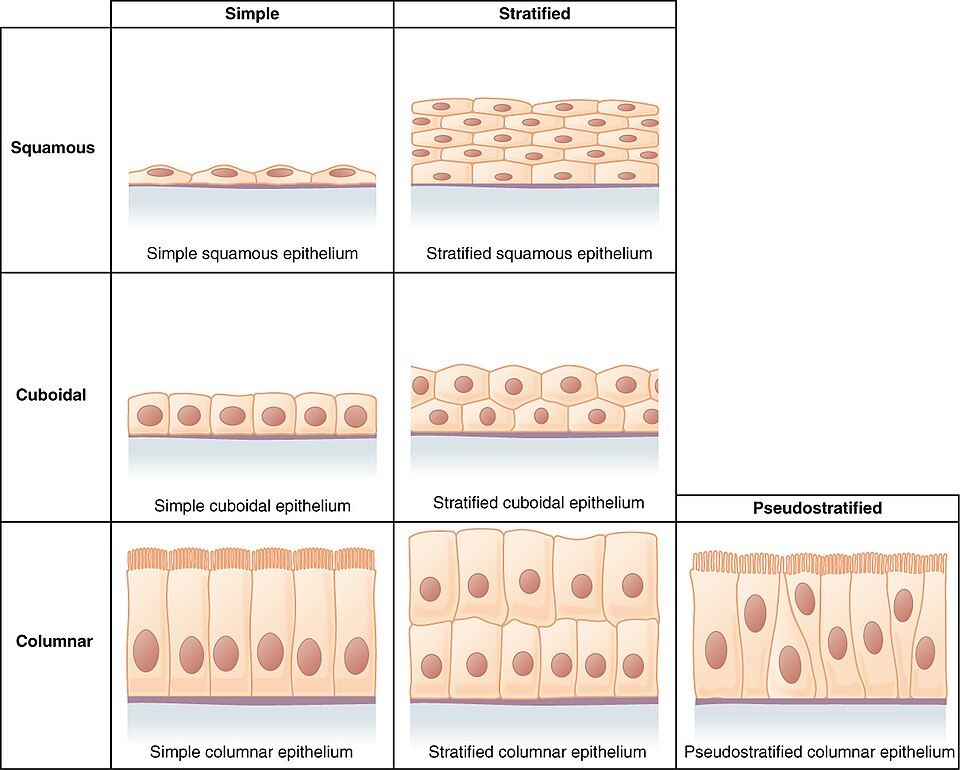
What every epithelium has in common
Epithelial tissue covers every open surface of the body. It lines every space, tube, and duct. Think of your outer skin, the inside of your gut, your airways, and your blood vessels. Because it sits at every border, it has a set of features built for that role.
Its cells are tightly packed, with very little material between them. So almost nothing gets across without going through a cell. Every epithelium has polarity, which means it has a top and a bottom. The apical surface is the top. It faces the open space and often has tiny fingers (microvilli) or hairs (cilia). The basal surface is the bottom. It is anchored to a thin basement membrane that glues it to the connective tissue below.
Epithelium is avascular. This means it has no blood vessels of its own. It gets its food by diffusion from the tissue underneath. Yet it has plenty of nerves. It also regenerates, or regrows, quickly. It has to, because being a surface means cells are always wearing away.
The two-word naming rule
Here is the big reward of this section. Every epithelium is named with the same simple formula. Once you learn the rule, you can name a tissue you have never seen. The name has two parts. First comes the number of layers. Then comes the shape of the cells at the surface.
- Layers. One layer of cells is simple. Two or more stacked layers is stratified.
- Shape. Flat cells, like fish scales, are squamous. Cells shaped like cubes are cuboidal. Tall cells shaped like columns are columnar.
Snap the two halves together and you have the name. One layer of flat cells is simple squamous. Many stacked layers of flat cells make stratified squamous. One row of tall cells is simple columnar.
The build even tells you the job. Thin simple epithelia are best where things must cross quickly. Simple squamous lines the air sacs of the lungs and the walls of capillaries. Oxygen and nutrients slip across it in an instant. Thick stratified epithelia are built for protection. Stratified squamous forms the surface of your skin and lines your mouth and esophagus. You can afford to lose and rebuild these layers.
| Epithelium | Build | Best-known job and place |
|---|---|---|
| Simple squamous | One layer of flat cells | Fast diffusion: lung air sacs, lining of capillaries and vessels (endothelium) |
| Simple cuboidal | One layer of cube cells | Releasing and absorbing: kidney tubes, gland ducts |
| Simple columnar | One layer of tall cells | Absorbing and releasing: lining of the stomach and intestines |
| Stratified squamous | Many stacked flat layers | Protection from rubbing and scraping: skin surface, mouth, esophagus, vagina |
| Pseudostratified columnar | One layer that looks layered | Lining of the airways, with cilia that sweep mucus upward |
| Transitional | Stretchy layers that change shape | Bladder and ureters: stretches as they fill |
Two rows in that table are the famous exceptions. Pseudostratified columnar epithelium is really just one layer. Every cell touches the basement membrane. But the nuclei sit at different heights, so it looks stacked. That is why it is called "pseudo" (false) stratified. Transitional epithelium is the shape-shifter of the urinary tract. Its cells slide over each other and flatten as the bladder fills. Then they bunch back up as it empties.
Build an epithelium's name box by box and watch it appear in the interactive.
- Epithelia are tightly packed and polar (apical top, basal bottom). They sit on a basement membrane, are avascular, and regenerate fast.
- Name any epithelium by layers (simple = one, stratified = many) + cell shape (squamous, cuboidal, columnar).
- Simple epithelia are for absorbing, releasing, and diffusion. Stratified epithelia are for protection. Pseudostratified and transitional are the special cases.
Section 3Connective tissue
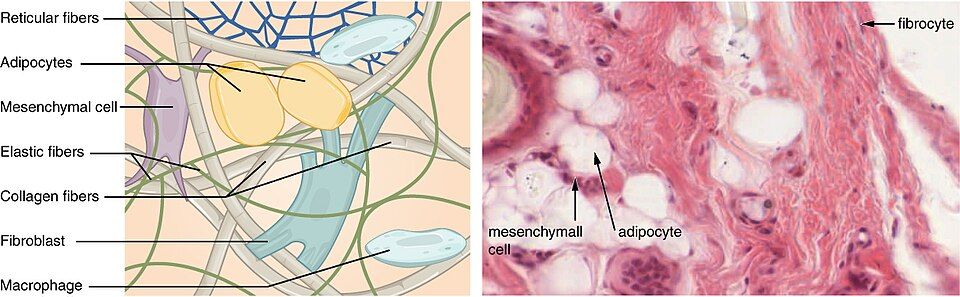
One recipe, many results
Connective tissue is the most common tissue in the body. It is also the most varied. At first it can seem like a random mix. Bone, fat, tendon, cartilage, and even blood all belong to it. What links them is one shared plan.
In epithelium, the cells are everything. Connective tissue is different. It is mostly extracellular matrix. This is non-living material that the cells make and then sit inside. The cells are few and spread far apart. The feel of the tissue comes almost entirely from the matrix around them.
This is the key idea of the whole section: change the matrix and you change the tissue. Make the matrix a firm, rubbery gel, and you get cartilage. Harden it with calcium salts, and you get bone. Make it liquid, and you get blood. Adipose tissue, or fat, is the useful exception. Its cells store fat inside themselves. Each cell swells up with one big droplet. So the matrix gets squeezed down to almost nothing. Fill the cells instead of the matrix, and you get fat.
The matrix: fibers and ground substance
The extracellular matrix always has two parts. The first part is protein fibers. There are three kinds. Collagen fibers are strong, like ropes, and resist pulling. Elastic fibers stretch and snap back into shape, like rubber bands. Reticular fibers are thin and form a fine mesh that holds things up.
The second part is the ground substance. It fills the space between the fibers and cells. Depending on the tissue, it can be watery, like jelly, or rock hard.
The cells often come in two kinds, named by a simple rule. A name that ends in -blast is a young, busy builder cell that makes matrix. Examples are the fibroblast, osteoblast, and chondroblast. A name that ends in -cyte is a grown-up cell that keeps the matrix in good shape. Examples are the fibrocyte, osteocyte, and chondrocyte.
| Connective tissue | Matrix | Job and place |
|---|---|---|
| Loose (areolar) | Soft and gel-like, with loosely woven fibers | All-purpose packing and cushion; found under epithelia everywhere |
| Adipose (fat) | Cells so full of fat that there is little matrix | Stores energy, holds in heat, pads organs |
| Dense regular | Tightly packed collagen, all lined up in the same direction | Strong pull in one direction: tendons and ligaments |
| Cartilage | Firm, rubbery gel | Bendable support: nose, ears, joint surfaces, discs in the spine |
| Bone (osseous) | Collagen hardened with calcium salts | Stiff support and protection; stores minerals |
| Blood | Liquid matrix (plasma) | Carries cells, gases, nutrients, and wastes |
Read that table from top to bottom. You can watch one idea stretch across every level of stiffness. It goes from a soft cushion, to a fat pad, to a tough cable, to a rubbery shock absorber, to solid mineral, and all the way to a flowing liquid. It is the same recipe with very different results. What changes is what the cells put into the matrix.
Rebuild the matrix in the interactive and watch one tissue turn into the next.
- All connective tissue follows one recipe: spread-out cells in an extracellular matrix made of fibers + ground substance.
- There are three fiber types: collagen (strength), elastic (stretch), and reticular (mesh support). -blast cells build the matrix. -cyte cells keep it up.
- Changing the matrix gives the whole family: loose, adipose, dense, cartilage, bone, and blood.
Section 4Muscle tissue
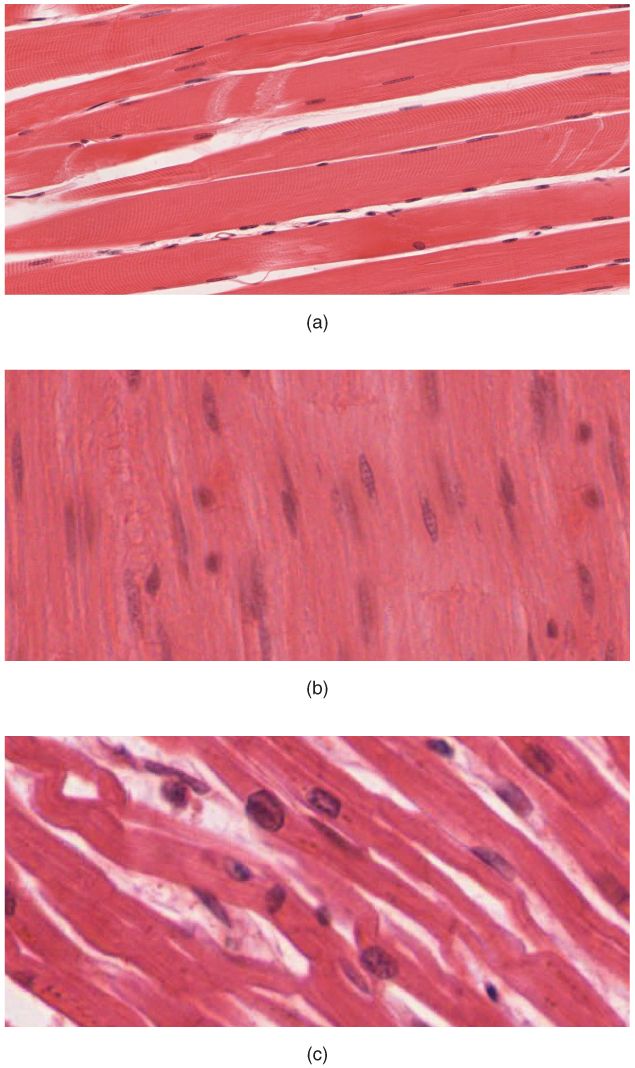
Cells built to shorten
Muscle tissue has one skill that no other tissue has. It can contract. That means it can actively shorten to pull on something. Its cells are packed with two protein threads, actin and myosin. These threads slide past each other to shorten the cell. Everything about a muscle cell's shape helps with that pull.
Sometimes these threads line up in neat, repeating rows. Then they catch the light in bands, and the tissue looks striated, or striped. When the threads are less orderly, the tissue looks smooth. Contraction does more than move the body. It also makes much of your body heat. That is why shivering warms you up.
The three muscle tissues
There are exactly three muscle tissues. You can tell them apart with three questions. Is it striped? Can you control it on purpose? What shape are its cells?
Skeletal muscle is the meat that moves your bones. It is striated and voluntary, which means you control it on purpose. It is made of long, tube-shaped fibers, each with many nuclei.
Cardiac muscle is found only in the wall of the heart. It is striated but involuntary, so it works without you thinking about it. Its short, branching cells are joined end to end by intercalated discs. These let the whole heart squeeze as one team.
Smooth muscle lines the walls of hollow organs like the gut, blood vessels, and bladder. It is non-striated and involuntary. It is made of small, tapered cells shaped like spindles, thick in the middle and pointed at the ends. They squeeze those organs slowly and without tiring.
| Feature | Skeletal | Cardiac | Smooth |
|---|---|---|---|
| Striations (stripes) | Striated | Striated | Non-striated |
| Control | Voluntary | Involuntary | Involuntary |
| Cell shape | Long tubes | Short, branched | Tapered spindles |
| Nuclei per cell | Many | One (or two) | One |
| Where | Attached to bones | Heart wall only | Walls of hollow organs |
Here is a handy shortcut. The two striated muscles, skeletal and cardiac, are the fast, strong ones. The one smooth muscle is the slow, steady one. And only one of the three, skeletal, does what you tell it. The heart and the gut run on their own.
Watch each of the three muscles contract in the interactive below.
- Muscle tissue contracts as actin and myosin threads slide. Neat rows of threads make it look striated.
- Skeletal is striated and voluntary, with long fibers that have many nuclei. Cardiac is striated and involuntary, with branched cells joined by intercalated discs. Smooth is non-striated and involuntary, with spindle cells.
- Tell them apart with three questions: striped? voluntary? cell shape?
Section 5Nervous tissue
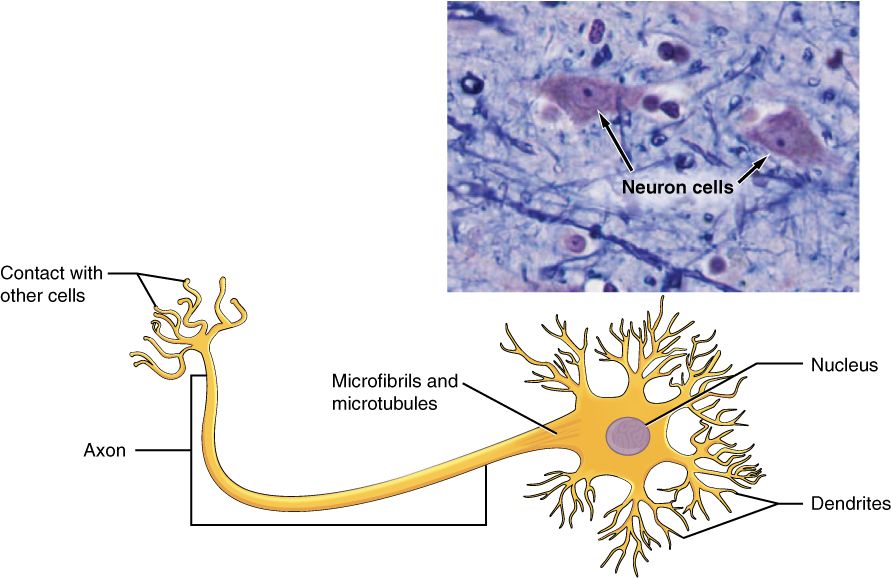
The neuron: a cell shaped like a message
Nervous tissue senses changes, makes decisions, and sends electrical signals. It does this faster than any other tissue in the body. Its star cell is the neuron, or nerve cell. The neuron's odd shape is really a map of how a signal flows through it. The signal goes in one end and out the other.
Signals arrive at the bushy dendrites. These are short, branching arms that pick up messages from other cells. The signals flow into the cell body (or soma). The cell body holds the nucleus and keeps the cell running. If the incoming signal is strong enough, the neuron fires an electrical pulse. The pulse races away down the axon, one long fiber that carries the message to the next cell.
Many axons are wrapped in a fatty myelin sheath. It works like the plastic coating on a wire. It lets the signal jump along much faster. The traffic only goes one way: dendrite → cell body → axon, every time.
| Part | What it is | Its job in the signal |
|---|---|---|
| Dendrites | Short, branching arms | Receive incoming signals from other cells |
| Cell body (soma) | Holds the nucleus and organelles | Integrates, or adds up, the input; keeps the cell alive |
| Axon | One long fiber | Sends the electrical pulse toward the next cell |
| Myelin sheath | Fatty wrap on the axon, like the coating on a wire | Speeds the signal along the axon |
| Axon terminals | Branched tips of the axon | Pass the signal to the next cell at a synapse, the meeting point |
Neuroglia: the support crew
Neurons get the fame. But there are at least as many neuroglia, also called glial cells. These are the support cells of nervous tissue. Careful counts show about one glial cell for each neuron across the whole brain. Glia outnumber neurons in the cerebral cortex, the brain's wrinkled outer layer. Neurons far outnumber glia in the cerebellum, at the back of the brain.
Glia do not carry the signal themselves. Instead, they feed neurons and wrap their axons in myelin. They hold the tissue together and defend it from germs. Two features define what nervous tissue can do. Excitability is the ability to respond to a trigger by making an electrical signal. Conductivity is the ability to carry that signal from one place to another. Together, they make this tissue the body's high-speed communication network.
Tap a part of the neuron and watch a signal fire in the interactive.
- The neuron carries a one-way signal. Dendrites receive → the cell body adds it up → the axon sends it on.
- The fatty myelin sheath wraps the axon and speeds the signal. Neuroglia support and protect neurons.
- Nervous tissue is defined by excitability and conductivity. Grown-up neurons rarely divide, so damage to the brain and spinal cord (the CNS) often heals poorly.
Section 6Tissue repair
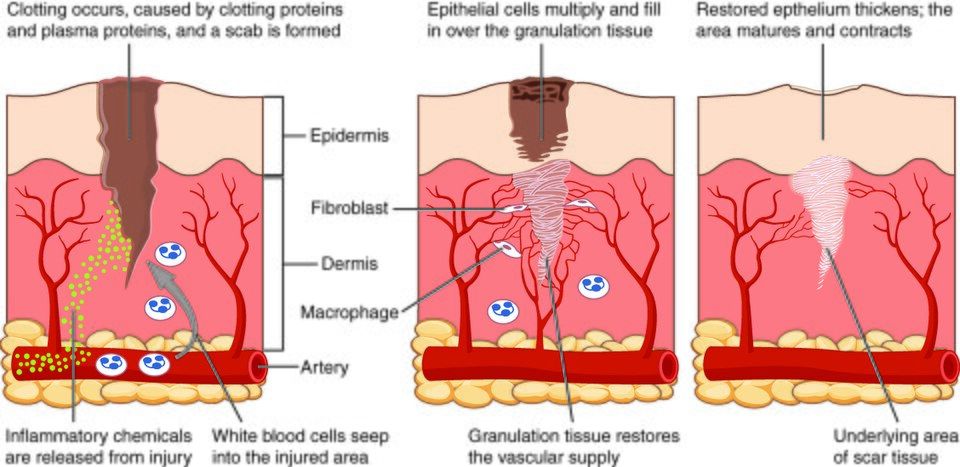
Two ways to fix a wound
When a tissue is hurt, the body can fix it in one of two ways. The better result is regeneration. The damaged cells are replaced with new cells of the very same type. The tissue goes back to normal, as if the injury never happened.
The backup plan is fibrosis. Here the gap is filled with thick, tough scar tissue instead of the original cells. Scar tissue plugs the hole and makes the area strong again. But it cannot do the original job. Scar in the heart cannot beat. Scar in the skin has no hair or sweat glands.
Which path a tissue takes depends mostly on how well its cells can divide. Tissues whose cells divide fast, like skin and gut, regenerate very well. Tissues whose cells barely divide, like heart muscle and neurons, tend to scar.
The healing playbook
For any tissue, the body runs the same four-step repair plan, in order. Think of it as a building project on a rush schedule. First stop the flooding. Then clear the site. Then rebuild the frame. Then finish the surfaces.
| Stage | What happens | Purpose |
|---|---|---|
| 1. Hemostasis | Blood clots seal the broken vessels, and a scab forms | Stop the bleeding |
| 2. Inflammation | Vessels widen, and immune cells arrive to clear away junk and germs | Clean up the wound |
| 3. Proliferation | New tiny blood vessels and collagen build pink granulation tissue. Epithelium spreads across the top. | Rebuild the tissue |
| 4. Remodeling | Collagen is rearranged and made stronger. The scar matures and shrinks. | Make the area strong again over weeks to months |
The signs you can see in stage two are redness, heat, swelling, and pain. These are the classic marks of inflammation. They feel like the problem, but they are really the body doing its job. The vessels widen and leak. That causes the redness and swelling. It also brings in the clotting factors, germ fighters, and cleanup crews the wound needs. Inflammation is not the injury. It is the repair getting started.
Step through a healing wound from clot to scar in the interactive below.
- Healing happens by regeneration (the same cells come back) or fibrosis (scar tissue fills the gap). Which one depends on how well the cells divide.
- The repair steps always go hemostasis → inflammation → proliferation → remodeling.
- Inflammation (redness, heat, swelling, pain) is the repair at work, not the injury itself.
The chapter in one breath
- A tissue is a group of similar cells that share a job. The whole body is built from just four of them.
- Epithelial tissue covers and lines. It is tightly packed, polar, and avascular. It is named by layers (simple or stratified) + cell shape (squamous, cuboidal, or columnar).
- Connective tissue binds and supports. Its cells are spread out in an extracellular matrix of fibers and ground substance. Change the matrix and you get cartilage, bone, or blood. Adipose is the exception. It fills its cells with fat instead.
- Muscle tissue contracts. Skeletal is striated and voluntary. Cardiac is striated and involuntary, with intercalated discs. Smooth is non-striated and involuntary.
- Nervous tissue communicates. The neuron carries a one-way signal from dendrites → cell body → axon. Neuroglia support it.
- Hurt tissue heals by regeneration or fibrosis. It always goes through hemostasis → inflammation → proliferation → remodeling.
- How well a tissue heals comes down mostly to its blood supply and how easily its cells divide.
ReferenceWords worth knowing
Here are the key words from this chapter. Skim them now, or come back any time a word trips you up.
- Apical surface
- The free top surface of an epithelial cell. It faces the open space, cavity, or lumen, and often has microvilli or cilia.
- Areolar tissue
- The most common loose connective tissue. It is soft, all-purpose packing that lies under epithelia and cushions organs.
- Axon
- The one long fiber of a neuron. It carries the electrical signal away from the cell body toward the next cell.
- Basement membrane
- A thin layer that anchors the bottom (basal) surface of an epithelium to the connective tissue below it.
- Cardiac muscle
- Striated, involuntary muscle found only in the heart wall. Its branched cells are joined by intercalated discs, so the heart squeezes as one.
- Collagen fiber
- The strong, rope-like protein fiber of connective tissue. It resists pulling.
- Connective tissue
- The varied tissue that binds, supports, protects, and carries things. It is made of spread-out cells in an extracellular matrix.
- Dendrite
- A short, branching arm of a neuron. It picks up signals from other cells.
- Epithelial tissue
- Tightly packed tissue that covers body surfaces, lines spaces and tubes, and forms glands.
- Extracellular matrix
- The non-living material, fibers plus ground substance, that connective tissue cells make and sit inside.
- Fibrosis
- Repair by laying down tough scar tissue in place of the original cells. It brings back strength but not full function.
- Ground substance
- The part of the extracellular matrix that fills the space between cells and fibers. It can be watery, like jelly, or solid.
- Histology
- The study of tissues under the microscope. It is anatomy at high zoom.
- Muscle tissue
- Tissue built to contract using actin and myosin threads. It makes movement, force, and heat.
- Nervous tissue
- Tissue built to sense, sort out, and quickly send electrical signals. It is made of neurons and neuroglia.
- Neuroglia
- The support cells of nervous tissue. They feed, wrap, hold together, and protect neurons.
- Neuron
- The signal-carrying cell of nervous tissue. It has dendrites, a cell body, and an axon.
- Regeneration
- Repair in which damaged cells are replaced by new cells of the same type. Normal structure and function come back.
- Simple epithelium
- An epithelium one cell layer thick. It is suited to diffusion, absorbing, and releasing substances.
- Squamous
- Describes flat, scale-like epithelial cells. They are ideal where substances must cross quickly.
- Stratified epithelium
- An epithelium with two or more stacked layers of cells. It is built to protect against rubbing and scraping.
- Tissue
- A group of similar cells that work together to do a shared job.
Check yourself
The Integumentary System
Spread flat, your skin would cover about two square meters. It weighs more than any other organ you have. Yet most of us never think of it as an organ at all. This chapter will change that.
You will build the skin from the top down, one layer at a time. Then you will follow a single cell on its month-long trip. It starts as a busy, living cell and ends as a dead flake on the surface. You will learn where skin color comes from. You will meet the hair, nails, and glands that grow out of the skin. You will also see the five quiet jobs your skin does every second. We end with burns and skin cancer, the two main ways this amazing barrier can fail.
By the end of this chapter you can
- Name the two true layers of the skin, the epidermis and the dermis. Name the hypodermis below them. Say what tissue each is made of and what job it does.
- List the five epidermal strata (layers) in order. Follow a skin cell through keratinization, from its birth to the day it flakes off.
- Explain how melanocytes and melanin give skin its color and shield DNA from ultraviolet light.
- Describe how hair, nails, and the sebaceous and sweat glands are built. Say what each one adds.
- Sum up the skin's five functions: protection, thermoregulation (heat control), sensation, vitamin D synthesis, and excretion.
- Sort burns by how deep they go. Estimate how much skin is burned with the rule of nines. Tell apart the three skin cancers.
- Use the ABCDE warning signs to tell a harmless mole from a possible melanoma.
Section 1Layers of the skin
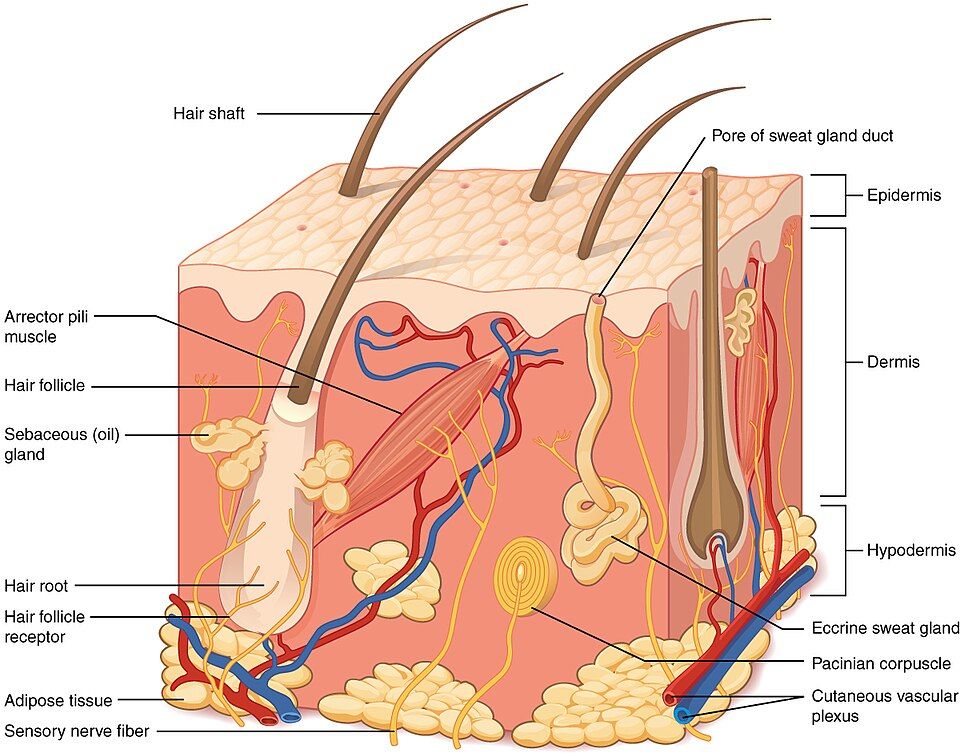
An organ you can see
The integumentary system is your skin plus everything that grows out of it. That means hair, nails, and glands. The word integument just means "a covering." That is the simplest way to picture skin. It is a wrapper. It keeps the wet, carefully controlled world inside you apart from the dry, risky world outside.
But "wrapper" sells it short. The skin is a true organ, a body part built from several tissue types working together. In fact, it uses all four types. It is the largest organ in the body, both by weight and by surface area. One fact holds this whole chapter together. The skin is two layers stacked on top of a third, supporting layer. And that third layer is not really skin at all.
Two layers of skin, one layer beneath
Read the skin from the surface down, and you pass through three named layers. The top two are the skin itself. The third one holds the skin to the body.
| Layer | Tissue | What is there and what it does |
|---|---|---|
| Epidermis | Keratinized stratified squamous epithelium (many layers of flat, tough cells) | The tough, waterproof outer sheet. It has no blood vessels. Food and oxygen seep up to it from below. |
| Dermis | Dense irregular connective tissue | The living core. It holds blood vessels, nerves, hair follicles, glands, and the collagen that makes skin strong. |
| Hypodermis (subcutaneous) | Areolar (loose) and adipose (fat) tissue | Not part of the skin. It holds skin to muscle and bone, keeps in heat, and stores energy. |
The epidermis is the top layer. It is made only of epithelium, a sheet of tightly packed cells. It is also avascular, which means it has no blood vessels of its own. Its living cells get oxygen and food that seep up from the dermis below. The outer part of the epidermis is too far from this supply. So those outer cells are all dead.
The dermis is where the action is. It is a thick mesh of collagen and stretchy fibers. It is packed with blood vessels, nerves, hair follicles, and glands. These are the parts that let skin do its jobs. The dermis has two smaller layers. On top is a thin, bumpy papillary layer. Its bumps, the dermal papillae, make your fingerprints. Below it is a thick reticular layer that holds most of the collagen.
Under the dermis lies the hypodermis. It is also called the subcutaneous layer or superficial fascia. It is mostly fat. It pads and warms the body. It also ties the skin loosely to the parts underneath.
Thick skin and thin skin
Not all skin is the same thickness. Thick skin covers the palms of your hands and the soles of your feet. These are the spots that get rubbed the most. Thick skin has all five layers of epidermis, including an extra clear one.
Thin skin covers the rest of your body. It is more delicate and has only four layers of epidermis. It is also the only skin that grows hair. Watch out for one common mix-up. The names "thick" and "thin" describe the epidermis only. They do not describe how thick the whole skin is.
- The integumentary system is the skin plus hair, nails, and glands. The skin is the body's largest organ.
- The skin has two true layers. The epidermis is made of epithelium and has no blood vessels. It sits on the dermis, a connective tissue layer that has blood vessels and holds the skin's structures.
- The hypodermis below is fat and loose tissue. It is not skin. It holds the skin in place and keeps in heat.
- Thick skin (palms and soles) has five layers of epidermis. Thin skin has four and grows hair.
Section 2The five epidermal strata
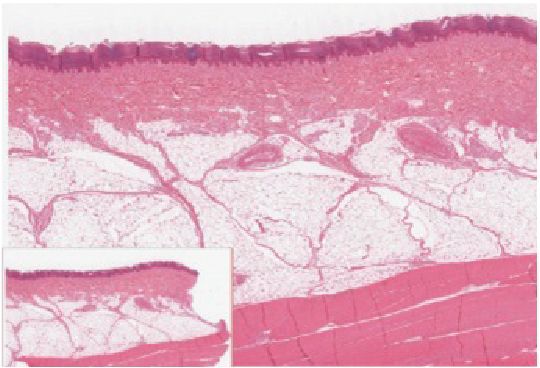
A conveyor belt of cells
The epidermis is like a factory that never stops. Its main cell is the keratinocyte. It is born at the very bottom. New cells form below it and push it upward. As it rises, it fills with a tough protein called keratin. It dies along the way. At last it flakes off the top.
The whole trip takes about four weeks, or roughly 25 to 45 days. So the outer surface of your body is fully replaced about once a month. This slow climb is called keratinization. It is the most important process in the epidermis.
The five layers, bottom to top
In thick skin, the keratinocyte passes through five named layers, or strata, on its way up. Learn them in order. Start at the deepest layer, where cells are born. End at the surface, where they are shed:
| Stratum (deep → surface) | Nickname | What happens here |
|---|---|---|
| Stratum basale | The nursery | One row of dividing stem cells. New keratinocytes are made here by cell division (mitosis). Melanocytes and touch-sensing Merkel cells live here too. |
| Stratum spinosum | The spiny layer | Several rows of keratinocytes held together by strong desmosomes, tiny "rivets" between cells. They give the layer a spiny look. Immune dendritic cells patrol here. |
| Stratum granulosum | The dying layer | Cells fill with grains of keratin and a waterproof fat. Their nuclei break down, and the cells start to die. |
| Stratum lucidum | The clear layer | A thin, see-through band of dead cells. It is found only in thick skin (palms and soles). |
| Stratum corneum | The horny layer | 15–30 layers of flat, dead cells packed with keratin. This is the tough, waterproof barrier you actually touch. |
A memory trick helps. Read from the base up: Basale, Spinosum, Granulosum, Lucidum, Corneum. Think "Bad Students Get Lousy Classes." The bottom two layers, basale and spinosum, are alive. They are sometimes grouped together as the stratum germinativum, the growth zone. From the granulosum up, the cells are dying or dead.
By the time a cell reaches the stratum corneum, it is just a flat bag of keratin. It is glued to its neighbors and coated in fat. That dead, waterproof crust is what makes skin such a good barrier. You shed about a million of these cells every day.
- Keratinocytes are born in the stratum basale. They are pushed upward and shed from the surface in about a month. This process is called keratinization.
- The order from deep to surface is basale → spinosum → granulosum → lucidum → corneum ("Bad Students Get Lousy Classes").
- The stratum lucidum is found only in thick skin. The stratum corneum is the dead, keratin-filled barrier you touch.
Section 3Skin color & melanin
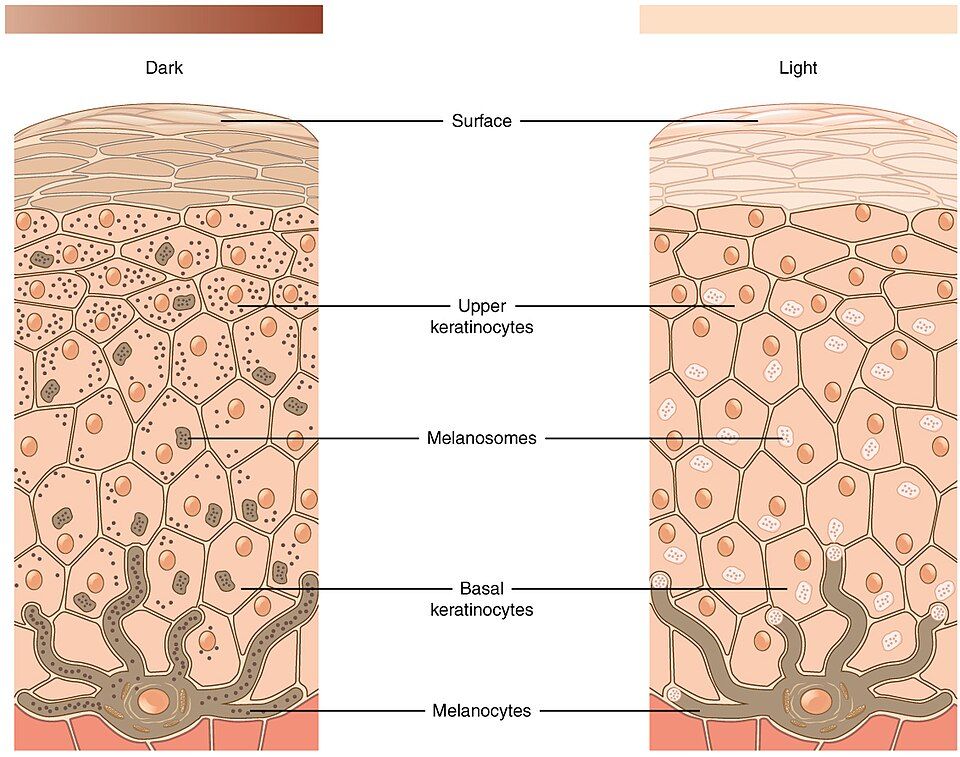
Three pigments, one main player
Skin color comes from three pigments mixed together. A pigment is a substance that gives color. Melanin is the main one. It is a brown-to-black (or red-to-yellow) pigment made in the epidermis. Carotene is a yellow-orange pigment that comes from food, such as carrots. It collects in the stratum corneum and in the fat of the hypodermis.
Hemoglobin is the red pigment in blood. It shows through where the epidermis is thin. It gives lighter skin its pink glow. Of the three, melanin matters most. It is also the one that varies most from person to person.
Melanocytes hand off their pigment
Melanin is made by a special cell called the melanocyte. It sits down in the stratum basale. Here is the surprising part. Melanocytes do not keep their pigment. They pack melanin into tiny sacs called melanosomes. Then they hand these sacs to the keratinocytes around them.
Inside a keratinocyte, the melanin moves to the sunny side of the cell. It forms a small cap over the top of the nucleus. It is like a tiny umbrella held over the cell's DNA. There it soaks up incoming ultraviolet (UV) radiation, the invisible rays in sunlight. It catches the UV before it can reach and harm the DNA. That is the whole point of skin pigment. Melanin is sunscreen your cells make for themselves.
When pigment goes wrong, and reading skin color in the clinic
Two conditions show what happens at the extremes. In albinism, an inherited condition, melanocytes are present but cannot make melanin. So the skin, hair, and eyes have little or no color, and they burn easily. In vitiligo, the immune system destroys melanocytes in patches. This leaves pale blotches on the skin.
Skin color also gives some of the fastest clues to illness. Health workers can see it right at the bedside. That is because skin color reflects what is happening in the blood underneath.
| Color change | What it looks like | What it usually means |
|---|---|---|
| Cyanosis | Bluish skin, lips, and nail beds | Blood that is low in oxygen (low O₂) |
| Pallor | Pale, washed-out skin | Low blood flow or anemia (too few red blood cells). Seen with shock, fear, or cold. |
| Erythema | Redness | More blood flow. Seen with fever, swelling and irritation (inflammation), blushing, or sunburn. |
| Jaundice | Yellow skin and yellow whites of the eyes (sclerae) | A buildup of bilirubin, a yellow waste. Usually a liver problem. |
| Bronzing | A golden-bronze tone | Adrenal glands that do not make enough hormone (Addison disease) |
- Skin color mixes three pigments: melanin (the main one), carotene, and hemoglobin from blood.
- Melanocytes in the stratum basale make melanin. They hand it to keratinocytes. There it caps the nucleus and soaks up UV to protect DNA.
- Everyone has about the same number of melanocytes. Color differences come from the amount and type of melanin. A tan is a defense against UV.
- Skin color gives clues about the blood. Cyanosis, pallor, erythema, jaundice, and bronzing each point to a certain problem.
Section 4Hair, nails & glands
Hair: keratin threads with a living root
The skin's extra parts, like hair and glands, are called accessory structures. Each one grows from the epidermis. But each one is tucked down into the dermis, where the blood supply is.
Hair is a bendy strand of dead, hard keratin. The part you see above the skin is the shaft. The part below is the root. The root sits inside a tube called the hair follicle. At the very bottom, the follicle swells into a bulb. Inside the bulb is a small knot of connective tissue called the papilla. It brings in the blood vessels that feed the growing hair.
Just above the papilla is the matrix. It is the only living, dividing part of a hair. That is why a haircut does not hurt but plucking a hair does. A tiny muscle called the arrector pili is attached to each follicle. When you are cold or scared, it tightens. It pulls the hair upright and dimples the skin into "goosebumps."
Nails: a window over the fingertip
A nail is a plate of hard keratin. It protects the tip of each finger and toe. It also gives you a tool for scratching and gripping. The part you see is the nail body. It sits on the nail bed. The pale half-moon at its base is the lunula. It marks the nail matrix underneath, where the nail actually grows. The cuticle (eponychium) is the fold of skin that seals the base against dirt and germs.
Nails are a useful window on health. They turn blue when the blood is low in oxygen. They become curved and rounded, called clubbed, in long-term heart or lung disease. They curve inward like a spoon in iron-deficiency anemia, when the body is short on iron.
Glands: oil and sweat
The skin holds two big families of glands. Sebaceous (oil) glands usually empty into a hair follicle. They release an oily mix called sebum. Sebum keeps the hair and skin soft and slows the growth of bacteria. When a follicle clogs with sebum and dead cells, the result is acne.
Sweat (sudoriferous) glands come in two types. It is worth keeping them straight:
| Gland | Where it is and what it releases | Job |
|---|---|---|
| Sebaceous (oil) | Into hair follicles. Releases oily sebum. | Keeps skin and hair soft. Mildly fights bacteria. |
| Eccrine (merocrine) sweat | All over the body, onto the skin surface. Releases watery sweat. | Cools the body as sweat dries (evaporates). The main gland for thermoregulation, or heat control. |
| Apocrine sweat | Armpits and groin, into hair follicles. Releases thicker sweat with protein in it. | Turns on at puberty. Feeds skin bacteria that cause body odor. |
| Ceruminous & mammary | Ear canal / breast | Changed sweat glands that make earwax and milk |
- Hair is dead keratin. It grows only from the living matrix at its base, which is fed by the papilla. It stands up when the arrector pili muscle tightens.
- Nails are keratin plates. They grow from the nail matrix under the lunula. Their color and shape can reveal disease in the whole body.
- Sebaceous glands make oily sebum. Eccrine sweat glands cool the body. Apocrine glands (armpit, groin) cause body odor once bacteria act on their sweat.
Section 5What the skin does
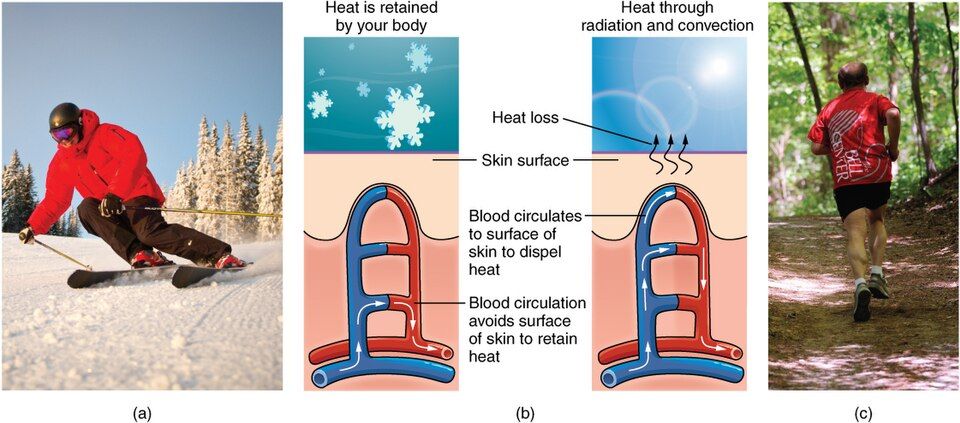
One organ, five jobs
It is easy to think the skin just covers you. But covering you is only the first of five real jobs it does every moment. Hold on to all five. They come up again and again in later chapters.
| Function | How the skin does it |
|---|---|
| 1. Protection | A physical barrier (keratin and tightly joined cells). A chemical barrier (the slightly acidic "acid mantle" made by sweat and oil). A biological barrier (immune dendritic cells that catch invaders). |
| 2. Thermoregulation | To cool down, sweat dries off the skin and blood vessels in the dermis widen (dilate) to let heat out. To warm up, those vessels narrow (constrict) to keep heat in. |
| 3. Sensation | Packed with receptors, sensors for touch, pressure, vibration, temperature, and pain. It is the body's largest sense organ. |
| 4. Vitamin D synthesis | UV light turns a relative of cholesterol in the skin into vitamin D₃. You need it to absorb calcium from food. |
| 5. Excretion & storage | Sweat gets rid of small amounts of water, salts, and wastes. The dermis stores a blood reservoir (up to about 5% of the body's blood). |
The barrier you rebuild every month
Protection is the star job. The dead, keratin-packed stratum corneum keeps water in. Without it, you would dry out in hours. It also keeps germs, chemicals, and UV out.
Sweat and oil coat the surface in a slightly acidic film called the acid mantle. This film makes life hard for bacteria and fungi. Dendritic immune cells are woven through the epidermis. They grab any invader that slips past. The whole barrier is rebuilt about once a month. So small damage heals with barely a trace.
Temperature, sensation, and a vitamin the skin makes
The skin is also your main thermostat, the part that controls your body heat. When you get too hot, eccrine glands pour out sweat. As the sweat dries, it carries heat away. Blood vessels in the dermis also widen to give off heat at the surface. That is why you turn pink when you are hot. When you are cold, those same vessels squeeze down to trap warmth deep inside.
The dermis is also crowded with sensory receptors. These make the skin the largest sense organ you have. They send your nervous system a steady stream of touch, pressure, temperature, and pain signals.
The skin also makes vitamin D, a job no other organ can start. UV light strikes a molecule like cholesterol in the epidermis. This begins its change into vitamin D₃. Without vitamin D, you cannot absorb the calcium your bones and nerves depend on.
- The skin's five jobs are protection, thermoregulation, sensation, vitamin D synthesis, and excretion/storage.
- Protection is physical (keratin), chemical (the acidic acid mantle), and biological (immune dendritic cells).
- Cooling uses sweat plus wider blood vessels. Warming uses narrower blood vessels. Vitamin D₃ is made in the skin with the help of UV. You need it to absorb calcium.
Section 6Burns & skin cancer
Burns: it's all about depth
A burn destroys skin. It can be caused by heat, electricity, chemicals, or radiation. How bad a burn is depends first on how deep it goes. The skin's barrier, water control, and heat control all live in these layers. So the deeper the burn, the more dangerous it is. This is not because a deep burn hurts more. In fact, a deep burn may stop hurting at all.
| Burn (depth) | Layers destroyed | How it looks and feels |
|---|---|---|
| First-degree (superficial) | Epidermis only | Red, dry, and painful, with no blisters. A typical sunburn. Heals in days. |
| Second-degree (partial thickness) | Epidermis plus part of the dermis | Blisters, redness, and a lot of pain. Heals but may scar. |
| Third-degree (full thickness) | All of the epidermis and dermis | White, brown, or blackened, and leathery. Often painless because the nerves are destroyed. Needs skin grafting (moving healthy skin onto the wound). |
A serious burn has two big dangers: fluid loss and infection. Once the barrier is gone, water pours out and germs pour in. The body can no longer hold its temperature steady either.
To judge how much skin is burned, doctors and nurses use the rule of nines. It splits the adult body surface into regions worth about 9% each, or a multiple of nine. Each arm is 9%. Each leg is 18%. The front of the trunk is 18%, and so on. A burn is usually called critical in three cases. It covers more than 25% of the body. Or it involves the hands, face, or feet. Or it is third-degree over more than 10% of the body.
Skin cancer: three kinds, one that kills
Skin cancer is the most common cancer of all. Its leading cause is years of UV exposure. There are three main types. Telling them apart matters a lot. Some are just a nuisance, but one can kill. Notice that each one starts in a cell you already met in this chapter.
| Cancer | Cell it starts in | How it behaves |
|---|---|---|
| Basal cell carcinoma | Cells of the stratum basale | The most common and least dangerous. Rarely spreads. Usually cured by cutting it out. |
| Squamous cell carcinoma | Keratinocytes of the stratum spinosum | Less common. Can spread if ignored, but usually curable if caught early. |
| Melanoma | Melanocytes | The least common but most deadly. Spreads (metastasizes) early and fast. Catching it early saves lives. |
The dangerous one is melanoma, a cancer of the melanocytes that make pigment. It often starts in or near a mole. It metastasizes, or spreads to other parts of the body, early. So spotting it early is everything.
The ABCDE rule helps you check a mole that looks suspicious. Asymmetry: one half does not match the other. Border: the edges are ragged or blurred. Color: the color is uneven, with several shades. Diameter: it is wider than about 6 mm, the size of a pencil eraser. Evolving: it changes in size, shape, or color over time.
Any mole that shows these signs should be checked by a doctor.
- Burns are graded by depth. First-degree burns hurt only the epidermis. Second-degree burns reach into the dermis and blister. Third-degree burns go all the way through, are often painless, and need skin grafts.
- Serious burns kill through fluid loss and infection. The rule of nines estimates what percent of the body surface is burned.
- There are three skin cancers. Basal cell is common and mild. Squamous cell can spread. Melanoma is rare but deadly. Check moles with ABCDE.
The chapter in one breath
- The integumentary system is the skin plus hair, nails, and glands. The skin is the body's largest organ.
- Skin has two true layers. The epidermis is epithelium with no blood vessels. It sits on the dermis, a connective tissue layer with blood vessels. Both rest on the fatty hypodermis.
- Keratinocytes ride upward through five strata: basale → spinosum → granulosum → lucidum → corneum. They fill with keratin, die, and flake off in about a month.
- Melanocytes make melanin and pass it to keratinocytes. There it caps the nucleus and soaks up UV to protect DNA. Color differences come from the amount of melanin, not the number of melanocytes.
- Hair and nails are keratin structures that grow from living matrices. Sebaceous glands make oil. Eccrine glands cool you. Apocrine glands cause body odor.
- The skin does five jobs: protection, thermoregulation, sensation, vitamin D synthesis, and excretion/storage.
- Burns are graded by depth (first- to third-degree) and by area (rule of nines). The three skin cancers are basal cell, squamous cell, and the deadly melanoma. Moles are checked with ABCDE.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Apocrine sweat gland
- A sweat gland in the armpit and groin that empties into a hair follicle. It makes a thick sweat with protein in it, turns on at puberty, and causes body odor once bacteria break the sweat down.
- Arrector pili
- A tiny smooth muscle attached to a hair follicle. When it tightens, it pulls the hair upright and makes "goosebumps."
- Basal cell carcinoma
- The most common and least dangerous skin cancer. It starts in cells of the stratum basale and rarely spreads.
- Carotene
- A yellow-orange pigment from food. It collects in the stratum corneum and hypodermis and adds to skin color.
- Dermis
- The deep, living layer of skin, made of dense irregular connective tissue. It holds blood vessels, nerves, hair follicles, and glands.
- Eccrine (merocrine) sweat gland
- The most common sweat gland, found all over the body. It opens right onto the skin, and its watery sweat cools you as it dries.
- Epidermis
- The top layer of skin. It is a keratinized stratified squamous epithelium (many layers of flat, tough cells) with no blood vessels of its own.
- Hair follicle
- The tube of tissue around the hair root. The hair grows out of it.
- Hypodermis (subcutaneous layer)
- The layer of fat and loose tissue under the skin. It is not part of the skin itself. It holds the skin in place, keeps in heat, and stores energy.
- Integument
- A covering. The integumentary system is the skin plus hair, nails, and glands.
- Keratin
- A tough, water-resistant protein. It fills skin cells, hair, and nails, and makes them strong and waterproof.
- Keratinocyte
- The main cell of the epidermis. It is born in the stratum basale, fills with keratin as it is pushed up, dies, and is shed.
- Melanin
- The brown-to-black (or red-to-yellow) pigment that gives skin most of its color. It soaks up ultraviolet light to protect DNA.
- Melanocyte
- The pigment-making cell in the stratum basale. It makes melanin and passes it to nearby keratinocytes.
- Melanoma
- The least common but most dangerous skin cancer. It starts in melanocytes, spreads early, and is checked for with the ABCDE rule.
- Rule of nines
- A way to estimate what percent of the body's surface is burned. It splits the adult body into regions of about 9% or multiples of nine.
- Sebaceous gland
- An oil gland that usually empties into a hair follicle. Its sebum keeps skin and hair soft and holds back bacteria.
- Sebum
- The oil made by sebaceous glands. When a follicle clogs with sebum and dead cells, acne results.
- Squamous cell carcinoma
- A skin cancer that starts in keratinocytes of the stratum spinosum. It can spread if not treated but is usually curable if caught early.
- Stratum basale
- The deepest layer of the epidermis. It is one row of dividing stem cells and also holds melanocytes and Merkel cells.
- Stratum corneum
- The outermost layer of the epidermis. It is 15–30 rows of dead, keratin-filled cells that form the tough, waterproof barrier.
- Vitamin D
- A vitamin the skin starts to make when ultraviolet light hits a relative of cholesterol in the epidermis. You need it to absorb calcium from food.
Check yourself
Bone Tissue & the Skeletal System
It is easy to picture the skeleton as a dry rack of poles, the part of us that lasts after everything else is gone. That picture is wrong in the most important way. Bone is living tissue. It is laced with blood vessels and nerves. It is rebuilt every day of your life. And it quietly does jobs that have nothing to do with holding you up.
In this chapter you will meet the skeleton as an organ system, a group of organs that work together. You will see how it is built and what its cells do. You will learn how it keeps the calcium in your blood in a very narrow range. You will also see how it heals itself when it breaks. Once you see bone as alive, the rest of the skeleton makes sense.
By the end of this chapter you can
- List the major functions of the skeletal system. Split the skeleton into its axial and appendicular parts.
- Sort bones by shape: long, short, flat, irregular, and sesamoid. Give an example of each.
- Name the main parts of a long bone that you can see without a microscope. Describe how compact and spongy bone differ.
- Name the four bone cells. Explain how remodeling balances building bone up against breaking it down.
- Describe the organic and inorganic parts of bone matrix and what each one adds.
- Draw how parathyroid hormone and calcitonin keep blood calcium near its set point.
- Recognize common fracture patterns. Put the four stages of bone repair in order.
Section 1What the skeleton is for
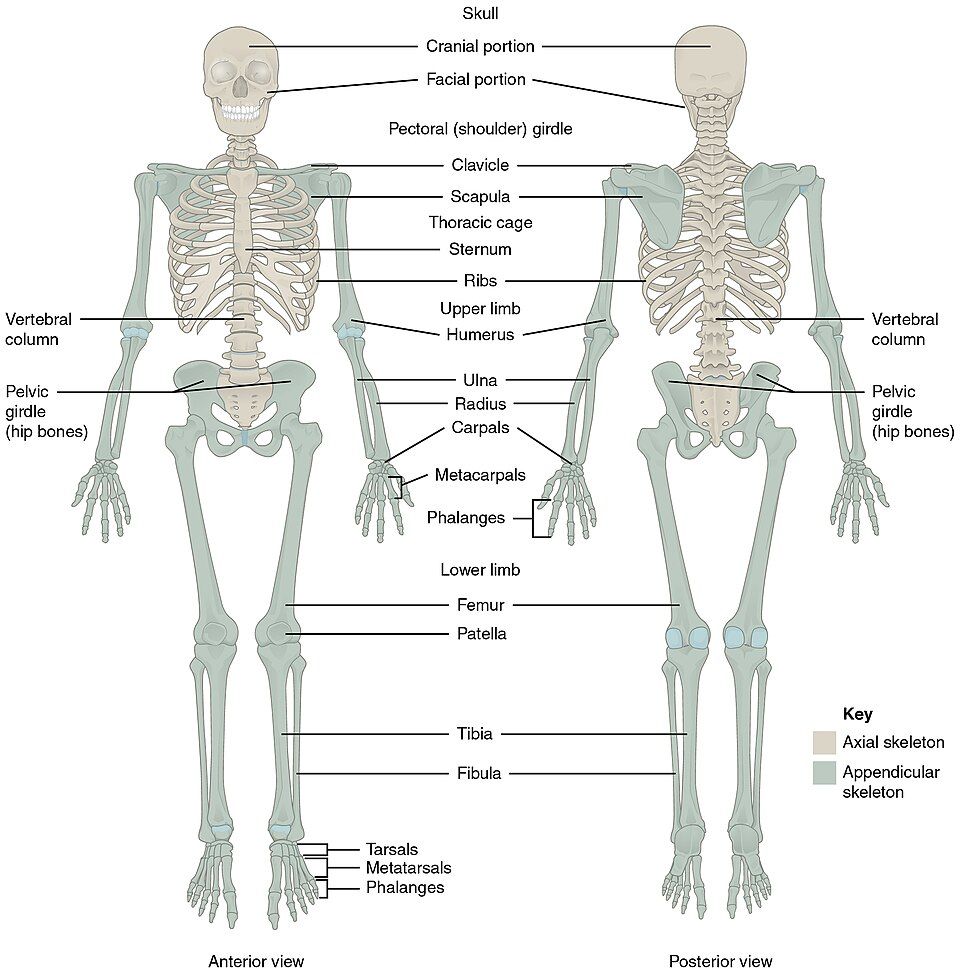
A frame that is also a factory
Every bone is an organ. It is made of several tissue types working together. These include bone tissue, cartilage, dense connective tissue, blood, and nerve tissue. And a bone is very much alive. Snap a fresh bone and it bleeds. Leave a broken one alone and it heals.
All your bones, cartilages, and joints together make up the skeletal system. This system does far more than give you a shape. It works as a support beam, a suit of armor, and a set of levers. It is also a mineral bank and a factory for blood cells. Often it does all of these at the same time.
The jobs bones do
It is worth learning the skeleton's main jobs as a short list. Almost everything else in this chapter is one of these jobs seen up close. Bone stores fat and minerals, makes blood, moves you, protects you, and holds you up.
| Function | How the skeleton does it |
|---|---|
| Support | A stiff frame that holds the body up. It gives soft organs and muscles a place to attach. |
| Protection | Hard cases shield key organs. The skull guards the brain. The vertebrae guard the spinal cord. The rib cage guards the heart and lungs. |
| Movement | Bones act as levers that muscles pull on. Where two bones meet at a joint, motion happens. |
| Mineral & fat storage | Bone is a storehouse for calcium and phosphate. It stores them or releases them as needed. Yellow marrow stores energy as fat. |
| Blood-cell formation | Hematopoiesis, the making of blood cells. Red marrow inside some bones makes red cells, white cells, and platelets. |
Axial and appendicular: two halves of one set
An adult skeleton has 206 bones. They split into two named groups. The axial skeleton has about 80 bones. It runs down the center line, or axis, of the body. It includes the skull, the backbone (vertebral column), and the rib cage (thoracic cage). Its main jobs are protection and support.
The appendicular skeleton has about 126 bones. It is everything that hangs off the axis. That means the arms and legs. It also includes the two girdles, the shoulder (pectoral) and hip (pelvic) girdles, which attach the limbs to the trunk. Its main job is movement. In the reference figure, the axial bones are one color and the appendicular bones are another. This is a handy way to keep the two straight.
Tap each of the skeleton's jobs in the interactive to see what carries it out.
- A bone is a living organ. The skeletal system is bones, cartilages, and joints together.
- Main jobs: support, protection, movement, mineral/fat storage, and blood-cell formation (hematopoiesis).
- The axial skeleton (about 80 bones) protects and supports. The appendicular skeleton (about 126 bones) lets you move. An adult has 206 bones in all.
- About 99% of the body's calcium is stored in bone.
Section 2Classifying bones by shape
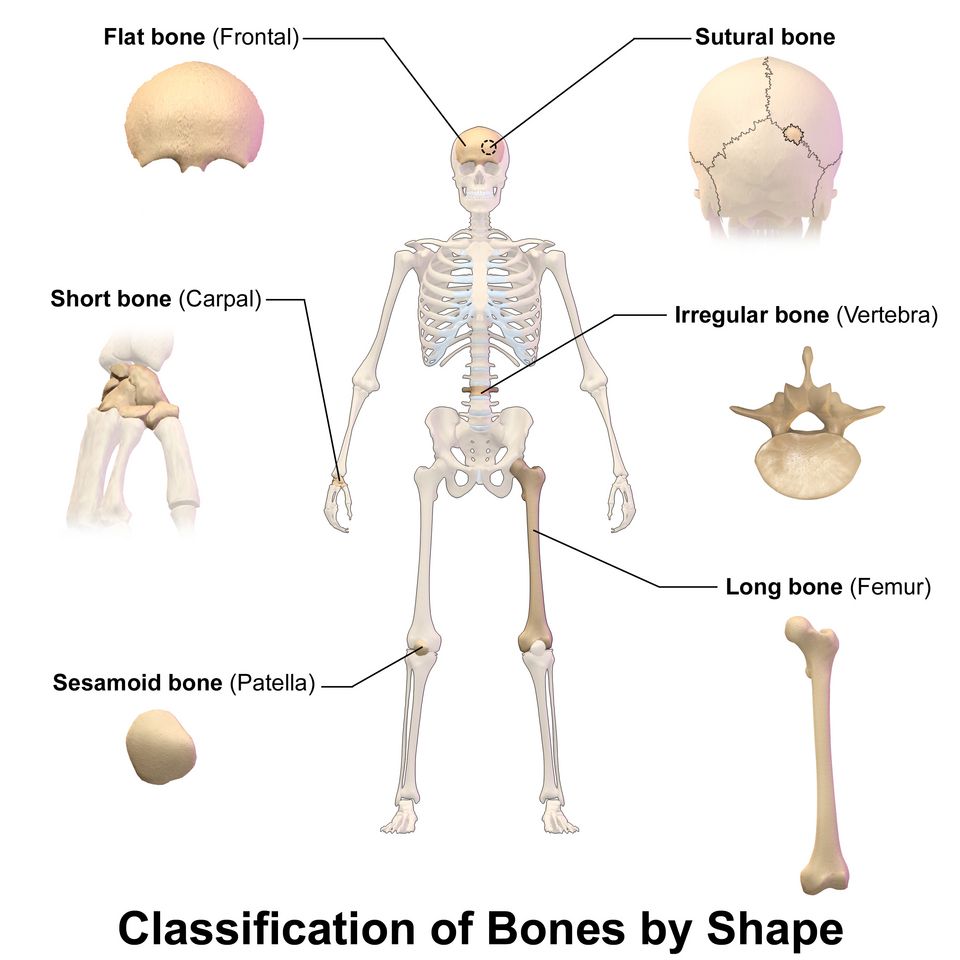
Shape follows the job
Bones come in a few shapes you can learn to spot. As with the rest of the body, the shape is a clue to the job. A bone built to act as a lever looks nothing like a bone built to shield a soft organ. Sorting bones into five shape classes gives you quick words to describe any bone you meet.
The five shapes
| Class | Shape & role | Examples |
|---|---|---|
| Long bone | Longer than it is wide, with a shaft and two ends. Acts as a lever for movement. | Femur (thigh), humerus (upper arm), phalanges (fingers & toes) |
| Short bone | Roughly cube-shaped. Gives steady support with only a little motion. | Carpals (wrist), tarsals (ankle) |
| Flat bone | Thin plates that are often curved. They protect organs and give muscles a wide place to attach. | Skull bones, sternum (breastbone), ribs, scapula (shoulder blade) |
| Irregular bone | Odd shapes that fit no other class. They do many kinds of protection and support. | Vertebrae, hip bones, many face bones |
| Sesamoid bone | Small bones set inside a tendon. They protect the tendon and give it a better pull. | Patella (kneecap) |
Notice that the phalanges of your fingers count as long bones, even though they are tiny. The label is about proportion, not size. A long bone is longer than it is wide and has a shaft. It also works as a lever. The reference figure also shows a sutural (Wormian) bone. This is a small extra bone that can show up in the seams of the skull. Think of it as a special kind of flat bone, not a sixth class.
Tap each shape in the interactive to see the bone and where it lives in the body.
- There are five shape classes: long, short, flat, irregular, and sesamoid.
- Long bones are levers. Short bones give steady support. Flat bones protect. Irregular bones do special jobs. Sesamoids sit inside tendons.
- The patella is the largest sesamoid. The phalanges are small long bones.
Section 3Inside a long bone
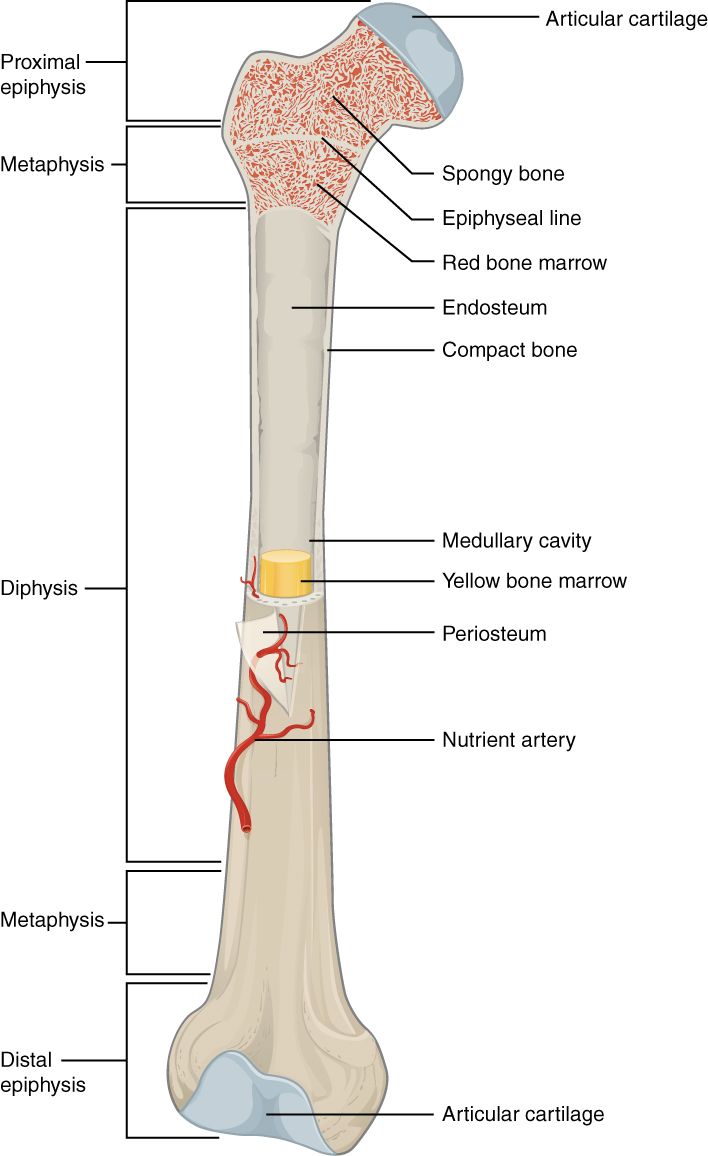
The shaft and the ends
A long bone, like the femur, has a neat layout once you learn its parts. The long middle tube is the diaphysis, or shaft. Its wall is a tube of dense compact bone. Its hollow center is the medullary cavity. In adults it is filled with fatty yellow marrow.
Each rounded end is an epiphysis. It is filled with light spongy (trabecular) bone. The spaces in spongy bone hold red marrow, where blood cells are made. Where the end meets another bone at a joint, it is capped with slick articular cartilage. This cartilage cushions the joint and lets it glide.
Between the shaft and each end is the metaphysis. In a growing child, it holds the epiphyseal (growth) plate. This is a disc of cartilage where the bone gets longer. When growth ends, the plate turns to bone. It leaves a thin epiphyseal line.
The living wrappers
Two thin layers keep bone alive and connected. The periosteum is a tough sheath on the outside of the bone. It covers every surface except the joint caps. It carries blood vessels and nerves. It anchors tendons and ligaments. It also holds bone-making cells for growth and repair.
The inner surfaces are lined by the thin endosteum. It lines the medullary cavity and the spaces in spongy bone. It also holds bone cells. A nutrient artery enters the shaft through a small hole. It feeds the bone from the inside.
Zoom in: the osteon
Under a microscope, compact bone is not a solid block. It is a bundle of tiny pillars that bear weight, called osteons (Haversian systems). Each osteon is a set of rings of bone matrix, like the rings in a tree trunk. These rings are the lamellae. They wrap around a central canal that carries a blood vessel and a nerve.
Small pockets between the rings are called lacunae. Mature bone cells, the osteocytes, are trapped inside them. The cells stay linked to each other and to the central vessel by hair-thin channels called canaliculi. This system of canals and channels works like plumbing. It keeps the buried cells in hard bone fed and alive.
| Part | What it is or holds |
|---|---|
| Diaphysis | The shaft. A tube of compact bone around the medullary cavity. |
| Epiphysis | A wide end filled with spongy bone and red marrow |
| Metaphysis | The area between the shaft and the end. Home of the growth plate or growth line. |
| Medullary cavity | The hollow center of the shaft. Holds yellow (fatty) marrow in adults. |
| Articular cartilage | Smooth cartilage that caps the joint surface of each epiphysis |
| Periosteum | Outer layer. Holds vessels, nerves, attachment points, and bone-making cells. |
| Endosteum | Inner lining of the marrow cavity and the spongy bone spaces |
Tap each labeled part in the interactive to find it on the bone and learn its role.
- The diaphysis (shaft) is compact bone around a marrow-filled medullary cavity. The epiphyses (ends) are spongy bone with red marrow.
- The metaphysis holds the epiphyseal plate (growth plate). It becomes the epiphyseal line when growth stops.
- The periosteum wraps the outside. The endosteum lines the inside.
- Compact bone is built of osteons. Each is rings of lamellae around a central canal. Osteocytes sit in lacunae, linked by canaliculi.
Section 4Bone cells & remodeling
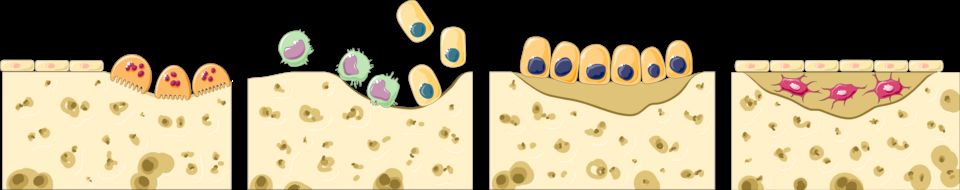
What bone is made of
Bone tissue is a wonder of design. It mixes two opposite qualities. Its organic part is mostly collagen fibers. Collagen gives bone flexibility and tensile strength, the strength to resist being pulled. So bone bends a little under a load instead of snapping.
Its inorganic part is made of mineral salts of calcium and phosphate. These form hard crystals called hydroxyapatite. They give bone its hardness and compressive strength, the strength to resist being squeezed. Take the mineral away, and bone turns rubbery. Take the collagen away, and it turns as brittle as chalk. Healthy bone needs both, in balance.
Four cells, one crew
Four cell types build and care for this matrix. The easiest way to remember them is by their jobs. Osteogenic (osteoprogenitor) cells are like stem cells. They divide to make the builders. Osteoblasts lay down new bone matrix. They build.
An osteoblast can wall itself into the matrix it made. Then it matures into an osteocyte. This is the caretaker cell. It lives in a lacuna and keeps the tissue healthy. The wrecking crew is the osteoclasts. These are large cells with many nuclei. They dissolve old bone and release its minerals back into the blood.
| Cell | Job | Memory hook |
|---|---|---|
| Osteogenic cell | Stem cell that divides to make osteoblasts | The source |
| Osteoblast | Builds new bone matrix | “b” for build |
| Osteocyte | Mature cell. Keeps bone healthy and senses stress on it. | A retired builder, walled in |
| Osteoclast | Breaks down bone. Frees calcium. | “c” for consume/carve |
The tug-of-war called remodeling
Bone is never finished. All through life, osteoclasts dissolve old bone. Osteoblasts lay down fresh bone right behind them. This nonstop cycle is called remodeling. It replaces about 10% of the skeleton every year. When the two crews stay balanced, the amount of bone stays steady.
Two things tune the balance. The first is mechanical stress, the load placed on a bone. Bone gets thicker where it is loaded and thinner where it is not. This rule is called Wolff's law. It is why exercise that puts weight on your bones makes them stronger. It is also why bones weaken during bed rest or in space. The second is hormones, especially the two calcium hormones you will meet next.
Sometimes breakdown beats building for years. This often happens after menopause. The result is osteoporosis, bone full of holes that breaks easily.
Watch the crews trade places in the interactive, and meet the four cells one at a time.
- Bone matrix is collagen (for bending) plus hydroxyapatite mineral (for hardness). It needs both.
- There are four cells: osteogenic (source), osteoblast (build), osteocyte (maintain), and osteoclast (break down).
- Remodeling balances breakdown and building. It replaces about 10% of bone each year. It responds to load (Wolff's law) and to hormones.
- If breakdown wins for a long time, the result is osteoporosis.
Section 5Calcium homeostasis
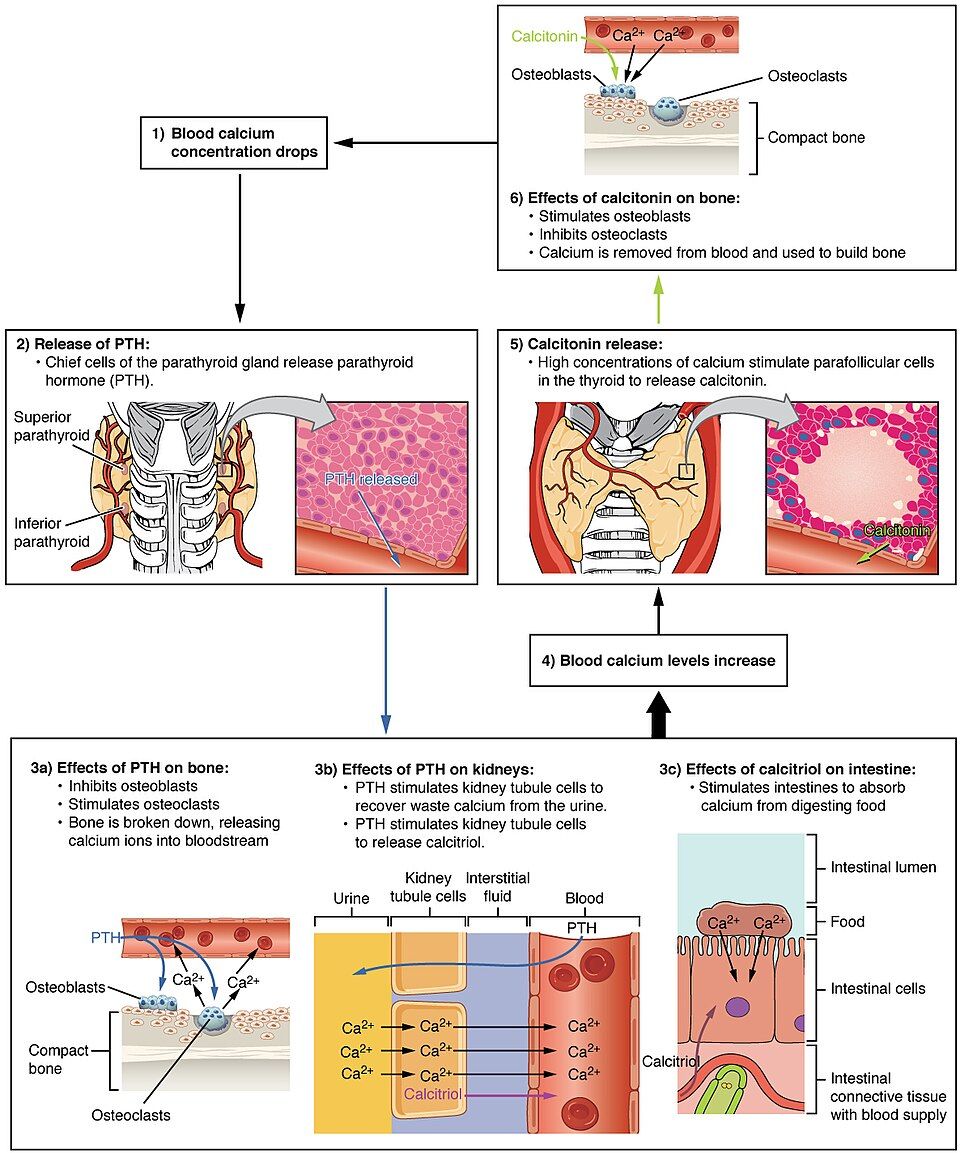
Why calcium is worth guarding
Blood calcium (Ca²⁺) must stay in a tight range, about 9–10 mg/dL. So much depends on it. Calcium makes muscles contract. It lets nerves fire. It is needed for blood clotting. It also carries messages inside cells.
If calcium drops too low, nerves get jumpy. This causes muscle spasms and cramps, called tetany. If it climbs too high, nerves and muscles get sluggish. This is a classic example of homeostasis, the idea from Chapter 1. The body holds a value near a set point using feedback, much like a thermostat. The skeleton is the store the body draws on to protect that value.
PTH raises calcium
When blood calcium falls, the parathyroid glands respond. These are four small glands on the back of the thyroid. They release parathyroid hormone (PTH). PTH raises calcium in three ways at once.
In bone, it spurs osteoclasts to dissolve matrix. This releases calcium into the blood. In the kidneys, it tells the tubes to take back calcium that would be lost in urine. It also has the kidneys turn vitamin D into its active form, calcitriol. Calcitriol then makes the intestines absorb more calcium from food. Bone, kidneys, and gut all pour calcium into the blood. The level climbs back toward normal.
Calcitonin lowers calcium
When blood calcium runs high, the thyroid gland responds. Its parafollicular (C) cells release calcitonin. Calcitonin does the opposite of PTH. It holds back osteoclasts and favors osteoblasts. So calcium is pulled out of the blood and stored back in bone. The level settles down.
The two hormones work as a push-pull pair. PTH is the gas pedal, and calcitonin is the brake. Together they keep blood calcium very steady.
| Feature | Parathyroid hormone (PTH) | Calcitonin |
|---|---|---|
| Released when | Blood calcium is low | Blood calcium is high |
| Source | Parathyroid glands | Thyroid C (parafollicular) cells |
| Effect on calcium | Raises it | Lowers it |
| Bone | Spurs osteoclasts (breakdown) | Holds back osteoclasts (favors building) |
| Kidney / gut | Kidneys take back Ca. Activates vitamin D → gut absorbs more. | Minor role |
Knock blood calcium off its set point in the interactive and watch the right hormone respond.
- Blood calcium is kept near 9–10 mg/dL because nerves, muscles, and clotting depend on it.
- PTH (from the parathyroids) raises calcium. It acts on bone, kidneys, and gut (through calcitriol, the active vitamin D).
- Calcitonin (from thyroid C cells) lowers calcium by holding back osteoclasts.
- The body will take calcium from bone to protect the blood level.
Section 6Fractures & repair
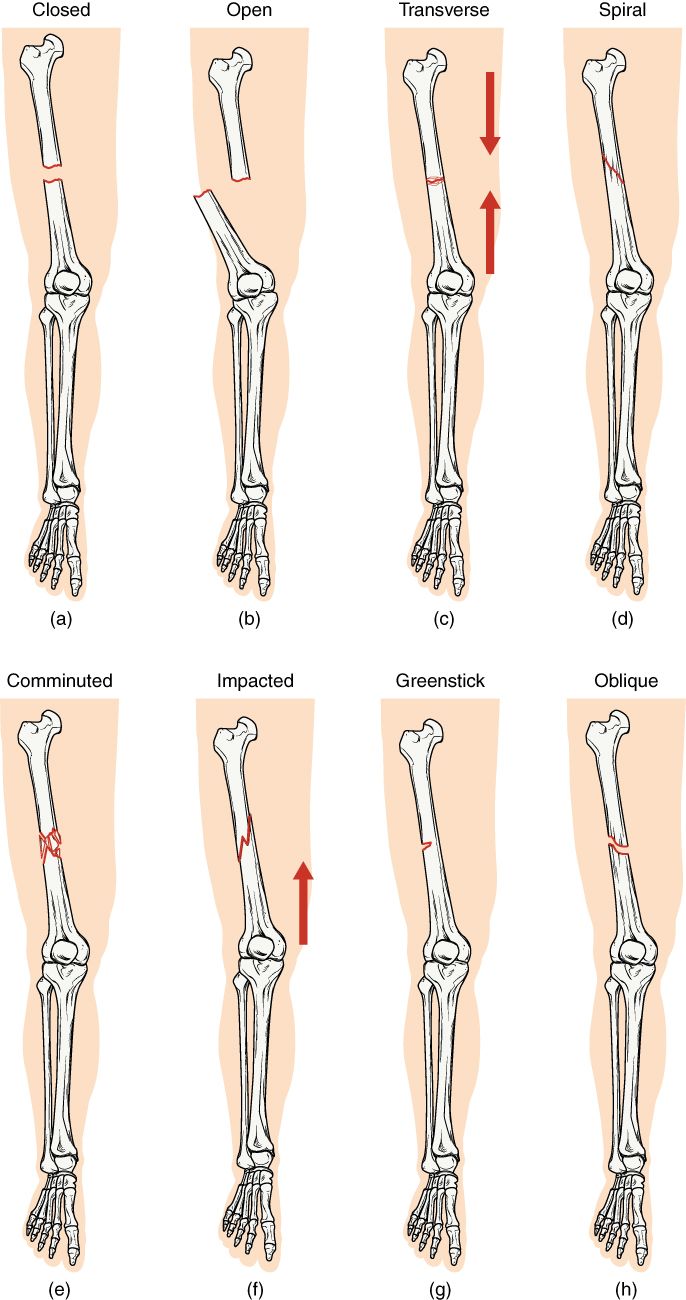
How bones break
A fracture is simply a broken bone. Doctors name the pattern of the break. The pattern hints at what caused it and how to treat it. The first and most important question is whether the skin stayed whole.
A closed (simple) fracture leaves the skin unbroken. An open (compound) fracture breaks through the skin. An open fracture is far more serious. It opens a door for infection. Breaks are also named for the line they follow and how bad they are.
| Type | What it looks like |
|---|---|
| Closed vs open | Skin whole (closed) vs bone poking through the skin (open). Open fractures risk infection. |
| Transverse | The break runs straight across the shaft. |
| Oblique | The break runs at an angle across the bone. |
| Spiral | A twisting break that winds around the shaft. It points to a twisting force. |
| Comminuted | The bone shatters into three or more pieces. |
| Impacted | One broken end is driven into the other. |
| Greenstick | A partial break. The bone bends and cracks on one side. Seen mostly in children. |
How a bone heals: four stages
A broken bone repairs itself in a set order. The full process can take months. First, torn blood vessels bleed and clot. This forms a fracture hematoma, a blood clot that seals the gap and sets the stage.
Next, cells build a fibrocartilaginous (soft) callus out of collagen and cartilage. It splints the broken ends together. Then osteoblasts replace this soft bridge with a bony (hard) callus of spongy bone. This happens about six weeks after the injury. Last, over months, the bone remodels. Osteoclasts and osteoblasts reshape the callus back toward the bone's first shape. The same stresses that shape every bone guide this step.
| Stage | What happens |
|---|---|
| 1. Fracture hematoma | Bleeding forms a clot that fills and seals the break. |
| 2. Soft (fibrocartilaginous) callus | Collagen and cartilage bridge the gap and splint the ends. |
| 3. Hard (bony) callus | Osteoblasts replace the soft callus with spongy bone (about 6 weeks). |
| 4. Bone remodeling | Over months, the callus is reshaped toward the bone's first shape. |
Doctors help this along in two steps. If the broken ends have moved apart, the fracture is first reduced. This means the ends are lined back up. It can be done by moving them from the outside (closed reduction) or by surgery (open reduction). Then the bone is immobilized, or held still, in a cast or with metal hardware. This keeps the fragile callus safe while it matures.
Explore each fracture pattern in the interactive, then step through the four stages of repair.
- Closed means the skin is whole. Open (compound) means the bone breaks the skin and risks infection.
- Patterns include transverse, oblique, spiral, comminuted, impacted, and greenstick.
- Healing runs in four stages: hematoma → soft callus → hard callus → remodeling.
- Treatment is reduction (lining the ends up) and then immobilization (holding still) to protect the callus.
The chapter in one breath
- Bone is living tissue. The skeletal system does five jobs: support, protection, movement, mineral/fat storage, and blood-cell formation.
- The skeleton splits into the axial (about 80 bones) and appendicular (about 126 bones) parts, 206 in all.
- Bones are sorted by shape as long, short, flat, irregular, or sesamoid. The shape follows the job.
- A long bone has a diaphysis of compact bone around a marrow cavity. Its epiphyses are spongy. Compact bone is built of osteons.
- Four cells drive remodeling, the lifelong balance of building and dissolving bone. They are the osteogenic cell, osteoblast, osteocyte, and osteoclast.
- The matrix mixes collagen (for bending) with hydroxyapatite mineral (for hardness).
- PTH raises blood calcium and calcitonin lowers it. Together they keep it near 9–10 mg/dL. The skeleton is the calcium bank.
- Fractures come in named patterns. They heal in four stages: hematoma → soft callus → hard callus → remodeling.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Appendicular skeleton
- The bones of the arms and legs, plus the shoulder and hip girdles that attach them to the axis (about 126 bones). Built for movement.
- Axial skeleton
- The bones along the body's center line: skull, backbone, and rib cage (about 80 bones). Built for support and protection.
- Calcitonin
- A hormone from the thyroid's parafollicular (C) cells. It lowers blood calcium by holding back osteoclasts.
- Calcitriol
- The active form of vitamin D. It helps the gut absorb calcium, and PTH helps switch it on.
- Callus
- The repair bridge that forms across a break. First it is a soft (fibrocartilaginous) callus, then a hard (bony) callus.
- Compact bone
- Dense, strong bone tissue built of osteons. It forms the outer wall of bones and the shaft of long bones.
- Diaphysis
- The tube-shaped shaft of a long bone. It is compact bone around the medullary cavity.
- Endosteum
- The thin layer that lines the inside surfaces of bone: the medullary cavity and the spaces in spongy bone.
- Epiphyseal plate
- The cartilage growth plate in the metaphysis, where a long bone gets longer. It becomes the epiphyseal line when growth ends.
- Epiphysis
- The wide end of a long bone. It is spongy bone with red marrow, capped by articular cartilage.
- Hematopoiesis
- The making of blood cells (red cells, white cells, and platelets) in the red marrow of bone.
- Hydroxyapatite
- The crystal mineral of calcium and phosphate in bone matrix. It makes bone hard.
- Medullary cavity
- The hollow center of a long bone's shaft. In adults it stores fatty yellow marrow.
- Osteoblast
- The bone-building cell that makes new matrix. It becomes an osteocyte once bone surrounds it.
- Osteoclast
- A large cell with many nuclei. It dissolves bone matrix and releases its minerals into the blood.
- Osteocyte
- A mature bone cell that lives in a lacuna. It keeps the matrix healthy and senses stress on the bone.
- Osteon
- The basic building block of compact bone. It is rings of matrix (lamellae) around a central (Haversian) canal.
- Parathyroid hormone (PTH)
- The hormone from the parathyroid glands that raises blood calcium. It acts on bone, kidneys, and intestine.
- Periosteum
- The tough outer layer of a bone. It carries vessels and nerves, anchors tendons, and holds bone-making cells.
- Remodeling
- The lifelong cycle in which osteoclasts break down bone and osteoblasts build it back, in balance.
- Sesamoid bone
- A small bone set inside a tendon, such as the patella. It protects the tendon and gives it more leverage.
- Spongy bone
- Light bone tissue full of holes, made of thin struts (trabeculae). It is found in the epiphyses, and its spaces hold red marrow.
Check yourself
The Axial Skeleton
A column of bone runs down the center of your body. It holds you upright, guards your most delicate organs, and gives your muscles something to pull on. This core is the axial skeleton, made of the skull, the spine, and the rib cage, with eighty bones lined up along the long axis of your body. In this chapter, we will take that core apart piece by piece. You will name the bones of the skull and stack the twenty-six bones of the backbone. You will look closely at one vertebra to learn the plan they all share. Then you will build the cage that guards the heart and lungs. Last, you will trace the gentle S-curve that lets your spine carry your weight without bending in. By the end, a chest X-ray or a skull drawing will read like a map you already know.
By the end of this chapter you can
- Split the skeleton into its axial and appendicular parts, and list what belongs in each.
- Name the eight cranial and fourteen facial bones, and find the main sutures (seams) of the skull.
- List the five regions of the backbone and the number of bones in each.
- Label the parts of a typical vertebra, and tell what the body, arch, and processes each do.
- Sort the ribs into true, false, or floating, and name the three parts of the breastbone.
- Tell primary spine curves from secondary ones, and spot kyphosis, lordosis, and scoliosis.
- Link each axial bone to the organ or job it protects or supports.
Section 1Axial vs appendicular
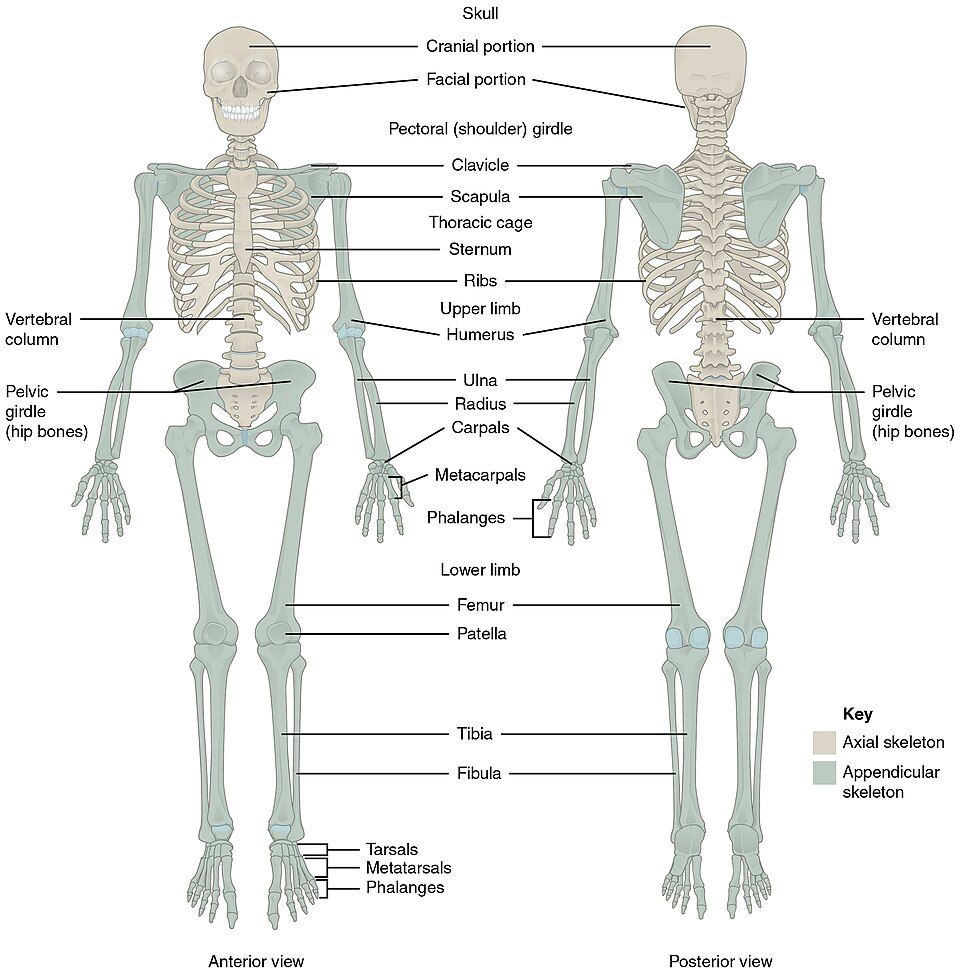
Two skeletons in one
An adult body has 206 bones. Anatomists sort every one of them into two groups. The axial skeleton forms the center line, or axis, of your body. This line runs from the top of the skull, down the spine, and out through the ribs. The axial skeleton has 80 bones. Its job is protection and support. It holds the brain, the spinal cord, the heart, and the lungs, and it gives your trunk a firm core.
The appendicular skeleton is everything that hangs off that center line. These are the appendages, or limbs. It has 126 bones, which make up your arms and legs, plus the two girdles (shoulder and hip) that hold the limbs on. Its job is movement. Here is a quick way to tell them apart. If a bone sits on the midline or wraps around an organ, it is axial. If it helps you reach, walk, or grip, it is appendicular.
What the axial 80 are made of
The eighty axial bones fall into just three groups, and this whole chapter is a tour of them. The skull and the bones that go with it make up twenty-nine. The vertebral column, or backbone, has twenty-six. The thoracic cage, or rib cage, has twenty-five. See how each group matches the organ it guards. The skull wraps the brain, the vertebrae wrap the spinal cord, and the rib cage wraps the heart and lungs. In a real sense, the axial skeleton is your body's suit of armor.
| Region | Bones in it | Count |
|---|---|---|
| Skull | 8 cranial + 14 facial bones | 22 |
| Bones that go with the skull | 6 ear bones (auditory ossicles) + 1 hyoid bone | 7 |
| Vertebral column | 24 vertebrae + sacrum + coccyx | 26 |
| Thoracic cage | 24 ribs (12 pairs) + 1 sternum | 25 |
| Axial total | — | 80 |
Switch between the two skeletons below. Watch the axial and appendicular bones light up in turn.
- The skeleton splits into two parts. The axial part has 80 bones on the center line, for protection and support.
- The appendicular part has 126 bones in the limbs and girdles, for movement.
- The axial skeleton has three parts: the skull, vertebral column, and thoracic cage.
- Axial bones sit on the midline. They guard the brain, spinal cord, heart, and lungs. 80 + 126 = 206.
Section 2The skull
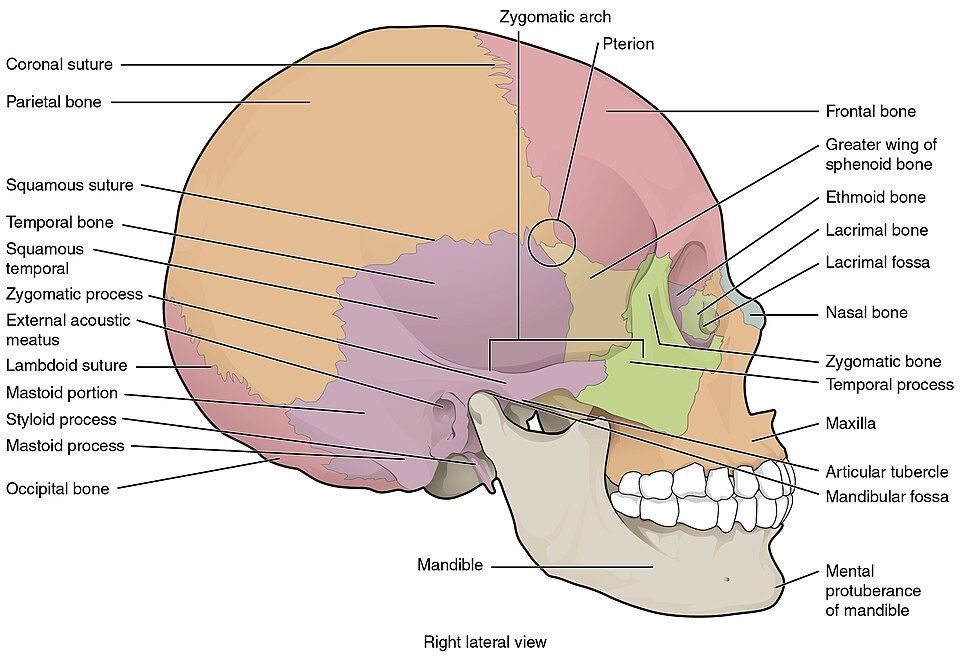
Eight bones cradle the brain
The skull has 22 bones, and the first split is between the part around the brain and the part that builds the face. The cranium is the braincase, and it is made of eight cranial bones. Four of them are single bones on the midline:
The frontal bone is your forehead. The occipital bone is the back and base of the skull. It has a large hole, the foramen magnum, where the spinal cord leaves the skull. The sphenoid bone is shaped like a bat. It spans the floor of the skull and locks the other bones together, like the keystone of an arch. The ethmoid bone is a thin, fragile bone between the eyes. It forms part of the nose cavity.
The other two come in pairs. The two parietal bones form the roof and upper sides. The two temporal bones sit low on each side and hold the ears. Together these bones form a hard dome whose only job is to keep the brain safe.
Fourteen bones build the face
The 14 facial bones give your face its shape, and they frame the openings for seeing, smelling, and eating. Most come in pairs:
The two maxillae form the upper jaw. They join at the midline. The two zygomatic bones are your cheekbones. The two nasal bones form the bridge of the nose. The two lacrimal bones are tiny bones at the inner corner of each eye. They help drain tears. The two palatine bones form the back of the hard palate, the roof of your mouth. The two inferior nasal conchae are curled shelves inside the nose.
Two facial bones are single. The vomer forms the lower part of the wall between your nostrils (the nasal septum). The mandible is the lower jaw. The mandible is special, because it is the only freely movable bone in the skull. It meets the temporal bone at the jaw joint (the temporomandibular joint), which lets you chew and speak.
| Group | Single bones | Paired bones |
|---|---|---|
| Cranial (8) | Frontal, occipital, sphenoid, ethmoid | Parietal (2), temporal (2) |
| Facial (14) | Mandible, vomer | Maxilla (2), zygomatic (2), nasal (2), lacrimal (2), palatine (2), inferior nasal concha (2) |
Sutures, sinuses, and the infant skull
The cranial bones do not meet at smooth joints. Instead, they lock together along jagged seams that cannot move. These seams are called sutures, and they fit together like the teeth of a zipper. Four are worth naming:
The coronal suture runs between the frontal and parietal bones. The sagittal suture runs front to back between the two parietal bones. The lambdoid suture runs between the parietal bones and the occipital bone. The squamous suture runs along the top of each temporal bone.
In a newborn, these seams have not closed yet. The gaps between them are the fontanelles, or "soft spots." They let the skull bend a little during birth and grow as the brain grows.
Some skull bones are also hollowed out by air-filled spaces. These are the paranasal sinuses, the air pockets around the nose. They make the skull lighter and help your voice ring and carry.
Tap any bone on the side view to find it and name it.
- The skull has 22 bones: 8 cranial bones around the brain and 14 facial bones that shape the face.
- The single cranial bones are the frontal, occipital, sphenoid, and ethmoid. The parietal and temporal bones come in pairs.
- The mandible is the only skull bone that moves freely.
- Cranial bones meet at sutures that cannot move. In babies these are still open as fontanelles.
Section 3The vertebral column
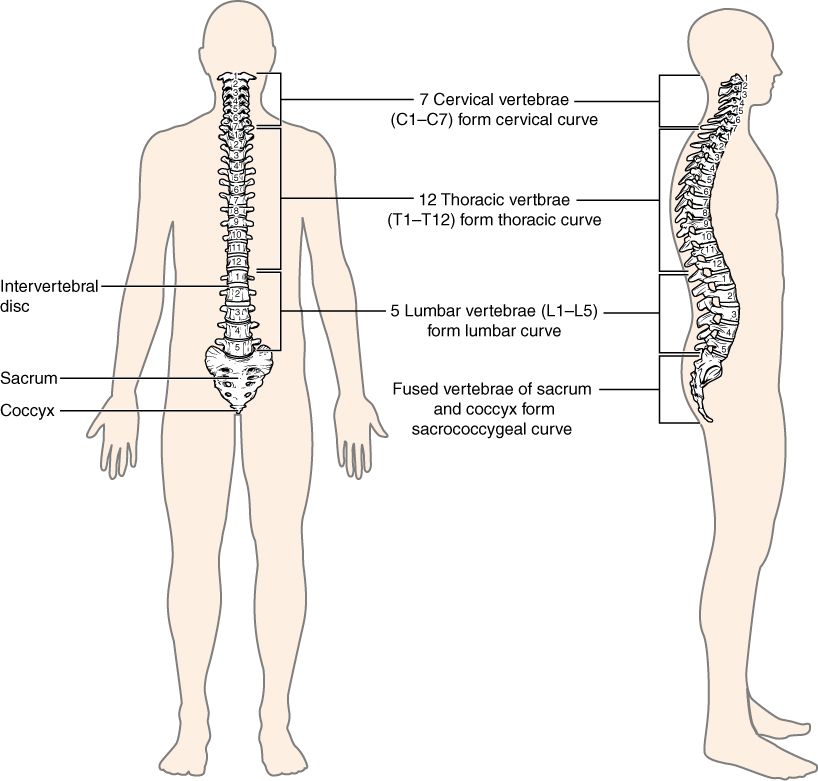
Twenty-six bones, five regions
The vertebral column is your backbone, a stack of 26 bones that runs from the base of the skull to the hips. It does three big jobs at once. It supports your head and trunk. It protects the spinal cord that runs down its center. And it bends enough to let you bend and twist.
Each bone in the stack is a vertebra, and together they are called vertebrae. They are grouped into five regions from top to bottom. A classic memory trick links the counts to mealtimes. Eat breakfast at 7, lunch at 12, and dinner at 5:
| Region | Bones | Where it is & notes |
|---|---|---|
| Cervical | 7 (C1–C7) | The neck. C1 is the atlas, and C2 is the axis. |
| Thoracic | 12 (T1–T12) | The chest. Each one holds a pair of ribs. |
| Lumbar | 5 (L1–L5) | The lower back. These are the largest and carry the most weight. |
| Sacral | 1 (5 fused) | The sacrum. It joins the hip bones. |
| Coccygeal | 1 (4 fused) | The coccyx, or tailbone. |
A child actually starts with 33 separate vertebrae. As you grow, five of them fuse into one sacrum and four more fuse into the coccyx, so the adult total ends up at 26. Notice a pattern, too. The vertebrae get steadily larger as you move down the column. That is because each lower bone carries the weight of everything above it. The lumbar vertebrae hold up the whole upper body, so they are the biggest and bulkiest of all.
Discs, the cushions between
From C2 downward, a pad called an intervertebral disc sits between each pair of vertebrae. It has a tough outer ring of fibers, the anulus fibrosus. That ring wraps around a soft, jelly-like center, the nucleus pulposus. Think of a jelly donut, and you have 23 of them in your spine.
The discs do two jobs. They act as shock absorbers that soften the jolt of every step. They also form joints that move a little, so the spine can bend. Sometimes the soft center pushes out through a weak spot in the ring. This is a herniated ("slipped") disc. It can press on a nearby spinal nerve and send pain shooting down an arm or leg.
Tap each region to pick it out and see its vertebrae.
- The column has 26 bones in five regions: 7 cervical, 12 thoracic, 5 lumbar, plus the fused sacrum and coccyx. Remember 7–12–5.
- Vertebrae get larger as you go down, because they carry more weight. The lumbar vertebrae are the largest.
- Intervertebral discs cushion the spine and let it move. A herniated disc can press on a spinal nerve.
Section 4A typical vertebra
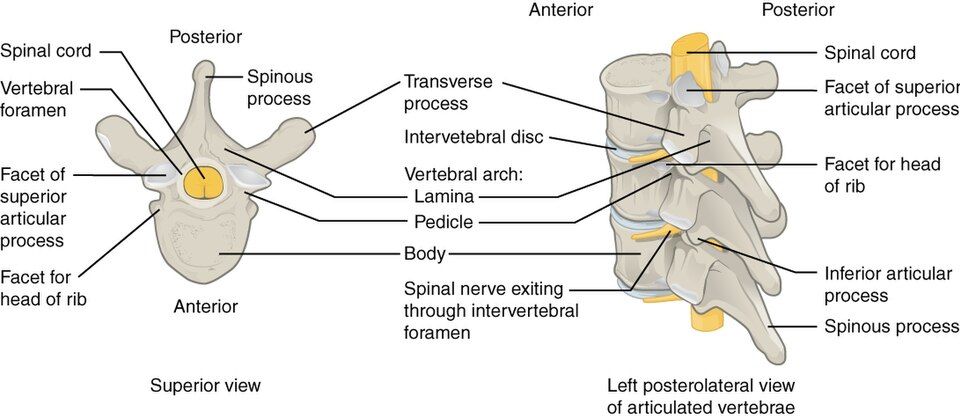
The body: the weight-bearer
Vertebrae look different from region to region, but they all share one basic plan. The front part of every vertebra is the body, also called the centrum. It is a thick, round block of bone that faces the front (anterior) and does the heavy lifting. The bodies stack on top of each other, with discs between them. Together they form a sturdy pillar that carries the weight of your head and trunk. This is why the bodies get bigger toward the lower back. The lower you go, the more weight there is to hold up.
The arch: the shield
Behind the body is the vertebral arch, a ring of bone that sticks out toward the back. Two short walls rise from the body, and these are the pedicles. Two flat plates form the roof and meet in the middle, and these are the laminae.
The body in front and the arch behind surround a hole. This hole is the vertebral foramen. When all the vertebrae are stacked, these holes line up to form one long tunnel, the vertebral canal. This bony tunnel shelters the spinal cord along its whole length. So the arch works like the spine's version of the skull, and its job is pure protection.
The processes: the handles
Seven bony knobs called processes stick out from the arch, and they work as levers and joints. The single spinous process points straight back. These are the bumps you feel down the middle of your back. The two transverse processes stick out to the sides. Muscles and ligaments grab onto the spinous and transverse processes.
The last four are the paired superior and inferior articular processes. "Superior" means upper, and "inferior" means lower. Each has a smooth, flat surface called a facet. The facets form joints with the vertebra just above and just below, which links the whole column together.
| Part | Number | Job |
|---|---|---|
| Body (centrum) | 1 | Carries weight. Faces the front. |
| Pedicles + laminae | 2 + 2 | Form the vertebral arch |
| Vertebral foramen | 1 | Hole that the spinal cord runs through |
| Spinous process | 1 | Points back. Muscles and ligaments attach here. |
| Transverse processes | 2 | Point to the sides. Muscles and ligaments attach here. |
| Articular processes | 4 | Form joints with the vertebrae above and below |
Look straight down on a vertebra. Tap each part to name it.
- Every vertebra has a weight-bearing body in front. Behind it is a protective arch, made of pedicles and laminae.
- The body and arch surround the vertebral foramen. Stacked up, these holes form the vertebral canal, which holds the spinal cord.
- The spinous and transverse processes hold muscles. The articular processes form joints with the vertebrae next to them.
Section 5The thoracic cage
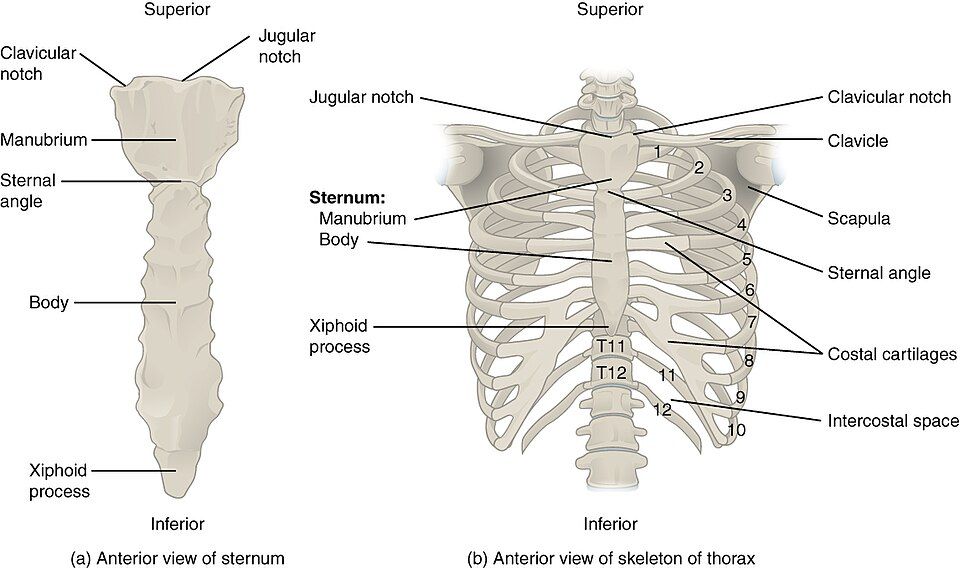
The sternum: the breastplate
The front of the chest is held in place by the sternum, or breastbone. It is a flat bone shaped like a dagger, with three parts. The wide manubrium sits on top and joins the collarbones. The long body forms the middle. The small xiphoid process is the pointed tip at the bottom, and it starts out as cartilage.
Where the manubrium meets the body, there is a small ridge. This is the sternal angle, also called the angle of Louis. You can feel it through your skin, and it lines up with the second rib. So doctors and nurses use it as a starting point for counting ribs and placing a stethoscope.
Twelve pairs of ribs: true, false, and floating
You have 12 pairs of ribs, which curve from the spine in back around to the front of the chest. Every rib joins a thoracic vertebra in back. But ribs differ in how they reach the sternum in front, or if they reach it at all. That is how we sort them:
The true ribs are pairs 1–7. Each one joins the sternum directly by its own strip of costal cartilage. This is a strip of bendy tissue that links a rib to the breastbone. The false ribs are pairs 8–12. They do not reach the sternum directly. Pairs 8–10 join the costal cartilage of the rib just above them. The last two pairs, 11 and 12, have no front attachment at all. They are called floating ribs, and they end freely in the muscles of the back wall.
| Type | Rib pairs | How they attach in front |
|---|---|---|
| True ribs | 1–7 | Straight to the sternum, each by its own costal cartilage |
| False ribs | 8–10 | Not directly. They join the costal cartilage of the rib above. |
| Floating ribs | 11–12 | None. They do not attach to the sternum. |
A cage that breathes
The thoracic cage is not a solid box. It is a bendable basket that moves with every breath. When you breathe in, muscles lift the ribs up and out. This makes your chest bigger, so the lungs have room to fill with air. When you breathe out, the ribs drop back down. All the while, the cage shields the heart, lungs, and great vessels (the largest blood vessels) inside it. It also gives your breathing and upper-body muscles a frame to pull on, so it is both armor and machine in one.
Tap the sternum, the spine, and each group of ribs to see how the cage fits together.
- The sternum has three parts: the manubrium, body, and xiphoid process. The sternal angle marks the second rib.
- Ribs 1–7 are true ribs that join the sternum directly. Ribs 8–10 are false ribs that join through the rib above. Ribs 11–12 are floating ribs with no front attachment.
- The cage protects the heart and lungs. It expands with each breath.
Section 6Spinal curvatures
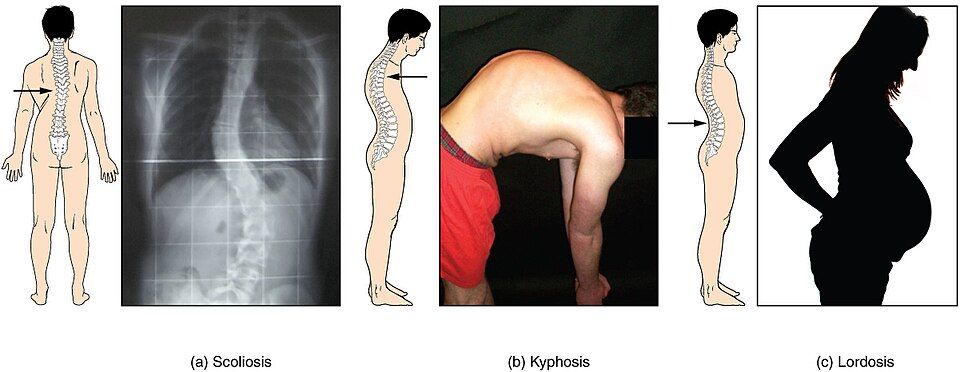
Four curves, two born and two learned
Seen from the side, a healthy spine is not straight. It makes a gentle S-shape with four curves. These curves balance your weight over your hips, and they act like a spring that softens every step.
Two of them are primary curves, which you have at birth. They match the curled-up shape of a baby in the womb. They are the thoracic curve (in the chest) and the sacral curve (in the pelvis). Both bend away from the front, so they are hollow in front.
The other two are secondary curves. They form after birth, as a baby learns to hold up its head and then to walk. The cervical curve appears when a baby starts to lift its head. The lumbar curve appears when a toddler stands and walks. Together, the four curves let the spine carry a heavy head and trunk without tipping over.
| Curve | Type | When it appears |
|---|---|---|
| Cervical | Secondary | When a baby lifts its head |
| Thoracic | Primary | There at birth |
| Lumbar | Secondary | When a toddler stands and walks |
| Sacral | Primary | There at birth |
When curves go wrong
The curves are healthy when they are gentle. But a curve can become too deep or bend the wrong way, and then it gets a medical name.
Kyphosis is a thoracic curve that is too deep. It gives a rounded, hunched upper back, sometimes called "hunchback." It is common in older adults with osteoporosis (weak, thin bones). Lordosis is a lumbar curve that is too deep. The lower back sways inward too much. This is called "swayback." Scoliosis is different from both. It is a sideways (lateral) curve of the spine. Seen from behind, the spine bends into a C or an S shape.
Children are checked for scoliosis at school. Finding it early, while the skeleton is still growing, gives the best chance to fix it.
Compare the normal S-curve with kyphosis, lordosis, and scoliosis side by side.
- The spine has four curves. The primary curves (thoracic, sacral) are there at birth.
- The secondary curves (cervical, lumbar) form later, as a baby lifts its head and learns to walk.
- Kyphosis is a thoracic curve that is too deep. Lordosis is a lumbar curve that is too deep. Both are front-to-back curves.
- Scoliosis is an abnormal lateral (sideways) curve. Children are checked for it while they grow.
The chapter in one breath
- The skeleton splits in two. The axial part has 80 bones in the skull, spine, and rib cage, for protection and support. The appendicular part has 126 bones in the limbs and girdles, for movement.
- The skull has 22 bones: 8 cranial bones around the brain and 14 facial bones. The mandible is the only one that moves. The others are joined by sutures that do not move.
- The vertebral column has 26 bones in five regions: 7 cervical, 12 thoracic, 5 lumbar, plus the fused sacrum and coccyx. Discs cushion the bones.
- Every vertebra has a weight-bearing body. It has an arch that surrounds the vertebral foramen. It also has processes for muscles and joints.
- The thoracic cage is the three-part sternum plus 12 pairs of ribs. The ribs are true, false, and floating. The cage guards the heart and lungs and moves with each breath.
- The spine's four curves form a springy S. The thoracic and sacral curves are primary. The cervical and lumbar curves are secondary. Problem curves are kyphosis, lordosis, and the sideways scoliosis.
- One theme runs through it all. The axial skeleton is armor for your most vital organs.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back when a word trips you up.
- Appendicular skeleton
- The 126 bones of the limbs and the two girdles (shoulder and hip) that hold them on. They are built for movement.
- Atlas (C1)
- The first neck vertebra. It holds up the skull and lets your head nod "yes."
- Axial skeleton
- The 80 bones along the center line of the body: the skull, spine, and rib cage. They protect and support.
- Axis (C2)
- The second neck vertebra. It has a peg that points up and lets your head turn to say "no."
- Coccyx
- The small tailbone at the bottom of the spine. It is made of four fused vertebrae.
- Costal cartilage
- The strip of cartilage that links a rib to the sternum. It joins directly, or through the rib above.
- Cranial bones
- The eight skull bones that surround the brain. They are the frontal, occipital, sphenoid, and ethmoid, plus the paired parietals and temporals.
- Facial bones
- The fourteen skull bones that shape the face. They frame the eyes, nose, and mouth.
- Floating ribs
- Rib pairs 11 and 12. They attach only to the vertebrae in back and have no front connection.
- Fontanelle
- A soft gap of tough tissue between a baby's skull bones. It lets the skull bend at birth and grow with the brain.
- Foramen magnum
- The large hole in the occipital bone. Here the spinal cord joins the brain.
- Intervertebral disc
- A pad of tough cartilage between two vertebral bodies. It absorbs shock and lets the spine move.
- Kyphosis
- A thoracic curve that bends back too far. It gives a hunched upper back.
- Lordosis
- A lumbar curve that bends forward too far. It gives an overdone swayback.
- Mandible
- The lower jaw. It is the only skull bone that moves freely.
- Manubrium
- The wide top part of the sternum. It forms joints with the collarbones (clavicles) and the first ribs.
- Sacrum
- A triangle-shaped bone made of five fused vertebrae. It joins the spine to the hip bones.
- Scoliosis
- An abnormal sideways (lateral) curve of the spine.
- Sternal angle
- The ridge you can feel where the manubrium meets the body of the sternum. It lines up with the second rib.
- Suture
- A joint between two cranial bones. The bones lock together and cannot move.
- Vertebral foramen
- The central hole of a vertebra, formed by the body and arch. The spinal cord runs through it.
- Xiphoid process
- The small pointed tip at the bottom of the sternum. It is a key landmark for CPR.
Check yourself
The Appendicular Skeleton
Think of the axial skeleton as the central mast of your body. The appendicular skeleton is everything that hangs off that mast and lets you act on the world. It includes the arms that reach and grip and the legs that carry you and spring. It also includes two bony girdles, which are frames that bolt the limbs to the trunk. This part of the skeleton has 126 bones, and almost every one of them is a lever built for movement. In this chapter, we work outward from each girdle to the fingertips and toes. Along the way, you will see one theme again and again. The shoulder is built for freedom, and the hip is built for strength. The whole design is a set of trade-offs between the two. Learn the bones in this order, and the hand and foot will make sense. With 27 and 26 bones each, they stop being a jumble and become a clear map.
By the end of this chapter you can
- Define the appendicular skeleton, list its four divisions, and account for all 126 bones.
- Name the two bones of the pectoral girdle. Explain why the sternoclavicular joint is the only bony link between the arm and the axial skeleton.
- Name the bones of the upper limb (humerus, radius, and ulna), and place the radius on the thumb side.
- Sort the 27 bones of the hand and wrist into carpals, metacarpals, and phalanges, and name the eight carpals.
- Describe how three bones fuse to form each hip bone. Explain why the hip is steadier than the shoulder, and why the shoulder moves more freely.
- Compare the male and female pelvis, and explain how the female pelvis is shaped for childbirth.
- Name the bones of the lower limb, and tell the weight-bearing tibia from the fibula, which carries almost no weight.
- Sort the 26 bones of the foot and ankle into tarsals, metatarsals, and phalanges. Explain how the foot's arches absorb shock.
Section 1The pectoral girdle
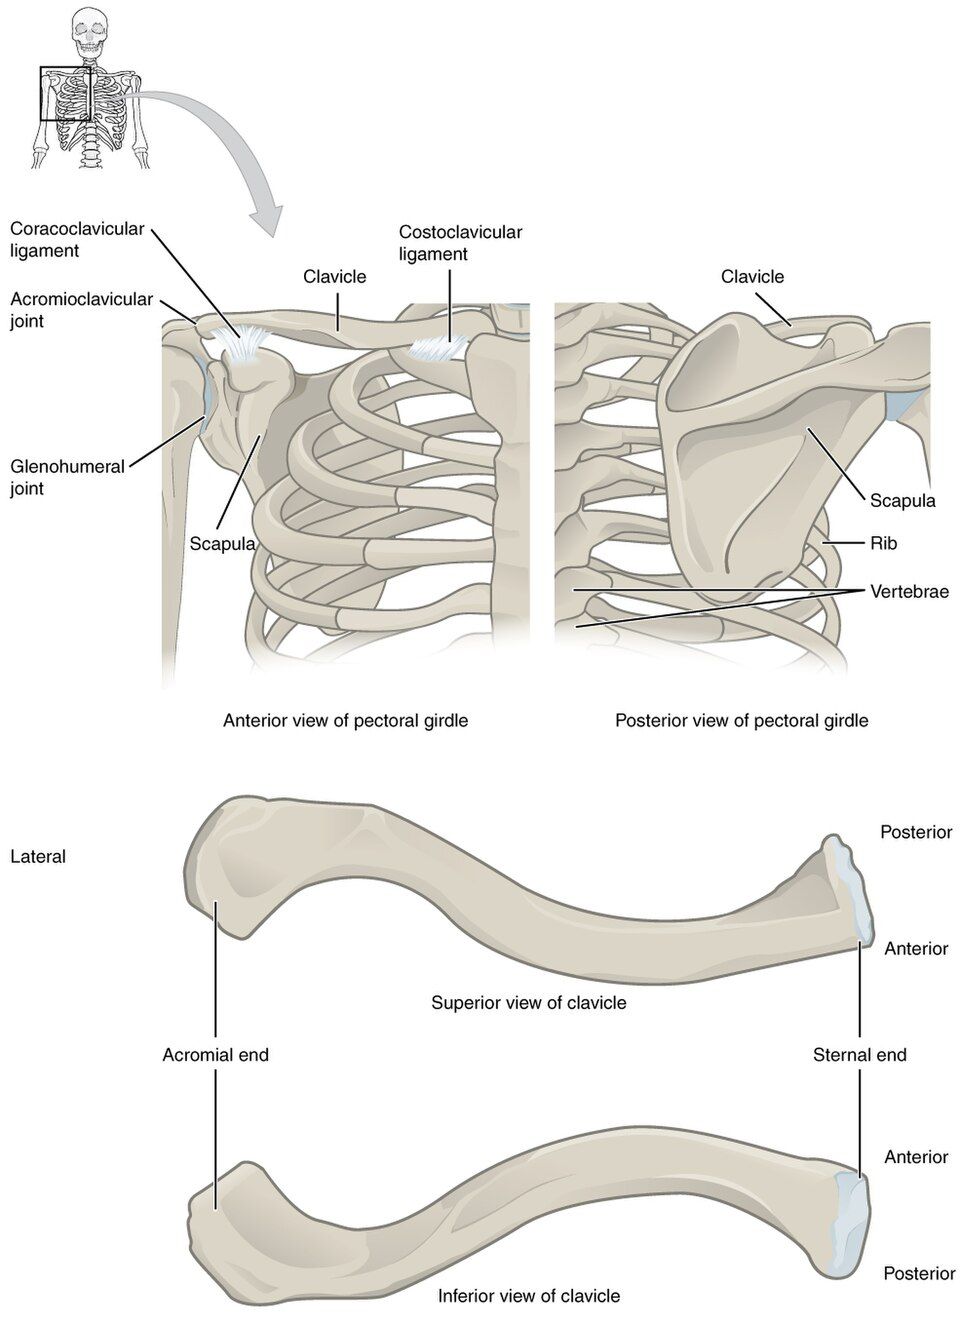
Two bones, one clever compromise
The pectoral girdle is your shoulder girdle. It is the frame that connects each arm to your trunk. It has only two bones on each side. The clavicle (collarbone) is in front, and the scapula (shoulder blade) is in back.
What is surprising is how loosely the whole arm is attached to the rest of the skeleton. The entire arm hangs from the axial skeleton at one small joint. This is the sternoclavicular joint, where the inner end of the clavicle meets the top of the breastbone (the manubrium of the sternum). The scapula is not joined by bone to the ribs or spine at all. It floats on the back of the rib cage, and only muscles hold it in place.
This loose setup is a trade. The shoulder gives up steadiness to gain a huge range of motion, which means how far a joint can move. You can swing your arm around in almost a full circle in every direction. The price is that the shoulder is one of the easiest joints in the body to dislocate, or pop out of place.
The clavicle: a slender strut
The clavicle is an S-shaped bone that works like a brace. It holds the shoulder out and away from the chest, so the arm can swing freely. Its rounded inner end is the sternal (medial) end, and it forms a joint with the sternum. Its flat outer end is the acromial (lateral) end. It meets a part of the scapula called the acromion at the acromioclavicular (AC) joint.
The clavicle is thin, and it sits right under the skin with nothing to pad it. So it is the most frequently fractured bone in the body. It usually breaks in its middle third. This often happens when someone falls onto an outstretched arm or onto the tip of the shoulder.
The scapula: a triangle of landmarks
The scapula is a flat, triangle-shaped bone. It is covered with bumps and ridges where muscles attach. A ridge called the spine runs across its back. On the outer side, the spine ends in the acromion, which is the bony tip of your shoulder that you can feel. A hook called the coracoid process curves forward like a bent finger. It anchors muscles and ligaments.
The most important feature is the glenoid cavity, also called the glenoid fossa. This is a shallow socket on the outer corner of the scapula. The rounded head of the upper arm bone (humerus) fits into it to form the shoulder joint. That shallow socket is the key to the whole design. It lets the arm bone swing widely, but it also lets the head slip out too easily. Picture a ball resting on a saucer instead of sitting in a cup.
| Bone / feature | What it is | Why it matters |
|---|---|---|
| Clavicle | S-shaped collarbone at the front of the girdle | Holds the shoulder out. It is the bone broken most often. |
| Scapula | Triangle-shaped shoulder blade at the back | Held on only by muscles. It carries the socket for the arm. |
| Glenoid cavity | Shallow socket on the scapula | Holds the head of the humerus. Shallow means it moves a lot but is not steady. |
| Acromion | Outer tip of the spine of the scapula | Forms the point of the shoulder. It joins the clavicle. |
| Sternoclavicular joint | Where the clavicle meets the sternum | The only bony joint that links the arm to the axial skeleton |
Explore both bones and their landmarks in the interactive below.
- The pectoral girdle has just two bones on each side, the clavicle and the scapula.
- The arm's only bony link to the axial skeleton is the sternoclavicular joint. The scapula floats on muscle.
- The glenoid cavity is shallow. It gives up steadiness for a huge range of motion.
- The clavicle is the most commonly fractured bone in the body.
Section 2Bones of the upper limb
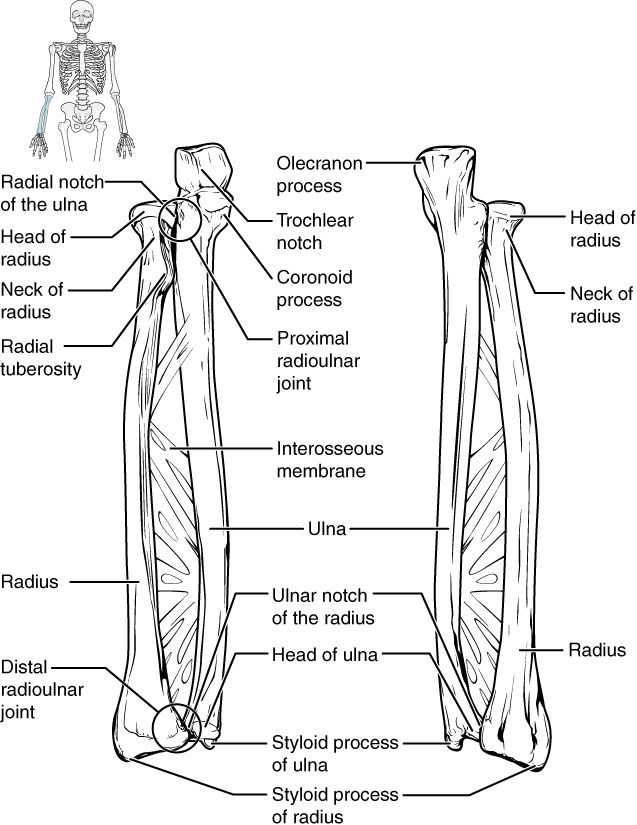
Three long bones between shoulder and wrist
Each upper limb has 30 bones, but three big long bones do most of the work of holding it up. The upper arm is called the brachium, and it has one bone, the humerus. The forearm is called the antebrachium, and it has two bones side by side, the radius and the ulna.
To tell them apart, use the anatomical position. That means standing with your palms facing forward. In this position, the radius is on the thumb (lateral) side. The ulna is on the little-finger (medial) side. Here is a phrase that sticks: the radius rotates around the ulna, and the radius is on the same side as the thumb.
The humerus and the elbow
The humerus is the long bone of the upper arm. Its rounded head fits into the glenoid cavity at the shoulder. Just below the head is the surgical neck. This is a common place for breaks, and it sits very close to an important nerve (the axillary nerve). Farther down the shaft is the deltoid tuberosity, a rough bump where the deltoid muscle attaches.
At the elbow end, two rounded surfaces form the joint. The capitulum meets the radius. The trochlea is shaped like a pulley, and it grips the ulna. On either side of them are two bumps, the medial and lateral epicondyles. The ulnar nerve runs behind the inner (medial) one, in a shallow groove. There it lies just under the skin, with no muscle to cover it. So when you bump that spot, you press right on the nerve. A jolt shoots down your forearm. This is your "funny bone."
Radius and ulna: a rotating pair
The two forearm bones are joined along their length by a sheet of tough tissue, the interosseous membrane. They also meet at small joints near the top and bottom. This setup lets the forearm do a neat trick. It can turn the palm up, which is supination, or turn it down, which is pronation. In pronation, the radius turns and crosses over the ulna.
At the elbow, the ulna is the main partner. Its olecranon forms the bony point of your elbow. Its trochlear notch wraps around the trochlea of the humerus, like a wrench on a bolt. At the wrist, the radius takes over. It is the forearm bone that forms most of the joint with the wrist bones (carpals). Both bones end in a pointed tip called a styloid process.
| Bone | Where it is | Main job |
|---|---|---|
| Humerus | Upper arm (brachium) | Its head fits the glenoid cavity. Its lower end forms the elbow. |
| Radius | Forearm, thumb (lateral) side | Turns during pronation and supination. Forms the wrist joint. |
| Ulna | Forearm, pinky (medial) side | Its olecranon forms the point of the elbow. Keeps the forearm steady. |
Tap each of the three bones. Then turn the forearm from supination to pronation.
- The upper limb has three long bones: the humerus in the upper arm, and the radius and ulna in the forearm.
- With palms facing forward, the radius is lateral (thumb side) and the ulna is medial (pinky side).
- The ulna is the main bone at the elbow (the olecranon). The radius is the main bone at the wrist, and it does the turning.
Section 3The hand & wrist
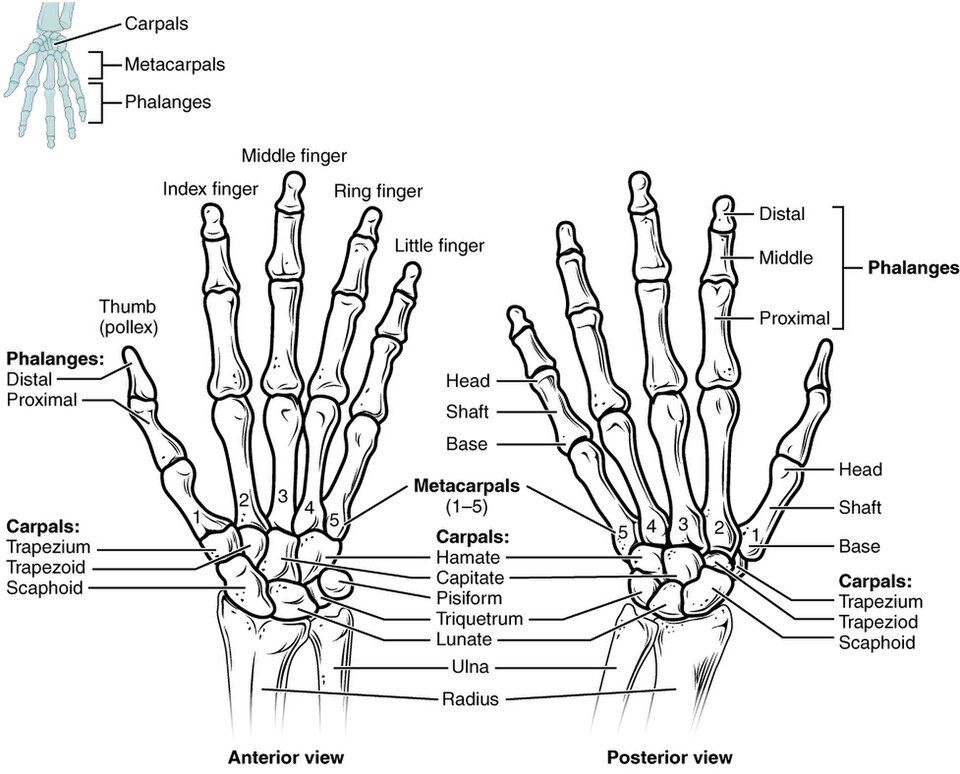
Twenty-seven bones in three groups
Your hand is the most skillful part of your body. That skill comes from packing 27 bones, and all the joints between them, into a small space. They sort neatly into three groups, from the wrist outward. There are 8 carpals in the wrist, 5 metacarpals in the palm, and 14 phalanges in the fingers. Learn those three numbers (8, 5, 14) in order, and you know the whole hand.
The carpals: eight little stones
The carpals are eight small wrist bones set in two rows of four. Ligaments bind them tightly, so the wrist bends as one unit. Start on the thumb side of the row nearest the forearm, then move to the row nearest the fingers. In that order, they are the scaphoid, lunate, triquetrum, pisiform, then the trapezium, trapezoid, capitate, hamate. A classic memory trick keeps the order: "Sally Left The Party To Take Cathy Home."
The scaphoid needs special attention. It is the carpal bone that breaks most often, usually in a fall onto an outstretched hand. Its blood supply enters from only one end. So a break can cut off blood to part of the bone, and that part can die.
Metacarpals and phalanges
The metacarpals are the five bones of the palm. They are numbered 1 to 5, starting at the thumb. Their rounded ends near the fingers are your knuckles. The thumb's metacarpal meets the trapezium at a saddle joint, shaped like a rider sitting in a saddle. This special joint lets the thumb swing across the palm to touch the other fingers. This is the opposable grip that makes the human hand so useful.
The phalanges are the finger bones. Each finger has three: proximal (nearest the palm), middle, and distal (at the tip). But the thumb, or pollex, has only two. That makes 14 per hand. (One finger bone is called a phalanx.)
| Group | Count | Where it is & notes |
|---|---|---|
| Carpals | 8 | Wrist, in two rows of four. The scaphoid is the one broken most often. |
| Metacarpals | 5 | Palm, numbered 1–5 from the thumb. Their heads are the knuckles. |
| Phalanges | 14 | Each finger has 3. The thumb has only 2. |
Tap each of the three groups below: the wrist, the palm, and the fingers.
- The hand has 27 bones: 8 carpals + 5 metacarpals + 14 phalanges.
- In order, the eight carpals are the scaphoid, lunate, triquetrum, pisiform, trapezium, trapezoid, capitate, and hamate.
- Each finger has 3 phalanges, and the thumb has 2. The thumb's saddle joint lets it touch the other fingers.
Section 4The pelvic girdle
Built for strength, not freedom
The shoulder is built to move freely. The pelvic girdle, or hip girdle, is built for the opposite. Its jobs are strength and weight-bearing. It must pass the whole weight of your upper body down into your legs. It must also take the pounding of every step.
So the pelvic girdle does not float on muscle. Instead, it attaches firmly to the axial skeleton at the sacroiliac joints. These are strong joints that barely move. The girdle itself is the pair of hip bones, also called coxal bones or os coxae. Together with the sacrum and coccyx, they form the bony pelvis, a bowl of bone at the base of your trunk.
Three bones fused into one
Each hip bone starts out as three separate bones. They fuse into one bone during adolescence, as a child grows into an adult. They meet at a deep, cup-shaped socket called the acetabulum. The ilium is the large, fan-shaped upper part. Its rim, the iliac crest, is the "hip" where you rest your hands. The ischium is the lower back part. Its rough ischial tuberosity is the bone you sit on. The pubis is the front part. The two pubic bones meet in front at the pubic symphysis, a joint made of tough cartilage (fibrocartilage).
Notice how different this is from the shoulder. The acetabulum is a deep socket that grips the head of the thigh bone (femur) firmly. So the hip almost never dislocates. It is the mirror image of the shallow glenoid cavity, which moves freely.
Male and female pelvis: shaped by childbirth
The pelvis is the part of the skeleton that differs most clearly between males and females. That is because the female pelvis is shaped to let a baby pass through. Compared with the male pelvis, the female pelvis is wider and shallower. Its opening at the top, the pelvic inlet, is larger and more rounded. The angle under the pubic bones, called the subpubic angle, is also wider. In a female it is greater than 90°.
The male pelvis is narrower and heavier. Its inlet is heart-shaped, and its subpubic angle is less than 90°. These differences are reliable. So anatomists and forensic scientists use the pelvis to tell whether a skeleton is male or female.
| Feature | Female pelvis | Male pelvis |
|---|---|---|
| Overall shape | Wider, shallower, lighter | Narrower, deeper, heavier |
| Pelvic inlet | Rounded, oval, and larger | Heart-shaped and smaller |
| Subpubic angle | Wide, more than 90° | Narrow, less than 90° |
| Reason for the difference | Roomy birth canal for childbirth | — |
Tap the ilium, ischium, and pubis. Then switch between the male and female pelvis.
- The pelvic girdle is two hip bones. Each is made of the ilium + ischium + pubis, fused where they meet at the acetabulum.
- It attaches firmly to the axial skeleton at the sacroiliac joints. It is built to bear weight, not to move a lot.
- The female pelvis is wider, with a subpubic angle greater than 90°. This shape helps with childbirth.
Section 5Bones of the lower limb
The strongest bones in the body
The lower limb carries your whole body weight and powers every step. So its bones are the largest and strongest you have. Like the arm, each lower limb has 30 bones. Four of them are the big bones that hold it up. The thigh has one bone, the femur. The patella, or kneecap, guards the knee. The lower leg has two bones, the tibia and fibula. They match the radius and ulna of the forearm, but with one key difference, which we will get to soon.
Femur and patella
The femur is the longest, heaviest, and strongest bone in the body. Its ball-shaped head sits deep in the acetabulum. Below the head is the angled neck. This is where a "hip fracture" usually happens in older adults with thin bones. Two bumps, the greater and lesser trochanters, anchor strong hip muscles. A ridge down the back, the linea aspera, gives muscles more places to attach. At the knee, the femur's rounded ends, the condyles, roll on top of the tibia.
The patella is the largest sesamoid bone in the body. A sesamoid bone is a bone that forms inside a tendon. The patella sits in the tendon of the quadriceps, the big muscle on the front of the thigh. It works like a pulley. It gives the thigh muscles better leverage when you straighten your knee. It also shields the knee from a direct hit.
Tibia and fibula: one carries, one steadies
Here is how the leg differs from the forearm. In the leg, the two bones do not share the load. The tibia, or shinbone, is the thick inner (medial) bone. It carries almost all the weight. Its wide, flat top, the tibial plateau, supports the femur. Its lower end forms the medial malleolus, the bump on the inside of your ankle.
The fibula is the thin outer (lateral) bone. It carries almost no weight. Its jobs are to stabilize the ankle, or keep it steady, and to give muscles a place to attach. Its lower end forms the lateral malleolus, the bump on the outside of your ankle. In fact, the fibula does not even reach the knee. Only the tibia meets the femur there.
| Bone | Where it is | Job |
|---|---|---|
| Femur | Thigh | Longest, strongest bone. Its head fits the acetabulum. |
| Patella | Front of the knee | Largest sesamoid bone. Gives the quadriceps better leverage. |
| Tibia | Lower leg, medial | Weight-bearing shinbone. Forms the medial malleolus. |
| Fibula | Lower leg, lateral | Carries almost no weight. Steadies the ankle and forms the lateral malleolus. |
Tap each of the four bones. Then find the two malleoli at the ankle.
- The four big bones of the lower limb are the femur, patella, tibia, and fibula.
- The femur is the longest and strongest bone in the body. The patella is its largest sesamoid bone.
- The tibia (medial) bears the weight and forms the knee joint with the femur. The fibula (lateral) mainly steadies the ankle.
Section 6The foot & ankle
Twenty-six bones, built to bear weight
The foot is a lot like the hand, with three groups of bones. But it is tuned for a very different job. Instead of grabbing, it must bear weight and spring you forward. It has 26 bones. There are 7 tarsals in the ankle and heel, 5 metatarsals in the sole, and 14 phalanges in the toes. It is the same three-group plan as the hand, with slightly different numbers to remember (7, 5, 14).
The tarsals and the weight it takes
The tarsals are seven bones that form the ankle and the back of the foot. Two of them do the hard work. The talus sits on top, and the tibia and fibula grip it. It takes the body's weight from the leg and passes it down. The calcaneus, or heel bone, is the largest tarsal. It forms the heel and takes the weight when your foot hits the ground. The other five tarsals link the ankle to the sole. They are the navicular, the cuboid, and three cuneiforms.
The metatarsals are numbered 1–5, starting at the big toe. They form the sole and the ball of the foot. The phalanges are the toe bones. Each toe has three, but the big toe, or hallux, has only two. This is exactly the same pattern as the hand.
The arches: the foot's suspension
What really sets the foot apart from the hand is its arches. Ligaments and tendons hold the tarsals and metatarsals in three curves. The medial longitudinal arch is the high one along the inside of the foot. The lateral longitudinal arch runs along the outside. The transverse arch runs across the foot.
These arches make the foot a natural spring and shock absorber, like the springs in a car. They flatten a little to soak up the impact of each step. Then they spring back to push you off. When the arches drop, the result is flat feet (pes planus). This can make the feet and legs tired, because the shock absorber is gone.
| Group | Count | Where it is & notes |
|---|---|---|
| Tarsals | 7 | Ankle and heel. The talus takes weight from the leg. The calcaneus is the heel. |
| Metatarsals | 5 | Sole, numbered 1–5 from the big toe. Their heads form the ball of the foot. |
| Phalanges | 14 | Each toe has 3. The big toe (hallux) has 2. |
Tap each of the three groups (ankle, sole, and toes) below, and see the arches.
- The foot has 26 bones: 7 tarsals + 5 metatarsals + 14 phalanges.
- The talus takes weight from the leg. The calcaneus is the heel and the largest tarsal.
- Three arches make the foot a spring and shock absorber. When they fall, the result is flat feet.
The chapter in one breath
- The appendicular skeleton has 126 bones. These are the two limb girdles plus the arms and legs that hang from them.
- The pectoral girdle (clavicle + scapula) links the arm to the trunk by just one bony joint, the sternoclavicular joint. It gains freedom of movement but loses steadiness.
- The upper limb has three long bones: the humerus, the radius (thumb side), and the ulna (pinky side). The ulna leads at the elbow, and the radius leads at the wrist.
- The hand has 27 bones: 8 carpals, 5 metacarpals, and 14 phalanges. Its thumb can touch the other fingers, which makes the hand skillful.
- The pelvic girdle is two hip bones. Each is the ilium + ischium + pubis, fused at the acetabulum. It is built for strength and bearing weight. The female pelvis is shaped for childbirth.
- The lower limb has the strongest bones in the body: the femur, the patella, the weight-bearing tibia, and the steadying fibula.
- The foot has 26 bones: 7 tarsals, 5 metatarsals, and 14 phalanges. Its arches make it a spring and shock absorber.
- The whole design is a trade-off. The shoulder chooses freedom, and the hip chooses strength.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back when a word trips you up.
- Acetabulum
- The deep, cup-shaped socket on the hip bone. The head of the femur fits into it to form the hip joint.
- Appendicular skeleton
- The 126 bones of the limbs and the two girdles (pectoral and pelvic). The girdles attach the limbs to the axial skeleton.
- Calcaneus
- The heel bone. It is the largest tarsal, and it bears weight when your foot hits the ground.
- Carpals
- The eight small bones of the wrist, set in two rows of four.
- Clavicle
- The S-shaped collarbone that holds the shoulder out. It is the bone broken most often in the body.
- Femur
- The thigh bone. It is the longest, heaviest, and strongest bone in the body.
- Fibula
- The thin outer (lateral) bone of the lower leg. It carries almost no weight. It steadies the ankle and forms the lateral malleolus.
- Glenoid cavity
- The shallow socket on the scapula. The head of the humerus fits into it at the shoulder joint.
- Hip bone (os coxae)
- Also called the coxal bone. Each one is the ilium, ischium, and pubis fused together, and the pair forms the pelvic girdle.
- Humerus
- The single long bone of the upper arm. It runs from the shoulder to the elbow.
- Metacarpals
- The five bones of the palm, numbered 1 to 5 from the thumb. Their heads form the knuckles.
- Metatarsals
- The five bones of the sole of the foot, numbered 1 to 5 from the big toe.
- Patella
- The kneecap. It is the largest sesamoid bone, and it forms inside the quadriceps tendon to improve leverage.
- Pectoral girdle
- The shoulder girdle, made of the clavicle and scapula. It attaches each arm to the axial skeleton.
- Pelvic girdle
- The two hip bones. They attach the legs to the axial skeleton and bear the body's weight.
- Phalanges
- The bones of the fingers and toes. Each digit has three, except the thumb and big toe, which have two. One bone is a phalanx.
- Radius
- The outer (thumb-side) bone of the forearm. It turns during pronation and forms most of the wrist joint.
- Scapula
- The triangle-shaped shoulder blade. Only muscles hold it to the trunk, and it carries the glenoid cavity.
- Talus
- The tarsal bone that the tibia and fibula grip. It takes the body's weight from the leg.
- Tarsals
- The seven bones of the ankle and the back of the foot. They include the talus and calcaneus.
- Tibia
- The inner (medial) shinbone. It is the weight-bearing bone of the lower leg. It forms the knee joint with the femur and forms the medial malleolus.
- Ulna
- The inner (pinky-side) bone of the forearm. Its olecranon forms the point of the elbow.
Check yourself
Joints
Bones give your body its frame. But a frame that could not bend would be a statue. Any place where two bones meet is a joint, and joints are where movement starts. In this chapter you will learn the two ways to sort every joint in the body. You will meet the six shapes of the free-moving synovial joints, the ones with a pocket of fluid inside. You will open up the fluid-filled case that lets them glide. And you will learn a name for each motion your body can make. Along the way, one big idea ties it all together. There is always a trade-off between how much a joint moves and how stable it stays.
By the end of this chapter you can
- Sort any joint two ways. Sort it structurally, by what it is made of (fibrous, cartilaginous, synovial). Sort it functionally, by how much it moves (synarthrosis, amphiarthrosis, diarthrosis). Then explain how the two lists line up.
- State the mobility–stability trade-off. Use a joint's build to predict where it falls.
- Name the six types of synovial joint. Say how each one moves, and give an example from the body.
- Label the parts of a synovial joint. Explain the three jobs of synovial fluid.
- Do and name the body movements in their opposite pairs. Include the special moves of the forearm, foot, and thumb.
- Tell apart the kinds of fibrous joints (suture, syndesmosis, gomphosis). Do the same for cartilaginous joints (synchondrosis, symphysis).
- Describe how the shoulder, hip, knee, and elbow are built, and the weak spot of each.
- Link common injuries to the joint parts that fail. These include sprains, dislocations, torn menisci, and arthritis.
Section 1Two ways to classify a joint
What is a joint, and why do we sort them twice?
A joint (also called an articulation) is any place where two bones come together. It can also be where bone meets cartilage, or where a tooth meets bone. That is a huge, mixed group. The seams of the skull that never move are joints. So is the shoulder, which moves a lot. To make sense of it all, experts describe every joint in two separate ways at once. Get in the habit of giving both.
The first way is structural. It asks what holds the bones together, and is there a fluid-filled space between them? By that test there are just three kinds. Fibrous joints are held by tough, dense tissue, with no space inside. Cartilaginous joints are held by cartilage, a firm, rubbery tissue, again with no space. Synovial joints have a space filled with fluid between the bones.
The second way is functional. It asks a simpler question: how much does it move? A synarthrosis does not move. An amphiarthrosis moves a little. A diarthrosis moves freely.
Movement versus stability: the great trade-off
The two ways are not random. They match up, because what holds a joint together decides how much it can move. Tie two bones with tough fibers and you get a rock-solid joint that barely moves. That is fibrous, and most often a synarthrosis. Pad them with cartilage and you get a little give. That is cartilaginous, and most often an amphiarthrosis.
Now put a slippery, fluid-filled gap between them. They can swing freely. But now only ligaments and muscles hold them in place. That is synovial, and always a diarthrosis.
This is the most important idea in the whole chapter: mobility and stability pull against each other. Mobility means how much a joint can move. Stability means how well it stays in place. Every joint in your body sits somewhere on that scale. Its design is a deal made for the job it does.
Your skull has to guard your brain. So it gives up all movement to be as stable as it can be. Your shoulder has to throw and reach. So it gives up stability to get a huge range of motion. That is exactly why the shoulder is the joint people dislocate most.
| Functional class | Movement | Usual structure | Example |
|---|---|---|---|
| Synarthrosis | Immovable | Fibrous (some are cartilaginous) | Skull sutures; a tooth in its socket |
| Amphiarthrosis | Moves a little | Cartilaginous (some are fibrous) | Pubic symphysis; discs between the vertebrae (intervertebral discs) |
| Diarthrosis | Moves freely | Synovial | Shoulder, hip, knee, elbow, fingers |
Tap through the sorting tree in the interactive. Watch how much each joint really moves.
- Every joint is described twice. One way is by structure (fibrous / cartilaginous / synovial). The other is by function (synarthrosis / amphiarthrosis / diarthrosis).
- Structure = what holds the bones and whether there is a space. Function = how much the joint moves.
- The two ways match because the material sets the motion. Fibrous → does not move. Cartilaginous → moves a little. Synovial → moves freely.
- The big theme is the mobility–stability trade-off. More movement always costs stability.
Section 2The six synovial joints
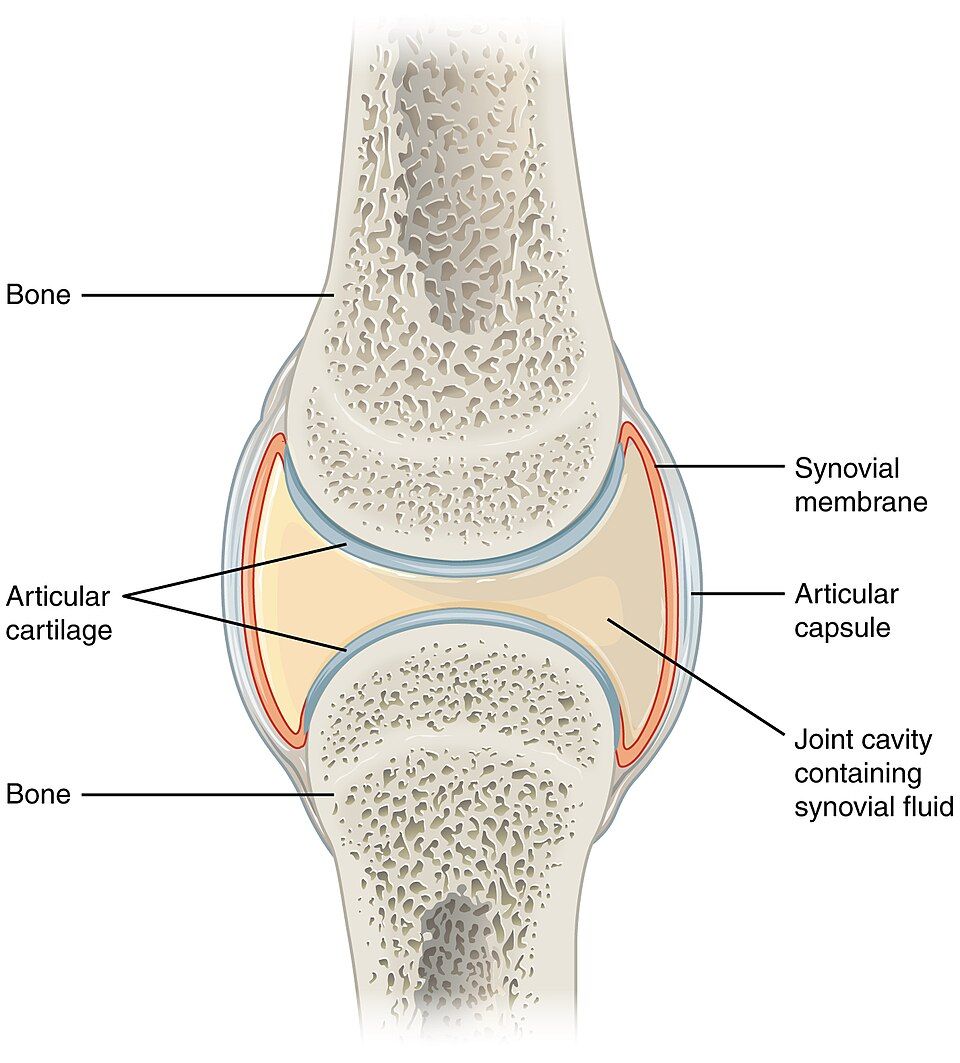
Same blueprint, six shapes
All synovial joints share the same fluid-filled design. You will see it in the next section. But the shape of the two bone ends that meet decides how the joint can move. There are six shapes, and each allows its own set of motions. A neat way to keep them straight is by their axes of movement. An axis here means a direction in which the bones can swing.
A nonaxial joint slides but does not swing. A uniaxial joint moves in one plane, or one flat path, like a door on a hinge. A biaxial joint moves in two planes. A multiaxial joint moves in all directions and can spin, too. As you go down that list, the joint can move more. And, true to this chapter's theme, it gets less stable.
| Type | Axes / movement | Where you have one |
|---|---|---|
| Plane (gliding) | Nonaxial: flat surfaces slide back and forth | Between the small wrist bones (intercarpal joints); between the facets of the vertebrae |
| Hinge | Uniaxial: bending and straightening (flexion and extension) only | Elbow, knee, finger joints |
| Pivot | Uniaxial: turning around one long axis (rotation) | Atlas–axis (shaking your head “no”); the radius at the elbow |
| Condyloid (ellipsoid) | Biaxial: flexion/extension + abduction/adduction | Knuckles (metacarpophalangeal joints); wrist |
| Saddle | Biaxial, with a wider range than condyloid | Base of the thumb (first carpometacarpal joint) |
| Ball-and-socket | Multiaxial: moves in every plane and also rotates | Shoulder and hip |
Reading the shape tells you the move
Once you can picture the shape, you can work out the motion. A hinge is a rounded end sitting in a curved trough. So it can only rock one way. Your elbow cannot swing side to side, just as a door cannot.
A ball-and-socket joint is a round head set in a cup. It can swing in any direction and spin. That is why your shoulder and hip are the two joints that move the most. The saddle joint at the base of your thumb has bones shaped like a rider on a saddle. This joint gives humans a thumb that can truly cross over to touch the fingers. It is the reason you can grip things.
Tap each of the six shapes in the interactive. See how each one moves and where you have one.
- All six synovial types share one design. The shape of the bone ends sets the movement.
- By axes: plane (nonaxial) → hinge and pivot (uniaxial) → condyloid and saddle (biaxial) → ball-and-socket (multiaxial).
- The ball-and-socket joint (shoulder, hip) moves the most. Plane joints only glide.
- The saddle joint at the base of the thumb makes the human grip possible.
Section 3Inside a synovial joint
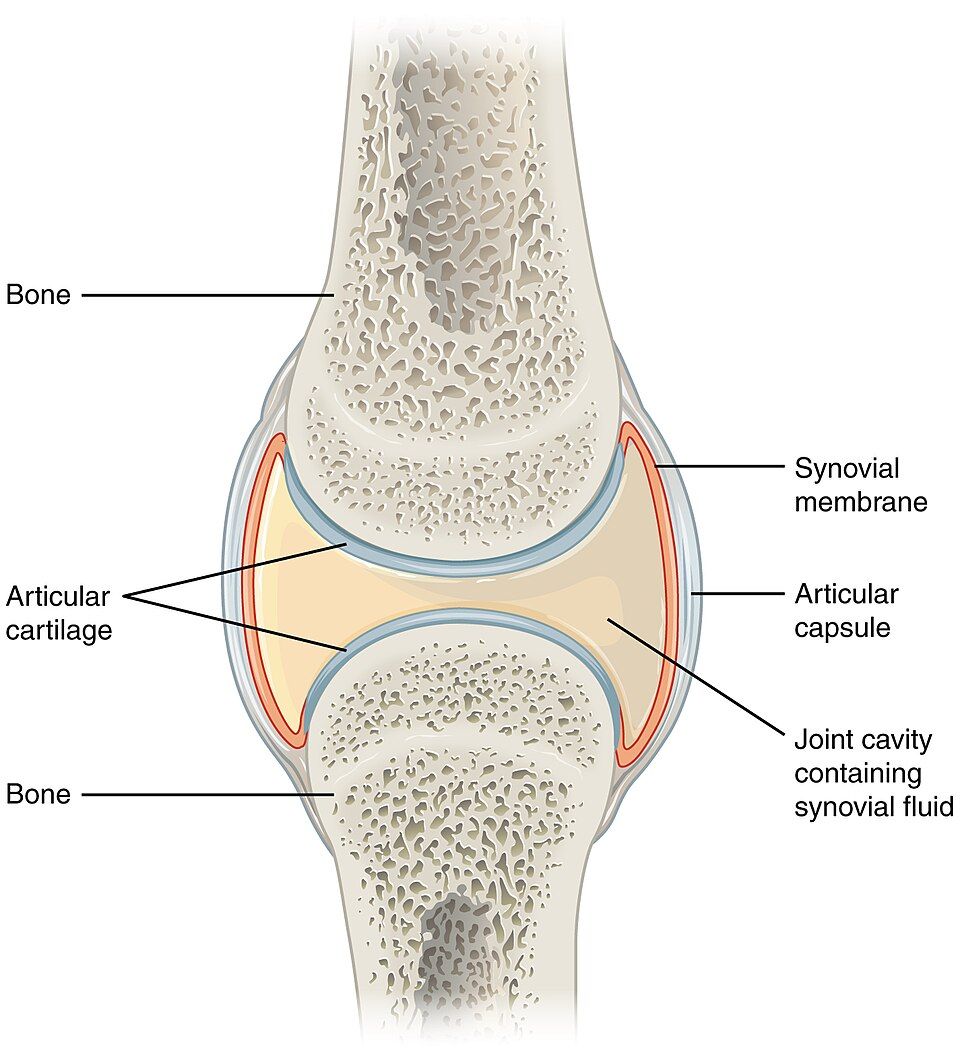
The essential parts
A synovial joint moves freely because of a small space filled with fluid. This is the joint (synovial) cavity. It sits between the two bone ends, so they never really touch. Every other part of the joint is there to guard, feed, and oil that gap. Learn these parts and you can label any synovial joint in the body.
Each bone end has a smooth cap of articular cartilage. This is glassy hyaline cartilage. It gives an almost friction-free surface and cushions the blow of every step. The whole joint is wrapped in an articular capsule with two layers.
The outer layer is the tough fibrous layer. It joins with the covering of the bones and holds everything together. The thin inner layer is the synovial membrane. It lines the space and makes the fluid inside. That fluid is synovial fluid. It fills the space like oil in a door hinge.
| Structure | What it does |
|---|---|
| Articular cartilage | Hyaline cartilage that caps each bone end; a smooth surface that absorbs shock |
| Joint (synovial) cavity | Fluid-filled space between the bones that lets them move freely |
| Articular capsule | Outer fibrous layer for strength; inner synovial membrane that makes the fluid |
| Synovial fluid | Slippery fluid full of hyaluronic acid; it oils the joint, feeds the cartilage, and absorbs shock |
| Ligaments | Bands of tough, dense tissue that tie bone to bone and make the capsule stronger |
| Bursae & tendon sheaths | Fluid-filled sacs that cushion spots where tendons or skin rub over the joint |
Synovial fluid: oil, food, and cushion
Synovial fluid does three jobs at once. First, it lubricates, or oils, the joint. Its hyaluronic acid makes it slick. So the cartilage surfaces glide with less friction than ice sliding on ice.
Second, it feeds the cartilage. Articular cartilage has no blood supply of its own. So it soaks up oxygen and food from the fluid, and it sends its waste back out into it.
Third, it absorbs shock. When you press on a joint, fluid squeezes out of the pressed cartilage. When you let go, the fluid seeps back in. This self-oiling action is called weeping lubrication. It is one reason gentle movement is good for sore joints.
Bursae: the joint's shock pads
Many joints have small, flat sacs of synovial fluid around them. These are called bursae. They sit wherever a tendon, ligament, or patch of skin would rub against bone. They work like greased cushions. If you overuse one, it can get swollen and painful. Kneeling all day or throwing overhead again and again can do this. The problem is called bursitis.
Tap each labeled part in the interactive. See how the capsule, space, cartilage, and fluid fit together.
- The key feature is a fluid-filled joint cavity that keeps the bone ends apart.
- Articular cartilage caps the bones. The articular capsule has a tough fibrous outer layer. Inside is a synovial membrane that makes the fluid.
- Synovial fluid does three jobs. It oils the joint, feeds the cartilage (which has no blood vessels), and absorbs shock.
- Bursae cushion tendons and skin over the joint. When they swell, that is bursitis. Worn cartilage causes osteoarthritis.
Section 4The movements of the body
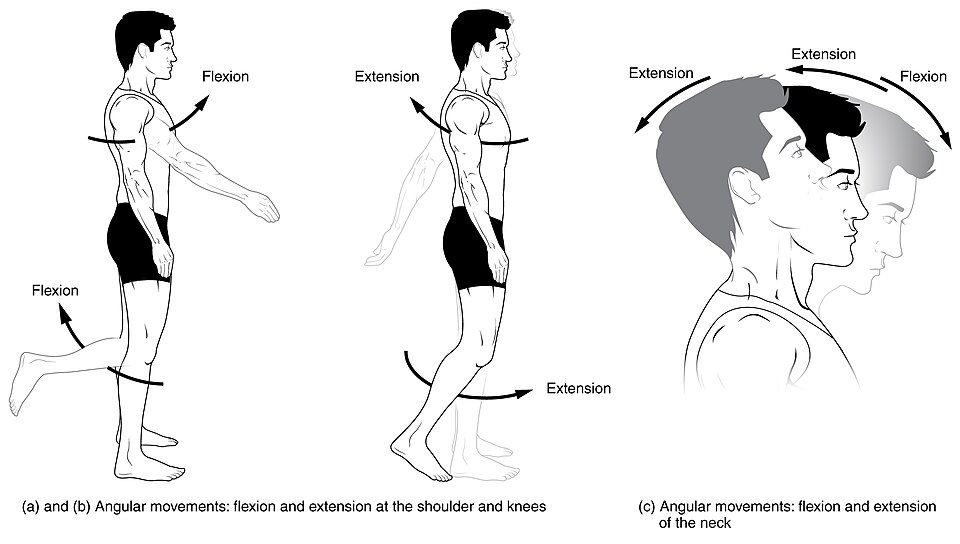
Motions come in opposite pairs
Each movement a synovial joint makes has an exact name. The best part is that the names come in opposing pairs. Learn one and you almost know its partner. All of them are described from the anatomical position. This is the same pose you met in Chapter 1: standing tall, palms facing forward.
The most common pair is flexion and extension. Flexion makes the angle at a joint smaller. Bending your elbow or curling forward at the waist are examples. Extension makes the angle bigger and straightens the joint back out. Push a joint past straight and you get hyperextension. Tilting your head back to look at the ceiling is one example.
The next pair moves limbs toward or away from the midline, the center line of the body. Abduction moves a limb away from the midline. Adduction brings it back toward the midline. Now hold your arm out and trace a full cone in the air. That is circumduction. It links flexion, abduction, extension, and adduction into one circle. Last, rotation turns a bone around its own long axis. Shaking your head “no” rotates your skull on your spine.
| Movement | What happens | Everyday example |
|---|---|---|
| Flexion / Extension | Make the joint angle smaller / bigger | Bending vs. straightening the elbow |
| Abduction / Adduction | Away from / toward the midline | Raising the arm out to the side and back down |
| Circumduction | Moving a limb in a cone-shaped circle | Swinging the whole arm around like a windmill |
| Rotation | Turning a bone on its long axis | Shaking the head “no” |
| Supination / Pronation | Palm turned up / palm turned down | Turning a doorknob back and forth |
| Dorsiflexion / Plantar flexion | Toes up toward the shin / toes pointing down | Standing on your heels vs. on your toes |
| Inversion / Eversion | Sole turned inward / outward | Rolling the ankle in or out |
| Elevation / Depression | Raising / lowering a part | Shrugging the shoulders and dropping them |
The special movements
A few joints make motions that need their own names. At the forearm, supination turns the palm up, as if you were carrying soup. Pronation turns it down. At the ankle, lifting your toes toward your shin is dorsiflexion. Pointing them down is plantar flexion. Turning the sole inward is inversion, and turning it outward is eversion.
The jaw and shoulders can protract (move forward) and retract (move back). They can also elevate (lift) and depress (lower). And the thumb can do opposition. It crosses the palm to meet the fingertips. This is the movement that makes the human hand such a good tool.
Tap each movement in the interactive. Watch a body do it, and see its opposite.
- Movements are named in opposite pairs. They are defined from the anatomical position.
- Flexion/extension change a joint angle. Abduction/adduction move a limb away from or toward the midline. Rotation spins a bone on its axis. Circumduction joins these into one cone.
- Special movements include supination/pronation (forearm) and dorsiflexion/plantar flexion (foot). They also include inversion/eversion (foot), elevation/depression, protraction/retraction, and opposition of the thumb.
Section 5Fibrous & cartilaginous joints
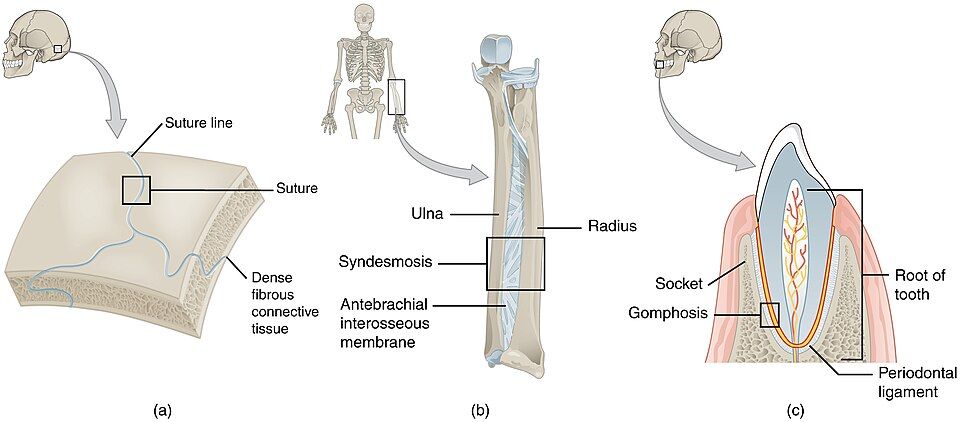
Joints without a cavity
Not every joint is built for motion. Two of the structural classes have no synovial space. These are fibrous and cartilaginous joints. They give up movement to get the stability the body needs in certain spots. They hold bones together with tissue, not with a gap of fluid. Most of them do not move at all, or move only a little.
Fibrous joints: bound by tough fibers
In a fibrous joint, tough, dense tissue stitches the bones right together. There are three kinds.
A suture is the jagged, zipper-like seam between the flat bones of the skull. A thin layer of fibrous tissue holds it. It is basically immovable (a synarthrosis). That is just what a case that guards the brain should be.
A syndesmosis joins two bones that lie side by side. They are linked by a wide sheet or cord of fibrous tissue. One example is the interosseous membrane between the radius and ulna in your forearm. This joint allows a little give (an amphiarthrosis).
A gomphosis is a peg-in-a-hole joint. It holds each tooth in its bony socket. The periodontal ligament holds it in place. It is also immovable.
Cartilaginous joints: bound by cartilage
In a cartilaginous joint, cartilage holds the bones together. A synchondrosis uses hyaline cartilage, a smooth, glassy kind of cartilage. The classic example is the epiphyseal (growth) plate in a long bone that is still growing. Another is the joint between the first rib and the breastbone (sternum). Both are immovable.
A symphysis uses fibrocartilage, a tough, springy kind of cartilage. It allows a little movement (an amphiarthrosis). There are two you must know. One is the pubic symphysis at the front of the pelvis. The other is the intervertebral discs between the bones of the spine. Each disc lets the spine bend a little. Added together, all that bending gives you a flexible back.
| Structural type | Subtype | Binding material | Movement | Example |
|---|---|---|---|---|
| Fibrous | Suture | Thin fibrous tissue | Immovable | Skull seams |
| Syndesmosis | Sheet or cord of fibrous tissue | Moves a little | Radius–ulna membrane | |
| Gomphosis | Periodontal ligament | Immovable | Tooth in its socket | |
| Cartilaginous | Synchondrosis | Hyaline cartilage | Immovable | Growth (epiphyseal) plate; 1st rib to sternum |
| Symphysis | Fibrocartilage | Moves a little | Pubic symphysis; intervertebral discs |
Tap each fibrous and cartilaginous type in the interactive. See how each one gives up movement to gain stability.
- Fibrous and cartilaginous joints have no space inside. They favor stability over movement.
- Fibrous types: suture (skull, immovable), syndesmosis (radius–ulna membrane, moves a little), gomphosis (tooth, immovable).
- Cartilaginous types: synchondrosis (hyaline cartilage; growth plate; immovable) and symphysis (fibrocartilage; pubic symphysis and discs; moves a little).
- A growth plate is a short-term joint. Later it fuses into bone, forming a synostosis.
Section 6Four joints that do the work
Shoulder and hip: two ball-and-sockets, two philosophies
The shoulder and the hip are both ball-and-socket joints. Yet they solve the mobility–stability problem in opposite ways.
The shoulder (glenohumeral) joint is built for reach. The ball of the humerus rests against a shallow socket, like a ball on a saucer. This gives it the widest range of any joint in the body. The price is weakness. The socket barely holds the ball. So the muscles of the rotator cuff do most of the work of holding it in place. It is the joint people dislocate, or pop out of place, most often.
The hip joint makes the opposite deal. The head of the femur sits deep in a true cup, called the acetabulum. Thick ligaments ring it. It gives up some range to become one of the most stable joints in the body. It has to be, because it carries your whole body weight with every step.
The knee: a hinge that does more than hinge
The knee is the largest and most complex joint in the body. It works mainly as a hinge, bending and straightening the leg. But it also allows a little rotation when it is bent. That is where trouble starts.
Two half-moon pads of fibrocartilage sit on top of the tibia. These are the menisci. They spread out the load and cushion the joint. Deep inside, two ligaments cross each other in an X. These are the anterior and posterior cruciate ligaments (ACL and PCL). They keep the femur and tibia from sliding past each other. A hard twist on a planted foot can tear the ACL and a meniscus together. That is why knee injuries end so many sports seasons.
The elbow: stability by design
The elbow shows what a joint looks like when the body picks stability. It is a hinge. The humerus and ulna lock together so snugly that the joint moves cleanly in one plane. It rarely dislocates. Strong collateral ligaments on each side make it even stronger.
A separate pivot joint at the radius lets the forearm rotate. This gives supination and pronation without loosening the hinge. The elbow is a quiet lesson in this chapter's theme. A joint that gives up range gains a toughness the shoulder can only wish for.
| Joint | Type | Main stabilizers | Signature injury |
|---|---|---|---|
| Shoulder (glenohumeral) | Ball-and-socket | Rotator-cuff muscles (the socket is shallow) | Dislocation; rotator-cuff tear |
| Hip | Ball-and-socket | Deep socket + thick ligaments | Fracture (often with age) |
| Knee | Hinge (+ a little rotation) | Cruciate ligaments, menisci, collateral ligaments | ACL / meniscus tear |
| Elbow | Hinge (+ pivot) | Bones lock together + collateral ligaments | Dislocation (not common) |
Tap each of the four joints in the interactive. Compare how each one balances mobility against stability.
- The shoulder moves the most because its socket is shallow. It pays for this by being the joint that dislocates most. The rotator cuff holds it steady.
- The hip is a deep ball-and-socket joint bound by ligaments. It is built to bear weight and stay stable.
- The knee is a complex hinge held steady by menisci and cruciate ligaments. Twisting injuries tear them.
- The elbow gives up range to be a snug, tough hinge. It has a pivot that lets the forearm rotate.
The chapter in one breath
- A joint is any place where two bones meet. Every joint is sorted by structure (fibrous, cartilaginous, synovial). It is also sorted by function (synarthrosis, amphiarthrosis, diarthrosis).
- The two ways match because the material sets the motion. The big theme is the mobility–stability trade-off: more movement always costs stability.
- Synovial joints are the ones that move freely. They come in six shapes: plane, hinge, pivot, condyloid, saddle, and ball-and-socket. These range from nonaxial to multiaxial.
- A synovial joint has a fluid-filled cavity between bones capped with cartilage. An articular capsule wraps it. Synovial fluid oils the joint, feeds the cartilage (which has no blood vessels), and absorbs shock.
- Movements are named in opposite pairs. These include flexion/extension, abduction/adduction, rotation, and circumduction. There are also special motions like supination/pronation and opposition.
- Fibrous joints (suture, syndesmosis, gomphosis) and cartilaginous joints (synchondrosis, symphysis) have no space inside. They favor stability. Some, like the growth plate, later fuse into bone.
- The shoulder, hip, knee, and elbow each strike the mobility–stability balance in a different way. That tells you how each one tends to get hurt.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back when a word trips you up.
- Abduction
- Movement of a limb away from the midline of the body. Raising your arm out to the side is an example.
- Adduction
- Movement of a limb toward the midline, back to the body.
- Amphiarthrosis
- A joint that moves a little. Examples are the pubic symphysis and an intervertebral disc.
- Articular capsule
- The two-layer sleeve that wraps a synovial joint. It has a tough fibrous outer layer and a synovial membrane inside that makes fluid.
- Articular cartilage
- The smooth hyaline cartilage that caps each bone end in a synovial joint. It cuts friction and absorbs shock.
- Bursa
- A small sac of fluid that cushions a spot where a tendon, ligament, or skin rubs over bone. When it swells, that is bursitis.
- Circumduction
- Moving a limb in a cone shape. It joins flexion, abduction, extension, and adduction in order.
- Diarthrosis
- A joint that moves freely. All synovial joints are diarthroses.
- Fibrous joint
- A joint where tough, dense tissue binds the bones right together, with no space inside. Types are the suture, syndesmosis, and gomphosis.
- Flexion
- A movement that makes the angle at a joint smaller, such as bending the elbow.
- Gomphosis
- The immovable peg-in-a-hole fibrous joint that holds a tooth in its socket. The periodontal ligament holds it in place.
- Ligament
- A band of tough, dense tissue that joins bone to bone and makes a joint stronger.
- Meniscus
- A half-moon pad of fibrocartilage between bone ends, as in the knee. It spreads the load and helps the bones fit.
- Suture
- An immovable fibrous joint. Sutures form the zipper-like seams between the flat bones of the skull.
- Symphysis
- A cartilaginous joint that moves a little, joined by fibrocartilage. Examples are the pubic symphysis and intervertebral discs.
- Synarthrosis
- A joint that does not move, such as a skull suture.
- Synchondrosis
- A cartilaginous joint joined by hyaline cartilage, such as the growth (epiphyseal) plate.
- Syndesmosis
- A fibrous joint where a sheet or cord of tissue links two bones. It allows a little movement, as between the radius and ulna.
- Synovial fluid
- The slippery fluid that fills a joint space. It is rich in hyaluronic acid. It oils the joint, feeds the cartilage, and cushions.
- Synovial joint
- A joint that moves freely. It has a fluid-filled space between bones capped with cartilage, all wrapped in a capsule.
Check yourself
Muscle Tissue
Muscle is the tissue that turns a choice into a movement. Every heartbeat, every blink, and every step is muscle at work. So is every push of food through your gut. Each one is a muscle cell doing the one thing muscle does best: shortening on command.
In this chapter we take one skeletal muscle apart, layer by layer. We keep going until we reach the tiny engine that actually pulls: the sarcomere. Then we watch that engine run. You will see how a nerve signal crosses into the muscle and how calcium flips the switch. You will see how threads of protein slide past each other. And you will see how the body turns the force up from a gentle flicker to an all-out heave. By the end, muscle action will not seem like magic. It will be a neat chain of events you can follow from thought to motion.
By the end of this chapter you can
- Compare the three types of muscle tissue: skeletal, cardiac, and smooth. Compare them by build, by control, and by where they are found.
- Trace the connective-tissue wrappings of a skeletal muscle, from the epimysium down to a single fiber. Name the parts inside that fiber.
- Draw a sarcomere and label its bands, zones, and lines. Explain why skeletal muscle looks striped.
- Explain the sliding filament theory and the steps of the cross-bridge cycle. Include the roles of ATP and calcium.
- Describe the neuromuscular junction. Follow a signal from a motor neuron to a muscle action potential.
- Define a motor unit. Explain how recruitment and summation raise muscle tension from a twitch to tetanus.
- Tell apart the three skeletal muscle fiber types. Match each one to the kind of work it does best.
Section 1How a muscle is built
Three kinds of muscle tissue
Before we open up one muscle, it helps to know that the body makes three kinds of muscle. Each is tuned to a different job.
Skeletal muscle is attached to bones and moves the body. It is under voluntary control, which means you choose when it works. Under the microscope its cells are long and striped (striated), and each has many nuclei.
Cardiac muscle is found only in the wall of the heart. It is striated too, but it is involuntary. That means it works without you thinking about it. Its cells are branched and most often have one nucleus. They are joined end to end by intercalated discs. These links let the whole heart squeeze as one.
Smooth muscle lines the walls of hollow organs, such as blood vessels, the gut, the bladder, and the airways. There it squeezes slowly and never seems to tire. It is involuntary and has no stripes. Its cells taper at both ends and have one nucleus in the middle.
This chapter focuses on skeletal muscle, because it shows every idea most clearly. But keep the other two in mind. Most of the machinery for squeezing is shared.
| Feature | Skeletal | Cardiac | Smooth |
|---|---|---|---|
| Location | Attached to bones | Heart wall only | Walls of hollow organs & vessels |
| Striations | Striated | Striated | Not striated |
| Control | Voluntary | Involuntary | Involuntary |
| Cell shape | Long tube shape, many nuclei | Branched, most often 1 nucleus | Spindle shape with tapered ends, 1 nucleus |
| Special feature | Controlled by motor neurons | Intercalated discs; sets its own rhythm | Slow and long-lasting; can trigger itself |
Bundles inside bundles
A whole skeletal muscle, such as your biceps, is not one solid block. It is a set of bundles inside bundles. Each bundle is wrapped in its own sheet of connective tissue. Let's go from the outside in.
The whole muscle is wrapped in the epimysium. Inside that, fibers are grouped into bundles called fascicles. Each fascicle is wrapped in perimysium. Inside each fascicle, every single muscle cell (a muscle fiber) is wrapped in a thin endomysium.
These three sheets are all joined to each other. At the ends of the muscle, they merge and reach past it. They form a tendon (a cord) or an aponeurosis (a flat sheet) that ties the muscle to bone. This setup is more than neat packing. The connective tissue carries blood vessels and nerves to each fiber. It also passes the pull of every cell to the tendon, so the whole muscle moves as one.
Inside a single fiber
Zoom into one muscle fiber and you find a cell built for pulling. Its cell membrane is called the sarcolemma. Its cytoplasm, the jelly inside, is the sarcoplasm. The word part sarco- means “flesh.” The sarcolemma dives deep into the cell as tunnels called transverse (T) tubules. They carry the electrical signal into the core of the fiber.
Wrapped around the working parts is the sarcoplasmic reticulum (SR). It is a special kind of smooth endoplasmic reticulum. It stores and releases the calcium that sets off a contraction. Most of the cell is filled with hundreds of long threads called myofibrils. Each myofibril is a chain of the units that shorten, the sarcomeres. These are made of myofilaments of two proteins, actin and myosin.
A muscle fiber forms when many cells fuse together as the body develops. So it holds many nuclei, pushed to the edge just under the sarcolemma. Nearby sit spare satellite cells that help repair damage.
Follow all of this in the interactive. Start at the whole muscle and zoom in, one wrapping at a time, down to the sarcomere.
- Three muscle types: skeletal (voluntary, striated, on bones), cardiac (involuntary, striated, in the heart), smooth (involuntary, not striated, in hollow organs).
- A skeletal muscle has bundles inside bundles: epimysium → fascicle (perimysium) → fiber (endomysium). All of these join the tendon.
- Inside a fiber: the sarcolemma, T-tubules, sarcoplasmic reticulum, and myofibrils of actin and myosin. There are also many nuclei at the edge.
Section 2The sarcomere
Stripes with a purpose
Skeletal and cardiac muscle have stripes. These stripes are not just for show. They are the outward sign of very orderly machinery inside. In every myofibril, the proteins that pull are lined up in the same repeating segments. Each segment is a sarcomere. It is the functional unit of contraction, the smallest part that can do the job. One sarcomere runs from one Z-disc to the next Z-disc.
When millions of these little units all shorten at once, lined up, the whole muscle shortens. Each unit has dark and light parts. Stacked side by side across the fiber, they look like stripes to our eyes. These are the striations.
The bands, zones, and lines
A sarcomere is built from two kinds of filament, or thread. The thick filaments are made of myosin. Each has a hinged head that sticks out. The thin filaments are made of actin. Where the two overlap, the sarcomere looks dark. Where only one kind is found, it looks lighter. It is worth learning this map of bands. In the next section you will watch these parts change size as the muscle contracts.
| Region | What it contains | Appearance |
|---|---|---|
| A band | The full length of the thick filaments (with overlap at its edges) | Dark; does not change length during contraction |
| I band | Thin filaments only, reaching into two sarcomeres side by side | Light; gets narrower during contraction |
| H zone | Thick filaments only, in the center of the A band (no overlap) | Lighter center; gets narrower during contraction |
| Z-disc (Z-line) | Holds the thin filaments in place; the border of the sarcomere | Dark line; Z-discs are pulled together |
| M-line | Holds the thick filaments at the center of the sarcomere | Thin line in the center |
Thick, thin, and the switch proteins
The thin filament is more than plain actin. A rope-like protein called tropomyosin lies along it. In a resting muscle, it covers the spots where myosin would grab on. These spots are the myosin-binding sites. A three-part protein group called troponin holds tropomyosin in place. One part of it, troponin C, senses calcium.
This is the switch. When calcium binds to troponin, the whole group shifts. Tropomyosin slides aside, and the binding sites open up.
Two more proteins keep the sarcomere in order. Titin is a huge, springy protein. It runs from the Z-disc to the M-line. It keeps the thick filament centered and lets muscle spring back when stretched. Nebulin runs along the thin filament and sets its length. Once again, the build is made exactly for the job.
Tap each part in the interactive to see how the filaments make the stripes.
- The sarcomere (Z-disc to Z-disc) is the functional unit of contraction. Sarcomeres lined up in order make the stripes you can see, the striations.
- Thick filaments are myosin, with heads. Thin filaments are actin. They are guarded by tropomyosin and by troponin, which senses calcium.
- The A band stays the same, while the I band and H zone narrow during contraction. This is the telltale sign of sliding filaments.
Section 3The sliding filament theory
Sliding, not shrinking
Here is the most important idea in this chapter. It surprises almost everyone the first time: the filaments do not get shorter. When a muscle contracts, the thick and thin filaments slide past each other. They overlap more and drag the Z-discs closer together. Each filament keeps its exact length. It is the sarcomere that shortens.
That is why the A band never changes in the reference figure. The A band is the length of the thick filament. Meanwhile the I band and H zone shrink, and the Z-discs move inward. Now add up that tiny slide across millions of sarcomeres lined up end to end. The whole muscle clearly shortens and pulls on its tendon.
The cross-bridge cycle
The myosin heads power the sliding. They act like tiny oars. Each head reaches out and grabs actin, forming a cross-bridge. Then it swivels. This is the power stroke. It pulls the thin filament a few nanometers toward the center. Then the head lets go, gets cocked again, and grabs again farther along. The cycle repeats many times each second. It runs on ATP, the cell's energy molecule:
| Step | What happens | Role of ATP / Ca²⁺ |
|---|---|---|
| 1. Cross-bridge forms | The charged-up myosin head binds to an open site on actin | Needs Ca²⁺ to have opened the site |
| 2. Power stroke | The head swivels and slides the thin filament inward; ADP & Pi (inorganic phosphate) are released | Uses energy stored from an earlier ATP |
| 3. Detachment | A new ATP binds the myosin head, and the head lets go of actin | ATP binding breaks the cross-bridge |
| 4. Re-cocking | ATP is split into ADP + Pi, which charges up and resets the head | ATP hydrolysis (splitting ATP) cocks the head again |
Notice that ATP has two jobs. It is needed to release the head (step 3). It is also needed to re-cock it (step 4). This leads to something you may have heard of. After death, the body stops making ATP. The myosin heads bind actin and can no longer let go. So the body stiffens. This is called rigor mortis.
Calcium throws the switch: excitation–contraction coupling
Cross-bridges can form only if the binding sites are uncovered. That is calcium's job. The link between an electrical signal and a pull is called excitation–contraction coupling. Here is how it works.
A muscle action potential, an electrical signal, races along the sarcolemma. It dives down the T-tubules into the fiber. That change in voltage tells the sarcoplasmic reticulum to release its stored Ca²⁺ into the sarcoplasm. Calcium binds to troponin. Troponin pulls tropomyosin off the actin. The binding sites open, and cross-bridges begin to form. The filaments start to slide.
Relaxing is just the reverse. When the signal stops, a pump called SERCA moves Ca²⁺ back into the SR. Tropomyosin covers the sites again. Cross-bridges can no longer form, and the muscle goes slack. No calcium, no contraction.
In the interactive, watch the Z-lines pull together while the filaments keep their length.
- In the sliding filament theory, the filaments keep their length. The sarcomere shortens as the thick and thin filaments overlap more.
- The cross-bridge cycle has four steps: bind, power stroke, detach, re-cock. It runs on ATP, which is needed to release and to re-charge the myosin head.
- Excitation–contraction coupling: an action potential → T-tubules → SR releases Ca²⁺ → troponin/tropomyosin uncover the binding sites. To relax, SERCA pumps the calcium back.
Section 4The neuromuscular junction
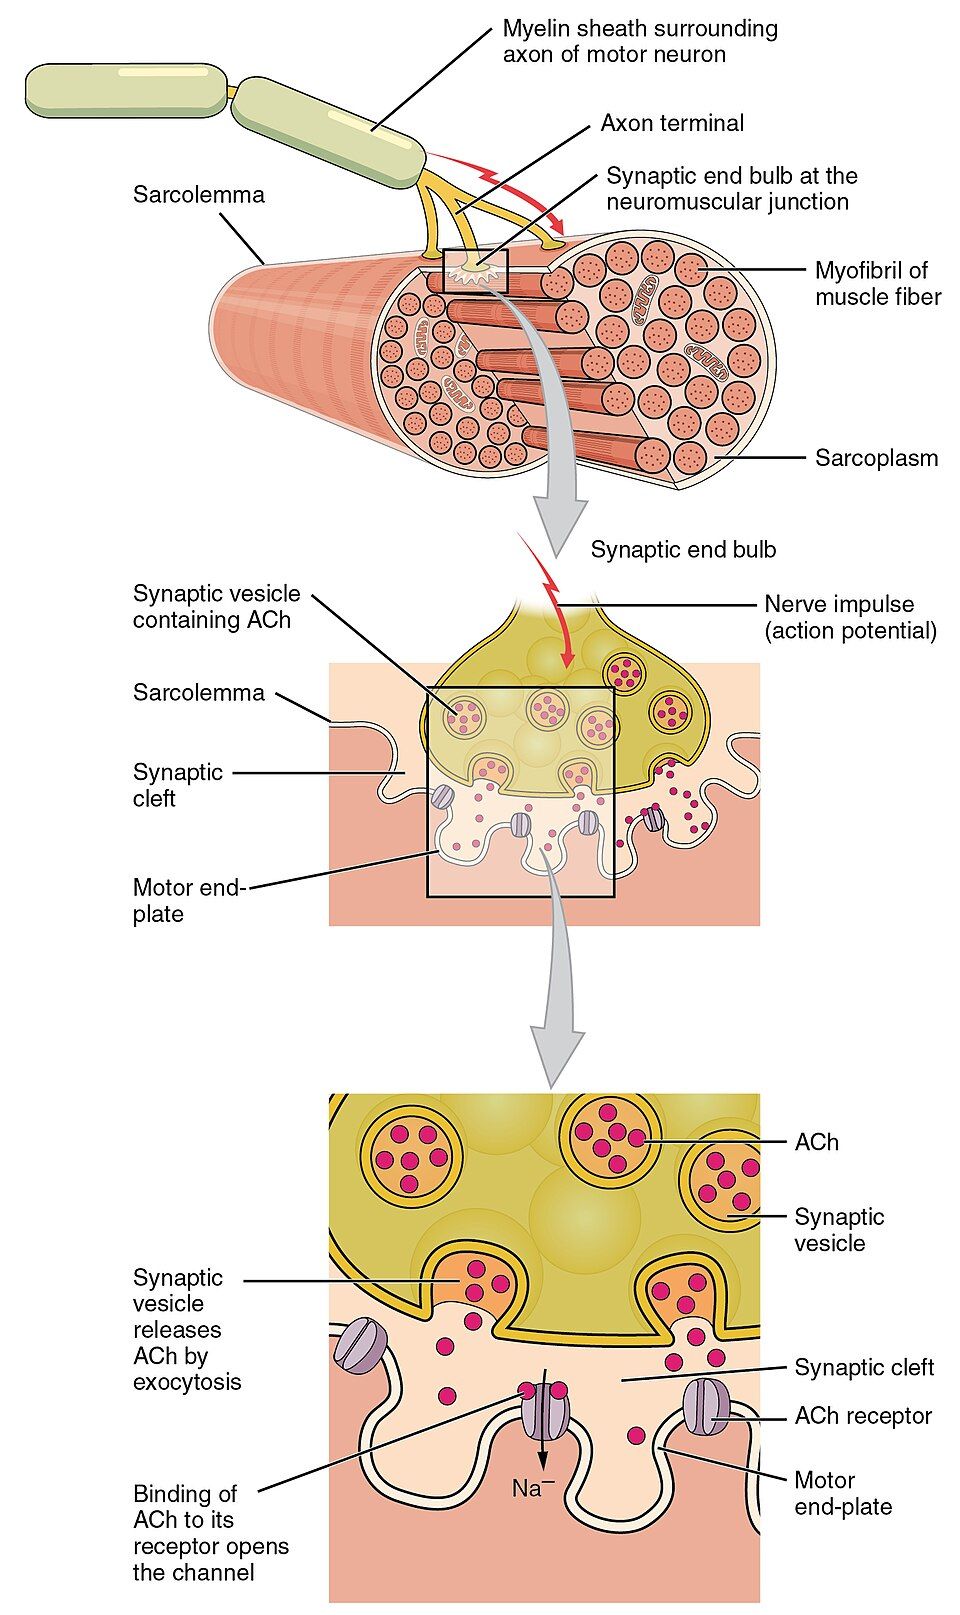
From nerve to muscle
A skeletal muscle fiber will not contract on its own. It waits for a command from a nerve. That command is delivered at a special synapse, or meeting point, called the neuromuscular junction (NMJ). A motor neuron reaches out from the spinal cord. The end of its axon rests just above a folded patch of sarcolemma. This patch is the motor end plate.
The two never touch. A tiny gap, the synaptic cleft, separates them. To cross that gap, the neuron uses a chemical messenger. This is the neurotransmitter acetylcholine (ACh).
The handoff, step by step
Passing the signal from nerve to muscle is one of the most reliable events in the body. A single nerve impulse almost always sets off a muscle impulse. Follow the chain:
| Step | Event |
|---|---|
| 1 | A nerve action potential reaches the end of the axon (the axon terminal). |
| 2 | Voltage-gated Ca²⁺ channels open. Calcium rushes into the axon terminal. |
| 3 | Calcium makes small sacs (vesicles) release acetylcholine into the synaptic cleft. |
| 4 | ACh crosses the cleft and binds to nicotinic receptors on the motor end plate. |
| 5 | The receptor channels open. Na⁺ floods in and makes an end-plate potential. |
| 6 | This change in charge sets off a muscle action potential. It spreads along the sarcolemma and down the T-tubules. Then contraction follows. |
See how this fits with the last section. Step 6 is the very same muscle action potential that starts excitation–contraction coupling. The NMJ is the doorway. The sliding filaments are the room it opens into.
Switching the signal off, and where it breaks
A signal that never ended would leave the muscle stuck in contraction. So the cleft holds an enzyme called acetylcholinesterase (AChE). It chops ACh apart within milliseconds. This neat on/off system is also where many drugs and diseases act. That makes the NMJ one of the most important spots in medicine.
In myasthenia gravis, the immune system destroys ACh receptors. So muscles tire quickly and grow weak. Curare, an arrow poison, blocks the receptors and causes paralysis. Organophosphate bug sprays and nerve agents block AChE. Then ACh piles up and muscles seize. Botulinum toxin (Botox) blocks the release of ACh, so muscle relaxes. This is useful for treating spasms and wrinkles.
Step through the chemical handoff yourself in the interactive.
- The neuromuscular junction is the synapse where a motor neuron signals a muscle fiber. It uses acetylcholine to cross the synaptic cleft.
- ACh binds nicotinic receptors on the motor end plate. This lets Na⁺ in, which triggers a muscle action potential. Then acetylcholinesterase ends the signal.
- NMJ problems follow the messenger. Blocking ACh → weakness (myasthenia gravis, curare, botulinum toxin). Letting ACh last too long → spasm (AChE blockers, nerve agents).
Section 5Motor units & muscle tension
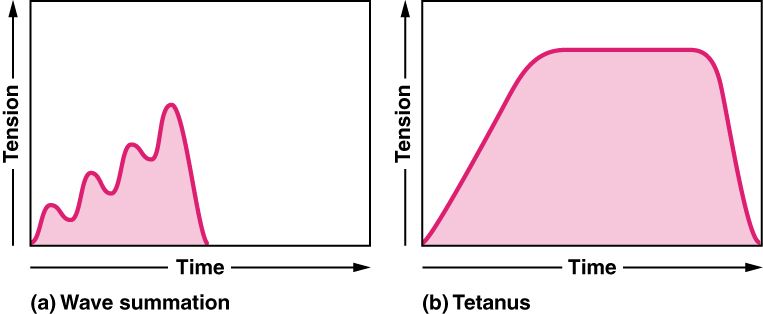
The motor unit
One motor neuron rarely controls just one muscle fiber. It branches and connects to a group of fibers. The neuron plus all the fibers it controls is a motor unit. When that neuron fires, every fiber in its unit contracts at once. They act as an all-or-nothing team.
The size of the unit sets how finely a muscle can be controlled. Muscles that need a gentle touch, like those that move the eye or the fingers, have small motor units. Each neuron links to only a few fibers. Muscles built for power, like the quadriceps or the calf, have large motor units. Each neuron links to hundreds of fibers. Small units mean fine control. Large units mean strong, rough force.
Twitch, summation, tetanus
One short stimulus gives a single quick contraction and relaxation. This is a twitch. It has three phases. First is a latent period, a hidden delay while calcium is released. Next is a contraction phase, then a relaxation phase. A twitch is a flick, not a useful pull.
To get smooth, strong movement, the nervous system fires the motor neuron again before the fiber fully relaxes. So the second contraction stacks on top of the first. This stacking is wave (temporal) summation. Fire even faster, and the twitches blur into a partly smooth pull. This is unfused (incomplete) tetanus. Faster still, and you get a steady, perfectly smooth, all-out pull. This is fused (complete) tetanus. Almost all normal movements use tetanus, not single twitches.
| Response | Stimulus pattern | Result |
|---|---|---|
| Twitch | One stimulus | One short contraction, then full relaxation |
| Wave summation | A second stimulus before relaxation ends | The second contraction adds to the first, giving more tension |
| Unfused tetanus | Fast, repeated stimuli | Strong, lasting pull with slight wobbles |
| Fused tetanus | Stimuli at a very high rate | All-out, perfectly smooth, lasting contraction |
Two dials for force: recruitment and rate
The body controls how hard a muscle pulls with two dials at once. The first dial is recruitment, which means turning on more motor units. It follows the size principle. Small, weak units that resist tiring are turned on first. Larger, stronger ones join only when more force is needed. So movements start smooth and easy to control.
The second dial is rate coding. This means firing each active unit faster, to climb from summation up to tetanus. With both dials, the same muscle can lift a feather or a heavy weight. Even at rest, a few units are always active, taking turns. They keep muscles firm and ready. This steady, low tension is muscle tone.
Pick a stimulus pattern in the interactive. Watch tension climb from twitch to tetanus.
- A motor unit is one motor neuron plus all the fibers it controls. Small units give fine control. Large units give power.
- Tension builds from a twitch through wave summation to tetanus as the stimuli come faster. Real movement uses tetanus.
- Force is set by recruitment (adding units, smallest first; this is the size principle) and rate coding (firing faster). The steady activity at rest is muscle tone.
Section 6The three fiber types
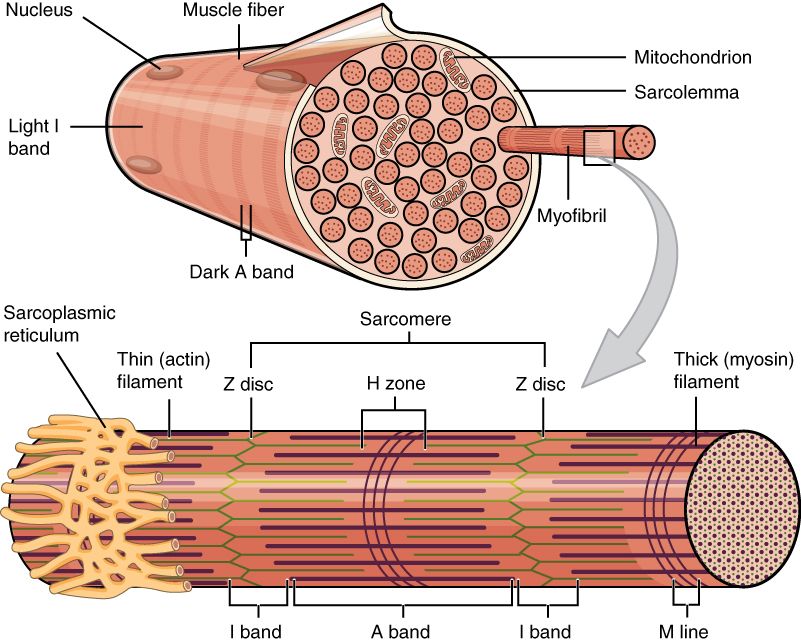
Speed versus stamina
Not every skeletal muscle fiber is the same. There are three types. They trade speed against endurance, or staying power. No one design can be both as fast as possible and as tireless as possible.
Slow oxidative (Type I) fibers contract slowly and make only modest force. But they can keep going for hours. They are the endurance experts. Fast glycolytic (Type IIx) fibers contract quickly and with great power. But they tire within minutes. They are the experts at sprinting and lifting. In between are fast oxidative (Type IIa) fibers. They are fast and fairly slow to tire, a useful middle ground.
Aerobic versus anaerobic engines
The difference comes down to how each fiber makes its ATP. Oxidative fibers use aerobic respiration, which needs oxygen. They are packed with mitochondria, the cell's power plants. They have lots of capillaries, the tiniest blood vessels. They are also loaded with myoglobin, a pigment that holds oxygen and makes them look red. This red, oxygen-fed system is slow but can keep going.
Glycolytic fibers rely on anaerobic glycolysis, which does not need oxygen. They have few mitochondria and little myoglobin, so they look pale. They store lots of glycogen, a sugar fuel, for quick bursts. They give explosive power. But they fill up with lactate and tire fast.
| Property | Slow oxidative (I) | Fast oxidative (IIa) | Fast glycolytic (IIx) |
|---|---|---|---|
| Contraction speed | Slow | Fast | Fast |
| Fatigue resistance | High | Moderate | Low |
| Main ATP source | Aerobic (oxidative) | Both | Anaerobic (glycolytic) |
| Mitochondria / capillaries | Many | Many | Few |
| Myoglobin / color | High / red | High / red-pink | Low / white |
| Best for | Posture, endurance | Walking, steady effort | Sprinting, lifting |
Everybody is a mixture, plus a word on the other two muscles
Almost every real muscle has all three fiber types. The mix is set partly by your genes and partly by how you train. Endurance training moves fibers toward the oxidative end, where they resist tiring. Strength and sprint training push toward bigger, more powerful fibers. That is why a marathon runner's calves and a sprinter's thighs are built for different feats.
Now recall the two muscle types we set aside at the start. Cardiac muscle acts like tissue that is always tuned for endurance. It sets its own rhythm, and intercalated discs join its cells, so the heart never truly rests. Smooth muscle has no sarcomeres at all. It can hold tension for a long time using very little energy. This “latch” state is perfect for keeping a blood vessel or a sphincter squeezed all day.
Tap each fiber type in the interactive to compare speed, color, and stamina.
- Three fiber types trade speed for stamina. Slow oxidative (I) = endurance. Fast glycolytic (IIx) = power. Fast oxidative (IIa) = in between.
- Oxidative fibers are red (many mitochondria, lots of myoglobin and capillaries) and use oxygen. Glycolytic fibers are pale and do not use oxygen. They are powerful but tire quickly.
- Most muscles are a mix shaped by genes and training. Cardiac and smooth muscle are separate designs, built for work that never stops.
The chapter in one breath
- Muscle comes in three types. They are skeletal (voluntary, striated), cardiac (involuntary, striated, sets its own rhythm), and smooth (involuntary, not striated). All share the same basic machinery for contraction.
- A skeletal muscle is bundles inside bundles. They are wrapped in epimysium, perimysium, and endomysium, which all join the tendon. Inside each fiber are the sarcolemma, T-tubules, sarcoplasmic reticulum, and myofibrils.
- The sarcomere (Z-disc to Z-disc) is the functional unit. Overlapping thick (myosin) and thin (actin) filaments make the stripes. Tropomyosin and troponin guard the binding sites.
- In the sliding filament theory, the filaments keep their length while the sarcomere shortens. The cross-bridge cycle runs on ATP. Ca²⁺ released by the SR uncovers the binding sites.
- The neuromuscular junction passes the signal from nerve to muscle using acetylcholine. Then acetylcholinesterase clears it away. Toxins here cause weakness or spasm.
- A motor unit is one neuron and its fibers. Tension rises from a twitch to tetanus. It is controlled by recruitment and rate coding.
- Three fiber types trade speed for endurance. Most muscles blend all three, in a mix shaped by genes and training.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back when a word trips you up.
- A band
- The dark part of a sarcomere that spans the full length of the thick filaments. It does not change length during contraction.
- Acetylcholine (ACh)
- The neurotransmitter a motor neuron releases at the neuromuscular junction. It sets off a muscle action potential.
- Actin
- The protein of the thin filament. It has the myosin-binding sites where cross-bridges attach.
- Cross-bridge
- The link made when a myosin head binds an open site on actin. Its cycle of binding, power stroke, and release makes the filaments slide.
- Endomysium
- The thin sheet of connective tissue that wraps each single muscle fiber.
- Epimysium
- The sheet of connective tissue that wraps a whole skeletal muscle.
- Excitation–contraction coupling
- The chain of events that links a muscle action potential to contraction. The signal travels down the T-tubules and makes the sarcoplasmic reticulum release Ca²⁺.
- Fascicle
- A bundle of muscle fibers wrapped in perimysium.
- Motor unit
- One motor neuron plus all the muscle fibers it controls. They contract as one.
- Myofibril
- A long thread inside a muscle fiber. It is made of a chain of sarcomeres.
- Myosin
- The protein of the thick filament. Its hinged heads form cross-bridges and do the power stroke.
- Neuromuscular junction
- The synapse between a motor neuron and a skeletal muscle fiber. Here acetylcholine passes on the signal.
- Recruitment
- Raising muscle force by turning on more motor units. The smallest units, which tire the least, go first (the size principle).
- Sarcolemma
- The cell membrane of a muscle fiber. Its tunnels into the cell are the T-tubules.
- Sarcomere
- The functional unit of striated muscle, the part that shortens. It runs from one Z-disc to the next.
- Sarcoplasmic reticulum (SR)
- The special smooth ER of a muscle fiber. It stores and releases the Ca²⁺ that sets off contraction.
- Sliding filament theory
- The idea that muscle shortens because thick and thin filaments slide past each other. The filaments themselves do not get shorter.
- Tetanus
- A lasting contraction. It happens when stimuli come faster than the fiber can fully relax between them. It is unfused (incomplete) when some relaxing still shows as slight wobbles. It is fused (complete), smooth and all-out, when stimuli come at a very high rate.
- Tropomyosin
- The thin-filament protein that covers the myosin-binding sites at rest. It slides aside when calcium binds troponin.
- Troponin
- The thin-filament protein group that binds Ca²⁺. It moves tropomyosin to uncover the binding sites.
- Twitch
- A single short contraction and relaxation of a muscle fiber after one stimulus. It has latent, contraction, and relaxation phases.
Check yourself
The Muscular System
Every move you choose to make is a muscle pulling on a bone or on your skin. A smile, a step, a breath and a signature all work this way. In the last chapters you looked inside a single muscle fiber. Now we zoom out to the whole body. You have more than 600 skeletal muscles, and each one can only pull. So how do they team up to make smooth, controlled moves? And why do their names sound like Latin riddles? You will learn to crack those riddles, so you can know a muscle you never memorized. This chapter tours the body's muscles, one region at a time. We go from the tiny muscles that shape your face to the big ones that launch you off the ground.
By the end of this chapter you can
- Explain why skeletal muscles can only pull. Explain why this makes them work in opposing pairs across a joint.
- Define a muscle's origin and insertion. Give the roles of agonist, antagonist, synergist, and fixator in a movement.
- Describe how bones and joints act as levers. Explain how a third-class lever trades force for speed.
- Use the six naming clues to guess a muscle's place, shape, size, fiber direction, number of heads, or action from its name.
- Tell the muscles of facial expression from the muscles of mastication (chewing). Name the cranial nerve that runs each group.
- Identify the main muscles of the trunk: the breathing muscles, the belly wall, and the deep back. Say what each one does.
- Name the main muscles that move the shoulder, arm, and forearm. Include the rotator cuff and the classic flexor/extensor pairs.
- Name the main muscles that move the hip, knee, and ankle. Include the quadriceps, hamstrings, and calf.
Section 1How muscles work together

A muscle can only pull
Everything in this section rests on one fact: a muscle can only pull, never push. When a muscle contracts, its fibers get shorter. This draws its two ends toward each other. That is the only trick it has. It cannot stretch itself out to shove a bone away.
So how does your forearm bend up and then straighten back down? Muscles almost never work alone. They are set up in opposing teams on each side of a joint. To reverse a move, the body relaxes one team and contracts the other.
To describe the pull clearly, we name a muscle's two ends. The origin is where the muscle attaches to the bone that stays fairly still. It is usually the heavier bone, closer to the body's center (proximal). The insertion is where it attaches to the bone that moves. That bone is usually farther out (distal).
Between the two ends is the thick middle part that contracts. This is the belly. When the muscle gets shorter, the insertion is pulled toward the origin. Muscles attach to bone by tough cords called tendons. Some attach by wide, flat sheets called aponeuroses.
Four roles in every movement
Muscles work in teams, so every move is like a small crew at work. Each crew member has a job. Learn these four roles, and you can study any movement in the body:
| Role | What it does | Example (bending the elbow) |
|---|---|---|
| Agonist (prime mover) | The main muscle that makes the move | Biceps brachii flexes (bends) the elbow |
| Antagonist | Works against the agonist. It relaxes and stretches while the agonist acts. | Triceps brachii relaxes so the elbow can bend |
| Synergist | Helps the agonist or holds the joint steady | Brachialis helps the biceps bend the elbow |
| Fixator | Holds the origin still so the pull works well | Shoulder muscles hold the scapula (shoulder blade) still |
The same muscle can switch roles. It depends on the move. When you bend your elbow, the biceps is the agonist and the triceps is the antagonist. When you straighten it, they swap jobs. So no muscle is just a “flexor” in general. A muscle is a flexor or an extensor only for one joint in one move.
Bones are levers, joints are fulcrums
Muscles do not move bones by brute force alone. They work through levers. A lever is a stiff bar that turns on a fixed point. Your body is full of them. The bone is the bar. The joint is the turning point, called the fulcrum. The muscle's pull is the effort. The weight being moved is the load. How these three points are lined up decides what a joint is good at. It favors either power or speed and range.
Most joints in the body are third-class levers. In this setup, the effort is between the fulcrum and the load. Your elbow is a good example. The biceps attaches just past the joint, while the load sits far out at your hand. This setup is weak for lifting heavy things. But it gives you something more useful. A small, quick shortening of the muscle makes your hand sweep a long way, fast. Your body traded raw force for speed and reach. That is why you can throw a ball hard but strain to curl a heavy dumbbell.
Bend and straighten the elbow in the interactive. Watch the biceps and triceps trade the agonist and antagonist roles.
- A muscle can only pull. Opposing muscles across a joint undo each other's actions.
- The origin is the fixed end, usually proximal. The insertion is the moving end, usually distal. The insertion is pulled toward the origin.
- Every move uses an agonist, antagonist, synergist, and fixator. Muscles swap these roles from one move to the next.
- Bones act as levers. Most body joints are third-class levers. They favor speed and range over force.
Section 2How muscles are named
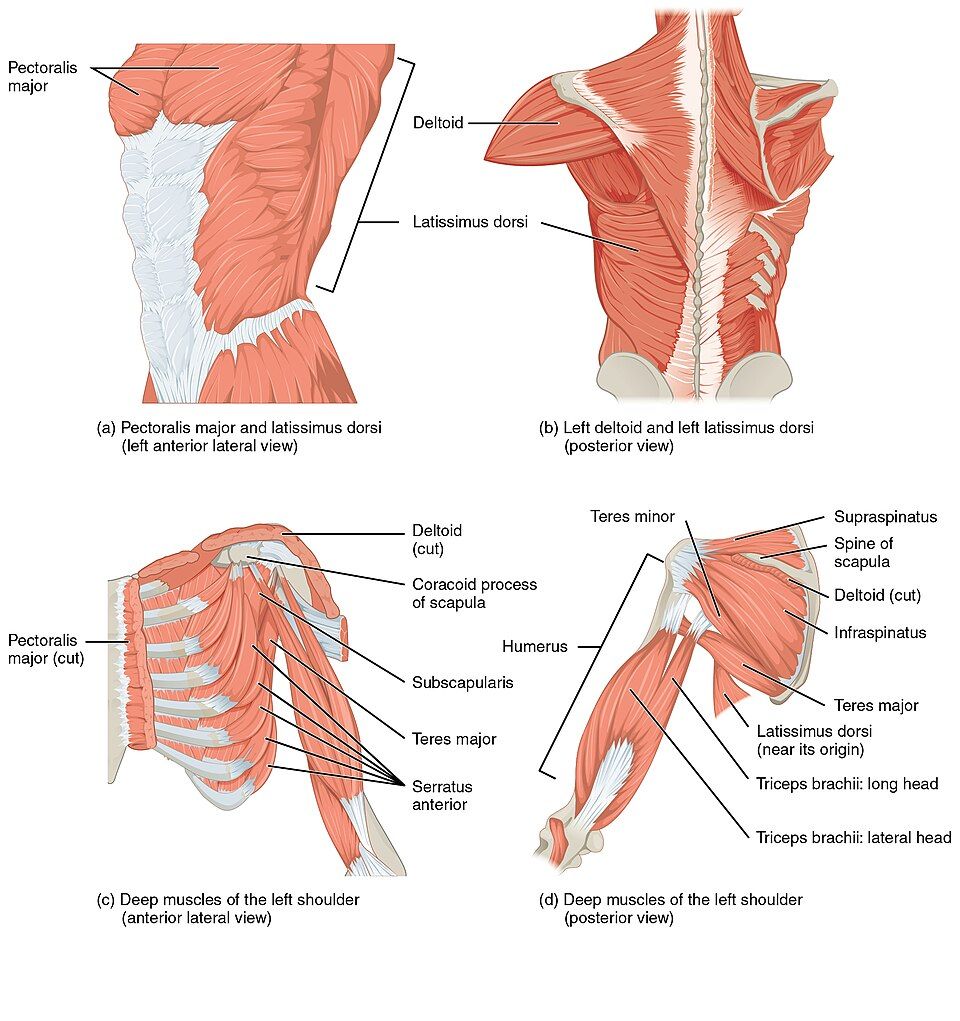
Names are descriptions in disguise
The first time you see a name like extensor carpi radialis longus, it can feel like a wall of Latin to memorize. It is not. Scientists named muscles the way sailors named knots. They described them. Almost every muscle name is a short description. It tells you where the muscle is, what it looks like, how big it is, which way its fibers run, how many heads it has, or what it does. Once you know the words, a new name becomes a set of directions. It tells you where to find the muscle and what it does.
The six clues
A name can carry six kinds of clues. Many muscles pack several clues into one name:
| Clue | Tells you | Example words & muscles |
|---|---|---|
| Location | The body part or a nearby bone | temporalis (temporal bone), tibialis anterior (front of the tibia) |
| Shape | The muscle's outline | deltoid (triangle), trapezius (trapezoid), rhomboid |
| Size | How big or long it is compared to others | maximus/minimus, longus/brevis, major/minor |
| Fiber direction | Which way the fibers run compared to the body's midline | rectus (straight), transversus (across), oblique (at a slant) |
| Number of heads | How many origins the muscle has | biceps (two), triceps (three), quadriceps (four) |
| Action | The move it makes | flexor, extensor, adductor, levator, masseter (chewer) |
Watch the clues stack up. Extensor digitorum longus means “the long muscle that extends the digits.” It gives the action, then the body part, then the size. Rectus femoris is “the straight muscle of the femur.” Even a monster like flexor carpi radialis is simple. It is “the muscle that flexes the wrist (carpus) on the radius side.” You do not have to memorize it as one blob. You read it like a sentence.
Tap each of the six clues in the interactive. See how a name reveals a muscle.
- Muscle names are descriptions, not random labels. Decode them, and you can figure out muscles you never memorized.
- The six clues are location, shape, size, fiber direction, number of heads, and action.
- Many names mix several clues. Read them from left to right, like a sentence.
Section 3Muscles of the head and neck
The muscles that make a face
The muscles of facial expression are the muscles that shape your face. They are unlike almost any others in the body. Most of them do not move a bone at all. Instead, they insert into the skin. When they contract, they tug the skin of your face into shapes. That is how you smile, frown, raise an eyebrow, or wink. One nerve runs this whole group. It is the facial nerve (cranial nerve VII).
Here are the key players. The orbicularis oris is a ring around the mouth. It purses your lips to whistle or kiss. The orbicularis oculi is a ring around the eye. It closes the eye to blink and squint.
The buccinator is in the cheek. It flattens the cheek to blow out a candle. It also holds food against your teeth while you chew. The zygomaticus pulls the corner of the mouth up to smile. The occipitofrontalis raises the eyebrows and wrinkles the forehead.
The muscles that chew
The second job up here is mastication, which means chewing. The muscles of mastication are not like the face muscles. They do move a bone. They close the mandible (lower jaw) and grind it at the jaw joint. That joint is called the temporomandibular joint. This group answers to a different nerve, the trigeminal nerve (cranial nerve V).
The masseter runs from the cheekbone to the angle of the jaw. For its size, it is one of the strongest muscles in the body. You can feel it bulge when you clench your teeth. The fan-shaped temporalis spreads over the side of the skull. It helps close the jaw and pull it back. The deep pterygoid muscles move the jaw from side to side to grind food.
| Group | Job | Inserts on | Nerve | Members |
|---|---|---|---|---|
| Facial expression | Move the skin of the face | Skin | Facial (CN VII) | Orbicularis oris & oculi, buccinator, zygomaticus, occipitofrontalis |
| Mastication | Move the mandible to chew | Mandible (bone) | Trigeminal (CN V) | Masseter, temporalis, pterygoids |
| Neck | Move and hold up the head | Skull & shoulder girdle | Accessory / cervical | Sternocleidomastoid, trapezius |
Down in the neck, two large muscles move the head itself. There is a sternocleidomastoid muscle on each side of the neck. When both work together, they bend the neck forward (flex it). When one works alone, it turns the head to the opposite side. The wide trapezius tips the head back (extends it). It also steadies the shoulder girdle behind it.
Tap each muscle in the interactive to light it up. See whether it makes a face or chews.
- Muscles of facial expression insert into skin. They are run by the facial nerve (CN VII).
- Muscles of mastication move the mandible to chew. They are run by the trigeminal nerve (CN V). The masseter is the strongest for its size.
- The sternocleidomastoid bends the neck and turns the head to the opposite side.
Section 4Muscles of the trunk
The muscles that breathe
The trunk muscles do the body's quiet but vital work. None of it is more vital than breathing. The diaphragm is the main muscle of breathing (respiration). It is a wide dome of muscle that seals off the bottom of the chest. When it contracts, it flattens. This makes the chest space (the thoracic cavity) bigger. The pressure inside drops, and air is pulled into the lungs. When the diaphragm relaxes, the dome springs back up and pushes air out.
Other muscles help. The external intercostals are muscles between the ribs. They lift the rib cage when you breathe in. The internal intercostals pull the ribs down when you breathe out hard. You use them when you cough or blow out a candle.
The abdominal wall and the back
Four flat muscles wrap the front and sides of your belly. They are layered like plywood. Their fibers run in different directions, which makes the wall strong. The rectus abdominis is the “six-pack.” It runs straight up the middle. It flexes (bends) the spine, the vertebral column. That is the move of a sit-up.
Three more muscles cover the sides. They are the external oblique, the internal oblique, and the deepest one, the transversus abdominis. The fibers of the transversus wrap sideways around you like a corset. Together, this wall squeezes the belly. It bends and twists the trunk. It protects the soft organs behind it. It also raises the pressure you need to cough, give birth, and have a bowel movement.
Along the back runs the erector spinae. It is a set of three columns of muscle that run the length of the spine. It does the opposite of the belly muscles. It extends the spine, which means it straightens you up after you bend over. It also holds you upright against gravity all day long.
| Region | Muscles | Main action |
|---|---|---|
| Breathing | Diaphragm, external & internal intercostals | Change the size of the chest to move air in and out |
| Abdominal wall | Rectus abdominis, external & internal obliques, transversus abdominis | Bend and twist the trunk. Squeeze and protect the belly. |
| Deep back | Erector spinae group | Extend the spine and hold you upright |
| Pelvic floor | Levator ani and its partners | Hold up the pelvic organs. Control holding in urine and stool (continence). |
Tap each trunk muscle in the interactive. See whether it breathes, bends, or protects.
- The diaphragm is the main breathing muscle. When it contracts, the dome flattens and pulls air in.
- Four layers of belly muscle bend and twist the trunk and protect the organs (viscera). They are the rectus abdominis, the two obliques, and the transversus abdominis.
- The erector spinae extends the spine and holds your posture. The diaphragm is run by the phrenic nerve (C3–C5).
Section 5Muscles of the upper limb
Anchoring and moving the shoulder
Your upper limb is built for reaching and for skilled hand work. It starts at the shoulder. The shoulder moves more than any other joint, so it is also the least stable. Several large muscles anchor the shoulder blade and swing the arm. The trapezius and serratus anterior hold and turn the scapula (shoulder blade). This makes it a moving base for the arm.
The fan-shaped pectoralis major on the chest pulls the arm forward and across the body. The wide latissimus dorsi on the back pulls the arm down and back. It is the muscle of a swimmer's stroke. On top of the shoulder sits the deltoid. This triangle-shaped muscle abducts the arm, which means it lifts the arm out to the side.
Deep around the joint itself is the rotator cuff. It is a set of four small muscles: supraspinatus, infraspinatus, teres minor, and subscapularis. Together they are called the “SITS” group. They do not make big moves. Their job is to hold the ball at the top of the humerus snugly in its shallow socket. They do this while the bigger muscles move the arm.
The arm and forearm
The arm runs from the shoulder to the elbow. It holds the classic agonist and antagonist pair. On the front, the biceps brachii flexes (bends) the elbow. It also turns the palm up, which is called supination. The brachialis, under the biceps, helps it. On the back, the triceps brachii extends the elbow to straighten the arm. It is the only major muscle there.
Past the elbow, the forearm has two opposing groups. On the palm side, flexors curl the wrist and fingers. On the back side, extensors straighten them. Their long tendons run down into the hand. That is why much of the power for your grip comes from muscle bellies up in the forearm.
| Muscle | Location | Main action |
|---|---|---|
| Deltoid | Top of the shoulder | Abducts the arm (lifts it out to the side) |
| Pectoralis major | Front of the chest | Flexes the arm and adducts it (pulls it in) |
| Latissimus dorsi | Wide part of the back | Extends the arm and adducts it |
| Rotator cuff (SITS) | Deep around the shoulder | Holds the head of the humerus steady |
| Biceps brachii | Front of the arm | Flexes the elbow, supinates the forearm (palm up) |
| Triceps brachii | Back of the arm | Extends the elbow |
Tap each muscle in the interactive. Find the movers of the shoulder, arm, and forearm, and their pairs.
- The deltoid abducts the arm. The pectoralis major pulls the arm forward, and the latissimus dorsi pulls it back.
- The rotator cuff (SITS) steadies the loose shoulder joint. The supraspinatus tears most often.
- At the elbow, the biceps brachii flexes and supinates. The triceps brachii extends. Forearm flexors and extensors move the wrist and fingers through long tendons.
Section 6Muscles of the lower limb
The hip and the buttock
Your lower limb carries the whole weight of your body. It drives every step. So it holds the biggest, strongest muscles you have. At the hip is the gluteus maximus. It makes up most of the buttock. It is the largest single muscle in the body. It extends the hip with great power. It drives you up from a squat, up the stairs, and into a run.
Under it and to the side sit the gluteus medius and gluteus minimus. They abduct the thigh, moving it out to the side. Even more important, they steady the pelvis each time you stand on one leg to take a step. On the front of the hip, the deep iliopsoas is the main hip flexor. It lifts the thigh toward the chest.
The thigh and the leg
The thigh has opposing groups. On the front is the quadriceps femoris. It is four muscles: the rectus femoris and the three vastus muscles. They share one tendon over the kneecap. They extend the knee to straighten the leg for a kick or a step. On the back are the three hamstrings: the biceps femoris, semitendinosus, and semimembranosus. They do the reverse. They flex the knee and help extend the hip. On the inner thigh, the adductors squeeze the legs together.
Below the knee, the calf gives you your push-off. The gastrocnemius has two heads. It and the deeper soleus join into the Achilles (calcaneal) tendon. Together they plantarflex the ankle. That means they point the toes and lift the heel. This launches you into every step and jump. On the shin, the tibialis anterior works against them. It dorsiflexes the ankle, pulling the toes up. This keeps your toes off the ground as your foot swings forward.
| Muscle / group | Location | Main action |
|---|---|---|
| Gluteus maximus | Buttock | Extends the hip (running, stairs) |
| Gluteus medius & minimus | Side of the hip | Abduct the thigh. Steady the pelvis when you walk. |
| Iliopsoas | Deep in the front of the hip | Flexes the hip |
| Quadriceps femoris | Front of the thigh | Extends the knee |
| Hamstrings | Back of the thigh | Flex the knee, extend the hip |
| Gastrocnemius & soleus | Calf | Plantarflex the ankle (push off) |
| Tibialis anterior | Front of the leg (shin) | Dorsiflexes the ankle (toes up) |
Tap each muscle in the interactive. Trace the movers of the hip, knee, and ankle.
- The gluteus maximus extends the hip. The gluteus medius/minimus abduct the thigh and steady the pelvis when you walk.
- The quadriceps extend the knee and the hamstrings flex it. They are a front/back antagonist pair. The iliopsoas flexes the hip.
- The gastrocnemius and soleus plantarflex the ankle through the Achilles tendon. The tibialis anterior dorsiflexes it.
The chapter in one breath
- A skeletal muscle can only pull. So muscles work in opposing pairs across joints. Each one pulls its insertion toward its fixed origin.
- Every move has an agonist, antagonist, synergist, and fixator. Bones act as levers. Most are third-class levers, built for speed and range.
- Muscle names are descriptions built from six clues: location, shape, size, fiber direction, number of heads, and action.
- The head has muscles of facial expression, which insert into skin (CN VII). It also has muscles of mastication, which move the mandible (CN V).
- The trunk holds the diaphragm and intercostals for breathing. It also has the four-layer abdominal wall and the erector spinae for posture.
- The upper limb is moved by the deltoid, pectoralis major, and latissimus dorsi. The rotator cuff (SITS) steadies the shoulder. The biceps/triceps pair works the elbow.
- The lower limb's powerhouses are the glutes, the quadriceps and hamstrings, and the calf muscles. The calf muscles plantarflex the ankle through the Achilles tendon.
ReferenceWords worth knowing
Here is a quick guide to the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Abduction
- Moving a limb away from the midline of the body. The deltoid abducts the arm.
- Adduction
- Moving a limb toward the midline of the body. The thigh adductors squeeze the legs together.
- Agonist (prime mover)
- The main muscle that makes a certain move.
- Antagonist
- The muscle that works against an agonist. It relaxes and gets longer while the agonist contracts.
- Aponeurosis
- A wide, flat sheet of connective tissue. It attaches a muscle to bone or to another muscle.
- Belly
- The thick middle part of a muscle that contracts. It lies between the origin and insertion.
- Diaphragm
- The dome-shaped main muscle of breathing. It separates the chest (thoracic) and belly (abdominal) cavities. The phrenic nerve runs it.
- Erector spinae
- A group of deep back muscles. They extend the spine and hold you upright.
- Fixator
- A muscle that holds the origin, or a nearby joint, steady. This lets the prime mover work well.
- Insertion
- Where a muscle attaches to the bone that moves. It is usually the bone farther out (distal).
- Intercostal muscles
- The muscles between the ribs. The externals lift the rib cage to breathe in. The internals pull it down to breathe out hard.
- Lever
- A stiff bar (a bone) that turns on a fulcrum (a joint) to move a load. Most levers in the body are third-class.
- Masseter
- A strong chewing muscle that runs from the cheekbone to the angle of the jaw. It closes the mandible.
- Mastication
- Chewing. Muscles that move the mandible grind the food. The trigeminal nerve (CN V) runs them.
- Muscles of facial expression
- Muscles that insert into the skin of the face to make expressions. The facial nerve (CN VII) runs them.
- Origin
- Where a muscle attaches to the bone that stays fairly still. It is usually the bone closer in (proximal).
- Quadriceps femoris
- The four-headed muscle group on the front of the thigh. It extends the knee.
- Rotator cuff
- Four muscles that hold the shoulder joint steady. They are the supraspinatus, infraspinatus, teres minor, and subscapularis (“SITS”).
- Sternocleidomastoid
- A neck muscle that links the sternum, clavicle, and mastoid process. It bends the neck and turns the head.
- Synergist
- A muscle that helps an agonist or holds a joint steady during a move.
- Tendon
- A tough, cord-like band of dense connective tissue. It attaches a muscle to a bone.
Check yourself
The Nervous System & Nervous Tissue
Every thought you have had was carried by a wave of electricity. So was every move you have made and every feeling you have felt. That wave races along a living wire. This chapter tells the story of that wire, the neuron, and the tissue it lives in. First we map how the whole nervous system is set up. Then we meet the loyal helper cells that keep neurons alive. Then we get to the heart of it. You will see how a neuron builds up an electrical charge and fires an action potential. You will see how that signal flies down an axon wrapped in myelin. And you will see how it hands the message to the next cell across a tiny gap. Learn these ideas well. The rest of the nervous system, from the brain and spinal cord to reflexes and the senses, is built on this one theme.
By the end of this chapter you can
- Divide the nervous system into its central and peripheral parts. Also divide it into its sensory, motor, somatic, and autonomic pathways.
- State the nervous system's three core jobs: sensory input, integration, and motor output. Give an example of each.
- Name the parts of a neuron and the six neuroglia. Say what each glial cell does and where it lives.
- Explain how the resting membrane potential of about −70 mV is created and kept steady.
- Walk through the phases of an action potential. Explain why it is all-or-nothing and only goes one way.
- Compare continuous and saltatory conduction. List the two things that set how fast a signal travels.
- Describe the steps of chemical synaptic transmission. Tell an excitatory signal from an inhibitory one.
- Link each process to a real medical problem, such as multiple sclerosis, local anesthetics, and nerve gas.
Section 1How the nervous system is organized

One control center, wires everywhere
The nervous system is the body's fast message network. Scientists split it up in two ways. One way is by where the parts are. The other is by which way the signals flow.
By location, there are just two parts. The central nervous system (CNS) is the brain and spinal cord. It is the headquarters, where information is handled and choices are made. The peripheral nervous system (PNS) is everything else. It is the nerves and ganglia (clusters of nerve cell bodies) that fan out from the CNS to every corner of the body. Think of the CNS as a computer. The PNS is the set of cables that run to every sensor and every motor.
Three jobs: sense, decide, act
A nerve pathway may look complex. But it is always doing one of three things. First comes sensory input. Receptors sense a change, inside or outside the body, and send that news toward the CNS. Second is integration. The CNS sorts through the incoming signals and decides what to do, if anything. Third is motor output. A command travels away from the CNS to an effector, which is a muscle or a gland. The effector carries out the response.
Touch a hot stove, and all three happen in a heartbeat. Skin receptors sense heat (input). The spinal cord decides "pull back" (integration). Arm muscles yank the hand away (output).
The words for these directions are worth learning. You will see them on every diagram. Neurons that carry signals toward the CNS are afferent, or sensory. Neurons that carry commands away from the CNS are efferent, or motor.
The efferent side splits again by where its signals go. The somatic nervous system carries commands you control to skeletal muscle. These are the moves you choose. The autonomic nervous system (ANS) runs the automatic chores inside you. It sends signals to cardiac muscle, smooth muscle, and glands without you having to think about it. The ANS itself has two arms that usually work against each other. The sympathetic division is the "fight-or-flight" gas pedal. The parasympathetic division is the "rest-and-digest" brake.
| Division | What it includes | Direction / job |
|---|---|---|
| Central (CNS) | Brain and spinal cord | Integration: sorts input, sends out commands |
| Peripheral (PNS) | Nerves and ganglia | Carries signals to and from the CNS |
| Sensory (afferent) | Sensory neurons | Toward the CNS (input) |
| Motor (efferent) | Motor neurons | Away from the CNS (output) |
| Somatic | Motor neurons to skeletal muscle | Movement you choose (voluntary) |
| Autonomic (ANS) | Motor neurons to heart muscle, smooth muscle & glands | Automatic (involuntary) control |
| Sympathetic | Leaves the spinal cord from the chest and lower back (thoracolumbar) | Fight-or-flight (speed up) |
| Parasympathetic | Leaves from the brain and the base of the spine (craniosacral) | Rest-and-digest (calm down) |
Tap through each division in the interactive below. Try central and peripheral, sensory and motor, and somatic and autonomic.
- By location, the CNS is the brain and spinal cord. The PNS is the nerves and ganglia.
- By job, afferent (sensory) signals arrive at the CNS. Efferent (motor) signals exit toward effectors.
- The motor side splits into somatic (voluntary, skeletal muscle) and autonomic (involuntary). The autonomic side splits into sympathetic and parasympathetic.
- Every act of the nervous system comes down to three steps: sensory input → integration → motor output.
Section 2Neurons and their support crew
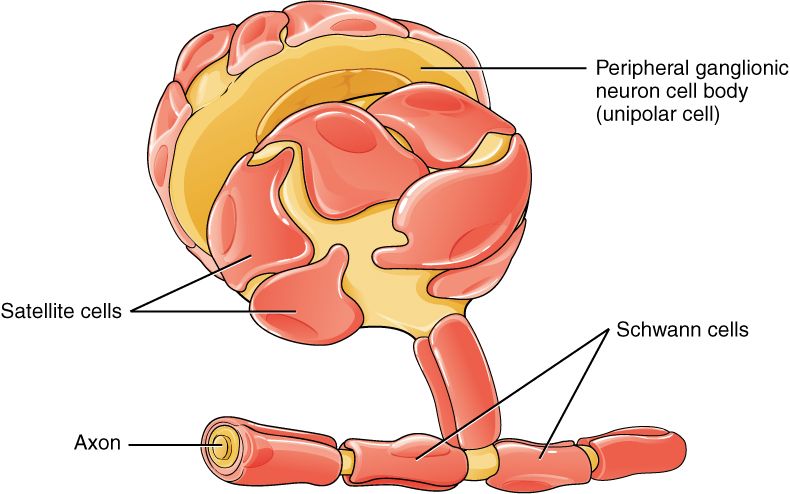
The neuron: a cell built to signal
Before we meet the helper cells, meet the star. A neuron is a nerve cell. It is an excitable cell, which means it can fire an electrical signal. Its shape suits one purpose. It takes in a signal at one end and passes it on from the other. Three parts do the work.
The dendrites are branches, like antennae, that receive incoming signals. The cell body, or soma, holds the nucleus. It keeps the cell alive and running. It is also where incoming signals are added up. The axon is one long fiber that carries the outgoing signal away. It is often wrapped in a fatty myelin sheath. It ends in axon terminals that hand the message to the next cell.
Neurons are also amitotic. This means most of them cannot divide to replace themselves. That is exactly why damage to the brain and spinal cord is so hard to repair.
The support crew: six kinds of glia
For every neuron, there are about as many neuroglia, or more. These are also called glial cells. They are the crew that feeds, insulates, cleans, and protects neurons. Glia do not fire action potentials. But without them, neurons would starve, short-circuit, and drown in waste. There are six types. Four live in the CNS, and two live in the PNS.
| Glial cell | Where | Job |
|---|---|---|
| Astrocyte | CNS | The most common type. It ties neurons to their blood supply, controls the chemicals around them, and helps form the blood–brain barrier. |
| Oligodendrocyte | CNS | Wraps CNS axons in myelin. One cell covers many axons. |
| Microglia | CNS | The brain's immune cells. They swallow germs and dead cells. |
| Ependymal cell | CNS | Line the hollow spaces of the brain. They help move cerebrospinal fluid. |
| Satellite cell | PNS | Surround and support neuron cell bodies in ganglia |
| Schwann cell | PNS | Wraps PNS axons in myelin. One cell covers one segment. |
Two cells make myelin, so keep them straight
People often mix up the two cells that make myelin. So let's pin them down now. In the CNS, an oligodendrocyte reaches out several arms. It wraps many different axons at once. In the PNS, a Schwann cell wraps itself around a single segment of one axon, like a jelly roll.
Both make the same fatty insulation. But the difference matters in medicine. Multiple sclerosis attacks CNS myelin. Guillain–Barré syndrome attacks PNS myelin. They are totally separate diseases, and they play out in different ways.
Tap each of the six glial cells. See where it sits and what it does.
- A neuron has three parts. The dendrites receive. The cell body/soma adds up signals and keeps the cell alive. The axon sends the signal on.
- The six glia in the CNS are the astrocyte, oligodendrocyte, microglia, and ependymal cell. In the PNS, they are the satellite cell and Schwann cell.
- Oligodendrocytes each wrap many CNS axons in myelin. Schwann cells each wrap one PNS segment.
- Microglia are the immune cells of the CNS. Astrocytes are the most common glia and help form the blood–brain barrier.
Section 3The resting membrane potential
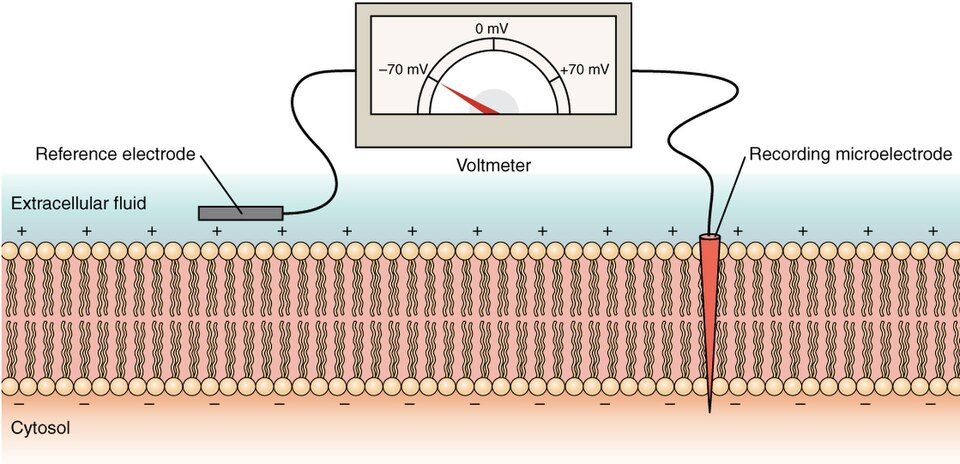
A charged battery, waiting
A neuron at rest is not doing nothing. It is armed and ready. There is a tiny voltage across its membrane. It is called the resting membrane potential, and it is about −70 mV. This means the inside of the cell is 70 millivolts more negative than the outside.
A membrane that keeps charges apart like this is called polarized. It is like a charged battery, ready to be used. Every signal a neuron sends is a quick, controlled release of that stored charge. So the first question is simple. How does the cell build up the charge in the first place?
Why the inside is negative
The answer is unequal ion distribution. Ions are charged particles. The cell keeps different amounts of each ion inside and outside. Sodium (Na⁺) is piled up outside the cell. Potassium (K⁺) is packed inside. The inside is also stuffed with large proteins and phosphates that carry negative charge. They are too big to leave.
Now add the membrane's channels. At rest, the membrane lets potassium leak through much more easily than sodium. It has many more open leak channels for K⁺. So potassium trickles out, from where there is more of it to where there is less. It carries positive charge with it. This leaves the inside more negative. The potassium leak, along with the trapped negative particles inside, is the main reason the resting voltage lands near −70 mV.
| Ion | Concentrated where | Role at rest |
|---|---|---|
| Sodium (Na⁺) | Outside the cell | Ready to rush in. The membrane is mostly closed to it at rest. |
| Potassium (K⁺) | Inside the cell | Leaks out through many open channels. This sets the resting voltage. |
| Chloride (Cl⁻) | Outside the cell | Adds to the negative inside |
| Large anions (proteins) | Trapped inside | Cannot cross, so they hold negative charge in |
The pump that never sleeps
Over time, leaks would run the gradients down. Sodium would trickle in. Potassium would drift out. The battery would go flat. To stop this, the membrane runs the sodium–potassium pump (Na⁺/K⁺ ATPase) all day and night. It burns ATP for fuel. It pumps 3 Na⁺ out for every 2 K⁺ in. This keeps rebuilding both gradients.
The pump moves three positive charges out for every two it brings in. So it also removes a little positive charge overall. This makes the inside slightly more negative. The pump is so vital that it uses a large share of the body's energy at rest. That is a big reason the brain is such a hungry organ.
Explore the ion gradients, the leak channels, and the tireless pump in the interactive below.
- The resting membrane potential is about −70 mV, with the inside negative. The membrane is polarized.
- It comes from unequal ion distribution. Na⁺ is high outside, K⁺ is high inside, and large negative particles (anions) are trapped inside.
- Potassium leaking out through open channels is the main thing that sets the resting voltage.
- The Na⁺/K⁺ pump (3 out, 2 in, using ATP) keeps up the gradients. It also makes the inside a little more negative.
Section 4The action potential
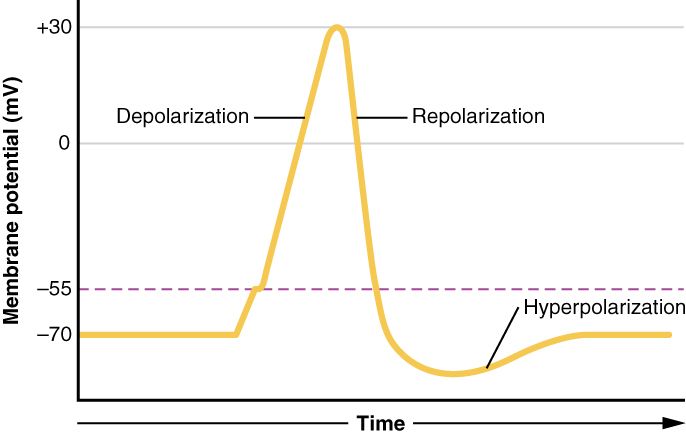
All or nothing
An action potential is the neuron's signal. It is a quick, dramatic flip of the voltage across the membrane. This flip shoots down the axon. But it only happens if the membrane is pushed up from its resting −70 mV to a key level. That level is the threshold, at about −55 mV.
Below threshold, nothing fires. Reach threshold, and a full-sized spike goes off every time. The spike is the same height whether the push was barely enough or huge. This is the famous all-or-nothing rule. A neuron cannot fire part of an action potential, just as a gun cannot fire part of a bullet. So how does a neuron signal a strong stimulus? Not with bigger spikes. It fires more often.
The upstroke: sodium floods in
The whole event is run by voltage-gated channels. These are ion gates that open when the voltage changes. At threshold, voltage-gated Na⁺ channels snap open. Sodium was piled up outside. It is pulled in by two forces: its concentration gradient and the negative inside. So it floods in.
Each positive charge that enters makes the inside less negative. That opens even more sodium gates. This fast, self-boosting rush is called depolarization. It drives the voltage from −55 all the way up to about +30 mV. For an instant, the inside of the cell is actually positive.
The downstroke and the reset
The spike ends as fast as it began. At the peak, the Na⁺ channels inactivate, which means they shut on their own. Now the slower voltage-gated K⁺ channels finish opening. Potassium rushes out. It carries positive charge away, and the voltage drops back down. This is repolarization.
The potassium gates are slow to close. So a little too much K⁺ leaves. The membrane briefly dips below rest, to about −80 mV. This dip is called hyperpolarization, or the undershoot. Then the leak channels and the Na⁺/K⁺ pump bring things back to a tidy −70 mV.
During the recovery there is a refractory period. In the first part (absolute), the axon cannot fire at all. In the later part (relative), it needs an extra-strong stimulus to fire.
| Phase | What the channels do | Voltage |
|---|---|---|
| Resting | Only leak channels are open | −70 mV |
| Threshold | Enough Na⁺ gates start to open | −55 mV |
| Depolarization | Voltage-gated Na⁺ channels open. Na⁺ rushes in. | rising to +30 mV |
| Repolarization | Na⁺ channels inactivate. K⁺ channels open, and K⁺ leaves. | falling back down |
| Hyperpolarization | K⁺ channels close slowly, so the voltage dips a bit too far | ~−80 mV |
| Return to rest | Leak channels + Na⁺/K⁺ pump restore the balance | −70 mV |
Hit "Stimulate" in the interactive below. Follow the voltage through every phase.
- An action potential fires only if the membrane reaches threshold (~−55 mV). Then it is all-or-nothing.
- Depolarization: voltage-gated Na⁺ channels open, Na⁺ floods in, and the voltage climbs to about +30 mV.
- Repolarization: Na⁺ channels inactivate, K⁺ channels open, K⁺ leaves, and the voltage falls. A brief hyperpolarization follows.
- The refractory period keeps the signal moving one way and limits how fast a neuron fires. The strength of a stimulus is coded by frequency.
Section 5Saltatory conduction & speed
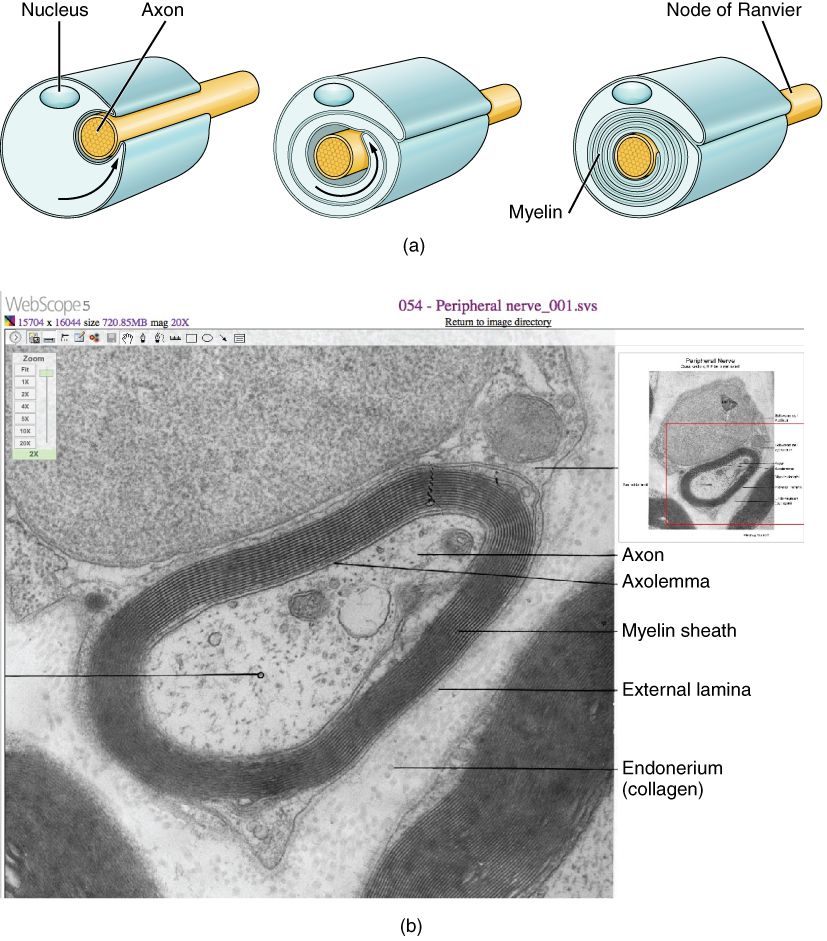
Crawling versus leaping
Once an action potential starts, it has to travel the whole length of the axon. There are two ways to do that. Some axons are bare, or unmyelinated. On these, the spike rebuilds itself at every patch of membrane in a row. It marches along step by step. This is continuous conduction. It works, but it is slow.
Other axons are myelinated. The fatty sheath insulates long stretches, so current cannot leak out there. The action potential can only rebuild itself at the bare gaps between the myelin segments. So the signal seems to jump from gap to gap. It skips the insulated parts in between. This leaping is saltatory conduction. The name comes from the Latin word saltare, which means "to leap." It is much faster.
Nodes of Ranvier
The bare gaps have a name worth knowing: the nodes of Ranvier. These small bare rings are packed with voltage-gated sodium channels. So the action potential is rebuilt fresh and at full strength at each node. Between the nodes is a covered stretch called the internode. It carries the current quickly and passively, with no channels to slow it down. So the impulse hops from node to node. It rebuilds, glides, rebuilds, and glides. This covers far more ground in the same time than a steady crawl.
What sets conduction speed
Two features decide how fast a nerve fiber carries a signal. The first is myelination. A myelinated axon is much faster than an unmyelinated one of the same size. The second is axon diameter, or how thick the axon is. Thick axons are faster because current flows through them more easily. In the same way, a wide pipe moves water faster than a narrow one.
The body uses both of these on purpose. Large fibers with thick myelin carry reflexes and the sense of where your limbs are. They can carry signals at over 100 meters per second. Thin fibers with no myelin carry dull, aching pain. They crawl along at barely one meter per second. Sharp pain that you can pinpoint travels on thinner myelinated fibers. These are faster than the dull kind, but far short of that top speed.
| Factor | Faster conduction | Slower conduction |
|---|---|---|
| Myelin | Myelinated (saltatory) | Unmyelinated (continuous) |
| Axon diameter | Large diameter (thick) | Small diameter (thin) |
| Typical role | Reflexes, sharp pain you can pinpoint, limb position | Dull aching pain, temperature, autonomic signals |
Race a myelinated signal against an unmyelinated one in the interactive below. Watch it leap the nodes.
- Continuous conduction rebuilds the spike at every patch. It is slow and happens on unmyelinated axons. Saltatory conduction leaps between gaps. It is fast and happens on myelinated axons.
- The bare gaps are the nodes of Ranvier, packed with Na⁺ channels. The covered internodes carry current passively.
- Speed goes up with myelination and with axon diameter.
- Diseases that strip myelin slow or block signals. Examples are MS in the CNS and Guillain–Barré in the PNS.
Section 6The synapse: passing the message on
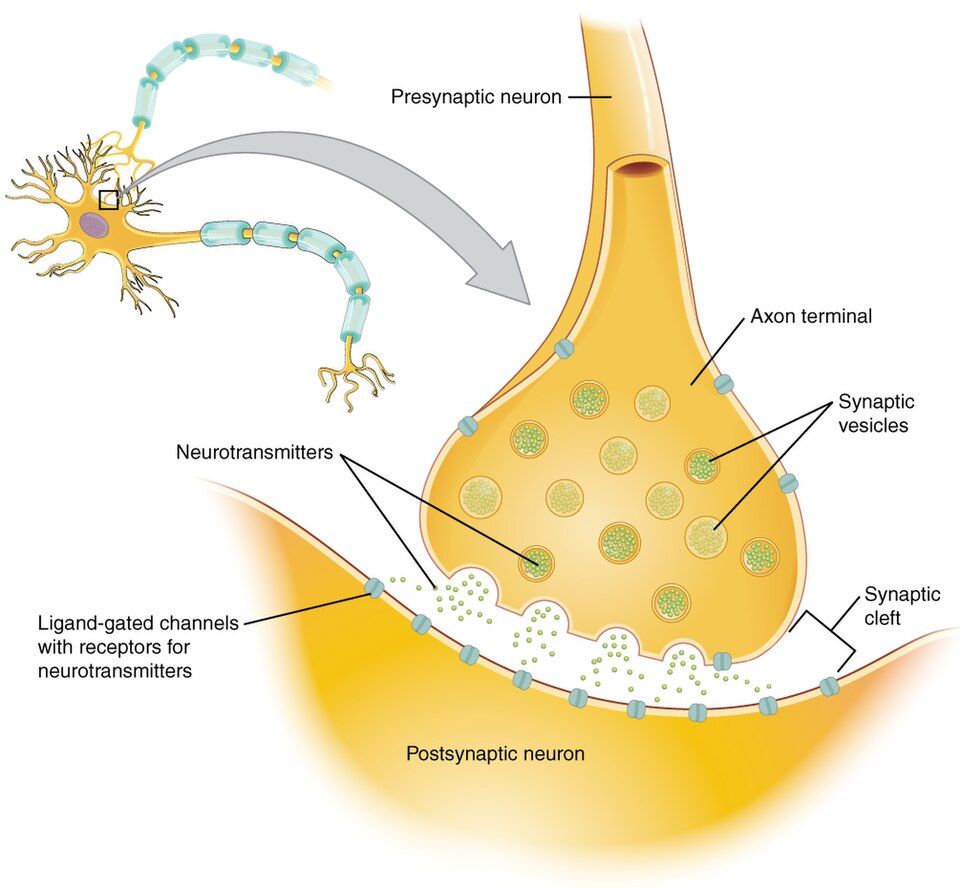
Neurons don't quite touch
An action potential reaches the end of an axon. Now it has a problem. The next cell is not connected to it. There is a tiny gap in between, called the synaptic cleft. The whole meeting point is the synapse. The neuron sending the message is presynaptic ("before the synapse"). The cell getting it is postsynaptic ("after the synapse").
The electrical signal cannot jump the gap by itself. So most synapses turn it into a chemical messenger, called a neurotransmitter. The chemical drifts across the gap. On the far side, it creates the signal again. The message goes from electrical, to chemical, to electrical again.
Six steps across the gap
Chemical transmission always follows the same six steps. (1) The action potential arrives at the presynaptic axon terminal. (2) Its voltage opens voltage-gated calcium (Ca²⁺) channels, and calcium flows into the terminal. (3) Calcium makes tiny sacs called synaptic vesicles merge with the membrane and dump what they hold.
(4) The neurotransmitter is released (by exocytosis) and drifts across the cleft. (5) It binds receptors on the postsynaptic membrane. This opens ion channels, which create a small graded potential. (6) The neurotransmitter is quickly cleared away. Enzymes may break it down. It may be taken back into the sending cell (reuptake). Or it may drift away. This keeps the signal crisp and short.
Excitatory or inhibitory?
What the postsynaptic cell does next depends on which neurotransmitter and receptor are involved. An excitatory signal depolarizes the postsynaptic membrane. It nudges the cell toward threshold. This is an excitatory postsynaptic potential (EPSP). An inhibitory signal hyperpolarizes the membrane. It pushes the cell away from threshold. This is an inhibitory postsynaptic potential (IPSP).
One neuron gets thousands of these signals at once. It sums, or adds up, all of them. It fires only if the "go" signals beat the "stop" signals by enough to reach threshold. In other words, the synapse is where the nervous system actually makes decisions.
| Neurotransmitter | Typical effect | Where / note |
|---|---|---|
| Acetylcholine (ACh) | Excites skeletal muscle | Neuromuscular junction (nerve meets muscle). Broken down by acetylcholinesterase. |
| Glutamate | Excitatory | The main “go” transmitter of the CNS |
| GABA | Inhibitory | The main “stop” transmitter of the CNS |
| Glycine | Inhibitory | Common in the spinal cord |
| Norepinephrine | Excites or inhibits | Sympathetic (fight-or-flight), mood, alertness |
| Dopamine | Modulatory (tunes other signals up or down) | Reward, movement. Disrupted in Parkinson disease. |
Step through the electrical-to-chemical-to-electrical handoff in the interactive below.
- Neurons meet at a synapse, across the synaptic cleft. The sender is presynaptic. The receiver is postsynaptic.
- Transmission: action potential (AP) arrives → Ca²⁺ enters → vesicles merge → neurotransmitter released → binds receptors → cleared.
- An EPSP pushes the postsynaptic cell toward threshold. An IPSP pushes it away. The cell sums them to decide whether to fire.
- Key transmitters are ACh (muscle), glutamate (main excitatory), and GABA (main inhibitory). The synapse is where most drugs act.
The chapter in one breath
- The nervous system splits into the CNS (brain and spinal cord) and the PNS (nerves and ganglia). Its work is always sensory input → integration → motor output.
- Motor pathways split into somatic (voluntary) and autonomic (involuntary). The autonomic side splits into sympathetic and parasympathetic. Afferent arrives, and efferent exits.
- A neuron (dendrites, soma, axon) is supported by six neuroglia. The astrocyte, oligodendrocyte, microglia, and ependymal cell are in the CNS. The satellite cell and Schwann cell are in the PNS.
- At rest, the membrane is polarized to about −70 mV. This is set by K⁺ leaking out and by trapped negative particles inside. The Na⁺/K⁺ pump keeps it steady.
- Reaching threshold (~−55 mV) fires an all-or-nothing action potential. Na⁺ comes in (depolarize), then K⁺ goes out (repolarize). A refractory period follows.
- Myelin lets the impulse leap from node to node. This is saltatory conduction. Speed goes up with myelination and diameter.
- At the synapse, the signal crosses as a neurotransmitter. The postsynaptic cell sums EPSPs and IPSPs to decide whether to fire.
ReferenceWords worth knowing
Here is a quick guide to the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Action potential
- The neuron's electrical signal. It is a quick, all-or-nothing flip of the membrane voltage that travels down an axon.
- Afferent (sensory) neuron
- A neuron that carries signals toward the central nervous system. Afferent arrives.
- All-or-nothing
- The rule that a neuron fires either a full-sized action potential or none at all. The strength of a stimulus is coded by how often the neuron fires.
- Astrocyte
- The most common glial cell in the CNS. It ties neurons to blood vessels, controls the chemicals around them, and helps form the blood–brain barrier.
- Autonomic nervous system
- The automatic (involuntary) motor division. It controls heart muscle, smooth muscle, and glands. It splits into sympathetic and parasympathetic arms.
- Axon
- The one long fiber of a neuron. It carries the action potential away from the cell body.
- Depolarization
- A shift of the membrane voltage toward positive (less negative). It happens mainly when Na⁺ enters the cell.
- Efferent (motor) neuron
- A neuron that carries commands away from the central nervous system to an effector. Efferent exits.
- Myelin sheath
- Fatty insulation wrapped around an axon that speeds up signals. Oligodendrocytes make it in the CNS, and Schwann cells make it in the PNS.
- Neuroglia
- The helper cells of nervous tissue. They feed, insulate, clean, and protect neurons. There are six types across the CNS and PNS.
- Neuron
- The nerve cell that sends signals. It has dendrites (receive), a cell body (adds up signals), and an axon (sends the signal on).
- Neurotransmitter
- A chemical messenger released across a synapse. It passes a signal to the next cell.
- Node of Ranvier
- A bare gap between myelin segments, packed with Na⁺ channels. The action potential is rebuilt here during saltatory conduction.
- Refractory period
- A short time after a spike when that patch of membrane cannot fire again (absolute) or needs a stronger push (relative). It makes signals travel one way.
- Repolarization
- The return of the membrane voltage toward its negative resting value. It happens mainly when K⁺ leaves the cell.
- Resting membrane potential
- The voltage across a resting neuron's membrane, about −70 mV with the inside negative. Ion gradients and the K⁺ leak set it.
- Saltatory conduction
- Fast signaling along a myelinated axon. The signal leaps from node to node.
- Schwann cell
- The PNS glial cell that wraps one segment of an axon in myelin.
- Sodium–potassium pump
- A membrane pump powered by ATP. It moves 3 Na⁺ out and 2 K⁺ in, which keeps up the ion gradients.
- Synapse
- The meeting point where one neuron passes a message to another cell, across the synaptic cleft.
- Threshold
- The membrane voltage (about −55 mV) that must be reached to set off an action potential.
Check yourself
Anatomy of the Nervous System
Inside your skull sits the most complex object we know of. It is about three pounds of soft tissue that lets you read this line, remember when you were small, and pull your hand off a hot stove before you even feel the burn. This chapter is a guided tour of that brain. We will walk over the wrinkled top of the cerebrum. We will drop down through its inner regions to the brainstem, which keeps you alive, and look at the cerebrospinal fluid that cushions it all. We will peel back the three meninges, the wraps that guard it. We will follow the spinal cord down its bony tunnel. Last, we will count off the twelve cranial nerves that leave the brain directly. By the end, you will be able to picture a whole brain and name what you see.
By the end of this chapter you can
- Find the four lobes of the cerebrum. Name the skull bone over each one, and match each lobe to its main jobs.
- Find the primary motor and primary somatosensory cortex. Find the central sulcus, the groove that splits them.
- Split the brain into its four main regions: cerebrum, diencephalon, brainstem, and cerebellum. Say what each one does.
- Trace how cerebrospinal fluid flows through the four ventricles and out into the subarachnoid space. Explain its three jobs.
- Name the three meninges in order. Describe the spaces between them, and link each one to an emergency.
- Read a cross-section of the spinal cord, with its gray horns, white columns, and dorsal and ventral roots. Explain its one-way traffic rule.
- List the twelve cranial nerves in order. Sort each one as sensory, motor, or mixed, and give its main job.
Section 1The cerebral lobes
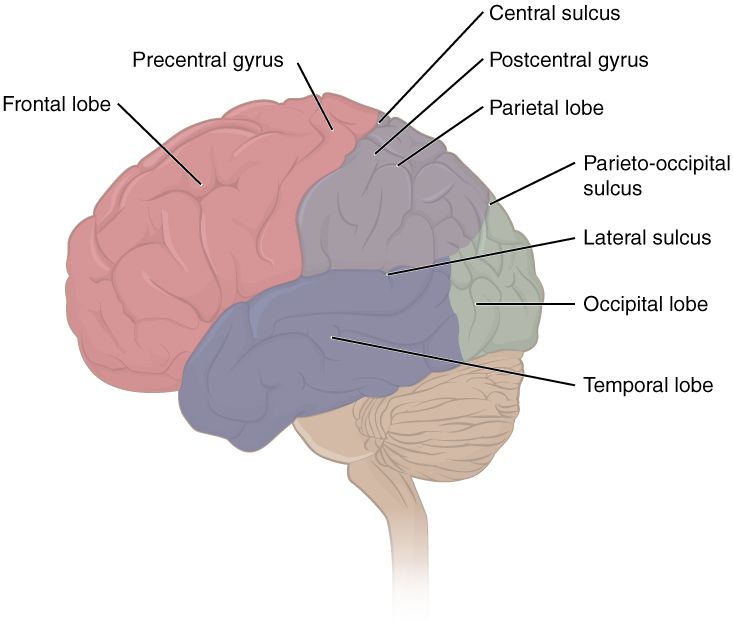
A wrinkled sheet of gray matter
Picture a brain. You likely see a pale, deeply folded dome. That is the cerebrum, the biggest part of the brain and the place where thinking happens. Its outer layer, only a few millimeters thick, is the cerebral cortex. It is a sheet of gray matter, which is packed with billions of nerve cell bodies.
Under the cortex lies white matter. It is made of axons, the long nerve fibers, wrapped in a fatty coat called myelin, and these fibers wire one part of the brain to another. The wrinkles are not just for looks, though. Each ridge is a gyrus, and each groove is a sulcus. A deep groove is a fissure. Folding lets a huge sheet of cortex fit inside the skull, like a crumpled towel in a cup. About two-thirds of it is hidden down in the grooves. More cortex means more brain power. That is why smart animals tend to have very folded brains.
Four lobes, four skull bones
Each half of the brain is called a hemisphere, and the cortex of each half has four lobes. They are easy to name, because each lobe gets its name from the skull bone right on top of it. Two big grooves mark the borders. The central sulcus runs down across the top of the brain and splits the frontal lobe in front from the parietal lobe behind it. The deep lateral sulcus (Sylvian fissure) runs along the side and marks off the temporal lobe below. At the very back sits the occipital lobe. One more area, the insula, is tucked deep inside the lateral sulcus, and it is often called a hidden fifth lobe.
The two halves are not exact twins. They show lateralization, which means they split up the work. One side tends to lead on certain tasks. Language is usually on the left, while space and music skills are often on the right. The two halves talk all the time through a thick bridge of white matter called the corpus callosum. It carries hundreds of millions of axons from one side to the other.
Who does what
Each lobe has its own special jobs. A few areas are worth learning well, because damage to them causes classic, testable problems. Just in front of the central sulcus is a strip called the precentral gyrus. It is the primary motor cortex, which sends the orders for movements you choose to make. Just behind the central sulcus is the postcentral gyrus. It is the primary somatosensory cortex, which takes in touch, pressure, and temperature from the whole body. Each strip holds a map of the body that is upside down and out of shape, with huge areas for the hands and face.
| Lobe | Sits under | Main jobs |
|---|---|---|
| Frontal | Frontal bone | Movements you choose (primary motor cortex), planning, judgment, personality, and making speech (Broca’s area) |
| Parietal | Parietal bone | Touch, pressure, pain, and temperature (primary somatosensory cortex); sense of space |
| Temporal | Temporal bone | Hearing, smell, memory, and understanding language (Wernicke’s area) |
| Occipital | Occipital bone | Vision; holds the primary visual cortex |
Tap through the lobes and watch each one light up below.
- The cerebral cortex is a folded sheet of gray matter. Its gyri (ridges) and sulci (grooves) fit more surface into the skull.
- There are four lobes: frontal, parietal, temporal, occipital. Each is named for the skull bone on top of it.
- The central sulcus splits the motor cortex (precentral, in front) from the somatosensory cortex (postcentral, behind).
- The corpus callosum links the two halves. The halves split up the work, which is called lateralization.
Section 2The major brain regions
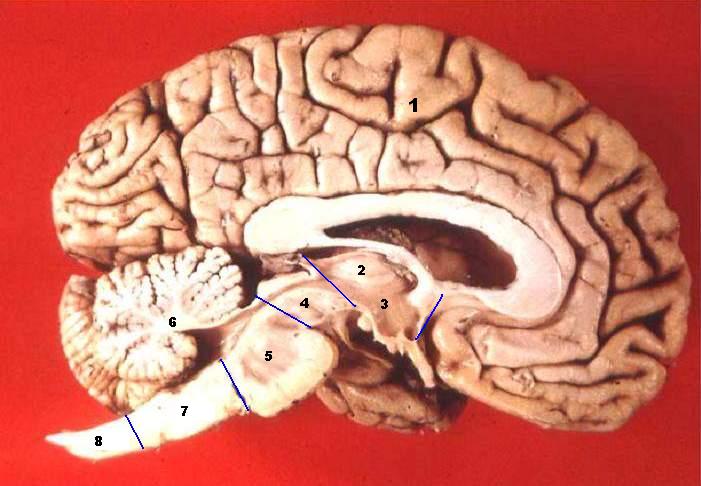
Slice it down the middle
The lobes are only the outside story. To see how the whole brain is built, picture cutting it right down the middle. This cut is called a midsagittal section. On the cut face you will see four main regions, which stack from the thinking parts on top to the life-support parts below. They are the cerebrum, the diencephalon, the brainstem, and the cerebellum.
Here is a rough rule. The higher a part sits, the more “human” and chosen its job. The lower it sits, the older and more automatic its job. You can lose a lot of cerebrum and still live. But a tiny stroke in the brainstem can kill you.
The diencephalon: the brain’s relay and thermostat
The diencephalon is buried under the cerebrum. It wraps around the third ventricle, one of the brain’s fluid-filled spaces. It is small but very important, and it has two stars. The first is the thalamus, the brain’s main train station. Almost every sense signal heading to the cortex, such as sight, sound, touch, and taste, stops here first. The thalamus sorts each signal and sends it on. Smell is the one sense that skips it.
Below and in front sits the hypothalamus. It is only about the size of an almond, yet it runs a huge share of homeostasis, the body’s way of keeping things steady inside. It controls body temperature, hunger, thirst, and the sleep–wake cycle. It also runs the pituitary gland that hangs below it, so it steers that gland’s hormones. The hypothalamus is where the nervous system and the hormone (endocrine) system shake hands.
The brainstem and the cerebellum
The brainstem links the brain to the spinal cord, and inch for inch, it is the most vital tissue you have. From top to bottom, it has three parts: the midbrain, the pons, and the medulla oblongata. The medulla holds the reflex centers that set your heart rate, blood pressure, and breathing. You never think about these jobs, but you cannot live without them. All twelve cranial nerves, except the first two, attach to the brainstem.
Behind the brainstem, tucked under the occipital lobe, is the cerebellum. Its name means “little brain,” and it is tightly folded. It fine-tunes movement, keeps your balance, and makes your motions smooth. It does not start a movement. Instead, it edits one, like an editor fixing a draft. That is why damage to it makes a person clumsy and unsteady, but not paralyzed.
| Region | Key parts | Main job |
|---|---|---|
| Cerebrum | Two hemispheres, cortex, corpus callosum | Thinking, feeling, movements you choose, memory, language |
| Diencephalon | Thalamus, hypothalamus, epithalamus | Relays sense signals (thalamus); keeps the body steady and runs hormones (hypothalamus) |
| Brainstem | Midbrain, pons, medulla oblongata | Life-saving reflexes (heartbeat, breathing), hub for cranial nerves, highway between brain and cord |
| Cerebellum | Two hemispheres, folia (folds), vermis (middle strip) | Teamwork of muscles, balance, smooth and exact movement |
Cut the brain down the middle and tap each region below.
- There are four main regions: cerebrum, diencephalon, brainstem, cerebellum. Higher parts do chosen tasks. Lower parts do automatic ones.
- The thalamus passes almost all sense signals on to the cortex. The hypothalamus keeps the body steady and runs the pituitary.
- The brainstem (midbrain, pons, medulla) controls life-saving reflexes. Most cranial nerves attach to it.
- The cerebellum smooths movement and keeps balance. It edits motion. It does not start it.
Section 3Ventricles & cerebrospinal fluid
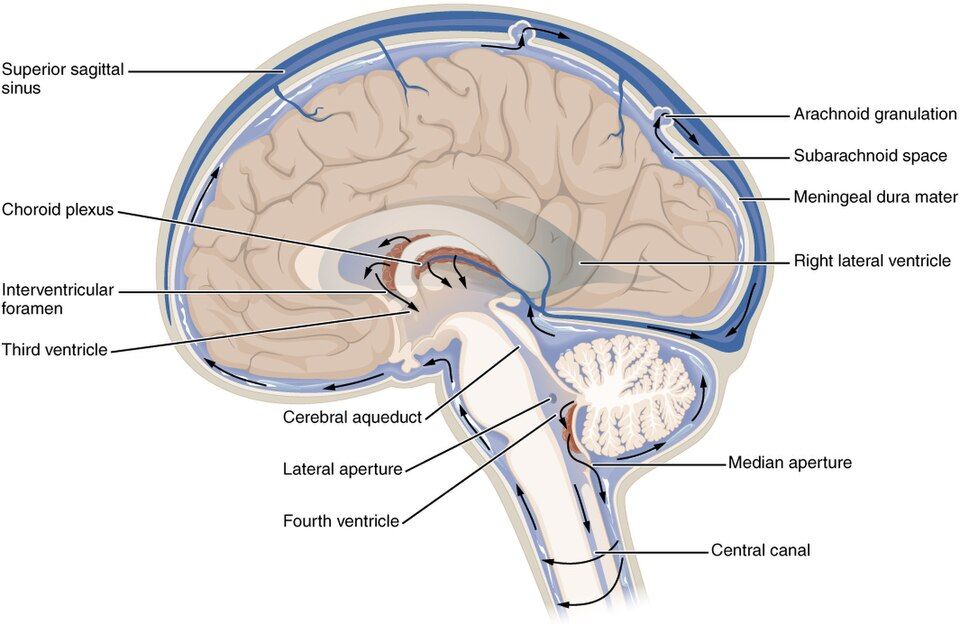
A brain that floats
The brain is not solid all the way through. In its core is a set of linked hollow rooms called the ventricles, and a clear liquid fills them and also bathes the outside of the brain. This liquid is cerebrospinal fluid, or CSF. There are four ventricles. Two big, C-shaped lateral ventricles sit one in each half of the brain. A thin, slit-like third ventricle sits in the middle of the diencephalon. A diamond-shaped fourth ventricle sits between the brainstem and the cerebellum.
CSF is made by the choroid plexus. This is a lacy web of tiny blood vessels (capillaries) that lines the ventricles. It filters plasma, the liquid part of blood, and makes about 500 mL of CSF a day. Yet the total amount stays near 150 mL. That is because the fluid is drained and replaced several times each day.
Following the flow
CSF is not a still pond. Instead, it flows on a one-way path, from the top of the ventricles down and out around the brain and cord. Trace it once and you will remember it. Fluid made in the lateral ventricles passes through small holes called the interventricular foramina and enters the third ventricle. Then it flows down a narrow channel, the cerebral aqueduct, into the fourth ventricle.
From there, it leaves through three small openings into the subarachnoid space, which surrounds the whole brain and spinal cord. This gives the whole central nervous system a liquid cushion. Last, the fluid goes back into the blood through arachnoid granulations, little bumps shaped like cauliflower that poke into the large veins that drain the brain. That closes the loop.
| Step | Structure | What happens |
|---|---|---|
| 1 | Choroid plexus (lateral ventricles) | CSF is made from filtered blood plasma |
| 2 | Interventricular foramina | Fluid passes into the third ventricle |
| 3 | Cerebral aqueduct | Fluid flows down to the fourth ventricle |
| 4 | Openings → subarachnoid space | Fluid bathes the brain and spinal cord |
| 5 | Arachnoid granulations | Fluid goes back into the blood in the veins |
Why the fluid matters
CSF does three jobs. The first is buoyancy, which means it helps the brain float. The brain weighs about 1,400 g, but floating in CSF it presses down with a weight of only about 50 g. Without this, the brain would crush its own base. The second job is protection. The liquid soaks up shocks, so the brain bobs gently instead of slamming into the skull during a bump. The third job is chemical stability. CSF brings food in and washes waste out, and it also helps keep the exact mix of salts (ions) that nerve cells need to fire.
Watch the fluid flow and tap each chamber below.
- There are four ventricles: two lateral, the third, and the fourth. They are hollow rooms filled with CSF.
- The choroid plexus makes CSF. It flows lateral → third → fourth ventricle → subarachnoid space → blood in the veins.
- CSF gives the brain and cord buoyancy, shock protection, and chemical stability.
- A blocked flow causes hydrocephalus, with swollen ventricles and rising pressure.
Section 4The meninges
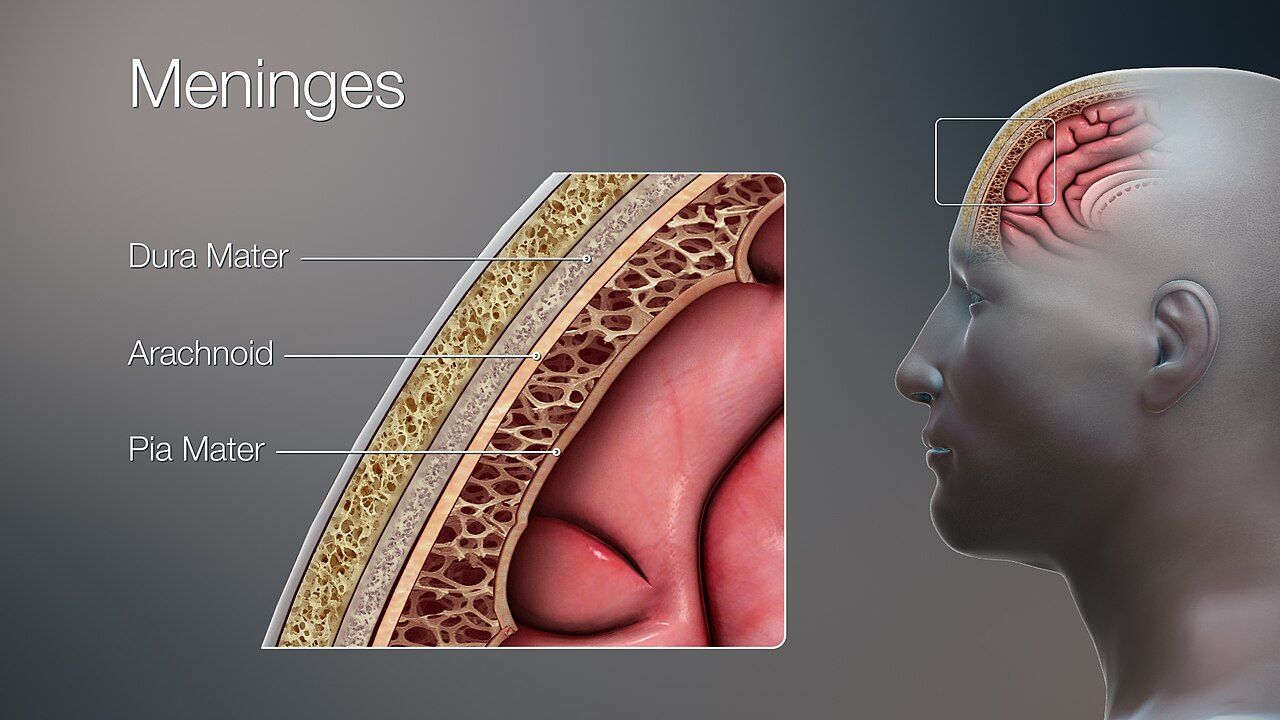
Three coats around the cord
The brain and spinal cord are too precious to rest right against bone. Instead, they are wrapped in three thin sheets of tissue called the meninges. From the outside in, they are the dura mater, the arachnoid mater, and the pia mater. Learn them in that order, because the spaces between them are where the big medical emergencies happen. The Latin names tell you what they are like. Dura mater means “tough mother.” Pia mater means “tender mother.”
From tough to tender
The dura mater is the outer layer, and it is thick, strong, and like leather. Around the brain it has two layers. Where the two layers pull apart, they form the dural venous sinuses, channels that drain blood from the brain. The dura also folds inward. One fold, the falx cerebri, dips down between the two halves of the brain and holds it steady.
Under the dura is the arachnoid mater. It is a thin layer that looks like a web, and its name comes from the Greek word for spider. Fine threads called arachnoid trabeculae cross the gap beneath it. That gap is the subarachnoid space, and it is filled with CSF. Last comes the pia mater, a very thin film that is rich in blood vessels. It clings to every ridge and groove of the brain, like plastic wrap pressed into every fold.
| Layer | What it is like | Space / feature |
|---|---|---|
| Dura mater | Tough outer coat, like leather | Forms dural venous sinuses; the epidural space lies outside it |
| Arachnoid mater | Thin middle layer, like a web | The subdural space is above it; the subarachnoid space (with CSF) is below it |
| Pia mater | Thin inner film, full of blood vessels | Sticks right onto the brain and cord |
Peel back the layers one at a time below.
- The three meninges, from outside in, are the dura mater (tough), arachnoid mater (like a web), and pia mater (thin and soft).
- The subarachnoid space, under the arachnoid, holds flowing CSF.
- The pia mater follows every fold of the brain. The dura forms blood channels (sinuses) and steadying folds like the falx cerebri.
- The spaces name the bleeds. An epidural bleed is from an artery and lens-shaped. A subdural bleed is from veins and crescent-shaped. Infection of the meninges is meningitis.
Section 5The spinal cord
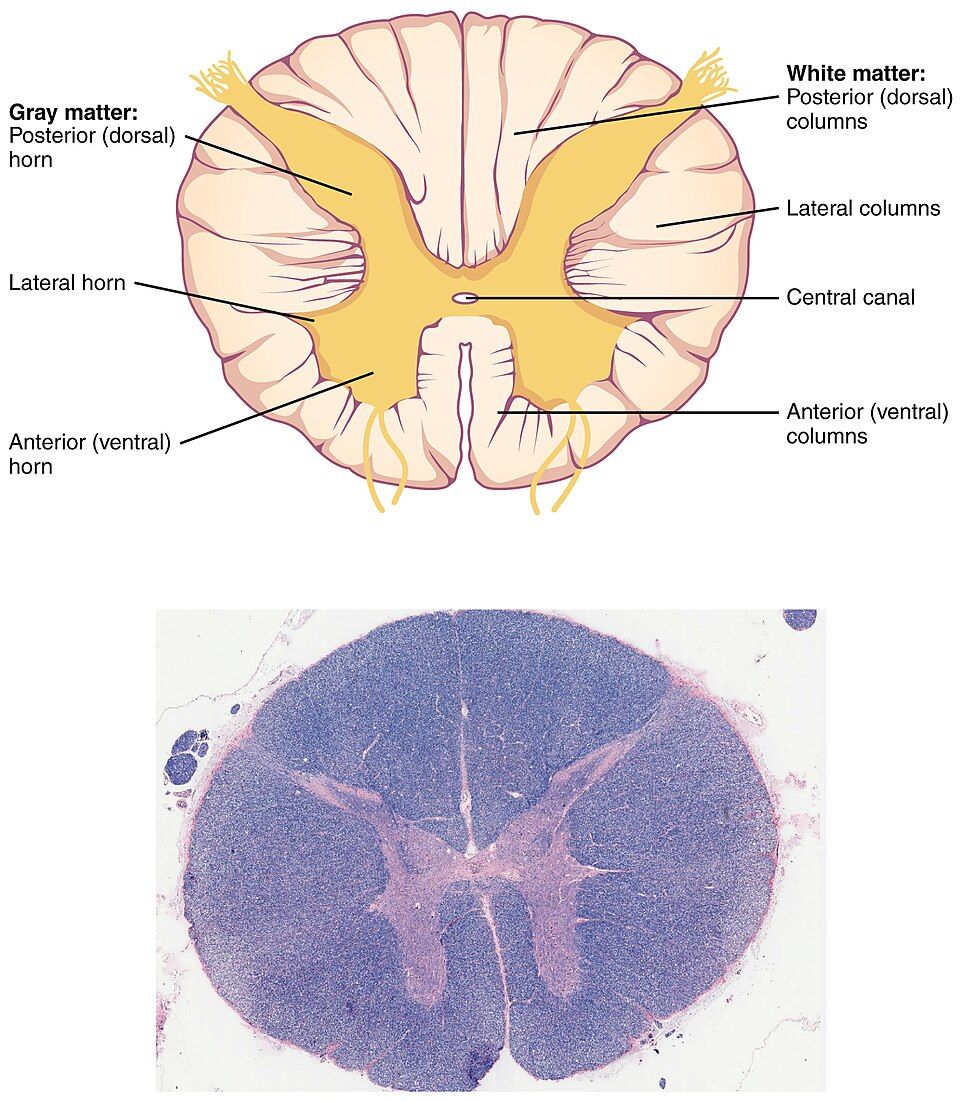
A cable and a switchboard
The spinal cord is the body’s main message cable. It starts at the bottom of the brainstem and runs down through a tunnel in the backbone (the vertebral column). It ends near the first or second lumbar bone of the lower back (L1–L2). Below that, it splits into a spray of nerve roots called the cauda equina, a name that means “horse’s tail.”
The cord does two things at once. First, it carries messages up and down between the body and the brain. Second, it works as its own local switchboard that can handle reflexes without waiting for the brain.
Reading a slice
Cut the cord across, and you will see a neat layout. In the center is a region of gray matter shaped like a butterfly or the letter H. It holds nerve cell bodies, and around it is white matter, made of coated nerve fibers in bundles. This is the reverse of the brain, where gray matter is on the outside.
The gray matter has wings called horns. The dorsal (posterior) horns, toward the back, handle incoming sensory signals. The ventral (anterior) horns, toward the front, send out motor orders to muscles. Small lateral horns on the sides, in the chest and upper belly part of the cord, hold nerve cells of the automatic (autonomic) system. A tiny central canal, filled with CSF, runs down the middle.
One-way traffic at the roots
Each spinal nerve splits into two roots where it joins the cord. These roots follow a strict one-way traffic rule. The dorsal root carries sensory signals into the cord. It has a clear bulge called the dorsal root ganglion, which is where the sensory nerve cell bodies sit. The ventral root carries motor signals out to muscles and glands.
Just past the cord, the two roots join into one mixed spinal nerve. There are 31 pairs of these nerves. The white matter is sorted into columns. The columns hold bundles of fibers called tracts. Some tracts go up and carry feeling, while others go down and carry movement orders. They are the express lanes that run the length of the cord.
| Structure | Type | Function |
|---|---|---|
| Dorsal (posterior) horn | Gray matter | Takes in sensory signals |
| Ventral (anterior) horn | Gray matter | Sends motor orders to muscles |
| Dorsal root (with ganglion) | Sensory | Carries feeling into the cord |
| Ventral root | Motor | Carries orders out of the cord |
| White columns / tracts | White matter | Highways going up (sensory) and down (motor) |
Slice the cord and tap each part below.
- The cord runs to about L1–L2. Below that, it goes on as the nerve roots of the cauda equina. 31 pairs of spinal nerves branch off.
- In a slice, gray matter (horns) sits in the center, with white matter (tracts) around it. The brain is the other way around.
- Dorsal horns and roots = sensory in. Ventral horns and roots = motor out. This is the Bell–Magendie rule.
- The dorsal root ganglion holds sensory cell bodies. A lumbar puncture is done below the end of the cord to be safe.
Section 6The cranial nerves
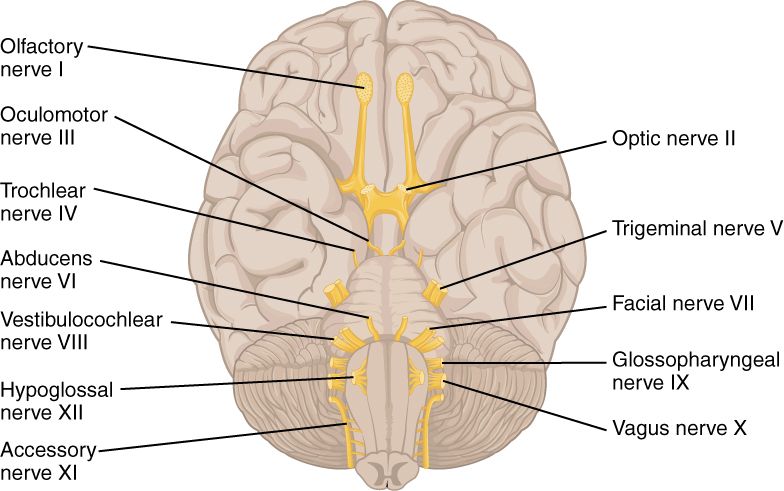
Twelve nerves straight from the brain
Most nerves branch off the spinal cord. But twelve special pairs come straight out of the brain. These are the cranial nerves, and they are numbered with Roman numerals, I through XII. The numbers go from front to back, in the order the nerves appear on the underside of the brain. The first two, the olfactory and optic nerves, grow out of the cerebrum and diencephalon. The other ten sprout from the brainstem.
Together, these nerves handle the special senses of the head. They move the eyes, face, and tongue. And one “wandering” nerve reaches all the way down into the chest and belly.
Sensory, motor, or both
Each cranial nerve is sorted by the kind of message it carries. Some are only sensory, which means they bring information in. Some are only motor, which means they send orders out. Some are mixed, doing both. An old memory trick shows the pattern: “Some Say Marry Money, But My Brother Says Big Brains Matter Most.” The first letter of each word is S, S, M, M, B, M, B, S, B, B, M, M. Each letter tells you if nerves I through XII are Sensory, Motor, or Both. To remember the names, students have long used “On Old Olympus’ Towering Tops, A Finn And German Viewed Some Hops.”
| # | Name | Type | Main function |
|---|---|---|---|
| I | Olfactory | Sensory | Smell |
| II | Optic | Sensory | Vision |
| III | Oculomotor | Motor | Most eye movements; makes the pupil smaller; lifts the eyelid |
| IV | Trochlear | Motor | Moves the eye (superior oblique muscle) |
| V | Trigeminal | Both | Feeling in the face; chewing muscles |
| VI | Abducens | Motor | Moves the eye out to the side (lateral rectus muscle) |
| VII | Facial | Both | Facial expressions; taste (front of tongue); tears and spit (saliva) |
| VIII | Vestibulocochlear | Sensory | Hearing and balance |
| IX | Glossopharyngeal | Both | Taste (back of tongue); swallowing; saliva |
| X | Vagus | Both | Calming (parasympathetic) control of the heart, lungs, and gut |
| XI | Accessory | Motor | Moves the neck and shoulders (sternocleidomastoid and trapezius muscles) |
| XII | Hypoglossal | Motor | Moves the tongue |
The wandering nerve
One cranial nerve needs a special note. The vagus nerve (X) is the odd one out. Every other cranial nerve stays in the head and neck, but the vagus travels down into the chest and belly. Its name even means “wanderer.” It is the main highway of the parasympathetic system, the calming side of your automatic nerves. It slows the heart, drives digestion, and checks on the inner organs. When you hear about the “rest-and-digest” response, that is the vagus at work.
Count off each nerve and tap it below.
- There are twelve pairs of cranial nerves, numbered I–XII from front to back. All but the first two come from the brainstem.
- Each one is sensory, motor, or mixed. The trick “Some Say Marry Money…” gives the pattern.
- Several move the eye (III, IV, VI). Others carry special senses: I smell, II vision, VIII hearing and balance.
- The vagus (X) is the only cranial nerve that leaves the head and neck. It carries most calming (parasympathetic) signals to the organs.
The chapter in one breath
- The cerebrum is a folded sheet of gray matter with four lobes: frontal, parietal, temporal, occipital. Each lies under the skull bone with the same name.
- The central sulcus splits the motor cortex (front) from the somatosensory cortex (back). The corpus callosum links the two halves.
- Four brain regions stack from thinking to survival: cerebrum → diencephalon → brainstem → cerebellum. The medulla runs the life-saving reflexes.
- The choroid plexus makes cerebrospinal fluid. It flows through four ventricles into the subarachnoid space. It helps the brain float, guards it, and keeps its chemistry steady.
- Three meninges (dura, arachnoid, pia) wrap the brain and cord. The spaces between them name the epidural, subdural, and subarachnoid bleeds.
- The spinal cord has gray horns in the center and white tracts around them. Feeling enters by the dorsal root. Motor orders leave by the ventral root.
- Twelve cranial nerves (I–XII) serve the head and neck. Each is sensory, motor, or mixed. Only the vagus reaches the chest and belly.
ReferenceWords worth knowing
Here is a quick list of the key words in this chapter. Skim it now, or come back when a word trips you up.
- Arachnoid mater
- The middle layer of the meninges, thin and like a web. Under it, the subarachnoid space holds flowing cerebrospinal fluid.
- Brainstem
- The stalk that links the brain to the spinal cord. It is made of the midbrain, pons, and medulla oblongata, and holds life-saving reflex centers and most cranial nerves.
- Central sulcus
- The groove that splits the frontal lobe (with its motor cortex) from the parietal lobe (with its somatosensory cortex).
- Cerebellum
- The “little brain” behind the brainstem. It keeps your balance and smooths the movements you choose.
- Cerebral cortex
- The thin outer sheet of gray matter on the cerebrum. It handles thinking, feeling, and the movements you choose.
- Cerebrospinal fluid (CSF)
- The clear liquid made by the choroid plexus. It fills the ventricles and subarachnoid space, where it cushions and feeds the brain and cord.
- Choroid plexus
- The web of tiny blood vessels lining the ventricles. It filters blood plasma to make cerebrospinal fluid.
- Corpus callosum
- The thick band of white matter that carries nerve fibers between the two halves of the brain.
- Cranial nerves
- The twelve pairs of nerves (I–XII) that come straight out of the brain. They serve the head and neck, and through the vagus, the inner organs.
- Diencephalon
- The central brain region that holds the thalamus and hypothalamus. It wraps around the third ventricle.
- Dorsal root ganglion
- The bulge on a spinal nerve’s dorsal root. It holds the cell bodies of sensory nerve cells.
- Dura mater
- The tough outer layer of the meninges, like leather. It forms the dural venous sinuses and folds like the falx cerebri.
- Gyrus
- A raised ridge on the surface of the cerebral cortex. The plural is gyri.
- Hypothalamus
- A part of the diencephalon that controls body heat, hunger, thirst, sleep, and hormone release. It links the nervous and hormone systems.
- Medulla oblongata
- The lowest part of the brainstem. It holds the reflex centers for heart rate, blood pressure, and breathing.
- Meninges
- The three sheets of tissue that wrap the brain and spinal cord: dura, arachnoid, and pia mater.
- Pia mater
- The thin inner layer of the meninges, rich in blood vessels. It clings right onto the brain and cord.
- Sulcus
- A shallow groove between the ridges of the cerebral cortex. The plural is sulci. A deep one is called a fissure.
- Thalamus
- The paired relay station in the diencephalon. It sorts almost all sense signals and sends them on to the cortex.
- Vagus nerve
- Cranial nerve X. It is the only cranial nerve that goes past the head and neck, carrying most calming (parasympathetic) signals to the heart, lungs, and gut.
- Ventricles
- The four linked, fluid-filled rooms inside the brain: two lateral, the third, and the fourth. CSF is made in them and flows through them.
Check yourself
The Somatic Nervous System
The somatic nervous system is the part of you that deals with the outside world. It carries sensation in, and it sends voluntary commands to your skeletal muscles out. Voluntary means the movements you choose to make. This chapter follows that two-way traffic from start to finish. We begin where every feeling starts: at the receptors in your skin. Then we move up to the special senses. These are the eye and its visual pathway, the ear that lets you hear and keeps you balanced, and the chemical senses of taste and smell. Last, we close the loop with the fastest circuit in the body, the reflex arc. Here a signal comes in and a muscle answers before your brain has even been told. By the end, you will be able to trace a signal from the world all the way to a response.
By the end of this chapter you can
- Tell general senses from special senses. Sort sensory receptors by what they detect (mechano-, thermo-, noci-, chemo-, and photoreceptors).
- Name the skin receptors for light touch, deep pressure, temperature, and pain. Explain sensory adaptation.
- Name the three tunics of the eye. Trace the path of light to the retina, and explain refraction and accommodation.
- Follow the visual pathway from the light-sensing cells, through the optic chiasm, to the visual cortex. Predict what vision is lost when a given spot is damaged.
- Describe the outer, middle, and inner ear. Explain how the organ of Corti turns a sound wave into a nerve signal.
- Explain how taste and smell detect chemicals, and why smell is so closely tied to memory and feelings.
- List the five parts of a reflex arc. Compare a one-synapse stretch reflex with a many-synapse withdrawal reflex.
Section 1How sensation begins: the receptors
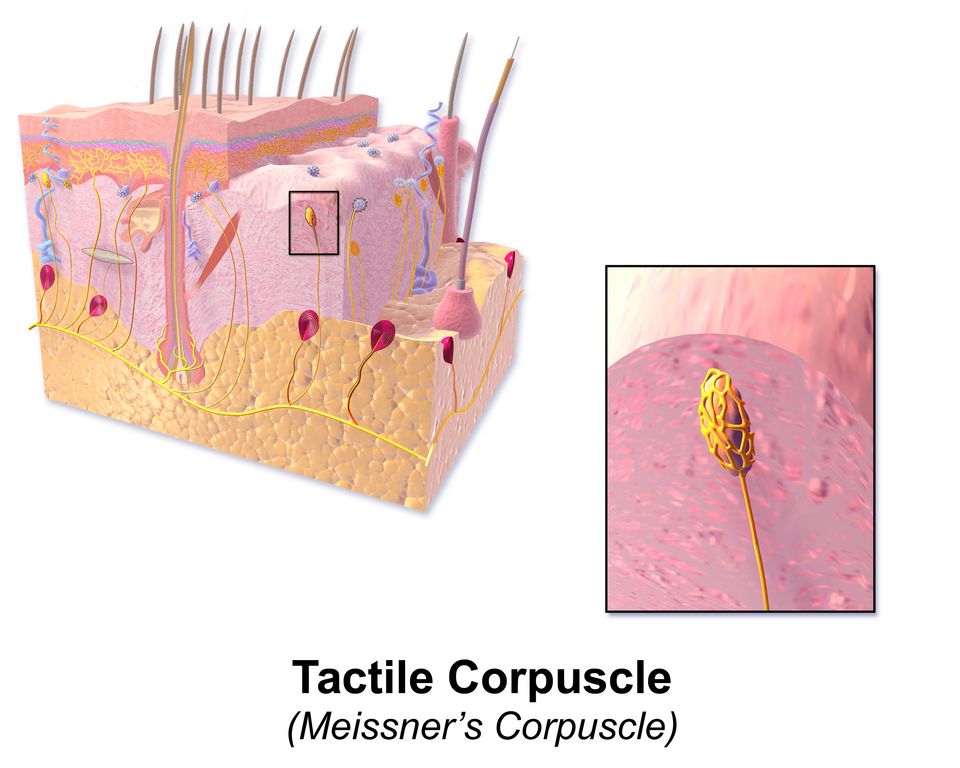
Two families of senses
Everything you sense starts with a sensory receptor. This is a special nerve ending that turns some kind of energy into an electrical signal. The nervous system can then read that signal. This change is called transduction, and it is the first step in every sense.
We sort the senses into two families. The general senses are touch, pressure, vibration, temperature, pain, and your sense of where your body parts are (proprioception). Their receptors are spread all over the body, in the skin, muscles, joints, and organs. The special senses are vision, hearing, balance, taste, and smell. They sit in complex organs in the head, and they fill the rest of this chapter.
Receptors are named for what they detect
There are dozens of receptor types. The easiest way to sort them is by the kind of signal each one responds to. Learn these five groups, and you can place almost any receptor in the body:
| Receptor type | Responds to | Example |
|---|---|---|
| Mechanoreceptor | Being pushed or bent out of shape: touch, pressure, stretch, vibration, sound | Tactile corpuscles; hair cells of the ear |
| Thermoreceptor | Temperature and changes in it | Warm and cold free nerve endings in skin |
| Nociceptor | Tissue damage; these are the pain receptors | Free nerve endings that signal cuts, burns, and swelling |
| Chemoreceptor | Chemicals in liquid or in the air | Taste and smell receptors; sensors for O₂ and CO₂ in the blood |
| Photoreceptor | Light | Rods and cones of the retina |
The touch receptors of the skin
Your skin alone holds many kinds of nerve endings. Each one is tuned to a slightly different feeling. Free nerve endings are the simplest. They are bare fibers that report pain, temperature, and rough touch. Tactile (Merkel) discs sit just under the surface and pick up fine texture and edges. Tactile (Meissner’s) corpuscles are the egg-shaped parts in the figure above. They sit in small bumps of the dermis in hairless skin, like the fingertips and lips. They sense light touch and gentle, slow (low-frequency) vibration.
Deeper down are the large lamellated (Pacinian) corpuscles. They are built in layers, like an onion. They respond to deep pressure and fast, buzzing (high-frequency) vibration. Bulbous (Ruffini) corpuscles sense skin stretch and steady pressure.
How many receptors you have in one spot decides how sensitive it is. Your fingertips are crowded with receptors. Each one covers a tiny patch of skin, called its receptive field. So you can feel two close points as two separate points. That is why you read Braille with a fingertip, not an elbow.
Another key trait is adaptation. Many receptors are phasic, or fast-adapting. They fire hard when a touch starts or stops. But they go quiet if the touch holds steady. That is why you stop noticing your shirt seconds after you put it on.
Find and name each of the skin’s receptors below.
- Transduction turns a stimulus into a nerve signal. General senses are found all over the body. Special senses live in organs in the head.
- Receptors are grouped by what they sense: mechano-, thermo-, noci-, chemo-, and photoreceptors.
- Skin touch receptors range from free nerve endings and Merkel discs to Meissner’s (light touch), Pacinian (deep pressure and vibration), and Ruffini (stretch) corpuscles.
- Phasic receptors adapt to a steady stimulus. Nociceptors (pain) hardly adapt at all.
Section 2The eye: catching the light
Three layers wrapped around a ball of fluid
The eyeball is built from three coats, one inside the other. Each coat is called a tunic. The tough outer coat is the fibrous tunic. Most of it is the white sclera, which gives the eye its shape. In front, it becomes the clear, curved cornea. The cornea is the eye’s main window, and it bends light more than any other part.
Under that is the vascular tunic, which carries the blood supply. The dark choroid feeds the retina and soaks up stray light. The ciliary body makes fluid and adjusts the lens. The colored iris opens and closes the pupil to control how much light gets in. The inner coat is the neural tunic, or retina. This is where light finally becomes a nerve signal.
| Tunic | Structures | Job |
|---|---|---|
| Fibrous (outer) | Sclera; cornea | Protects the eye and gives it shape; the cornea does most of the focusing |
| Vascular (middle) | Choroid; ciliary body; iris | Brings blood, makes aqueous humor, and controls the lens and pupil |
| Neural (inner) | Retina (rods, cones, and relay nerve cells) | Turns light into nerve signals (action potentials) |
The path of a light ray
Follow one ray of light from the world to the retina. It passes through the cornea → aqueous humor → pupil → lens → vitreous humor → retina. Two fluids fill the eye and keep it firm. The watery aqueous humor fills the space in front of the lens. It feeds the cornea and lens, which have no blood vessels. It drains out all the time through the scleral venous sinus (canal of Schlemm).
Behind the lens, a jelly called the vitreous humor fills the large back space of the eye. Refraction means the bending of light. The cornea does most of it. The lens makes the fine changes.
Accommodation and the sharpest spot
To focus on something close, the eye uses accommodation. The ciliary muscle tightens. This loosens the small ligaments that hold the lens. The stretchy lens then bulges into a rounder, stronger shape. For things far away, the ciliary muscle relaxes. The ligaments pull tight, and the lens flattens.
The image lands on the retina. The retina has two kinds of light receptors. Rods work very well in dim light, but they see no color. Cones need bright light, and they give us color and detail. A small pit called the fovea centralis is packed almost only with cones. It gives the sharpest, most detailed color vision. Where the optic nerve leaves the eye, there are no light receptors at all. This spot is the optic disc, your natural blind spot.
Explore every part of the eyeball in the slice below.
- The eye has three tunics: fibrous (sclera and cornea), vascular (choroid, ciliary body, iris), and neural (retina).
- Light travels cornea → aqueous humor → pupil → lens → vitreous → retina. The cornea bends light the most, and the lens fine-tunes it.
- Accommodation: the ciliary muscle tightens → the lens gets rounder for close-up vision.
- The fovea (all cones) gives the sharpest vision. The optic disc is the blind spot. Rods work in dim light, and cones give color.
Section 3The visual pathway: from retina to cortex
The route to the back of the brain
Once the retina makes a signal, the signal must reach the part of the brain that can make sense of it. That part is the visual cortex in the occipital lobe, at the very back of the head. The trip goes like this: ganglion cell axons of the retina → optic nerve (CN II) → optic chiasm → optic tract → lateral geniculate nucleus of the thalamus → optic radiations → primary visual cortex.
The most important stop is the optic chiasm. This is an X-shaped crossing just under the brain. Here, fibers from the nasal half of each retina (the half nearer the nose) cross to the other side. Fibers from the temporal half (the half nearer the temple) stay on the same side.
Why each brain half sees the opposite world
This partial crossing has a neat result. The left half of what you see is handled by the right side of the brain, and the right half by the left side. That may sound backwards. But remember that the lens flips every image. So the left half of the world lands on the nasal retina of the left eye. It also lands on the temporal retina of the right eye. Both of those fiber groups end up in the right brain.
This crossing is not an accident. It lets the brain blend the slightly different views of your two eyes into one 3-D picture. From the cortex, the signal splits again, as the figure above shows. An upper, or dorsal “where/how” stream, goes toward the parietal lobe. A lower, or ventral “what” stream, goes toward the temporal lobe.
Lesions map to the pathway
A lesion is a damaged spot. Because the pathway is so orderly, damage at each point causes a loss of vision you can predict. This shows up on almost every nerve exam:
| Lesion site | Visual field result |
|---|---|
| Optic nerve (one side) | Total blindness in that one eye |
| Optic chiasm (center) | Loss of both outer (temporal) halves of vision, called bitemporal hemianopia |
| Optic tract or beyond (one side) | Loss of the same half of vision on the opposite side in both eyes, called homonymous hemianopia |
Step through the whole trip, from light receptor to cortex, below.
- The pathway: retina → optic nerve → optic chiasm → optic tract → thalamus (LGN) → visual cortex in the occipital lobe.
- At the chiasm, nasal fibers cross. So each side of the brain handles the opposite half of what you see.
- The cortex feeds a dorsal “where” stream (parietal) and a ventral “what” stream (temporal).
- Where the damage is predicts what vision is lost. Damage to the chiasm gives bitemporal hemianopia.
Section 4The ear: hearing and balance
Three parts passing a wave inward
The ear does two jobs at once. It hears, and it keeps you balanced. It is built in three parts. The outer ear is the flap you can see (the auricle) and the ear canal (external acoustic meatus). It funnels sound to the tympanic membrane, or eardrum, and makes it vibrate.
The middle ear is filled with air. It holds the three smallest bones in the body, called the ossicles. They are the malleus, incus, and stapes. They act like levers. They pass the vibration across and press it onto the oval window. The auditory (Eustachian) tube links the middle ear to the throat to even out pressure. That is the tube that “pops” on a plane.
The inner ear is filled with fluid and buried in the temporal bone. It holds the spiral cochlea for hearing. It also holds the vestibule and semicircular canals for balance.
| Region | Key structures | Job |
|---|---|---|
| Outer ear | Auricle, ear canal, tympanic membrane | Gathers sound and makes the eardrum vibrate |
| Middle ear | Malleus, incus, stapes; auditory tube | Makes the vibration stronger and passes it to the oval window |
| Inner ear | Cochlea; vestibule & semicircular canals | Turns vibration into hearing; senses head position and motion |
How the cochlea turns motion into sound
The coiled cochlea holds three fluid-filled tubes. When the stapes rocks the oval window, it sends a pressure wave through a fluid called perilymph. That wave makes the basilar membrane shiver. Sitting on the basilar membrane is the organ of Corti (the spiral organ). It is dotted with hair cells. Each hair cell has tiny hairs called stereocilia. They brush against the tectorial membrane, which hangs over them.
When the hairs bend, small gates (ion channels) pop open. The hair cell becomes charged (depolarizes) and fires the cochlear nerve, which is part of cranial nerve VIII. The round window bulges out to let off the pressure, so the wave can keep moving.
Pitch is coded by place. At the base of the cochlea, the basilar membrane is narrow and stiff. There it responds to high-frequency (high-pitched) sounds. At the tip, or apex, it is wide and floppy. There it responds to low-frequency (low-pitched) sounds. So the brain knows what note it hears by which hair cells fire. It is a lovely case of the body’s shape doing the math.
Next door, the vestibule senses gravity and moving in a straight line. The semicircular canals sense spinning and turning. Together they give you your sense of balance, through the same eighth nerve.
Send a sound wave inward through all three parts of the ear below.
- The ear has three parts: the outer ear gathers sound, the middle ear’s ossicles make it stronger, and the inner ear holds the cochlea and balance organs.
- The organ of Corti sits on the basilar membrane. Its hair cells turn vibration into a cochlear nerve (CN VIII) signal.
- Pitch is mapped by place on the basilar membrane: the base for high tones, the apex for low tones.
- The vestibule and semicircular canals handle balance. Hair-cell (sensorineural) loss is permanent.
Section 5Taste and smell: the chemical senses
Tasting the dissolved, smelling the airborne
Taste and smell both use chemoreceptors. They detect molecules, not energy. The only difference is where the molecules are. Taste (gustation) reads chemicals dissolved in your spit (saliva). Smell (olfaction) reads chemicals floating in the air.
Taste happens in taste buds. Most sit on the bumps of the tongue, called papillae. There are mushroom-shaped fungiform papillae, ridged foliate papillae, and large circumvallate papillae at the back. The pointed filiform papillae have no taste buds. They only grip food and sense texture. Each bud is a cluster of gustatory cells, or taste cells. Their taste hairs poke up through a taste pore to sample the fluid. Basal cells sit behind them. They keep replacing worn-out taste cells every week or two.
| Basic taste | Signals | Trigger |
|---|---|---|
| Sweet | Sugars, energy | Glucose and other carbohydrates |
| Sour | Acids, unripe or spoiled food | Hydrogen ions (H⁺) |
| Salty | Minerals and body salts (electrolytes) | Sodium ions (Na⁺) |
| Bitter | Possible poisons | Alkaloids and many poisons |
| Umami | Protein, a savory taste | Glutamate (as in broth or aged cheese) |
Smell: a neuron with its feet in the air
High in the roof of the nose sits the olfactory epithelium. Its receptor cells are true nerve cells (neurons). They have tiny hairs (cilia) bathed in mucus. There are only about 400 kinds of smell receptors. Yet the nose can tell apart thousands of odors. That is because each smell turns on its own mix of receptors. It is like a chemical fingerprint that the brain learns to read.
The fibers of these nerve cells thread up through tiny holes in the cribriform plate of the ethmoid bone. They reach the olfactory bulb. Here is what makes smell strange and special. Unlike every other sense, smell signals go straight to the smell and limbic areas of the brain, without stopping first in the thalamus. And unlike most nerve cells, smell neurons grow back all through life.
Switch between the two chemical senses and explore their receptors below.
- Both senses use chemoreceptors. Taste reads molecules dissolved in liquid. Smell reads molecules in the air.
- Taste buds on the papillae hold gustatory cells. They detect five basic tastes: sweet, sour, salty, bitter, umami.
- Smell neurons reach the brain through the cribriform plate. They are among the few nerve cells that regenerate, or grow back.
- Only smell skips the thalamus. It links straight to the limbic system, which ties it to memory and feelings.
Section 6The reflex arc: sensation answered
The fastest circuit in the body
We began this chapter with feelings coming in. We end it with a response going out. A reflex is a fast, automatic reaction to a stimulus that you can predict. Its key feature is that it does not wait for you to think. The signal runs a short, built-in loop called the reflex arc. It often turns around in the spinal cord. It fires a muscle before your brain even knows what happened. That speed keeps you safe. You jerk your hand off a hot stove long before you feel the burn.
The five parts of every reflex arc
Some reflexes are simple and some are complex. But every reflex arc has the same five parts in the same order. Learn them once, and you can draw any reflex in the body:
| Step | Component | What it does |
|---|---|---|
| 1 | Receptor | Senses the stimulus (for example, a muscle spindle senses stretch) |
| 2 | Sensory (afferent) neuron | Carries the signal into the brain or spinal cord (the CNS) |
| 3 | Integration center | One or more synapses (nerve-to-nerve links) in the spinal cord or brainstem |
| 4 | Motor (efferent) neuron | Carries the order back out |
| 5 | Effector | The muscle or gland that responds |
Knee-jerk simple, withdrawal complex
The classic stretch (patellar) reflex is the knee-jerk a doctor tests with a small hammer. It is the simplest kind. It is a monosynaptic arc, with just one synapse between the sensory and motor nerve cells. Here is how it works. Tapping the tendon stretches the thigh muscle. The muscle spindle, a stretch sensor in the muscle, fires. The sensory nerve cell links straight to a motor nerve cell in the cord. The quadriceps muscle tightens, and the leg kicks out.
At the same moment, an interneuron (a go-between nerve cell) blocks the opposite muscle, the hamstring. So the hamstring relaxes and gets out of the way. This trick is called reciprocal inhibition, and you can see it in the figure above. Other reflexes are polysynaptic. They pass through one or more interneurons. One example is the withdrawal reflex that yanks your foot off a tack. It is paired with a crossed-extensor reflex. That reflex stiffens your other leg so you do not fall.
Set off the knee-jerk and follow the signal through all five parts of the arc.
- A reflex is a fast response you do not choose. It turns around in the cord or brainstem, not the thinking brain.
- Every arc has five parts: receptor → sensory neuron → integration center → motor neuron → effector.
- The stretch reflex is monosynaptic (one synapse). Withdrawal reflexes are polysynaptic and add interneurons.
- Reciprocal inhibition relaxes the opposite muscle. Testing reflexes checks the whole arc and helps find where damage is.
The chapter in one breath
- The somatic nervous system carries feelings in and sends chosen commands to skeletal muscle out. Every sense begins when a receptor turns a stimulus into a nerve signal.
- Receptors are grouped by what they sense (mechano-, thermo-, noci-, chemo-, photoreceptor). Skin touch endings range from free nerve endings to Meissner’s, Pacinian, and Ruffini corpuscles. Most adapt, but pain does not.
- The eye’s three tunics focus light through the cornea and lens onto the retina. Accommodation rounds the lens for close-up vision. Rods work in dim light, while cones and the fovea give color and detail.
- The visual pathway crosses at the optic chiasm, so each side of the brain sees the opposite half. Where the damage is predicts the vision loss (chiasm → bitemporal hemianopia).
- The ear’s outer, middle, and inner parts pass a wave to the organ of Corti. There, hair cells fire the cochlear nerve. The vestibule and semicircular canals handle balance.
- Taste and smell are chemical senses. Taste buds detect five basic tastes. Smell skips the thalamus and links straight to the limbic system.
- A reflex arc answers a stimulus in five steps (receptor → sensory neuron → integration center → motor neuron → effector). The stretch reflex is the one-synapse model, and testing reflexes helps find damage.
ReferenceWords worth knowing
Here is a quick list of the key words in this chapter. Skim it now, or come back when a word trips you up.
- Accommodation
- How the eye adjusts to see up close. The ciliary muscle tightens, and the lens gets rounder so it bends light more.
- Adaptation (sensory)
- When a receptor fires less because a stimulus stays the same. Phasic (fast-adapting) receptors adapt quickly; tonic ones hardly adapt at all.
- Basilar membrane
- The sheet in the cochlea that holds up the organ of Corti. Different spots on it vibrate for different pitches of sound.
- Chemoreceptor
- A receptor that detects chemicals. Examples are taste and smell receptors and the body’s blood-gas sensors.
- Cochlea
- The coiled, fluid-filled organ of the inner ear. It turns sound waves into nerve signals.
- Cone
- A light receptor in the retina that works in bright light. It gives color and sharp detail, and it is packed into the fovea.
- Fovea centralis
- A tiny pit in the retina packed with cones. It gives the sharpest, most detailed vision.
- General senses
- The senses found all over the body: touch, pressure, vibration, temperature, pain, and proprioception (knowing where your body parts are). Their receptors are in skin, muscle, and organs.
- Gustation
- The sense of taste. Chemoreceptors in the taste buds detect dissolved molecules.
- Mechanoreceptor
- A receptor that responds to being pushed or bent, such as by touch, pressure, stretch, vibration, or sound.
- Nociceptor
- A pain receptor (a free nerve ending). It signals real or possible tissue damage and hardly adapts.
- Olfaction
- The sense of smell. Receptor nerve cells in the roof of the nose detect molecules in the air, and these cells grow back.
- Optic chiasm
- The X-shaped crossing under the brain. Here the nasal fibers of each retina cross to the other side, so each half of what you see goes to the opposite side of the brain.
- Organ of Corti
- The spiral organ that sits on the basilar membrane. Its hair cells turn vibration into a cochlear nerve signal.
- Photoreceptor
- A light-sensing receptor in the retina. The rods and cones are photoreceptors.
- Reflex arc
- The five-part nerve pathway that carries out an automatic reflex: receptor, sensory neuron, integration center, motor neuron, and effector.
- Refraction
- The bending of light as it passes through the cornea and lens, so that it focuses on the retina.
- Retina
- The eye’s inner (neural) tunic. It holds the light receptors and the relay nerve cells that start the visual pathway.
- Rod
- A light receptor in the retina that works very well in dim light but sees no color. Rods are most common in the outer retina.
- Special senses
- The senses housed in complex organs of the head: vision, hearing, balance, taste, and smell.
- Stretch (patellar) reflex
- The knee-jerk reflex. Stretching a muscle makes that same muscle tighten, using just one synapse (monosynaptic).
- Taste bud
- A cluster of taste (gustatory) cells, mostly on the tongue’s papillae. It detects the five basic tastes through a taste pore.
Check yourself
The Autonomic Nervous System
Right now, your heart is beating. Your gut is working on breakfast. Your pupils are adjusting to the light. Your blood pressure moves up and down many times a minute. You do not have to think about any of it. All of this quiet work belongs to the autonomic nervous system. It is the part of you that runs your organs while your mind is busy with other things.
In this chapter you will meet its two parts. The sympathetic system is the "fight or flight" side. The parasympathetic system is the "rest and digest" side. You will see how they pull most organs in opposite ways to keep the body in tune. You will learn the two-nerve-cell wiring that sets this system apart. You will meet the two chemicals that carry its messages. And you will see the clever reflex that keeps you from fainting each time you stand up.
By the end of this chapter you can
- Define the autonomic nervous system. Explain how it differs from the somatic (voluntary) motor system.
- Compare the sympathetic and parasympathetic divisions. Look at their main job, where they leave the brain and spinal cord, and what they do to organs.
- Describe the two-neuron autonomic pathway. Find the ganglia of each division.
- Explain dual innervation and autonomic tone. Predict what happens when one division takes the lead.
- Follow the fight-or-flight response through the body, organ by organ. Describe how the parasympathetic side brings you back to calm.
- Match the autonomic neurotransmitters (acetylcholine, norepinephrine) to their receptors. Predict the effect at each target.
- Draw the baroreceptor reflex as a negative feedback loop that guards blood pressure.
Section 1Two divisions, opposite jobs
A motor system for the organs you never think about
Your nervous system sends out two kinds of motor commands. The somatic system carries the commands you choose to make. It goes to skeletal muscle, the muscle you use to lift a cup. The autonomic nervous system (ANS) does everything else. It is the involuntary motor system for your organs. It controls smooth muscle, heart muscle, and glands.
The ANS sets your heart rate. It sets how wide your pupils and airways are. It sets the pace of digestion and how tight your blood vessels are. It also runs your sweat glands and the glands that make spit. All of this happens on its own, below your awareness. You only notice it now and then. You might feel your heart pound before a test. Or your mouth may go dry when you are nervous.
Two divisions that pull opposite ways
The ANS has two divisions. They usually work against each other. The sympathetic division is the body's gas pedal. It is the "fight or flight" system. It revs you up to face a threat. The parasympathetic division is the brake. It is the "rest and digest" system. It runs the body when you are calm. It takes care of the everyday jobs of digesting food, getting rid of waste, and storing energy.
Most organs get nerves from both divisions. This setup is called dual innervation, which means "two nerve supplies." The two supplies push the organ in opposite ways. The heart is the clearest example. Sympathetic signals speed it up. Parasympathetic signals slow it down. Your heart rate at any moment is the balance between the two.
Where each division leaves the central nervous system
The two divisions leave the brain and spinal cord (the CNS) from different places. This is the easiest way to tell them apart. All sympathetic fibers come out of the thoracolumbar region. That is the chest and lower-back part of the spinal cord. They leave from the side horns of spinal segments T1 through L2. So the sympathetic division is often called the thoracolumbar outflow.
Parasympathetic fibers come out of the two ends of the CNS. Some leave the brainstem in four cranial nerves. These are III, VII, IX, and the long, far-reaching vagus nerve, X. The rest leave the sacral spinal cord, at segments S2–S4, near the tailbone. This top-and-bottom pattern gives the parasympathetic division its nickname, the craniosacral outflow.
| Target organ | Sympathetic ("fight or flight") | Parasympathetic ("rest and digest") |
|---|---|---|
| Heart | Beats faster and stronger | Beats slower |
| Pupil | Dilates (gets wider) | Constricts (gets smaller) |
| Airways (bronchi) | Dilate, letting in more air | Constrict |
| Digestive tract | Slows down; blood is sent elsewhere | Speeds up; juices flow |
| Salivary glands | A little thick spit (dry mouth) | Lots of watery spit |
| Urinary bladder | Relaxes (holds urine) | Contracts (empties) |
| Liver | Releases sugar (glucose) into the blood | Stores sugar (glucose) |
Tap any organ in the interactive. You will see its two opposite nerve supplies side by side.
- The autonomic nervous system is the involuntary motor system. It runs smooth muscle, heart muscle, and glands.
- Its two divisions work against each other. The sympathetic side is fight or flight, the gas pedal. The parasympathetic side is rest and digest, the brake.
- Sympathetic fibers leave from the thoracolumbar cord (T1–L2). Parasympathetic fibers leave craniosacral spots (CN III, VII, IX, X and S2–S4).
- Most organs have dual innervation. The body steers them by shifting the balance of steady autonomic tone.
Section 2The two-neuron pathway
Two neurons in a relay, not one
One simple fact sets the whole autonomic system apart. It takes two neurons (nerve cells) to carry a signal from the CNS to an organ. They meet at a relay station called a ganglion. A ganglion is a small cluster of nerve cell bodies outside the CNS.
The first nerve cell is the preganglionic neuron. "Pre" means "before," so it comes before the ganglion. Its cell body sits inside the CNS. Its long fiber, the axon, runs out to the ganglion and connects there. The second nerve cell is the postganglionic neuron. "Post" means "after." Its cell body sits in the ganglion. Its axon goes the rest of the way to the organ.
Compare this to the somatic system. There, a single motor neuron runs all the way from the spinal cord to the muscle. It has no relay in between. The extra connection in the ganglion is where the two autonomic divisions differ the most.
Sympathetic wiring: short first, long second, and it spreads
In the sympathetic division, the ganglia sit close to the spinal cord. Most of them form the sympathetic chain ganglia, also called paravertebral ganglia. These make a beaded double column that runs along each side of the spine. You can see them beside the cord in the figure. A few others sit in front of the aorta, the body's main artery. These are the prevertebral (collateral) ganglia, such as the celiac and mesenteric ganglia. The splanchnic nerves reach them.
The relay is near the cord. So sympathetic preganglionic fibers are short, and postganglionic fibers are long. Here is the key point. Each preganglionic fiber connects to many postganglionic neurons. This fanning out is called divergence. It is why a sympathetic response is not local. It sweeps through the whole body at once.
Parasympathetic wiring: long first, short second, and it stays local
The parasympathetic division flips this layout. Its ganglia sit in or right next to the target organ. These are called terminal or intramural ganglia. So preganglionic fibers are long, and postganglionic fibers are very short.
There is little fanning out. So a parasympathetic signal has a small, local effect on one organ. It does not cause a body-wide rush. You can slow the heart without also cramping the gut. This precise control fits the calm, one-job-at-a-time style of rest and digest.
| Feature | Sympathetic | Parasympathetic |
|---|---|---|
| Where it leaves the CNS | Thoracolumbar (T1–L2) | Craniosacral (brainstem + S2–S4) |
| Where the ganglia are | Near the spinal cord (chain & prevertebral) | Near or in the target organ |
| Preganglionic fiber | Short | Long |
| Postganglionic fiber | Long | Short |
| Divergence (fanning out) | High → body-wide response | Low → local response |
Switch between the two divisions in the interactive. Watch the ganglion move from beside the cord to beside the organ.
- Every autonomic path uses two neurons, a preganglionic one and a postganglionic one. They meet at a ganglion.
- Sympathetic: ganglia near the cord (chain & prevertebral). Short first fiber, long second fiber. High divergence → body-wide response.
- Parasympathetic: ganglia at the organ. Long first fiber, short second fiber. Low divergence → local response.
- The adrenal medulla is a changed sympathetic ganglion. It releases epinephrine into the blood as a hormone.
Section 3Fight or flight, rest and digest

One switch, and the whole body answers
Sympathetic fibers fan out widely. The adrenal medulla adds a hormone boost. So the sympathetic division works as one team that acts all at once. Picture yourself stepping off a curb as a car horn blasts. Before you can think, your heart pounds. Your breathing deepens. Your eyes go wide. Your palms sweat, and your stomach seems to drop.
That is the fight-or-flight response. The sympathetic division is shifting the whole body toward one goal. That goal is a sudden burst of hard physical effort, so you can escape a threat or face it. Every change has a purpose. Each one moves resources away from long-term upkeep and toward instant muscle power.
The sympathetic surge, organ by organ
Follow the surge through the body. Every change makes sense. The heart beats faster and harder to move oxygen quickly. The airways widen so more air reaches the lungs. The pupils dilate to take in more of the scene. The liver pours stored sugar, or glucose, into the blood to fuel muscle.
Blood vessels constrict (tighten) in the gut and skin. But they dilate (widen) in skeletal muscle. This sends blood where it is needed. Digestion and urination pause, since there is no time for either. Sweat glands turn on to cool the body before hard work. It all fits together. Everything that helps you run or fight gets turned up. Everything that can wait gets turned down.
| Fight-or-flight change | How it helps you survive |
|---|---|
| Heart beats faster and harder | Gets oxygen and fuel to muscle faster |
| Bronchioles (small airways) dilate | More air flows in, so you take in more oxygen |
| Pupils dilate | You see the threat more sharply and widely |
| Liver releases glucose | Ready fuel for a burst of effort |
| Blood shifts to skeletal muscle | Power goes to muscles, not the gut |
| Digestion and urination stop | Saves energy for the emergency |
| Sweating increases | Cools the body before hard work |
Rest and digest: paying the debt back
Once the threat is gone, the parasympathetic division takes over. It brings the body back to normal. Then it gets back to the quiet work the emergency cut short. The heart slows. The airways and pupils go back to normal. Blood flows back to the gut. Digestion, taking in nutrients, and getting rid of waste start up again.
You spend most of your life in this state. Your body is building and storing, not spending. The two divisions are not enemies. They are a well-matched pair. The sympathetic side is the sprint. The parasympathetic side is the recovery. Good health depends on moving smoothly between them.
Flip the switch in the interactive to set off the sympathetic surge. Then let the parasympathetic division calm the body back down.
- The fight-or-flight response is a body-wide sympathetic reaction. All its parts work together to prepare for hard physical effort.
- It raises heart rate, airflow, pupil size, and blood sugar. It shifts blood to muscle. It pauses digestion and urination.
- The parasympathetic division brings the body back to normal. It restarts the everyday rest-and-digest jobs.
- Epinephrine in the blood lasts longer than the nerve signals. That is why the rush fades slowly after a scare.
Section 4The chemistry: acetylcholine and norepinephrine
Only two chemicals do all the talking
The ANS controls a lot. Yet it uses a very small set of words. Almost every autonomic message is carried by just two neurotransmitters. A neurotransmitter is a chemical that a nerve cell uses to pass on a signal. A neuron that releases acetylcholine (ACh) is called cholinergic. A neuron that releases norepinephrine (NE) is called adrenergic.
Which chemical is used where follows a simple pattern. All preganglionic neurons in both divisions are cholinergic. They release ACh in the ganglion. Then the postganglionic neurons split up. Parasympathetic postganglionic fibers release ACh onto the organ. Sympathetic postganglionic fibers release NE. There are two neat exceptions. Sympathetic fibers to sweat glands use ACh. And the adrenal medulla releases epinephrine into the blood.
The receptor decides the effect, not the chemical
This next idea is the one you most need to get. The same chemical can speed up one organ and slow down another. The result depends on the receptor it lands on. A receptor is a protein on the target cell that the chemical fits into, like a key in a lock.
ACh (cholinergic) receptors come in two kinds. Nicotinic receptors are in all autonomic ganglia. They are also where nerves meet skeletal muscle. Muscarinic receptors sit on the organs that parasympathetic fibers control. Adrenergic receptors also come in groups, called alpha and beta types.
Here is an example. When this family of chemicals acts on alpha-1 receptors, blood vessels tighten. When the same family acts on beta-2 receptors, the airways relax and open. Norepinephrine does most of the alpha-1 work. It binds beta-2 only weakly. So the job of opening the airways falls to epinephrine in the blood, which comes from the adrenal medulla. Beta-2 drugs such as albuterol do this job too. One chemical family can have opposite effects. The target cell's receptor decides what happens.
| Fiber | Neurotransmitter | Receptor on target |
|---|---|---|
| Preganglionic (both divisions) | Acetylcholine | Nicotinic |
| Parasympathetic postganglionic | Acetylcholine | Muscarinic |
| Sympathetic postganglionic (most) | Norepinephrine | Adrenergic (α or β) |
| Sympathetic fibers to sweat glands | Acetylcholine | Muscarinic |
| Adrenal medulla → blood | Epinephrine (a hormone) | Adrenergic (α or β) |
A loose spray, not a tight synapse
Look at the figure. The postganglionic axon does not end in one neat tip. Instead, it is dotted with beads called varicosities. These beads spray the chemical loosely over a wide patch of smooth muscle. So one autonomic fiber can affect a broad sheet of tissue at once. This works well for setting the tone of a whole blood vessel wall or a stretch of gut. It is not meant to command just one cell.
Tap each receptor in the interactive. See how the same two chemicals cause different effects.
- All preganglionic fibers and all parasympathetic postganglionic fibers release acetylcholine (cholinergic). Most sympathetic postganglionic fibers release norepinephrine (adrenergic).
- The receptor decides if a target is sped up or slowed down. It may be nicotinic or muscarinic, alpha or beta.
- Postganglionic axons release their chemical from varicosities. They spray a whole patch of tissue.
- Receptor types are the reason autonomic drugs can be so precise. Examples are beta-blockers, albuterol, and atropine.
Section 5The baroreceptor reflex
The body's fastest blood-pressure guard
The autonomic system does more than react to emergencies. It also runs steady, silent reflexes. These keep key body numbers stable. The most important one is the baroreceptor reflex. It guards your blood pressure second by second. It is a classic negative feedback loop. That means it always pushes a change back the other way. It has three parts that you met in Chapter 1: a sensor, a control center, and effectors.
Sense, compare, correct
The sensors are baroreceptors. These are stretch sensors packed into two places. One is the wall of the carotid sinus, where blood heads up to the brain. The other is the aortic arch, the curve of the body's main artery. When blood pressure rises, these walls stretch more. Then the sensors fire faster. When pressure falls, they fire less.
Their reports travel along two cranial nerves. These are IX (glossopharyngeal) and X (vagus). The signals reach the cardiovascular center in the medulla, the lowest part of the brainstem. This is the control center. It compares the signal to the pressure the body wants.
Then the medulla adjusts its two autonomic effectors. It turns parasympathetic (vagal) and sympathetic output up or down. This changes heart rate, how hard the heart squeezes, and how wide the vessels are. The response always works against the change. So pressure is pushed back toward its normal set point.
| Blood pressure | Baroreceptor firing | Autonomic response | Result |
|---|---|---|---|
| Goes too high | Goes up | Parasympathetic up, sympathetic down | Heart slows, vessels widen → BP falls |
| Goes too low | Goes down | Sympathetic up, parasympathetic down | Heart speeds up, vessels tighten → BP rises |
Standing up without fainting
You count on this reflex every time you stand. When you get up, gravity pulls blood down into your legs. For a moment, pressure at your head drops. Baroreceptors sense the drop right away. The medulla turns up the sympathetic drive. Your heart speeds up and your vessels tighten. Pressure comes back before your brain runs short of blood. All this takes just a heartbeat or two.
Sometimes this reflex is slow. Aging, losing too much body water, or some drugs can cause this. Then the fix lags behind. You feel lightheaded when you stand up. This is called orthostatic hypotension, which means "low blood pressure on standing."
Push the pressure off target in the interactive. Watch the reflex pull it back home.
- The baroreceptor reflex is a negative feedback loop. It keeps blood pressure steady from moment to moment.
- Baroreceptors in the carotid sinus and aortic arch sense stretch. They report through CN IX and X to the medulla.
- The medulla fixes pressure by shifting the sympathetic/parasympathetic balance. This changes heart rate, heart force, and vessel width.
- A slow reflex causes orthostatic hypotension, or feeling lightheaded when you stand.
Section 6Somatic versus autonomic
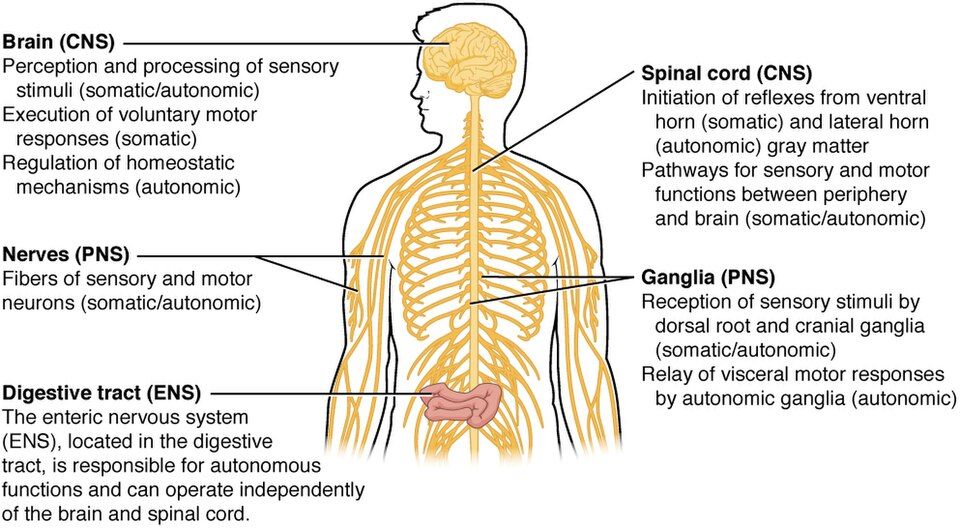
Two ways the brain moves the body
It helps to put the autonomic system next to its sibling, the somatic motor system. The contrast makes both clearer. The somatic system carries commands you choose to make. They go to skeletal muscle. It uses a single motor neuron that runs from the CNS straight to the muscle. That neuron releases acetylcholine onto nicotinic receptors.
Its effect is always the same: excitation. A somatic motor neuron can only tell a muscle to contract. It can never tell it to relax. To stop a movement, the CNS simply stops sending signals.
Where the autonomic system differs
The autonomic system is different in almost every way. It is involuntary. It targets smooth muscle, heart muscle, and glands. It uses a two-neuron chain that relays at a ganglion. It uses ACh or NE, depending on the fiber. And it can either excite or inhibit (speed up or slow down) its target.
For example, the parasympathetic vagus nerve can actively slow the heart. No somatic neuron can do that to a muscle. This power to both push and hold back is what lets the ANS fine-tune organs in both directions.
| Feature | Somatic | Autonomic |
|---|---|---|
| Control | Voluntary (you choose) | Involuntary (automatic) |
| Effector (target) | Skeletal muscle | Smooth & heart muscle, glands |
| Neurons to target | One | Two (relay at a ganglion) |
| Neurotransmitter | Acetylcholine only | Acetylcholine or norepinephrine |
| Effect on target | Always excites | Excites or inhibits |
A third player: the gut's own brain
The figure also names a quieter third part. It is the enteric nervous system (ENS). It is a huge web of neurons built into the wall of the digestive tract. It has so many neurons that people call it the "second brain." The ENS can run gut reflexes on its own. It controls the squeezing and the juices of the gut, even if its links to the CNS are cut.
The autonomic divisions still adjust it. Parasympathetic signals speed up digestion. Sympathetic signals slow it down. But the day-to-day churning of your gut mostly runs itself.
Switch between the somatic and autonomic paths in the interactive. Compare how they are wired and how they act.
- The somatic system is voluntary. It uses one neuron to skeletal muscle and releases only ACh. It is always excitatory.
- The autonomic system is involuntary. It uses a two-neuron chain to smooth muscle, heart muscle, and glands. It uses ACh or NE, and it can excite or inhibit.
- The enteric nervous system is a "second brain" in the gut wall that runs itself. The ANS adjusts it but does not command it.
The chapter in one breath
- The autonomic nervous system is the involuntary motor system. It runs smooth muscle, heart muscle, and glands.
- Its two divisions work against each other. The sympathetic side is fight or flight and leaves the thoracolumbar cord. The parasympathetic side is rest and digest and is craniosacral. Most organs have dual innervation and are steered by shifting tone.
- Every autonomic path is a two-neuron chain that relays at a ganglion. Sympathetic ganglia sit near the cord and fan out widely. Parasympathetic ganglia sit at the organ and stay local.
- The fight-or-flight response is a body-wide sympathetic surge. The parasympathetic division brings back calm. Adrenal epinephrine clears slowly, so the rush fades slowly.
- Just two neurotransmitters, acetylcholine and norepinephrine, run the system. The receptor decides if a target is sped up or slowed down.
- The baroreceptor reflex is a negative feedback loop. It guards blood pressure by balancing sympathetic and parasympathetic output through the medulla.
- The somatic system is voluntary, uses one neuron, uses ACh, and always excites. The autonomic system is involuntary, uses two neurons, and can both excite and inhibit. The enteric system runs the gut mostly on its own.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Acetylcholine (ACh)
- The chemical messenger released by all autonomic preganglionic fibers and by parasympathetic postganglionic fibers. Neurons that use it are called cholinergic.
- Adrenal medulla
- The inner core of the adrenal gland. It is a changed sympathetic ganglion that releases epinephrine into the blood, so fight or flight has a longer-lasting hormone phase.
- Adrenergic
- Describes a neuron or receptor that uses norepinephrine (or epinephrine). Adrenergic receptors come in alpha and beta types.
- Autonomic nervous system
- The involuntary motor part of the nervous system. It controls smooth muscle, heart muscle, and glands.
- Autonomic tone
- The steady background firing of both divisions. The body controls an organ by shifting the balance between them, not by switching one on from off.
- Baroreceptor
- A stretch sensor in the carotid sinus and aortic arch. It senses blood pressure by how much the vessel wall stretches.
- Baroreceptor reflex
- The negative feedback loop that keeps blood pressure steady. It adjusts sympathetic and parasympathetic output to the heart and vessels.
- Cholinergic
- Describes a neuron or receptor that uses acetylcholine. Cholinergic receptors are either nicotinic or muscarinic.
- Craniosacral outflow
- Where parasympathetic fibers leave the CNS: the brainstem (cranial nerves III, VII, IX, X) and the sacral spinal cord (S2–S4).
- Dual innervation
- When one organ gets nerves from both the sympathetic and parasympathetic divisions. The two push it in opposite ways.
- Enteric nervous system
- The large web of neurons in the wall of the digestive tract. It can run gut reflexes without help from the brain and spinal cord.
- Fight-or-flight response
- The body-wide sympathetic reaction that gets the body ready for hard physical effort when facing a threat.
- Ganglion (autonomic)
- The relay station outside the CNS. Here a preganglionic neuron connects to a postganglionic neuron.
- Muscarinic receptor
- An ACh receptor on the organs served by parasympathetic (and sweat-gland) fibers. It can excite or inhibit, depending on the organ.
- Nicotinic receptor
- An ACh receptor found in all autonomic ganglia and where nerves meet skeletal muscle. It always excites.
- Norepinephrine (NE)
- The chemical messenger released by most sympathetic postganglionic fibers. It acts on adrenergic receptors.
- Parasympathetic division
- The "rest and digest" part of the ANS. It leaves the CNS in a craniosacral pattern. It saves energy and runs digestion and waste removal.
- Postganglionic neuron
- The second neuron in an autonomic path. Its cell body is in the ganglion, and its axon runs to the organ.
- Preganglionic neuron
- The first neuron in an autonomic path. Its cell body is in the CNS, and its axon runs to the ganglion.
- Sympathetic chain ganglia
- The paired columns of ganglia (paravertebral ganglia) along the spine. They hold most sympathetic postganglionic cell bodies.
- Sympathetic division
- The "fight or flight" part of the ANS. It leaves the CNS in a thoracolumbar pattern and gets the body ready for hard effort.
- Thoracolumbar outflow
- Where sympathetic fibers leave the CNS: the side horns of spinal segments T1 through L2.
Check yourself
The Neurological Exam
A skilled doctor or nurse can find the exact spot where the nervous system has broken. It might be one nerve, a strip of spinal cord, or one side of the brain. All they need is a pin, a tuning fork, a flashlight, and some well-chosen questions. That is the quiet magic of the neurological exam. It turns the outside of a patient into a window on the inside.
In this chapter you will walk through its five parts in the same order an examiner does. You will go from the thinking cortex down to the walking feet. Along the way you will learn the one habit that makes it all work. It is called localization. It means working back from a finding to the part of the nervous system that caused it.
By the end of this chapter you can
- Explain the goal of the neurological exam, which is to localize a problem at the bedside. Name its five main parts in order.
- Do the mental status exam. Match the main language areas (Broca’s and Wernicke’s) to the aphasia that damage to each one causes.
- List the twelve cranial nerves. Describe the quick bedside test for each one.
- Use dermatome landmarks to find a sensory level. Tell apart the two sensory pathways that run up to the brain: the spinothalamic tract and the dorsal columns.
- Grade muscle strength on the 0–5 scale. Tell upper from lower motor neuron weakness.
- Do the cerebellar coordination tests. Explain dysmetria, ataxia, and a positive Romberg sign.
- Work back from any one finding to the region of the nervous system behind it.
Section 1The exam, part by part

An exam that localizes
Most exams in medicine ask what is wrong. The neurological exam adds a second, sharper question: where? The nervous system is wired in a neat, mapped-out way. One region handles language. One nerve runs the tongue. One strip of skin belongs to one spinal segment. So a careful examiner can take a handful of findings and point to a single place. That skill is called localization, and it is the whole game.
Here is an example. A weak right arm, slurred speech, and a drooping right face all point to the left side of the brain. A numb band around the belly points to one level of the spinal cord. In a way, the exam is a scanner made of questions. Long before MRI scans existed, this is how brain doctors (neurologists) found the problem spot, or lesion.
The five parts, from top to bottom
The exam is easiest to remember as a trip down the nervous system. It goes from the highest thinking to simple walking. Each part checks a different level. So a problem in one part tells you roughly where to look.
| Part | What it tests | Points to |
|---|---|---|
| 1. Mental status | Alertness, knowing where and when you are, memory, language | The cerebral cortex |
| 2. Cranial nerves | Vision, eye movement, face, hearing, tongue: the twelve nerves | The brainstem and the nerves themselves |
| 3. Sensory | Touch, pain, temperature, vibration, position | A spinal nerve, the cord, or a sensory pathway |
| 4. Motor | Strength, tone, muscle size (and reflexes) | The motor pathway: upper vs lower motor neuron |
| 5. Coordination & gait | Smooth movement, balance, walking | The cerebellum |
Notice how neatly the parts stack up. Mental status and language live in the cortex at the top. The cranial nerves come out of the brainstem in the middle. Sensory and motor tests check the long pathways of the spinal cord and the nerves in the body. Coordination checks the cerebellum, tucked at the back of the brain. Reflexes are usually part of the motor exam. Do the parts in order, and you have checked the nervous system from head to toe.
Tap through the five parts in the interactive. Watch each one light up the region it points to.
- The neuro exam is for localizing a problem at the bedside. You work back from a finding to a region.
- It has five parts: mental status, cranial nerves, sensory, motor, coordination & gait. Together they check the nervous system from top to bottom.
- Each part matches a level: cortex, brainstem, cord and nerves, motor pathway, and cerebellum.
Section 2Mental status & language
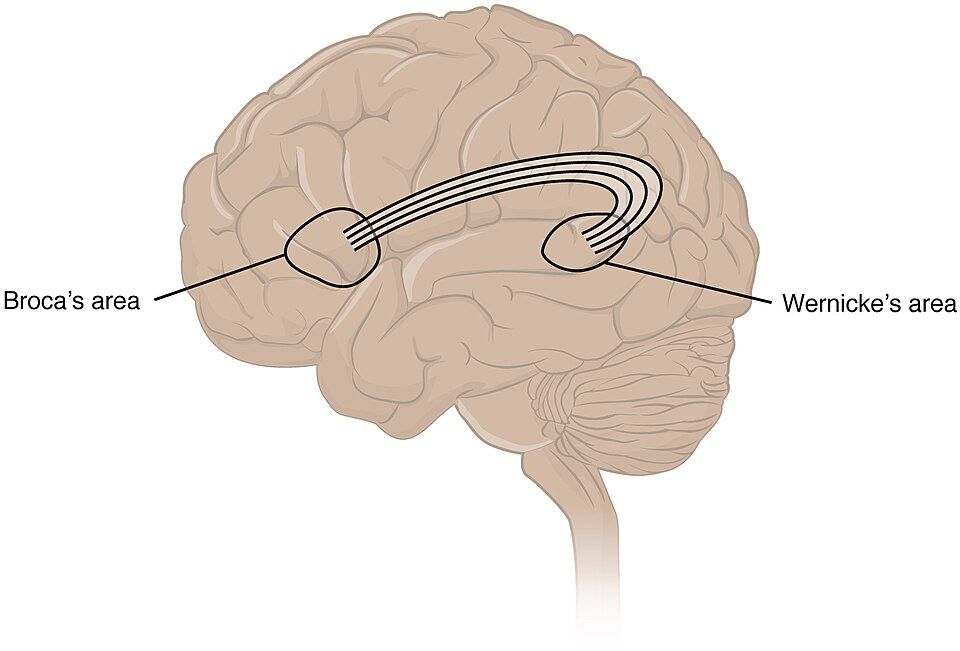
Reading the cortex
The mental status exam checks the brain's highest-level work. That work happens in the cerebral cortex, the brain's wrinkled outer layer. The exam checks if the patient is awake and alert. It checks if they know who they are, where they are, and what time it is. It also checks attention and memory. Most telling of all, it checks language.
You do not need a formal test to start. A two-minute chat already tells you a lot. Is the person confused? Can they find their words? Do they follow what you say? When something is off, the pattern points to a certain patch of cortex. That is because different jobs live in different places.
The two language areas, and the aphasias
Language is lateralized, which means it lives mostly on one side of the brain. In nearly everyone, that is the left side. Language is split between two areas with two different jobs. Broca’s area is in the frontal lobe, just in front of the motor strip. It produces speech. It builds words and grammar. Wernicke’s area is in the temporal lobe, near the hearing area. It understands language. It attaches meaning to words.
Damage to each area causes a very different aphasia, or loss of language. The type of aphasia tells you just which area failed.
| Area | Its job | If damaged |
|---|---|---|
| Broca’s area | Produces speech (words, grammar) | Broca’s (expressive) aphasia: slow, hard, choppy speech with few small words. The patient still understands. They know their speech is wrong and feel frustrated. |
| Wernicke’s area | Understands language (meaning) | Wernicke’s (receptive) aphasia: smooth-flowing but meaningless “word salad.” The patient cannot understand. They often do not realize anything is wrong. |
| Prefrontal cortex | Executive function: judgment, planning, personality, self-control | Acting without a filter, poor judgment, personality change (the famous story of Phineas Gage) |
| Hippocampus | Makes new long-term memories | Anterograde amnesia: cannot make new memories, though old ones remain |
Here is an easy way to keep them straight. Broca’s is Broken speech. The words come out slowly and with effort. But the mind behind them is clear and aware. Wernicke’s is Wordy nonsense. The speech flows easily. But the meaning is gone, both coming in and going out.
Testing is simple. To check speech output, ask the patient to name objects and repeat a phrase. To check understanding, give a command they must follow. For example: “Point to the ceiling, then the door.” To check short-term memory, name three words. Ask for them back a few minutes later. This is a bedside test of the hippocampus.
Tap each region in the interactive. See its language job and the aphasia that damage there causes.
- The mental status exam checks the cortex. It tests alertness, orientation, memory, and above all, language.
- Language is usually on the left side (lateralized). Broca’s area produces speech. Wernicke’s area understands it.
- Broca’s aphasia: hard, slow speech, understanding intact, patient frustrated. Wernicke’s aphasia: smooth nonsense, understanding lost, patient unaware.
Section 3The cranial nerve exam
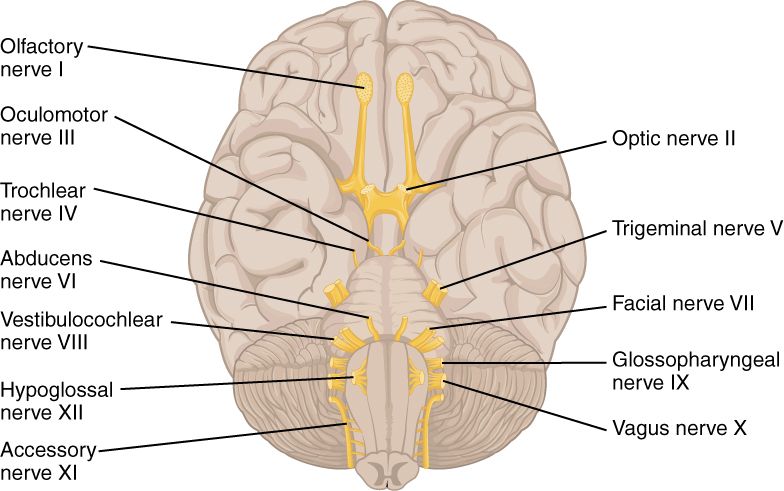
Twelve nerves, twelve tests
Twelve pairs of cranial nerves leave the underside of the brain. They serve the head and neck. They handle smelling, seeing, moving the eyes, and feeling the face. They also handle hearing, tasting, swallowing, speaking, and turning the head. Most of them come from the brainstem. So testing them one by one is a way to check the brainstem from top to bottom.
The exam has a rhythm to it. Each nerve has one quick bedside test. If a test fails, it points straight to that nerve. Or it points to the part of the brainstem the nerve comes from.
| Nerve | How it is tested |
|---|---|
| I — Olfactory | Name a familiar smell (coffee, mint) with eyes closed, one nostril at a time |
| II — Optic | Sharpness of vision (eye chart), side vision, and how the pupil reacts to light |
| III — Oculomotor | Pupil shrinking to light and most eye movements. A wide, fixed pupil or a drooping lid (ptosis) points to CN III. |
| IV — Trochlear | Look down and in toward the nose. Weakness causes up-and-down double vision, often noticed on stairs. |
| V — Trigeminal | Feeling on the face in three zones. Clench the jaw to feel the chewing muscle (masseter). |
| VI — Abducens | Look laterally (out to the side). If it fails, the eye cannot turn out. |
| VII — Facial | Smile, raise the eyebrows, puff the cheeks. A droop on one side signals a facial nerve problem (such as Bell’s palsy). |
| VIII — Vestibulocochlear | Hearing (a whisper or finger rub) and balance. Tuning-fork tests add detail. |
| IX — Glossopharyngeal | The gag reflex and taste at the back of the tongue (tested along with CN X) |
| X — Vagus | Say “ahh.” The soft palate and uvula should rise evenly on both sides. Also check voice and swallowing. |
| XI — Accessory | Shrug the shoulders and turn the head while you push back (trapezius & SCM muscles) |
| XII — Hypoglossal | Stick out the tongue. It points toward the weak (damaged) side. |
Small signs, precise meaning
The best part of the cranial nerve exam is how much a tiny difference between sides can tell you. Say the tongue pokes out crooked, leaning toward the bad side. That points to CN XII on that side. A soft palate that lifts unevenly points to CN X. A pupil that will not shrink in light, along with a droopy lid, hints at CN III. In the right setting, that is an emergency.
For years, students have kept the twelve nerves in order with an old memory trick: “On Old Olympus’ Towering Tops, A Finn And German Viewed Some Hops.” Each first letter stands for a nerve, from I to XII.
Tap any of the twelve nerves in the interactive. See how it is tested and what a failed test would mean.
- The twelve cranial nerves serve the head and neck. Most come from the brainstem, so testing them checks the brainstem.
- Each nerve has one quick test. Examples are smell, the eye chart, a jaw clench, “ahh,” a shoulder shrug, and sticking out the tongue.
- The tongue (XII) and a facial droop (VII) lean toward the damaged side.
Section 4The sensory exam
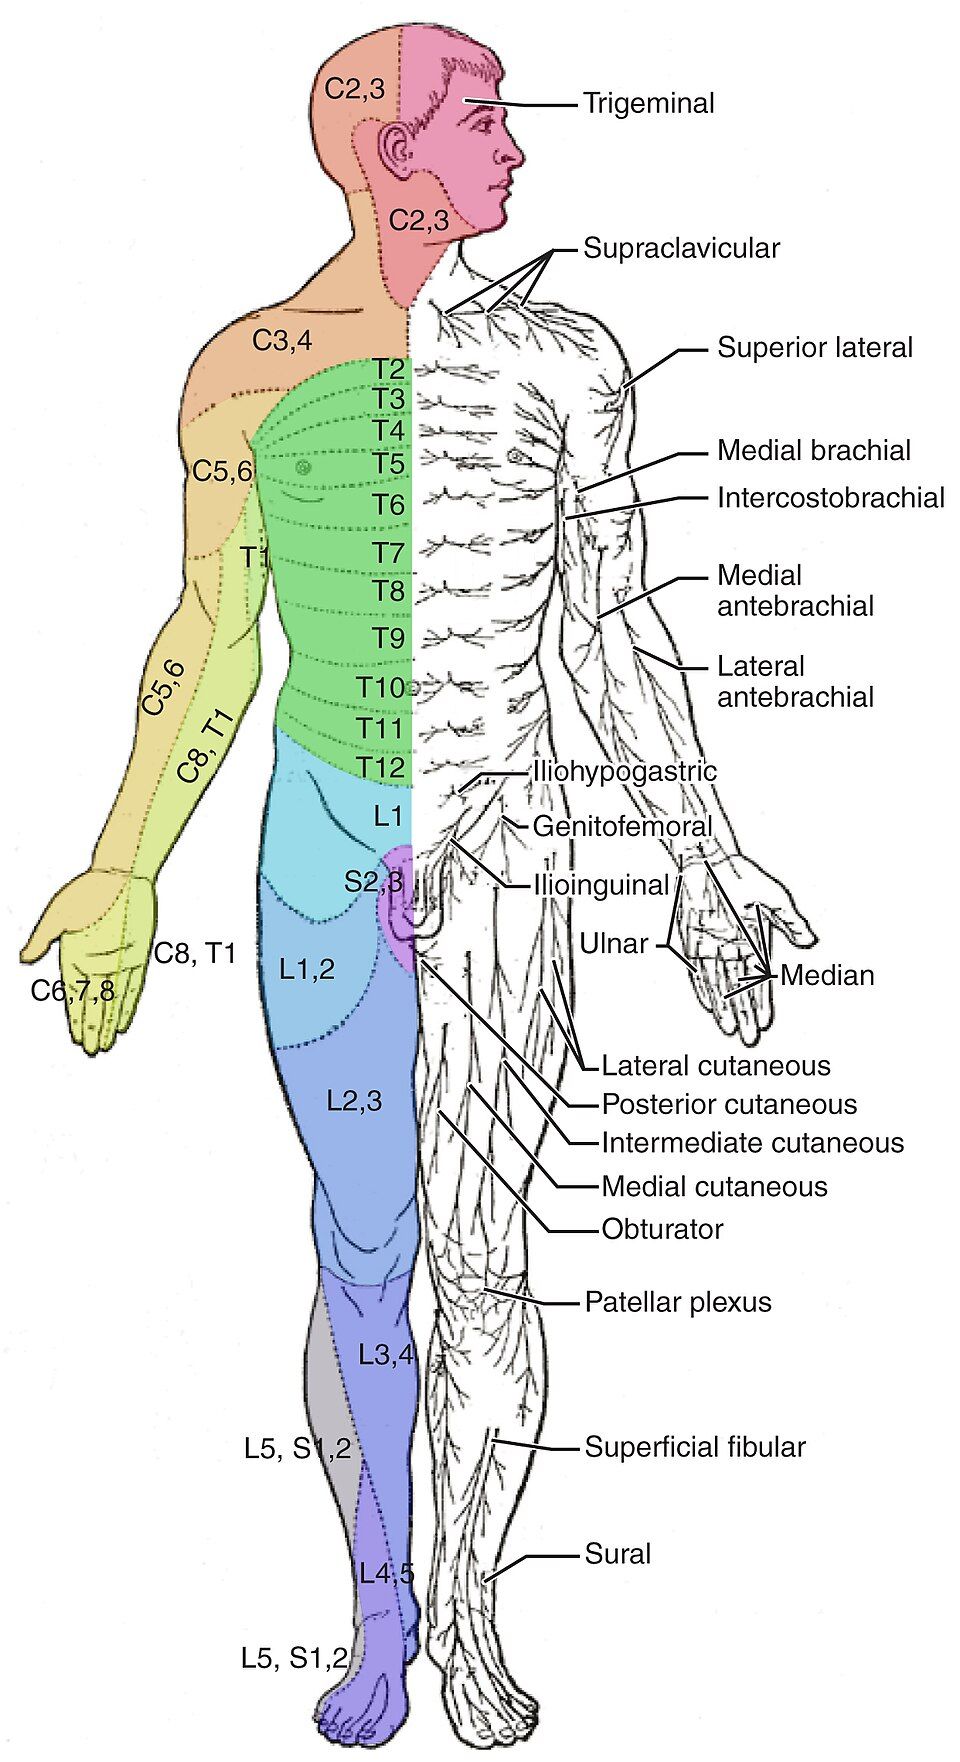
Skin comes in strips
Each spinal nerve carries feeling from one band of skin. This band is called a dermatome. Side by side, the dermatomes cover the whole body like the stripes on a map. That map is very useful. Say a patient has numbness in one strip. You can read the strip backward to the exact spinal level that serves it.
You do not have to memorize all thirty or so dermatomes. A handful of reliable landmarks anchors the whole map. The rest fall into place between them.
| Level | Landmark |
|---|---|
| C6 | The thumb and the thumb side of the forearm |
| C7 | The middle finger (C7 also powers the triceps) |
| C8 | The little finger and the pinky side of the forearm |
| T4 | The nipple line |
| T10 | The umbilicus (belly button) |
| L1 | The groin (inguinal area) |
| L4 | The inner knee and shin (L4 powers the knee-jerk) |
| L5 | The top of the foot and big toe (L5 lifts the foot up, called dorsiflexion) |
| S1 | The little toe and sole (S1 powers the ankle-jerk) |
Two roads to the brain
Feeling does not travel on one channel. It travels on two. The neuro exam tests them apart because they take different routes. They also cross the midline in different places. The midline is the imaginary line down the middle of the body.
Pain and temperature ride the spinothalamic tract. This pathway crosses to the other side almost at once, right inside the spinal cord. Fine touch, vibration, and position sense (proprioception) ride the dorsal columns. These stay on the same side all the way up. They cross only high up, in the medulla of the brainstem.
Since they cross in different spots, one cord injury can cause a strange pattern. It can knock out one sense on one side of the body and the other sense on the other side. This pattern tells you right away that both pathways are involved.
| Pathway | Carries | Crosses | Tested with |
|---|---|---|---|
| Spinothalamic tract | Pain & temperature | In the cord (right away) | Pinprick, warm or cold |
| Dorsal columns | Touch, vibration, position | In the medulla (high up) | Tuning fork, sensing toe position |
Tap a landmark in the interactive to find its spinal level. Then compare the two pathways that carry feeling up to the brain.
- A dermatome is the strip of skin served by one spinal nerve. Numbness in a strip points to that spinal level.
- Landmarks to learn: C6 thumb, C7 middle finger, C8 little finger, T4 nipple, T10 umbilicus, L1 groin, S1 sole.
- There are two pathways. The spinothalamic tract carries pain and temperature and crosses in the cord. The dorsal columns carry touch, vibration, and position and cross in the medulla.
Section 5The motor exam
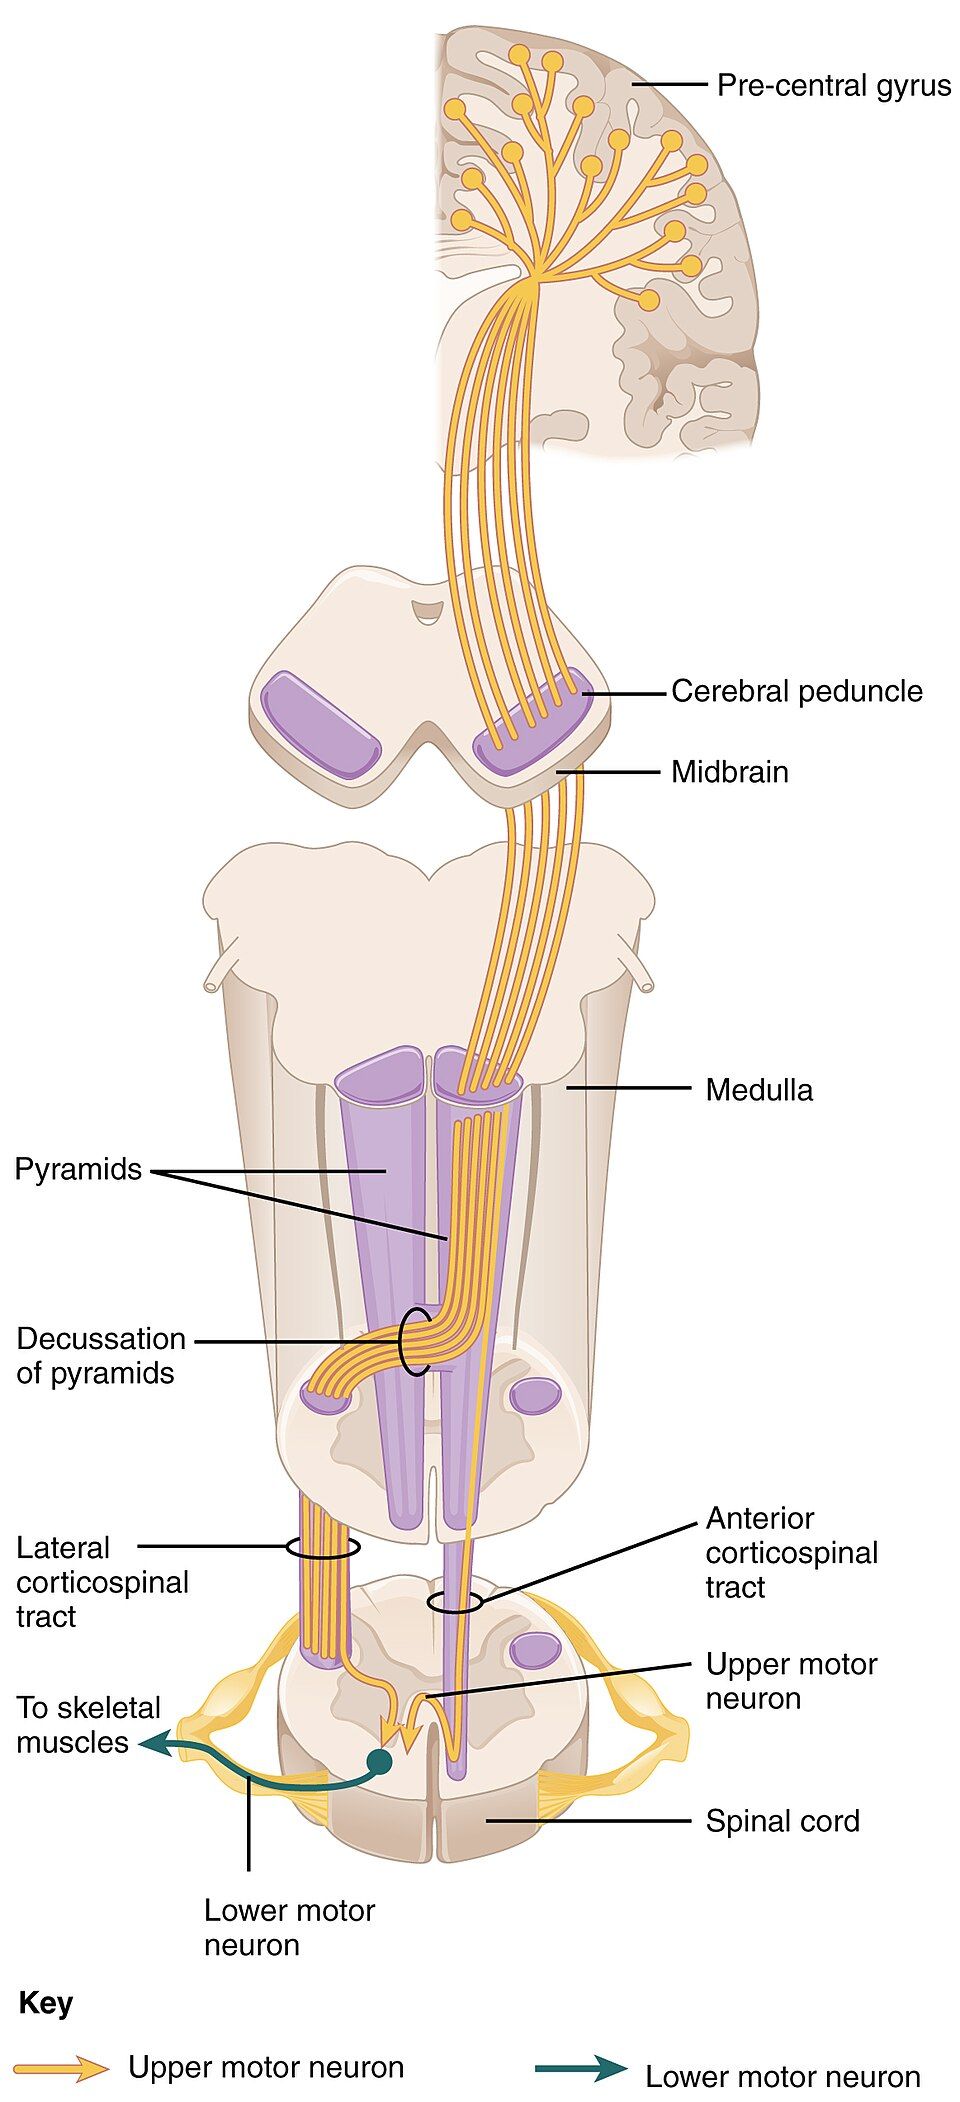
Grading strength, zero to five
The motor exam starts by measuring strength. The examiner checks one muscle group at a time. They use a standard scale that runs from 0 to 5. Gravity is the key to the scale. Grade 3 is the turning point. A 3 means the limb can just lift against gravity, but not against any extra push. Above 3, muscles can hold against your push. Below 3, they cannot even beat gravity.
It is worth learning the scale exactly. Writing “4/5” in a chart says something precise. Another doctor or nurse can act on it.
| Grade | What it means |
|---|---|
| 5 | Normal power: full strength against full push |
| 4 | Moves against gravity and some push, but weaker than normal |
| 3 | Moves against gravity only: can lift the limb, but not against a push |
| 2 | Moves only with gravity taken away (sliding side to side) |
| 1 | A flicker or trace of muscle squeeze, but the joint does not move |
| 0 | No muscle squeeze at all: complete paralysis |
Where does the weakness come from?
The motor pathway has two relays. The upper motor neuron (UMN) runs from the motor cortex down the corticospinal tract to the spinal cord. The lower motor neuron (LMN) runs from the cord out along a nerve to the muscle. Weakness can come from either one. The exam tells them apart by the other signs that come with the weakness.
UMN damage takes away the brain's control over the cord below it. So the muscle becomes spastic (stiff) and its reflexes get too strong. LMN damage cuts the muscle's only lifeline. So the muscle goes flaccid (limp). It wastes away and twitches. Checking tone, reflexes, and muscle size turns “this arm is weak” into “the problem is here.”
| Sign | Upper motor neuron | Lower motor neuron |
|---|---|---|
| Location | Brain → spinal cord | Spinal cord → muscle |
| Tone | Higher (spastic, stiff) | Lower (flaccid, limp) |
| Reflexes | Stronger than normal (hyper) | Weaker or missing |
| Babinski sign | Present (big toe goes up) | Absent |
| Atrophy (muscle wasting) | Little, and late | A lot, and early |
| Fasciculations | Absent | Present (twitches you can see) |
Slide through the strength scale in the interactive. Then switch views to compare the two motor neuron patterns.
- Strength is graded 0–5. Grade 3 is the turning point: the limb moves against gravity but not against a push.
- The pathway has two relays: upper (cortex → cord) and lower (cord → muscle) motor neurons.
- UMN: stiff, strong reflexes, Babinski present, little wasting. LMN: limp, weak reflexes, early wasting, twitches.
Section 6Coordination & gait
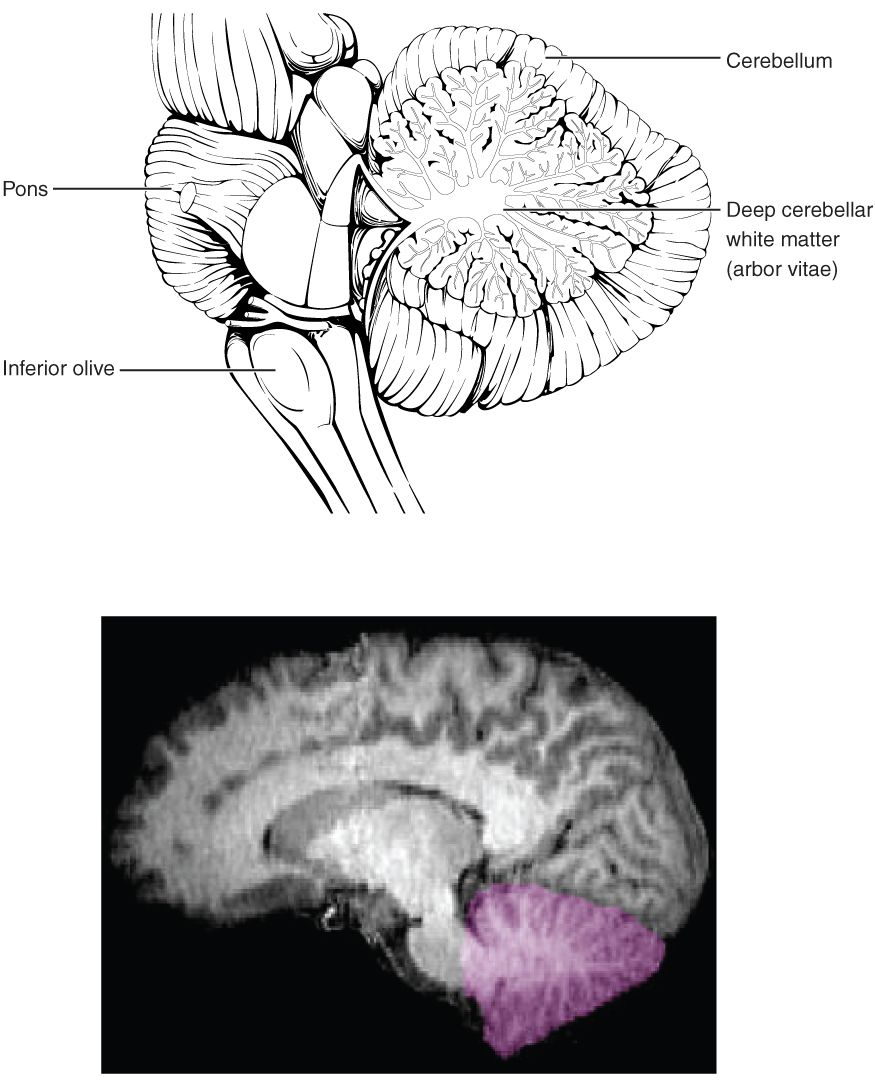
The smoothness check
Strength moves a limb. The cerebellum makes the movement smooth, accurate, and well-timed. The last part of the exam tests that polish. A patient can be fully strong and still not touch their own nose cleanly. That is because the cerebellum fine-tunes aim and keeps balance steady.
When the cerebellum fails, movements overshoot, wobble, and stagger. This group of signs is called ataxia. Each cerebellar test checks one piece of coordination.
| Test | What it checks | Abnormal finding |
|---|---|---|
| Finger-to-nose | How well you aim | Dysmetria (overshooting or undershooting) and an intention tremor that gets worse near the target |
| Rapid alternating movements | Switching a movement back and forth smoothly | Dysdiadochokinesia: clumsy, uneven switching |
| Heel-to-shin | Leg coordination | A heel that wobbles off track: limb ataxia |
| Romberg test | Proprioception (position sense) | Steady with eyes open, but falls with eyes closed. This is a sensory (dorsal-column) problem. |
| Gait | Overall balance and walking | A wide-based, staggering (ataxic) walk points to the cerebellum |
| Pronator drift | Mild upper motor neuron weakness | One arm slowly drifts down and turns palm-down. This is an early UMN sign. |
The Romberg trap
One test in this group is a clever detective. It is not a cerebellar test at all. In the Romberg test, the patient stands with feet together and closes their eyes. Balance depends on three inputs. They are vision, the inner ear, and proprioception. Proprioception is the dorsal-column sense of where your limbs are.
Closing the eyes takes vision away. Then the body must rely on the other two. Say a patient is steady with eyes open but sways or falls with eyes closed. That is a positive Romberg. It points to a sensory (dorsal-column) problem, not the cerebellum. A person with a true cerebellar problem is unsteady either way. The cerebellum never relied on the eyes to begin with. This small test neatly separates two very different causes of poor balance.
Tap each test in the interactive. See what an abnormal result reveals.
- The cerebellum makes movement smooth and accurate. When it fails, you get ataxia: dysmetria, intention tremor, and a wide-based walk.
- Key tests are finger-to-nose, rapid alternating movements, heel-to-shin, gait, and pronator drift.
- A positive Romberg (falling only with eyes closed) is a proprioception/dorsal-column sign. It is not a cerebellar sign.
The chapter in one breath
- The neuro exam is for localizing a problem at the bedside. Its five parts check the nervous system from top to bottom.
- Mental status checks the cortex. Language is mostly on the left. Broca’s aphasia means hard, slow speech in an aware patient. Wernicke’s aphasia means smooth nonsense in an unaware patient.
- The twelve cranial nerves check the brainstem, each with one quick test. The tongue and a facial droop lean toward the damage.
- A dermatome points to a sensory level (T4 nipple, T10 umbilicus, S1 sole). Pain and temperature travel the spinothalamic tract. Touch, vibration, and position travel the dorsal columns.
- Strength is graded 0–5. Upper motor neuron problems are stiff, with strong reflexes and a Babinski sign. Lower motor neuron problems are limp, wasted, and twitchy.
- The cerebellum makes movement smooth. When it fails, you get ataxia. A positive Romberg is a sensory sign, not a cerebellar one.
- Every finding is a clue to a place. The whole exam is the skill of working back from a sign to a region.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Aphasia
- A loss of language caused by damage to a language area of the cortex. The type depends on which area failed.
- Ataxia
- Clumsy, uncoordinated movement, with overshooting, wobbling, and staggering. It usually comes from a cerebellum problem.
- Babinski sign
- The big toe moves up when the sole is stroked. In adults, it is a sign of an upper motor neuron problem. It is normal in babies.
- Broca’s area
- The part of the frontal lobe that produces speech. Damage causes slow, choppy speech (expressive aphasia), but understanding stays intact.
- Cranial nerves
- The twelve pairs of nerves that leave the underside of the brain to serve the head and neck.
- Decussation
- When a nerve pathway crosses from one side of the body to the other. For example, the dorsal columns cross in the medulla.
- Dermatome
- The strip of skin whose feeling is carried by one spinal nerve. Together the dermatomes cover the body like a map.
- Dorsal columns
- The pathway that carries fine touch, vibration, and position sense up to the brain. It crosses high up, in the medulla.
- Dysdiadochokinesia
- Clumsy, uneven rapid back-and-forth movements. It is a cerebellar sign.
- Dysmetria
- Poor aim when reaching, overshooting or undershooting a target. It shows up on the finger-to-nose test in cerebellar disease.
- Flaccid
- Limp, with low muscle tone. It is typical of a lower motor neuron problem.
- Localization
- Working back from the pattern of exam findings to the part of the nervous system that is causing them.
- Lower motor neuron (LMN)
- The neuron that runs from the spinal cord out along a nerve to the muscle. Damage causes limp weakness, wasting, and twitches (fasciculations).
- Mental status exam
- The part of the neuro exam that tests the cortex. It checks alertness, orientation, attention, memory, and language.
- Pronator drift
- With eyes closed, an arm held straight out slowly drifts down and turns inward. It is an early sign of upper motor neuron weakness.
- Proprioception
- Your sense of where your limbs and body are in space. The dorsal columns carry it, and the Romberg test checks it.
- Romberg test
- Standing with feet together and eyes closed. A fall points to a position-sense (dorsal-column) problem, not a cerebellar one.
- Spasticity
- Higher muscle tone, so the muscle resists being moved. It is typical of an upper motor neuron problem.
- Spinothalamic tract
- The pathway that carries pain and temperature up to the brain. It crosses to the other side almost at once, inside the spinal cord.
- Upper motor neuron (UMN)
- The neuron that runs from the motor cortex down the corticospinal tract to the cord. Damage causes stiff weakness, strong reflexes, and a Babinski sign.
- Wernicke’s area
- The part of the temporal lobe that understands language. Damage causes smooth but meaningless speech, and understanding is lost.
Check yourself
The Endocrine System
Your nervous system is the body's fast messenger. It uses electric signals that are over in a split second. The endocrine system is its patient partner. It is a set of glands that send chemical messengers, called hormones, into your blood. The blood carries them everywhere at once. Their signals start slowly and fade slowly. But they reach every part of your body, and they can last for hours, days, or even a lifetime. This system decides how fast you burn fuel and how tall you grow. It shapes how you handle a stressful morning. It also sets how much sugar is in your blood after breakfast. In this chapter you will meet the main glands. You will learn the two very different ways a hormone can give its message to a cell. You will also trace the neat feedback loops that keep the whole system in balance.
By the end of this chapter you can
- Tell the endocrine system apart from the nervous system and from exocrine glands. Find the main endocrine glands in the body.
- Define a hormone. Explain why it changes only certain target cells, even though it reaches the whole body.
- Compare lipid-soluble and water-soluble hormones. Say where their receptors sit and how fast they work.
- Describe how the hypothalamus–pituitary team works. Name the hormones of the front and back parts of the pituitary.
- Explain how insulin and glucagon work as an opposing pair to control blood sugar.
- Draw the thyroid axis as a negative feedback loop. Predict the signs of a thyroid that works too little or too much.
- Name the layers of the adrenal gland and match each one to the hormones it makes.
- See how negative feedback controls almost every hormone in the body.
Section 1The endocrine glands
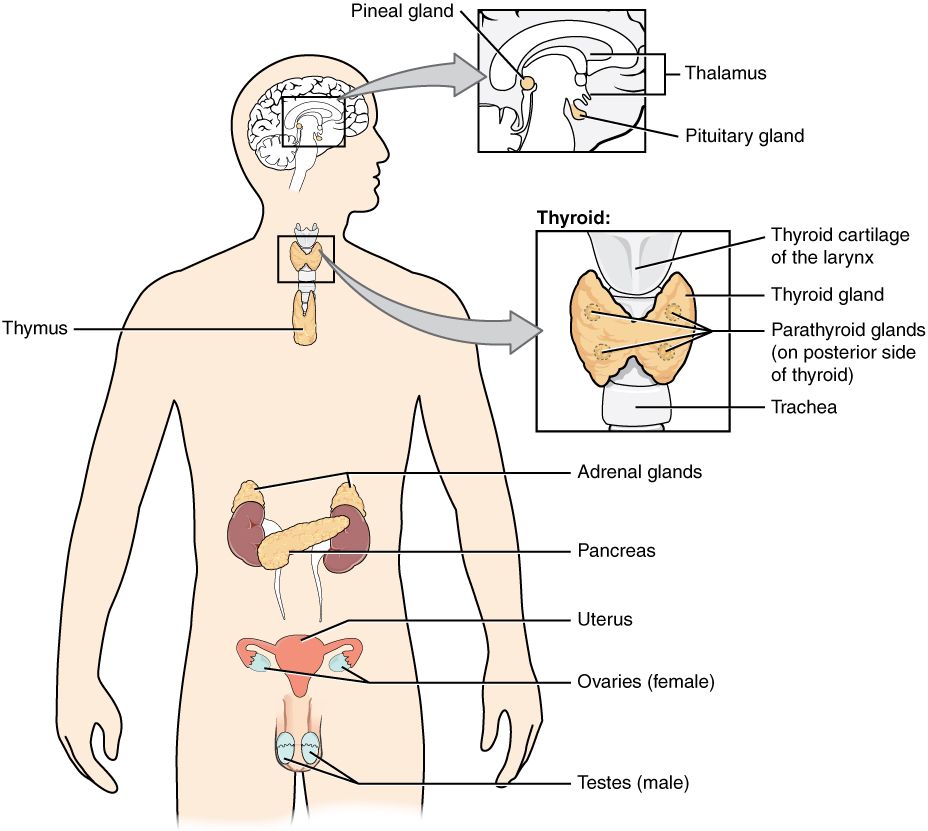
Two systems that share the job of control
Your body needs two ways to send messages. They work side by side. The nervous system sends fast electric signals along wires called neurons. Each message goes to an exact spot. It arrives in a split second and stops as soon as the signal stops.
The endocrine system works the other way. It has no wires. Its glands release chemical messengers called hormones right into the blood. The blood then carries them all over the body. So you trade speed for reach and staying power. A hormone may take seconds to minutes to act. But its effect can be wide and can last a long time. Think of the nervous system as a phone call to one person. The endocrine system is more like a message sent out to everyone. Only the people it is meant for will act on it.
Endocrine versus exocrine
The word endocrine means "to release within." Endocrine glands are ductless, which means they have no tubes. They release their hormones straight into the fluid around them and into the blood. Exocrine glands are different. They send their products through a duct, a small tube, onto a surface. Sweat glands, spit (salivary) glands, and tear glands are all exocrine.
A few organs do both jobs. The pancreas is the classic example. Its exocrine part drips digestive enzymes into a duct that empties into the gut. At the same time, small islands of endocrine tissue release insulin and glucagon into the blood.
The cast of glands
Some glands have making hormones as their main job. These full-time endocrine glands are the pituitary, pineal, thyroid, parathyroid, and adrenal glands. The hypothalamus, a small part of the brain, sits at the top of the chain of command.
Other organs make hormones as a side job. These include the pancreas, the gonads (ovaries and testes), and the thymus. Even the heart, kidneys, stomach, and body fat release hormones. Learn the main glands first. The part-time players will come up in their own chapters.
| Gland | Main hormone(s) | Main job |
|---|---|---|
| Hypothalamus | Releasing & inhibiting hormones | Gives orders to the pituitary; links the brain to the endocrine system |
| Pituitary | GH, TSH, ACTH, FSH, LH, ADH, oxytocin | Passes orders on to many other glands |
| Thyroid | Thyroid hormone (T₃/T₄), calcitonin | Sets how fast you burn fuel; lowers blood calcium |
| Parathyroid | Parathyroid hormone (PTH) | Raises blood calcium |
| Adrenal | Cortisol, aldosterone, epinephrine | Stress response; salt and water balance |
| Pancreas (islets) | Insulin, glucagon | Controls blood sugar (glucose) |
| Pineal | Melatonin | Sets the sleep–wake rhythm |
| Gonads | Estrogen/progesterone; testosterone | Making babies and sex traits |
Tap each gland in the interactive to see where it sits and what it makes.
- The endocrine system controls the body with hormones carried in the blood. Its signals are slower than nerve signals, but they reach more places and last longer.
- Endocrine glands have no ducts and release into the blood. Exocrine glands release through ducts onto a surface.
- The main glands are the hypothalamus, pituitary, thyroid, parathyroid, adrenal, pancreas, pineal, and gonads.
- A hormone acts only on its target cells. These are the cells that have the matching receptor.
Section 2How hormones act
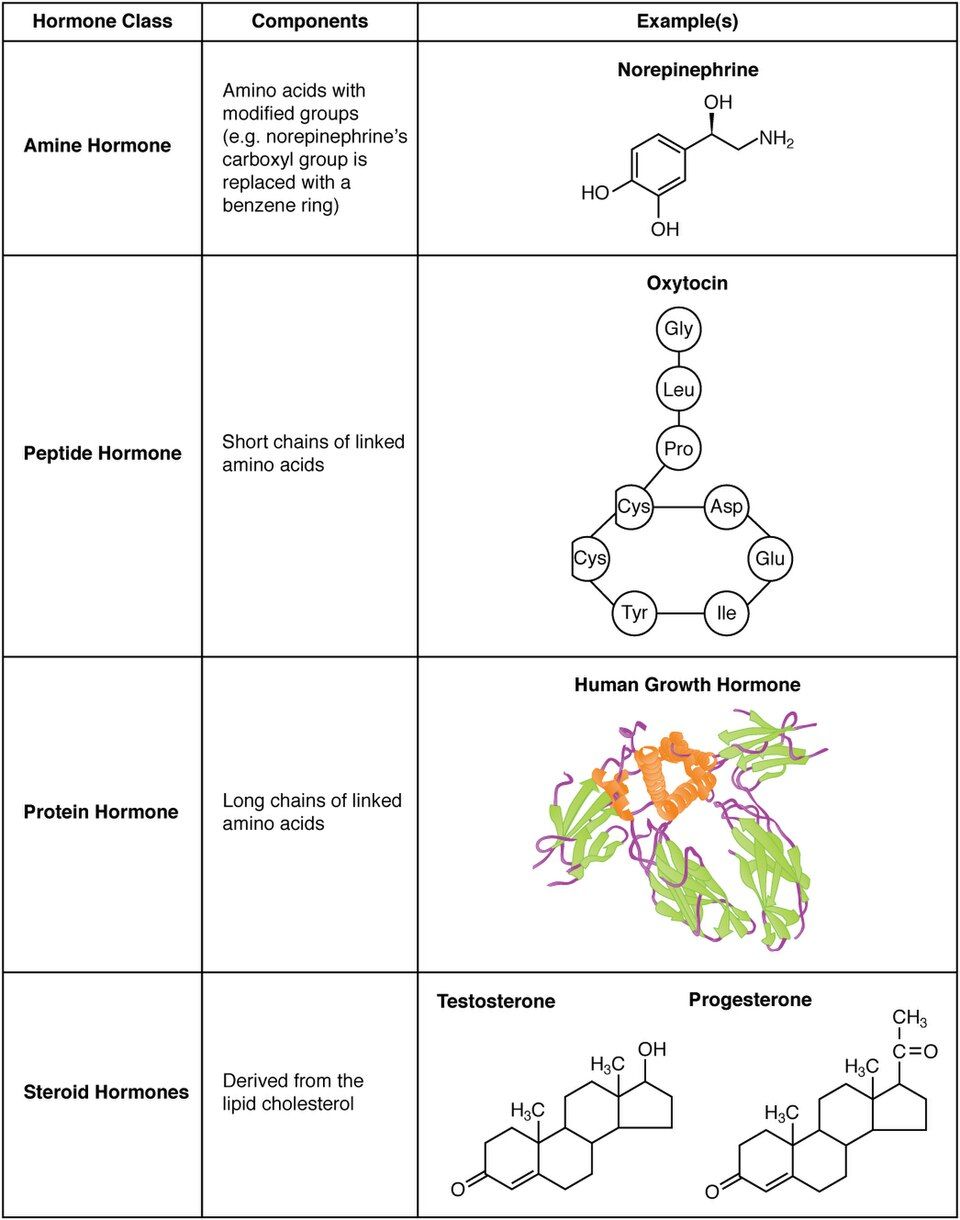
Chemistry decides the delivery
Hormones come in two main chemical families. This is not a small detail. It decides exactly how a hormone talks to a cell.
Most hormones are amino-acid based, which means they are built from the building blocks of protein. Some are peptides and proteins, such as insulin and growth hormone. Others are amines, such as the adrenal catecholamines. These hormones are water-soluble, so they mix well with water. They are also lipid-insoluble, so they do not mix with fat. That means they cannot cross the fatty cell membrane.
The second family is the steroid hormones. These include cortisol, aldosterone, and the sex hormones. They are built from cholesterol. They are lipid-soluble, so they slip right through the fatty membrane. That one question splits hormone action into two clear stories. Can the hormone cross the membrane or not?
Lipid-soluble hormones: walk right in
A lipid-soluble hormone can pass through the membrane. So it does not need to knock from outside. It moves into the cell and binds to an intracellular receptor, a receptor inside the cell. This is usually in the nucleus. The hormone and receptor then work directly on the DNA. They switch certain genes on or off.
The cell responds by making new proteins. These are often new enzymes that change how the cell behaves. Building proteins takes time, so these hormones are slow to start. But the new proteins stick around, so the effects are long-lasting. Steroid hormones such as cortisol work this way.
Water-soluble hormones: knock from outside
A water-soluble hormone cannot get into the cell. So it binds to a receptor on the cell surface instead. This does not reach the DNA. Instead, it starts a relay inside the cell. The relay uses a second messenger. The best-known one is cyclic AMP (cAMP).
The hormone is the "first messenger," and it stays outside. The second messenger carries the signal on. It turns on a chain of enzymes that are already waiting in the cell's fluid. These enzymes are ready-made and just need to be switched on. So the response is fast. But it also fades fast once the hormone is gone. Peptide hormones like insulin and glucagon use this surface route. So does the amine epinephrine.
| Feature | Lipid-soluble (steroid) | Water-soluble (peptide/amine) |
|---|---|---|
| Crosses the membrane? | Yes, it enters the cell | No, it stays outside |
| Where the receptor is | Inside the cell (often the nucleus) | On the cell surface |
| How it works | Turns genes on/off → new proteins | Second messenger (cAMP) → chain of enzymes |
| How fast it starts | Slow (hours) | Fast (seconds to minutes) |
| How long it lasts | Long | Short |
| Examples | Cortisol, aldosterone, estrogen, testosterone | Insulin, glucagon, growth hormone, epinephrine |
Switch between a lipid-soluble and a water-soluble hormone in the interactive. Then step through each path.
- Hormones are either amino-acid based (water-soluble) or steroid (lipid-soluble). Whether they dissolve in fat decides how they work.
- Lipid-soluble hormones enter the cell and bind intracellular receptors. They change gene expression, which genes are turned on. They are slow but lasting.
- Water-soluble hormones bind surface receptors and use a second messenger (cAMP). They are fast but brief.
- Thyroid hormone is the exception. It is an amine that dissolves in fat and acts like a steroid.
Section 3The hypothalamus & pituitary axis
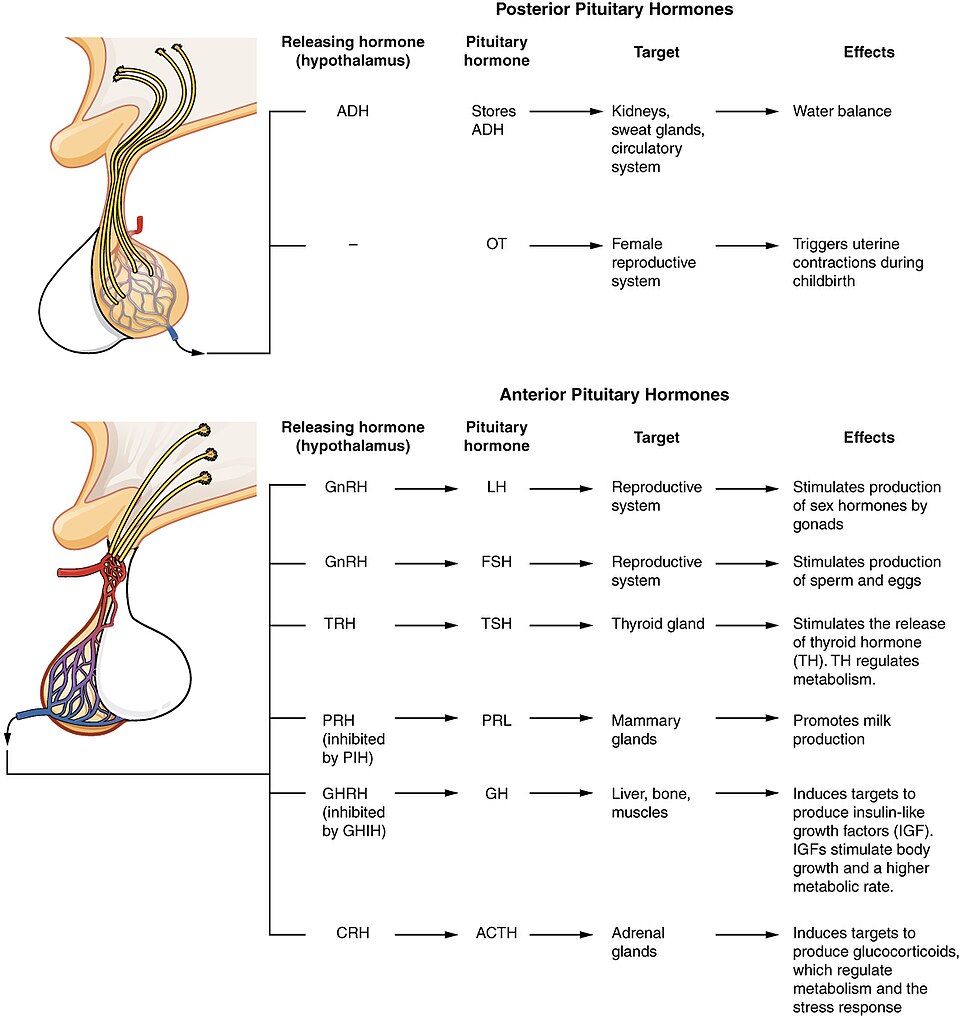
The real chain of command
The pituitary gland is about the size of a pea. It hangs just below the brain. It is often called the "master gland" because it directs so many other glands. But the pituitary has a boss of its own. That boss is the hypothalamus, a small part of the brain just above it.
The hypothalamus is where the nervous and endocrine systems meet. It takes in signals from the brain. Then it turns them into hormone orders for the pituitary. So the true master is the hypothalamus. The pituitary is its strong second-in-command. The pituitary has two lobes, or parts. They are wired in very different ways.
The posterior pituitary: a storage terminal
The posterior pituitary is the back lobe. It makes no hormones of its own. It is really nerve tissue that grows down from the hypothalamus. Two hormones are stored here. They are antidiuretic hormone (ADH) and oxytocin. Both are made by nerve cells in the hypothalamus. They travel down the long arms (axons) of those cells. Then they are stored in the posterior pituitary until needed.
ADH tells the kidneys to save water. This makes the urine more concentrated. Oxytocin makes the uterus squeeze during childbirth. It also makes milk flow (let-down) during nursing. So the back lobe is a release station, not a factory.
The anterior pituitary: a true factory under remote control
The anterior pituitary is the front lobe. It is gland tissue that makes and releases its own hormones. But it does this only when the hypothalamus tells it to. The hypothalamus sends tiny releasing and inhibiting hormones. They start or stop the front lobe's work. They travel through a private set of blood vessels called the hypophyseal portal system. These vessels carry them the short trip to the front lobe.
Several front-lobe hormones are tropic hormones. Their job is to give orders to other glands. TSH drives the thyroid. ACTH drives the outer layer of the adrenal gland (the adrenal cortex). FSH and LH drive the gonads. Other front-lobe hormones act on body tissues directly. Growth hormone (GH) acts on almost everything. Prolactin (PRL) acts on the breast.
| Hormone | Lobe | Target & effect |
|---|---|---|
| Growth hormone (GH) | Anterior | Body tissues: growth and fuel use |
| Thyroid-stimulating (TSH) | Anterior | Thyroid: make thyroid hormone |
| Adrenocorticotropic (ACTH) | Anterior | Adrenal cortex: make cortisol |
| Follicle-stimulating (FSH) | Anterior | Gonads: help eggs and sperm mature |
| Luteinizing (LH) | Anterior | Gonads: release of an egg (ovulation), sex hormones |
| Prolactin (PRL) | Anterior | Breast: make milk |
| Antidiuretic (ADH) | Posterior | Kidney: save water |
| Oxytocin | Posterior | Uterus & breast: squeezing, milk let-down |
Tap a pituitary hormone in the interactive. Trace its path from the brain to its target organ.
- The hypothalamus is the true master. It controls the pituitary, which controls many other glands.
- The posterior pituitary only stores and releases ADH and oxytocin. Both are made in the hypothalamus.
- The anterior pituitary makes six hormones when the hypothalamus says so. Four are tropic (TSH, ACTH, FSH, LH).
- Remember them with FLAT PIG.
Section 4Blood glucose regulation
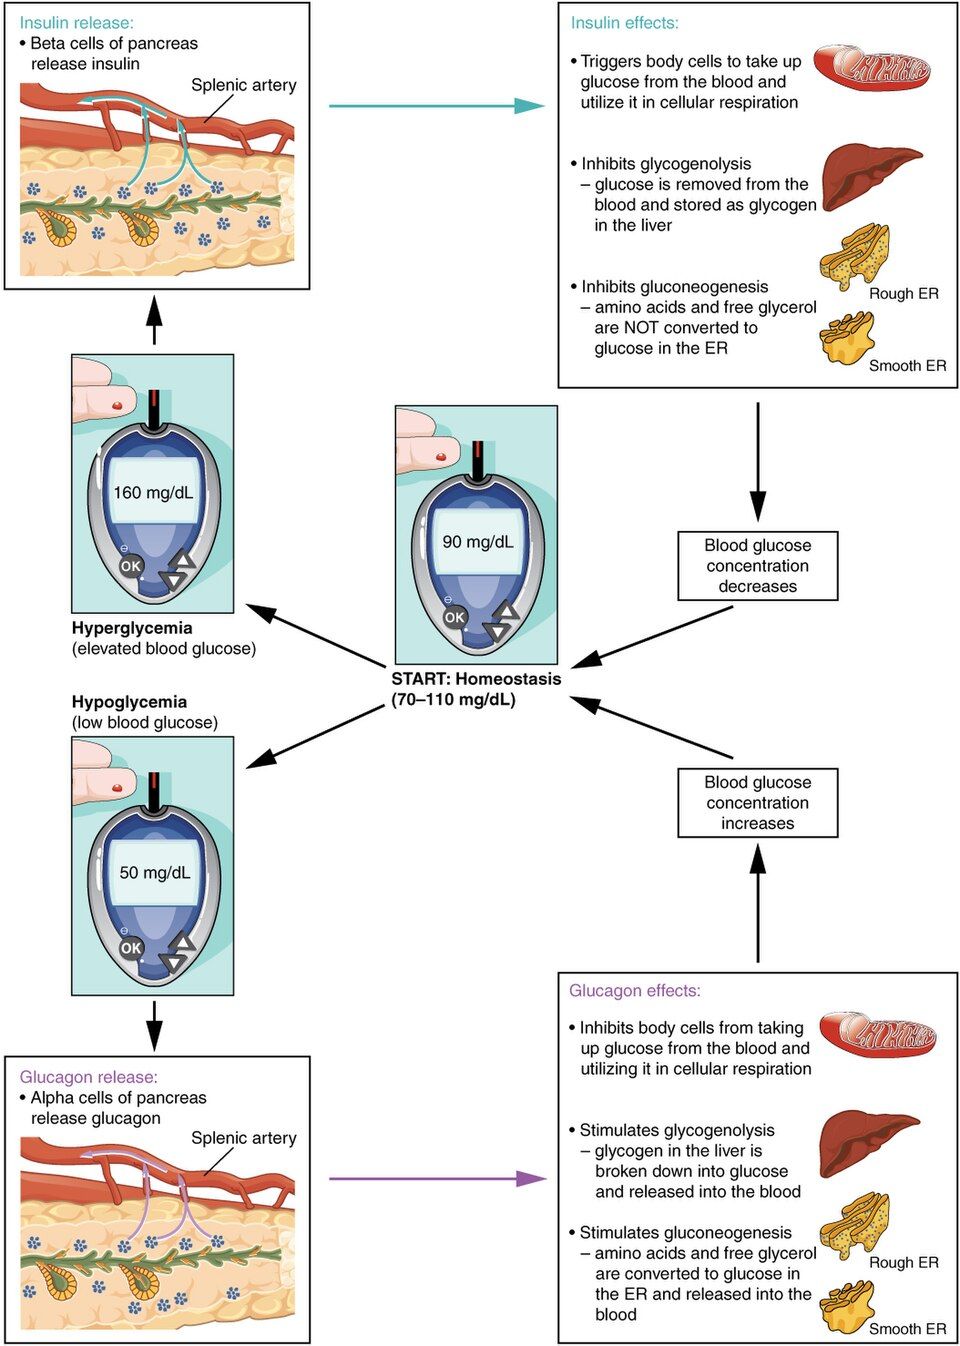
Two hormones from one gland, pulling opposite ways
Blood glucose, or blood sugar, is one of the most closely guarded values in your body. The pancreas guards it with two hormones that work against each other. They are an antagonistic pair. Small clusters of hormone-making cells are spread through the pancreas. They are called the pancreatic islets (islets of Langerhans).
The beta cells in the islets make insulin. The alpha cells make glucagon. One hormone lowers blood sugar and the other raises it. So the pancreas can nudge sugar either way as needed. It is a great example of negative feedback, with a gas pedal and a brake.
Insulin: the "fed-state" hormone that lowers glucose
After a meal, your blood sugar goes up. The beta cells sense the rise and release insulin. Its whole job is to lower blood glucose. Insulin tells body cells to open up and take in sugar. Muscle and fat cells do this most. Insulin also tells the liver to store the extra sugar as glycogen, a stored form of sugar.
As cells soak up the sugar, blood sugar drops back to normal. Then less insulin is released. Here is a handy way to remember it. Insulin is the hormone of the fed state. It moves fuel out of the blood and into storage.
Glucagon: the "fasting" hormone that raises glucose
Between meals, blood sugar slowly drops. Now the alpha cells release glucagon. It does the opposite of insulin. It raises blood glucose. Glucagon tells the liver to break glycogen back down into sugar. This is called glycogenolysis, which means "glycogen splitting." It also tells the liver to make new sugar from other molecules. This is called gluconeogenesis, which means "making new sugar."
The liver releases this sugar into the blood. Blood sugar climbs back to its normal set point, and glucagon release slows. Glucagon is the hormone of the fasting state. It pulls fuel out of storage and back into the blood.
| Feature | Insulin | Glucagon |
|---|---|---|
| Made by | Beta cells | Alpha cells |
| Released when | Blood sugar is high (after eating) | Blood sugar is low (fasting) |
| Effect on blood sugar | Lowers it | Raises it |
| What it tells the liver | Store sugar as glycogen | Break down glycogen; make new sugar |
| Overall role | Fed state: storing fuel | Fasting state: releasing fuel |
Pick a meal or a fast in the interactive. Watch insulin or glucagon pull blood sugar back to normal.
- The pancreatic islets control blood sugar with two hormones that work against each other.
- Insulin comes from beta cells. It lowers blood sugar after a meal. It gets cells to take in sugar and the liver to store it as glycogen.
- Glucagon comes from alpha cells. It raises blood sugar when you fast. It breaks down glycogen and makes new sugar.
- Insulin is the only hormone that lowers blood glucose. Losing it, or cells ignoring it, causes diabetes.
Section 5The thyroid axis
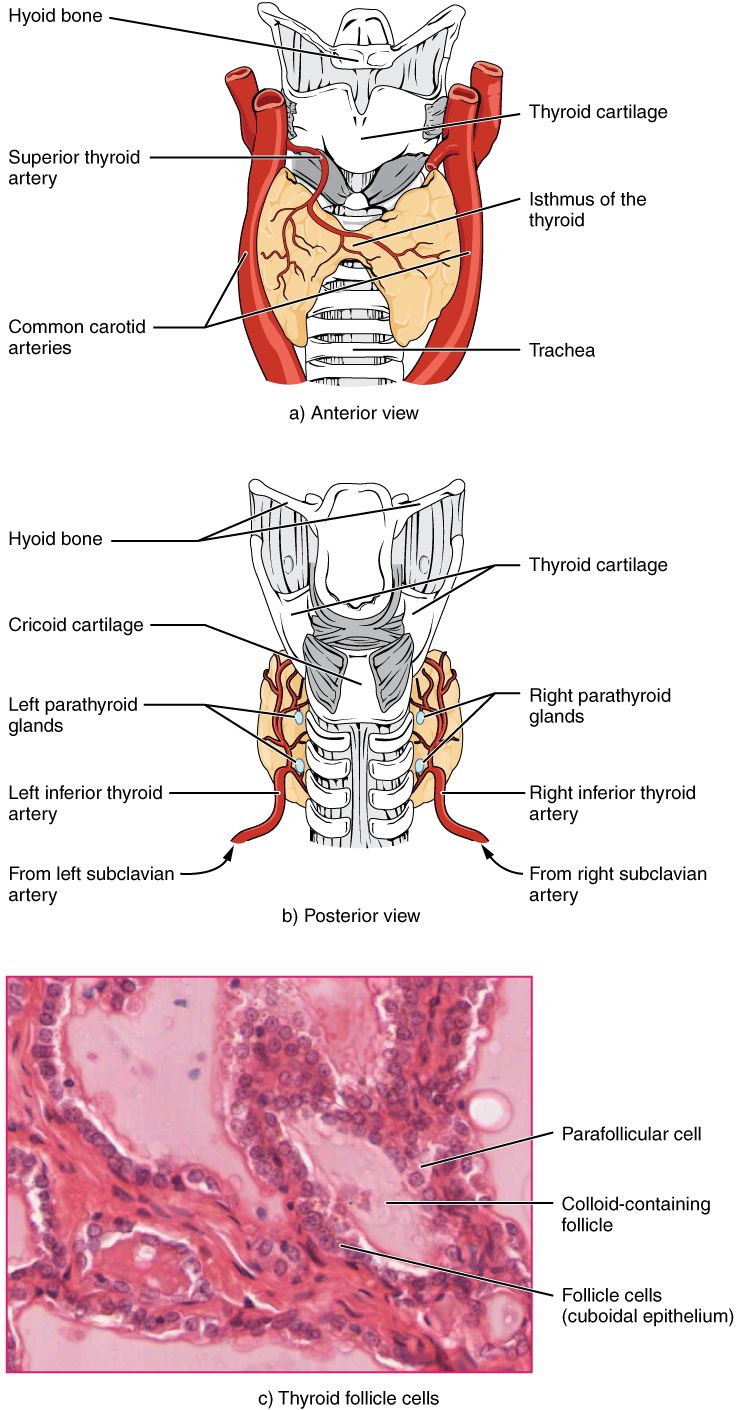
The gland that sets your idle speed
The thyroid gland is shaped like a butterfly. It wraps around the front of your windpipe. It makes thyroid hormone, which comes in two forms, T₃ and T₄. The numbers tell you how many iodine atoms each one has. That is why you need iodine in your diet to make them.
Thyroid hormone sets your basal metabolic rate. This is the speed at which almost every cell burns fuel and makes heat. Turn it up and the whole body runs faster and hotter. Turn it down and everything slows. It is like the idle speed of a car engine.
The feedback loop that keeps it steady
Thyroid hormone is controlled by a three-step chain. It is called the hypothalamus–pituitary–thyroid (HPT) axis. It is a classic negative feedback loop. First, the hypothalamus releases TRH (thyrotropin-releasing hormone). TRH tells the front lobe of the pituitary to release TSH (thyroid-stimulating hormone). TSH then tells the thyroid to release T₃ and T₄.
Here is the clever part. The thyroid hormones loop back and block both the hypothalamus and the pituitary. This turns down TRH and TSH. It works like a brake. When there is plenty of thyroid hormone, the brake keeps it from rising more. When thyroid hormone falls, the brake lets go. TSH rises and pushes the thyroid to work harder.
When the thyroid does too little or too much
Thyroid hormone sets the body's pace. So its problems look like the two ends of a dial. In hypothyroidism, there is too little hormone, and everything slows. You may see weight gain, tiredness, feeling cold, dry skin, and a slow heart rate. In hyperthyroidism, there is too much, and everything speeds up. You may see weight loss even with a big appetite. People feel hot and anxious, and the heart races. Both problems can make the gland swell into a lump you can see, called a goiter.
The feedback loop also helps doctors find the problem. Take primary hypothyroidism, where the thyroid itself is failing. It makes little hormone, so the brake lifts and TSH rises. That is why a high TSH points to an underactive thyroid.
| Sign | Hypothyroidism (too little) | Hyperthyroidism (too much) |
|---|---|---|
| Metabolic rate | Slower | Faster |
| Body weight | Gain | Loss |
| Temperature | Can't stand cold | Can't stand heat |
| Heart rate | Slow | Fast |
| Energy & mood | Tired, sluggish | Anxious, restless |
| TSH level (primary) | High | Low |
Run the interactive to see the normal loop. Then make the thyroid do too little or too much.
- Thyroid hormone (T₃/T₄, made with iodine) sets the body's basal metabolic rate, its idle speed.
- The HPT axis runs TRH → TSH → T₃/T₄. It is a negative feedback loop. Thyroid hormone blocks TRH and TSH.
- Hypothyroidism slows the body (weight gain, feeling cold, tiredness). Hyperthyroidism speeds it up (weight loss, feeling hot, racing heart).
- When the thyroid itself is the problem, TSH moves opposite to thyroid output. A high TSH signals an underactive gland.
Section 6The adrenal gland
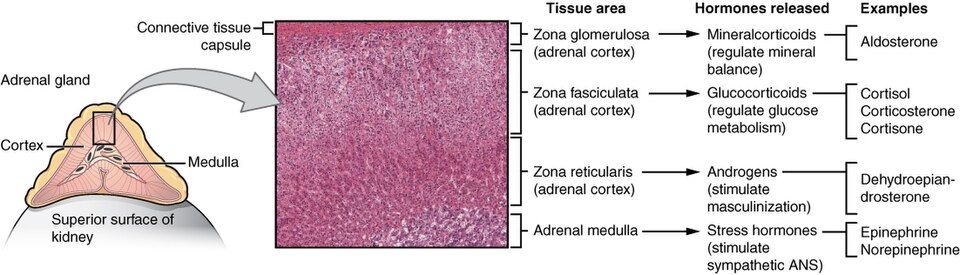
Two glands stacked into one
The adrenal gland sits like a cap on top of each kidney. It is really two different glands joined together. The outer part is the adrenal cortex. It makes steroid hormones, and you cannot live without it. The inner part is the adrenal medulla. It makes the catecholamines epinephrine and norepinephrine. The medulla is a direct part of the sympathetic nervous system, the "fight-or-flight" side of your nerves.
The two parts work on very different time scales. The medulla responds in seconds. The cortex takes minutes to hours. But both are key to how your body handles stress.
The cortex: three layers, three kinds of hormone
The cortex has three zones, or layers. Each one makes a different kind of steroid. This is a rare case where you can read the job straight off the layout, from the outside in.
The outer layer is the zona glomerulosa. It makes mineralocorticoids, which control salts. The main one is aldosterone. It tells the kidney to hold on to sodium (Na⁺) and water and to get rid of potassium (K⁺). This raises blood volume and blood pressure.
The wide middle layer is the zona fasciculata. It makes glucocorticoids, which affect sugar. The main one is cortisol, the body's main stress hormone. It raises blood sugar, frees up fuel, and calms swelling (inflammation). The inner layer is the zona reticularis. It makes small amounts of androgens. These are sex hormones such as DHEA.
The medulla: instant adrenaline
The medulla is at the very center. It is wired straight into the sympathetic nervous system. So it fires the moment a threat appears. It floods the blood with epinephrine (adrenaline) and norepinephrine. This causes the well-known fight-or-flight rush. Your heart pounds and your airways open wide. Sugar is released for fuel. Blood is sent to your muscles.
This is the fast, short part of the stress response. It is a jolt that fades within minutes. Cortisol, from the cortex, is the slow, steady part. It carries the body through long or repeated stress.
| Layer (outside → in) | Hormone type | Main hormone & effect |
|---|---|---|
| Zona glomerulosa | Mineralocorticoids | Aldosterone: keep Na⁺ & water, raise blood pressure |
| Zona fasciculata | Glucocorticoids | Cortisol: raise blood sugar, handle stress, reduce swelling |
| Zona reticularis | Androgens | DHEA: building blocks for sex hormones |
| Medulla | Catecholamines | Epinephrine: fast fight-or-flight rush |
Tap each layer of the gland in the interactive. Go from the outer cortex to the inner medulla.
- The adrenal gland is two glands in one. It has an outer cortex (steroids) and an inner medulla (catecholamines).
- Cortex zones, from outside in: glomerulosa → aldosterone (salt), fasciculata → cortisol (sugar and stress), reticularis → androgens (sex).
- The medulla is part of the sympathetic nervous system. It releases epinephrine for the fast fight-or-flight rush.
- Cortisol is the slow, steady stress hormone. Epinephrine is the fast one.
The chapter in one breath
- The endocrine system controls the body with hormones in the blood. It is slower than the nervous system, but it reaches more places and lasts longer. Its glands are ductless.
- A hormone reaches every cell. But it acts only on its target cells, which have the matching receptor.
- Lipid-soluble (steroid) hormones enter the cell and change genes. They are slow and lasting. Water-soluble (peptide/amine) hormones use surface receptors and a second messenger. They are fast and brief.
- The hypothalamus gives orders to the pituitary. The back lobe stores ADH and oxytocin. The front lobe makes six hormones, and four of them are tropic (FLAT PIG).
- The pancreatic islets balance blood sugar with an opposing pair. Insulin lowers it and glucagon raises it. Insulin is the only hormone that lowers it.
- The thyroid sets how fast you burn fuel through the HPT feedback axis. Too little hormone slows the body, and too much speeds it up. TSH moves opposite to thyroid output.
- The adrenal gland has a cortex wrapped around a medulla. The cortex makes aldosterone, cortisol, and androgens (salt, sugar, sex). The medulla makes epinephrine for the fast fight-or-flight rush.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- ACTH (adrenocorticotropic hormone)
- A tropic hormone from the front lobe of the pituitary. It tells the adrenal cortex to make cortisol.
- Adrenal cortex
- The outer part of the adrenal gland. Its three layers make steroid hormones: aldosterone, cortisol, and androgens.
- Adrenal medulla
- The inner core of the adrenal gland. It is part of the sympathetic nervous system and releases epinephrine and norepinephrine.
- Aldosterone
- A mineralocorticoid from the zona glomerulosa. It makes the kidney keep sodium and water, which raises blood pressure.
- Anterior pituitary
- The front lobe of the pituitary, made of gland tissue. It makes six hormones (GH, TSH, ACTH, FSH, LH, PRL) when the hypothalamus says so.
- Cortisol
- The main glucocorticoid, made in the zona fasciculata. It is the main long-acting stress hormone. It raises blood sugar and reduces swelling.
- Endocrine gland
- A gland with no duct that releases hormones straight into the blood. An exocrine gland, by contrast, uses a duct.
- Glucagon
- A hormone from the alpha cells of the pancreas. It raises blood sugar during fasting by breaking down glycogen and making new sugar.
- Glucocorticoid
- A type of adrenal steroid, mainly cortisol. It helps control blood sugar and the stress response.
- Hormone
- A chemical messenger that an endocrine gland releases into the blood. It acts on target cells far away.
- Hypothalamus
- The part of the brain that links the nervous and endocrine systems. It controls the pituitary gland.
- Insulin
- A hormone from the beta cells of the pancreas. It lowers blood sugar after a meal by helping cells take in sugar and store it as glycogen.
- Lipid-soluble hormone
- A hormone that dissolves in fat, such as a steroid or thyroid hormone. It crosses the cell membrane, binds receptors inside the cell, and changes which genes are active.
- Negative feedback
- A control loop where a hormone's output blocks its own making. This holds the value near a set point.
- Pancreatic islets
- Clusters of hormone-making cells in the pancreas. Beta cells make insulin, and alpha cells make glucagon.
- Posterior pituitary
- The back lobe of the pituitary, made of nerve tissue. It stores and releases ADH and oxytocin, which are made in the hypothalamus.
- Second messenger
- A relay molecule inside the cell, such as cyclic AMP. It passes on a water-soluble hormone's signal after the hormone binds a surface receptor.
- Steroid hormone
- A fat-soluble hormone built from cholesterol, such as cortisol, aldosterone, or a sex hormone. It acts on genes inside the cell.
- Target cell
- A cell that responds to a certain hormone because it has the matching receptor.
- Thyroid hormone
- The iodine-containing hormones T₃ and T₄. They set the body's basal metabolic rate.
- Tropic hormone
- A hormone whose target is another endocrine gland. Examples are TSH, ACTH, FSH, and LH.
- Water-soluble hormone
- A hormone that cannot enter the cell, such as a peptide, protein, or catecholamine. It works through a surface receptor and a second messenger.
Check yourself
The Cardiovascular System: Blood
Blood is the only tissue in your body you can pour into a test tube. It is easy to think little of it, since it looks like a plain red liquid. But that liquid is a connective tissue. It is a living fleet of cells floating in a sea full of proteins, and it touches every other cell you have. In this chapter we take a tube of blood apart, layer by layer. There is the straw-colored plasma on top and the packed red cells below. Between them is a thin white line. You will learn what each part carries and where blood cells are made. You will see how a red cell carries oxygen and how a cut seals itself in seconds. You will also learn why matching a patient's blood type before a transfusion can mean life or death.
By the end of this chapter you can
- List the main functions of blood: transport, regulation, and protection. Explain why blood counts as a connective tissue.
- Describe the layers a spun tube of blood splits into. Define plasma, buffy coat, and hematocrit.
- Name the three formed elements and the five kinds of white blood cell. Give the main job of each.
- Trace hematopoiesis, the making of blood cells, from one stem cell down the myeloid and lymphoid lines. Name the hormone that drives red cell making.
- Explain how hemoglobin picks up oxygen in the lungs and drops it off in the tissues. Explain how blood carries carbon dioxide.
- Walk through the three steps of hemostasis. Describe how the clotting chain builds a mesh of fibrin.
- Predict which ABO and Rh blood types match. Name the universal donor and the universal recipient.
Section 1What blood is made of
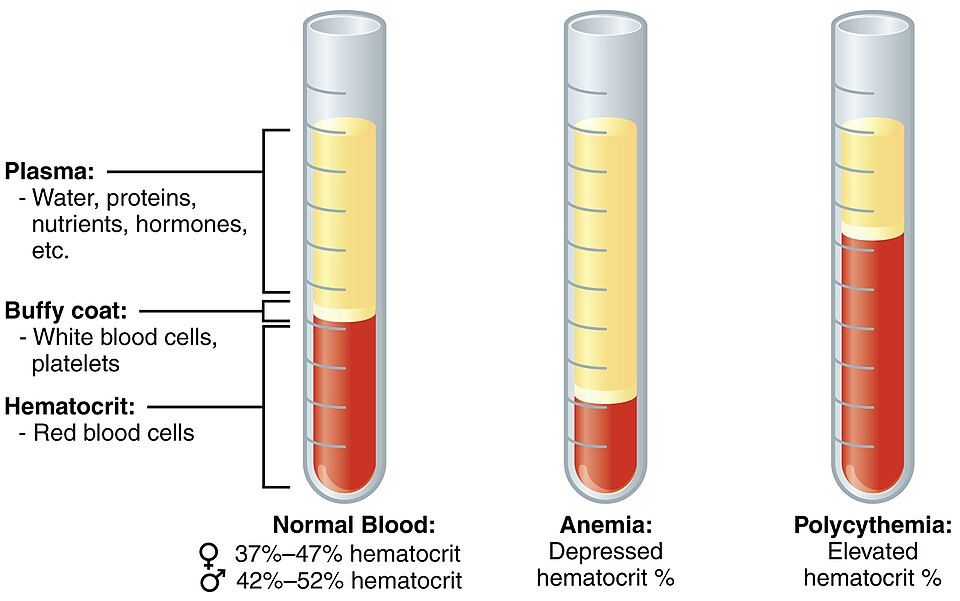
A tissue you can pour
Many people are surprised to hear that blood is a connective tissue. A connective tissue has cells spread out in an extracellular matrix, a material that fills the space between cells. Blood fits this perfectly. Its "cells" are the red cells, white cells, and platelets. Its matrix is the liquid plasma they float in. What makes blood unusual is that its matrix is a fluid. In bone the matrix is hard, and in cartilage it is rubbery.
An average adult has about 5 liters of blood. Women have a little less and men a little more. Blood makes up about 8 percent of body weight. It is heavier and thicker than water, about five times as thick (viscous). It is warm, at about 38 °C. It is also slightly basic (alkaline). Its pH stays in a narrow range, from 7.35 to 7.45.
Three jobs: transport, regulation, protection
Everything blood does fits into three groups. The first is transport, or carrying things. Blood brings O₂ and nutrients to cells. It takes away CO₂ and other wastes. It also carries hormones from glands to targets far away.
The second job is regulation, or keeping things steady. Blood can change where it flows and how much heat it takes to the skin. This helps keep body temperature steady. Chemicals in blood called buffers keep the body's pH steady. Blood proteins help control fluid balance between the blood and the tissues.
The third job is protection. White cells and antibodies fight germs. The clotting system seals leaks, so you do not bleed out from a small cut.
Spin it down and it splits in three
Put a tube of blood in a spinning machine called a centrifuge, and the heavier parts sink. You end up with three layers you can see. How big each layer is tells doctors a lot:
| Layer | What it holds | Share of blood |
|---|---|---|
| Plasma (top) | Water, plasma proteins, nutrients, gases, hormones, wastes, ions (salts) | About 55% |
| Buffy coat (middle) | Leukocytes (white cells) and platelets | Less than 1% |
| Erythrocytes (bottom) | Red blood cells. This share is the hematocrit. | About 45% |
That bottom layer has its own name. The hematocrit is the percent of whole blood that is red cells. Normal values are about 37–47 percent in women and 42–52 percent in men.
Plasma itself is about 92 percent water. Most of the rest is plasma proteins. Albumin is the most common one. It holds water inside the blood vessels and carries fatty molecules. Globulins include antibodies and proteins that carry things. Fibrinogen is the raw material for clots. One more term to learn now is serum. If you let blood clot and take the clot out, a pale fluid is left. That is serum, which is plasma without its clotting proteins.
Spin your own tube and pull apart the layers in the interactive below.
- Blood is a fluid connective tissue. It is cells (formed elements) floating in a liquid matrix (plasma). An adult has about 5 L, which is 8% of body weight.
- Its jobs fall into three groups: transport, regulation, and protection.
- Spun blood gives plasma (~55%), a thin buffy coat of white cells and platelets, and red cells (hematocrit, ~45%).
- Serum is plasma with the clotting proteins taken out.
Section 2The formed elements
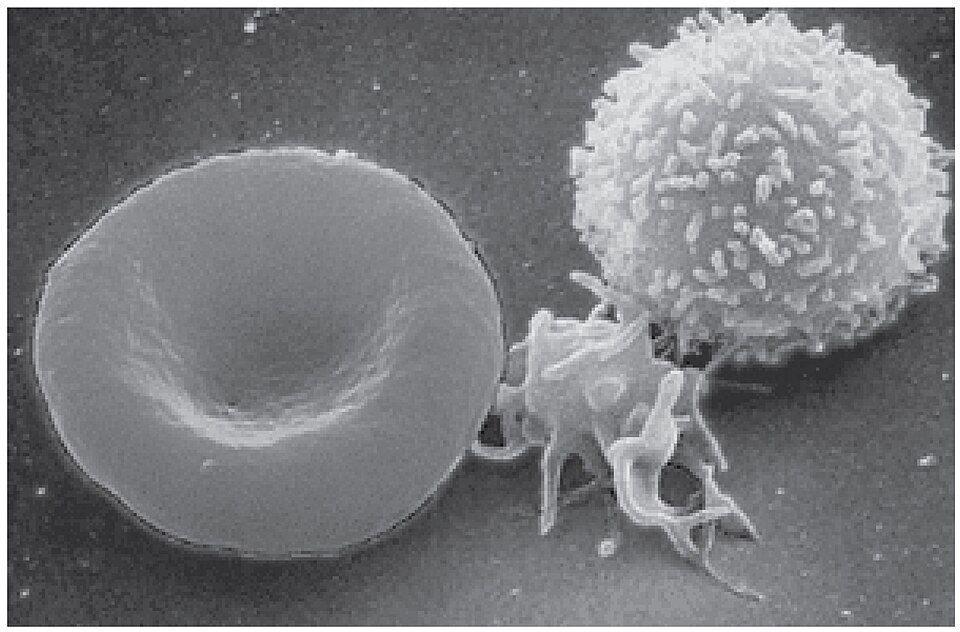
Three kinds of passenger
The living cargo of blood is called the formed elements. They come in three types. Erythrocytes are red blood cells. Leukocytes are white blood cells. Platelets are also called thrombocytes.
Their numbers are very uneven. Red cells rule, with about 5 million per microliter (a tiny drop) of blood. Platelets number a few hundred thousand. White cells are the rarest, with only about 5,000 to 10,000 per microliter. That is why the spun tube from Section 1 is almost all red on the bottom. The buffy coat is only a thin line.
Red cells: oxygen with everything stripped away
An erythrocyte is built to do one job well. It is a biconcave disc. That means it is a flat circle that is pinched in on both sides, like a donut with no hole. This shape gives it lots of surface for swapping gases. It also lets the cell fold so it can squeeze through capillaries, the tiny vessels narrower than itself.
The mature red cell makes room for as much hemoglobin as it can. To do this, it throws almost everything else out. It has no nucleus and no organelles, the small working parts of a cell. This has a cost. With no nucleus, the cell cannot repair itself. So it wears out in about 120 days. Then the spleen and liver recycle it. We will follow its oxygen work in Section 4.
White cells: the mobile defense force
Unlike red cells, every leukocyte keeps its nucleus. All of them are soldiers of the immune system. They split into two families. The split depends on whether they have tiny grains (granules) you can see.
The granulocytes have grainy insides. They are neutrophils, eosinophils, and basophils. The agranulocytes have no visible grains. They are lymphocytes and monocytes. To learn them from most to least common, use this memory trick. Never Let Monkeys Eat Bananas stands for Neutrophils, Lymphocytes, Monocytes, Eosinophils, Basophils.
| White cell | Group | Rough share | Main job |
|---|---|---|---|
| Neutrophil | Granulocyte | 50–70% | First to arrive; eats bacteria (phagocytosis) |
| Lymphocyte | Agranulocyte | 20–30% | Targeted (adaptive) immunity: T, B, and NK cells |
| Monocyte | Agranulocyte | 2–8% | Turns into a macrophage, a big cell that eats germs |
| Eosinophil | Granulocyte | 1–4% | Attacks parasites; plays a part in allergy |
| Basophil | Granulocyte | <1% | Releases histamine and heparin; causes inflammation |
Platelets: fragments that plug leaks
Platelets are not whole cells at all. They are cell fragments, small pieces pinched off from giant marrow cells. These giant cells are called megakaryocytes. Platelets have no nucleus and live only about 10 days. They have one purpose. They rush to a wound, pile up, and start a clot. We will watch them do it in Section 5.
Meet all three formed elements, and the five white cells, in the interactive.
- The three formed elements are erythrocytes (oxygen), leukocytes (defense), and platelets (clotting). Red cells far outnumber the rest.
- The red cell is a biconcave disc with no nucleus. It is packed with hemoglobin and lasts about 120 days.
- The five white cells, from most to least: neutrophils, lymphocytes, monocytes, eosinophils, basophils (Never Let Monkeys Eat Bananas).
- Platelets are megakaryocyte fragments that start clotting.
Section 3Where blood cells are born
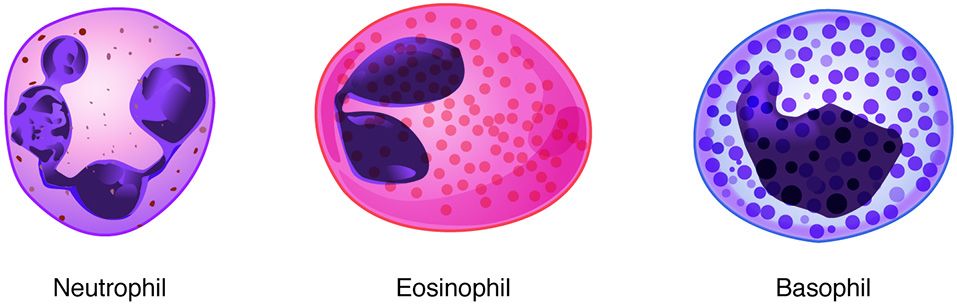
One stem cell, every blood cell
Red cells wear out in four months. Neutrophils wear out in just days. So your body must replace blood cells all the time. It makes hundreds of billions each day. The factory is the red bone marrow. The whole process of making blood cells is called hematopoiesis.
Amazingly, every one of these cells comes from a single kind of parent cell. It is the hematopoietic stem cell, also called a hemocytoblast. It is multipotent. This means it can become any blood cell, but only blood cells. It cannot become liver, nerve, or muscle. It also renews itself, so the supply never runs out. (Save the word pluripotent for embryonic stem cells and induced pluripotent stem cells. They can make tissues from all three germ layers, the first cell layers of an embryo.)
Two family lines: myeloid and lymphoid
Early on, the stem cell's offspring pick one of two branches. The myeloid line is the bigger one. It makes red cells and platelets (by way of megakaryocytes). It also makes most white cells: neutrophils, eosinophils, basophils, and monocytes. The lymphoid line makes only the lymphocytes. These are the T, B, and NK cells of targeted (adaptive) immunity.
Knowing which line a cell comes from is more than trivia. Blood cancers called leukemias are sorted as myeloid or lymphoid. The name depends on which branch of this tree went wrong.
| Line | Cells it makes | Notice |
|---|---|---|
| Myeloid | Erythrocytes, platelets, neutrophils, eosinophils, basophils, monocytes | The broad branch: almost everything |
| Lymphoid | Lymphocytes (T cells, B cells, NK cells) | The specialist branch: adaptive immunity |
Hormones set the pace
Blood cell making is not left to chance. Hormones and growth factors match it to what the body needs. The star is erythropoietin (EPO). The kidneys release it when they sense low oxygen. EPO tells the marrow to make more red cells. Thrombopoietin comes from the liver and drives platelet making. A group of colony-stimulating factors and interleukins boosts white cell making during an infection.
Building a red cell also needs raw materials. You need iron for hemoglobin. You also need vitamin B₁₂ and folate to make DNA. Run short on any of these and you become anemic. New red cells that are not quite finished are called reticulocytes. Doctors count them to see how hard the marrow is working.
Climb the family tree, one step at a time, in the interactive.
- Hematopoiesis happens in red bone marrow. Every blood cell comes from a multipotent hematopoietic stem cell.
- The stem cell branches into the myeloid line (red cells, platelets, most white cells) and the lymphoid line (lymphocytes).
- Erythropoietin from the kidney drives red cell making. Iron, B₁₂, and folate are the raw materials.
Section 4How blood carries oxygen
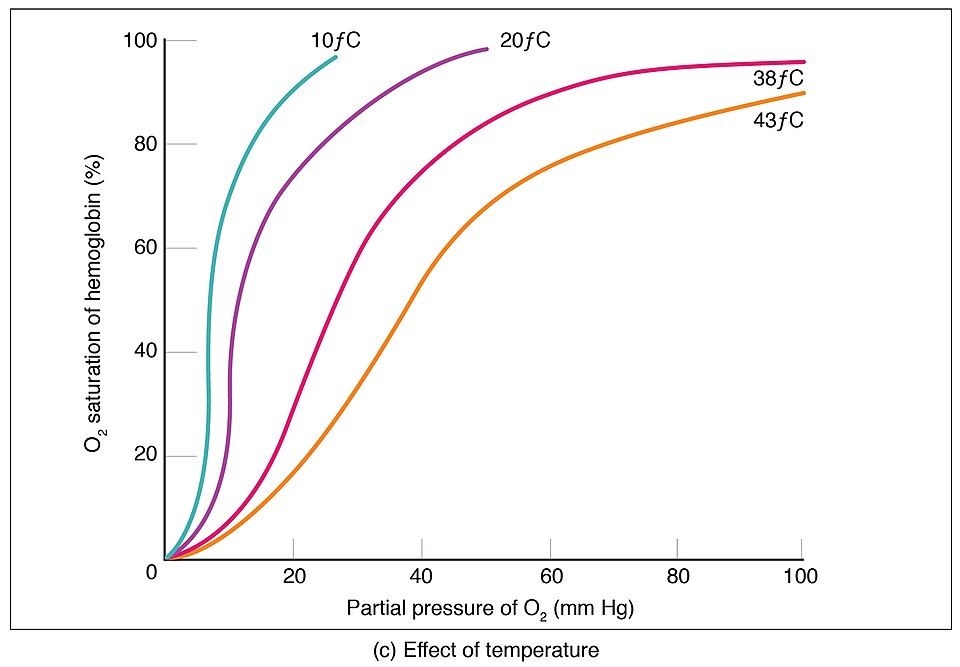
The molecule that does the carrying
Red cells matter because of one molecule, hemoglobin. Each hemoglobin is built from four protein chains. Two are alpha chains and two are beta chains, and they are called globins. Each chain holds a heme group. There is an atom of iron at the center of each heme. Oxygen binds to that iron.
One hemoglobin has four heme groups. So it can carry four O₂ molecules at once. A single red cell is stuffed with about 270 million hemoglobins. So one cell can carry over a billion oxygen molecules. Iron is the actual seat that oxygen sits on. That is why low iron so directly starves the tissues of oxygen.
Load in the lungs, unload in the tissues
Hemoglobin's genius is that it grabs oxygen where there is plenty. Then it lets go where oxygen is scarce. In the lungs, the pressure of oxygen (partial pressure) is high. Here hemoglobin binds O₂ and becomes oxyhemoglobin. This oxygen-rich blood is a bright scarlet red.
Out in the tissues, cells have used up their oxygen. Here the oxygen pressure is low. Hemoglobin lets go of its load and becomes deoxyhemoglobin, a darker brick red. That color change is why blood in arteries looks so much brighter than blood in veins.
The binding is also cooperative. Once the first O₂ is on, the next ones bind more easily. So loading and unloading both happen fast. Some conditions push hemoglobin to release more oxygen. These are warmth, extra CO₂, and more acid. These are exactly the conditions in a hard-working muscle. So oxygen is dropped off right where it is needed.
And the return trip: carbon dioxide
Blood does not just bring oxygen. It also clears away the CO₂ that cells make. This waste rides back in three ways. The shares are worth knowing:
| Gas | How it travels | Share |
|---|---|---|
| O₂ | Bound to hemoglobin as oxyhemoglobin | ~98.5% |
| O₂ | Dissolved in plasma | ~1.5% |
| CO₂ | As bicarbonate (HCO₃⁻) in plasma | ~70% |
| CO₂ | Bound to hemoglobin (carbaminohemoglobin) | ~23% |
| CO₂ | Dissolved in plasma | ~7% |
Watch a red cell load up and drop off, over and over, in the interactive.
- Hemoglobin has four globin chains, each with an iron-holding heme. Each molecule carries up to four O₂.
- It forms oxyhemoglobin (bright red) in the lungs. It releases O₂ and becomes deoxyhemoglobin (darker) in the tissues.
- CO₂ travels back mostly as bicarbonate (~70%). Some rides on hemoglobin, and a little is dissolved.
- Carbon monoxide beats oxygen to hemoglobin and blocks delivery.
Section 5How bleeding stops
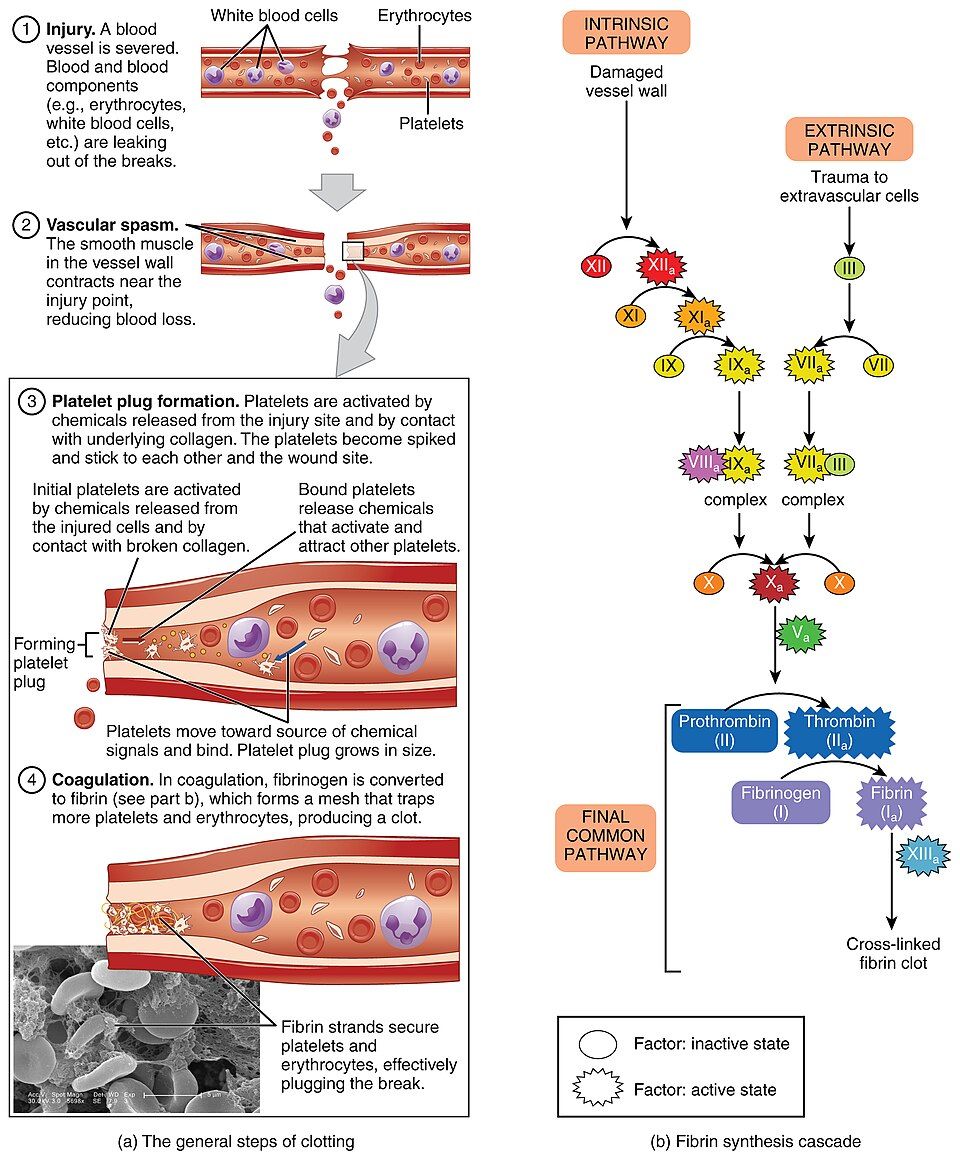
Three fast steps
When a blood vessel is cut, the body must seal the leak before too much blood escapes. This is called hemostasis, which means "blood standing still." It happens in three steps that overlap. Each step buys time for the next. The whole thing can start within seconds.
| Step | What happens | Result |
|---|---|---|
| 1. Vascular spasm | Smooth muscle in the vessel wall tightens near the injury | The vessel narrows, which slows blood loss |
| 2. Platelet plug | Platelets stick to bare collagen, switch on, and pile up | A soft plug fills the hole |
| 3. Coagulation | A chain of clotting factors builds a fibrin mesh | A firm clot locks the plug in place |
The platelet plug snowballs
A vessel has a smooth inner lining. When it tears, the tough collagen under it is exposed. Platelets grab onto the collagen. A linking protein called von Willebrand factor helps them hold on. This contact changes platelets from smooth discs into spiky, sticky, active platelets.
Active platelets then release chemicals. These are ADP, thromboxane A₂, and serotonin. They call in and switch on even more platelets. This is a classic positive feedback loop. Each new platelet calls in others, so the plug grows fast until the hole is covered. This is also the step that aspirin weakens. Aspirin blocks thromboxane. That is why low-dose aspirin makes platelets less sticky.
Coagulation: turning liquid into gel
A platelet plug alone is weak. Coagulation, or clotting, makes it strong. A relay of plasma proteins called clotting factors switch each other on in a cascade, like falling dominoes. There are two starting paths, the intrinsic and the extrinsic pathway. They join into one common pathway.
The end has two moves. First, the enzyme thrombin is switched on. Then thrombin turns fibrinogen, a plasma protein that dissolves, into threads of fibrin that do not dissolve. These threads weave a net that traps red cells and platelets. That net is the actual clot.
Two helpers work behind the scenes. Calcium (clotting factor IV) is needed at several steps. The liver needs vitamin K to build several of the factors in the first place. Once the wound heals, an enzyme called plasmin breaks up the clot. This is called fibrinolysis, which means "fibrin breaking."
Step through how the leak is sealed and then made strong in the interactive.
- Hemostasis has three steps: vascular spasm → platelet plug → coagulation.
- The platelet plug grows by positive feedback, as active platelets call in more. Aspirin weakens this step.
- Coagulation ends with thrombin turning fibrinogen into a fibrin mesh. It needs calcium and vitamin K.
Section 6Blood types and transfusion
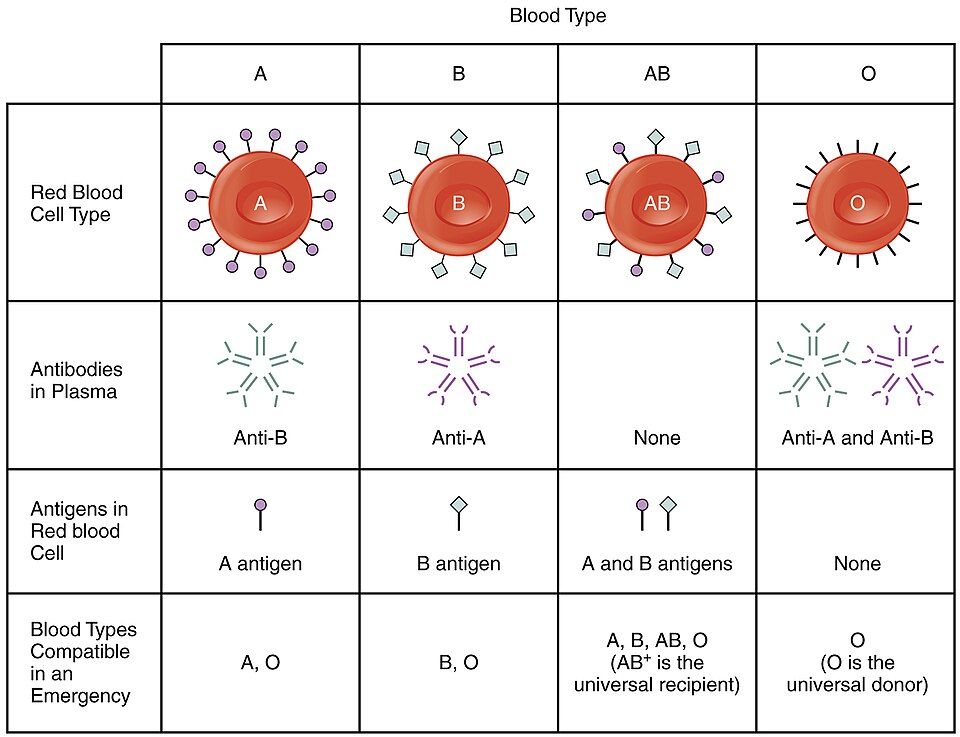
Antigens on the cell, antibodies in the plasma
Your blood type depends on tiny flags on the surface of your red cells. These flags are called antigens (agglutinogens). In the ABO system there are two possible flags, A and B. Your genes decide which ones you have.
Here is the key rule. Your plasma has antibodies (agglutinins) against any antigen you lack. A type A person has A antigens and anti-B antibodies. A type B person has B antigens and anti-A antibodies. A type AB person has both antigens and no ABO antibodies. A type O person has neither antigen, but has both anti-A and anti-B.
Why a mismatch is dangerous
Say a patient gets red cells with an antigen that their plasma has antibodies against. Those antibodies grab the donor cells and clump them together. This is called agglutination. Then the cells burst, which is called hemolysis. The broken pieces can clog small vessels and overload the kidneys. A serious transfusion reaction can kill. That is why blood is always typed and cross-matched before it is given.
| Type | Antigen on red cells | Antibody in plasma | Can receive from |
|---|---|---|---|
| A | A | Anti-B | A, O |
| B | B | Anti-A | B, O |
| AB | A and B | None | A, B, AB, O: the universal recipient |
| O | None | Anti-A and Anti-B | O only. It is the universal donor of red cells. |
The Rh factor
On top of ABO is the Rh system. It is named for the rhesus monkey, which was used in the tests that found it. It has several antigens: C, c, D, E, and e. But one of them, D, triggers the immune system by far the most. It is the only one tested for as a routine. If you have D, you are Rh-positive. If not, you are Rh-negative.
ABO antibodies are there from early in life. Rh antibodies are different. An Rh-negative person makes anti-D antibodies only after being exposed to Rh-positive blood. This fact leads to a very important case in pregnancy care. It is called hemolytic disease of the newborn.
Say an Rh-negative mother carries an Rh-positive baby. Her body can become sensitized to the D antigen, which means it learns to attack it. In a later Rh-positive pregnancy, her antibodies may cross the placenta. There they attack the baby's red cells. The fix is simple and clever. A shot of Rh immune globulin (RhoGAM) clears the baby's cells from her blood before her immune system can react.
Pick a blood type in the interactive. See exactly who it can give to and take from.
- Your blood type is set by the antigens on your red cells. Your plasma holds antibodies against the antigens you lack.
- A mismatched transfusion causes agglutination and hemolysis. So blood is typed and cross-matched first.
- O-negative is the universal red cell donor. AB-positive is the universal recipient.
- Rh-negative mothers with Rh-positive babies risk hemolytic disease of the newborn. RhoGAM prevents it.
The chapter in one breath
- Blood is a fluid connective tissue, with formed elements floating in plasma. It handles transport, regulation, and protection.
- Spun blood splits into plasma (~55%), a thin buffy coat, and red cells (hematocrit, ~45%). Plasma is mostly water plus albumin, globulins, and fibrinogen.
- The formed elements are erythrocytes (oxygen), five kinds of leukocyte (defense), and platelets (clotting).
- Hematopoiesis in red marrow starts from one stem cell. It branches into the myeloid and lymphoid lines. The kidney's erythropoietin drives red cell making.
- Hemoglobin carries four O₂ on iron-heme seats. It loads in the lungs and unloads in the tissues. CO₂ rides back mostly as bicarbonate.
- Hemostasis seals a wound in three steps: vascular spasm, platelet plug, and coagulation. It ends in a fibrin mesh.
- Blood type is set by red cell antigens (A, B, Rh). Plasma holds antibodies against the ones you lack. This makes O-negative the universal donor and AB-positive the universal recipient.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Agglutination
- The clumping of red blood cells when antibodies bind matching antigens. It happens in a mismatched transfusion.
- Albumin
- The most common plasma protein. It holds water in the blood vessels (osmotic pressure) and carries fatty molecules and drugs.
- Antibody (agglutinin)
- A plasma protein that finds and binds one certain antigen. ABO antibodies target the A or B antigen a person lacks.
- Antigen (agglutinogen)
- A marker on the surface of red cells (A, B, or Rh D). It sets your blood type and can trigger an immune response.
- Buffy coat
- The thin layer of white blood cells and platelets. It sits between the plasma and red cells in a spun sample.
- Coagulation
- The clotting chain, where factors switch each other on. It ends by turning fibrinogen into a fibrin mesh.
- Erythrocyte
- A red blood cell. It is a biconcave cell with no nucleus, packed with hemoglobin to carry oxygen.
- Erythropoietin (EPO)
- A hormone from the kidney. When oxygen is low, it tells the red bone marrow to make more red blood cells.
- Fibrin
- The protein thread that does not dissolve. Thrombin makes it from fibrinogen, and the threads form a mesh that traps cells in a clot.
- Formed elements
- The cell parts of blood: erythrocytes, leukocytes, and platelets.
- Hematocrit
- The percent of whole blood that is red blood cells. It is about 37–52%, and it differs between men and women.
- Hematopoiesis
- The making of blood cells in red bone marrow. All of them come from a multipotent hematopoietic stem cell.
- Hemoglobin
- The iron-holding protein in red cells, with four globin chains and four heme groups. It binds and carries oxygen.
- Hemostasis
- The stopping of bleeding. It happens through vascular spasm, a platelet plug, and coagulation.
- Leukocyte
- A white blood cell. These defenders have a nucleus and are split into granulocytes and agranulocytes.
- Plasma
- The liquid matrix of blood. It is about 92% water plus proteins, nutrients, gases, hormones, and wastes.
- Platelet (thrombocyte)
- A cell fragment from a megakaryocyte. It sticks to wounds and starts clotting.
- Rh factor
- The D antigen of the Rh blood group system. It is found in Rh-positive blood and missing in Rh-negative blood.
- Serum
- Plasma with its clotting proteins taken out. It is the fluid left after blood clots.
- Thrombin
- The enzyme that turns fibrinogen into fibrin. This is the last step in building a clot.
Check yourself
The Cardiovascular System: The Heart
Behind your breastbone is a muscle about the size of your fist. It squeezes about once a second, and it has never taken a break. Over a lifetime it will beat more than two and a half billion times. It will move enough blood to fill a small lake. In this chapter, we open up that pump. You will see how the heart is built as two pumps in one. You will follow one drop of blood on its full loop through the lungs and the body. You will watch the four valves keep blood moving forward. And you will follow the tiny electrical spark the heart makes for itself. A machine can read that spark right off the skin. The reading is called an ECG.
By the end of this chapter you can
- Find the heart in the mediastinum, the space between the lungs. Name the layers of its wall and the sac around it. Explain why the left ventricle is the thickest chamber.
- Name the four chambers and the great vessels, the big tubes attached to the heart. Say which ones carry blood rich in oxygen and which carry blood poor in oxygen.
- Trace blood flow through the heart in order. Tell the pulmonary loop (to the lungs) from the systemic loop (to the body).
- Name the four valves and say where each one sits. Explain how chordae tendineae and pressure keep blood flowing one way.
- Describe the conduction system, the heart's wiring, from the SA node to the Purkinje fibers. Explain why the AV node delay matters.
- Break one heartbeat into the steps of the cardiac cycle. Say what makes the “lub-dub” heart sounds.
- Match each wave of the ECG (P, QRS, and T) to the electrical event it records.
- Work out cardiac output from heart rate and stroke volume. Predict how it will change.
Section 1The heart as a double pump
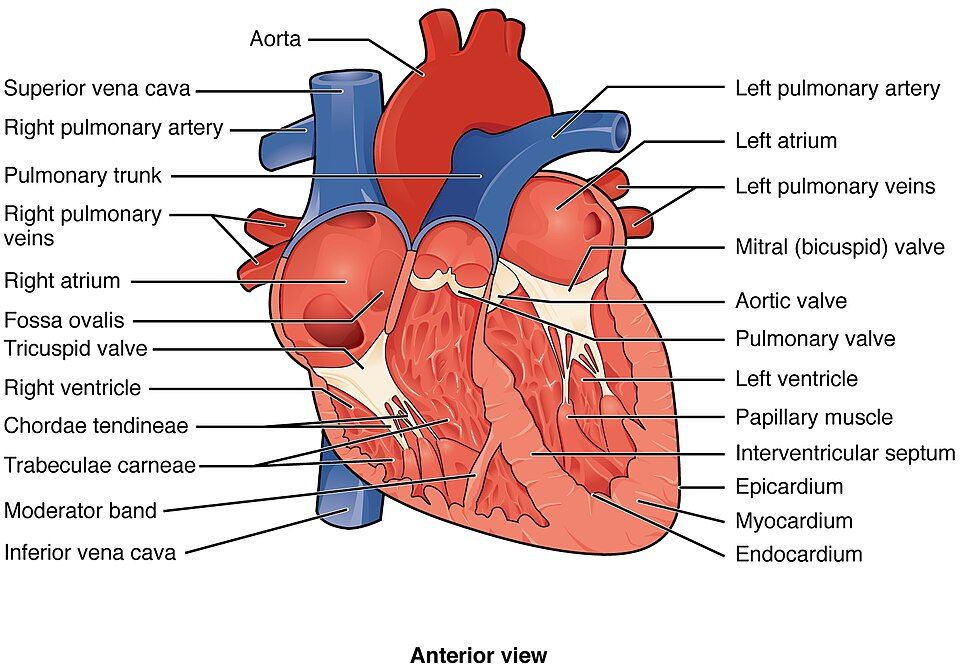
A fist-sized pump in the middle of the chest
The heart sits in the mediastinum, the space between your two lungs. It rests on the diaphragm, the big breathing muscle under your lungs. It is tilted, so about two-thirds of it lies to the left of your body's midline. The broad top, where the big vessels attach, is the base. The blunt tip points down and to the left. That tip is the apex. It is the spot where you can feel your heartbeat against your chest.
A tough sac with two walls wraps around the heart. This sac is the pericardium. Its outer layer, the fibrous pericardium, holds the heart in place. It also keeps the heart from overfilling. Inside that is the serous pericardium, which has two thin layers. It makes a slippery fluid that fills the pericardial cavity, the thin space around the heart. This fluid lets the beating heart glide without rubbing. Sometimes this space fills with fluid or blood and squeezes the heart. That is called cardiac tamponade, and it is a true emergency.
Two pumps, four chambers
Here is the most useful idea in this chapter. The heart is really two pumps bolted together. They sit side by side and work in perfect step. The right heart takes in blood low in oxygen coming back from the body. It pushes that blood a short way to the lungs. The left heart takes in fresh blood, full of oxygen, coming back from the lungs. It sends that blood out to the whole rest of the body.
A solid wall of muscle, the septum, keeps the two sides from mixing. Each pump has two chambers. On top is a thin-walled atrium that receives blood. Below is a thick-walled ventricle that pumps blood out. Blood always moves the same way: atrium → ventricle → out an artery.
| Chamber | Gets blood from | Sends blood to |
|---|---|---|
| Right atrium | The body, through the superior & inferior venae cavae (the two biggest veins) | Right ventricle |
| Right ventricle | Right atrium | The lungs, through the pulmonary trunk & arteries |
| Left atrium | The lungs, through the four pulmonary veins | Left ventricle |
| Left ventricle | Left atrium | The whole body, through the aorta |
Three layers, and a heart that feeds itself
The heart wall has three layers. The inner layer is the endocardium. It is a smooth lining that joins up with the lining of the blood vessels. So blood never touches a rough surface. The thick middle layer is the myocardium. This is the heart muscle that does the pumping. It is much thicker on the left side. The outer layer is the epicardium. It is the inner layer of the serous pericardium, the one stuck to the heart.
Look at the figure. See how the left ventricle wall is much thicker than the right one? The left side must make about five times as much pressure. It has to push blood all the way around the body. The right side only has to reach the lungs, which are close by.
All that hard-working muscle needs its own blood supply. The coronary arteries bring it. They branch off the aorta. If one gets blocked, the muscle past the block starves and dies. That is a heart attack. Its medical name is a myocardial infarction.
Tap through the chambers, vessels, and wall layers in the activity below.
- The heart lies in the mediastinum. It is wrapped in the pericardial sac. Fluid in the sac lets it beat without rubbing.
- It is two pumps in one. The right heart serves the lungs. The left heart serves the body. The septum keeps them apart.
- Atria receive, and ventricles pump out. The wall has three layers: endocardium, myocardium, and epicardium. The left ventricle is thickest because it faces the highest pressure.
- The coronary arteries feed the heart muscle. A blocked one causes a heart attack, or myocardial infarction.
Section 2Blood flow through the heart
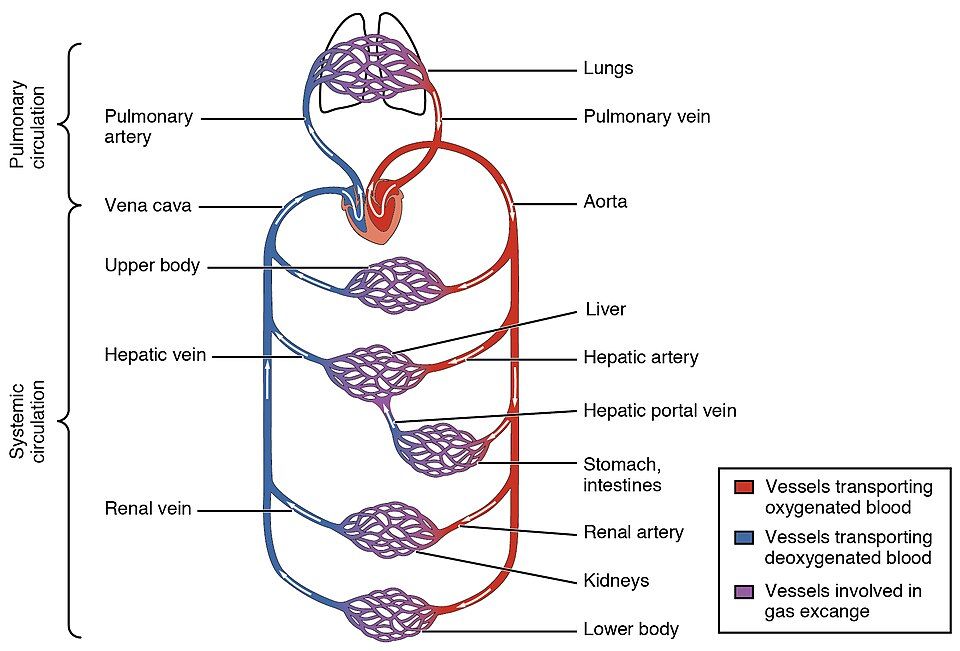
One drop, one full loop
Let's follow one drop of blood all the way around. It comes back from the body low in oxygen. It empties into the right atrium through the superior and inferior venae cavae. These are the two biggest veins. Next it drops through the tricuspid valve into the right ventricle. The right ventricle squeezes it through the pulmonary valve. From there it goes into the pulmonary trunk and on to the lungs.
In the lungs, it gives off carbon dioxide and picks up fresh oxygen. Now it is bright red. It flows back through the pulmonary veins into the left atrium. It passes the mitral valve into the strong left ventricle. Then it is pushed through the aortic valve into the aorta. From there it starts its trip around the body again.
| Step | Structure | Blood here is |
|---|---|---|
| 1 | Venae cavae → right atrium | Low in oxygen |
| 2 | Tricuspid valve → right ventricle | Low in oxygen |
| 3 | Pulmonary valve → pulmonary arteries → lungs | Low in oxygen (as it arrives) |
| 4 | Pulmonary veins → left atrium | Rich in oxygen |
| 5 | Mitral valve → left ventricle | Rich in oxygen |
| 6 | Aortic valve → aorta → body | Rich in oxygen |
Two circuits, run in series
That one loop is really two loops joined end to end. The pulmonary circuit goes from the right heart to the lungs and back. Its only job is to swap gases. The systemic circuit goes from the left heart out to every other tissue and back. That means the brain, gut, kidneys, muscles, and the rest.
The two loops are linked in series, one after the other. So each drop must pass through both. This means the two ventricles must pump the exact same amount of blood over time. Say the right side pumped a bit more than the left for a long time. Blood would back up in the lungs. If the left side pumped more, blood would back up in the body. That is why heart failure on one side slowly drags down the other side too.
The great exception
Here is a rule to learn by heart. Arteries carry blood away from the heart. Veins carry blood back toward it. Notice that the rule says nothing about oxygen. In most places, arteries happen to carry blood rich in oxygen. Veins usually carry blood low in oxygen. But the pulmonary vessels flip that.
The pulmonary arteries carry blood low in oxygen. It is going away from the heart, toward the lungs. The pulmonary veins carry blood rich in oxygen. It is coming back toward the heart. These vessels show that the real rule is about direction, not color.
Play or step one drop of blood through the whole loop in the activity.
- The forward path is: venae cavae → RA → tricuspid → RV → pulmonary valve → lungs → pulmonary veins → LA → mitral → LV → aortic valve → aorta.
- The pulmonary circuit (right heart ↔ lungs) and the systemic circuit (left heart ↔ body) run in series. So both ventricles move the same amount of blood.
- Arteries lead away, and veins lead back. The rule is about direction. The pulmonary vessels are the exception for oxygen.
Section 3The four one-way valves
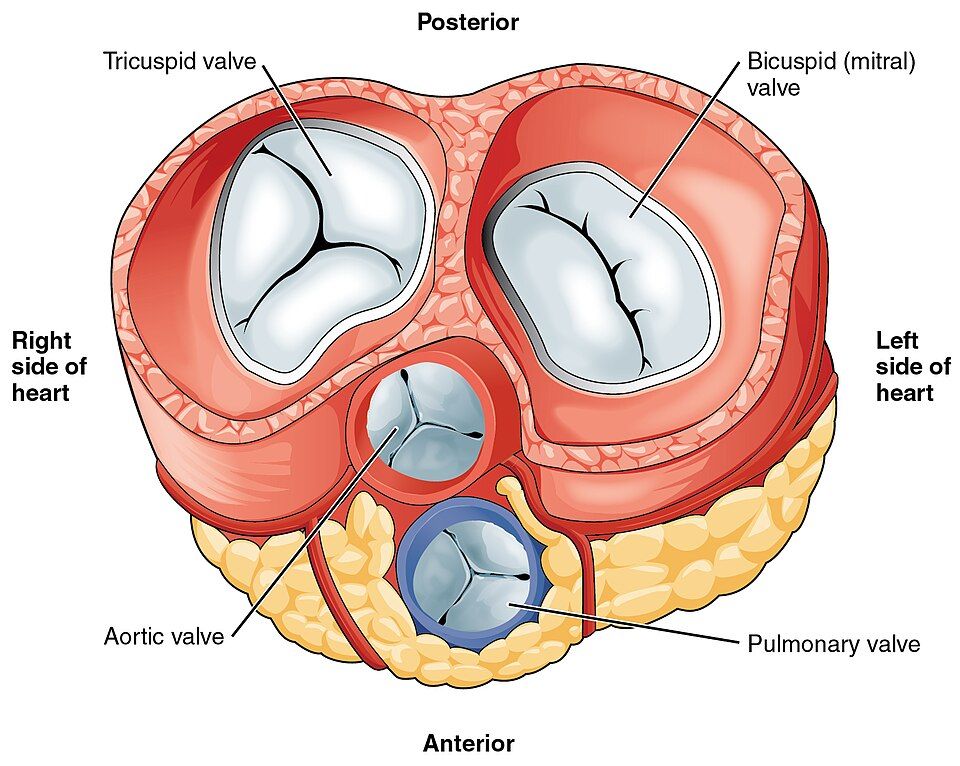
Four doors that only open one way
A pump is only as good as its valves. The heart has four. Each one is a flap door. It opens when blood pushes forward. It slams shut when blood pushes back.
Two of them are the atrioventricular (AV) valves. They sit between each atrium and the ventricle below it. The tricuspid valve is on the right side and has three flaps, or cusps. The mitral valve, also called the bicuspid valve, is on the left side and has two cusps. The other two are the semilunar valves. They guard the exits where the big arteries leave. The pulmonary valve sits at the opening of the pulmonary trunk. The aortic valve sits at the opening of the aorta. Together, they make sure blood can only go forward with each squeeze.
| Valve | Type | Location | Open when |
|---|---|---|---|
| Tricuspid | AV | Right atrium → right ventricle | Ventricles relaxed (filling) |
| Mitral (bicuspid) | AV | Left atrium → left ventricle | Ventricles relaxed (filling) |
| Pulmonary | Semilunar | Right ventricle → pulmonary trunk | Ventricles squeezing (pumping out) |
| Aortic | Semilunar | Left ventricle → aorta | Ventricles squeezing (pumping out) |
What holds them shut
The two types of valves stop backflow in different ways. When the ventricles squeeze hard, the pressure could push the AV valve flaps up into the atria. To stop this, each flap is tied down by tough strings. These are the chordae tendineae, or “heart strings.” They attach to small bumps of muscle on the ventricle floor, called papillary muscles.
The papillary muscles tighten just before the squeeze. The strings then hold the flaps like the ropes on a parachute. The flaps can close flat, but they cannot flip inside out. The semilunar valves need no strings. Each has three cup-shaped pockets. After the squeeze, some blood tries to fall back. The pockets catch it, and the weight snaps them shut.
When valves go wrong
Valves can fail in two ways, and the words are worth knowing. A stenotic valve is stiff and narrow. It will not open all the way. So the heart must strain to push blood through a smaller hole. A regurgitant valve is leaky. It is also called an insufficient valve. It will not close all the way, so blood sloshes backward with each beat.
Both problems make blood swirl in a rough way. You can hear this swirling with a stethoscope. The sound is called a murmur. The normal, healthy “lub-dub” is just the sound of valves snapping shut. That leads us to the cardiac cycle.
Tap each valve to watch it open and close in the activity.
- Two AV valves sit between the atria and ventricles: the tricuspid on the right and the mitral (bicuspid) on the left. Two semilunar valves, the pulmonary and aortic, guard the artery exits.
- Chordae tendineae and papillary muscles hold the AV flaps. This keeps them from flipping back during the squeeze.
- A valve can fail by stenosis (it won’t open) or regurgitation (it won’t close). Both cause murmurs. The normal S1/S2 sounds are valves snapping shut.
Section 4The conduction system
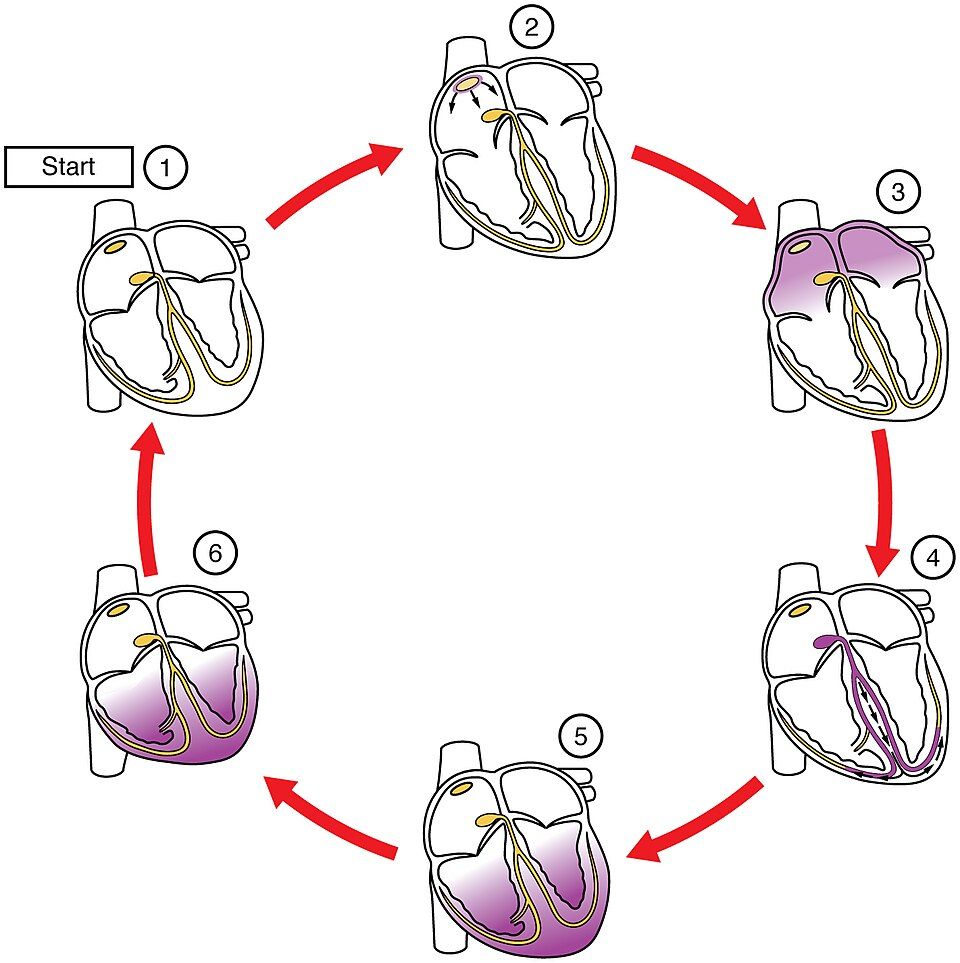
A heart that writes its own rhythm
Your arm muscles wait for the brain to tell them to move. The heart does not. A small group of special cells can fire an electrical signal all on their own, again and again. This is called autorhythmicity, which means “self-rhythm.”
The fastest of these cells form the sinoatrial (SA) node. It sits in the wall of the right atrium. It fires about 60 to 100 times a minute. It sets the pace for all the other cells. That is why the SA node is called the heart’s pacemaker. If you cut every nerve to the heart, it would keep right on beating. The nerves only speed it up or slow it down, as you will see.
The path of the spark
The signal spreads in a set order. That way the chambers squeeze in the right sequence: atria first, then ventricles. It starts at the SA node and sweeps across both atria. This makes them squeeze and top off the ventricles. Next it reaches the atrioventricular (AV) node. This node is the only electrical doorway between the atria and the ventricles. Here the signal pauses on purpose for about a tenth of a second.
From the AV node, the signal races down the AV bundle, also called the bundle of His. It splits into the right and left bundle branches, which run along the septum. Then it fans out through the Purkinje fibers into the ventricle walls. The ventricles squeeze from the bottom up, starting at the apex. This pushes blood toward the exits, like squeezing a tube of toothpaste from the bottom.
| Part | Job | Rate it fires on its own |
|---|---|---|
| SA node | Pacemaker. Starts each beat and fires the atria. | 60–100 / min |
| AV node | Gateway to the ventricles. Delays the signal. | 40–60 / min |
| AV bundle & branches | Carry the signal down the septum | — |
| Purkinje fibers | Spread the signal through the ventricle walls | 20–40 / min |
Why the pause, and who controls the tempo
The delay at the AV node is not a flaw. In fact, it is key. It gives the atria just enough time to finish emptying into the ventricles. Only then do the ventricles squeeze. Without the pause, all four chambers would squeeze at once. Then the heart would pump much less blood.
The heart also has built-in backups. If the SA node stops working, the AV node can take over. It fires at a slower 40 to 60 beats a minute. The Purkinje fibers can take over too, but even more slowly. This safety net keeps a failing heart beating, just too slowly.
The autonomic nervous system is the heart’s speed dial. This is the part of your nervous system that runs without your control. Sympathetic nerves speed up the SA node and make each squeeze stronger. They act during fear or exercise. The parasympathetic vagus nerve slows the heart back down when you rest.
Follow the spark from the SA node all the way down in the activity.
- The heart is autorhythmic. It makes its own beat. The SA node is the pacemaker. It fires 60–100 times a minute.
- The path is SA node → AV node → AV bundle → bundle branches → Purkinje fibers. So the atria squeeze before the ventricles.
- The AV node delay lets the atria finish filling the ventricles. Slower backup pacemakers take over if the SA node fails.
- Sympathetic nerves speed up the heart. Parasympathetic (vagus) nerves slow it down.
Section 5The cardiac cycle
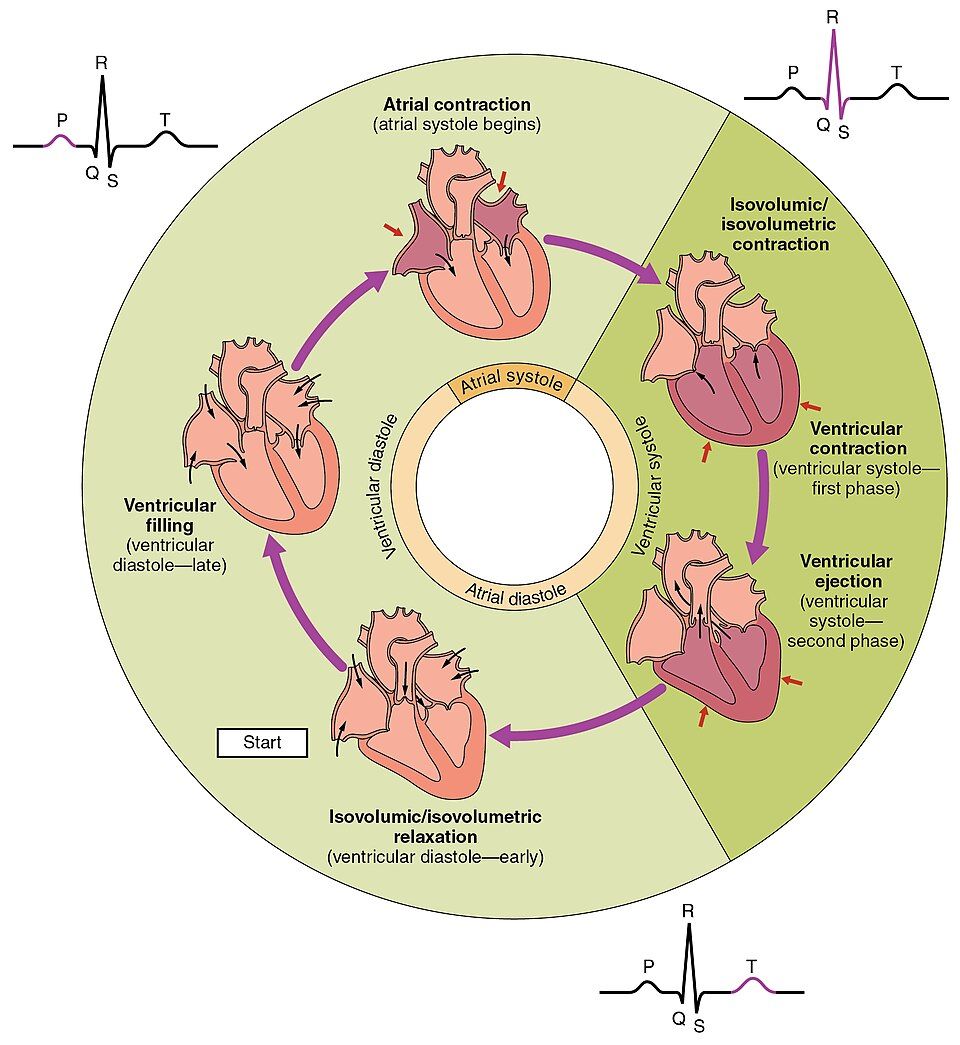
Squeeze and rest, over and over
One heartbeat switches between two states, over and over. Systole is the squeeze. A chamber tightens to push blood out. Diastole is the rest. A chamber loosens to fill back up. At rest, your heart beats about 75 times a minute. At that pace, one full cycle takes about 0.8 seconds.
Here is an important fact. The heart spends more of that time resting than squeezing. That rest is not laziness. It is when the ventricles refill. It is also the only time the coronary arteries can push blood into the thick heart muscle. If the heart beats too fast, it cuts the rest time short. That means less filling and less blood for the heart muscle.
The phases, in order
Walk around the wheel in the figure, and the order makes sense. First comes atrial systole. The atria give a gentle squeeze. This tops off the ventricles, which are already mostly full.
Next comes ventricular systole, which has two parts. First is isovolumetric contraction. “Isovolumetric” means “same volume.” All four valves are shut. Pressure builds, but no blood moves. Then comes ventricular ejection. The semilunar valves pop open, and blood rushes into the arteries.
Last comes ventricular diastole, which also has two parts. First is isovolumetric relaxation, when all the valves are shut again. Then comes ventricular filling. The AV valves open, and blood pours in. Most of it flows in on its own, before the atria even squeeze.
| Phase | What happens | AV valves | Semilunar valves |
|---|---|---|---|
| Atrial systole | Atria squeeze and add the last 20–30% of filling | Open | Closed |
| Isovolumetric contraction | Ventricles tighten. Pressure builds, but no blood leaves. | Closed | Closed |
| Ventricular ejection | Ventricles push blood into the arteries | Closed | Open |
| Isovolumetric relaxation | Ventricles relax. Pressure falls, but no blood enters. | Closed | Closed |
| Ventricular filling | Blood flows into the ventricles on its own | Open | Closed |
Lub-dub, and the numbers that matter
The two heart sounds come from valves closing, not opening. S1 is the low “lub.” It is the AV valves snapping shut as the ventricles start to squeeze. S2 is the sharper “dub.” It is the semilunar valves snapping shut as the ventricles start to relax. Between the two sounds, the heart is pumping blood out. After S2, it is filling.
A few numbers sum it all up. The amount of blood in a ventricle when it is done filling is the end-diastolic volume (EDV). The amount left after it pumps is the end-systolic volume (ESV). The amount actually pumped out in one beat is the stroke volume. You find it by taking EDV − ESV. Now multiply stroke volume by heart rate. That gives you cardiac output. This is how many liters of blood the heart moves each minute. At rest, it is about 5 L.
Step through each phase and hear the lub-dub in the activity.
- Systole is the squeeze, and diastole is the rest. At rest, one cycle takes about 0.8 s. Most of that time is diastole.
- The phases go in this order: atrial systole → isovolumetric contraction → ejection → isovolumetric relaxation → filling.
- S1 (“lub”) is the AV valves closing. S2 (“dub”) is the semilunar valves closing.
- Stroke volume = EDV − ESV. Cardiac output = heart rate × stroke volume. At rest, that is about 5 L/min.
Section 6The ECG
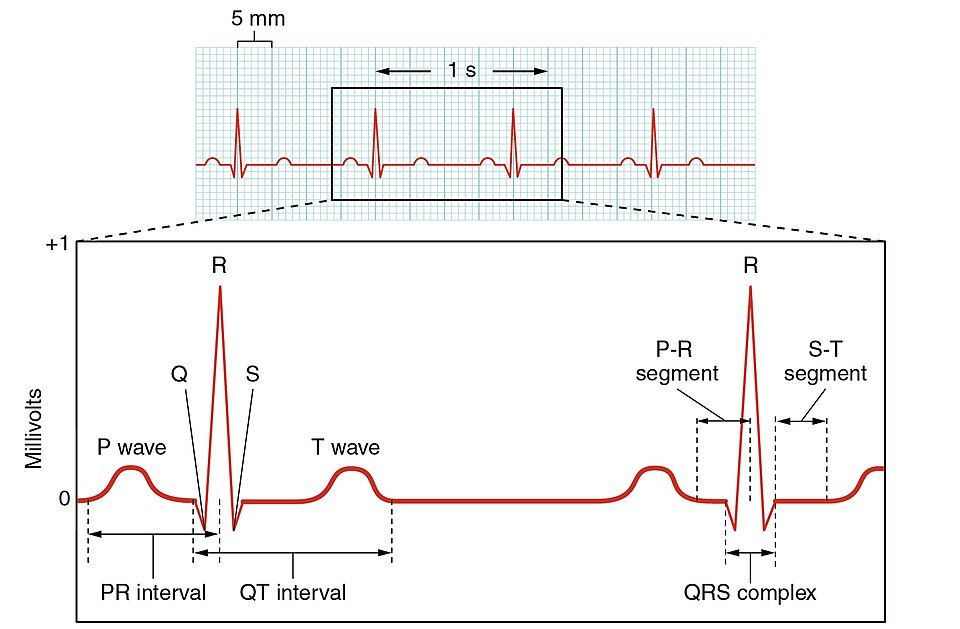
Reading the heart’s electricity off the skin
Each time the heart fires, a wave of electrical change spreads through it. This firing is called depolarization. The wave is strong enough to reach the skin. Small sensors stuck to the skin can pick it up. When you plot that signal over time, you get an electrocardiogram, or ECG (also written EKG).
The ECG is one of the most useful tests in medicine. It is painless and cheap. It does not record the heartbeat itself. It records the electrical events that set off the heartbeat. So each bump on the tracing lines up with a step in the wiring you just learned. Learn to read three simple bumps, and the whole picture opens up.
P, QRS, and T
The tracing repeats three main shapes. The small P wave shows atrial depolarization. This is the SA node’s signal spreading across the atria, just before they squeeze. The tall, spiky QRS complex shows ventricular depolarization. It is big and sharp because the ventricles have so much muscle.
The atria also reset, or repolarize, at this time. But that signal is hidden inside the QRS, so it never gets its own wave. The rounded T wave shows ventricular repolarization. This is when the ventricles reset their electrical charge so they can relax and fill again. Remember, the electrical firing is what starts the squeeze. So on the tracing, the electrical wave always comes a moment before the squeeze.
| Feature | Electrical event | What the heart does |
|---|---|---|
| P wave | Atrial depolarization | Atria squeeze |
| PR interval | SA node fires, and the signal passes through the AV-node delay | Signal waits at the AV node |
| QRS complex | Ventricular depolarization | Ventricles squeeze |
| T wave | Ventricular repolarization | Ventricles relax |
Intervals, rate, and trouble
The flat parts between the waves tell you as much as the waves do. The PR interval runs from the start of the P wave to the start of the QRS. It covers the atria firing plus that key pause at the AV node. If it gets too long, the person has a heart block. The QRS duration tells you how fast the ventricles are being fired. The QT interval covers the whole span of the ventricles’ electrical activity.
You can even read the heart rate right off the paper. The tracing moves at a fixed speed. So the space between two QRS peaks tells you the beats per minute. A heart rate that is too fast is tachycardia. One that is too slow is bradycardia.
Sometimes the line is a messy, shaking squiggle with no real QRS at all. This is ventricular fibrillation. The ventricles are just twitching, and no blood is moving. A defibrillator is built to shock this rhythm back into order.
Tap each wave to link it to its step in the heart’s wiring in the activity.
- An ECG records the heart’s electrical events from the skin. Each bump matches a step in the heart’s wiring.
- P = atrial depolarization. QRS = ventricular depolarization. T = ventricular repolarization. The electrical wave comes just before the squeeze.
- The PR interval holds the AV-node delay. A long one is a sign of heart block.
- Rhythm names: tachycardia (fast), bradycardia (slow), and ventricular fibrillation (messy, with no blood pumped). ST elevation is a warning sign of a heart attack.
The chapter in one breath
- The heart is a fist-sized double pump in the mediastinum. It is wrapped in a pericardial sac. The left ventricle is thickest because it faces the highest pressure.
- On each side, blood flows atrium → ventricle → artery. The right heart serves the pulmonary circuit (lungs). The left heart serves the systemic circuit (body). The two loops run in series.
- Arteries lead away, and veins lead back. The rule is about direction. The pulmonary vessels flip the usual oxygen pattern.
- Four one-way valves keep blood moving forward. Two are AV valves (tricuspid, mitral), and two are semilunar (pulmonary, aortic). Chordae tendineae hold the AV flaps in place.
- The heart is autorhythmic. The SA node sets the pace. The AV node delays the signal. The Purkinje fibers carry it into the ventricles.
- One beat is made of systole and diastole. S1/S2 are the sounds of valves closing. Cardiac output = heart rate × stroke volume.
- The ECG reads the heart’s electrical events from the skin: P (atria), QRS (ventricles firing), and T (ventricles resetting).
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back any time a word trips you up.
- Aorta
- The largest artery in the body. It carries blood rich in oxygen out of the left ventricle to start the trip around the body.
- Atrioventricular (AV) node
- The electrical gateway between the atria and ventricles. It holds the signal for about a tenth of a second so the atria can finish filling the ventricles.
- Atrioventricular (AV) valve
- A valve between an atrium and the ventricle below it. The tricuspid is on the right, and the mitral (bicuspid) is on the left. Chordae tendineae hold them shut.
- Atrium
- An upper, thin-walled chamber of the heart that receives blood. The right atrium gets blood from the body. The left gets blood from the lungs.
- Cardiac cycle
- One full heartbeat. It is made of the chambers squeezing (systole) and relaxing (diastole).
- Cardiac output
- How much blood a ventricle pumps each minute. It equals heart rate times stroke volume, about 5 L/min at rest.
- Chordae tendineae
- Tough cords that tie the AV valve flaps to the papillary muscles. They keep the flaps from flipping backward when the heart squeezes.
- Diastole
- The resting phase of a heart chamber, when it fills with blood.
- Electrocardiogram (ECG)
- A recording of the heart’s electrical activity taken from the skin. Its P, QRS, and T waves match steps in the heart’s wiring.
- Endocardium
- The smooth inner lining of the heart. It joins up with the lining of the blood vessels.
- Myocardium
- The thick middle layer of heart muscle that does the pumping. It is thickest in the left ventricle.
- Pericardium
- The sac with two walls around the heart. Its inner layers make fluid so the beating heart moves without rubbing.
- Pulmonary circuit
- The loop from the right heart to the lungs and back. Here blood picks up oxygen and drops off carbon dioxide.
- Purkinje fibers
- Fast fibers that spread the electrical signal through the ventricle walls. They make the ventricles squeeze from the apex up.
- QRS complex
- The tall, spiky part of the ECG. It shows ventricular depolarization, just before the ventricles squeeze.
- Semilunar valve
- A cup-shaped valve at a ventricle’s exit into a big artery. The pulmonary and aortic valves are this type. They snap shut to stop backflow.
- Sinoatrial (SA) node
- The heart’s natural pacemaker, in the wall of the right atrium. It fires 60–100 times a minute and sets the rhythm.
- Stroke volume
- The amount of blood a ventricle pumps out in one beat. It is the end-diastolic volume minus the end-systolic volume.
- Systemic circuit
- The loop from the left heart out to all the body’s tissues and back to the right heart.
- Systole
- The squeezing phase of a heart chamber, when it pumps blood out.
- Ventricle
- A lower, thick-walled pumping chamber of the heart. The right one pumps blood to the lungs. The left one pumps it to the whole body.
Check yourself
Blood Vessels & Circulation
The heart is only the pump. The real work of blood flow happens in the tubes. In this chapter, you will follow one red blood cell on its trip. It is flung out of the heart into arteries that branch into smaller and smaller channels. Then it reaches capillaries, tubes so thin that oxygen and food leak through their walls into your tissues. Last, it climbs back up through the veins, against gravity, to start the loop again.
Along the way, you will learn why an artery wall is thick and a capillary wall is just one cell thick. You will learn what blood pressure really measures. You will see how fluid "decides" whether to leave the blood or go back in. You will also learn the clever tricks your body uses to lift blood up out of your feet. Once you know the vessels, you will know more than how blood moves. You will see why swollen ankles, bulging leg veins, and a stroke all come back to the same set of rules.
By the end of this chapter you can
- Name the three tunics, or layers, of a blood vessel wall. Describe the tissue in each one and its job.
- Compare arteries, veins, and capillaries. Look at how thick the wall is, how wide the inside is, the pressure, and the job.
- Define blood pressure and tell systolic from diastolic pressure. Work out pulse pressure and mean arterial pressure.
- Explain how pressure and resistance shape blood flow. Explain why the arterioles, the tiniest arteries, control most of the body's resistance.
- Draw capillary exchange as a tug-of-war between hydrostatic pressure and colloid osmotic pressure. Explain how this balance can cause swelling, or edema.
- Tell the pulmonary loop from the systemic loop. Describe special routes such as the hepatic portal system.
- List the ways blood gets back to the heart, called venous return. These are the skeletal muscle pump, the breathing pump, and one-way valves. Link their failure to real diseases.
Section 1The wall of a blood vessel
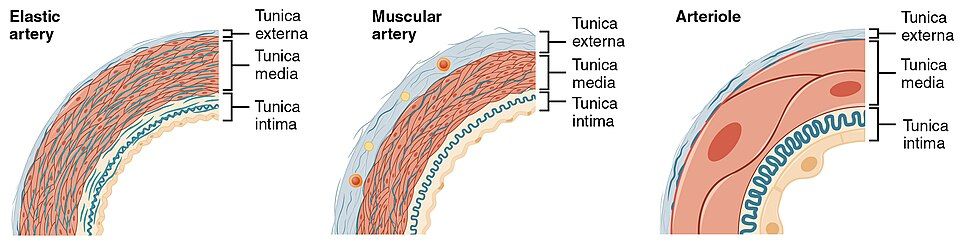
Three layers around a hollow center
Every artery and vein is built the same way. It has a set of layers, one inside the other, called tunics. The word comes from the Latin for "coats." These coats wrap around a hollow channel called the lumen. The lumen is the space the blood flows through.
From the inside out, the three layers are the tunica intima, the tunica media, and the tunica externa. Every vessel has the same layers. What changes from an artery to a vein to a capillary is how thick each layer is. It also changes how much muscle or stretchy tissue each layer has. Learn the three coats once, and you can read the wall of any vessel in the body.
Intima, media, externa: from lining to anchor
The inner coat is the tunica intima. It is mostly one sheet of flat cells called the endothelium. This sheet lines the heart and every blood vessel in one unbroken surface. It is much more than wallpaper. It is so smooth that blood cells glide past without clotting. It also sends out chemical signals, such as nitric oxide. These signals tell the muscle below to relax or tighten. Under the endothelium is a thin base layer. In arteries, there is also a springy sheet called the internal elastic lamina.
The middle coat is the tunica media. It is usually the thickest layer, and it is the vessel's muscle. It is made of rings of smooth muscle mixed with sheets of stretchy fibers. When the smooth muscle tightens, the lumen gets narrower. This is vasoconstriction. When the muscle relaxes, the lumen gets wider. This is vasodilation. Nerves and hormones control this layer. So the tunica media is the dial your body turns to send blood where it is needed. It also helps set your blood pressure.
The outer coat is the tunica externa, also called the tunica adventitia. It is a tough sleeve of collagen fibers. It anchors the vessel to the tissue around it and keeps it from stretching too far. Big vessels have walls too thick to feed themselves from the inside. So their tunica externa carries its own tiny blood vessels. These are called the vasa vasorum, which means "vessels of the vessels."
| Tunic | Main tissue | Job |
|---|---|---|
| Tunica intima | Endothelium + a thin base layer (+ internal elastic lamina in arteries) | Smooth, non-stick lining. Sends signals that relax or tighten the wall. |
| Tunica media | Smooth muscle + stretchy fibers | Vasoconstriction and vasodilation. Sets how wide the vessel is and helps set blood pressure. |
| Tunica externa | Collagen (and stretchy) connective tissue | Anchors and protects the vessel. Carries the vasa vasorum in big vessels. |
Peel the wall apart one layer at a time in the activity below.
- Every vessel wall has three tunics around a hollow center, the lumen. They are the intima, media, and externa.
- The tunica intima is lined by the endothelium. This smooth, non-stick lining tells the wall when to relax or tighten.
- The tunica media is smooth muscle. It sets how wide the vessel is through vasoconstriction and vasodilation.
- The tunica externa is collagen, and it anchors the vessel. Atherosclerosis starts when the intima is hurt.
Section 2Arteries, veins & capillaries
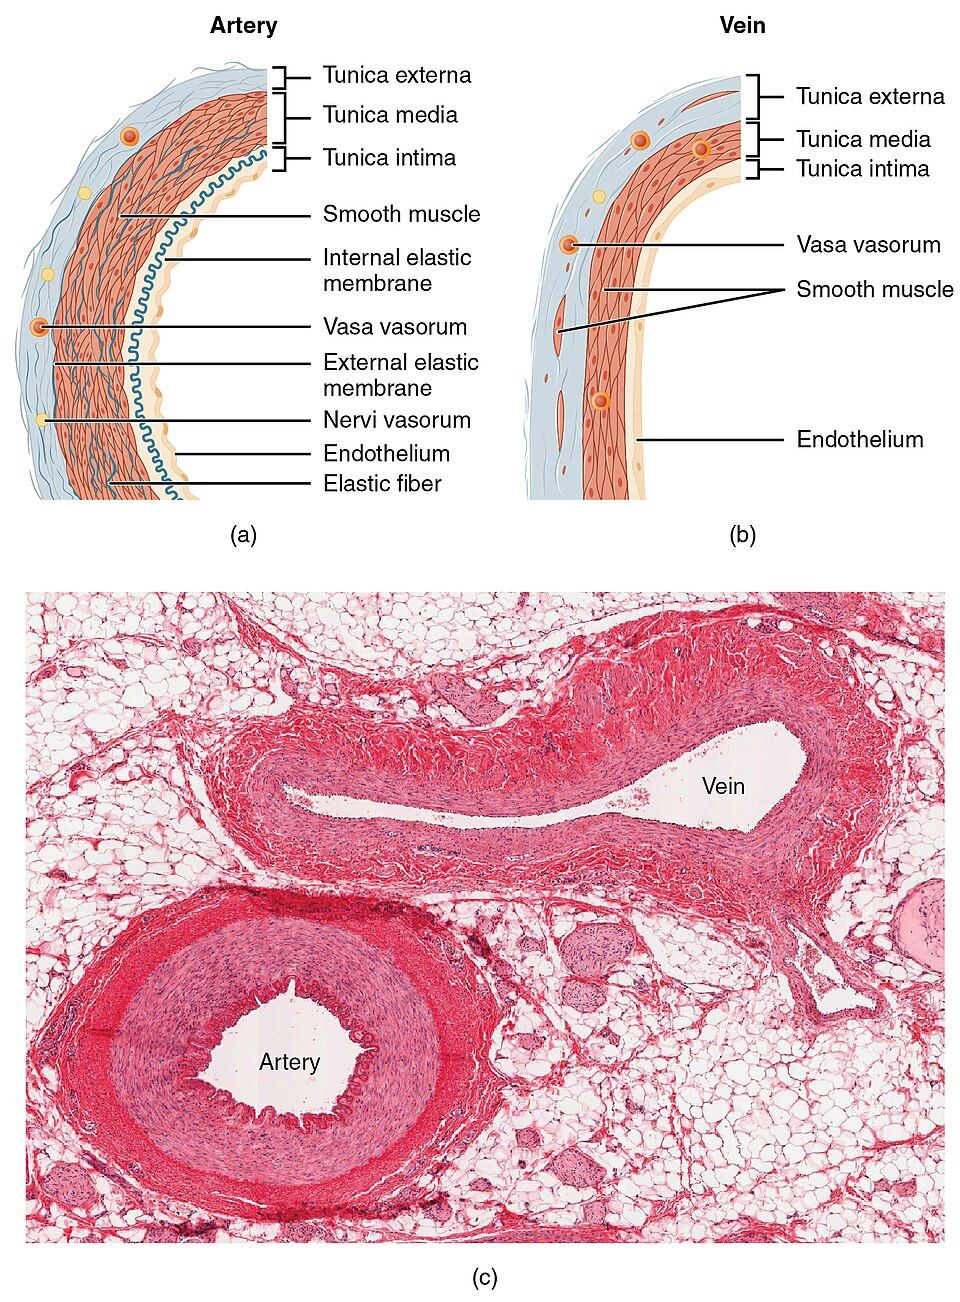
Arteries: the high-pressure pipes
An artery is any vessel that carries blood away from the heart. This rule is about direction, not about oxygen. That will matter later. Arteries get a hard push of blood with every heartbeat. So they have a thick, muscular tunica media and strong, stretchy walls.
The biggest arteries near the heart, like the aorta, are elastic (conducting) arteries. Their walls stretch as the ventricle pumps blood in. Then they spring back between beats. This turns the pulsing flow into a steadier stream. Farther out, muscular (distributing) arteries bring blood to each organ. The smallest branches are the arterioles. They act like nozzles you can adjust. They control how much blood flows into each bed of capillaries.
Veins: the low-pressure reservoirs
A vein carries blood back toward the heart. By the time blood reaches the veins, it has used up nearly all its pressure in the capillaries. So veins do not need thick, muscular walls. Instead, they have a thin middle layer, a wide and floppy lumen, and a large outer layer.
The key feature of veins is their one-way valves. These are flaps of the inner lining. They snap shut to stop blood from sliding backward. Veins stretch easily, so they act as the body's blood reservoir, or storage tank. At rest, about two-thirds of all your blood sits in your veins. It is ready to be squeezed back into use when your body needs more. For this reason, veins are also called capacitance vessels, which means "holding" vessels.
Capillaries: where the exchange happens
Between the smallest arteriole and the smallest venule are the capillaries. They are the reason the whole system exists. A capillary wall is just one layer of endothelium on a thin base layer. It is the tunica intima with everything else stripped away. That paper-thin wall is the point. Oxygen, carbon dioxide, sugar, and wastes can slip right across it, between the blood and the tissue.
There are so many capillaries that no cell in the body is more than about a tenth of a millimeter from one. Capillaries come in three levels of leakiness. Each type fits how much needs to cross. Continuous capillaries are the tightest. They are found in muscle and the brain. Fenestrated capillaries have small pores, or "windows." They are found in the kidney and intestine. Sinusoidal capillaries have the widest gaps. They are found in the liver and bone marrow.
| Feature | Artery | Capillary | Vein |
|---|---|---|---|
| Direction | Away from heart | Through tissues | Toward heart |
| Wall | Thick, muscular, stretchy | One endothelial cell thick | Thin, wide lumen |
| Pressure | High | Falling | Low |
| Valves | None (the aortic and pulmonary valves are in the heart) | None | Yes, one-way |
| Main job | Carry and spread out blood under pressure | Swap O₂, CO₂, nutrients, and wastes | Bring blood back and store it (reservoir) |
Switch between the three types of vessels and watch their jobs change.
- Arteries carry blood away from the heart under high pressure. They have thick, stretchy, muscular walls.
- Veins carry blood toward the heart. They have thin walls and one-way valves. They hold most of the blood as a reservoir.
- Capillaries are one cell thick. They are the only place where O₂, CO₂, and nutrients are swapped.
- Whether a vessel is an artery or a vein depends on the direction of flow, not on how much oxygen it carries.
Section 3Blood pressure & the pressure gradient
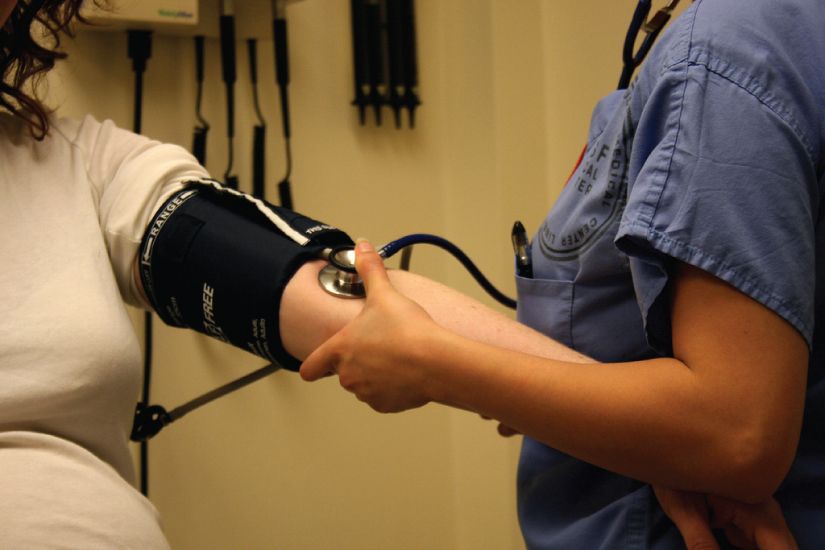
Systolic over diastolic
Blood pressure is the force of moving blood pushing on the vessel walls. It is measured in millimeters of mercury (mm Hg). In the big arteries, this pressure is not steady. It rises and falls with each heartbeat. When the ventricles squeeze and pump out blood, pressure peaks. That high point is the systolic pressure. When the ventricles relax and refill, pressure sinks to its low point. That is the diastolic pressure.
A typical healthy reading is about 120/80 mm Hg. That means systolic over diastolic. The gap between the two numbers is the pulse pressure. You find it by taking systolic minus diastolic. Here it is 40 mm Hg. It is the surge you feel as a pulse at your wrist.
Two numbers worth working out
The heart spends more of each beat resting than squeezing. So the true average pressure that pushes blood forward is not just the middle of the two numbers. This average is the mean arterial pressure (MAP). To estimate it, take the diastolic pressure and add one-third of the pulse pressure.
MAP matters to doctors because it is the pressure that actually pushes blood through your organs. If MAP falls much below about 60 mm Hg, the brain and kidneys do not get enough blood. For a reading of 120/80, MAP is about 80 + (40 ÷ 3) ≈ 93 mm Hg.
Pressure falls, and the arterioles set the toll
Follow the blood outward, and its pressure drops the whole way. That steady drop is the pressure gradient. It is exactly what keeps blood flowing, because fluid always moves from high pressure to low pressure. Pressure is high in the aorta and still pulses in the large arteries. Then it drops off a cliff across the arterioles. By the time blood reaches the venae cavae, the pressure is near zero.
Blood flow follows a simple rule: flow = pressure difference ÷ resistance. Resistance is how hard the vessel pushes back against the flow. It depends most on the vessel's radius, or half its width. Resistance goes up as the radius goes down, and it does so very fast. It changes with the fourth power of the radius (R ∝ 1 ÷ r⁴). So if you cut the radius in half, resistance goes up 16 times. If you double the radius, resistance drops to 1/16 of what it was.
Arterioles have muscular walls that can tighten or widen on command. That makes them the body's main resistance vessels. They are like faucets you can adjust. They set how much blood each organ gets. They also set your overall blood pressure.
| Location | About how much pressure | What is happening |
|---|---|---|
| Aorta / large arteries | ~120/80 mm Hg | High and pulsing. Stretchy walls spring back to smooth the flow. |
| Arterioles | Sharp drop | The biggest drop. These are the main resistance vessels. |
| Capillaries | ~35 → 17 mm Hg | Low and gentle. This protects the thin walls and drives the swap. |
| Venules / veins | Low | Little pressure is left. Other pumps take over. |
| Venae cavae | Near 0 mm Hg | Blood arrives back at the heart. |
Tap each part of the trip to see the pressure fall.
- Blood pressure is the force of blood on the vessel wall. It is written as systolic/diastolic, such as 120/80 mm Hg.
- Pulse pressure = systolic − diastolic. MAP ≈ diastolic + ⅓ of pulse pressure. MAP is what pushes blood through your organs.
- Blood flows down a pressure gradient. Flow = ΔP ÷ resistance. Resistance changes with 1 over r⁴ (R ∝ 1 ÷ r⁴), so a narrower vessel resists far more.
- Arterioles are the main resistance vessels. They are the dial for both organ blood flow and blood pressure.
Section 4Capillary exchange
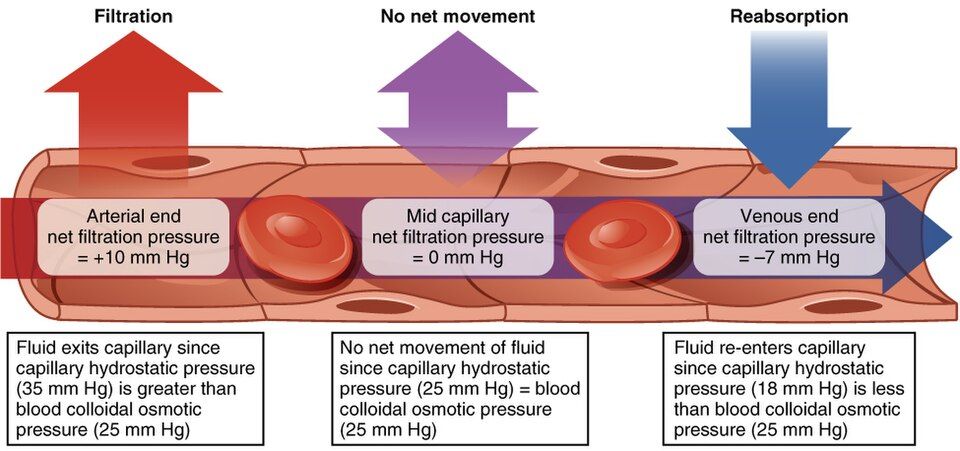
A tug-of-war between two pressures
The whole system is built to bring blood to the capillaries. This is where the key trade happens, across that wall only one cell thick. Small molecules cross easily. The trickier part is how fluid moves in and out. Two pressures pull in opposite directions to decide it.
The first is hydrostatic pressure. This is the blood pressure inside the capillary. It pushes fluid out through the wall and into the spaces in the tissue. The second is colloid osmotic pressure, also called oncotic pressure. It comes mostly from a large protein in the blood called albumin. Albumin is too big to leave the blood. Because these proteins stay behind, they pull water back in by osmosis. Fluid moves in whichever direction the stronger pressure wins.
Out at the start, back in at the end
Here is the clever part. The balance flips along the length of a capillary. At the arteriolar end, where blood comes in, hydrostatic pressure is fairly high. It is about 35 mm Hg. That easily beats the osmotic pull of about 25 mm Hg. So the overall force pushes fluid out. This is filtration. It brings water, oxygen, and nutrients to the cells.
As blood moves along the capillary, its hydrostatic pressure fades. But the osmotic pull stays the same. By the venule end, hydrostatic pressure has dropped below the osmotic pressure. Now the overall force pulls fluid back in. This is reabsorption. It picks up carbon dioxide and wastes on the way. At any point, the difference between the push and the pull is called the net filtration pressure.
The lymphatic safety net, and edema
The two sides do not quite balance. Capillaries push out a little more fluid than they take back. About 85% goes back into the blood. About 15% is left behind in the tissues. That extra fluid is not lost. The lymphatic vessels mop it up and later return it to the blood.
If any part of this system fails, fluid builds up in the tissues. The result is swelling, called edema. Three things can tip the balance this way. One is too much hydrostatic pressure, as in heart failure or a leg you stand on too long. Another is too little albumin to pull fluid back, as in liver disease, kidney disease, or not eating enough protein. The third is blocked lymph drainage.
| Force | Where it comes from | Direction |
|---|---|---|
| Hydrostatic pressure | Blood pressure inside the capillary | Pushes fluid out of the blood |
| Colloid osmotic (oncotic) pressure | Proteins in the blood, mostly albumin | Pulls fluid into the blood |
| Overall result at the arteriolar end | Hydrostatic > osmotic | Filtration (fluid leaves) |
| Overall result at the venule end | Osmotic > hydrostatic | Reabsorption (fluid comes back) |
Tap each end of the capillary to watch the tug-of-war play out.
- Fluid exchange is a contest. Hydrostatic pressure pushes fluid out, and colloid osmotic pressure pulls it in.
- Filtration wins at the arteriolar end. Reabsorption wins at the venule end.
- Capillaries push out a bit more fluid than they take back. The lymphatics return the extra.
- An imbalance causes edema. Causes include high hydrostatic pressure, low albumin, or blocked lymph vessels.
Section 5The circulatory routes
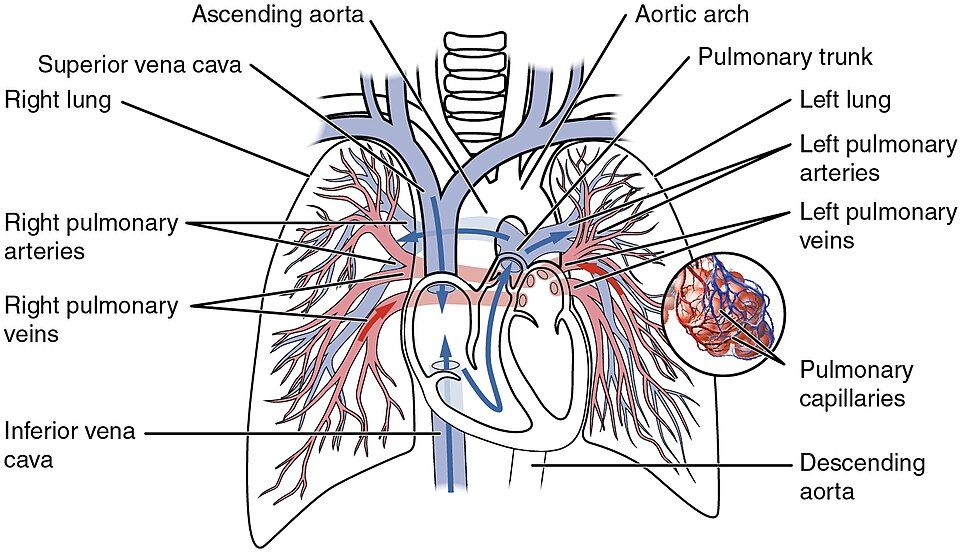
Two great circuits
Blood does not wander. It runs in set loops called circuits. The whole system is really two circuits joined at the heart. The pulmonary circuit is the short loop to the lungs. The right side of the heart pumps blood low in oxygen out through the pulmonary arteries. In the lung capillaries, the blood picks up oxygen and dumps carbon dioxide. Then the pulmonary veins carry the blood, now rich in oxygen, back to the left side of the heart.
The systemic circuit is the long loop to everything else. The left side of the heart pumps blood rich in oxygen out through the aorta. It goes to every organ, arm, and leg. Then the veins bring the blood, now low in oxygen, back to the right side of the heart to start again. The two circuits run one after the other, in series. So the same amount of blood must pass through both. The right and left sides of the heart pump in perfect step.
Portal systems: two capillary beds in a row
Most blood passes through only one bed of capillaries on its way from the heart and back. A portal system is different. Blood flows through two capillary beds, one after the other, joined by a vein. The most important example is the hepatic portal system. "Hepatic" means "of the liver."
Blood leaving the stomach and intestines is full of nutrients it just absorbed. It may also carry drugs or poisons you swallowed. This blood does not go straight back to the heart. Instead, the hepatic portal vein sends it into a second capillary bed inside the liver. The liver stores nutrients, cleans out harmful chemicals, and adjusts blood sugar. Only then does the blood move on. It joins the main flow through the hepatic veins.
Special deliveries
A few organs have their own special setups. The coronary circulation is the heart feeding itself. Its arteries branch off the aorta the moment blood leaves the heart. The cerebral circulation feeds the brain. It has a protective ring of linked arteries called the circle of Willis. If one artery into the ring is blocked, others can send blood around the gap.
Links like this between vessels are called anastomoses. They are natural detours that give a backup blood supply. Where there are few of these links, a blockage is much more dangerous. That is one reason a clot in a coronary artery so often causes a heart attack.
| Feature | Pulmonary circuit | Systemic circuit |
|---|---|---|
| Pumped by | Right side of the heart | Left side of the heart |
| Sends blood to | The lungs | The rest of the body |
| Blood leaving the heart | Low in oxygen (in the pulmonary arteries) | Rich in oxygen (in the aorta) |
| Blood coming back | Rich in oxygen (in the pulmonary veins) | Low in oxygen (in the venae cavae) |
| Main job | Load O₂ and unload CO₂ | Deliver O₂ and nutrients, and collect wastes |
Tap each route to trace where the blood goes.
- The pulmonary circuit (right heart → lungs) loads O₂. The systemic circuit (left heart → body) delivers it.
- In the pulmonary circuit, arteries carry blood low in oxygen, and veins carry blood rich in oxygen.
- The hepatic portal system sends blood from the gut through the liver before it goes back to the heart. It passes two capillary beds in a row.
- Anastomoses, like the circle of Willis, give backup routes. Where they are few, a blockage is dangerous.
Section 6Venous return
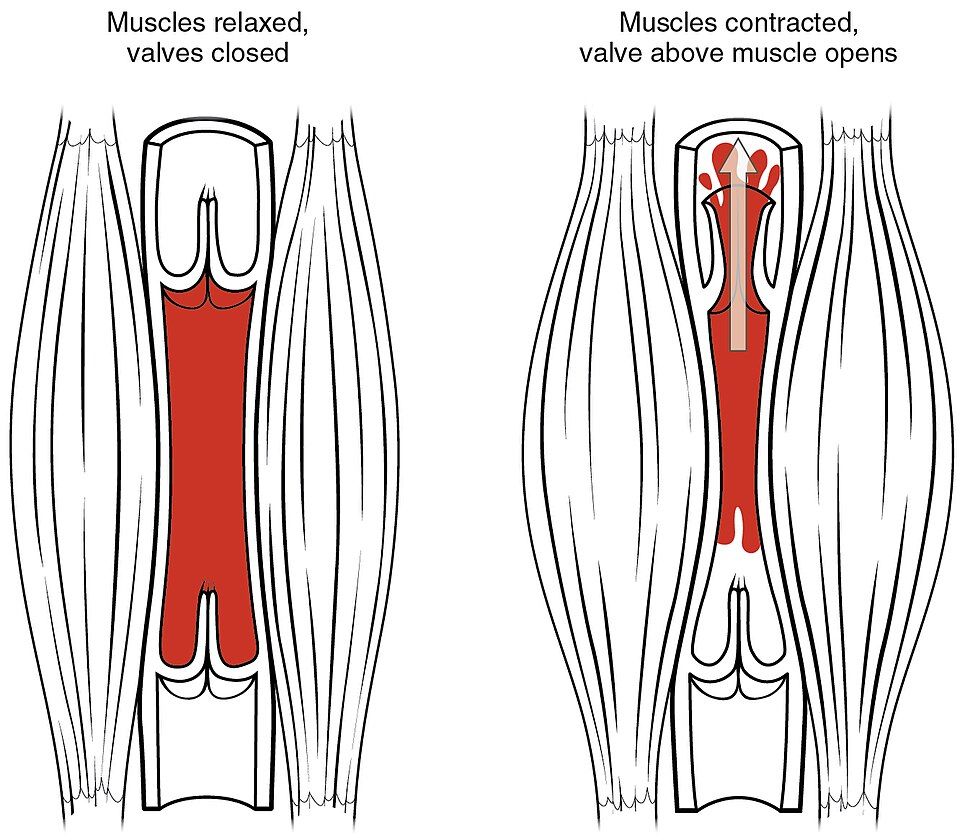
An uphill problem
By the time blood reaches the veins, it has almost no pressure left. It is often around 15 mm Hg, and it falls toward zero near the heart. Yet the blood in your feet must somehow climb more than a meter, against gravity, back to the right side of the heart.
The amount of blood coming back to the heart each minute is called venous return. Over time, it must exactly match the cardiac output. Whatever the heart pumps out, the veins must bring back. With so little pressure, the veins cannot do this alone. They rely on outside pumps and clever one-way plumbing.
The muscle pump and the valves
The main helper is the skeletal muscle pump. Deep veins run between your muscles. Every time you tighten a muscle, like with each step you take, it squeezes the veins. This forces blood along. The one-way valves make the squeeze work. When a muscle presses on a vein, the valve above opens to let blood rush upward. The valve below slams shut to stop it from falling back.
Tighten the muscle, and blood is pushed toward the heart. Relax it, and the valves hold onto the ground you gained. When you walk across a room, your calf muscles really are a second heart. They pump blood up your legs.
The breathing pump, and what fails
A second helper is the respiratory pump, or breathing pump. Each time you breathe in, your chest gets bigger and the pressure inside it drops. At the same time, pressure in your belly rises. This squeezes the belly veins. It draws blood up into the chest veins, where the pressure is low, and on toward the heart.
A third helper is venoconstriction. Here, the nervous system tightens the vein walls. This pushes stored blood back into use when the body needs more.
When these helpers fail, the results are familiar. If you stand still for a long time, the muscle pump stops. Blood pools in your legs, and you may faint. Weak or leaky valves let blood collect and stretch the veins. They become bulging varicose veins. Blood that sits still, like on a long flight or after surgery, can clot in a deep vein. This is a dangerous deep vein thrombosis.
| Helper | How it works | When it matters most |
|---|---|---|
| Skeletal muscle pump | Working muscles squeeze deep veins. Valves keep blood flowing one way. | Walking, running, and any leg movement |
| Respiratory pump | Breathing in lowers chest pressure and raises belly pressure. This draws blood upward. | Every breath, and deeper breaths during exercise |
| Venous valves | One-way flaps stop blood from flowing back between pumps | Standing up straight, against gravity |
| Venoconstriction | Nerves tighten the vein walls, pushing stored blood forward | Exercise, blood loss, and standing up |
Watch the muscle pump and valves lift blood against gravity in the activity.
- Venous return is the blood coming back to the heart. Over time, it must equal cardiac output.
- Veins have little pressure left. So they rely on the skeletal muscle pump, the respiratory pump, and one-way valves.
- Venoconstriction pushes stored blood forward during exercise or blood loss.
- When these fail, you can get fainting, varicose veins, and deep vein thrombosis. That is why moving matters.
The chapter in one breath
- Every vessel wall has three tunics (intima, media, externa) around a hollow lumen. Blood vessel disease starts in the endothelium lining.
- Arteries carry blood away under high pressure and have thick, stretchy walls. Veins bring it back under low pressure, have valves, and hold most of the blood. Capillaries are one cell thick and do all the swapping.
- Blood pressure is written as systolic/diastolic. Pulse pressure is the difference between them. MAP is what pushes blood through the organs.
- Blood flows down a pressure gradient (flow = ΔP ÷ resistance). The muscular arterioles are the main resistance vessels, because resistance changes with 1 ÷ r⁴.
- Capillary exchange is a tug-of-war. Hydrostatic pressure pushes out, and colloid osmotic pressure pulls in. Filtration happens at the arteriolar end and reabsorption at the venule end. An imbalance causes edema.
- Blood runs in a pulmonary circuit (to the lungs) and a systemic circuit (to the body). Special routes like the hepatic portal system send blood through two capillary beds.
- Venous return against gravity relies on the skeletal muscle pump, the respiratory pump, and one-way valves. When they fail, you can get fainting, varicose veins, and clots.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back any time a word trips you up.
- Arteriole
- A very small artery with a muscular wall. It controls how much blood flows into a capillary bed. It is the body's main resistance vessel.
- Artery
- A vessel that carries blood away from the heart. It is defined by direction, not by how much oxygen it carries.
- Blood pressure
- The force of moving blood pushing on the vessel wall. It is measured in millimeters of mercury (mm Hg).
- Capillary
- The smallest vessel, just one endothelial cell thick. Here oxygen, carbon dioxide, nutrients, and wastes are swapped with the tissues.
- Colloid osmotic (oncotic) pressure
- The inward pull made by proteins in the blood, mostly albumin. It draws water back into the capillary.
- Diastolic pressure
- The lower pressure in the arteries. It is measured while the ventricles relax and refill.
- Edema
- Swelling from extra fluid building up in the tissues. It happens when filtration and reabsorption in the capillaries get out of balance.
- Endothelium
- The single layer of flat cells lining the heart and all blood vessels. It is the inner surface of the tunica intima.
- Filtration
- Fluid moving out of a capillary into the tissues. It wins at the arteriolar end, where hydrostatic pressure is highest.
- Hepatic portal system
- A route that sends blood full of nutrients from the gut through the liver’s capillaries before it goes back to the heart.
- Hydrostatic pressure
- The blood pressure inside a capillary. It pushes fluid out through the wall.
- Mean arterial pressure (MAP)
- The average pressure pushing blood through the body loop. It is about the diastolic pressure plus one-third of the pulse pressure.
- Pulmonary circuit
- The loop from the right heart to the lungs and back. The blood picks up oxygen and drops off carbon dioxide.
- Pulse pressure
- The difference between systolic and diastolic pressure. It is the surge you feel as a pulse.
- Reabsorption
- Fluid moving back into a capillary from the tissues. It wins at the venule end, where osmotic pressure is higher than hydrostatic pressure.
- Resistance
- How much a vessel pushes back against blood flow. It depends mostly on the vessel’s radius. It changes with the fourth power of the radius (R ∝ 1 ÷ r⁴), so it rises steeply as the vessel narrows.
- Skeletal muscle pump
- Working muscles squeezing the deep veins. Together with one-way valves, this pushes blood back toward the heart.
- Systemic circuit
- The loop from the left heart to the whole body and back. It delivers oxygen and collects wastes.
- Systolic pressure
- The higher pressure in the arteries. It is measured while the ventricles squeeze and pump out blood.
- Tunica media
- The middle layer of a vessel, made of smooth muscle and stretchy fibers. It sets how wide the vessel is through vasoconstriction and vasodilation.
- Vein
- A vessel that carries blood toward the heart. It has thin walls and valves. It is the body’s main blood reservoir.
- Venous return
- The amount of blood coming back to the heart each minute. Over time, it must equal cardiac output.
Check yourself
The Lymphatic & Immune System
Every day, trillions of bacteria, viruses, and fungi test your borders. Most days you never notice. A layered defense force turns them away before they can take hold. This chapter follows that force, from its pipes to its sharpest weapons. First you will meet the lymphatic system. It is a quiet network that drains your tissues, carries fat from your meals, and houses your immune army. Then you will watch immunity, your body's power to fight off germs, unfold in three lines of defense. It starts with the skin on the outside. Next comes the fast fury of swelling and heat. Last come the slow, exact, lasting powers of T cells and B cells. By the end, you will know how you fight infection. You will also see why a vaccine protects you for years, but a shot of snakebite antivenom does not last.
By the end of this chapter you can
- Describe the three functions of the lymphatic system. Trace the path of lymph from a tissue back to the blood.
- Tell apart the primary and secondary lymphoid organs, and say what each one does.
- Compare innate and adaptive immunity. Place each of the body's defenses in the right line of defense.
- Explain the inflammatory response. Name its four main signs and link each sign to its cause.
- Compare the jobs of helper and cytotoxic T cells. Explain why T cells need antigen presentation.
- Describe how a B cell becomes a plasma cell. Describe the shape of an antibody and how antibodies stop a germ.
- Tell a primary immune response from a secondary one. Explain why memory cells make vaccines work.
- Sort immunity as active or passive and natural or artificial. Give a real example of each of the four types.
Section 1The lymphatic system
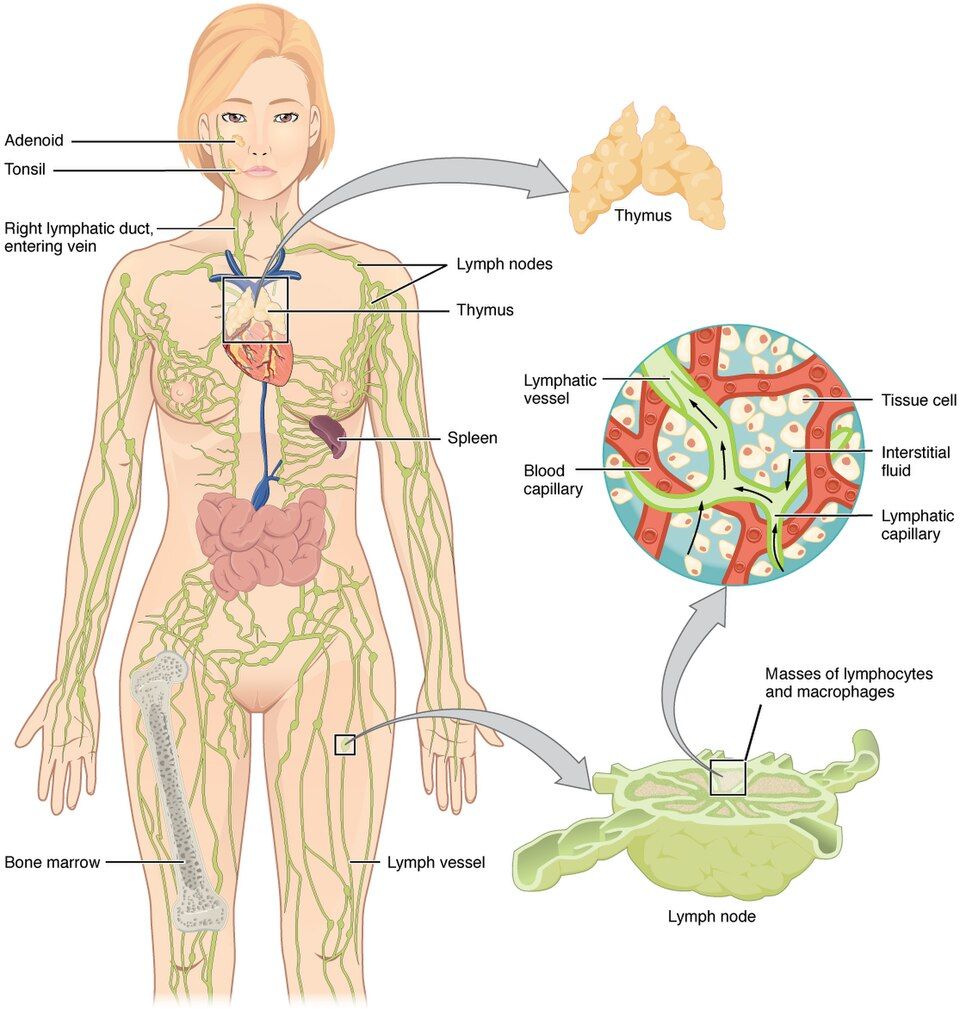
A drainage network with three jobs
Your blood vessels are not perfectly sealed. Blood pushes through the tiniest vessels, the capillaries. As it does, a little fluid squeezes out into the spaces between cells. About three liters a day more fluid leaks out than flows back in. If that fluid just pooled, you would swell up. Your blood volume would crash within hours.
The lymphatic system is the return line that stops this. It is a one-way network of vessels. It collects the leaked fluid, called interstitial fluid, which means "fluid between cells." Once that fluid is inside a lymphatic vessel, it gets a new name: lymph. The system hands the lymph back to the blood near the heart. That is its first and most basic job: fluid balance.
It also does two more jobs. The small intestine is lined with special lymph capillaries called lacteals. They soak up fats and fat-soluble vitamins from your food. These are too large to enter the blood capillaries directly. The milky, fatty lymph they carry is called chyle.
The third job matters most for this chapter. The lymphatic system is the home and highway of the immune system. It houses the lymphocytes and macrophages, the white blood cells that fight infection. It also filters lymph through checkpoints. There, those cells can catch invaders in the act.
| Function | What happens | Where |
|---|---|---|
| Fluid balance | Returns about 3 L a day of leaked fluid to the blood | Lymph capillaries all over the body |
| Fat absorption | Takes up fats and fat-soluble vitamins from food as chyle | Lacteals in the small intestine |
| Immune defense | Houses and moves lymphocytes; filters lymph for germs | Lymph nodes, spleen, and other lymphoid organs |
How lymph flows — with no pump
Lymph starts out in lymphatic capillaries. These are tiny tubes closed at one end. Their wall cells overlap like tiles and act as small one-way flaps. Fluid can push the flaps open to get in, but it cannot push its way back out. Next, lymph flows into larger lymphatic vessels. These look and act a lot like veins. They have thin walls and inner valves that stop backflow.
Along the way, the vessels pass lymph through bean-shaped lymph nodes. Then the vessels join into large lymphatic trunks. Last, they drain into two collecting ducts. The small right lymphatic duct drains the right arm and the right side of the head and chest. The large thoracic duct drains everything else. Both empty into the subclavian veins at the base of the neck. There, the fluid becomes part of the blood again.
Here is the catch. The lymphatic system has no heart of its own. It moves lymph the same way veins move blood back uphill. The skeletal muscle pump helps, as working muscles squeeze the vessels. The respiratory pump helps too, through pressure changes with each breath. Smooth muscle in the vessel walls also squeezes in a steady rhythm. The valves keep all of this flow going one way. This is why gentle movement lowers swelling. It is also why a limb that cannot move tends to puff up.
The lymphoid organs
The organs of the immune system fall into two groups, based on what they do. Primary lymphoid organs are where lymphocytes are born and grow up. One is the red bone marrow. All blood cells start there, and B lymphocytes mature there. The other is the thymus, an organ with two lobes in the chest. Here T lymphocytes finish maturing. They also learn not to attack the body's own tissues. The thymus is largest in childhood. It slowly shrinks after puberty.
Secondary lymphoid organs are where grown-up lymphocytes meet antigens and launch attacks. An antigen is any marker the immune system sees as foreign. The lymph nodes filter lymph. The spleen filters blood. Its red pulp removes worn-out red blood cells, and its white pulp checks the blood for germs. This group also includes the tonsils and the Peyer's patches in the intestine. Last is MALT (mucosa-associated lymphoid tissue). It is spread-out tissue that guards every wet surface of the body.
- The lymphatic system has three jobs. They are fluid balance (it returns leaked fluid), fat absorption (lacteals make chyle), and immune defense.
- Lymph flows one way: capillaries → vessels → nodes → ducts → subclavian veins. Muscles and breathing move it, not a pump. Valves keep it going one way.
- Primary lymphoid organs (bone marrow, thymus) make lymphocytes. Secondary organs (lymph nodes, spleen, tonsils, MALT) are where they fight.
Section 2The three lines of defense
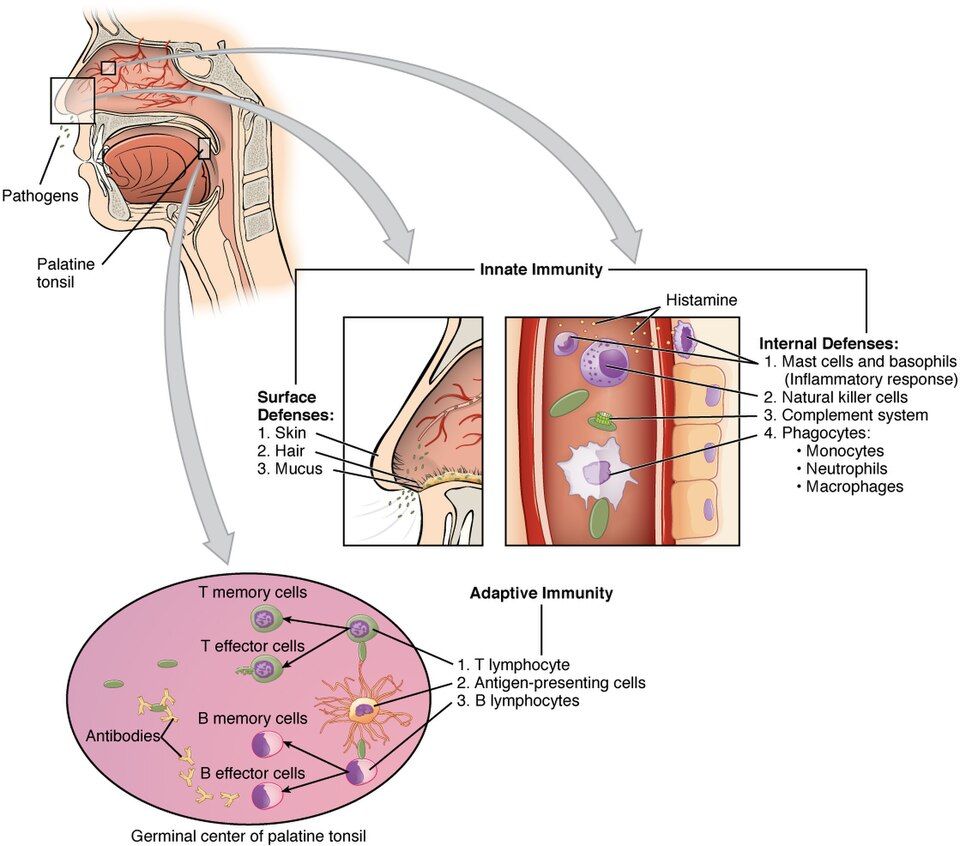
Two kinds of immunity, three layers of defense
Immunity comes in two broad styles. Innate (nonspecific) immunity is the defense you are born with. It treats every intruder the same way. It responds within minutes to hours. It keeps no memory of past attackers.
Adaptive (specific) immunity is the defense you build over your life. It aims at one certain germ with great precision. It takes days to get going the first time. Most important, it remembers. These two styles are set up as three lines of defense. Each line takes over if the one before it is broken.
The first line is the body's outer wall. It is made of the skin, the mucous membranes, and the fluids they give off. Healthy skin is a dry, tough layer that few germs can cross. Mucous membranes trap invaders in sticky mucus. Then tiny hairs called cilia sweep them out.
Chemicals back up the wall. Sweat and skin oil form a mildly sour coating called the acid mantle. Tears and saliva hold lysozyme, an enzyme that breaks down bacterial walls. Harsh stomach acid kills many germs you swallow. The normal flora, your harmless resident bacteria, crowd out dangerous ones. Nothing here aims at one germ. It is a barrier against all of them.
When the wall is breached
Sometimes a germ gets past the barrier. It may come in through a cut, a burn, or a droplet you breathe in. Then the second line meets it inside the body. This line is still innate and still nonspecific. But now the fight uses cells and chemicals.
Phagocytes are cells that swallow and digest invaders. Neutrophils and macrophages are both phagocytes. Natural killer (NK) cells destroy virus-infected cells and tumor cells on sight. The second line also includes the inflammatory response and fever. It uses germ-fighting proteins too. Interferons warn nearby cells about viruses. Complement is a chain of blood proteins. It punches holes in germs and tags them to be destroyed. The second line does not care which germ it is fighting. It only cares that something does not belong.
The third line is adaptive immunity. It is made of the lymphocytes, which are the T cells and B cells. It also includes the antibodies that B cells make. This line is slow to start, but it is extremely exact. It also leaves behind memory cells. So the next time the same germ shows up, the attack is faster and stronger. Most of this chapter is about the second and third lines.
| Line | Type | Defenses |
|---|---|---|
| First line | Innate: outer barriers | Skin, mucous membranes, and their fluids (acid, lysozyme, mucus, normal flora) |
| Second line | Innate: inside the body | Phagocytes, NK cells, inflammation, fever, interferons, complement |
| Third line | Adaptive: specific | T lymphocytes, B lymphocytes, antibodies, memory cells |
- Innate immunity is fast and general, and it has no memory. Adaptive immunity is slow at first and specific, and it remembers.
- The first line is outer barriers. The second line is inner innate defenses (phagocytes, NK cells, inflammation, fever, complement). The third line is lymphocytes and antibodies.
- Only the third line has memory. This is the basis of lifelong immunity and of vaccines.
Section 3The inflammatory response
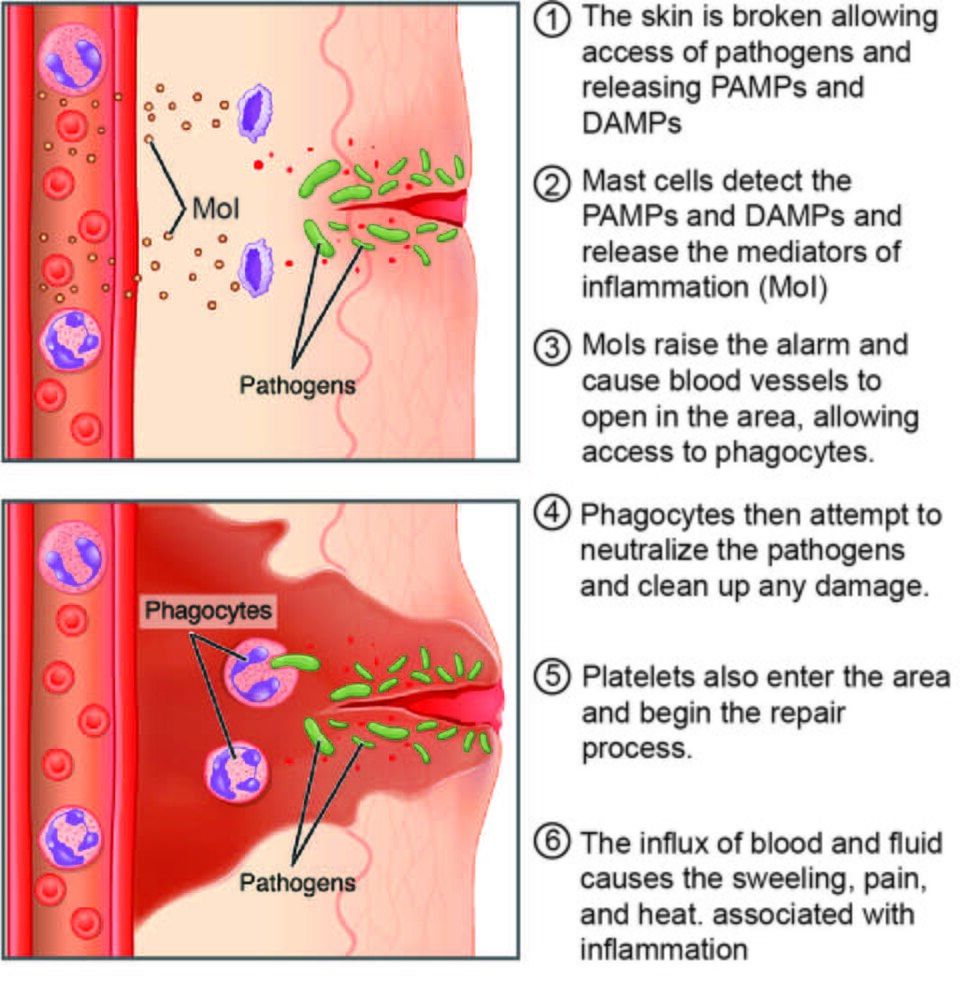
Four signs you already know
Cut your finger, and within minutes it turns red, warm, swollen, and sore. These are the four cardinal signs, or main signs. In Latin they are rubor, calor, tumor, and dolor. They are not the infection itself. They are your body's inflammatory response, a key weapon of the second line of defense.
Inflammation starts whenever tissue is hurt or invaded. It may feel like something is going wrong. In fact, it is a carefully planned rescue. It has three goals. It works to get rid of debris and germs. It tries to wall off the hurt area so infection cannot spread. And it sets the stage for repair.
What actually happens
As soon as tissue is hurt, damaged cells send out chemical alarm signals. So do nearby mast cells, which are immune cells that live in the tissue. The best-known signal is histamine. Others include prostaglandins. These chemicals do two things at once.
First, they cause vasodilation, which means the blood vessels widen. More blood rushes into the area. That causes the redness and the heat. Second, they make the capillary walls leakier. Fluid, clotting proteins, and defense cells seep out into the tissue. That causes the swelling, also called edema. The pressure of the swelling presses on nerve endings. So do the chemicals themselves. Together they cause the pain.
Now the cleanup crew arrives. Chemical signals from the injury draw phagocytes toward it. This is called chemotaxis. Neutrophils arrive first. They squeeze out of the blood through the vessel wall, a step called diapedesis. Then they swallow germs. Longer-lived macrophages come next. They eat germs and dead cells.
Sometimes a thick, creamy pus collects. It is just the leftover mess of the battle. It holds dead neutrophils, broken tissue, and destroyed germs. Once the threat is gone, the same spot becomes a workshop where repair begins.
| Cardinal sign | Latin | What causes it |
|---|---|---|
| Redness | Rubor | Vasodilation brings more blood to the area |
| Heat | Calor | More blood flow warms the tissue |
| Swelling | Tumor | Leakier capillaries let fluid seep into the tissue |
| Pain | Dolor | Swelling pressure plus alarm chemicals acting on nerve endings |
Inflammation can also spread to the whole body. This is called systemic inflammation. When infection is widespread, chemicals called pyrogens reset the brain's thermostat, the hypothalamus, to a higher setting. This causes fever. A moderate fever protects you. It slows the growth of many germs. It also speeds up the body's repair work. The bone marrow makes more white blood cells too. This is called leukocytosis. That is why a high white-cell count on a blood test hints at infection.
- The four cardinal signs are redness, heat, swelling, and pain. They come from widened blood vessels (vasodilation) and leakier capillaries.
- Histamine from mast cells starts it. Then neutrophils and then macrophages arrive by chemotaxis and diapedesis. They swallow debris and germs.
- Inflammation gets rid of threats, walls off the area, and prepares for repair. Across the whole body, it can cause helpful fever and leukocytosis.
Section 4T cells & cell-mediated immunity
Immunity that acts cell-to-cell
The third line splits into two branches. One branch is cell-mediated immunity, run by T lymphocytes. It deals with threats that hide inside your cells. These include viruses, some bacteria, and cancer cells. T cells work by direct cell-to-cell contact. They do not use antibodies.
T cells are born in the bone marrow. But they finish growing up in the thymus. (The "T" stands for thymus.) In the thymus, they are tested. Only cells that leave your own tissues alone are allowed to graduate.
Here is the key rule of T cells. They are blind to free-floating antigen. A T cell can only see an antigen when it is presented to it. That means another cell holds it up on its surface. It sits in a special display molecule called an MHC (major histocompatibility complex).
Every cell with a nucleus carries MHC class I. On it, the cell shows samples of the proteins it is making inside. A healthy cell shows its own normal proteins. But a virus-infected cell shows bits of the virus. In effect, it raises a flag that says "I am infected."
Some cells are antigen-presenting cells (APCs). These are dendritic cells, macrophages, and B cells. They also carry MHC class II. On it, they show bits of germs they have swallowed. This need for presentation is a safety switch. It keeps the powerful T-cell response from firing at random.
The T-cell lineup
Each T cell has a receptor that fits one antigen. Sometimes a T cell finds the presented antigen that matches it. That one cell is then chosen to multiply. It makes an army of identical copies, called clones. This process is called clonal selection. The clones grow into several special types:
| T cell type | Marker | Job |
|---|---|---|
| Helper T cell | CD4 | The coordinator. It reads antigen on MHC II and releases cytokines, or signal chemicals. These switch on cytotoxic T cells, B cells, and macrophages. |
| Cytotoxic T cell | CD8 | The killer. It reads antigen on MHC I and destroys infected or cancer cells with perforin and granzymes. |
| Regulatory T cell | CD4 | The brake. It calms the response and shuts it down, which prevents autoimmunity. |
| Memory T cell | — | The archive. It lasts for years and mounts a fast response if the germ comes back. |
The helper T cell is the quarterback of the whole adaptive response. It sends signals called cytokines. Without them, neither cytotoxic T cells nor B cells fully switch on.
The cytotoxic T cell is the assassin. It finds an infected cell and releases perforin, which punches a hole in the target. Then it sends in granzymes. These make the cell destroy itself, a process called apoptosis. The germ dies along with its hiding place.
- T cells mature in the thymus. They run cell-mediated immunity by direct contact, not with antibodies.
- T cells act only when antigen is presented on an MHC molecule. MHC I shows what is inside any cell. MHC II is used by APCs.
- Helper (CD4) cells coordinate the whole response. Cytotoxic (CD8) cells kill infected cells. Regulatory cells put on the brakes. Memory cells remember.
Section 5B cells & antibodies
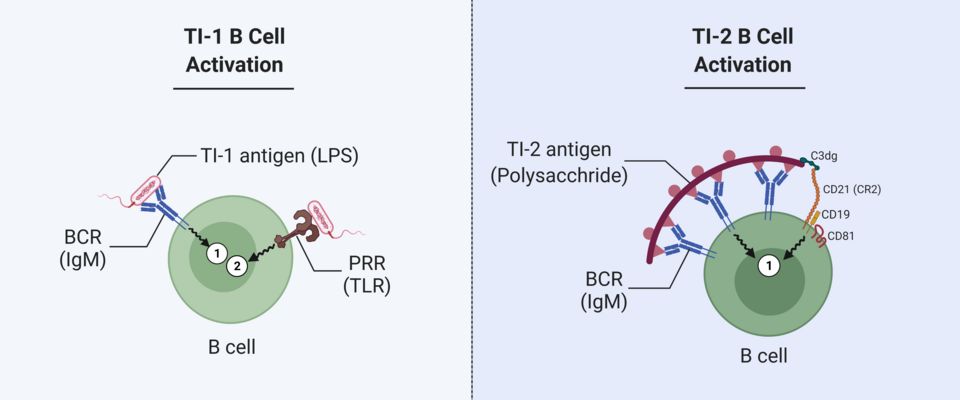
The antibody factories
The other branch of adaptive immunity is humoral immunity. The name comes from humor, an old word for body fluid. It is the job of B lymphocytes. T cells attack threats hidden inside cells. B cells fight germs floating free in the blood, lymph, and tissue fluid. They do not fight hand to hand. Instead, they make antibodies.
B cells mature in the red bone marrow. Here is a handy memory trick: B is for bone marrow. Then they wait in the lymph nodes and spleen for their matching antigen.
A B cell has a receptor on its surface. Sometimes that receptor locks onto its own antigen. Usually a helper T cell also gives it a push with cytokines. Then the B cell switches on. It goes through clonal selection and divides fast into two kinds of cells.
Most become plasma cells. These are short-lived but amazing antibody factories. Each one can pump out thousands of identical antibodies every second. The rest become memory B cells. They stay around for years. They are ready to respond at once if the same germ ever comes back.
What an antibody is and how it fights
An antibody is a Y-shaped protein. It is also called an immunoglobulin, or Ig. It is built from four chains, two heavy and two light. The two tips of the Y form the variable region. This is a custom-shaped antigen-binding site. It fits one antigen like a key fits a lock. The stem is the constant region. It sets the antibody's class.
Antibodies do not usually kill a germ outright. Instead, they tag it and disable it. They work in four ways. They neutralize toxins and viruses by covering the part that would stick to your cells. They agglutinate, or clump, many germs together so they are easy to clear away. They activate complement, which bursts the invader. And they opsonize. This means they coat the target so phagocytes can grab it more easily.
| Class | Where / when | Notable job |
|---|---|---|
| IgG | The most common kind; main antibody of the secondary response | Long-term immunity; the only class that crosses the placenta |
| IgM | The first antibody made in a new infection | Large, made of five units (a pentamer); strongly switches on complement |
| IgA | Body fluids like saliva, tears, mucus, and breast milk | Guards mucous membranes and passes immunity to a baby in milk |
| IgE | Attached to mast cells and basophils | Drives allergies and fights parasitic worms |
| IgD | On the B-cell surface | Acts as an antigen receptor that helps switch on the B cell |
Why the second exposure is different
The first time you meet a germ, you get a primary response. It is slow. It takes several days to find the right B cell. That cell must then multiply and start making antibody. At first it is mostly IgM, and then IgG. You may get sick in the meantime.
But this first meeting leaves behind memory B cells. If the same germ comes back, you get a secondary response. It is much faster and stronger. Memory cells release a flood of high-quality IgG within a day or two. They often clear the invader before you ever feel sick. That difference is the whole idea behind vaccination. A vaccine safely builds the memory now. Then the real infection meets a secondary response.
- B cells mature in bone marrow and run humoral immunity. They become plasma cells that make huge numbers of antibodies, and memory B cells that remember.
- An antibody is a Y-shaped protein with a variable region that binds antigen. It disables germs by neutralization, agglutination, complement activation, and opsonization.
- The secondary response is fast and strong because of memory cells. This is the idea behind every vaccine.
Section 6The four types of immunity
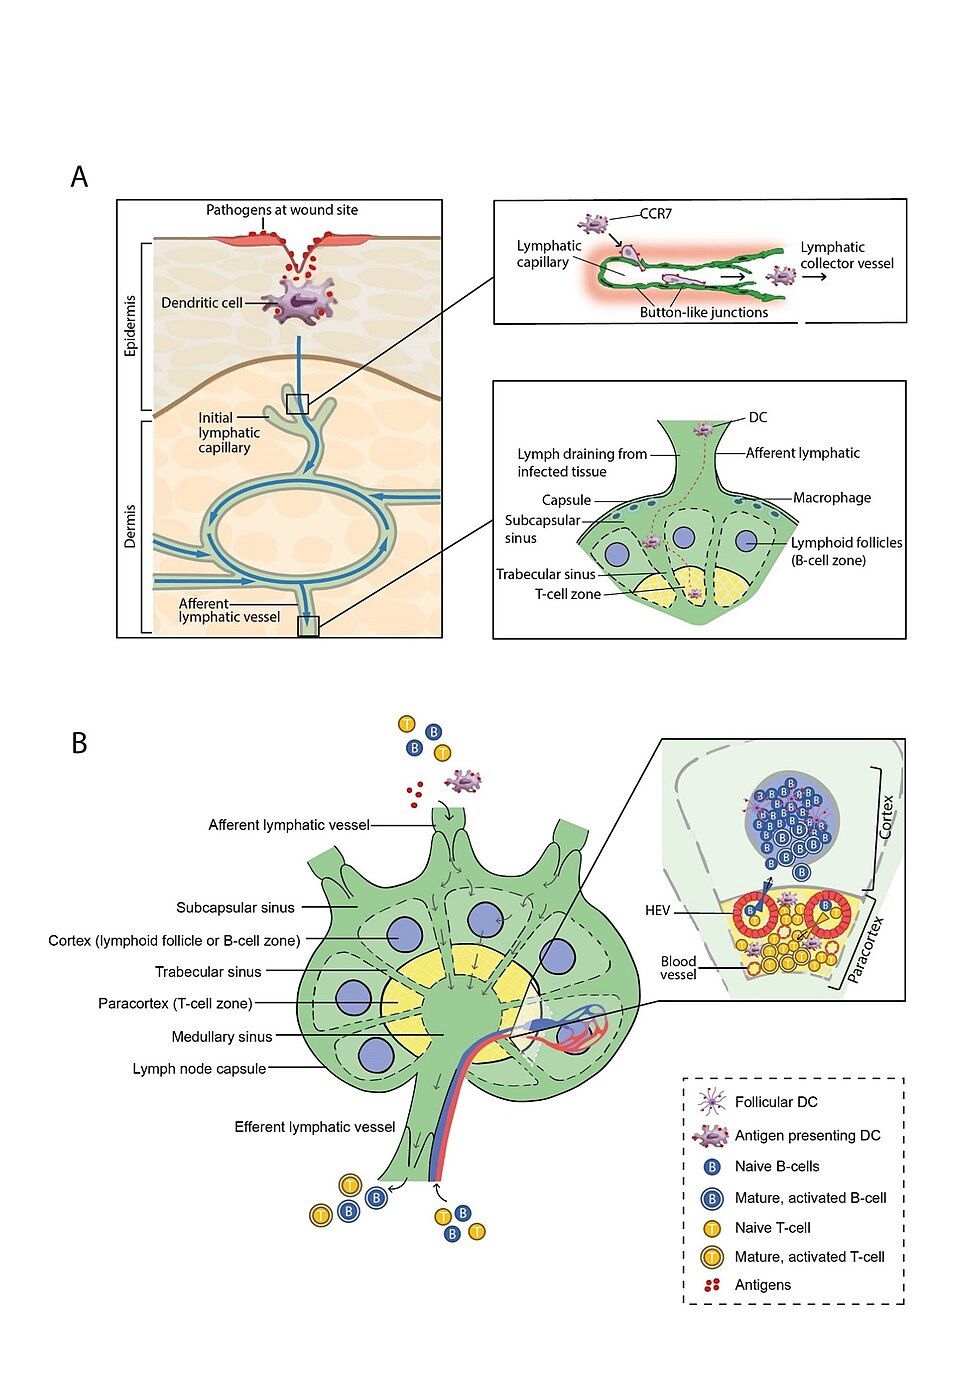
Two questions sort every kind of immunity
Acquired immunity is the kind you gain during life. You can sort it by asking two simple questions. The first question is: who made the antibodies?
If your own immune system made them, the immunity is active. It is slow to build, but it lasts a long time, because it comes with memory cells. If you got ready-made antibodies from someone else, the immunity is passive. It protects you right away, but only for a while. Those borrowed antibodies break down, and there are no memory cells to replace them.
The second question is: how did the exposure happen? If it came through everyday life, it is natural. If it came through medicine, it is artificial. Combine the two questions, and you get four types.
| Active (you make it) | Passive (you receive it) | |
|---|---|---|
| Natural | You catch an infection, get well, and make your own antibodies and memory | Antibodies pass from mother → child across the placenta (IgG) or in breast milk (IgA) |
| Artificial | A vaccine shows you a harmless form of the antigen, so you build antibodies and memory | A shot of ready-made antibodies (antiserum), such as antivenom or rabies or tetanus immunoglobulin |
When each one is used
Active immunity is the goal of prevention. You can earn it the hard way, by surviving an illness. That is naturally acquired active immunity. Or you can earn it the safe way, through a vaccine. That is artificially acquired active immunity. Either way, the payoff is the same. You gain a lasting supply of memory cells. They are ready to crush the germ if you ever meet it again. This is why childhood vaccines can protect for decades.
Passive immunity is the tool for emergencies. A fetus cannot wait to build its own defenses. So it borrows its mother's antibodies. That is naturally acquired passive immunity. Now think of a person just bitten by a venomous snake or a rabid animal. They cannot wait the weeks a vaccine would take. So they get a shot of ready-made antibodies for instant protection. That is artificially acquired passive immunity. The trade-off is always the same. Passive immunity works right now, but it fades in weeks to months. It never leaves memory behind.
- In active immunity, your body makes the antibodies. It is slow and lasting, and it has memory. In passive immunity, you get antibodies from another source. It is instant and short-lived, with no memory.
- Natural exposure happens through life. Artificial exposure happens through medicine. Together, these give four types in all.
- Vaccines give artificially acquired active immunity. Antivenom and antibodies from mother to baby are passive.
The chapter in one breath
- The lymphatic system returns leaked fluid to the blood, takes in fat from food as chyle, and houses immune cells. It moves lymph one way with no pump, using valves and muscles.
- Primary lymphoid organs (bone marrow, thymus) build lymphocytes. Secondary organs (lymph nodes, spleen, tonsils, MALT) are where they fight.
- Defense comes in three lines: outer barriers, then inner innate defenses, then specific adaptive immunity. Only the last line has memory.
- Inflammation (redness, heat, swelling, pain) is the second line at work. Widened vessels and leaky capillaries bring in phagocytes. They clear threats and start repair.
- T cells run cell-mediated immunity. They act only on presented antigen. Helper cells coordinate, and cytotoxic cells kill infected cells.
- B cells run humoral immunity. They become plasma cells that make antibodies, and memory cells that make the secondary response fast. This is the basis of vaccines.
- Immunity is active or passive and natural or artificial. Active immunity is slow and lasting, with memory. Passive immunity is instant and short-lived, without memory.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Active immunity
- Long-lasting immunity where your own body makes the antibodies and memory cells. You gain it naturally through infection or artificially through a vaccine.
- Antibody (immunoglobulin)
- A Y-shaped protein made by plasma cells. It binds one antigen and tags it to be destroyed by neutralization, agglutination, complement, or opsonization.
- Antigen
- Any molecule the immune system sees as foreign and can respond to. It is usually a piece of a germ.
- Antigen-presenting cell (APC)
- A cell that shows swallowed antigen on MHC class II to switch on helper T cells. Dendritic cells, macrophages, and B cells are APCs.
- B lymphocyte (B cell)
- A lymphocyte that matures in bone marrow and runs humoral immunity. It turns into antibody-making plasma cells and memory cells.
- Complement
- A chain of blood proteins in the innate second line. It bursts germs, boosts inflammation, and coats germs so phagocytes eat them.
- Cytotoxic T cell (CD8)
- A T lymphocyte that sees antigen on MHC I. It kills infected or cancer cells using perforin and granzymes.
- Helper T cell (CD4)
- A T lymphocyte that sees antigen on MHC II. It coordinates the adaptive response by releasing cytokines, and it is the main target of HIV.
- Humoral immunity
- Adaptive immunity carried out by antibodies in body fluids and run by B cells. It works against germs floating outside cells.
- Inflammation
- An innate response to injury or infection, marked by redness, heat, swelling, and pain. It clears threats and prepares tissue for repair.
- Innate immunity
- The general defenses you are born with, which are the first and second lines. They respond fast to any threat and keep no memory.
- Lymph
- Fluid from between the cells once it has entered a lymph vessel. It is on its way back to the blood.
- Lymph node
- A small, bean-shaped secondary lymphoid organ. It filters lymph and houses lymphocytes and macrophages.
- Lymphocyte
- A white blood cell of the lymphoid line. T cells and B cells carry out adaptive immunity, and natural killer (NK) cells act in innate immunity.
- Macrophage
- A large, long-lived phagocyte that swallows germs and debris. It can also present antigen to T cells.
- Memory cell
- A long-lived T or B cell left after an infection. It allows a fast, strong secondary response if the germ comes back.
- MHC (major histocompatibility complex)
- Surface molecules that show antigen to T cells. MHC I is on all cells with a nucleus, and MHC II is on antigen-presenting cells.
- Passive immunity
- Short-term immunity from ready-made antibodies you get from another source (placenta, breast milk, or a shot). It works at once but leaves no memory.
- Plasma cell
- A switched-on B cell that makes and releases huge numbers of antibodies, thousands per second.
- Thymus
- A primary lymphoid organ in the chest where T lymphocytes mature. There they are tested so they will not attack the body's own tissues.
- Vaccine
- A harmless form of an antigen that triggers artificially acquired active immunity. It builds antibodies and memory without causing disease.
Check yourself
The Respiratory System
Every cell in your body burns oxygen to make energy. Every one of them also makes carbon dioxide as waste. So 12 to 16 times a minute, your body trades one gas for the other. You never even have to think about it. This chapter follows a breath from the nostril to the tiny air sac where the trade happens. Then it explains the physics that pulls air in. It shows how the gases swap places and how clever chemistry carries them through the blood. Last, it covers the air volumes doctors measure to tell a healthy lung from a sick one. By the end, you will know not just how you breathe but why this whole elegant machine works the way it does.
By the end of this chapter you can
- Trace the path of air through the conducting and respiratory zones. Name each part it passes.
- Describe how the airway warms, humidifies, and filters the air you breathe in. Explain the mucociliary escalator.
- Draw the respiratory membrane. Explain why being thin and having a huge surface make it ideal for gas exchange.
- Explain the job of surfactant. Predict what happens when it is missing.
- Use Boyle’s law to explain breathing in and breathing out. Name the muscles and pressures involved in each.
- Apply partial-pressure gradients to external and internal respiration. Say which way each gas moves and why.
- Describe how oxygen and carbon dioxide are carried in the blood. Include hemoglobin and the bicarbonate system.
- Define the lung volumes and capacities. Explain how spirometry tells obstructive disease from restrictive disease.
Section 1The respiratory tract
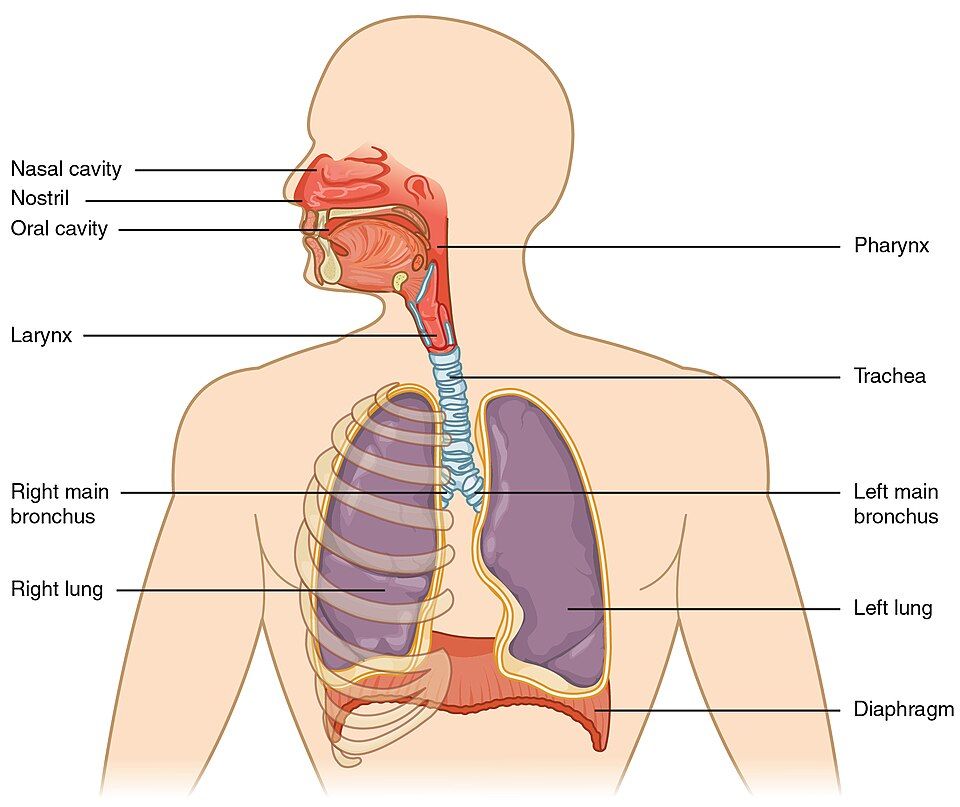
Two zones: a highway and a destination
The respiratory system has one main job. It moves oxygen in and carbon dioxide out. But it does more, too. It warms and moistens the air and filters out dirt. It gives you your sense of smell and makes your voice. It also helps control the pH of your blood, meaning how acidic it is.
To do all this, the airway is split into two working zones. The conducting zone is the plumbing. It is made of the nose, pharynx, larynx, trachea, bronchi, and bronchioles. These tubes carry air, but they never trade gases. The respiratory zone is where oxygen is actually traded for carbon dioxide. It is made of the respiratory bronchioles, alveolar ducts, and alveoli. Think of the conducting zone as the highway and the respiratory zone as the destination. Air only does its real work once it arrives.
Doctors also divide the tract by location. The upper respiratory tract is everything above the larynx. That means the nose, nasal cavity, sinuses, and pharynx. The lower respiratory tract is the larynx and everything below it. That means the trachea, bronchi, and lungs. This is why a "cold" feels so different from bronchitis or pneumonia. A cold is an upper-tract infection. The other two are lower-tract problems.
The journey of a breath
Follow one breath in. Air enters the nostrils and swirls through the nasal cavity. It passes into the pharynx, or throat, which has three parts. Next it slips through the larynx, the voice box. A flap called the epiglottis guards the larynx. It flips down when you swallow, so food goes to the esophagus and not the lungs.
Then air enters the trachea, or windpipe. C-shaped rings of cartilage hold it open at all times. The trachea splits into the right and left primary bronchi. These branch again and again, like an upside-down tree. They form smaller and smaller bronchi and then bronchioles. At last the tubes end in clusters of alveoli, the tiny air sacs. The whole branching pattern is called the bronchial tree.
| Structure | Zone | Key feature |
|---|---|---|
| Nasal cavity | Conducting | Warms, moistens, and filters air; lined with mucous membrane |
| Pharynx | Conducting | Shared path for air and food (naso-, oro-, laryngo-) |
| Larynx | Conducting | Voice box; the epiglottis guards the airway |
| Trachea | Conducting | C-shaped cartilage rings keep it open |
| Bronchi | Conducting | Branch into each lung, then into lobes and segments |
| Bronchioles | Conducting | No cartilage; smooth muscle sets how wide they are |
| Alveoli | Respiratory | Thin-walled air sacs where gas exchange happens |
The air that arrives is conditioned
By the time air reaches the alveoli, it has changed a lot. It has been warmed to body heat. It is full of water vapor, and it has been scrubbed almost clean. The nasal cavity does most of this work. Its rich blood supply gives off heat. Its mucous lining traps dust and germs.
Under that mucus sits a carpet of tiny hairs called cilia. They beat in waves toward the throat. This is the mucociliary escalator. Like a moving stairway, it sweeps trapped dirt up and out. Then you swallow it or cough it away. This tireless cleaning system protects the delicate air sacs from the outside world.
Walk the whole tract, one part at a time, in the interactive below.
- The conducting zone (nose → bronchioles) moves air. The respiratory zone (respiratory bronchioles → alveoli) trades gases.
- Air path: nose → pharynx → larynx → trachea → bronchi → bronchioles → alveoli.
- Air coming in is warmed, humidified, and filtered. The mucociliary escalator sweeps dirt up and out.
Section 2The alveolus & respiratory membrane
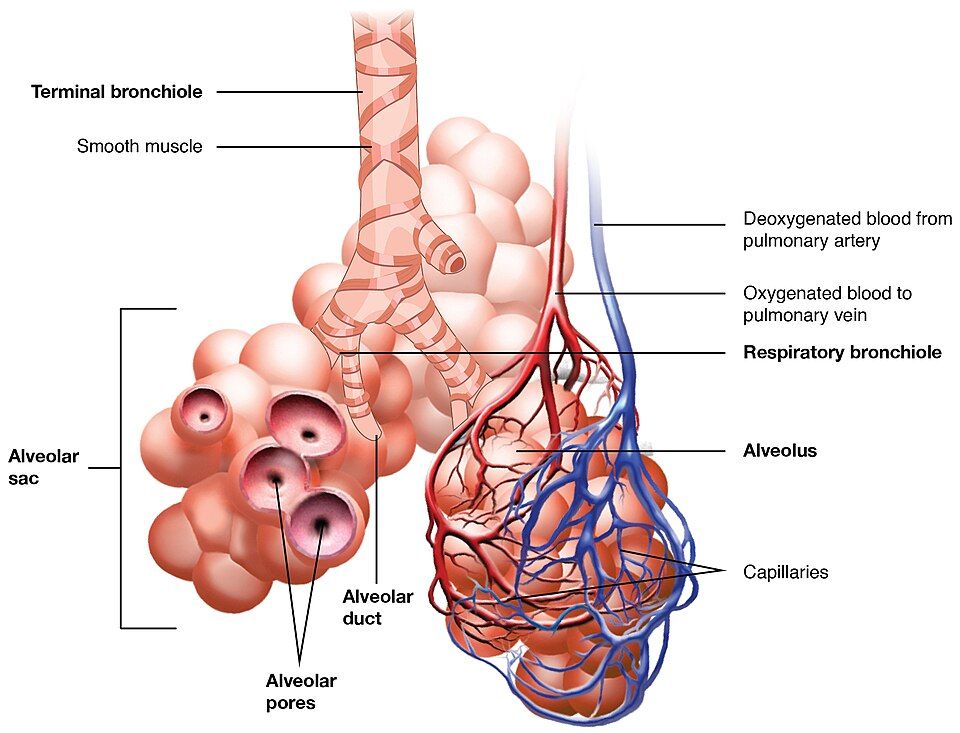
A surface the size of a room
Your lungs hold about 300 million alveoli. Each is a hollow sac, like a bubble, wrapped in a mesh of capillaries. One alone is tiny. But spread out, all their walls would cover about 70 square meters. That is about the floor of a small apartment, packed inside your chest.
This huge area is the whole point. The more surface you spread out, the more gas can cross it at once. Structure fits function. Here, the function is to move oxygen and carbon dioxide as fast and in as large amounts as possible.
The respiratory membrane: three thin layers
Gases are traded across the respiratory membrane. This is the barrier between the air in the alveoli and the blood in the capillaries. It has an important-sounding name, but it is almost nothing at all. It is about 0.5 micrometers thick, which is thinner than a soap bubble.
It has just three layers. First is the alveolar wall, a single flat layer of type I cells. Last is the capillary wall, a single flat layer of cells that line the vessel. Between them are their fused basement membranes, glued together. Oxygen crosses all three and enters the blood in a split second. Carbon dioxide crosses the other way just as fast.
| Cell / layer | What it is | Job |
|---|---|---|
| Type I alveolar cell | Simple squamous (flat) cell | Makes up most of the wall; thin enough for gases to cross |
| Type II alveolar cell | Rounded cell scattered in the wall | Makes and releases surfactant |
| Alveolar macrophage | Roaming immune cell ("dust cell") | Swallows dirt and germs that reach the sac |
| Capillary endothelium | Flat cells lining the capillary | The blood side of the respiratory membrane |
Why does being thin matter so much? Gases cross much more slowly when the barrier gets thicker. Some diseases thicken this membrane. In pulmonary edema, fluid floods it. In pulmonary fibrosis, scar tissue stiffens it. Now oxygen has farther to travel. The patient gets short of breath, even though the air and the blood are both right there.
Surfactant: keeping the sacs from collapsing
A bubble with wet walls tends to collapse. That is because the water molecules lining it pull toward each other. This pull is called surface tension. If nothing stopped it, the smallest alveoli would snap shut every time you breathed out.
To prevent this, the type II alveolar cells release surfactant. It is a soapy mix of fats and proteins that coats the inside of the sacs. It breaks up the water’s pull and lowers surface tension. This keeps the sacs open and easy to fill.
Zoom into a single sac and its capillary in the interactive below.
- About 300 million alveoli give about 70 m² of surface for gas exchange.
- The respiratory membrane is about 0.5 µm thick. It has three layers: the alveolar wall, the fused basement membranes, and the capillary wall.
- Type II cells make surfactant. It lowers surface tension and keeps alveoli from collapsing.
Section 3Breathing mechanics
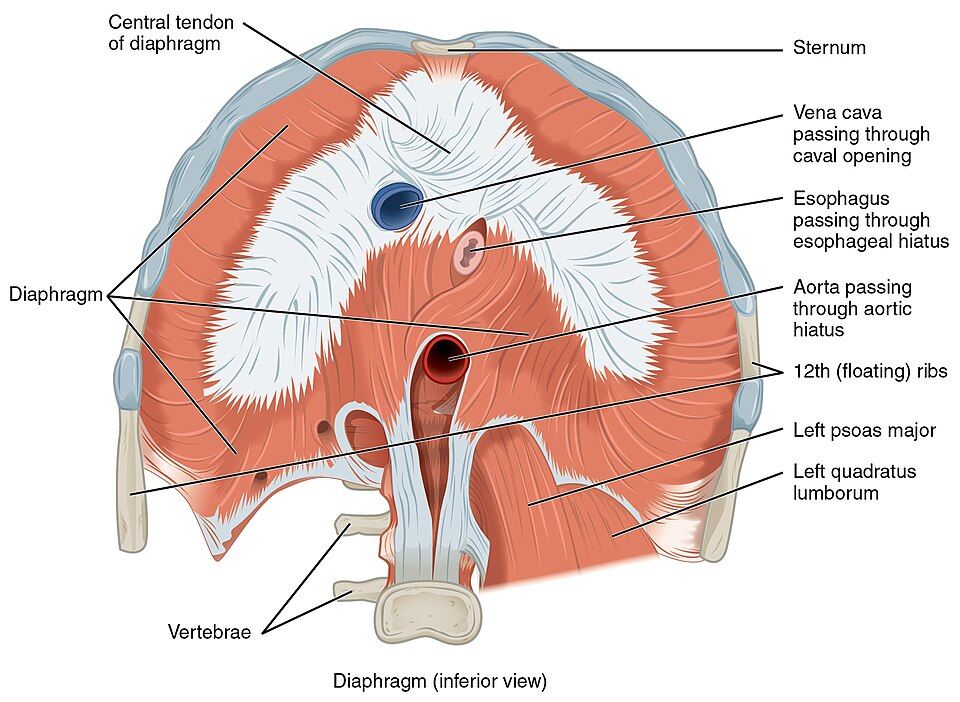
You make room, and air follows (Boyle’s law)
Here is a surprise. You do not actively suck air into your lungs. You make your chest bigger, and air rushes in on its own to fill the extra space.
The physics behind this is Boyle’s law. At a steady temperature, a gas’s pressure goes up when its volume goes down. Its pressure goes down when its volume goes up. Squeeze a container, and the pressure inside climbs. Make it bigger, and the pressure drops. Air always flows from higher pressure to lower pressure. So your muscles only have to change the size of your chest. The pressure difference moves the air for you.
Inspiration: an active pull
Breathing in, or inspiration, is active. It takes muscle work. The diaphragm is a dome of muscle under the lungs. It tightens and flattens downward. At the same time, the external intercostal muscles between the ribs lift the ribs up and out. Both actions enlarge the thoracic cavity, the space inside your chest.
By Boyle’s law, this bigger space lowers the pressure inside the lungs. This is called the intrapulmonary pressure. It drops just below the pressure of the air outside. So air flows in until the two pressures are equal.
The lungs themselves have no muscle. They follow the chest wall. A thin film of fluid holds them to it. So does the intrapleural pressure, which always stays negative. When the chest gets bigger, the lungs get bigger with it.
Expiration: mostly letting go
Breathing out, or expiration, is the opposite. At rest it is easier, because it is usually passive. The diaphragm and external intercostals just relax. The stretched lungs and chest wall recoil, or spring back, like a rubber band you let go. The chest gets smaller. The pressure inside the lungs rises above the pressure outside, so air flows out.
A quiet breath out needs no muscle work at all. Sometimes you need to force air out, like when you blow out candles, cough, or exercise hard. Only then do the internal intercostals and abdominal muscles join in to squeeze the chest.
| Inspiration | Expiration (quiet) | |
|---|---|---|
| Effort | Active (muscles tighten) | Passive (muscles relax) |
| Main muscles | Diaphragm, external intercostals | None; the lungs spring back on their own |
| Thoracic volume | Goes up | Goes down |
| Intrapulmonary pressure | Falls below the air outside | Rises above the air outside |
| Air movement | In | Out |
Watch the diaphragm change the chest’s volume and pressure in the interactive below.
- Boyle’s law: making the chest bigger lowers lung pressure, so air flows in. Making it smaller raises pressure, so air flows out.
- Inspiration is active (diaphragm + external intercostals). Quiet expiration is passive (the lungs spring back).
- A negative intrapleural pressure keeps the lungs stuck to the chest wall. Break the seal, and the lung collapses (pneumothorax).
Section 4Gas exchange
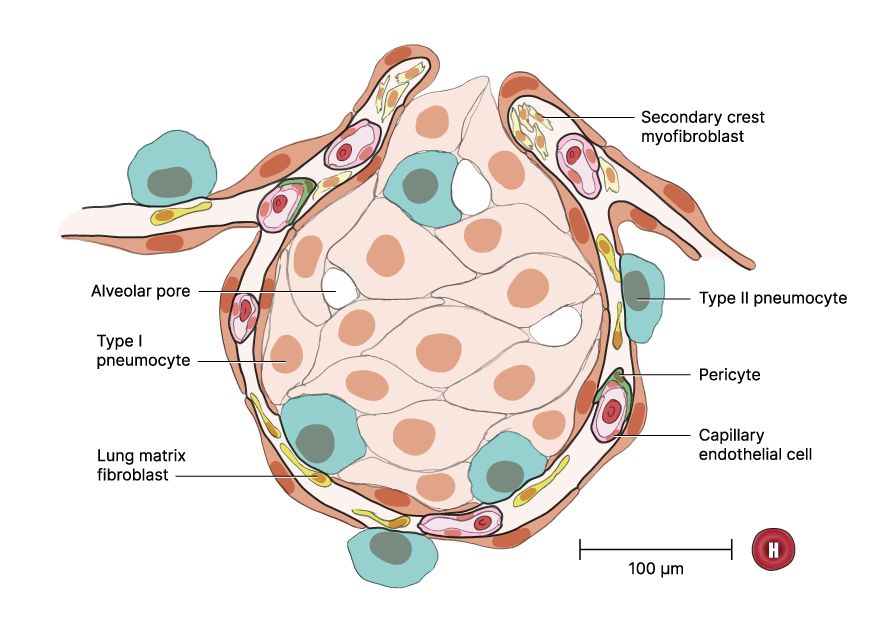
Partial pressure: each gas pushes on its own
Air is a mix of gases. In a mix, each gas adds its own share to the total pressure. That share is its partial pressure. Each gas acts as if the others were not there.
Oxygen makes up about 21% of air. So at sea level, its partial pressure is about 160 mmHg in the open air. We write this as PO₂. Inside the alveoli, the oxygen is mixed with other gases, so its PO₂ falls to about 104 mmHg.
This matters because of how gases spread, or diffuse. A gas moves from where its partial pressure is high to where it is low. It keeps moving until the two sides even out. Every gas exchange in the body is this one rule, used over and over.
External respiration: loading O₂, dumping CO₂
External respiration is the swap that happens in the lungs. It takes place between the air in the alveoli and the blood. Blood coming back from the body is low in oxygen, with a PO₂ of about 40 mmHg. It is high in carbon dioxide, with a PCO₂ of about 45 mmHg. The air in the alveoli is the reverse. It is high in oxygen (about 104 mmHg) and low in carbon dioxide (about 40 mmHg).
So oxygen moves down its gradient into the blood. Carbon dioxide moves the other way, out into the alveoli, and you breathe it out. Blood leaves the lungs fully loaded with oxygen. It has given up only a small part of its carbon dioxide. That is just enough to bring PCO₂ down from about 45 to about 40 mmHg. Most of the blood’s carbon dioxide stays with it, stored in a large bicarbonate pool. You will meet this pool in Section 5. Each trip through the lungs trims the pool. It does not empty it.
Internal respiration: the reverse at the tissues
Internal respiration is the same physics run backward, out in the body’s tissues. Cells always burn oxygen and give off carbon dioxide. So in the tissues, PO₂ is low, about 40 mmHg. PCO₂ is high, about 45 mmHg.
The blood arriving in the tissue capillaries is the opposite. So oxygen moves out of the blood into the cells. Carbon dioxide moves into the blood to be carried back to the lungs. It is the same rule in the opposite direction. The cycle repeats with every heartbeat.
| Gas | Alveoli (air) | Deoxygenated blood | Tissues |
|---|---|---|---|
| PO₂ | ~104 mmHg | ~40 mmHg | ~40 mmHg |
| PCO₂ | ~40 mmHg | ~45 mmHg | ~45 mmHg |
| Net movement | O₂ in, CO₂ out (external) | — | O₂ out, CO₂ in (internal) |
Switch between the lungs and the tissues in the interactive below.
- Each gas moves from high to low partial pressure. It stops when the pressures are equal.
- External respiration (lungs): O₂ goes into the blood, and CO₂ goes out to be breathed out.
- Internal respiration (tissues): O₂ goes out to the cells, and CO₂ goes into the blood. It is the same rule in reverse.
Section 5Gas transport in the blood
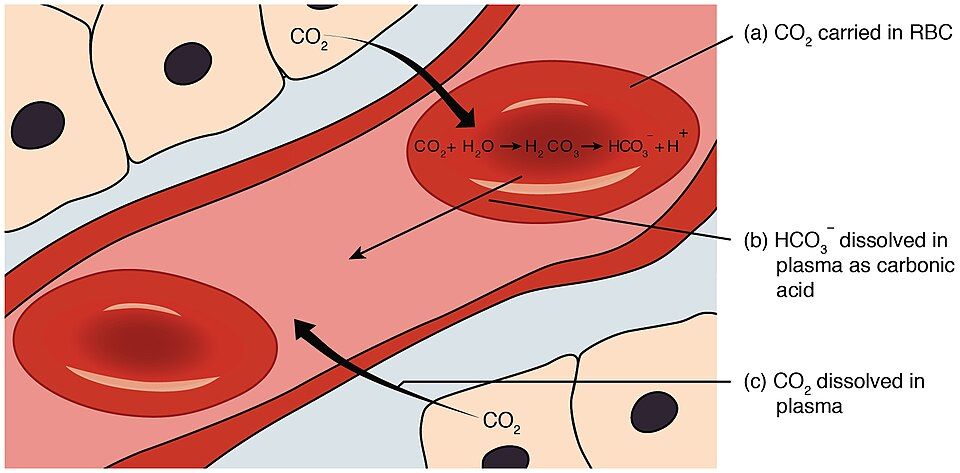
Oxygen rides on hemoglobin
Oxygen barely dissolves in water. So blood plasma alone could never carry enough to keep you alive. Only about 1.5% of the oxygen in blood is dissolved. The other 98.5% is bound to hemoglobin. This is an iron-containing protein packed inside red blood cells.
Each hemoglobin molecule can hold up to four oxygen molecules on its iron sites. Hemoglobin loaded with oxygen is called oxyhemoglobin. This is the whole reason red blood cells exist. Hemoglobin lets blood carry about seventy times more oxygen than it could without it.
The oxygen–hemoglobin dissociation curve
Hemoglobin has a wonderful talent. It grabs oxygen tightly where oxygen is plentiful, in the lungs. It lets go of oxygen where oxygen is scarce, in the tissues. You can graph how full of oxygen hemoglobin is against the PO₂ around it. The result is an S-shaped line called the oxygen–hemoglobin dissociation curve.
Even better, hemoglobin responds to what the tissue needs. A hard-working tissue is warmer and more acidic. It also has more carbon dioxide. There, hemoglobin loosens its grip. It hands off more oxygen right where it is needed most. The shift caused by low pH and high CO₂ is the Bohr effect. Warmth shifts the curve the same way, but through a separate path. This is homeostasis, or keeping things in balance, on a tiny scale. The busiest cells automatically get the most oxygen.
Carbon dioxide travels three ways
Carbon dioxide takes three different rides back to the lungs. A small share, about 7%, just dissolves in plasma. About 23% binds to hemoglobin as carbaminohemoglobin. It sits on a different spot than oxygen does.
Most of it, about 70%, is changed into bicarbonate inside red blood cells. The enzyme carbonic anhydrase joins CO₂ with water to make carbonic acid. The carbonic acid splits into a hydrogen ion and a bicarbonate ion (HCO₃⁻). The bicarbonate slips out into the plasma. At the lungs, the whole reaction runs in reverse. This frees CO₂ so you can breathe it out.
| Gas | Form in blood | Share |
|---|---|---|
| Oxygen | Bound to hemoglobin (oxyhemoglobin) | ~98.5% |
| Oxygen | Dissolved in plasma | ~1.5% |
| Carbon dioxide | As bicarbonate (HCO₃⁻) | ~70% |
| Carbon dioxide | Bound to hemoglobin (carbaminohemoglobin) | ~23% |
| Carbon dioxide | Dissolved in plasma | ~7% |
Switch between oxygen and carbon dioxide transport in the interactive below.
- Oxygen is carried mostly on hemoglobin (about 98.5%). Each molecule binds four O₂.
- In the Bohr effect, low pH plus high CO₂ make hemoglobin release more oxygen in hard-working tissues. The warmth of those tissues shifts the curve the same way, by a separate path.
- Carbon dioxide travels as bicarbonate (about 70%), on hemoglobin (about 23%), and dissolved (about 7%). This links breathing to blood pH.
Section 6Lung volumes & capacities
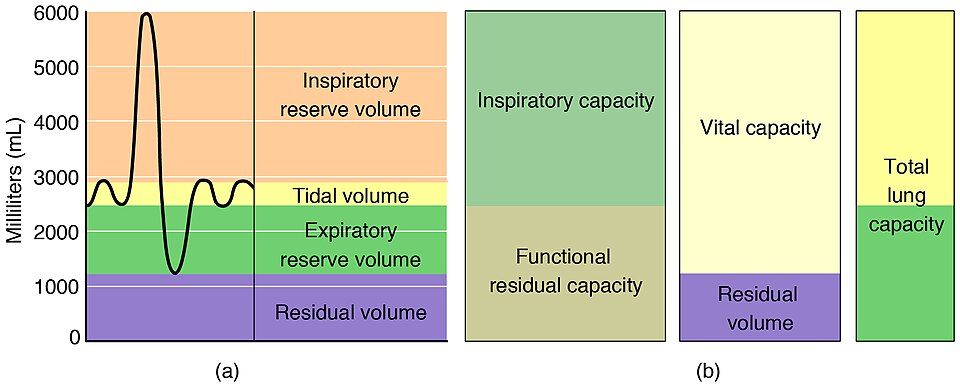
Four volumes
A spirometer is a device that records how much air you move as you breathe. Its tracing is split into four basic volumes. Tidal volume (TV) is the small amount you move in a normal, quiet breath. It is about 500 mL.
Inspiratory reserve volume (IRV, about 3000 mL) is the extra air you can pull in with your deepest breath. Expiratory reserve volume (ERV, about 1100 mL) is the extra you can force out after a normal breath out. Last, residual volume (RV, about 1200 mL) is the air that always stays behind. You can never fully empty your lungs. That leftover air keeps the alveoli from collapsing between breaths.
Four capacities (volumes added together)
A capacity is just two or more volumes added together. Each one answers a useful question. Vital capacity (VC) is the total you can move from your deepest breath in to your hardest breath out. It equals TV + IRV + ERV, about 4600 mL. It is the number doctors care about most.
Total lung capacity (TLC) adds the residual volume back in. It is everything the lungs can hold, about 5800 mL. Inspiratory capacity (IC = TV + IRV) is all you can breathe in from rest. Functional residual capacity (FRC = ERV + RV) is what is left after a normal breath out.
| Measure | Definition | Typical value |
|---|---|---|
| Tidal volume (TV) | Air in one normal, quiet breath | ~500 mL |
| Inspiratory reserve (IRV) | Extra air you can force in | ~3000 mL |
| Expiratory reserve (ERV) | Extra air you can force out | ~1100 mL |
| Residual volume (RV) | Air that cannot be breathed out | ~1200 mL |
| Vital capacity (VC) | TV + IRV + ERV | ~4600 mL |
| Total lung capacity (TLC) | VC + RV (everything) | ~5800 mL |
Dead space & what spirometry reveals
Not all the air you breathe in reaches the alveoli. About 150 mL stays in the conducting airways, where no gas exchange happens. This is the anatomical dead space. So of a 500 mL breath, only about 350 mL is fresh air that does real work.
Spirometry becomes truly powerful when it is timed. The FEV₁/FVC ratio tells how much of your vital capacity you can blow out in the first second. This ratio separates the two big families of lung disease. In obstructive disease, like asthma and COPD, the airways are narrow. Air comes out slowly, so the ratio drops. In restrictive disease, like fibrosis, the lungs are stiff and small. The volumes shrink, but the air that is there comes out quickly. So the ratio stays normal or high.
Trace each volume on a spirometer in the interactive below.
- There are four volumes: tidal, inspiratory reserve, expiratory reserve, and residual. Capacities are volumes added together (VC, TLC, IC, FRC).
- Residual volume always stays behind and keeps alveoli open. A simple spirometer cannot measure it.
- A low FEV₁/FVC ratio points to obstructive disease. Small volumes with a normal ratio point to restrictive disease.
The chapter in one breath
- The airway has a conducting zone that moves and conditions air. It also has a respiratory zone where gases are actually traded. Air travels nose → pharynx → larynx → trachea → bronchi → bronchioles → alveoli.
- Gases are traded across the paper-thin respiratory membrane of about 300 million alveoli. Surfactant from type II cells keeps the sacs from collapsing.
- Breathing follows Boyle’s law. Breathing in is active: the diaphragm and external intercostals make the chest bigger. A quiet breath out is passive: the lungs spring back.
- Gases move from high to low partial pressure. O₂ goes in and CO₂ goes out at the lungs (external respiration). The reverse happens at the tissues (internal respiration).
- Oxygen is carried mostly on hemoglobin. Carbon dioxide travels mostly as bicarbonate, which ties breathing to blood pH.
- The lung’s volumes and capacities measure how much air you move. A low FEV₁/FVC ratio points to obstructive disease. Small volumes point to restrictive disease.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Alveolus
- A tiny, thin-walled air sac (plural: alveoli). Here oxygen and carbon dioxide are traded with the blood.
- Bicarbonate (HCO₃⁻)
- The ion that most carbon dioxide is turned into so it can travel in the blood. It also plays a key part in the body’s acid–base balance.
- Bohr effect
- Hemoglobin holds oxygen less tightly when H⁺ rises (lower pH) and carbon dioxide rises. So it releases more oxygen in active tissue. Warmth shifts the curve the same way, but by a separate path, not by the Bohr effect.
- Boyle’s law
- At a steady temperature, a gas’s pressure goes up as its volume goes down, and the reverse. It explains how the chest moves air.
- Bronchiole
- A small airway of the conducting zone with no cartilage. Smooth muscle sets how wide it is.
- Conducting zone
- The airways, from the nose through the bronchioles. They carry, warm, moisten, and filter air, but they do not trade gases.
- Dead space (anatomical)
- The roughly 150 mL of air breathed in that stays in the conducting airways. It never reaches the alveoli for exchange.
- Diaphragm
- The dome-shaped muscle under the lungs. When it tightens, it is the main force behind breathing in.
- Expiration
- Breathing out. It is passive at rest, as the lungs spring back, and active when forced.
- External respiration
- Gas exchange in the lungs, between the air in the alveoli and the blood. Oxygen goes in, and carbon dioxide comes out.
- Hemoglobin
- The iron-containing protein in red blood cells. It binds and carries up to four oxygen molecules.
- Inspiration
- Breathing in. It is an active process in which the diaphragm and external intercostals make the chest bigger.
- Internal respiration
- Gas exchange in the tissues, between blood and cells. Oxygen goes out to the cells, and carbon dioxide goes into the blood.
- Intrapleural pressure
- The pressure in the fluid-filled space between the lung and the chest wall. It stays negative, so the lung stays filled against the wall.
- Partial pressure
- The share of the total pressure that comes from one gas in a mix. Gases move from high to low partial pressure.
- Residual volume
- The air (about 1200 mL) left in the lungs after your hardest breath out. You cannot push it out by choice.
- Respiratory membrane
- The barrier, about 0.5 µm thick, that gases cross. It is made of the alveolar wall, the fused basement membranes, and the capillary wall.
- Spirometry
- A test that measures how much air a person breathes and how fast. It is used to diagnose lung disease.
- Surfactant
- A mix of fats and proteins made by type II alveolar cells. It lowers surface tension and keeps alveoli from collapsing.
- Tidal volume
- The amount of air (about 500 mL) moved in one normal, quiet breath.
- Vital capacity
- The most air a person can breathe out after their deepest breath in. It equals the tidal, inspiratory reserve, and expiratory reserve volumes added together.
Check yourself
The Digestive System
Here is a strange idea. Every meal you have ever eaten stayed outside your body until this system took it apart. The digestive system is a long tube made of muscle. It runs roughly nine meters from mouth to anus. It takes in food and breaks it down, both by crushing and by chemistry. The goal is to make pieces small enough to cross a cell's outer skin, its membrane. Then it takes those pieces into the blood and gets rid of the leftovers. In this chapter we will walk the tube from one end to the other. You will watch the muscle in its walls push and mix. You will step inside the acid bath of the stomach and the soft, velvet lining of the small intestine. You will meet the helper glands that pour in their juices. Last, you will follow a bite of food down to the tiny building blocks your cells can burn. By the end, you should be able to trace a sandwich from your lips to your blood. You should also be able to name what happens at every stop.
By the end of this chapter you can
- Tell the alimentary canal apart from the accessory organs, and list the organs in each group.
- Name the six essential digestive processes and the four layers of the gut wall.
- Compare peristalsis and segmentation, and explain what each one does.
- Describe the regions of the stomach and the gastric gland cells, plus what each cell makes.
- Explain how the small intestine builds up its surface area. Explain how one villus takes in nutrients.
- State what the salivary glands, liver, gallbladder, and pancreas add, and how their juices reach the gut.
- Follow the chemical digestion of carbs, proteins, fats, and nucleic acids down to the small pieces the body takes in.
- Link common problems to the body parts that explain them. These include ulcers, celiac disease, gallstones, and lactose intolerance.
Section 1The digestive tract
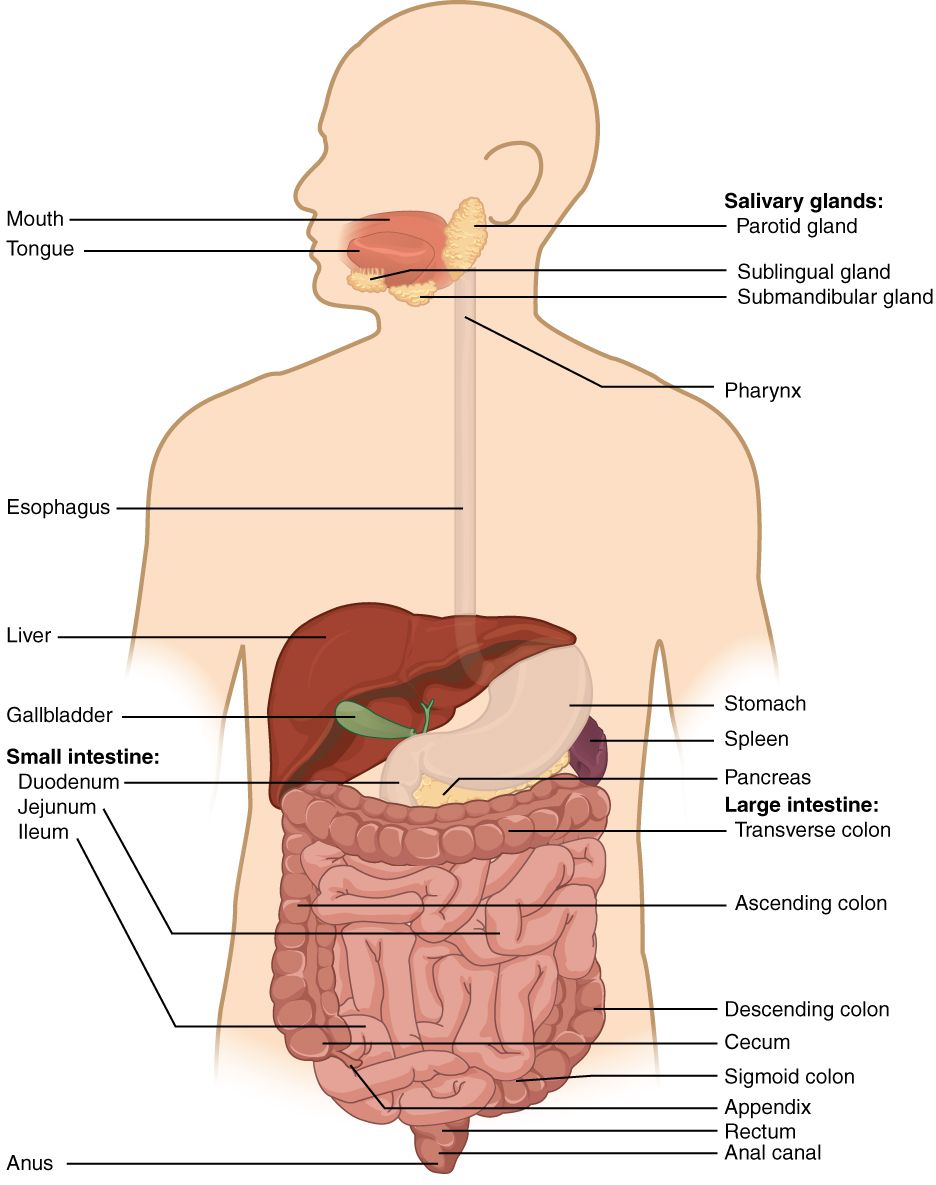
One long tube, two kinds of organs
The digestive system has two groups of organs. They are easy to keep straight once you see the idea. The first group is the alimentary canal, also called the gastrointestinal (GI) tract. It is the one long muscle tube that food actually passes through. In order, it is the mouth, pharynx (throat), esophagus, stomach, small intestine, large intestine, and anus. Laid out end to end in a body after death, it runs about nine meters. In a living person, muscle tension keeps it quite a bit shorter.
The second group is the accessory organs, the helpers. They are the teeth, tongue, salivary glands, liver, gallbladder, and pancreas. Food never passes through them. Instead, some help by physical work, like the teeth and tongue. Others pour juices into the tube through small pipes called ducts. Keep "tube" and "helpers" separate in your mind. It is the first big idea of this whole chapter.
Six jobs, start to finish
Everything this system does fits into six essential processes. It helps to name them in order. Ingestion is taking food in through the mouth. Propulsion moves food along the tube. First you swallow on purpose, and then waves of muscle called peristalsis take over on their own. Mechanical digestion breaks food into smaller bits by physical force. Chewing, stomach churning, and mixing in the intestine all count. This gives enzymes more surface to work on.
Chemical digestion uses enzymes, which are helper proteins, to split big molecules into small ones. Absorption moves the small molecules across the gut wall into blood or lymph. Last, defecation gets rid of what cannot be taken in. A seventh word, secretion, runs through all six steps. It means releasing useful fluids. Water, acid, enzymes, bile, and mucus are all released along the way to make digestion work.
The wall has four layers
From the esophagus to the anus, the tube is built from the same four layers. They wrap around each other like the layers of an onion. Once you know them, you can read any part of the tract. The innermost layer is the mucosa. It is the moist lining that makes juices and takes in food. It faces the hollow center of the tube, called the lumen. Around it is the submucosa. This is a layer of connective tissue full of blood vessels, lymph vessels, and a web of nerves.
Next comes the muscularis externa, the muscle layer. It is usually two sheets of smooth muscle. The inner sheet runs in rings, and the outer sheet runs along the length of the tube. When these muscles squeeze, they push and mix the food. The outermost layer is the serosa, also called the visceral peritoneum. It covers organs that hang free in the belly. Where an organ is fixed to the body wall, like the esophagus, the outer layer is an adventitia of tough, fiber-rich tissue instead.
| Layer | What it is | Main job |
|---|---|---|
| Mucosa | Lining cells, a thin layer of connective tissue, and a thin strip of muscle, facing the lumen | Makes juices, takes in food, and guards the surface |
| Submucosa | Loose connective tissue with blood vessels, lymph vessels, glands, and nerves | Feeds the mucosa; holds the submucosal nerve web |
| Muscularis externa | Inner circular and outer longitudinal smooth muscle | Peristalsis and segmentation; forms sphincters |
| Serosa / Adventitia | Outer visceral peritoneum, or a tough layer that anchors the organ | Wraps and hangs the organ, or ties it in place |
Tap each organ in the interactive below. You will see where it sits and what job it does.
- The alimentary canal is the tube food passes through. The accessory organs help from the side. They are the teeth, tongue, salivary glands, liver, gallbladder, and pancreas.
- The six processes are ingestion → propulsion → mechanical digestion → chemical digestion → absorption → defecation. Secretion happens all along the way.
- The gut wall has four layers: mucosa, submucosa, muscularis externa, serosa/adventitia.
- The lumen is really outside the body. Food only truly enters you once it crosses the wall.
Section 2Moving and mixing
Two muscle layers, two kinds of motion
The smooth muscle in the gut wall makes two very different movements. Each one solves a different problem. When the muscle moves food forward, that is propulsion. When it mixes food in one place, that is mechanical digestion. The inner ring muscle makes the tube narrower when it squeezes. The outer lengthwise muscle makes the tube shorter. By timing these two sheets, the gut can push a lump of food along. Or it can churn it like a washing machine. Almost all of this happens without you thinking about it. The gut's own nerve network runs the show, and the brain only adds background signals.
Peristalsis: the wave that pushes
Peristalsis is a wave of squeezing that travels along the tube and pushes food forward. Just behind the lump of food, called a bolus, the ring muscle squeezes. Just ahead of it, the muscle relaxes to make room. So the food gets pushed along, the way you squeeze toothpaste up the tube. Peristalsis carries a swallowed bite down the esophagus in a few seconds. It is strong enough to work against gravity. You can swallow while lying down, or even upside down. The food still reaches your stomach, because the muscle is doing the work, not gravity.
Segmentation: mixing in place
Segmentation is a mixing rhythm that does not move food forward much. It happens mostly in the small intestine. Rings of muscle squeeze here and there, chopping the contents into sections. Then they relax while nearby rings squeeze. This sloshes the chyme, the soupy food mix, back and forth. It does two useful things at once. It blends food well with enzymes. It also presses the mix against the wall again and again, so nutrients can be taken in.
Only when most of the food has been taken in does segmentation give way to peristalsis. Then peristalsis moves the leftovers on. Special pacemaker cells set the beat for both motions. They are called the interstitial cells of Cajal. They send out slow electrical waves that the muscle follows.
| Feature | Peristalsis | Segmentation |
|---|---|---|
| What it does overall | Moves food forward along the tube | Mixes food in place, with little forward motion |
| Muscle action | Squeeze behind, relax ahead. A wave that travels. | Rings that squeeze in place, taking turns |
| Main location | Whole tract: esophagus, stomach, intestines | Small intestine (and colon) |
| Main purpose | Propulsion | Mixing food and pressing it against the wall to be taken in |
Switch between the two motions in the interactive. Watch how each one moves the food.
- Peristalsis pushes food along. Muscle squeezes behind the bolus and relaxes ahead, so it moves forward, even against gravity.
- Segmentation mixes chyme in place and presses it against the wall so it can be taken in. It is the main motion in the small intestine.
- Interstitial cells of Cajal set the beat for both motions.
- Thick rings of muscle form sphincters. They act as one-way valves between parts of the tube.
Section 3The stomach
A muscular bag with regions and folds
The stomach is a J-shaped bulge in the tube. It is a storage tank, a mixing bowl, and a chemical lab all at once. It has four regions. The cardia is where the esophagus enters. The fundus is the dome that bulges up beside it. The body is the large middle part. The pylorus is a funnel at the end. It narrows to the pyloric sphincter, which guards the exit into the small intestine.
When the stomach is empty, its lining lies in deep folds called rugae. These folds flatten out as the stomach fills. That lets it stretch to hold a liter or more. The stomach also has a third muscle layer that the rest of the tube lacks. This inner oblique layer runs at a slant under the other two. It lets the stomach churn in many directions at once. The churning grinds a meal into a creamy, acidic soup called chyme.
The gastric glands and their cells
The stomach lining is dotted with millions of tiny holes called gastric pits. They lead down into gastric glands. Different cells line these glands, and each one makes its own product. Surface mucous cells line the inside of the stomach and the pits. They make a thick mucus that is rich in bicarbonate, a base. This mucus shields the lining from acid. Deeper down, in the neck of each gland, are mucous neck cells. They make a different mucus. It is thinner and a little acidic, and it is not the protective coat.
Parietal cells are the hard workers. They pump out hydrochloric acid (HCl). Just as important, they also make intrinsic factor. Chief cells release pepsinogen. This is the inactive form of pepsin, an enzyme that splits protein. Chief cells also make a little gastric lipase, which works on fat. Mixed in among them are enteroendocrine cells, which make hormones. One kind, the G cells, releases the hormone gastrin into the blood. Gastrin tells the other cells to make their juices. Together, these cells make two to three liters of stomach juice a day.
| Cell | Makes | What it does |
|---|---|---|
| Surface mucous cell | Thick mucus rich in bicarbonate (a base) | Coats the lining and protects it from acid and pepsin |
| Mucous neck cell | Thin, acidic mucus | Makes the gland neck slippery. It is not the protective coat. |
| Parietal cell | HCl and intrinsic factor | Makes chyme acidic, turns on pepsin, and kills germs. Intrinsic factor is needed to take in vitamin B₁₂. |
| Chief cell | Pepsinogen, gastric lipase | Pepsinogen turns into pepsin in acid and breaks down protein |
| Enteroendocrine (G) cell | Gastrin (a hormone) | Tells the stomach to make more juice and to churn |
Making acid, and surviving it
Parietal cells drive the stomach's pH down to about 1.5 to 2. That is very acidic. It is strong enough to unfold proteins. It also turns pepsinogen into active pepsin. Acid release is switched on in three phases that overlap. The cephalic phase starts in the brain, when you see, smell, or think about food. The gastric phase starts when the stomach stretches and meets protein. It is the largest phase. In the intestinal phase, chyme moves on. This phase first boosts acid release for a short time, then calms it down.
So why doesn't the stomach digest itself? Its mucosal barrier protects it in three ways. First, there is a thick coat of mucus full of bicarbonate. Second, tight seals called tight junctions join the lining cells to each other. Third, the surface cells are replaced every few days. So any damaged patch is quickly covered again.
Switch between the stomach's regions and its gland cells in the interactive.
- Regions: cardia, fundus, body, pylorus. Rugae let it stretch. A third, slanted oblique muscle layer churns food into chyme.
- Gland cells: parietal (HCl + intrinsic factor), chief (pepsinogen), mucous neck (mucus), G cells (gastrin).
- A pH of about 1.5–2 turns on pepsin. Acid release runs in cephalic, gastric, and intestinal phases.
- The mucosal barrier keeps the stomach from digesting itself. It uses bicarbonate mucus, tight junctions, and fast cell replacement.
Section 4The small intestine
Three segments, one enormous surface
The small intestine is where almost all chemical digestion finishes. It is also where almost all food is taken in. So nearly everything about it is built to give chyme as much surface as possible. It has three parts, in order. The duodenum is short and curved. It gets chyme from the stomach, plus bile and pancreatic juice. The jejunum is long, and it is the main place where food is taken in. The ileum finishes the job. It empties into the large intestine at the ileocecal valve.
The small intestine is only about an inch wide. But it is by far the longest part of the tube. It uses three levels of folding to turn that length into a huge surface. The surface is roughly the size of a tennis court, around 200 square meters.
Three amplifiers of surface area
The extra surface comes in three levels, each one folding the level above it. First, the wall itself has lasting ridges called circular folds (plicae circulares). They make chyme spiral slowly along, so it has more time and contact. Second, every fold is covered with millions of tiny fingers called villi. Each one sticks out about a millimeter. Third, each cell on a villus has thousands of tiny bumps on its top edge, called microvilli. They are packed so tight they look furry under a microscope. This fuzzy edge is called the brush border. Together, these three levels make the tube's surface more than 500 times bigger than a flat tube.
| Amplifier | What it is | Rough effect |
|---|---|---|
| Circular folds | Lasting ridges of the whole wall | Slow the chyme and make it spiral; about 3× the area |
| Villi | Tiny fingers of lining, about 1 mm tall | Cover every fold; about 10× the area |
| Microvilli (brush border) | Tiny bumps on the top edge of each cell | Huge final surface; about 20× the area; hold digestive enzymes |
Inside a single villus
Zoom in on one villus. You will find the whole food-taking machine in miniature. Its outer layer is a sheet of absorptive epithelial cells (enterocytes). These cells carry the brush border. Enzymes on the brush border finish breaking down sugars and small protein bits right where they are taken in. Inside the villus is a web of capillaries, the tiniest blood vessels. They carry sugars and amino acids off to the liver.
In the center is one lymph vessel with a closed end, called a lacteal. It takes in digested fats. Between the villi are deep pits called intestinal crypts. They keep making new cells to replace the ones worn off the tips. That is why the lining renews itself every few days.
In the interactive, tap each level of folding. Then explore the parts of one villus.
- The parts in order are duodenum → jejunum → ileum. Most digestion and absorption happen here.
- Three levels add surface: circular folds → villi → microvilli (brush border). Together they give about 200 m².
- A villus holds a capillary network (for sugars and amino acids) and a lacteal (for fats). New cells come from the crypts.
- When the villi are destroyed, as in celiac disease, the body can't take in food well.
Section 5The accessory organs
Glands that pour in from the side
Food never passes through the helper glands. Instead, they make juices and send them into the tube through ducts. Most juices go into the mouth or the duodenum. Three sets of glands matter most. First are the salivary glands. The parotid gland sits in front of each ear. The submandibular gland sits under the jaw. The sublingual gland sits under the tongue. Together they release up to a liter and a half of saliva a day.
Saliva wets food so it forms a soft lump, a bolus, that you can swallow. It starts breaking down starch with an enzyme called salivary amylase. It also guards your mouth. It has lysozyme, an enzyme that kills bacteria, plus antibodies that fight germs.
The liver and gallbladder
The liver is the body's largest gland. It is a chemical factory with dozens of jobs. But its one job in digestion is to make bile. Bile is a greenish fluid. It holds bile salts, which act on fat the way dish soap acts on grease. They emulsify fat. That means they break big blobs of fat into lots of tiny droplets. This gives fat-digesting enzymes far more surface to work on.
Between meals, bile flows into the gallbladder. This small, muscular pouch stores bile and makes it stronger. Then a fatty meal reaches the duodenum. A hormone called cholecystokinin (CCK) tells the gallbladder to squeeze. Bile flows down the common bile duct into the small intestine.
The pancreas: two glands in one
The pancreas sits behind the stomach and has two jobs. Its exocrine part sends juice into the gut through a duct. Clusters of cells called acinar cells make pancreatic juice. This is the most complete digestive juice in the body. It has enzymes for every food group. There is pancreatic amylase for starch and lipase for fat. There are trypsin and chymotrypsin for protein, and nucleases for nucleic acids. The juice also has lots of bicarbonate. This base cancels out the acid in the chyme coming from the stomach. That way, the enzymes in the intestine can work at a near-neutral pH.
The pancreas also has an endocrine part, which sends hormones into the blood. These are small clusters called the pancreatic islets. They release insulin and glucagon to control blood sugar. The pancreatic duct joins the common bile duct at a spot called the hepatopancreatic ampulla. Their mixed flow enters the duodenum through a ring of muscle, the sphincter of Oddi.
| Organ | What it releases | What it adds to digestion |
|---|---|---|
| Salivary glands | Saliva (amylase, lysozyme, mucus) | Wets food, starts starch digestion, guards the mouth |
| Liver | Bile (bile salts) | Emulsifies fats into small droplets |
| Gallbladder | None of its own (stores bile and makes it stronger) | Releases bile when CCK signals it |
| Pancreas (exocrine) | Pancreatic juice (enzymes + bicarbonate) | Digests all food groups; neutralizes acid |
Tap each helper organ in the interactive to see where its juice goes.
- The salivary glands (parotid, submandibular, sublingual) wet food. They start starch digestion with amylase.
- The liver makes bile, which emulsifies fat. The gallbladder stores bile and releases it when CCK signals.
- The pancreas makes enzymes for every food group, plus bicarbonate to cancel out acid. Separately, it makes insulin and glucagon.
- The pancreatic duct and bile duct join at the hepatopancreatic ampulla to enter the duodenum.
Section 6Chemical digestion
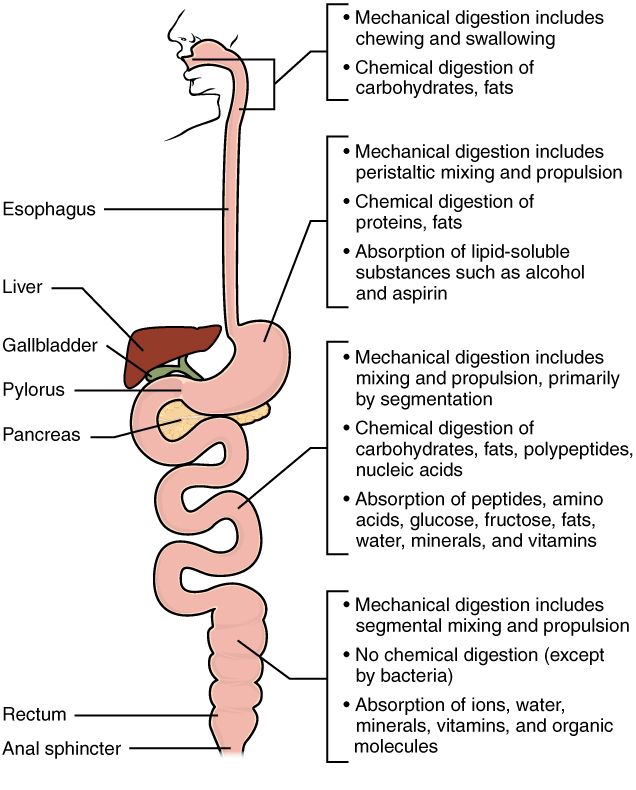
Why big molecules must be cut down
Most nutrients in food come as big, long chains. Starch, proteins, fats, and nucleic acids are all like this. They are simply too big to cross the cell membranes of the gut lining. Chemical digestion fixes this by hydrolysis, which means "splitting with water." Enzymes cut the bonds that hold each chain together. They add a molecule of water at every cut. They keep cutting until only small building blocks are left, which the body can take in.
Each food group has its own team of enzymes and its own end products. It is worth learning them side by side. Tests and doctors will both ask you to trace a nutrient from your plate to your blood.
Carbohydrates, proteins, and nucleic acids
Carbohydrate digestion starts in the mouth with salivary amylase. It picks up again in the small intestine with pancreatic amylase. Both break starch into maltose, a sugar made of two parts, and other small pieces. Next, enzymes on the brush border take over. Maltase, sucrase, and lactase split these two-part sugars into single sugars. The single sugars are glucose, fructose, and galactose, and these are taken in.
Protein digestion begins in the stomach with pepsin. It goes on in the intestine with two pancreatic enzymes, trypsin and chymotrypsin. Enzymes on the brush border called peptidases finish the job. They free single amino acids, the building blocks of protein.
Nucleic acids, like DNA and RNA, are cut by pancreatic nucleases into pieces called nucleotides. Then brush-border nucleosidases and phosphatases take those apart. The final pieces are nitrogenous bases, pentose sugars, and phosphate ions. Those pieces are taken in, not whole nucleotides.
Fats take a different route
Fat digestion is the special case. Fat does not mix with the watery chyme. So bile salts must first emulsify it into tiny droplets. Only then can pancreatic lipase cut each fat molecule, a triglyceride. The results are monoglycerides and free fatty acids. Little bundles of bile salts called micelles carry them to the surface of the villus. They pass into the gut cell.
Inside the cell, they are put back together into triglycerides. Then they are coated in protein and shipped out as droplets called chylomicrons. These are too big to enter the capillaries. So chylomicrons go into the lacteal instead. That is why fat from food travels through the lymph first. Sugars and amino acids go straight to the liver in the blood.
| Nutrient | Key enzymes | Taken in as |
|---|---|---|
| Carbohydrate | Salivary and pancreatic amylase; brush-border maltase, sucrase, lactase | Single sugars (glucose, fructose, galactose) |
| Protein | Pepsin (stomach); trypsin, chymotrypsin; brush-border peptidases | Amino acids |
| Fat | Bile salts (emulsify) + pancreatic lipase | Monoglycerides and fatty acids → chylomicrons |
| Nucleic acid | Pancreatic nucleases (make nucleotides); brush-border nucleosidases and phosphatases | Nitrogenous bases, pentose sugars, phosphate ions |
Tap a nutrient in the interactive. Follow it down to the building blocks your body takes in.
- Chemical digestion is hydrolysis. Enzymes cut long chains into small building blocks the body can take in.
- Carbs → single sugars (amylase, then brush-border maltase, sucrase, and lactase). Proteins → amino acids (pepsin, trypsin, chymotrypsin, peptidases). Nucleic acids → nucleotides → bases, pentose sugars, and phosphates.
- Fats need bile emulsification before lipase can work. Then they travel as chylomicrons into the lacteal.
- A missing brush-border enzyme (lactase) explains lactose intolerance.
The chapter in one breath
- The digestive system is an alimentary canal (mouth → anus) plus accessory organs. Its jobs are ingestion, propulsion, mechanical and chemical digestion, absorption, and defecation.
- The gut wall has four layers: mucosa, submucosa, muscularis externa, and serosa/adventitia. They repeat along the whole tube. The lumen is really outside the body.
- Smooth muscle makes peristalsis, which pushes food forward. It also makes segmentation, which mixes food so it can be taken in. Sphincters act as one-way gates.
- The stomach churns food into chyme. Its parietal, chief, mucous, and G cells make acid, pepsinogen, intrinsic factor, mucus, and gastrin. Its mucosal barrier protects it.
- The small intestine takes in almost everything. It uses circular folds, villi, and microvilli to build a huge surface. Each villus holds capillaries and a lacteal.
- The salivary glands, liver, gallbladder, and pancreas pour in saliva, bile, and pancreatic juice. Pancreatic juice is full of enzymes and bicarbonate.
- Chemical digestion breaks carbs into single sugars and proteins into amino acids. Fats are emulsified by bile, cut into fatty acids, and shipped as chylomicrons. Nucleic acids become nucleotides and then bases, sugars, and phosphates.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Absorption
- Moving digested nutrients across the gut wall into the blood or lymph.
- Accessory organs
- Helper organs that aid digestion, but food does not pass through them. They are the teeth, tongue, salivary glands, liver, gallbladder, and pancreas.
- Alimentary canal
- The one long muscle tube that food travels through, from mouth to anus. It is also called the GI tract.
- Bile
- A fluid made by the liver. Its bile salts emulsify fats. The gallbladder stores it and makes it stronger.
- Chylomicron
- A protein-coated droplet of fat. It carries fat from the gut cell into the lacteal and lymph.
- Chyme
- The soupy, acidic mix of partly digested food and stomach juice. It leaves the stomach.
- Emulsification
- Breaking big blobs of fat into tiny droplets, done by bile salts. It gives lipase more surface to work on.
- Hydrolysis
- Splitting a big molecule by adding water, with the help of an enzyme. It is the chemistry behind chemical digestion.
- Intrinsic factor
- A protein made by parietal cells. It is needed to take in vitamin B₁₂ in the ileum. Losing it causes pernicious anemia.
- Lacteal
- A closed-end lymph vessel in the center of a villus. It takes in digested fats as chylomicrons.
- Mucosa
- The innermost layer of the gut. It faces the lumen and makes juices and takes in food.
- Parietal cell
- A stomach gland cell that makes hydrochloric acid and intrinsic factor.
- Pepsin
- The stomach's protein-digesting enzyme. It forms when acid turns on pepsinogen from chief cells.
- Peristalsis
- A wave of smooth-muscle squeezing that travels along the tube and pushes food forward.
- Rugae
- Deep folds in the lining of an empty stomach. They flatten as it fills, so it can stretch.
- Segmentation
- Rings of muscle that squeeze in place. They mix chyme and press it against the wall so it can be taken in.
- Serosa
- The outer layer of a gut organ that hangs free in the belly. It is also called the visceral peritoneum.
- Sphincter
- A thick ring of muscle that acts as a valve between parts of the tube.
- Villus
- A tiny finger of lining in the small intestine. It is covered with microvilli and takes in nutrients.
Check yourself
Metabolism & Nutrition
Every second you are alive, thousands of chemical reactions are running inside your cells. Some build things up, and some break things down. All of them deal with energy. That whole web of reactions is called metabolism. In this chapter, the food on your plate finally meets the machines inside your cells. You will follow a molecule of glucose, a simple sugar, as it is taken apart to make ATP. You will watch your body switch between storing fuel after a meal and spending it between meals. You will also learn what the six kinds of nutrients do once they are inside you. By the end, a simple question, why do we eat?, will have a clear and satisfying answer.
By the end of this chapter you can
- Define metabolism. Tell anabolism apart from catabolism by which way they go and how they handle energy.
- Explain how ATP stores and hands out energy, and how catabolism is linked to anabolism.
- Follow glucose through the four steps of cellular respiration. Count the ATP made at each step.
- Explain why aerobic respiration needs oxygen, and what the cell does when it runs short.
- Compare the absorptive and postabsorptive states, and the roles of insulin and glucagon.
- Name the six classes of nutrients. Say which ones give energy, and how many calories each one gives.
- Sort the fat-soluble vitamins from the water-soluble ones. Predict which are stored and which you must eat often.
- Describe energy balance and the three parts of the energy you burn each day.
Section 1Anabolism & catabolism
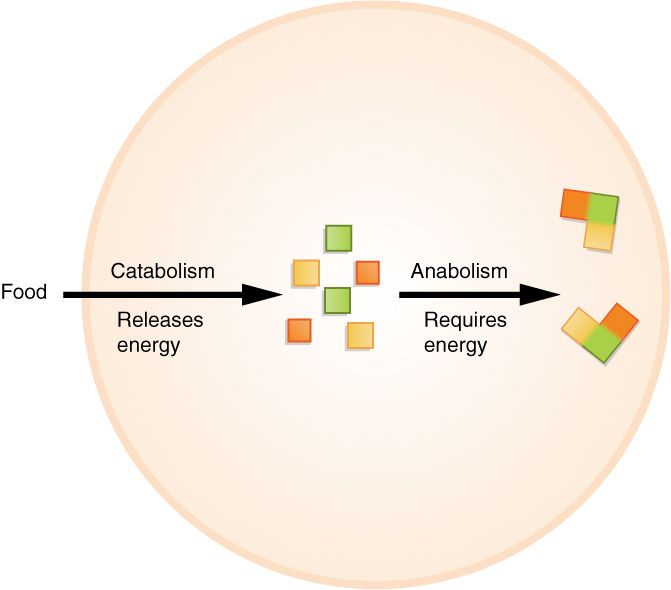
One word for every reaction
Metabolism is the sum of every chemical reaction in the body. A huge number of them run at the same time. To make sense of them, we sort each reaction into one of two directions. Anabolism is the building direction. Small molecules are joined into bigger ones. This is usually done by dehydration synthesis, which means a water molecule is removed to form a bond. Amino acids become proteins. Glucose units become glycogen, a stored form of sugar. Fatty acids and glycerol become fat.
Building costs energy. So anabolic reactions are endergonic, which means they take in energy. They must be paid for. Catabolism is the breaking-down direction. Big molecules are split into smaller ones. This is usually done by hydrolysis, which means water is added to break a bond. Catabolism frees the energy that was locked in those bonds. So these reactions are exergonic, which means they give off energy. They pay out. The two directions work as a team. The energy freed by catabolism is exactly what pays for anabolism.
ATP: the cell's rechargeable battery
The body does not spend food energy directly. Instead, it turns that energy into one kind of money that every cell uses. That money is ATP (adenosine triphosphate). ATP holds its energy in the bonds between its three phosphate groups. Snap off the last phosphate, and you get ADP, a free phosphate, and a burst of energy the cell can use. The cell uses that burst to power muscle movement, nerve signals, and building work.
Catabolism then recharges the battery. It sticks the phosphate back on, turning ADP back into ATP. This constant charge and use is called energy coupling. A reaction that gives off energy is linked to one that needs energy. That way, the energy is handed off instead of lost as heat. You cycle about your whole body weight in ATP every day. That is not because you store that much. It is because each molecule gets recharged thousands of times.
Following the electrons
Many reactions in metabolism are oxidation-reduction (redox) reactions. In these, electrons move from one molecule to another. A molecule that loses electrons is oxidized. A molecule that gains them is reduced. This matters because electrons carry energy. The cell moves them around with shuttle molecules called electron carriers. The main ones are NAD⁺ and FAD. When these carriers pick up electrons, they become NADH and FADH₂. They are loading up on energy to deliver later. Hold on to that idea. In the next section, those loaded carriers are the key to making most of your ATP.
| Feature | Anabolism | Catabolism |
|---|---|---|
| Direction | Builds big molecules from small ones | Breaks big molecules into small ones |
| Reaction type | Dehydration synthesis | Hydrolysis |
| Energy | Needs energy (endergonic); uses ATP | Gives off energy (exergonic); makes ATP |
| Example | Amino acids → protein; glucose → glycogen | Protein → amino acids; glycogen → glucose |
Switch between the building and breaking directions in the interactive below.
- Metabolism is all the reactions in the body. Anabolism builds up (endergonic, uses ATP). Catabolism breaks down (exergonic, makes ATP).
- ATP is the cell's energy money. It breaks into ADP + phosphate to do work, and catabolism recharges it.
- Energy coupling links reactions that give off energy to ones that need it. So the energy is used, not wasted.
- The electron carriers NAD⁺ and FAD carry energy-rich electrons from catabolism to the steps that make ATP.
Section 2Cellular respiration
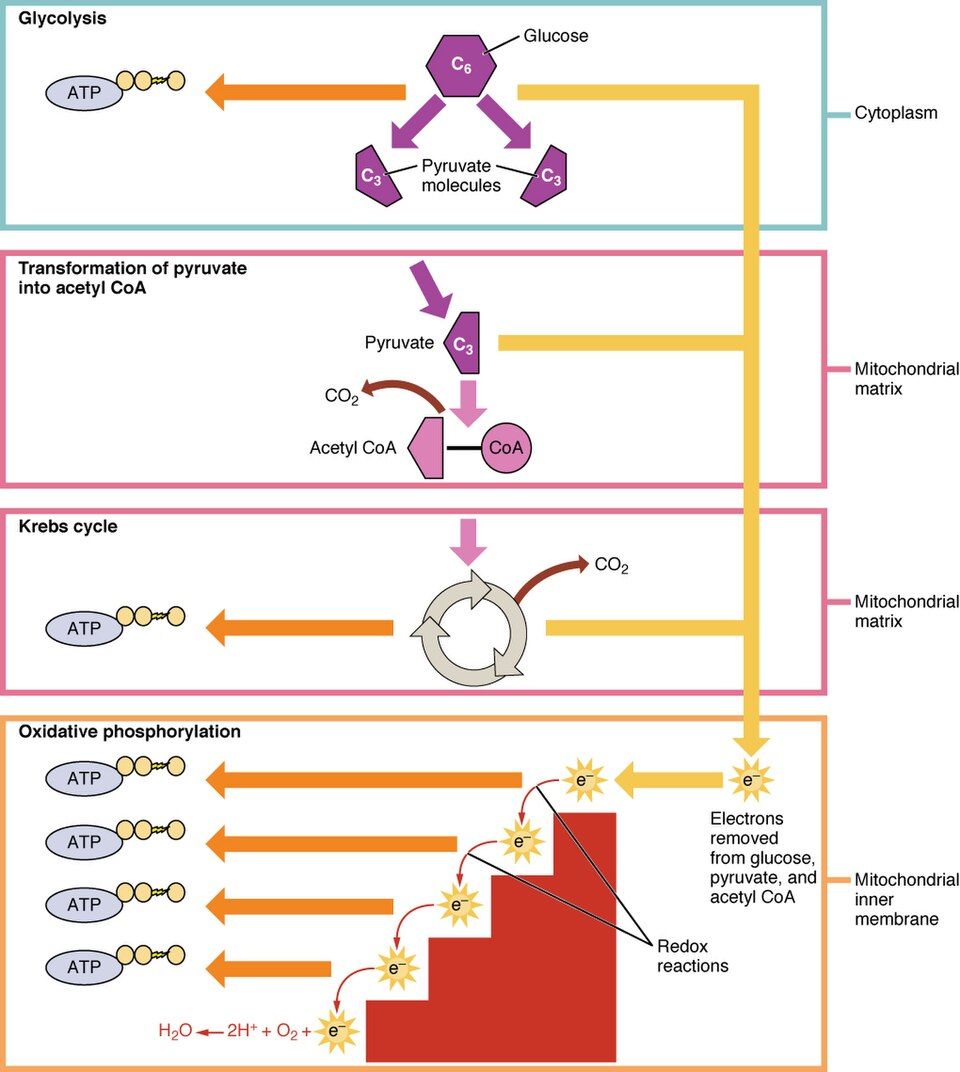
Burning glucose, carefully
Cellular respiration is the careful, step-by-step breakdown of glucose to make ATP. Think of it as a slow, safe burn. The cell does not free all of glucose's energy at once in a harmful flash. Instead, it takes the energy away in small steps and saves it in ATP as it goes. The process has four stages in two places. The first stage happens in the cytoplasm, the fluid that fills the cell. The last three happen inside the mitochondrion, the cell's power plant. With enough oxygen, one glucose molecule can make up to about 30 to 32 ATP. Let's follow it stage by stage.
The four stages
1. Glycolysis happens in the cytoplasm and needs no oxygen. One glucose, which has six carbons, is split into two pyruvate molecules. Each pyruvate has three carbons. The cell spends two ATP to start and gets four back. That is a net gain of 2 ATP, plus 2 NADH.
2. Pyruvate oxidation is also called the transition reaction. Each pyruvate moves into the matrix, the inner space of the mitochondrion. There, one carbon is cut off and leaves as CO₂. The rest is joined to a carrier to form acetyl CoA. This step makes more NADH.
3. The citric acid cycle (Krebs cycle) also happens in the matrix. Acetyl CoA is fed into a loop. The loop frees the rest of the carbons as CO₂. It makes a little ATP directly. Most important, it loads up many NADH and FADH₂ carriers.
4. Oxidative phosphorylation happens on the inner membrane of the mitochondrion. This is where the big payoff comes. The loaded carriers drop their electrons into the electron transport chain. The chain uses that energy to pump H⁺ ions across the membrane, building up a crowd on one side. The ions then rush back through an enzyme that spins like a water wheel. As it spins, it snaps phosphates onto ADP. This step alone makes most of the ATP.
| Stage | Location | Needs O₂? | Main products |
|---|---|---|---|
| Glycolysis | Cytoplasm | No | 2 pyruvate, net 2 ATP, 2 NADH |
| Pyruvate oxidation | Mitochondrial matrix | Yes (aerobic) | Acetyl CoA, CO₂, NADH |
| Citric acid cycle | Mitochondrial matrix | Yes (aerobic) | CO₂, 2 ATP, NADH, FADH₂ |
| Oxidative phosphorylation | Inner mitochondrial membrane | Yes | About 26–28 ATP, H₂O |
Why oxygen, and what happens without it
Here is the big point of the whole process. Oxygen is the final electron acceptor. At the very end of the electron transport chain, the used-up electrons and some H⁺ ions are handed to O₂. This forms H₂O, water. That is the water you make from breathing. If no oxygen is there to take them, the chain backs up like a clogged drain. The carriers stay loaded, and stages 2 through 4 grind to a stop.
When that happens, the cell falls back on anaerobic fermentation, which means making energy without oxygen. It keeps glycolysis going by turning pyruvate into lactic acid. This step frees up the NAD⁺ that glycolysis needs. It gives a fast trickle of 2 ATP with no oxygen. That helps a sprinting muscle. But it is very wasteful, and lactic acid builds up. That is part of why hard exercise burns.
Step through all four stages in the interactive. Watch the ATP add up.
- Cellular respiration is the careful breakdown of glucose. It makes up to about 30–32 ATP.
- Four stages: glycolysis (cytoplasm) → pyruvate oxidation → citric acid cycle (matrix) → oxidative phosphorylation (inner membrane).
- Oxidative phosphorylation makes most of the ATP. O₂ is the final electron acceptor, and it forms water.
- Without oxygen, cells use anaerobic fermentation. It makes only 2 ATP per glucose, and lactic acid is left over.
Section 3Metabolic states: fed vs fasting
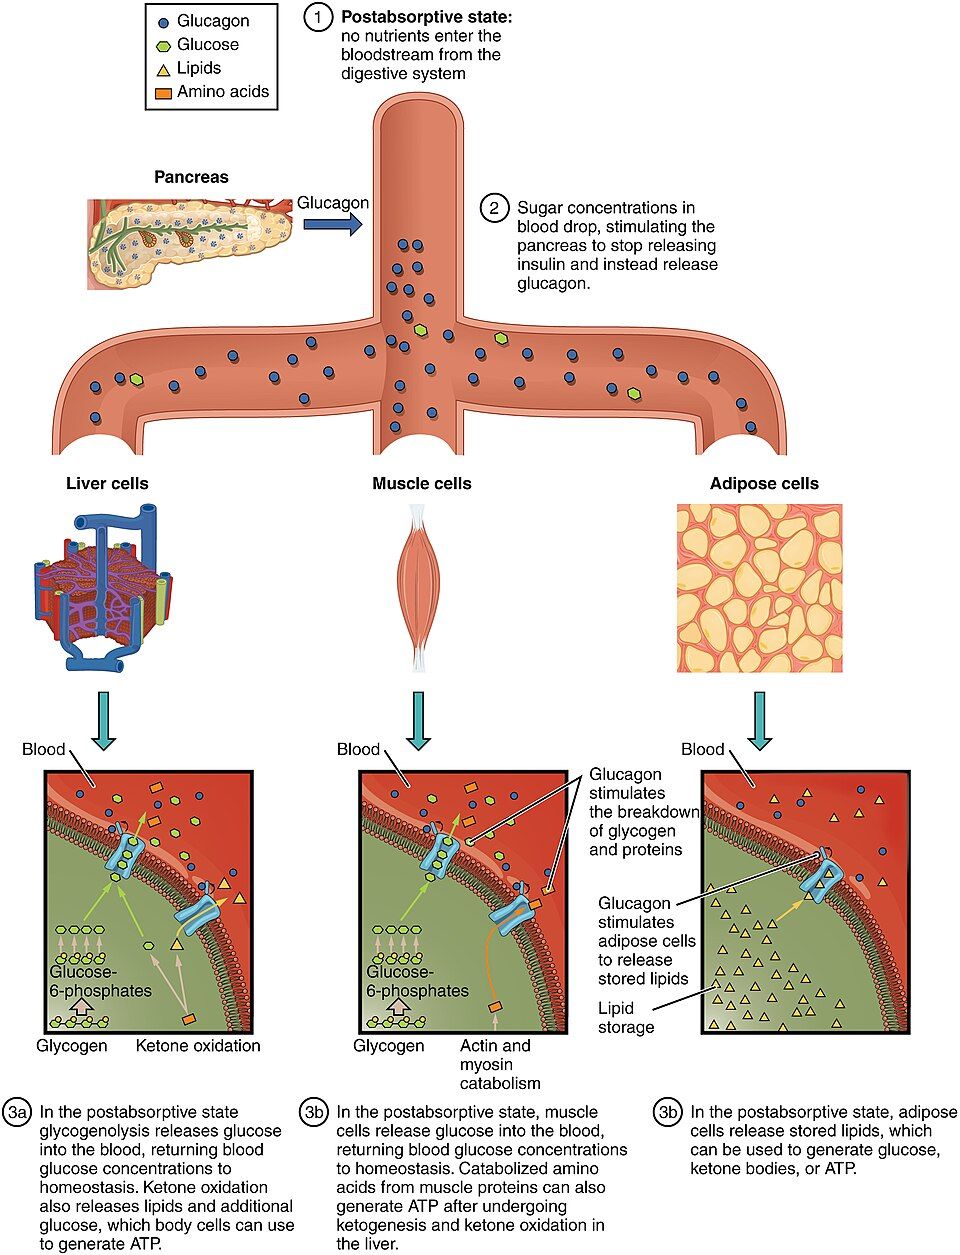
Two modes: store or spend
Your fuel supply is not steady. It comes in bursts at mealtimes, then runs low for hours. To cope, the body runs in two metabolic states. The absorptive (fed) state is the few hours after a meal. Nutrients pour in from the gut, and blood sugar rises. The job now is to store the extra. Extra glucose is packed into glycogen. This is called glycogenesis. Extra fuel is also turned into fat, which is called lipogenesis. Amino acids are used to build protein.
The postabsorptive (fasting) state takes over once the meal is fully taken in. This happens overnight, between meals, or during a fast. Now the job flips to releasing stored fuel to keep blood sugar steady. Glycogen is broken back down into glucose, which is called glycogenolysis. Fat is broken down, which is called lipolysis. The liver even makes brand-new glucose from things that are not carbs, like amino acids. This is called gluconeogenesis, which means "making new glucose."
Two hormones run the switch
Two hormones from the pancreas mostly decide which state you are in. They work against each other. Insulin is the storage hormone. It rises after a meal and moves glucose into cells. It turns on all the building pathways. Glucagon is the releasing hormone. It rises during fasting and turns on the pathways that free stored fuel. Think of them as a seesaw. High insulin means store. High glucagon means spend. One organ is the hub for all of this: the liver. It stores glycogen after meals and sends out glucose between them. This keeps blood sugar in its narrow, healthy range all day and night.
Protecting the brain
Why go to all this trouble? Because the brain runs almost only on glucose. It can't store its own fuel, so blood sugar must never crash. During a long fast, the body uses glucose sparing. Most tissues switch to burning fatty acids. That saves the scarce glucose for the brain. In long starvation, the liver turns fat into ketone bodies. These are a backup fuel the brain can partly use. It is a clever trick. But ketones are acidic, and a large buildup can make the blood dangerously acidic.
| Feature | Absorptive (fed) | Postabsorptive (fasting) |
|---|---|---|
| When | Hours after a meal | Between meals, overnight, fasting |
| Goal | Store extra fuel | Release stored fuel |
| Main hormone | Insulin | Glucagon |
| Key processes | Glycogenesis, lipogenesis, making protein | Glycogenolysis, lipolysis, gluconeogenesis, ketogenesis (making ketones) |
| Blood sugar trend | Rising → stored | Falling → protected |
Flip between the fed and fasting states in the interactive below.
- The absorptive state stores extra fuel (glycogenesis, lipogenesis). The postabsorptive state releases it (glycogenolysis, gluconeogenesis, lipolysis).
- Insulin drives storage, and glucagon drives release. They act like a seesaw, and the liver is the center.
- The brain needs glucose. So during fasting, the body protects blood sugar by glucose sparing. In a long fast, it also makes ketone bodies.
Section 4The six nutrient classes

Three that fuel you, three that don't
Everything worth eating falls into six classes of nutrients. Three of them give you energy you can use. You eat them in large amounts, so they are called the macronutrients ("macro" means large). They are carbohydrates, lipids (fats), and proteins. The other three give no energy at all. But you need them in smaller amounts. They are vitamins, minerals, and water.
"No energy" does not mean "you can skip it." Without water or tiny amounts of certain minerals, you would die long before you starved. Each class has a job. Carbs are the body's favorite quick fuel. Fats are the most packed energy store, and they build every cell's outer membrane. Proteins mostly build and run things, like enzymes, muscle, and antibodies. The body burns protein for energy only as a last choice.
How much energy is in food?
The energy in food is measured in kilocalories. On food labels, these are written as "Calories" with a capital C. Only the three macronutrients have calories, and they are not equal. Carbs and protein each give about 4 kcal per gram. Fat has more than twice that, about 9 kcal per gram. That is why fatty foods are so high in calories. It is also why the body picks fat for its long-term energy store. Alcohol is not a nutrient, but it also has energy, about 7 kcal per gram.
Essential nutrients: the ones you must eat
An essential nutrient is one your body can't make, or can't make enough of. So it must come from food. These include about nine essential amino acids and a couple of essential fatty acids. They also include all the vitamins and minerals. This is why protein quality matters. A complete protein has all the essential amino acids. Meat, eggs, dairy, and soy are examples. Most single plant foods are incomplete. But if you combine plants that fill each other's gaps, like beans with rice, you get the full set.
| Nutrient class | Gives energy? | Main role | Energy value |
|---|---|---|---|
| Carbohydrates | Yes | Favorite quick fuel | 4 kcal/g |
| Proteins | Yes | Building, enzymes, defense; last-choice fuel | 4 kcal/g |
| Lipids (fats) | Yes | Packed energy store; cell membranes; hormones | 9 kcal/g |
| Vitamins | No | Coenzymes (enzyme helpers) and controllers | None |
| Minerals | No | Ions, bone, enzyme helpers (Na⁺, Ca²⁺, Fe) | None |
| Water | No | Dissolves things, carries things, controls body heat | None |
Tap each nutrient class in the interactive to see its role.
- There are six nutrient classes. Carbohydrates, lipids, proteins give energy. Vitamins, minerals, water give no energy, but you still need them.
- Calories: carbs and protein give 4 kcal/g. Fat gives 9 kcal/g.
- Essential nutrients must come from food. They include some amino acids and fatty acids, and all vitamins and minerals.
- Complete proteins have all the essential amino acids. You can combine plant foods to get the same result.
Section 5Vitamins

Tiny amounts, huge consequences
Vitamins are carbon-based molecules the body needs in very small amounts to run its metabolism. Most act as coenzymes. These are helper molecules that enzymes need in order to work. You need only milligrams or even micrograms a day. Yet if you are short on even one, you can get a specific disease. Some of these diseases can kill.
One simple thing controls how a vitamin behaves: how it dissolves. Some dissolve in fat, and some dissolve in water. That splits all vitamins into two groups. This one fact tells you how each is taken in and whether it is stored. It also tells you whether it can build up to harmful levels.
Fat-soluble: stored, and able to overdose
The fat-soluble vitamins are A, D, E, and K. Remember them as "ADEK." Because they dissolve in fat, they are taken in along with the fat in your food. Then they are stored in the liver and in fat tissue. This storage cuts both ways. You can go a while without them, because you have a reserve. But the body can't easily flush out the extra. So very large doses of A or D can build up to toxic, or poisonous, levels. Each has its own job. A helps you see. D helps balance calcium and build bone. E is an antioxidant that protects cells from damage. K helps blood clot.
Water-soluble: not stored, needed steadily
The water-soluble vitamins are the B-complex and vitamin C. Because they dissolve in water, the body does not stock up on them. The kidneys filter out any extra, and it leaves in urine. That is why very high doses mostly make expensive urine. The downside is that you need a steady daily supply. If you don't get enough, problems show up fairly fast. Most B vitamins are coenzymes in energy pathways, the same ones from Sections 1 and 2.
The classic shortage diseases are worth knowing. Scurvy comes from a lack of vitamin C. Rickets, a softening of the bones, comes from a lack of vitamin D. Beriberi comes from a lack of B₁. Pellagra comes from a lack of B₃. Pernicious anemia comes from a lack of B₁₂.
| Property | Fat-soluble (A, D, E, K) | Water-soluble (B-complex, C) |
|---|---|---|
| Taken in with | Fat in food | Water |
| Stored? | Yes, in the liver and fat | No (B₁₂ is the exception) |
| Extra | Builds up → risk of poisoning | Leaves in urine |
| How often you need it | Less often (you have a reserve) | Often, almost daily |
| Shortage disease example | Rickets (D), night blindness (A) | Scurvy (C), beriberi (B₁) |
Switch between the two vitamin groups in the interactive, and tap each one.
- You need vitamins in tiny amounts. Most act as coenzymes. How they dissolve controls how they behave.
- Fat-soluble (A, D, E, K) vitamins are taken in with fat and stored. They can reach toxic levels.
- Water-soluble (B-complex, C) vitamins are not stored. Extra leaves in urine, so you need a steady daily supply.
- Each shortage has its own disease: scurvy (C), rickets (D), beriberi (B₁), pellagra (B₃), and pernicious anemia (B₁₂).
Section 6Energy balance
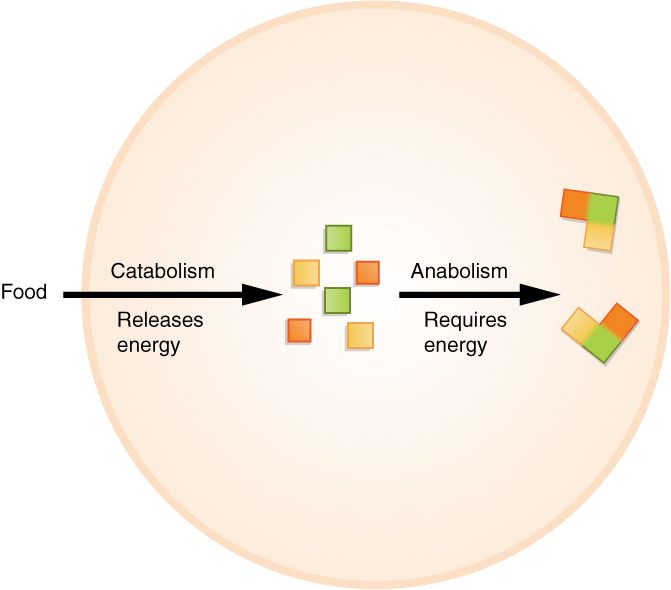
A ledger, not a mystery
At its core, body weight follows a simple money-like rule called energy balance. It compares the calories you take in as food with the calories you spend, or put out. When intake equals spending, weight stays steady. This is neutral balance. When intake is more than spending, the extra is stored, mostly as fat, and weight goes up. This is positive balance. When spending is more than intake, the body draws on its stores, and weight goes down. This is negative balance. The rule is simple. Weight is hard to control because biology runs both sides of the ledger. Willpower alone is not the whole story.
Where the calories go
"Energy out" is not just exercise. The total energy you burn has three parts. By far the largest is the basal metabolic rate (BMR). This is the energy your body burns just to stay alive at rest. It keeps your heart beating, your kidneys filtering, and your body warm. BMR makes up about 60 to 75% of what you burn in a day. That surprises most people.
A second part, about 10%, is the thermic effect of food. This is the energy spent digesting and taking in a meal. The last part changes the most. It is physical activity, from fidgeting to running a marathon. BMR is the biggest part. So things that change BMR have a big effect on how easily a person gains or loses weight. These include muscle mass, age, thyroid hormone, and body size.
The body defends its weight
Energy balance is not left to chance. It is controlled in the same way the body keeps other things steady. The hypothalamus, a small part of the brain, is the control center. It reads hormone signals about how much fuel the body has stored. Leptin comes from fat tissue. It signals that stores are full and turns down hunger. Ghrelin comes from the empty stomach. It signals hunger and makes you want to eat.
Here is a handy rule of thumb. A pound of body fat stores about 3,500 kcal. So eating about 500 kcal less than you burn each day takes off close to a pound a week. That holds at least until the body lowers its BMR to fight the loss.
| Balance | Intake vs output | Result |
|---|---|---|
| Neutral | In = out | Weight stays steady |
| Positive | In > out | Extra stored as fat → weight gain |
| Negative | In < out | Stores used up → weight loss |
Tip the balance one way or the other in the interactive, and see what happens.
- Energy balance compares calories in (food) with calories out. Positive balance stores fat. Negative balance uses it up.
- Total energy burned = BMR (about 60–75%, the largest part) + thermic effect of food (about 10%) + physical activity.
- The hypothalamus controls hunger and stores. It uses signals like leptin (full) and ghrelin (hungry).
- About 3,500 kcal equals a pound of fat. But the body defends its weight by changing its BMR.
The chapter in one breath
- Metabolism is every reaction in the body. Anabolism builds and uses energy. Catabolism breaks down and frees energy. ATP is the shared energy money.
- Cellular respiration breaks down glucose in four stages: glycolysis, pyruvate oxidation, the citric acid cycle, and oxidative phosphorylation. It makes up to about 32 ATP.
- Oxygen is the final electron acceptor. Without it, cells fall back on anaerobic fermentation. That makes only 2 ATP, plus lactic acid.
- The body switches between an absorptive state (store, insulin) and a postabsorptive state (release, glucagon). The liver keeps blood sugar steady for the brain.
- Food gives six nutrient classes. Carbs, fats, and proteins give energy (4, 9, and 4 kcal/g). Vitamins, minerals, and water give none.
- Vitamins split by how they dissolve. Fat-soluble A, D, E, K are stored and can be toxic. Water-soluble B and C leave in urine and are needed daily.
- Energy balance weighs calories in against calories out. Calories out come from BMR, the thermic effect of food, and activity. The body works hard to defend its weight.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Absorptive (fed) state
- The hours after a meal, when food is being taken in and blood sugar rises. Insulin directs the body to store the extra fuel.
- Anabolism
- The building side of metabolism. Small molecules are joined into bigger ones, which takes energy (endergonic).
- ATP (adenosine triphosphate)
- The cell's energy money. Energy is freed when its last phosphate comes off to form ADP. It is stored again when the phosphate goes back on.
- Basal metabolic rate (BMR)
- The energy the body burns at full rest just to stay alive. It is the largest part of the energy you burn each day.
- Catabolism
- The breaking-down side of metabolism. Big molecules are split into smaller ones, which frees energy (exergonic).
- Cellular respiration
- The careful, step-by-step breakdown of glucose. It saves glucose's energy in ATP.
- Citric acid cycle (Krebs cycle)
- A loop of reactions in the mitochondrion that breaks down acetyl CoA. It gives off CO₂ and loads NADH and FADH₂ for the electron transport chain.
- Electron transport chain
- A row of carriers in the inner membrane of the mitochondrion. It passes electrons along to pump H⁺ ions, which powers most ATP making.
- Energy balance
- How the calories you eat compare with the calories you burn. It decides whether your weight goes up, goes down, or stays steady.
- Essential nutrient
- A nutrient the body can't make enough of, so it must come from food. Examples are certain amino acids and fatty acids, and all vitamins and minerals.
- Fat-soluble vitamin
- A vitamin (A, D, E, or K) taken in with fat and stored in the body. Too much can be toxic.
- Gluconeogenesis
- The liver making new glucose from things that are not carbs, like amino acids. It happens during fasting.
- Glycogenolysis
- Breaking stored glycogen back into glucose to raise blood sugar between meals.
- Glycolysis
- The first stage of respiration, in the cytoplasm. It splits glucose into two pyruvate and nets 2 ATP without oxygen.
- Ketone bodies
- Acidic fuel molecules the liver makes from fat during a long fast. The brain can use them, but they can make the blood too acidic.
- Kilocalorie (Calorie)
- The unit of food energy. Carbs and protein give about 4 kcal/g, and fat gives about 9 kcal/g.
- Metabolism
- The sum of all chemical reactions in the body. It includes anabolism and catabolism.
- Oxidative phosphorylation
- The last stage of respiration, on the inner membrane of the mitochondrion. It uses the electron transport chain and oxygen to make most of the ATP.
- Postabsorptive (fasting) state
- The time between meals, when stored fuel is released to keep blood sugar steady. Glucagon directs it.
- Vitamin
- A carbon-based molecule needed in tiny amounts. It usually acts as a coenzyme in metabolism.
- Water-soluble vitamin
- A vitamin (the B-complex or C) that dissolves in water and is not stored. Extra leaves in urine, so you need it often.
Check yourself
The Urinary System
Each minute, about one fifth of the blood your heart pumps takes a side trip. It flows through two fist-sized organs tucked against your back. It comes out cleaner and better balanced than it went in. This chapter follows that trip. You will meet the four organs of the urinary system, the body parts that make, store and get rid of urine. You will cut open a kidney to see how it is built. Then you will shrink down to the tiny nephron, where urine is made. You will watch three steps: filter, take back, and fine-tune. These steps turn 180 liters of filtered fluid a day into only about a liter and a half of urine.
Along the way, you will see how a few hormones, the body's chemical messengers, let the kidney set your blood volume and blood pressure. You will also see how a simple spinal reflex, an automatic action, empties the bladder. You learned to override it as a toddler. Keeping the inside of the body steady is the big theme of this whole book. The kidney is its master builder.
By the end of this chapter you can
- List the four organs of the urinary system and the job of each. Describe the many ways the kidneys keep the body steady, beyond making urine.
- Name the main gross structures of the kidney, the parts you can see without a microscope. These are the cortex, medulla, pyramids, calyces and renal pelvis. Trace the path urine takes to leave.
- Describe the nephron as the working unit of the kidney. Name its parts in order, from renal corpuscle to collecting duct.
- Explain the filtration membrane. Tell how the renal corpuscle makes a filtrate with no protein in it.
- Tell apart the three steps of making urine: filtration, reabsorption, and secretion. Say where each one happens.
- Explain how ADH, aldosterone, the renin–angiotensin–aldosterone system, and ANP change water and salt. Tell how this controls blood volume and pressure.
- Describe the micturition reflex. Explain how you control the outer sphincter to decide when to pee.
Section 1What the urinary system does
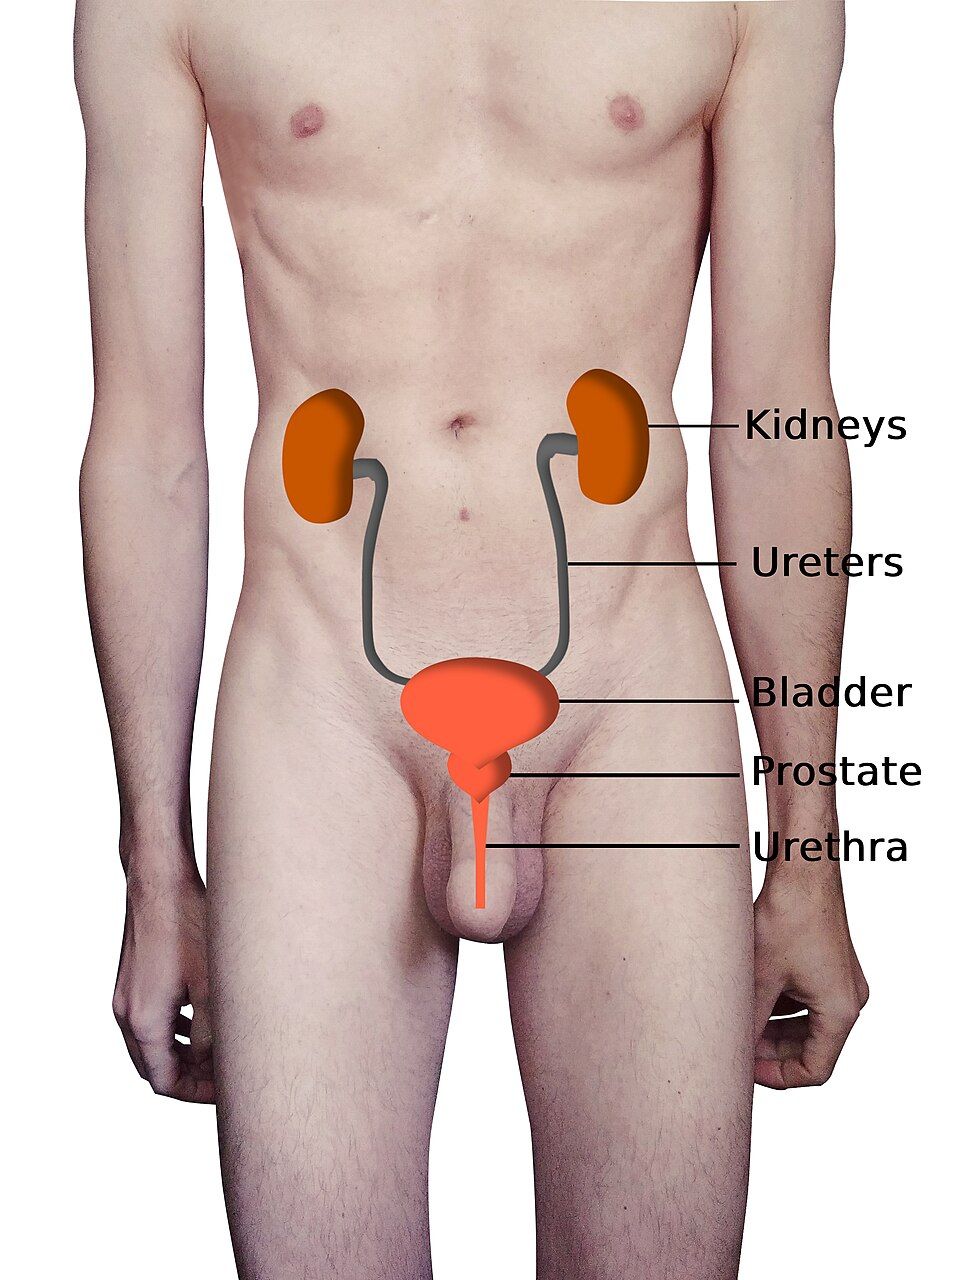
Not just a waste line
It is easy to think of the urinary system as just a way to get rid of waste. But that sells it short. Yes, the kidneys clear nitrogen wastes. One is urea, which comes from breaking down protein. Another is creatinine, which comes from muscle.
But their bigger job is homeostasis, the body's way of keeping things steady inside. Minute by minute, the kidneys decide how much water, sodium, potassium, calcium and acid to keep. They also decide how much to let go. This keeps your blood inside the narrow ranges your cells need to live. The kidney is where the idea of a steady inside turns into a real machine.
Drink a big glass of water, and the kidney gets rid of the extra within the hour. When you are low on water, it holds on tight. It makes the urine more concentrated, or stronger, to save every drop. The kidney also does jobs that have nothing to do with urine. It helps set blood pressure. It tells the bone marrow to make red blood cells. It also turns on vitamin D.
The four organs, in order
The plumbing is quite simple. Two kidneys make urine. Two ureters carry it down. One urinary bladder stores it. One urethra carries it out.
Everything up to the ureters is about chemistry, or changing the blood. Everything from the ureters down is about moving and storing urine. The kidneys sit high on the back wall of the belly, one on each side of the spine. They are retroperitoneal. This means they sit behind the lining of the belly, not inside it. The right kidney sits a bit lower than the left. That is because the large liver sits above it.
| Organ | Number | Main job |
|---|---|---|
| Kidneys | 2 | Filter blood and form urine. Balance water, salts and pH. Help set blood pressure and red blood cell count. |
| Ureters | 2 | Carry urine from kidney to bladder by peristalsis (waves of muscle squeezing) |
| Urinary bladder | 1 | Stores urine until it is a good time to let it out |
| Urethra | 1 | Carries urine from the bladder to the outside of the body |
A river of blood, a trickle of urine
The kidneys handle a huge amount of blood. Together they get about 20–25% of the entire cardiac output. That is the blood your heart pumps each minute. For their size, they get more blood than almost any other organ. From it, they filter about 180 liters of fluid every day.
If all of that left as urine, you would be in deep trouble. So the kidney takes back more than 99% of it. Only about 1–2 liters leave as urine. This plan is the secret to the kidney's control. It pushes a huge amount out. Then it picks exactly what to take back. That way, it can control dozens of substances one at a time.
Tap each of the four organs in the interactive. See where it sits and what it does.
- The urinary system has four organs. Two kidneys make urine. Two ureters move it. One bladder stores it. One urethra lets it out.
- The kidneys do much more than clear waste. They control water, electrolytes, and pH. They also help control blood pressure, red blood cell making, and vitamin D.
- The kidneys are retroperitoneal, behind the belly lining. They get about 20–25% of cardiac output. They filter about 180 L a day but pass only 1–2 L of urine.
Section 2Inside the kidney
The layers from outside in
Slice a kidney down the middle like a bean. You will see neat layers. A tough, fiber-filled renal capsule wraps the outside. (Renal means "of the kidney.") Just under it is the renal cortex. This grainy outer layer is where filtering starts.
Deeper in is the renal medulla. It is made of 8–18 cone-shaped renal pyramids. The pyramids point inward. The tip of each cone is the renal papilla. It drips finished urine into spaces that collect it. Strips of cortex called renal columns dip down between the pyramids. They carry blood vessels.
The whole kidney curves around a notch on its inner edge, called the hilum. Here the renal artery comes in. The renal vein and the ureter go out.
The drainage route
Once urine drips off a papilla, the kidney does not change it again. It is just collected and drained. This route is worth learning. It names the parts a kidney stone passes through.
Urine leaves the papilla into a cup-shaped minor calyx. Several of these join to form a major calyx. The major calyces empty into a funnel called the renal pelvis. The renal pelvis narrows at the hilum and becomes the ureter. So the path is: papilla → minor calyx → major calyx → renal pelvis → ureter.
| Structure | Location | What happens there |
|---|---|---|
| Renal capsule | Outer surface | Tough coat that protects the kidney |
| Renal cortex | Outer working layer | Holds the renal corpuscles. Filtering starts here. |
| Renal medulla (pyramids) | Under the cortex | Holds the loops and collecting ducts that concentrate urine |
| Renal papilla | Tip of each pyramid | Drips finished urine into a minor calyx |
| Calyces & renal pelvis | Central collecting space | Funnel urine toward the ureter (no more changes are made) |
| Hilum | Notch on the inner edge | Where the renal artery, renal vein and ureter go in and out |
Two capillary beds in a row
The kidney's blood supply has one odd feature. It makes everything else work. Most organs have one bed of capillaries, the tiniest blood vessels. The kidney has two capillary beds in series, which means one after the other.
Blood comes in through the renal artery. It branches down to a tiny afferent arteriole, a small artery that carries blood in. Then it enters the first bed. This is a high-pressure knot of capillaries called the glomerulus. Filtering happens here.
Blood does not drain into a vein next. It leaves the glomerulus through an efferent arteriole, a small artery that carries blood out. Then it enters a second bed. These are the peritubular capillaries, which wrap around the tubules. With two beds, the kidney can filter under high pressure in the first bed. Then it can take things back under low pressure in the second. Two opposite jobs happen one after the other.
Slice the kidney in the interactive below and explore each zone.
- From the outside in: capsule → cortex → medulla (pyramids). Renal columns made of cortex sit between the pyramids.
- Urine drains: papilla → minor calyx → major calyx → renal pelvis → ureter. It is not changed after the papilla.
- The kidney has two capillary beds in series. The high-pressure glomerulus filters. The low-pressure peritubular capillaries take things back.
Section 3The nephron
A million tiny factories
The kidney does not filter like one big strainer. Its work is split among about one million tiny units in each kidney. These units are called nephrons. Each one is a whole little urine factory.
A nephron has two parts. The renal corpuscle makes the filtrate, the fluid filtered out of the blood. A long, winding renal tubule then turns that filtrate into urine. If you understand one nephron, you understand the whole kidney. The organ is just this same unit, repeated a million times.
The renal corpuscle and the filtration membrane
The renal corpuscle is where blood becomes filtrate. It has two parts. The glomerulus is that high-pressure ball of capillaries. It sits inside a cup called the glomerular capsule, or Bowman's capsule. Fluid squeezes out of the blood in the glomerulus. It crosses a three-layer filtration membrane and enters the capsule.
This membrane is very choosy. Its first layer is the fenestrated capillary wall. Fenestrated means "with windows," and this wall is full of pores. Its middle layer is a basement membrane. It has a negative charge that pushes proteins away. Its third layer is made of octopus-like cells called podocytes. Their "feet" lock together like fingers. They leave narrow gaps called filtration slits.
Together, these layers let water and small particles pass easily. They hold back blood cells and blood proteins. So normal filtrate is basically blood plasma with no protein. Protein or blood in the urine is a warning sign. It means this membrane may be damaged.
Following the tubule
From the capsule, filtrate flows through the tubule's parts in a set order. Each part has its own job. First comes the proximal convoluted tubule (PCT). Proximal means "near," and convoluted means "twisted." Next is the hairpin-shaped loop of Henle. It has a part going down and a part going up. Then comes the distal convoluted tubule (DCT). Distal means "far." Last is the collecting duct. It gathers filtrate from many nephrons and carries it toward the papilla.
Some nephrons sit almost fully in the cortex. These are cortical nephrons. A smaller group are the juxtamedullary nephrons. Juxta means "next to," so they sit next to the medulla. They have long loops that dive deep into the medulla. They are what make concentrated urine possible.
| Segment | Location | Main role |
|---|---|---|
| Renal corpuscle | Cortex | Filtration. Makes filtrate with no protein. |
| Proximal convoluted tubule (PCT) | Cortex | Bulk reabsorption, taking back most of the water, Na⁺, glucose and amino acids |
| Loop of Henle | Medulla | Makes the medulla salty, which lets the kidney concentrate urine |
| Distal convoluted tubule (DCT) | Cortex | Fine-tuning under hormone control (Na⁺, K⁺, Ca²⁺) |
| Collecting duct | Cortex & medulla | Last step of water reabsorption (controlled by ADH). Drains to the papilla. |
Trace the filtrate through every twist of the nephron in the interactive.
- The nephron is the working unit of the kidney. There are about 1 million in each kidney. Each has a renal corpuscle and a renal tubule.
- The filtration membrane has three layers: a capillary wall with pores, a basement membrane, and podocyte slits. It lets water and small particles through. It holds back cells and proteins.
- Tubule order: corpuscle → PCT → loop of Henle → DCT → collecting duct. Juxtamedullary nephrons have long loops. They make the urine concentrated.
Section 4How urine is made
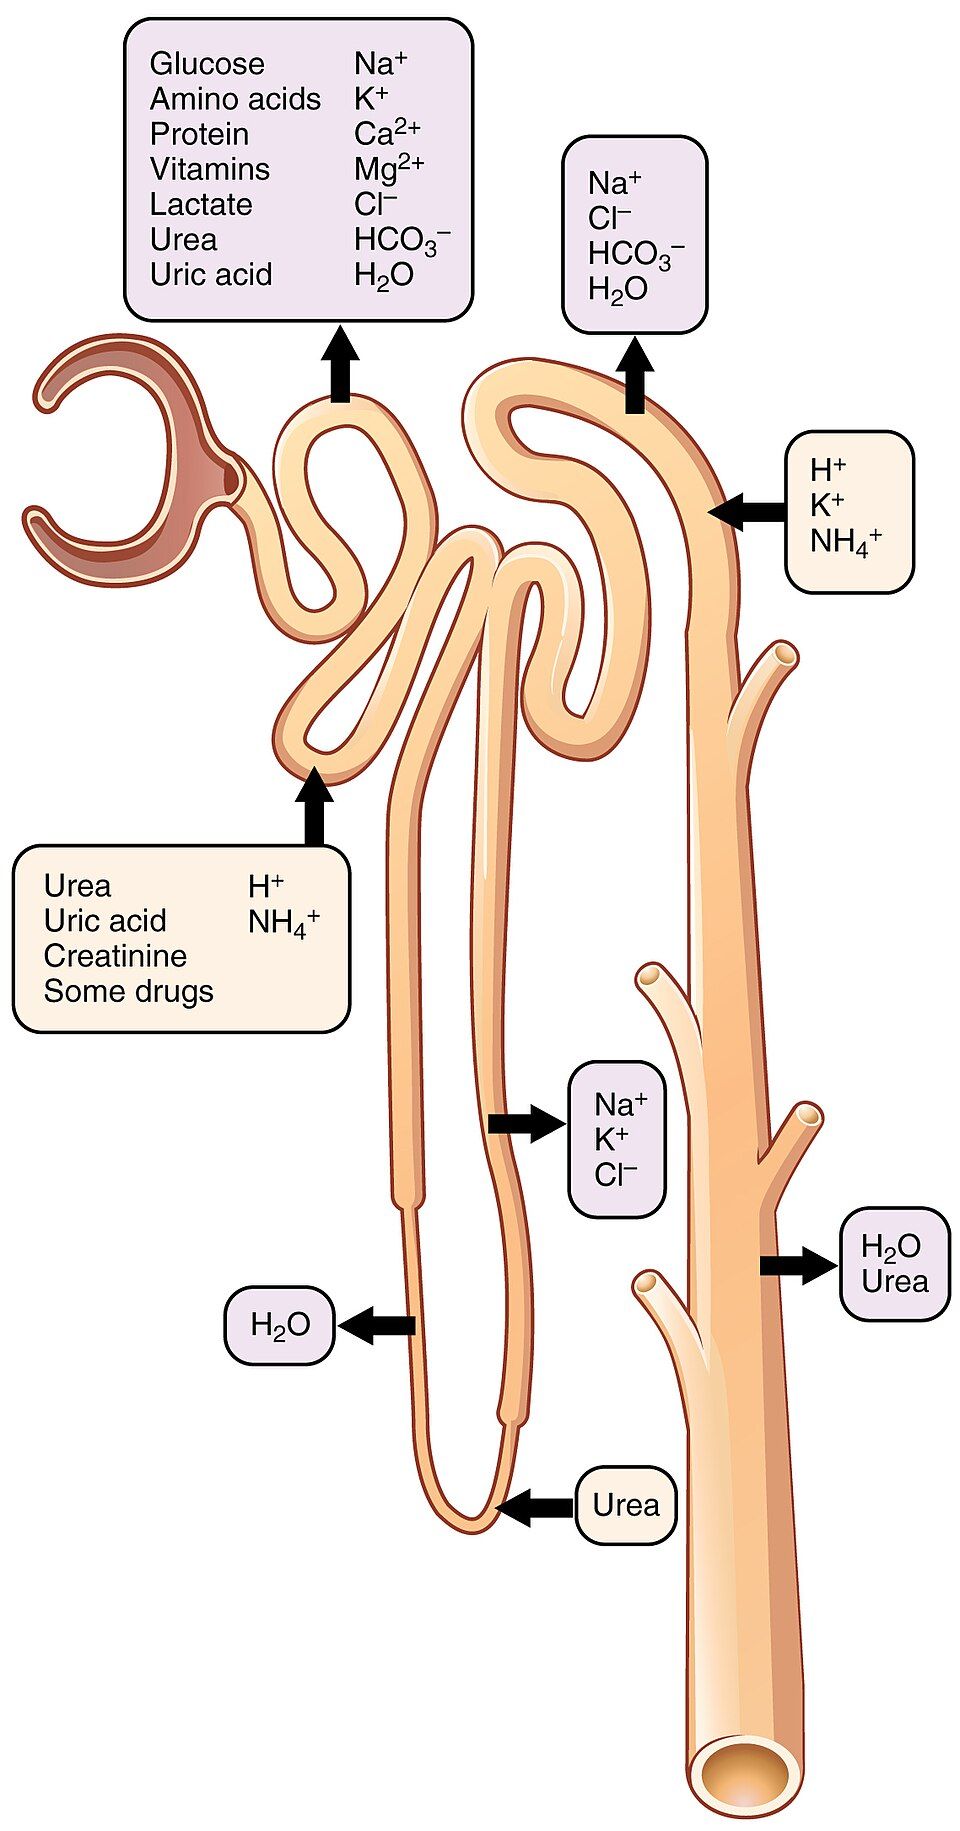
Three steps: dump, reclaim, fine-tune
The kidney's plan for making urine seems wasteful. But it is actually very smart: dump almost everything out, then take back what you want. This happens in three steps, in order.
First, glomerular filtration pushes a large amount of fluid out of the blood and into the tubule. Second, tubular reabsorption takes back the water and useful substances. It returns them to the blood. Third, tubular secretion moves a few extra wastes and ions from the blood into the tubule to be thrown out. (Ions are tiny charged particles, like sodium.) Whatever is left in the tubule after all three steps is the urine. The smart part is control. The kidney filters a huge amount and then takes back only what it chooses. So it can adjust each substance on its own.
Step one: glomerular filtration
Filtering is driven by pressure alone. Blood enters the glomerulus under high pressure. That is because a wide afferent arteriole feeds in, and a narrow efferent one drains out. Think of a garden hose with your thumb over the end. The pressure forces fluid across the filtration membrane into the capsule.
All the glomeruli together make filtrate at a certain speed. This is called the glomerular filtration rate (GFR). It is normally about 125 mL per minute, which adds up to about 180 L a day. GFR is like a vital sign for the kidney. A falling GFR is the main measure of kidney failure. The kidney guards its GFR closely. It widens or narrows the afferent and efferent arterioles. This keeps filtering steady even when blood pressure goes up and down.
Steps two and three: reabsorption and secretion
If filtering were the whole story, you would pee 180 liters a day. You would dry out and die very quickly. Reabsorption, taking fluid back, saves you. The PCT alone takes back about 65% of the filtered water and sodium. It also takes back almost 100% of the glucose and amino acids. (Glucose is blood sugar. Amino acids are the building blocks of protein.) These nutrients are too valuable to waste.
The loop of Henle makes the medulla salty. Later, that salt helps pull water back by osmosis, the flow of water toward saltier places. By the time filtrate reaches the collecting duct, only small changes are left.
Meanwhile, secretion runs the other way. It moves substances from the blood into the tubule. These include hydrogen ions (H⁺) to control pH, extra potassium (K⁺), and many drugs and poisons. Secretion is how the kidney clears things that do not filter well.
| Process | Direction | Where | What moves |
|---|---|---|---|
| Filtration | Blood → tubule | Renal corpuscle | Water & small particles (pushed by pressure, about 125 mL/min) |
| Reabsorption | Tubule → blood | Whole tubule (mostly PCT) | Water, Na⁺, glucose, amino acids: the useful things |
| Secretion | Blood → tubule | PCT, DCT, collecting duct | H⁺, K⁺, drugs, poisons: extra waste |
Step through filtration, reabsorption and secretion in the interactive below.
- Making urine has three steps. Filtration goes from blood→tubule. Reabsorption goes from tubule→blood. Secretion goes from blood→tubule.
- GFR is about 125 mL/min. It is the key measure of how well the kidneys work. The kidney changes the width of its arterioles to keep GFR steady.
- The PCT takes back the most: about 65% of water and Na⁺, and almost all glucose. Secretion clears H⁺, K⁺ and drugs.
Section 5Hormonal control
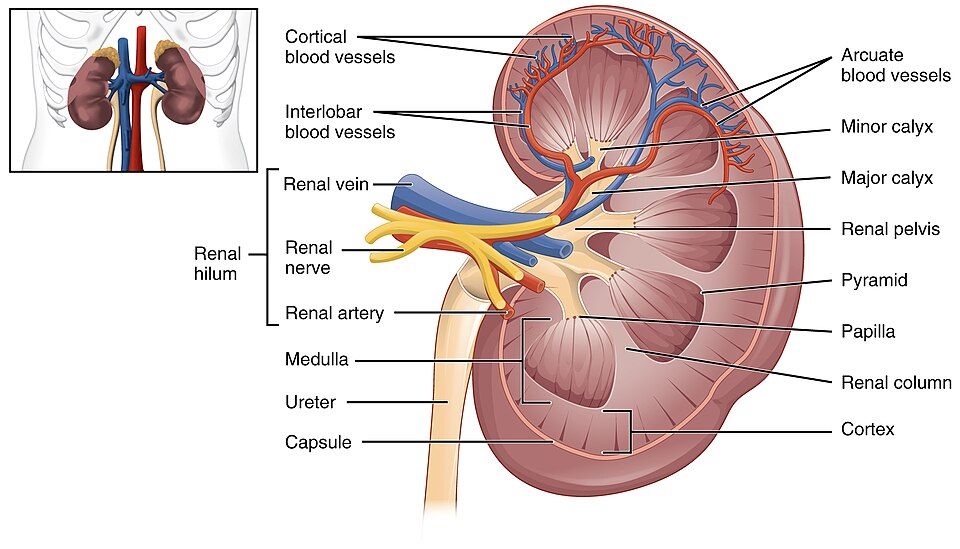
Water: antidiuretic hormone
The kidney does not decide on its own how much water to keep. The body sends it signals with hormones. The most important water hormone is antidiuretic hormone (ADH), also called vasopressin. Antidiuretic means "against making lots of urine."
When you are low on water, your blood gets too concentrated. The hypothalamus in the brain senses this. Then the back part of the pituitary gland releases ADH. ADH acts on the collecting duct. It puts water channels called aquaporins into the duct's wall. Water then flows out through them into the salty medulla. The result is a small amount of concentrated urine, and your body saves water.
When you have plenty of water, ADH drops. The channels are removed, and water stays in the tubule. You make a large amount of dilute, or watery, urine. Alcohol blocks ADH. That is why a night of drinking leaves you dried out.
Salt and pressure: the renin–angiotensin–aldosterone system
To control blood pressure, the kidney manages sodium. Here is why. Where sodium goes, water follows. More water means more blood volume. More volume means higher pressure. The main system for this is the renin–angiotensin–aldosterone system (RAAS).
When blood pressure drops, the kidney's granular cells release renin. Renin changes a protein made by the liver into angiotensin I. Then an enzyme in the lungs, called ACE, changes it into angiotensin II. (An enzyme is a protein that speeds up a chemical change.)
Angiotensin II is powerful. First, it squeezes blood vessels narrower. This raises pressure right away. Second, it tells the adrenal gland to release aldosterone. Aldosterone tells the DCT and collecting duct to take back more sodium, and water follows it. At the same time, they get rid of potassium. More sodium taken back means more water kept. That means more blood volume and higher pressure. This boost is slower, but it lasts.
Letting go: atrial natriuretic peptide
Every control needs an opposite. Sometimes blood volume gets too high. Then the walls of the heart's upper chambers, the atria, get stretched. They release atrial natriuretic peptide (ANP). It does the reverse of RAAS. It makes you lose sodium and water in the urine. This lowers blood volume and pressure.
So ADH tunes water, RAAS raises pressure, and ANP lowers it. The kidney sits in the middle of this constant push and pull. It keeps your blood volume steady, and so it keeps your blood pressure steady too.
| Hormone | Trigger | Effect on the kidney | Net result |
|---|---|---|---|
| ADH (vasopressin) | Blood that is too concentrated or too low in volume | Adds aquaporins to the collecting duct → takes back water | Less urine, more concentrated. Water is saved. |
| Aldosterone | Angiotensin II; high K⁺ | Takes back Na⁺ (and water) and gets rid of K⁺ | ↑ blood volume & pressure |
| Renin / angiotensin II | Low blood pressure | Narrows blood vessels. Causes aldosterone release. | ↑ blood pressure (fast & slow) |
| ANP | High blood volume (atria stretched) | Makes you lose more Na⁺ and water in urine | ↓ blood volume & pressure |
Tap each hormone in the interactive. See how it shifts water and salt.
- ADH controls water. It puts aquaporins in the collecting duct. This makes urine concentrated and saves water.
- The RAAS controls sodium and pressure: low pressure → renin → angiotensin II → aldosterone → Na⁺ and water taken back → more blood volume and higher pressure.
- ANP works against RAAS. It gets rid of Na⁺ and water when blood volume is high. Together, these hormones keep blood pressure steady.
Section 6Storing and voiding urine
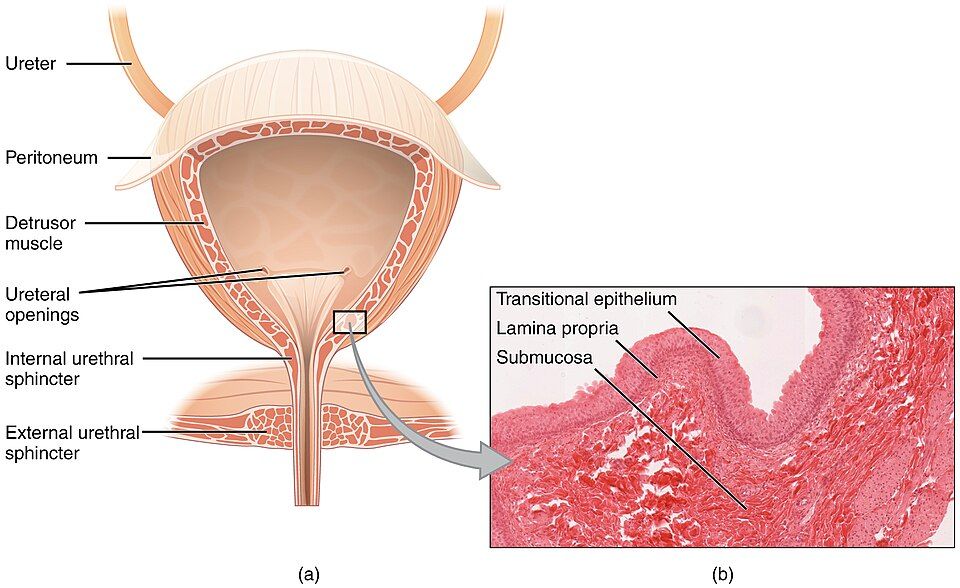
The storage plumbing
Once urine leaves the kidney, it is finished. The rest is just moving and storing it. The ureters squeeze urine down to the bladder with waves of muscle called peristalsis. So urine keeps moving even when you lie down.
The urinary bladder is a stretchy bag made of muscle. It is lined with transitional epithelium, a lining that can stretch flat as the bladder fills. When the bladder is empty, the lining falls into folds called rugae. The muscle in the bladder wall is the detrusor muscle. A smooth triangle on the bladder floor, the trigone, funnels urine toward the exit.
Two gates guard the way out. The internal urethral sphincter is smooth muscle. It works on its own, without your control. The external urethral sphincter is skeletal muscle. You control it on purpose. The urethra then carries urine out. It is short in females, about 4 cm. It is longer in males, about 20 cm, because it also runs through the penis.
The micturition reflex
Emptying the bladder starts as a simple spinal reflex. The bladder fills to about 200–400 mL. Then stretch receptors in the detrusor wall fire. These sensors send signals to the lowest (sacral) part of the spinal cord.
The cord answers with a parasympathetic command. This is part of the "rest and digest" nerve system. The command does two things at once. It contracts the detrusor muscle to squeeze the bladder. It also relaxes the internal sphincter to open the first gate. This is the micturition reflex. (Micturition means peeing.) A baby's nervous system has not yet learned control. So in a baby, the reflex just runs to the end, and the baby pees.
The voluntary override
The second gate is what makes you different from a baby. The external urethral sphincter is skeletal muscle that you can hold shut on purpose. Higher brain centers can allow peeing or put it off. These include a control area in the pons, a part of the brainstem, guided by the cortex.
Say the reflex fires at a bad time. Your brain keeps the external sphincter squeezed, and the urge passes for a while. When you decide it is time, the brain relaxes the external sphincter. The reflex finishes, and the bladder empties. Learning this override is what "potty training" teaches. Losing it can cause many kinds of incontinence, or leaking urine. This can happen through a spinal injury, a stroke or old age.
| Step | What happens |
|---|---|
| 1. Fill | Urine collects. The detrusor stretches as the amount nears 200–400 mL. |
| 2. Sense | Stretch receptors fire and send signals to the sacral spinal cord |
| 3. Reflex | Parasympathetic nerves contract the detrusor and relax the internal sphincter |
| 4. Decide | The brain (pons and cortex) holds or lets go of the external sphincter. This is the gate you control. |
| 5. Void | The external sphincter relaxes. The bladder empties through the urethra. |
Fill the bladder and empty it in the interactive. Watch the reflex play out.
- Ureters move urine by peristalsis. The bladder stores it behind two sphincters. Its key parts are the detrusor muscle, transitional epithelium and trigone.
- The micturition reflex is a reflex of the sacral spinal cord: stretch → parasympathetic nerves → the detrusor squeezes and the internal sphincter opens.
- The external sphincter is skeletal muscle you control on purpose, through the pons and cortex. This override lets you choose when to pee.
The chapter in one breath
- The urinary system has four organs: two kidneys, two ureters, one bladder and one urethra. They filter blood, balance water and salts, and drain urine. The kidneys also help set blood pressure, red blood cell count and vitamin D.
- A kidney has cortex on the outside and medulla (pyramids) inside. Urine drains papilla → calyces → renal pelvis → ureter. Blood passes through two capillary beds in series.
- The nephron is the working unit. There are about 1 million per kidney. Each has a renal corpuscle that filters. It also has a tubule that makes the urine (PCT → loop of Henle → DCT → collecting duct).
- Urine forms in three steps. Filtration goes from blood→tubule. Reabsorption goes from tubule→blood. Secretion goes from blood→tubule. GFR is about 125 mL/min.
- ADH saves water. The RAAS keeps sodium to raise blood pressure. ANP gets rid of sodium and water to lower it.
- The bladder stores urine. The micturition reflex lets it out. The external sphincter, which you control, lets you decide when to pee.
- Above all, the kidney is the body's great homeostatic organ. It turns the idea of a steady inside into a working machine.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back when a word trips you up.
- Aldosterone
- A hormone from the adrenal gland. It tells the distal tubule and collecting duct to take back sodium (and water with it) and get rid of potassium. This raises blood volume and pressure.
- Antidiuretic hormone (ADH)
- A hormone from the back part of the pituitary gland. It puts aquaporins into the collecting duct so water is taken back. This makes concentrated urine and saves body water.
- Calyx
- A cup-shaped space that catches urine dripping from a renal papilla. Minor calyces join into major calyces, which drain into the renal pelvis.
- Collecting duct
- The last part of the tubule, shared by many nephrons. Here ADH controls the last bit of water taken back before urine reaches the papilla.
- Detrusor muscle
- The smooth muscle of the bladder wall. It squeezes to push urine out during the micturition reflex.
- Glomerular filtration rate (GFR)
- The amount of filtrate all the glomeruli make each minute, normally about 125 mL/min. It is the main measure of how well the kidneys work.
- Glomerulus
- The high-pressure ball of capillaries inside the renal corpuscle. Here blood is filtered into the glomerular capsule.
- Juxtaglomerular apparatus
- The spot where a nephron's rising limb meets its afferent arteriole. Its cells sense salt and pressure and release renin.
- Loop of Henle
- The hairpin part of the tubule, with a part going down and a part going up. It makes the medulla salty, which is needed to concentrate urine.
- Micturition
- Peeing, or emptying the bladder. A spinal stretch reflex starts it, and you can allow it or put it off on purpose.
- Nephron
- The tiny working unit of the kidney, with about 1 million per kidney. It is made of a renal corpuscle and a renal tubule.
- Podocyte
- An octopus-shaped cell in the filtration membrane. Its "feet" form narrow filtration slits that help hold back proteins.
- Proximal convoluted tubule (PCT)
- The first part of the tubule after the corpuscle. It takes back most of the water, sodium, glucose and amino acids.
- Reabsorption (tubular)
- The movement of water and useful substances out of the tubule and back into the blood.
- Renal corpuscle
- The filtering part of the nephron. It is the glomerulus plus the glomerular (Bowman's) capsule around it.
- Renin
- An enzyme the kidney releases when blood pressure falls. It starts the chain of steps that makes angiotensin II and aldosterone.
- Retroperitoneal
- Sitting behind the peritoneum, the lining of the belly, against the back wall. The kidneys and ureters are found here.
- Secretion (tubular)
- The movement of wastes and ions (H⁺, K⁺, drugs) out of the blood and into the tubule to be thrown out.
- Trigone
- The smooth triangle on the bladder floor. Its corners are the two ureter openings and the opening to the urethra.
- Ureter
- The muscle tube that carries urine from a kidney to the bladder by peristalsis.
- Urethra
- The tube that carries urine from the bladder to the outside. It is short in females and longer in males.
Check yourself
Fluid, Electrolyte & Acid-Base Balance
You are, quite truly, mostly water. Staying alive is largely about keeping three things in very narrow ranges. These are that water, the salts dissolved in it, and how acidic it is. This chapter follows the fluid. First you will see the spaces, or compartments, where it lives. Then you will see the daily balance of what comes in and what goes out. Next come the electrolytes, the charged particles that float in the fluid. Then comes pH, a measure of how acidic a fluid is. Every enzyme in your body depends on it.
You will meet the buffers that catch stray acid in an instant. You will see the lungs and kidneys finish the job over minutes and days. You will also meet the four classic acid-base disorders that show up when the whole system slips. By the end, you will be able to read a set of blood numbers. You will be able to say plainly what has gone wrong and how the body is fighting back.
By the end of this chapter you can
- Name the body's fluid compartments. Estimate how much of the body's water is in each. Describe how their ions differ.
- Balance a day's water intake against output. Name the ways water comes in and goes out, including insensible loss (water you lose without noticing).
- Explain how thirst and antidiuretic hormone keep total body water steady.
- List the main electrolytes. Say where each is found, what it does, and which hormone controls it.
- Write the bicarbonate buffer equation. Explain how a buffer fights a change in pH.
- Rank the body's three lines of acid-base defense by speed. Describe how each one works.
- Sort the four acid-base disorders by cause and direction. Predict how the body makes up for each.
- Read a simple set of blood gas numbers and name the acid-base problem.
Section 1The fluid compartments
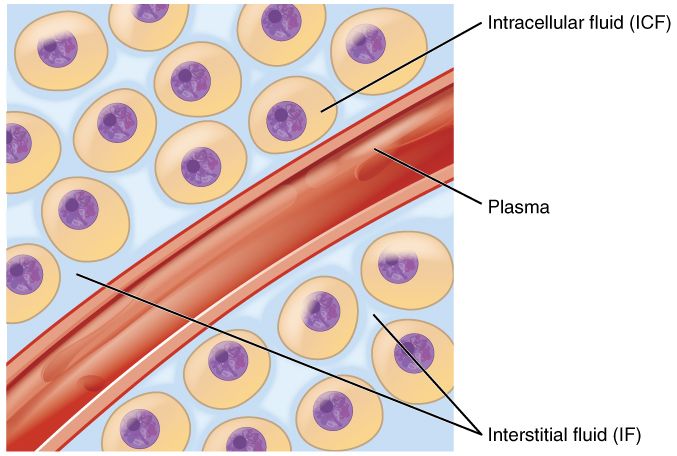
How much of you is water
In a healthy adult, about 60% of body mass is water. That is about 42 liters in a person who weighs 70 kilograms. The number is not fixed. It is higher in babies, near 75%. It is lower in older adults.
Fat tissue holds very little water. So a leaner body is a wetter body. On average, women carry a bit more fat for their size than men. So their water share is a few points lower. This total body water, all the water in your body, is not one big puddle. It is split into compartments. Living membranes separate them. Fluid balance is really about how water and dissolved substances move between these compartments.
Two great pools, and a smaller subdivision
The first and biggest split is made by the cell membrane. About two-thirds of your water is inside your cells. This is the intracellular fluid, or ICF. (Intra means "inside.") The other one-third is outside the cells. This is the extracellular fluid, or ECF. (Extra means "outside.")
The walls of the blood vessels split the ECF again. Most of it bathes the tissues directly. This is interstitial fluid, the water in the gaps between cells. A smaller share is the plasma, the fluid part of blood inside the vessels. A tiny extra part is the transcellular fluid. It includes special pools like the fluid around the brain and spinal cord, joint fluid, and the fluid in the front of the eye.
| Compartment | Share of total body water | Where it is |
|---|---|---|
| Intracellular (ICF) | About 2/3 (about 40% of body weight) | Inside all the cells |
| Extracellular (ECF) | About 1/3 (about 20% of body weight) | Outside the cells. It is split into the two parts below. |
| · Interstitial | About 3/4 of the ECF | In the spaces between cells |
| · Plasma | About 1/4 of the ECF | The fluid part of blood, inside vessels |
| Transcellular | A small extra pool | CSF (brain and spinal fluid), joint fluid, eye fluid, gut juices |
Same water, very different salt
What makes the compartments different is not the water. It is the solutes, the things dissolved in it. The ICF and ECF have very different mixes of ions. (Ions are particles with an electric charge.) The cell membrane and its pumps keep them apart.
The ECF is a salty sea, a lot like seawater. It is full of sodium (Na⁺) and chloride (Cl⁻). The ICF, on the other hand, is rich in potassium (K⁺), magnesium, phosphate and proteins with a negative charge. Every cell membrane has a sodium-potassium pump. It works around the clock to keep this difference. It pushes Na⁺ out and pulls K⁺ in. That stored difference works like a charged battery. It powers nerve signals, muscle squeezing and much of the traffic across membranes.
Water follows dissolved particles by osmosis. So the amount of dissolved particles in each compartment decides where the water goes. This amount is called osmolarity. Add salt to the ECF, and it becomes more concentrated. It pulls water out of the cells, and they shrink. Make the ECF more watery, and water rushes in. Then the cells swell. Sodium is the most common particle in the ECF. That is why it is the single biggest lever on fluid movement in the body.
Tap each compartment in the interactive below to see where the water lives.
- Water is about 60% of body mass. Leaner bodies and babies hold more. Older adults hold less.
- Two-thirds of body water is intracellular, inside cells. One-third is extracellular, outside cells. The ECF splits into interstitial fluid and plasma.
- ECF is high in Na⁺/Cl⁻. ICF is high in K⁺ and proteins. The sodium-potassium pump keeps this difference.
- Water follows dissolved particles by osmosis. So ECF sodium is the main control on where fluid moves.
Section 2Water in, water out
A ledger that must balance
Total body water stays very steady from day to day. The reason is simple bookkeeping. Over any 24 hours, water in must equal water out. A typical adult moves about 2.5 liters through this "bank account" each day.
On the intake side, most comes from what you drink, about 1.5 L. A good amount comes from water hidden in food, about 0.7 L. Fruit, vegetables and even bread are wetter than you might think. A small but real amount is made inside you. Each time a cell burns sugar or fat for energy, water is a by-product. This metabolic water adds about 0.3 L a day, without you drinking a drop.
The four ways out
Water leaves by four routes. Only one of them is closely controlled. The kidneys make urine, about 1.5 L. It is the largest output and the only one the body tightly controls.
Much of the rest is insensible loss. This is water you lose without noticing. It dries off your skin all the time. It also leaves as vapor in every breath from your lungs. Together, these add up to about 0.9 L. A small amount leaves in the feces, or poop. More pours out as sweat when you are hot or working hard. Fever, heat, exercise, throwing up and diarrhea can all make these losses soar. That is why they can upset the balance so fast.
| Direction | Route | Rough daily amount |
|---|---|---|
| In | Fluids you drink | About 1.5 L |
| In | Water in food | About 0.7 L |
| In | Metabolic water (made by your cells) | About 0.3 L |
| Out | Urine (controlled) | About 1.5 L |
| Out | Skin & lungs (insensible, not noticed) | About 0.9 L |
| Out | Feces | About 0.1 L |
Thirst and the water-saving hormone
You choose when to drink, but much of your water loss cannot be stopped. So the body controls both ends. When you lose water, the ECF gets more concentrated. Its osmolarity goes up. Tiny sensors in the hypothalamus of the brain notice this. They are called osmoreceptors. They do two things.
First, they cause thirst. This drives you to drink, which raises intake. Second, they signal the back part of the pituitary gland to release antidiuretic hormone (ADH), also called vasopressin. ADH travels to the kidney. It tells the collecting ducts to put in water channels called aquaporins. Water flows back into the blood through them. The result is a small amount of concentrated urine.
Drink too much, and the reverse happens. Osmolarity falls, and ADH switches off. The kidney then lets a large amount of watery urine flow. Thirst pulls water in, and ADH works like a tap that holds water back. Together, they keep total body water within about one percent from one day to the next.
Tap each route in the interactive. See how the body keeps water in and water out equal.
- Over a day, intake ≈ output ≈ 2.5 L. Intake is drink + food + metabolic water.
- Output is urine, the only tightly controlled route. It also includes insensible loss from skin and lungs, plus feces and sweat.
- Thirst raises intake. ADH (vasopressin) lowers output by making the kidney take back water.
- A minimum obligatory urine volume must always be passed to clear wastes.
Section 3The electrolytes
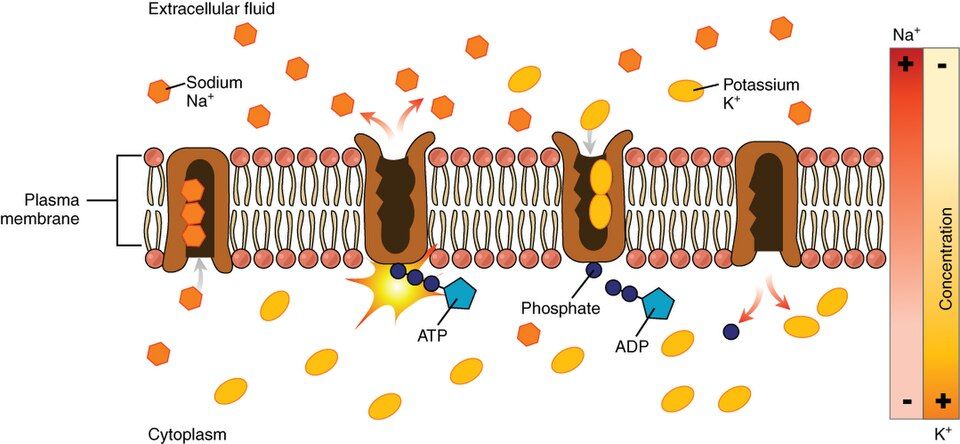
Charged particles that do the work
An electrolyte is any substance that breaks apart into charged ions when it dissolves. This lets a fluid carry an electric current. Electrolytes are the reason body fluids can carry current at all. They do much more than just float there. Their uneven spread drives every nerve impulse and every muscle contraction. It also drives every shift of water between compartments.
These jobs are very sensitive. So the body controls electrolyte levels tightly. It measures them in milliequivalents per liter (mEq/L). This unit counts electric charge, not plain weight. Ions with a positive charge are cations (Na⁺, K⁺, Ca²⁺, Mg²⁺). Ions with a negative charge are anions (Cl⁻, bicarbonate, phosphate).
The big four cations
Sodium (Na⁺) is the main cation of the ECF. It is the boss of fluid volume, because where sodium goes, water follows. Its normal level is 135–145 mEq/L. It is guarded mainly by aldosterone. This hormone from the adrenal gland tells the kidney to take back sodium.
Potassium (K⁺) is the main cation of the ICF. It sets the resting membrane potential, the small electric charge across the membrane of nerve and muscle cells at rest. Its normal range is narrow, 3.5–5.0 mEq/L. This matters a lot to the heart. Too much or too little potassium can stop it.
Calcium (Ca²⁺) is 99% stored in bone. It runs muscle contraction, blood clotting and nerve signals. Parathyroid hormone and vitamin D tune its blood level. Magnesium is a quieter partner. It helps hundreds of enzymes work. It also keeps nerves and muscles steady.
| Electrolyte | Mainly in | Key job | Main regulator |
|---|---|---|---|
| Sodium (Na⁺) | ECF | ECF volume & osmolarity; nerve and muscle signals | Aldosterone, ADH, ANP |
| Potassium (K⁺) | ICF | Resting membrane potential; heart rhythm | Aldosterone |
| Calcium (Ca²⁺) | Bone / ECF | Muscle contraction, clotting, nerves | PTH, calcitriol (active vitamin D), calcitonin |
| Chloride (Cl⁻) | ECF | Follows sodium; balances charge; stomach acid | Follows how Na⁺ is handled |
| Bicarbonate (HCO₃⁻) | ECF | The body's main pH buffer | Kidneys |
| Phosphate | ICF / bone | ATP, DNA, bone; buffer | PTH |
When the numbers drift
These ions carry electric charge. So small changes can cause big symptoms. Low sodium is called hyponatremia. (Hypo means "low," and natrium is Latin for sodium.) It draws water into brain cells. This brings confusion, headache and seizures. High sodium dries brain cells out.
Potassium problems are dangerous mainly for the heart. High potassium is hyperkalemia, and low potassium is hypokalemia. (Hyper means "high," and kalium is Latin for potassium.) Both cause arrhythmias, or uneven heartbeats, that can kill. Low calcium makes nerves too jumpy. This leads to tetany, which means muscle spasms and tingling. High calcium dulls nerves, causing weakness and confusion. Doctors check electrolytes every day for a good reason. These are the numbers that keep hearts beating and nerves firing.
Tap each electrolyte in the interactive. See where it lives and what it does.
- Electrolytes are ions (cations and anions) measured in mEq/L. They drive nerves, muscles and fluid balance.
- Sodium rules ECF volume. Potassium sets membrane potential and is vital to the heart. Calcium runs contraction, clotting and nerves.
- Aldosterone keeps sodium and gets rid of potassium. PTH and vitamin D control calcium.
- Small shifts cause big trouble: hyponatremia (brain), hyperkalemia (heart), hypocalcemia (tetany).
Section 4Blood pH and buffers
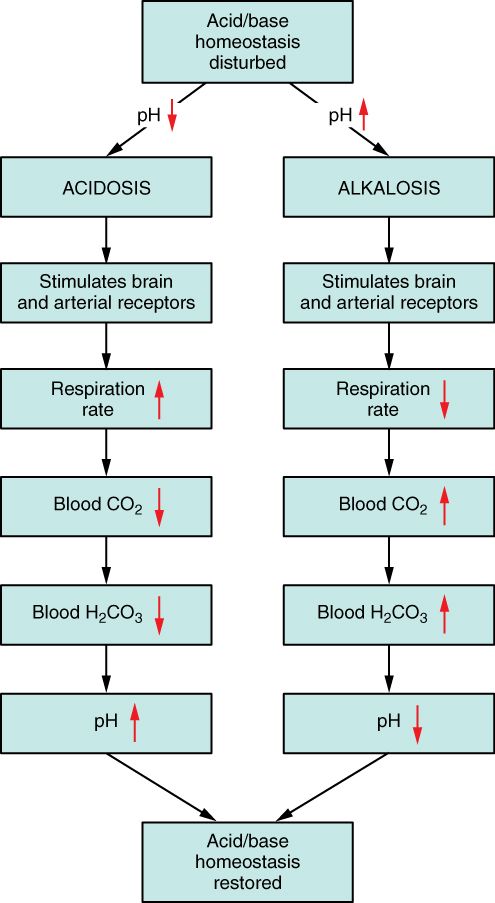
A razor-thin window
pH measures how acidic or basic a fluid is. The scale runs from 0 to 14, and 7 is neutral. Lower numbers mean more acidic. That means more free hydrogen ions (H⁺). Higher numbers mean more basic.
Blood in the arteries is kept slightly basic. It stays in the tiny band of 7.35 to 7.45. This is not a comfort zone. It is a survival zone. Below 7.35 is acidemia, or acid blood. Above 7.45 is alkalemia, or basic blood. Life is not possible outside about 6.8 to 7.8.
The stakes are high because pH bends the shape of proteins. Enzymes are proteins. So a drifting pH slows or stops the chemistry of every cell at once. The trouble is that your body makes acid all the time. Burning fuel makes carbon dioxide, which turns into acid in water. Hard work or going without food adds lactic acid and ketoacids on top.
What a buffer does
The first defense against this flood of acid is a buffer. A buffer is a pair of chemicals. It soaks up extra H⁺ when acid is added. It gives off H⁺ when base is added. This softens the swing in either direction, like a sponge.
Buffers act in an instant. But they do not remove acid from the body. They only hold on to it for a while, until the lungs or kidneys can get rid of it. The body's most important buffer is the bicarbonate system. It is summed up in one reaction worth learning:
CO₂ + H₂O ⇆ H₂CO₃ ⇆ H⁺ + HCO₃⁻
Read it both ways. When acid floods in, bicarbonate (HCO₃⁻) grabs the extra H⁺. This drives the reaction to the left, toward carbonic acid and CO₂. The lungs can breathe the CO₂ out. When base is added, carbonic acid gives up an H⁺ to replace what was lost. This drives the reaction to the right.
What makes this buffer so strong is that it is open at both ends. The lungs can blow off the CO₂ on the left. The kidneys can change the bicarbonate on the right. So the body can shift the whole equation instead of just using up the buffer.
| Buffer system | Where it works | Note |
|---|---|---|
| Bicarbonate | Blood / ECF | The main ECF buffer. It is linked to the lungs and kidneys, so it can be controlled. |
| Phosphate | Inside cells; urine | Important in the ICF and in making urine acidic |
| Protein | Cells & plasma | Biggest total capacity. Hemoglobin buffers the CO₂ carried in blood. |
Add acid or base in the interactive. Watch the bicarbonate buffer fight to hold the line.
- Blood pH in the arteries is held at 7.35–7.45. Straying from it stops enzymes from working and puts life at risk.
- A buffer soaks up or gives off H⁺ to soften pH swings right away. But it does not remove acid from the body.
- The bicarbonate buffer is CO₂ + H₂O ⇆ H₂CO₃ ⇆ H⁺ + HCO₃⁻. It is central because the lungs control CO₂ and the kidneys control HCO₃⁻.
- Phosphate and protein buffers back it up. Proteins have the biggest total buffering power.
Section 5The three lines of defense
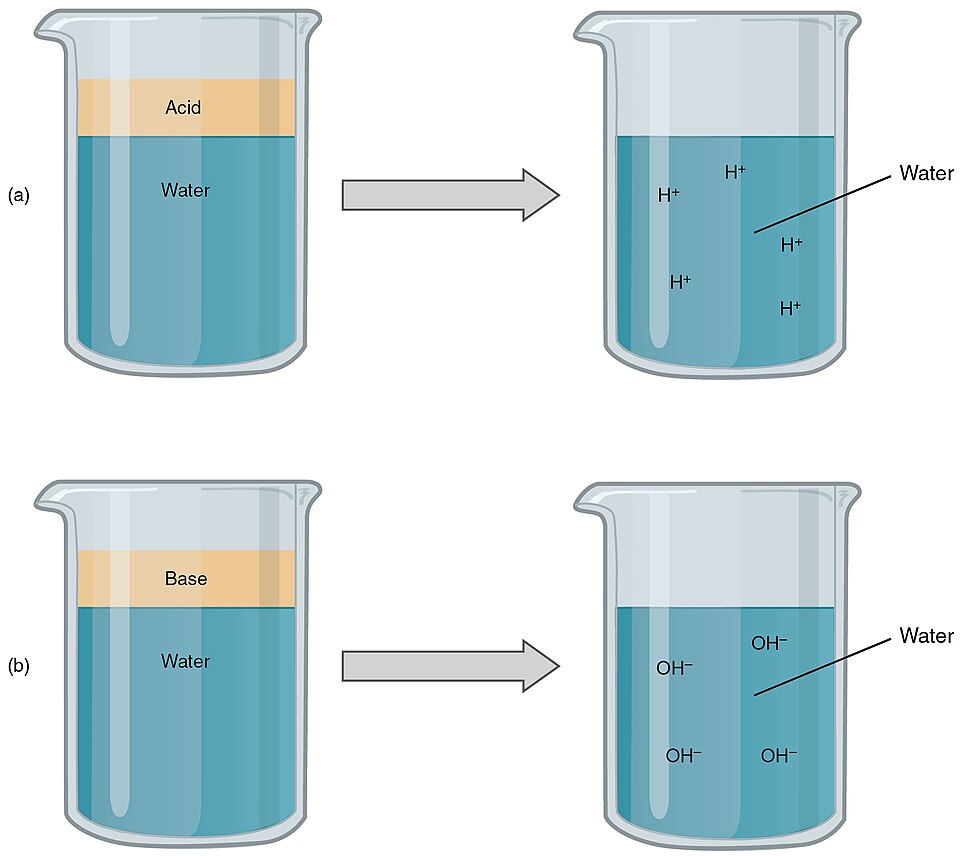
Three defenders, three clocks
The body guards its pH in three ways. Each works at a very different speed. Each one covers for the limits of the others. Think of an emergency response in stages. First comes an instant reflex. Next comes a fast fix. Last comes a slow but complete repair.
The first is chemical buffering, which we just met. It acts within seconds. But it can only handle so much. It also only hides the acid instead of removing it. The second is respiratory control, by the lungs. The third is renal control, by the kidneys. Together, they let the body soak up an acid load right away and then truly clear it.
The lungs: fast and forceful
The lungs change pH by controlling how much CO₂ stays in the blood. CO₂ forms acid, so breathing works like a pH dial. When blood gets too acidic, sensors notice the rising H⁺. They tell the breathing center in the brain to breathe faster and deeper. This blows off CO₂ and pulls the buffer equation to the left. pH climbs back up within minutes.
When blood gets too basic, breathing slows. This keeps CO₂ in and lets pH fall. This lung response is quick and very strong. But it has a built-in limit. It cannot fix a problem that the lungs caused.
The kidneys: slow and complete
The last and most thorough defender is the kidney. It can actually add or remove acid and base from the body. It secretes H⁺ into the urine. It also takes back or makes bicarbonate and returns it to the blood. This resets the whole system. But it takes hours to days, not seconds.
The kidney is the slowest line of defense. It is also the only one that can fix an imbalance for good. That is why it has the final say on blood pH. Buffers buy time. The lungs buy more time. The kidneys settle the bill.
| Line of defense | Speed | How it works | Limit |
|---|---|---|---|
| 1. Chemical buffers | Seconds | Grab or give off H⁺ on the spot | Can only handle so much; only hides the acid |
| 2. Respiratory (lungs) | Minutes | Change breathing to blow off or keep CO₂ | Cannot fix a problem caused by the lungs |
| 3. Renal (kidneys) | Hours to days | Get rid of H⁺; take back or make HCO₃⁻ | Slow, but the only complete fix |
Tap each line of defense in the interactive. Watch it act at its own speed.
- Three defenses, in order of speed: chemical buffers (seconds), respiratory (minutes), and renal (hours to days).
- The lungs tune pH by breathing out more or less CO₂. They are fast and strong, but cannot fix problems the lungs caused.
- The kidneys get rid of H⁺ and adjust bicarbonate. They are slow, but they are the only complete fix.
- When one organ system causes the problem, the other compensates, or makes up for it.
Section 6The four acid-base disorders
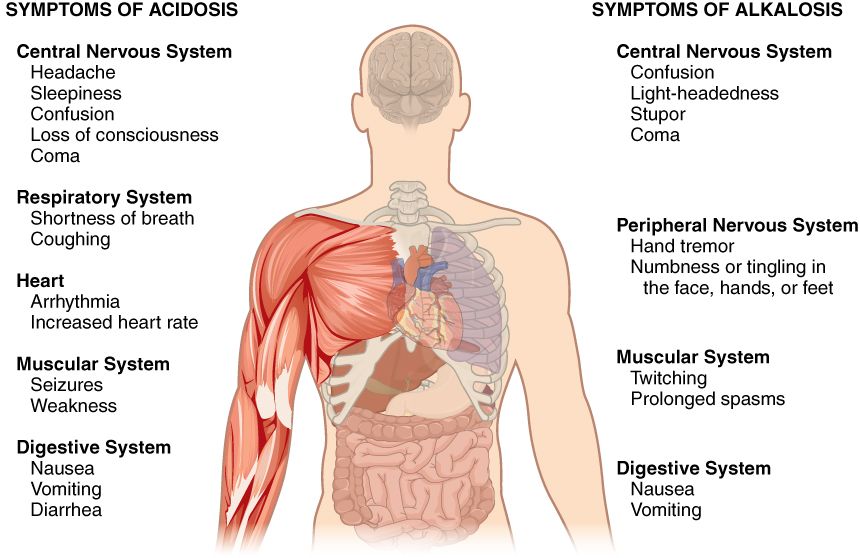
Two questions sort every case
When pH control fails, the result is always one of four core disorders. You can name any of them by asking two questions.
First, which way did the pH go? Is it too acidic? That is acidosis, with pH below 7.35. Or is it too basic? That is alkalosis, with pH above 7.45. Second, what is the cause? Is it a lung problem that changes CO₂? That is respiratory. Or is it a problem that changes bicarbonate or other acids? That is metabolic. Put those two questions together, and you get a simple two-by-two grid. Each box holds one disorder.
| Disorder | Primary change | pH | Typical causes |
|---|---|---|---|
| Respiratory acidosis | CO₂ kept in (hypoventilation, or breathing too little) | Low | COPD (a long-term lung disease), opioid overdose, chest injury |
| Respiratory alkalosis | CO₂ blown off (hyperventilation, or breathing too much) | High | Anxiety, high altitude, fever, pain |
| Metabolic acidosis | HCO₃⁻ lost or acid gained | Low | Diabetic ketoacidosis, lactic acidosis, diarrhea, kidney failure |
| Metabolic alkalosis | HCO₃⁻ gained or acid lost | High | Throwing up (loss of stomach acid), diuretics, too many antacids |
The body fights back: compensation
When one system fails, the other steps in to soften the damage. This is called compensation. If the trouble is metabolic, the lungs respond within minutes. Take diabetic ketoacidosis, where the body builds up acids called ketones. Deep, fast Kussmaul breathing shows up. This is the lungs working hard to blow off CO₂ and fight the acid.
If the trouble is respiratory, the kidneys respond over days. They keep or dump bicarbonate to nudge pH back. Compensation can be partial, with pH still not normal. Or, given time, it can be nearly full. Then pH is back in range, but the other numbers are still off. It never overcorrects past normal. It also never cures the cause. It only buys the patient time.
Reading the numbers
To read a blood gas result, look at three values in order. First is the pH. Which way is it off? Next is the CO₂, the lung number. Last is the bicarbonate, the metabolic number. Then ask which of the two fits the pH.
Say the pH is low and the CO₂ is high. Then the lungs are to blame. This is respiratory acidosis. Now say the pH is low and the bicarbonate is low. Then metabolism is to blame. This is metabolic acidosis. The value that moves along with the problem points to its cause.
Tap a box in the interactive. Explore each of the four disorders by its cause and direction.
- The four disorders come from two questions: direction (acidosis or alkalosis) × cause (respiratory or metabolic).
- Respiratory problems change CO₂. Metabolic problems change bicarbonate.
- Compensation uses the other organ system. The lungs help with metabolic problems (Kussmaul breathing). The kidneys help with respiratory ones.
- Read the numbers with ROME. In respiratory problems, pH and CO₂ move in opposite ways. In metabolic problems, pH and HCO₃⁻ move the same way.
The chapter in one breath
- Water is about 60% of body mass. It is split two-thirds intracellular and one-third extracellular (interstitial fluid plus plasma).
- The compartments differ in what is dissolved in them. ECF is rich in Na⁺/Cl⁻, and ICF is rich in K⁺. Water follows dissolved particles by osmosis.
- Each day, intake equals output at about 2.5 L. Thirst raises intake, and ADH lowers output. This holds total body water steady.
- Electrolytes drive nerves, muscles and fluid balance. Sodium rules volume, potassium rules the heart, and calcium rules contraction. Aldosterone keeps Na⁺ and dumps K⁺.
- Blood pH is held at 7.35–7.45 by the bicarbonate buffer, CO₂ + H₂O ⇆ H₂CO₃ ⇆ H⁺ + HCO₃⁻.
- Three defenses guard pH: buffers (seconds), lungs changing CO₂ (minutes), and kidneys changing HCO₃⁻ (days).
- When they fail, you get four disorders: respiratory or metabolic, and acidosis or alkalosis. You read them with ROME. Compensation softens them.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back when a word trips you up.
- Acidosis
- When blood pH falls below 7.35. It is respiratory when CO₂ builds up, and metabolic when bicarbonate is lost or acid is gained.
- Aldosterone
- A hormone from the adrenal gland. It makes the kidney take back sodium (and water) and get rid of potassium, which raises ECF volume and blood pressure.
- Alkalosis
- When blood pH rises above 7.45. It is respiratory when too much CO₂ is lost, and metabolic when bicarbonate is gained or acid is lost.
- Antidiuretic hormone (ADH)
- A hormone from the back part of the pituitary gland, also called vasopressin. It makes the kidney take back water, so urine is concentrated and body water is saved.
- Bicarbonate (HCO₃⁻)
- The main buffer anion of the ECF. It is the metabolic part of the bicarbonate buffer system, and the kidneys control it.
- Buffer
- A pair of chemicals that grabs extra H⁺ or gives it off to resist changes in pH. It acts right away but does not remove acid from the body.
- Compensation
- When one organ system (lungs or kidneys) fights a pH problem caused by the other. It eases the problem but does not cure it.
- Electrolyte
- A substance that breaks into charged ions in water. It lets fluids carry current and drives nerves, muscles and fluid balance.
- Extracellular fluid (ECF)
- The one-third or so of body water outside the cells. It is made of interstitial fluid and plasma, and it is rich in sodium and chloride.
- Insensible loss
- Water you lose without noticing. It dries off the skin and leaves as vapor in the breath you breathe out.
- Interstitial fluid
- The fluid outside cells that fills the spaces between them. It is the biggest part of the ECF.
- Intracellular fluid (ICF)
- The two-thirds or so of body water inside the cells. It is rich in potassium, magnesium, phosphate and proteins.
- Metabolic water
- Water made inside cells when they burn fuel for energy. It is a small daily source of water.
- Osmolarity
- How many particles are dissolved in a fluid. It decides which way water moves by osmosis.
- pH
- A 0–14 scale of how acidic something is, based on how many hydrogen ions it has. Blood is held at 7.35–7.45.
- Potassium (K⁺)
- The main cation inside cells. It sets the resting membrane potential and is vital for a normal heart rhythm.
- Respiratory acidosis
- A fall in pH caused by breathing too little (hypoventilation), which keeps CO₂ in. It happens in COPD or opioid overdose.
- Sodium (Na⁺)
- The main cation outside cells. It is the master control of ECF volume and osmolarity, and aldosterone mainly controls it.
- Thirst
- The urge to drink. Sensors in the hypothalamus trigger it when the ECF gets too concentrated.
- Total body water
- All the water in the body, about 60% of an adult's mass. It is split between the fluid inside and outside cells.
Check yourself
The Reproductive System
Every other system in this book works to keep you alive. The reproductive system looks past you. Its job is to make a new person. To do that, your body does something no other tissue does. It builds a special cell called a gamete, a sex cell such as a sperm or an egg. A gamete carries exactly half of your genetic instructions. So when a sperm meets an egg, the full set comes back together.
In this chapter you will walk through both body plans. You will follow the male path from testis to exit, and the female path from ovary to uterus. You will see the two "production lines" that turn stem cells into gametes. They are spermatogenesis, the making of sperm, and oogenesis, the making of eggs. You will also track the rise and fall of hormones in the menstrual cycle, the monthly cycle of the female body. Under all of it sits one clever kind of cell division, meiosis. We save it for last. Once you see it, the rest of the chapter clicks into place.
By the end of this chapter you can
- Trace the path of sperm from the seminiferous tubules to the urethra. Name the glands that add fluid along the way.
- Describe spermatogenesis. Tell how one diploid stem cell becomes four haploid sperm, where it happens, and how long it takes.
- Name the main female reproductive organs. Give the job of the ovary, uterine tube, uterus, and the layers of the uterus.
- Explain oogenesis. Tell how its unequal divisions and its long, lifelong pause differ from sperm making.
- Put the phases of the ovarian and uterine cycles in order. Match each phase to its main hormone (FSH, LH, estrogen, progesterone).
- Tell meiosis apart from mitosis. Explain how crossing over and independent assortment make each gamete different.
- Define diploid and haploid. Explain why cutting the number of chromosomes in half is key to making a baby.
Section 1Male reproductive anatomy
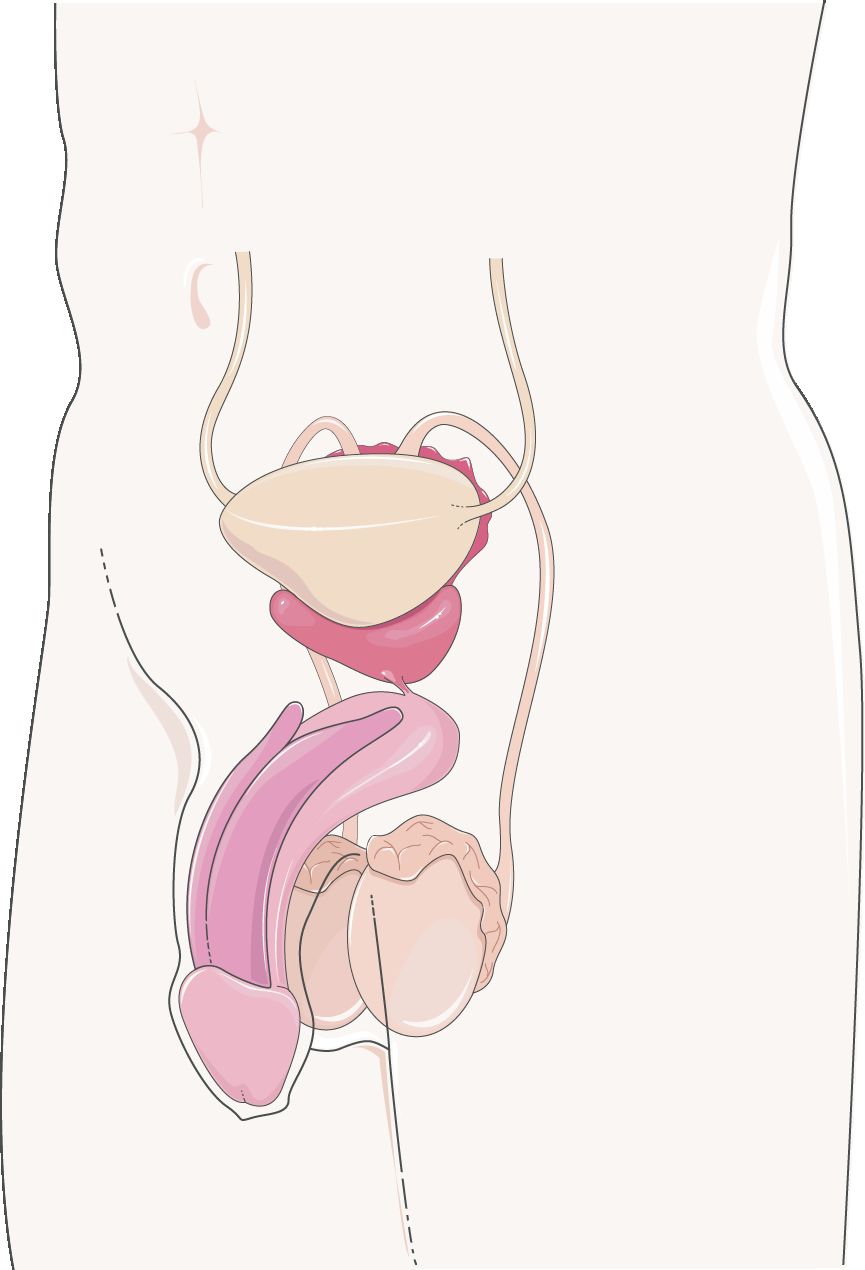
Two jobs: make sperm, deliver sperm
The male system has a simple task. It makes sperm, the male sex cells. Then it delivers them to the female body in a fluid that feeds them. Every part of the male anatomy helps with one of these two jobs.
Sperm are made in the two testes. The testes hang outside the body wall in a skin sac called the scrotum. That spot is no accident. Sperm making needs a temperature a few degrees cooler than the core of the body. A small muscle raises and lowers the testes to keep them at the right heat. So the scrotum works like a thermostat. Inside each testis are tightly coiled tubes called seminiferous tubules. Sperm are made along the walls of these tubes.
Following the road out
New sperm cannot swim yet, and they cannot fertilize an egg. First they move into the epididymis. This is a comma-shaped coil of tube that lies over the back of each testis. Sperm stay here for about two weeks. They grow up, learn to swim, and are stored.
Next they enter the ductus (vas) deferens. This muscular tube climbs out of the scrotum and loops over the bladder. It then joins the duct of a gland called the seminal vesicle. Together they form the ejaculatory duct. This short duct passes through the prostate. It empties into the urethra, the last tube, which carries semen out through the penis. In males the urethra is shared plumbing. It carries both urine and semen, but never at the same time.
| Structure | Role in the journey | Note |
|---|---|---|
| Seminiferous tubules | Where sperm are made | Coiled inside each testis |
| Epididymis | Sperm grow up, learn to swim, and are stored | About 6 m of coiled tube on the testis |
| Ductus (vas) deferens | Pushes sperm toward the urethra | Cut and tied in a vasectomy |
| Ejaculatory duct | Mixes sperm with fluid from the seminal vesicle | Passes through the prostate |
| Urethra | Carries semen (and urine) out | Shared tube in males |
The glands that make semen
Sperm are only a small part of semen, the fluid that leaves the body. Most of it is fluid from three kinds of helper glands. Each fluid has a job.
The two seminal vesicles add the most. Their fluid is thick and full of sugar. The sugar, called fructose, fuels the sperm's tails. The single prostate gland wraps around the urethra just below the bladder. It adds a milky fluid that is slightly alkaline, the opposite of acid. This helps sperm live through the acid in the female body. Last, the small bulbourethral glands give off a clear fluid before the rest. It makes the urethra slippery and cancels out any acid left from urine. Together these fluids wake up the sperm, feed them, and protect them for the trip.
Tap each part in the interactive. Trace the path sperm take from where they are made to the exit.
- Sperm are made in the seminiferous tubules of the testes. The testes sit in the scrotum to stay a bit cooler than the body.
- The road out runs testis → epididymis → ductus deferens → ejaculatory duct → urethra.
- Three glands add fluid. The seminal vesicles add fructose. The prostate adds alkaline fluid. The bulbourethral glands add a slippery fluid.
- In males the urethra is shared plumbing for both urine and semen.
Section 2Spermatogenesis
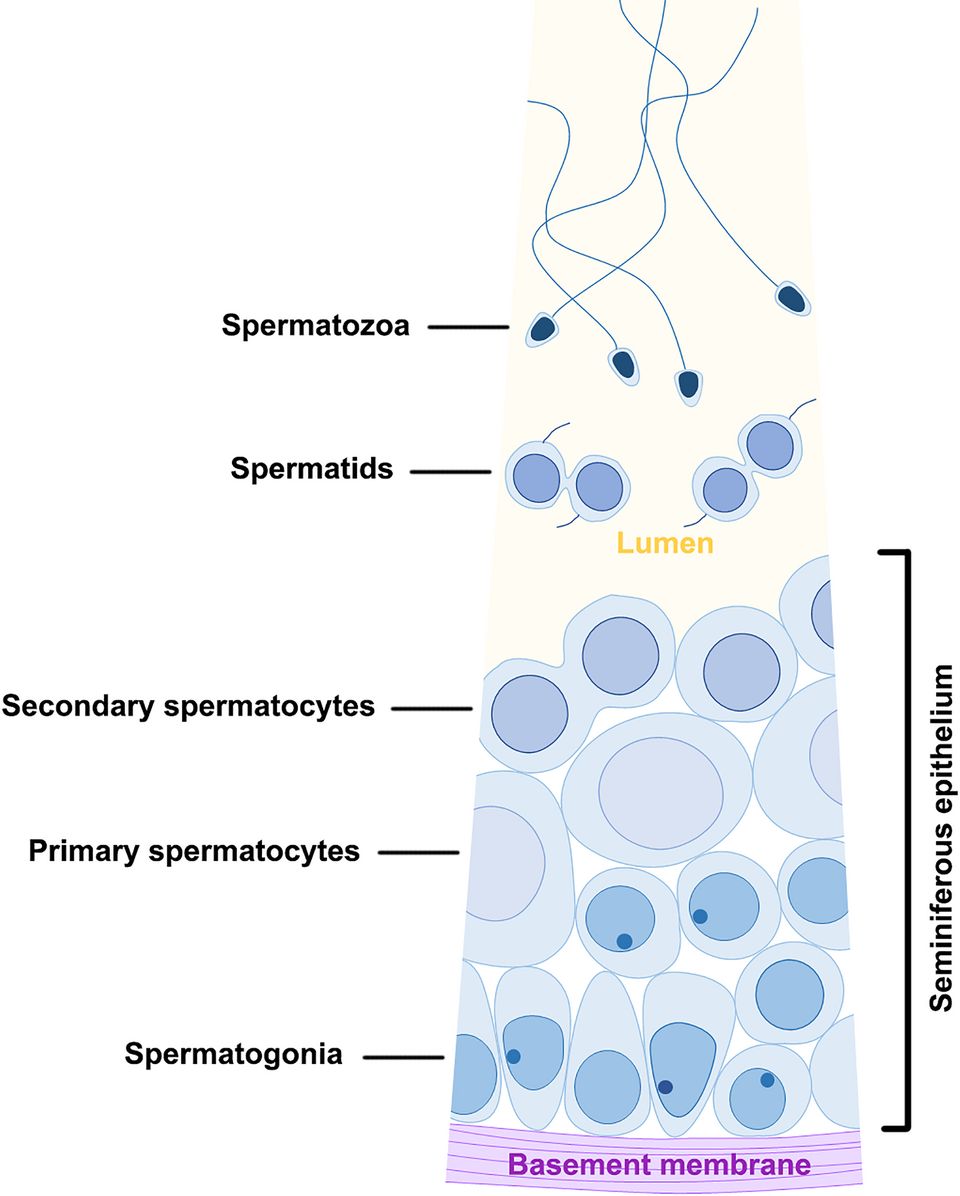
Turning a stem cell into a swimmer
Spermatogenesis is the making of sperm. Think of it as an assembly line. It turns a diploid stem cell into grown-up sperm. It runs all the time along the walls of the seminiferous tubules, from puberty on.
It starts with a spermatogonium. This is a stem cell with the full 46 chromosomes. A full set like this is called diploid, or 2n. When a spermatogonium divides, one daughter cell stays behind as a stem cell. That is why a male never runs out. The other daughter becomes a primary spermatocyte. It is now set on the path to becoming sperm. It enters meiosis, the special division that cuts the number of chromosomes in half.
Two divisions, four cells
The math here is neat. The primary spermatocyte finishes meiosis I and becomes two secondary spermatocytes. Each one now has the haploid number, or half set (n = 23). Each of those then finishes meiosis II. That gives a total of four spermatids. In sperm making, the divisions are equal. Every cell gets a fair share of cytoplasm, the jelly inside the cell. So one starting cell makes four useful cells. Egg making is not like this.
Spermatids are round and cannot move. They still must be remodeled into sleek sperm. This last step is called spermiogenesis. The cell sheds extra cytoplasm. It packs its DNA into a small head. It puts a cap full of enzymes on the head, called the acrosome. And it grows a whip-like tail, the flagellum, to swim with. A middle piece packed with mitochondria, the cell's power plants, gives energy for the trip.
| Stage | Chromosomes | What happens |
|---|---|---|
| Spermatogonium | Diploid (2n) | Stem cell; one daughter stays a stem cell |
| Primary spermatocyte | Diploid (2n) | Enters and finishes meiosis I |
| Secondary spermatocyte | Haploid (n) | Two cells; finish meiosis II |
| Spermatid | Haploid (n) | Four cells; round and cannot swim |
| Sperm (spermatozoon) | Haploid (n) | Head + acrosome + midpiece + tail |
Helped along by nurse cells
The growing sperm cells do not look after themselves. Tall Sustentacular (Sertoli) cells sit among them. They are also called nurse cells. They feed the growing sperm. They also form the blood–testis barrier. This wall keeps the immune system from attacking sperm as if they were germs.
Between the tubules sit the interstitial (Leydig) cells. They make testosterone. This hormone drives sperm making. It also causes male traits such as a deep voice and facial hair. The whole process, from spermatogonium to finished sperm, takes about 64 to 74 days. A healthy male makes hundreds of millions of sperm every day.
Step through each division in the interactive. Watch a stem cell become four swimming sperm.
- A diploid spermatogonium makes four haploid sperm through two equal divisions of meiosis.
- Spermiogenesis reshapes round spermatids into sleek sperm with an acrosome, midpiece, and tail.
- Sertoli cells care for the sperm and form the blood–testis barrier. Leydig cells make testosterone.
- The full process takes about 64–74 days, and it never stops.
Section 3Female reproductive anatomy
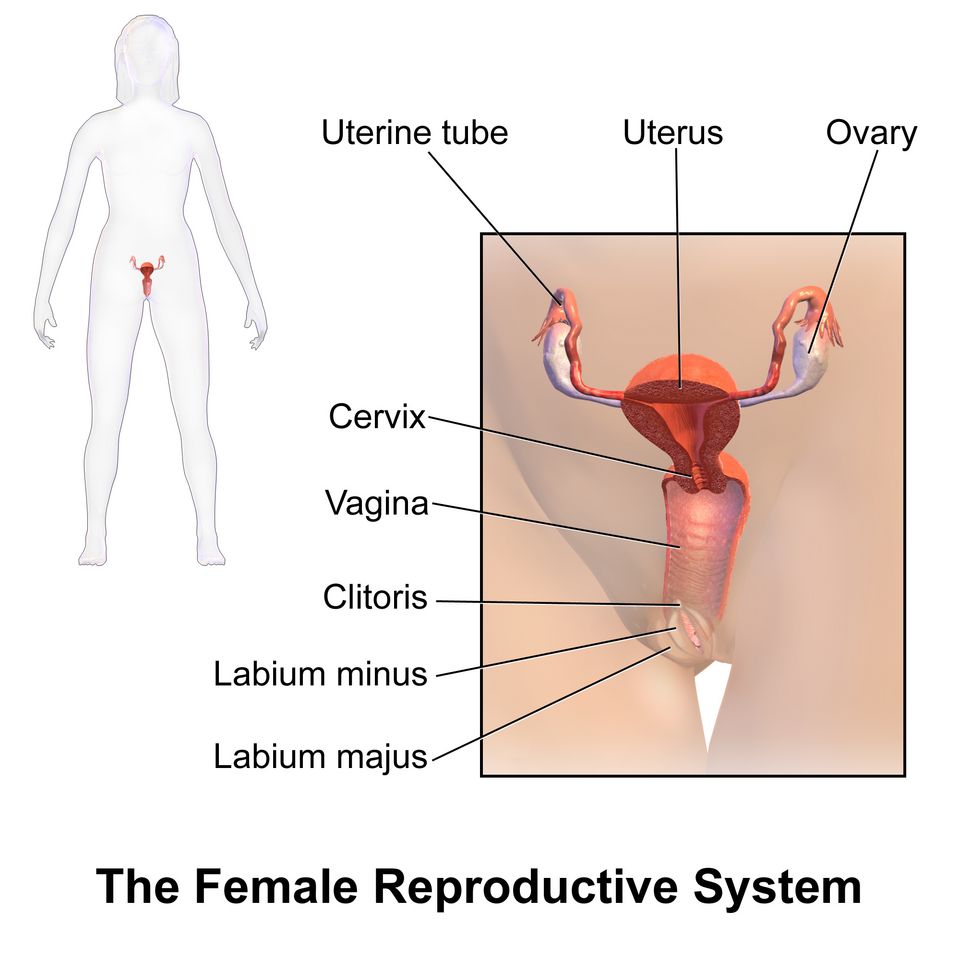
A place to make an egg and a place to grow a baby
The female system does something the male system does not. It makes the gamete, the egg. But it also gives a place where a fertilized egg can attach and grow for nine months.
The two ovaries are each about the size of an almond. They sit low in the pelvis. They hold the whole lifetime supply of eggs. About once a month, an ovary lets go of a ripe egg. This is called ovulation. A uterine (fallopian) tube reaches toward each ovary. Its end has a fringe of finger-like parts called fimbriae. They sweep the released egg into the tube. If fertilization happens, it is usually here, in the outer third of the tube.
The uterus and its layers
The tube carries the egg toward the uterus, or womb. This is a muscular, pear-shaped organ. It is built to hold a growing baby. Its wall has three layers you should know.
The inner layer is the endometrium. This lining thickens each month to receive an embryo. If no embryo arrives, the lining is shed as the monthly period. The thick middle layer is the myometrium. It is smooth muscle that squeezes hard during labor. The thin outer layer is the perimetrium. It is a smooth, moist covering. The lower neck of the uterus is the cervix. It opens into the vagina. The vagina is a muscular canal. It is the birth canal, and it receives sperm during sex.
| Organ | Function | Note |
|---|---|---|
| Ovary | Makes eggs and the hormones estrogen & progesterone | Holds all eggs from birth |
| Uterine (fallopian) tube | Carries the egg toward the uterus; where fertilization usually happens | Fimbriae sweep in the egg |
| Uterus | Holds and feeds the growing baby | Endometrium / myometrium / perimetrium |
| Cervix | Neck of the uterus; opens into the vagina | Opens wide in labor |
| Vagina | Birth canal; receives semen | Muscular and able to stretch |
The ovary is also a gland
It is easy to think of the ovary as just a place to store eggs. But it is also an endocrine organ, a gland that makes hormones. Each month, a cluster of cells forms around the ripening egg. This cluster is the follicle. It pumps out estrogen. After ovulation, the leftover follicle turns into the corpus luteum. The corpus luteum makes progesterone.
These two hormones drive the changes in the lining of the uterus. Working with the brain, they run the whole monthly cycle. You will meet it in Section 5. So the ovary has two jobs. It releases the egg, and it controls the tissue that will receive it.
Tap each part in the interactive to explore the female organs from the front.
- The ovaries store eggs. They are also glands that make estrogen and progesterone.
- The uterine tube catches the released egg with its fimbriae. Fertilization usually happens in its outer third.
- The wall of the uterus has three layers. The endometrium is the lining that is shed. The myometrium is the muscle for labor. The perimetrium is the outer cover.
- The cervix opens into the vagina, the birth canal.
Section 4Oogenesis
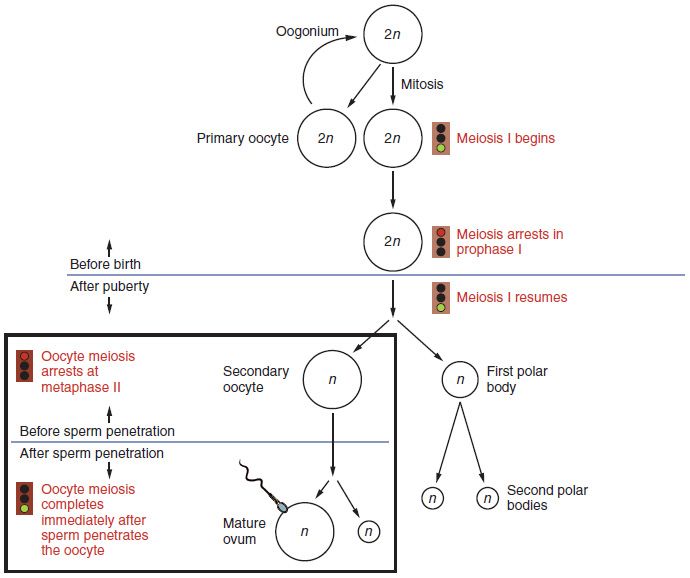
The same tool, used very differently
Egg making is called oogenesis. It uses the same meiosis as sperm making. But the female body runs it on a very different schedule, with a very different goal. The male makes four small sperm from one cell, and he does it without end. The female makes one large egg from one cell. She does it on a strict, once-a-month timetable.
Why the difference? It comes down to supplies. An egg must carry enough cytoplasm, food, and cell parts to start a new life. So the female body pours almost everything into a single egg.
Unequal divisions on purpose
Here is the twist. A primary oocyte is an early egg cell. When it finishes meiosis I, it does not split its cytoplasm evenly. It divides unequally. One daughter, the secondary oocyte, keeps nearly all the cytoplasm. The other becomes a tiny polar body. It gets almost nothing and later breaks down.
The same lopsided split happens again in meiosis II. But in humans, this second division only finishes if a sperm fertilizes the egg. In the end you get one working egg, called an ovum. You also get two or three polar bodies that will die off. One cell in, one useful egg out. It is the mirror image of the male's one in, four out.
| Feature | Oogenesis (egg) | Spermatogenesis (sperm) |
|---|---|---|
| Cells made from one starting cell | One egg (+ polar bodies) | Four sperm |
| How cytoplasm is split | Unequal; the egg keeps almost all of it | Equal |
| Timing | Starts before birth; one egg per cycle | Nonstop from puberty |
| Finishing meiosis II | Only if fertilized | Always finished |
| Lifetime total | About 400 eggs released | Trillions of sperm |
A process paused for decades
Oogenesis has the strangest timeline in the body. A female is born with all the eggs she will ever have. That is about one to two million primary oocytes. Before birth, they start meiosis I. Then they stop partway through and stay frozen. They wait like this for years.
Starting at puberty, one oocyte finishes meiosis I each month and is released. The rest keep waiting. So an egg released at age forty has been paused for four decades. This long wait helps explain why chromosome errors become more common as the mother gets older. Down syndrome is one example.
The supply shrinks over the years. By menopause, only about a thousand follicles are left. That is too few, and they respond too weakly, to keep the hormone cycle going. So the monthly cycles stop.
Step through the interactive. Watch the unequal divisions pack everything into one egg.
- Oogenesis makes one egg (plus polar bodies) from each starting cell. The cytoplasm is split unequally.
- All eggs start meiosis before birth and then pause. One finishes each cycle. Meiosis II finishes only at fertilization.
- A female is born with her lifetime egg supply. It drops to a very low level, about a thousand follicles, by menopause. Then the cycles stop.
- The long pause in meiosis helps explain why chromosome errors rise as the mother gets older.
Section 5The menstrual cycle
Two cycles running as one
The menstrual cycle lasts about 28 days. It is really two cycles running in step. One happens in the ovary, and one happens in the uterus. Four hormones run the show.
Two come from the pituitary gland, a small gland under the brain. They are follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The other two come from the ovary. They are estrogen and progesterone. The ovarian cycle tracks what happens to the egg and its follicle. The uterine cycle tracks the building and shedding of the lining. The two are timed so a fresh lining is ready just when an egg might arrive.
Follicular phase, ovulation, luteal phase
The cycle starts on day 1 with menstruation, the period. Last month's lining is shed. Next comes the follicular phase. FSH gets several follicles to grow. One takes the lead and pours out estrogen. Estrogen rebuilds the lining.
Rising estrogen then sets off a sudden jump in LH around day 14. This LH surge causes ovulation. The lead follicle bursts and lets go of its egg.
Next comes the luteal phase. The empty follicle becomes the corpus luteum. It makes progesterone. Progesterone keeps the lining thick and rich, ready in case an embryo arrives. If there is no pregnancy, the corpus luteum shrinks away. Progesterone and estrogen drop. With no hormones to hold it up, the lining is shed. Then the next cycle begins.
| Phase (days) | Main hormone | What is happening |
|---|---|---|
| Menstruation (1–5) | Estrogen and progesterone low; FSH rising | The old lining is shed while the next follicles start to grow |
| Follicular (1–13) | FSH, then estrogen | A follicle ripens; the lining rebuilds |
| Ovulation (~14) | LH surge | The follicle bursts; the egg is released |
| Luteal (15–28) | Progesterone | The corpus luteum makes the lining rich |
Feedback that flips
Here is a neat trick of this cycle. The same hormone can push in opposite ways, depending on timing. For most of the cycle, estrogen gives negative feedback. It quietly holds the pituitary back, like a brake.
But as the lead follicle ripens, estrogen climbs high and stays high. At that point the feedback flips to positive. Now high estrogen pushes the pituitary to release the LH surge. That surge causes ovulation. This is one of the few times the body uses positive feedback. As always, it is used to cause one big, one-time event. After ovulation, progesterone from the corpus luteum brings back negative feedback. Things calm down again.
Tap a phase in the interactive. See the hormones, the ovary, and the lining change together.
- Four hormones run the cycle. FSH and LH come from the pituitary. Estrogen and progesterone come from the ovary.
- The phases go menstruation → follicular → ovulation (LH surge, ~day 14) → luteal.
- Follicles make estrogen, which rebuilds the lining. The corpus luteum makes progesterone, which keeps the lining up.
- A high estrogen level flips to positive feedback. This sets off the LH surge that causes ovulation.
Section 6Meiosis
Why half is the whole point
We saved the engine for last. Every body cell you have is diploid. It has 46 chromosomes, the packages that hold your genes. They come in 23 pairs. One of each pair came from each of your parents.
What if a sperm with 46 chromosomes joined an egg with 46? The child would have 92. The number would double every generation. The body's answer is meiosis. This special division makes haploid gametes, with just 23 chromosomes each. When a haploid sperm meets a haploid egg, the full diploid set of 46 comes back. So the count stays the same, generation after generation. Cutting the number in half is not a side effect of making gametes. It is the reason meiosis exists.
Two divisions, not one
Meiosis gets to the haploid number in two divisions in a row. The DNA is copied only once, before the first. In meiosis I, matching chromosomes line up in pairs. These are called homologous pairs. The pairs are pulled apart. This is the step that cuts the number in half, from diploid to haploid.
Meiosis II looks a lot like ordinary mitosis. The two copies of each chromosome finally split apart. The end result is four haploid cells. That means four sperm, or one egg plus polar bodies. Compare this with mitosis, the normal division that builds and repairs the body. Mitosis is one division. It makes two identical diploid cells.
| Feature | Mitosis | Meiosis |
|---|---|---|
| Purpose | Growth and repair | Make gametes |
| Divisions | One | Two |
| Daughter cells | 2 | 4 |
| Chromosome number | Diploid (2n), no change | Cut in half to haploid (n) |
| Genes | Exact copies | Each one different |
Shuffling the deck
Meiosis does more than cut the number in half. It also reshuffles your genes, so no two gametes are alike. It does this in two ways.
In crossing over, paired chromosomes swap matching pieces during meiosis I. This mixes the versions you got from each parent. In independent assortment, each pair lines up and splits at random. So which grandparent's chromosome ends up in a gamete is a coin flip. And that flip happens 23 times over. Together these make millions of different gametes from one person. That is why brothers and sisters differ. It is also why sexual reproduction makes the variety that evolution acts on.
Sometimes a pair fails to split apart. This is called nondisjunction. Then a gamete ends up with the wrong number of chromosomes. This causes conditions such as trisomy 21, also called Down syndrome.
Step through both divisions in the interactive. Watch the chromosomes drop by half and the genes shuffle.
- Meiosis cuts the chromosome number in half, from diploid (46) to haploid (23). Then fertilization can bring back the full set.
- It uses two divisions. Meiosis I pulls apart homologous pairs; this is the halving step. Meiosis II splits the sister copies.
- Crossing over and independent assortment make every gamete different.
- In nondisjunction, a pair fails to split. This gives a gamete the wrong number of chromosomes.
The chapter in one breath
- The reproductive system is here to make a new person. That takes haploid gametes that join to bring back the full set of chromosomes.
- In males, sperm are made in the seminiferous tubules. They travel epididymis → ductus deferens → ejaculatory duct → urethra. Along the way they mix with fluid from the seminal vesicles, prostate, and bulbourethral glands.
- Spermatogenesis makes four sperm from each starting cell through equal divisions. It never stops, and it takes about 64–74 days.
- In females, the ovary stores eggs and makes hormones. The uterine tube catches the egg. The uterus (endometrium, myometrium, perimetrium) holds a pregnancy.
- Oogenesis makes one egg plus polar bodies through unequal divisions. It starts before birth. Meiosis II finishes only at fertilization.
- The menstrual cycle is run by FSH, LH, estrogen, and progesterone. Follicles make estrogen. An LH surge causes ovulation. The corpus luteum makes progesterone.
- Meiosis cuts the chromosomes in half in two divisions. Meiosis I reduces, and meiosis II divides. Crossing over plus independent assortment make every gamete different.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back when a word trips you up.
- Acrosome
- The cap full of enzymes on the head of a sperm. It helps the sperm get through the outer coat of the egg.
- Corpus luteum
- What the empty follicle becomes after ovulation. It makes progesterone to keep up the lining of the uterus.
- Diploid (2n)
- Having the full set of chromosomes. In humans that is 46, in 23 pairs. Body cells are diploid.
- Ductus (vas) deferens
- The muscular tube that pushes sperm from the epididymis toward the urethra. It is cut in a vasectomy.
- Endometrium
- The inner lining of the uterus. It thickens each cycle to receive an embryo. If none attaches, it is shed as the period.
- Epididymis
- The coiled tube on the back of the testis. Sperm grow up, learn to swim, and are stored here.
- Estrogen
- A hormone made mainly by the growing follicle in the ovary. It rebuilds the lining of the uterus and sets off the LH surge.
- Follicle
- The cluster of cells in the ovary around a growing egg. It makes estrogen and releases the egg at ovulation.
- FSH (follicle-stimulating hormone)
- A hormone from the pituitary. It makes follicles grow in the ovary and helps sperm making in the testis.
- Gamete
- A haploid sex cell, either a sperm or an egg. It joins with another gamete at fertilization.
- Haploid (n)
- Having half the set of chromosomes. In humans that is 23. Gametes are haploid.
- LH (luteinizing hormone)
- A hormone from the pituitary. Its surge in the middle of the cycle causes ovulation and forms the corpus luteum.
- Meiosis
- The two-step cell division that cuts the chromosome number in half to make gametes. It also shuffles genes.
- Menopause
- The lasting end of monthly cycles. It happens when too few follicles are left, and they respond too weakly, to keep the hormone cycle going. The supply gets very low, but not to zero.
- Nondisjunction
- When a chromosome pair fails to split apart in meiosis. The gamete gets the wrong number of chromosomes.
- Oogenesis
- The making of eggs. Unequal divisions make one ovum and two or three polar bodies.
- Ovulation
- The release of a ripe egg from the ovary. It is caused by the LH surge in the middle of the cycle.
- Polar body
- A small cell made by the unequal divisions of oogenesis. It gets little cytoplasm and breaks down.
- Progesterone
- The hormone made by the corpus luteum. It keeps the lining of the uterus thick and rich after ovulation.
- Semen
- The fluid that leaves the male body at ejaculation. It is sperm plus fluids from the seminal vesicles, prostate, and bulbourethral glands.
- Seminiferous tubules
- The coiled tubes inside the testis where sperm are made.
- Spermatogenesis
- The making of sperm. Equal divisions make four haploid sperm from one starting cell.
Check yourself
Development & Inheritance
Every human life starts as a single cell. It is no bigger than the period at the end of this sentence. Yet folded inside it is a full instruction book for building a person. This chapter follows that cell forward. First comes the exciting meeting of sperm and egg. Next comes a busy first week of cell division, as the new embryo digs into the uterus. Then three germ layers appear. These are sheets of cells that quietly split up the job of making every organ. After that comes the long stretch of fetal growth that ends in birth.
Then we turn the story around. We ask how the instruction book itself is passed on. These are the rules of inheritance. With a simple square grid, they let us predict the odds that a child will have brown eyes or a certain disease. It is the most packed-in wonder in all of body science, and it follows rules you can learn.
By the end of this chapter you can
- Describe the steps of fertilization. Start with the sperm crossing the egg's outer coats and end with the joining that forms a zygote. Explain how the egg stops more than one sperm from getting in.
- Trace the first week of growth through cleavage, the morula, and the blastocyst. Describe how and where implantation happens.
- Explain gastrulation. Name the three primary germ layers and the main tissues each one makes.
- Tell the embryonic period apart from the fetal period. Outline the key events of the three trimesters.
- Describe how the placenta is built and what it does. List the three stages of labor.
- Define allele, genotype, and phenotype. Compare dominant with recessive inheritance.
- Use a Punnett square to predict the genotype and phenotype ratios of children from two parents.
- Explain why two healthy parents can have a child with a recessive condition.
Section 1Fertilization
A race with one finisher
Fertilization is the joining of a sperm and an oocyte (egg). Together they make a new cell with its own unique set of genes. It usually does not happen in the uterus. Instead it happens high up in the uterine tube, in a wide part called the ampulla. It takes place within about a day of ovulation. That is because the released egg can only be fertilized for about 12 to 24 hours. Sperm live a few days at most.
Hundreds of millions of sperm are released, but the trip is harsh. Most are lost to the acid in the vagina or the mucus of the cervix. Many just take wrong turns. Only a few hundred reach the egg. On the way, the survivors go through capacitation. This is a last chemical change in the female tract. It gets their outer covers ready to join with the egg.
The egg they find is not bare. It is wrapped in a halo of follicle cells called the corona radiata. Under that is a thick shell of sugar-coated protein called the zona pellucida.
Breaking in: the acrosome reaction
To reach the egg's cell surface, a sperm must get through both coats. A cap called the acrosome sits over the sperm's head. It is a sac full of enzymes that digest things. When the sperm touches the zona pellucida, the acrosome bursts and spills its enzymes. This is the acrosome reaction. The enzymes dig a narrow tunnel through the shell.
It takes many sperm chipping away at the corona and zona to get through. So fertilization is a team effort, but it has only one winner. The first sperm to reach the egg's surface grabs onto receptors there. Then the outer covers of the two cells join. The sperm's nucleus, with its 23 chromosomes, slides into the egg.
| Barrier | What it is | How the sperm gets through |
|---|---|---|
| Corona radiata | Outer halo of granulosa (follicle) cells | Many sperm push and use enzymes to loosen the cells |
| Zona pellucida | Thick shell of sugar-coated protein around the egg | The acrosome reaction digests a path through it |
| Oocyte plasma membrane | The egg cell's own outer surface | The sperm grabs receptors; the two surfaces fuse |
One sperm only: the blocks to polyspermy
What if two sperm got in? This is called polyspermy. The embryo would have the wrong number of chromosomes, and it would die. So the egg has two safety locks. They snap shut the moment one sperm joins.
The fast block comes first. The electric charge across the egg's surface changes right away. This stops other sperm from grabbing on. The slow block, or cortical reaction, comes seconds later. Tiny sacs just under the egg's surface spill their contents into the zona pellucida. This hardens the zona into a wall no sperm can cross.
Only now does the egg finish its own last division (meiosis II). The two sets of 23 chromosomes, one from each parent, come together. This brings back the full human count of 46. The fertilized egg is now a single diploid cell called the zygote. Its sex was set at this exact moment. It depends on whether the winning sperm carried an X or a Y chromosome.
Step through the meeting of sperm and egg in the interactive below.
- Fertilization usually happens in the ampulla of the uterine tube. The egg can be fertilized for only about 12–24 hours.
- The sperm crosses the corona radiata and zona pellucida using the acrosome reaction. Then it joins with the egg's outer surface.
- A fast block (a change in electric charge) and a slow block (the cortical reaction that hardens the zona) stop polyspermy.
- The two nuclei join and bring back 46 chromosomes. This forms a diploid zygote. The sperm sets its sex.
Section 2The first week: cleavage & implantation
Cleavage: dividing without growing
Within about a day, the zygote starts to divide again and again by mitosis. These fast divisions are called cleavage. Here is the surprise. The whole ball does not get bigger. Each division splits the same cytoplasm into smaller and smaller cells. So the cluster stays about the size of the first egg. But the number of cells climbs: 2, then 4, then 8, then 16. These early cells are called blastomeres.
All this happens while the tiny embryo drifts down the uterine tube. Tiny hairs called cilia and waves of muscle push it toward the uterus. By about day 4 it is a solid ball of about 16 cells. It looks like a mulberry, so it is called the morula. That is Latin for "little mulberry."
From morula to blastocyst
Around day 5, fluid seeps into the center of the morula. It hollows the ball out into a sphere filled with fluid, called the blastocyst. This is the first time the embryo's cells take on different jobs. They split into two groups you need to know.
The outer shell of cells is the trophoblast. It will become the embryo's part of the placenta and the membranes around the baby. It is meant to be support tissue, not the baby. Pressed against one inner wall is the inner cell mass (embryoblast). This small group of cells will become the embryo itself. The fluid space between them is the blastocoel. In just a few days, the embryo has answered its first big question. Which cells build the child, and which build its life-support system?
| Day (about) | Stage | Where |
|---|---|---|
| 0 | Zygote (fertilized egg) | Ampulla of the uterine tube |
| 1–3 | Cleavage: 2-, 4-, 8-cell stages | Moving down the uterine tube |
| 4 | Morula (~16 cells) | Entering the uterus |
| 5 | Blastocyst (trophoblast + inner cell mass) | Floating free in the uterus |
| 6–10 | Implantation into the endometrium | Wall of the uterus |
Implantation and the pregnancy signal
Implantation is when the embryo digs into the wall of the uterus. First the blastocyst must "hatch." It breaks free of the leftover zona pellucida. Now its sticky trophoblast can touch the lining of the uterus. Around day 6 or 7, the trophoblast sticks to the endometrium, the lining, and starts to burrow in. Its cells release enzymes that eat into the lining. By about day 10 the embryo is fully buried.
Right away, the trophoblast starts making human chorionic gonadotropin (hCG). This hormone tells the corpus luteum in the ovary to keep making progesterone. That way the lining is not shed. This one hormone keeps the pregnancy from ending in a normal period. It is also exactly what a pregnancy test looks for.
Follow the zygote's first-week journey from division to implantation below.
- Cleavage splits the zygote into more and smaller cells, but the cluster does not grow. This makes the morula.
- The blastocyst has an outer trophoblast (future placenta) and an inner cell mass (future embryo). A fluid space, the blastocoel, sits between them.
- Implantation into the endometrium happens about days 6–10. First the blastocyst must hatch from the zona pellucida.
- The trophoblast makes hCG. This hormone keeps the pregnancy going, and pregnancy tests look for it.
Section 3The germ layers
Gastrulation: one sheet becomes three
Around the third week, the inner cell mass makes one of the most important moves in all of growth. It is called gastrulation. A groove called the primitive streak forms down the middle of the flat embryo. Cells from the top layer (the epiblast) stream toward it and dive under. They rearrange into three primary germ layers, three sheets of cells.
Your body has more than 200 kinds of cells. Every one of them comes from one of these three sheets. Laying down these layers in the right order and the right place is the base for every organ that follows.
Three layers, three destinies
The three germ layers split up the whole body among them. The outer layer is the ectoderm. It becomes the parts that face the world and sense it. That means the epidermis, the outer skin, and the whole nervous system.
The middle layer is the mesoderm. It becomes the bulk and machinery of the body. That means muscle, bone, blood, heart, blood vessels, and kidneys. The inner layer is the endoderm. It becomes the linings of the body's hollow tubes and the glands that grow off them. That means the lining of the gut and the airways, plus the liver and pancreas.
Here is an easy way to hold it. Ectoderm is the outside and the wiring. Endoderm is the innermost linings. Mesoderm is everything in the middle.
| Germ layer | Position | Main things it becomes |
|---|---|---|
| Ectoderm | Outer | Epidermis, hair, nails; the whole nervous system; parts of the eye |
| Mesoderm | Middle | Muscle; bone and cartilage; blood and heart; blood vessels; kidneys; dermis (deep skin) |
| Endoderm | Inner | Lining of the gut (GI tract) and airways; liver; pancreas |
Folding into a body: organogenesis
With the three layers in place, organogenesis begins. This is the actual building of organs. It goes on through the eighth week. The flat disc folds into a shape like a tube inside a tube. Each layer starts shaping the parts it was given.
One of the first and most important steps is when ectoderm folds into the neural tube. This tube will become the brain and spinal cord. If it does not close all the way, the result is a neural tube defect, such as spina bifida. The neural tube closes very early, often before a person even knows they are pregnant. So getting enough folic acid, a B vitamin, around the time of conception greatly lowers the risk.
Tap each of the three layers to see what it becomes in the interactive below.
- Gastrulation (week 3) forms three primary germ layers at the primitive streak.
- Ectoderm → skin and nervous system. Mesoderm → muscle, bone, blood, heart, kidney. Endoderm → linings of the gut and airways, liver, pancreas.
- Organogenesis builds the organs through week 8. The neural tube closes early, and closing well depends on enough folic acid.
Section 4Embryo to fetus: the timeline
The embryonic period versus the fetal period
Growth before birth is split into two named periods. The split comes at the end of week 8. From fertilization through week 8 is the embryonic period. In this time the germ layers form and every major organ is first laid down. From week 9 until birth is the fetal period. This time is mostly about growing and finishing organs that already exist.
This matters for health. Organs are being built in the embryonic weeks, so that is when they are easiest to harm. A teratogen is a drug, infection, or other thing that disrupts growth before birth. It does its worst harm in weeks 3 to 8, while body parts are forming. The same exposure later, in the fetal period, may cause little or no damage to body shape.
Three trimesters
A full-term pregnancy lasts about 38 weeks counted from fertilization. Doctors usually count from the last menstrual period (LMP) instead. Counted that way, it lasts about 40 weeks. The pregnancy is split into three roughly equal parts called trimesters.
The first trimester is where the action is. Implantation, gastrulation, and organ building all happen here. The embryo also becomes a fetus. By the end, the fetus looks clearly human, but it is only about the size of a plum.
The second trimester is a time of fast growth and movement. The mother usually feels the first kicks, called "quickening." The fetus grows toward the edge of viability, the point where it could live outside the uterus. That is about 23 to 24 weeks when doctors count from the LMP. It is about 21 to 22 weeks after fertilization. (Always check how weeks are counted. Doctors count from the LMP. Embryology counts from fertilization. The two differ by two weeks.)
The third trimester is mostly about gaining weight and final growth. The lungs and brain mature most of all. This gets the fetus ready to live outside the uterus.
| Trimester | Weeks (from fertilization) | Main events |
|---|---|---|
| First | 1–12 | Implantation, germ layers, organ building; the embryo becomes a fetus at week 9 |
| Second | 13–27 | Fast growth; first movements felt; nears viability (~21–22 weeks after fertilization; ~23–24 weeks counted from the LMP) |
| Third | 28–38 | Big weight gain; lungs and brain mature; ready for birth |
Tap through the stages of the earliest journey in the interactive below.
- The embryonic period (weeks 1–8) builds the organs. The fetal period (week 9 to birth) grows and finishes them.
- Teratogens do the most harm to body shape in weeks 3–8, when organs are forming.
- Pregnancy is about 38 weeks from fertilization, split into three trimesters. Viability starts around 23–24 weeks counted from the LMP (~21–22 weeks after fertilization).
Section 5Pregnancy & birth
The placenta: a shared border organ
The placenta is a short-term organ. It is built together from the embryo's tissue (which comes from the trophoblast) and the mother's endometrium. It is the lifeline for the whole pregnancy. Finger-like chorionic villi reach out from the baby's side into pools of the mother's blood. This makes a huge surface for trading materials.
Across that thin barrier, O₂ and food pass from mother to fetus. CO₂ and wastes pass the other way. Yet the two bloodstreams normally never mix. This is key. The placenta also becomes a strong hormone maker. It takes over from the corpus luteum and makes the progesterone and estrogen that keep the pregnancy going. The fetus is tied to the placenta by the umbilical cord. It floats inside the amnion, a sac of fluid that cushions it.
A body remade for pregnancy
Carrying a fetus changes almost every system in the mother's body. Her blood volume rises by about 30–50 percent to supply the placenta. Her heart pumps more blood each minute. The growing uterus crowds the diaphragm and bladder. This changes her breathing and makes her need to pee more often.
Hormones loosen ligaments, including those of the pelvis, to get ready for birth. They also shift her metabolism to put the fetus's fuel first. These are normal changes that work together. But they also explain why pregnancy puts stress on problems like heart disease. It is also why doctors watch blood pressure and blood sugar so closely.
Labor: birth in three stages
Near the end of pregnancy, a shift in the balance of hormones starts labor. Once it begins, a classic positive feedback loop drives it. The baby's head pushes on the cervix. This causes the release of oxytocin. Oxytocin makes the uterus squeeze harder. That pushes the head harder against the cervix, and the loop repeats. The cycle keeps building on itself. It only ends when the baby is born. Labor happens in three stages.
| Stage | Name | What happens |
|---|---|---|
| 1 | Dilation | The longest stage. Squeezes of the uterus thin (efface) and open the cervix all the way (~10 cm) |
| 2 | Expulsion | Strong squeezes and the mother's pushing move the baby out through the birth canal |
| 3 | Placental | The uterus squeezes out the placenta (the "afterbirth"), then clamps down to limit bleeding |
Step through the placenta and the three stages of birth in the interactive below.
- The placenta trades O₂, CO₂, food, and wastes without mixing the mother's and baby's blood. It also makes pregnancy hormones.
- Pregnancy brings big changes. Blood volume rises 30–50%, the heart pumps more, and belly organs get pushed aside.
- Labor is driven by oxytocin positive feedback. It has three stages: dilation → expulsion → placental.
Section 6Inheritance
Two copies of every gene
You get one set of chromosomes from each parent. So you carry two copies of nearly every gene, one from your mother and one from your father. The different versions of a gene are called alleles. For a gene with two alleles, a person can be homozygous, with two matching alleles. Or they can be heterozygous, with two different ones.
The pair of alleles a person carries is their genotype. The trait you can see is their phenotype. Examples are eye color, blood type, or whether a disease shows up. All of inheritance is about the link between these two. How does the genotype you cannot see make the phenotype you can?
Dominant and recessive
When the two alleles differ, they do not always count the same. A dominant allele hides the effect of a recessive one. So one copy is enough to show its trait. A recessive allele only shows its trait when both copies are recessive. By custom, the dominant allele gets a capital letter. The recessive one gets a small letter.
Take the example from the interactive. B = brown eyes (dominant) and b = blue (recessive). The genotypes BB and Bb both give brown eyes. Only bb gives blue. This is why a recessive trait can seem to "skip" generations. People with one copy, called carriers, can pass it on quietly for years. It shows up again only when two carriers each pass the recessive allele to the same child.
| Genotype | Name | Phenotype (B = brown, b = blue) |
|---|---|---|
| BB | Homozygous dominant | Brown eyes |
| Bb | Heterozygous (carrier) | Brown eyes |
| bb | Homozygous recessive | Blue eyes |
Predicting the odds: the Punnett square
A Punnett square is a simple grid. It predicts the chance of each genotype in the children. You list one parent's possible alleles across the top. You list the other parent's down the side. Then you fill each box by combining them.
Cross two brown-eyed carriers (Bb × Bb). The four boxes come out 1 BB : 2 Bb : 1 bb. That is a 3:1 ratio of brown to blue. So each child has a 25 percent chance of blue eyes, even though both parents have brown eyes. Read these as chances, not promises. A 1-in-4 chance starts fresh with every pregnancy, just like flipping a coin. Four children could all have brown eyes, or two could have blue.
Not every trait follows this neat dominant and recessive pattern. Some alleles are codominant, meaning both show, as in type AB blood. Genes on the X chromosome make special sex-linked patterns. But the two-allele Punnett square is the base that everything else builds on.
Set the two parents and watch the ratios change in the interactive below.
- You carry two alleles of most genes. Your genotype is the allele pair. Your phenotype is the trait you can see.
- A dominant allele shows with one copy. A recessive allele shows only when both copies are recessive.
- A Punnett square predicts the ratios in children (for example, Bb × Bb → 3:1). The results are chances that start fresh with each pregnancy.
- Two heterozygous carriers can have an affected child. This explains recessive diseases that skip generations.
The chapter in one breath
- Fertilization in the uterine tube joins sperm and egg into a diploid zygote. Fast and slow blocks stop polyspermy. The sperm sets the child's sex.
- Cleavage divides the zygote into a morula and then a blastocyst (trophoblast + inner cell mass). The blastocyst implants in the endometrium and makes hCG.
- Gastrulation forms three germ layers. Ectoderm makes skin and nerves. Mesoderm makes muscle, bone, blood, and kidney. Endoderm makes the linings of the gut and airways, the liver, and the pancreas.
- The embryonic period (weeks 1–8) builds organs and is most at risk from teratogens. The fetal period grows them. Pregnancy has three trimesters (~38 weeks in all).
- The placenta trades gases and food without mixing blood, and it makes pregnancy hormones. Labor is oxytocin positive feedback in three stages: dilation, expulsion, placental.
- The genotype (allele pair) makes the phenotype (the trait you see). Dominant alleles hide recessive ones.
- A Punnett square predicts the chances for children. Two carriers can have a child with a recessive condition.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back when a word trips you up.
- Allele
- One of the different versions of a gene. You carry two alleles of most genes, one from each parent.
- Blastocyst
- The early hollow ball of cells, filled with fluid, that implants in the uterus. It has an outer trophoblast and an inner cell mass.
- Cleavage
- The fast cell divisions after fertilization. They make more cells, but the embryo as a whole does not get bigger.
- Dominant allele
- An allele that shows its trait with just one copy. It hides any recessive allele. It is written with a capital letter.
- Ectoderm
- The outer germ layer. It makes the epidermis and the whole nervous system.
- Endoderm
- The inner germ layer. It makes the linings of the gut and airways, plus the liver and pancreas.
- Fertilization
- The joining of a sperm and an oocyte to form a diploid zygote. It usually happens in the ampulla of the uterine tube.
- Gastrulation
- The reshaping of the embryo around week 3. It forms the three primary germ layers at the primitive streak.
- Genotype
- The exact pair of alleles a person carries for a gene.
- Germ layer
- One of the three main sheets of cells in the embryo: ectoderm, mesoderm, and endoderm. All tissues grow from them.
- Heterozygous
- Having two different alleles of a gene (for example, Bb).
- Homozygous
- Having two matching alleles of a gene (for example, BB or bb).
- Human chorionic gonadotropin (hCG)
- The hormone made by the trophoblast. It keeps the corpus luteum, and so the pregnancy, going. Pregnancy tests look for it.
- Implantation
- When the blastocyst buries itself in the endometrium, the lining of the uterus. It happens about days 6–10 after fertilization.
- Mesoderm
- The middle germ layer. It makes muscle, bone, blood, the heart and blood vessels, and the kidneys.
- Morula
- The solid ball of about 16 cells made by cleavage. It looks like a mulberry and comes before the blastocyst.
- Phenotype
- The trait you can see that comes from a genotype. The environment can also shape it.
- Placenta
- The short-term organ built from the baby's and the mother's tissue. It trades gases, food, and wastes and makes pregnancy hormones.
- Punnett square
- A grid that predicts the chance of each genotype in the children of two parents.
- Recessive allele
- An allele whose trait shows only when both copies are recessive. It is written with a small letter.
- Trophoblast
- The outer layer of cells of the blastocyst. It forms the embryo's part of the placenta and makes hCG.
- Zygote
- The single diploid cell formed at fertilization. It carries the full set of 46 chromosomes.