The Cardiovascular System: The Heart
Behind your breastbone is a muscle about the size of your fist. It squeezes about once a second, and it has never taken a break. Over a lifetime it will beat more than two and a half billion times. It will move enough blood to fill a small lake. In this chapter, we open up that pump. You will see how the heart is built as two pumps in one. You will follow one drop of blood on its full loop through the lungs and the body. You will watch the four valves keep blood moving forward. And you will follow the tiny electrical spark the heart makes for itself. A machine can read that spark right off the skin. The reading is called an ECG.
By the end of this chapter you can
- Find the heart in the mediastinum, the space between the lungs. Name the layers of its wall and the sac around it. Explain why the left ventricle is the thickest chamber.
- Name the four chambers and the great vessels, the big tubes attached to the heart. Say which ones carry blood rich in oxygen and which carry blood poor in oxygen.
- Trace blood flow through the heart in order. Tell the pulmonary loop (to the lungs) from the systemic loop (to the body).
- Name the four valves and say where each one sits. Explain how chordae tendineae and pressure keep blood flowing one way.
- Describe the conduction system, the heart's wiring, from the SA node to the Purkinje fibers. Explain why the AV node delay matters.
- Break one heartbeat into the steps of the cardiac cycle. Say what makes the “lub-dub” heart sounds.
- Match each wave of the ECG (P, QRS, and T) to the electrical event it records.
- Work out cardiac output from heart rate and stroke volume. Predict how it will change.
Section 1The heart as a double pump
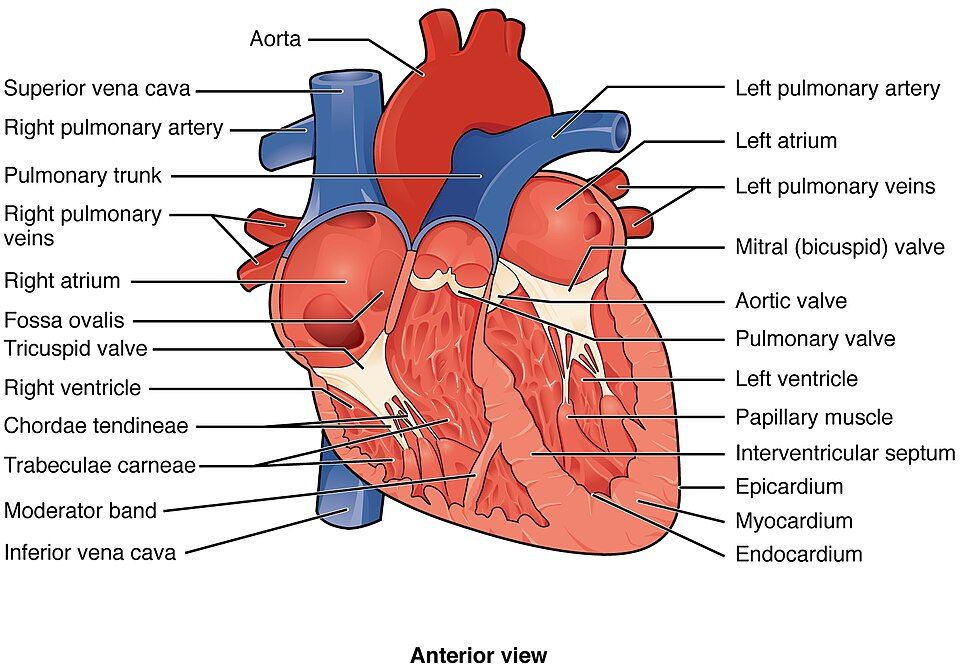
A fist-sized pump in the middle of the chest
The heart sits in the mediastinum, the space between your two lungs. It rests on the diaphragm, the big breathing muscle under your lungs. It is tilted, so about two-thirds of it lies to the left of your body's midline. The broad top, where the big vessels attach, is the base. The blunt tip points down and to the left. That tip is the apex. It is the spot where you can feel your heartbeat against your chest.
A tough sac with two walls wraps around the heart. This sac is the pericardium. Its outer layer, the fibrous pericardium, holds the heart in place. It also keeps the heart from overfilling. Inside that is the serous pericardium, which has two thin layers. It makes a slippery fluid that fills the pericardial cavity, the thin space around the heart. This fluid lets the beating heart glide without rubbing. Sometimes this space fills with fluid or blood and squeezes the heart. That is called cardiac tamponade, and it is a true emergency.
Two pumps, four chambers
Here is the most useful idea in this chapter. The heart is really two pumps bolted together. They sit side by side and work in perfect step. The right heart takes in blood low in oxygen coming back from the body. It pushes that blood a short way to the lungs. The left heart takes in fresh blood, full of oxygen, coming back from the lungs. It sends that blood out to the whole rest of the body.
A solid wall of muscle, the septum, keeps the two sides from mixing. Each pump has two chambers. On top is a thin-walled atrium that receives blood. Below is a thick-walled ventricle that pumps blood out. Blood always moves the same way: atrium → ventricle → out an artery.
| Chamber | Gets blood from | Sends blood to |
|---|---|---|
| Right atrium | The body, through the superior & inferior venae cavae (the two biggest veins) | Right ventricle |
| Right ventricle | Right atrium | The lungs, through the pulmonary trunk & arteries |
| Left atrium | The lungs, through the four pulmonary veins | Left ventricle |
| Left ventricle | Left atrium | The whole body, through the aorta |
Three layers, and a heart that feeds itself
The heart wall has three layers. The inner layer is the endocardium. It is a smooth lining that joins up with the lining of the blood vessels. So blood never touches a rough surface. The thick middle layer is the myocardium. This is the heart muscle that does the pumping. It is much thicker on the left side. The outer layer is the epicardium. It is the inner layer of the serous pericardium, the one stuck to the heart.
Look at the figure. See how the left ventricle wall is much thicker than the right one? The left side must make about five times as much pressure. It has to push blood all the way around the body. The right side only has to reach the lungs, which are close by.
All that hard-working muscle needs its own blood supply. The coronary arteries bring it. They branch off the aorta. If one gets blocked, the muscle past the block starves and dies. That is a heart attack. Its medical name is a myocardial infarction.
Tap through the chambers, vessels, and wall layers in the activity below.
- The heart lies in the mediastinum. It is wrapped in the pericardial sac. Fluid in the sac lets it beat without rubbing.
- It is two pumps in one. The right heart serves the lungs. The left heart serves the body. The septum keeps them apart.
- Atria receive, and ventricles pump out. The wall has three layers: endocardium, myocardium, and epicardium. The left ventricle is thickest because it faces the highest pressure.
- The coronary arteries feed the heart muscle. A blocked one causes a heart attack, or myocardial infarction.
Section 2Blood flow through the heart
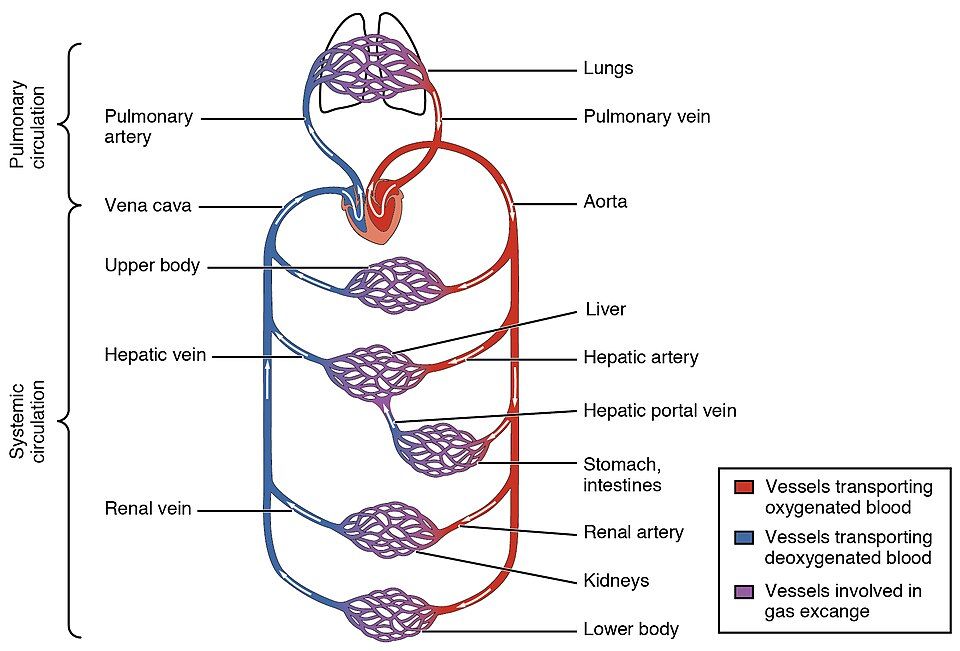
One drop, one full loop
Let's follow one drop of blood all the way around. It comes back from the body low in oxygen. It empties into the right atrium through the superior and inferior venae cavae. These are the two biggest veins. Next it drops through the tricuspid valve into the right ventricle. The right ventricle squeezes it through the pulmonary valve. From there it goes into the pulmonary trunk and on to the lungs.
In the lungs, it gives off carbon dioxide and picks up fresh oxygen. Now it is bright red. It flows back through the pulmonary veins into the left atrium. It passes the mitral valve into the strong left ventricle. Then it is pushed through the aortic valve into the aorta. From there it starts its trip around the body again.
| Step | Structure | Blood here is |
|---|---|---|
| 1 | Venae cavae → right atrium | Low in oxygen |
| 2 | Tricuspid valve → right ventricle | Low in oxygen |
| 3 | Pulmonary valve → pulmonary arteries → lungs | Low in oxygen (as it arrives) |
| 4 | Pulmonary veins → left atrium | Rich in oxygen |
| 5 | Mitral valve → left ventricle | Rich in oxygen |
| 6 | Aortic valve → aorta → body | Rich in oxygen |
Two circuits, run in series
That one loop is really two loops joined end to end. The pulmonary circuit goes from the right heart to the lungs and back. Its only job is to swap gases. The systemic circuit goes from the left heart out to every other tissue and back. That means the brain, gut, kidneys, muscles, and the rest.
The two loops are linked in series, one after the other. So each drop must pass through both. This means the two ventricles must pump the exact same amount of blood over time. Say the right side pumped a bit more than the left for a long time. Blood would back up in the lungs. If the left side pumped more, blood would back up in the body. That is why heart failure on one side slowly drags down the other side too.
The great exception
Here is a rule to learn by heart. Arteries carry blood away from the heart. Veins carry blood back toward it. Notice that the rule says nothing about oxygen. In most places, arteries happen to carry blood rich in oxygen. Veins usually carry blood low in oxygen. But the pulmonary vessels flip that.
The pulmonary arteries carry blood low in oxygen. It is going away from the heart, toward the lungs. The pulmonary veins carry blood rich in oxygen. It is coming back toward the heart. These vessels show that the real rule is about direction, not color.
Play or step one drop of blood through the whole loop in the activity.
- The forward path is: venae cavae → RA → tricuspid → RV → pulmonary valve → lungs → pulmonary veins → LA → mitral → LV → aortic valve → aorta.
- The pulmonary circuit (right heart ↔ lungs) and the systemic circuit (left heart ↔ body) run in series. So both ventricles move the same amount of blood.
- Arteries lead away, and veins lead back. The rule is about direction. The pulmonary vessels are the exception for oxygen.
Section 3The four one-way valves
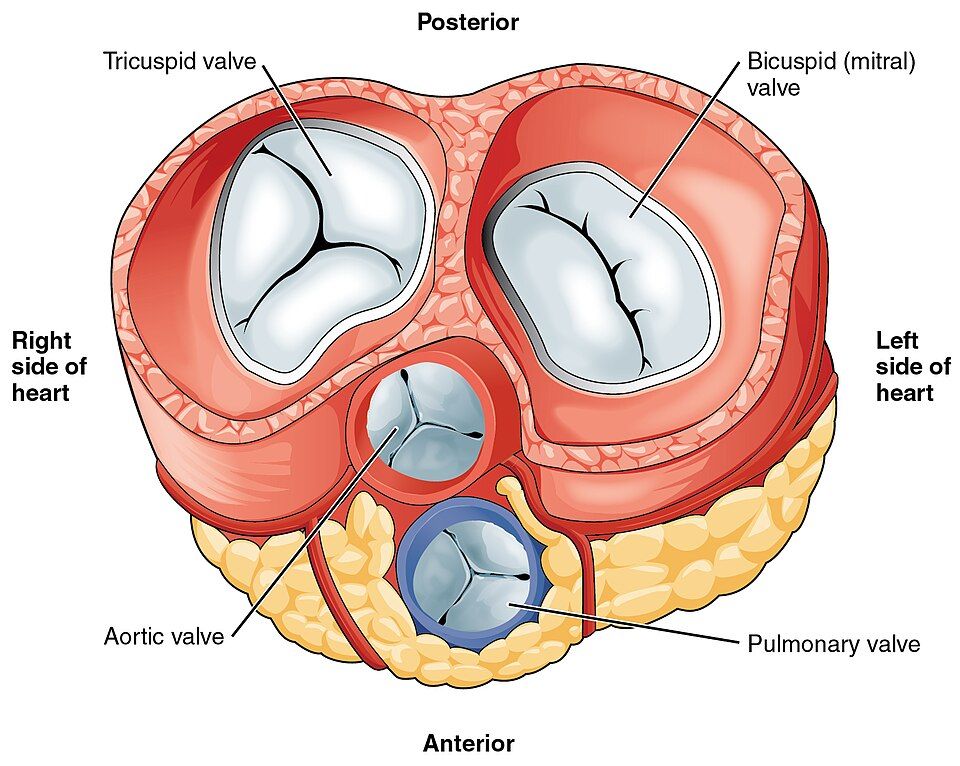
Four doors that only open one way
A pump is only as good as its valves. The heart has four. Each one is a flap door. It opens when blood pushes forward. It slams shut when blood pushes back.
Two of them are the atrioventricular (AV) valves. They sit between each atrium and the ventricle below it. The tricuspid valve is on the right side and has three flaps, or cusps. The mitral valve, also called the bicuspid valve, is on the left side and has two cusps. The other two are the semilunar valves. They guard the exits where the big arteries leave. The pulmonary valve sits at the opening of the pulmonary trunk. The aortic valve sits at the opening of the aorta. Together, they make sure blood can only go forward with each squeeze.
| Valve | Type | Location | Open when |
|---|---|---|---|
| Tricuspid | AV | Right atrium → right ventricle | Ventricles relaxed (filling) |
| Mitral (bicuspid) | AV | Left atrium → left ventricle | Ventricles relaxed (filling) |
| Pulmonary | Semilunar | Right ventricle → pulmonary trunk | Ventricles squeezing (pumping out) |
| Aortic | Semilunar | Left ventricle → aorta | Ventricles squeezing (pumping out) |
What holds them shut
The two types of valves stop backflow in different ways. When the ventricles squeeze hard, the pressure could push the AV valve flaps up into the atria. To stop this, each flap is tied down by tough strings. These are the chordae tendineae, or “heart strings.” They attach to small bumps of muscle on the ventricle floor, called papillary muscles.
The papillary muscles tighten just before the squeeze. The strings then hold the flaps like the ropes on a parachute. The flaps can close flat, but they cannot flip inside out. The semilunar valves need no strings. Each has three cup-shaped pockets. After the squeeze, some blood tries to fall back. The pockets catch it, and the weight snaps them shut.
When valves go wrong
Valves can fail in two ways, and the words are worth knowing. A stenotic valve is stiff and narrow. It will not open all the way. So the heart must strain to push blood through a smaller hole. A regurgitant valve is leaky. It is also called an insufficient valve. It will not close all the way, so blood sloshes backward with each beat.
Both problems make blood swirl in a rough way. You can hear this swirling with a stethoscope. The sound is called a murmur. The normal, healthy “lub-dub” is just the sound of valves snapping shut. That leads us to the cardiac cycle.
Tap each valve to watch it open and close in the activity.
- Two AV valves sit between the atria and ventricles: the tricuspid on the right and the mitral (bicuspid) on the left. Two semilunar valves, the pulmonary and aortic, guard the artery exits.
- Chordae tendineae and papillary muscles hold the AV flaps. This keeps them from flipping back during the squeeze.
- A valve can fail by stenosis (it won’t open) or regurgitation (it won’t close). Both cause murmurs. The normal S1/S2 sounds are valves snapping shut.
Section 4The conduction system
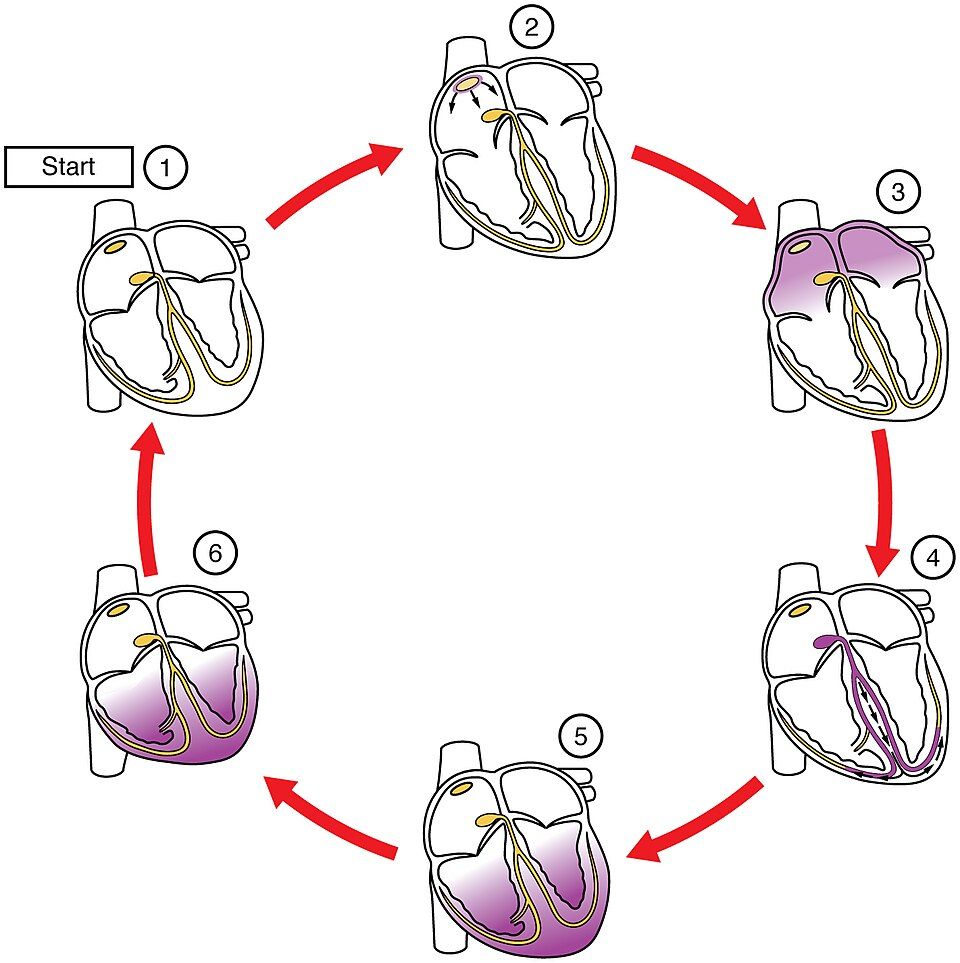
A heart that writes its own rhythm
Your arm muscles wait for the brain to tell them to move. The heart does not. A small group of special cells can fire an electrical signal all on their own, again and again. This is called autorhythmicity, which means “self-rhythm.”
The fastest of these cells form the sinoatrial (SA) node. It sits in the wall of the right atrium. It fires about 60 to 100 times a minute. It sets the pace for all the other cells. That is why the SA node is called the heart’s pacemaker. If you cut every nerve to the heart, it would keep right on beating. The nerves only speed it up or slow it down, as you will see.
The path of the spark
The signal spreads in a set order. That way the chambers squeeze in the right sequence: atria first, then ventricles. It starts at the SA node and sweeps across both atria. This makes them squeeze and top off the ventricles. Next it reaches the atrioventricular (AV) node. This node is the only electrical doorway between the atria and the ventricles. Here the signal pauses on purpose for about a tenth of a second.
From the AV node, the signal races down the AV bundle, also called the bundle of His. It splits into the right and left bundle branches, which run along the septum. Then it fans out through the Purkinje fibers into the ventricle walls. The ventricles squeeze from the bottom up, starting at the apex. This pushes blood toward the exits, like squeezing a tube of toothpaste from the bottom.
| Part | Job | Rate it fires on its own |
|---|---|---|
| SA node | Pacemaker. Starts each beat and fires the atria. | 60–100 / min |
| AV node | Gateway to the ventricles. Delays the signal. | 40–60 / min |
| AV bundle & branches | Carry the signal down the septum | — |
| Purkinje fibers | Spread the signal through the ventricle walls | 20–40 / min |
Why the pause, and who controls the tempo
The delay at the AV node is not a flaw. In fact, it is key. It gives the atria just enough time to finish emptying into the ventricles. Only then do the ventricles squeeze. Without the pause, all four chambers would squeeze at once. Then the heart would pump much less blood.
The heart also has built-in backups. If the SA node stops working, the AV node can take over. It fires at a slower 40 to 60 beats a minute. The Purkinje fibers can take over too, but even more slowly. This safety net keeps a failing heart beating, just too slowly.
The autonomic nervous system is the heart’s speed dial. This is the part of your nervous system that runs without your control. Sympathetic nerves speed up the SA node and make each squeeze stronger. They act during fear or exercise. The parasympathetic vagus nerve slows the heart back down when you rest.
Follow the spark from the SA node all the way down in the activity.
- The heart is autorhythmic. It makes its own beat. The SA node is the pacemaker. It fires 60–100 times a minute.
- The path is SA node → AV node → AV bundle → bundle branches → Purkinje fibers. So the atria squeeze before the ventricles.
- The AV node delay lets the atria finish filling the ventricles. Slower backup pacemakers take over if the SA node fails.
- Sympathetic nerves speed up the heart. Parasympathetic (vagus) nerves slow it down.
Section 5The cardiac cycle
Squeeze and rest, over and over
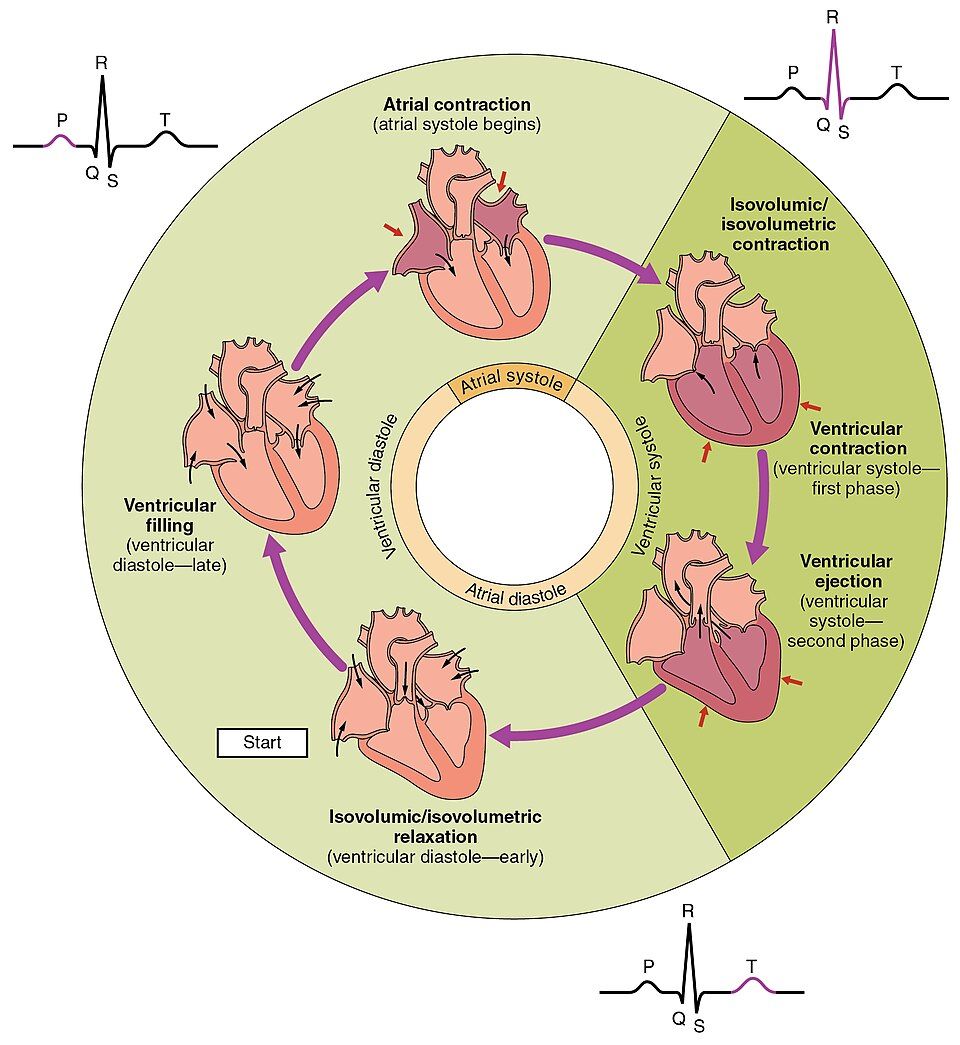
One heartbeat switches between two states, over and over. Systole is the squeeze. A chamber tightens to push blood out. Diastole is the rest. A chamber loosens to fill back up. At rest, your heart beats about 75 times a minute. At that pace, one full cycle takes about 0.8 seconds.
Here is an important fact. The heart spends more of that time resting than squeezing. That rest is not laziness. It is when the ventricles refill. It is also the only time the coronary arteries can push blood into the thick heart muscle. If the heart beats too fast, it cuts the rest time short. That means less filling and less blood for the heart muscle.
The phases, in order
Walk around the wheel in the figure, and the order makes sense. First comes atrial systole. The atria give a gentle squeeze. This tops off the ventricles, which are already mostly full.
Next comes ventricular systole, which has two parts. First is isovolumetric contraction. “Isovolumetric” means “same volume.” All four valves are shut. Pressure builds, but no blood moves. Then comes ventricular ejection. The semilunar valves pop open, and blood rushes into the arteries.
Last comes ventricular diastole, which also has two parts. First is isovolumetric relaxation, when all the valves are shut again. Then comes ventricular filling. The AV valves open, and blood pours in. Most of it flows in on its own, before the atria even squeeze.
| Phase | What happens | AV valves | Semilunar valves |
|---|---|---|---|
| Atrial systole | Atria squeeze and add the last 20–30% of filling | Open | Closed |
| Isovolumetric contraction | Ventricles tighten. Pressure builds, but no blood leaves. | Closed | Closed |
| Ventricular ejection | Ventricles push blood into the arteries | Closed | Open |
| Isovolumetric relaxation | Ventricles relax. Pressure falls, but no blood enters. | Closed | Closed |
| Ventricular filling | Blood flows into the ventricles on its own | Open | Closed |
Lub-dub, and the numbers that matter
The two heart sounds come from valves closing, not opening. S1 is the low “lub.” It is the AV valves snapping shut as the ventricles start to squeeze. S2 is the sharper “dub.” It is the semilunar valves snapping shut as the ventricles start to relax. Between the two sounds, the heart is pumping blood out. After S2, it is filling.
A few numbers sum it all up. The amount of blood in a ventricle when it is done filling is the end-diastolic volume (EDV). The amount left after it pumps is the end-systolic volume (ESV). The amount actually pumped out in one beat is the stroke volume. You find it by taking EDV − ESV. Now multiply stroke volume by heart rate. That gives you cardiac output. This is how many liters of blood the heart moves each minute. At rest, it is about 5 L.
Step through each phase and hear the lub-dub in the activity.
- Systole is the squeeze, and diastole is the rest. At rest, one cycle takes about 0.8 s. Most of that time is diastole.
- The phases go in this order: atrial systole → isovolumetric contraction → ejection → isovolumetric relaxation → filling.
- S1 (“lub”) is the AV valves closing. S2 (“dub”) is the semilunar valves closing.
- Stroke volume = EDV − ESV. Cardiac output = heart rate × stroke volume. At rest, that is about 5 L/min.
Section 6The ECG
Reading the heart’s electricity off the skin
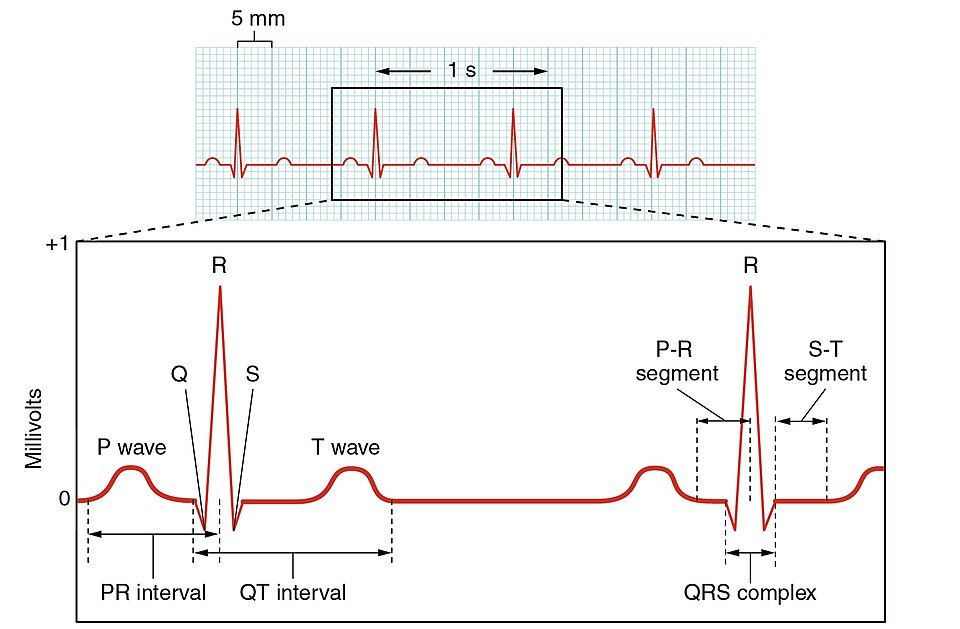
Each time the heart fires, a wave of electrical change spreads through it. This firing is called depolarization. The wave is strong enough to reach the skin. Small sensors stuck to the skin can pick it up. When you plot that signal over time, you get an electrocardiogram, or ECG (also written EKG).
The ECG is one of the most useful tests in medicine. It is painless and cheap. It does not record the heartbeat itself. It records the electrical events that set off the heartbeat. So each bump on the tracing lines up with a step in the wiring you just learned. Learn to read three simple bumps, and the whole picture opens up.
P, QRS, and T
The tracing repeats three main shapes. The small P wave shows atrial depolarization. This is the SA node’s signal spreading across the atria, just before they squeeze. The tall, spiky QRS complex shows ventricular depolarization. It is big and sharp because the ventricles have so much muscle.
The atria also reset, or repolarize, at this time. But that signal is hidden inside the QRS, so it never gets its own wave. The rounded T wave shows ventricular repolarization. This is when the ventricles reset their electrical charge so they can relax and fill again. Remember, the electrical firing is what starts the squeeze. So on the tracing, the electrical wave always comes a moment before the squeeze.
| Feature | Electrical event | What the heart does |
|---|---|---|
| P wave | Atrial depolarization | Atria squeeze |
| PR interval | SA node fires, and the signal passes through the AV-node delay | Signal waits at the AV node |
| QRS complex | Ventricular depolarization | Ventricles squeeze |
| T wave | Ventricular repolarization | Ventricles relax |
Intervals, rate, and trouble
The flat parts between the waves tell you as much as the waves do. The PR interval runs from the start of the P wave to the start of the QRS. It covers the atria firing plus that key pause at the AV node. If it gets too long, the person has a heart block. The QRS duration tells you how fast the ventricles are being fired. The QT interval covers the whole span of the ventricles’ electrical activity.
You can even read the heart rate right off the paper. The tracing moves at a fixed speed. So the space between two QRS peaks tells you the beats per minute. A heart rate that is too fast is tachycardia. One that is too slow is bradycardia.
Sometimes the line is a messy, shaking squiggle with no real QRS at all. This is ventricular fibrillation. The ventricles are just twitching, and no blood is moving. A defibrillator is built to shock this rhythm back into order.
Tap each wave to link it to its step in the heart’s wiring in the activity.
- An ECG records the heart’s electrical events from the skin. Each bump matches a step in the heart’s wiring.
- P = atrial depolarization. QRS = ventricular depolarization. T = ventricular repolarization. The electrical wave comes just before the squeeze.
- The PR interval holds the AV-node delay. A long one is a sign of heart block.
- Rhythm names: tachycardia (fast), bradycardia (slow), and ventricular fibrillation (messy, with no blood pumped). ST elevation is a warning sign of a heart attack.
The chapter in one breath
- The heart is a fist-sized double pump in the mediastinum. It is wrapped in a pericardial sac. The left ventricle is thickest because it faces the highest pressure.
- On each side, blood flows atrium → ventricle → artery. The right heart serves the pulmonary circuit (lungs). The left heart serves the systemic circuit (body). The two loops run in series.
- Arteries lead away, and veins lead back. The rule is about direction. The pulmonary vessels flip the usual oxygen pattern.
- Four one-way valves keep blood moving forward. Two are AV valves (tricuspid, mitral), and two are semilunar (pulmonary, aortic). Chordae tendineae hold the AV flaps in place.
- The heart is autorhythmic. The SA node sets the pace. The AV node delays the signal. The Purkinje fibers carry it into the ventricles.
- One beat is made of systole and diastole. S1/S2 are the sounds of valves closing. Cardiac output = heart rate × stroke volume.
- The ECG reads the heart’s electrical events from the skin: P (atria), QRS (ventricles firing), and T (ventricles resetting).
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back any time a word trips you up.
- Aorta
- The largest artery in the body. It carries blood rich in oxygen out of the left ventricle to start the trip around the body.
- Atrioventricular (AV) node
- The electrical gateway between the atria and ventricles. It holds the signal for about a tenth of a second so the atria can finish filling the ventricles.
- Atrioventricular (AV) valve
- A valve between an atrium and the ventricle below it. The tricuspid is on the right, and the mitral (bicuspid) is on the left. Chordae tendineae hold them shut.
- Atrium
- An upper, thin-walled chamber of the heart that receives blood. The right atrium gets blood from the body. The left gets blood from the lungs.
- Cardiac cycle
- One full heartbeat. It is made of the chambers squeezing (systole) and relaxing (diastole).
- Cardiac output
- How much blood a ventricle pumps each minute. It equals heart rate times stroke volume, about 5 L/min at rest.
- Chordae tendineae
- Tough cords that tie the AV valve flaps to the papillary muscles. They keep the flaps from flipping backward when the heart squeezes.
- Diastole
- The resting phase of a heart chamber, when it fills with blood.
- Electrocardiogram (ECG)
- A recording of the heart’s electrical activity taken from the skin. Its P, QRS, and T waves match steps in the heart’s wiring.
- Endocardium
- The smooth inner lining of the heart. It joins up with the lining of the blood vessels.
- Myocardium
- The thick middle layer of heart muscle that does the pumping. It is thickest in the left ventricle.
- Pericardium
- The sac with two walls around the heart. Its inner layers make fluid so the beating heart moves without rubbing.
- Pulmonary circuit
- The loop from the right heart to the lungs and back. Here blood picks up oxygen and drops off carbon dioxide.
- Purkinje fibers
- Fast fibers that spread the electrical signal through the ventricle walls. They make the ventricles squeeze from the apex up.
- QRS complex
- The tall, spiky part of the ECG. It shows ventricular depolarization, just before the ventricles squeeze.
- Semilunar valve
- A cup-shaped valve at a ventricle’s exit into a big artery. The pulmonary and aortic valves are this type. They snap shut to stop backflow.
- Sinoatrial (SA) node
- The heart’s natural pacemaker, in the wall of the right atrium. It fires 60–100 times a minute and sets the rhythm.
- Stroke volume
- The amount of blood a ventricle pumps out in one beat. It is the end-diastolic volume minus the end-systolic volume.
- Systemic circuit
- The loop from the left heart out to all the body’s tissues and back to the right heart.
- Systole
- The squeezing phase of a heart chamber, when it pumps blood out.
- Ventricle
- A lower, thick-walled pumping chamber of the heart. The right one pumps blood to the lungs. The left one pumps it to the whole body.